Trace gut boundaries, arterial territories, gastric orientation, and midgut return to distinguish normal development from congenital obstruction.
How can an early gut tube explain an adult artery, a vagal trunk, or a newborn's obstruction? Start with three relationships: origin predicts territory, growth changes position, and fixation determines what can twist. By the end, you should be able to locate developmental boundaries, trace stomach and midgut orientation, and distinguish a problem of return from a problem of rotation, lumen formation, or an embryonic connection.
Does 90 degrees mean the same thing everywhere? No. Name the organ, axis, and viewpoint before using an angle. The stomach changes orientation around its own longitudinal axis. The midgut develops around the superior mesenteric artery, abbreviated SMA. Their angles describe different relationships, not successive turns of one structure. [2][4]
During gastrulation, three germ layers form. Folding during approximately the fourth postfertilization week incorporates part of the yolk-sac lining into the gut tube. Endoderm provides most gastrointestinal epithelium and glandular epithelium; surrounding splanchnic mesoderm supplies connective tissue and smooth muscle. Neural crest cells provide enteric neurons. Thus, an endoderm-derived intestinal lining does not mean that every tissue in its wall is endodermal. [1][3]
Keep the reference frame attached to the angle
Structure
Standard teaching model
Useful consequence
StructureStomach
Standard teaching modelAbout 90 degrees clockwise around its longitudinal axis, viewed from the cranial end
Useful consequenceOriginal left surface is anterior; original right surface is posterior
StructureMidgut
Standard teaching model270 degrees counterclockwise around the SMA, viewed from the front
Useful consequenceSmall bowel returns within the developing colonic frame; later fixation establishes a broad attachment
Try the comparison: A diagram shows an artery at the center and a loop that temporarily extends into the umbilical cord. Decide which row applies before reading any angle. The loop and arterial axis identify midgut development; gastric rotation does not use the SMA as its axis. Now reverse the task: if a surgeon describes an anterior vagal trunk, use the stomach row rather than the midgut row.
These are orientation models, not a claim that the entire intestine spins like a rigid wheel. Human embryonic reconstructions show complex, unequal growth and changing relationships. The conventional angles remain useful for learning adult arrangement, but they do not substitute for the actual anatomy of a patient with malrotation. [6]
Find the landmark before naming the region
Is the entire duodenum foregut, and is the entire colon hindgut? Neither. The boundary diagram places three transitions along one continuous route. Trace the route distally and say what changes at each landmark: gut division at the papilla, gut division within the transverse colon, then epithelial germ-layer origin at the pectinate line.
Trace the tract downward. The major papilla separates foregut from midgut, the transverse-colon division separates midgut from hindgut, and the pectinate line distinguishes endoderm-derived upper anal canal from ectoderm-derived lower anal canal. Celiac, SMA, and IMA label the corresponding arterial territories; positions are schematic. [2][5]
The major duodenal papilla
The major papilla lies in the descending duodenum, where bile and the main pancreatic duct usually enter through the hepatopancreatic ampulla. The conventional foregut-midgut boundary is at this level: proximal duodenum is foregut-derived; duodenum distal to duct entry is midgut-derived. The papilla is a visible mucosal landmark, whereas the ampulla is the associated ductal structure. They describe the same regional transition, not identical structures. [2][3]
For example, compare two surgical samples on opposite sides of duct entry. A sample immediately proximal maps to foregut and one distal maps to midgut. Calling both samples simply "duodenum" loses the information needed to assign their developmental territories.
Nearby organs do not all share one origin
The pancreas develops from dorsal and ventral endodermal buds. The ventral bud contributes the uncinate process and part of the head; the dorsal bud contributes the rest of the head, body, and tail. Thus, proximity to the duodenum does not mean that the whole pancreas arose from one bud. The spleen is different: it develops from mesenchyme in the dorsal mesogastrium, not gut endoderm. Its celiac-derived splenic artery does not make its tissue an endodermal foregut derivative. [14][15]
The transverse colon
Midgut forms the distal duodenum, jejunum, ileum, cecum, appendix, ascending colon, and proximal two thirds of the transverse colon. Hindgut forms the distal one third of the transverse colon, descending colon, sigmoid colon, rectum, and upper anal canal. A lesion in the terminal ileum and one in the ascending colon therefore share a developmental region despite being in different named bowel divisions. [2][5]
Apply the map: Trace from ascending colon through transverse colon toward sigmoid colon. The embryologic region changes before you reach the descending colon. The two-thirds/one-third convention is a developmental guide, not an endoscopically visible seam or a guarantee of an exact perfusion border in every patient.
The pectinate line
The upper anal canal lining arises from hindgut endoderm. The lower lining arises from the ectodermal proctodeum. Their traditional boundary is the pectinate, or dentate, line. Unlike the two preceding landmarks, this transition changes epithelial germ-layer origin. It also helps organize differences in sensation: the lower canal has somatic sensation through inferior rectal branches of the pudendal nerve; the upper canal has visceral innervation. This does not mean that every painful anorectal disorder must arise below the line. [5]
Predict the effect of touching a superficial lesion below this line. Precisely localized pain is compatible with somatic sensation. Transfer that reasoning to a specimen: lower anal epithelium and adjacent intestinal smooth muscle do not have to share a germ-layer origin.
Use origin to predict vessels and parasympathetic supply
Can an artery name identify a developmental territory? Usually, provided you distinguish a major arterial root from the entire adult collateral network. The abdominal foregut corresponds primarily to the celiac trunk, midgut to the SMA, and hindgut to the inferior mesenteric artery, abbreviated IMA. The celiac rule should not be extended to the pharynx or the whole esophagus merely because they are foregut derivatives. [1][4]
Abdominal foregut
Stomach and proximal duodenal territory: mainly celiac branches; parasympathetic supply from the vagus.
Midgut
Distal duodenum through proximal two thirds of transverse colon: SMA branches; parasympathetic supply from the vagus.
Hindgut
Distal one third of transverse colon through upper anal canal: IMA territory, with additional pelvic arterial contributions distally; parasympathetic supply from pelvic splanchnic nerves, S2 to S4.
The nerve distinction is specific: pelvic splanchnic nerves are parasympathetic, whereas sacral splanchnic nerves are sympathetic. The vagus supplies foregut and midgut, so crossing the foregut-midgut boundary changes the principal arterial root without changing the named parasympathetic source. Crossing the midgut-hindgut boundary changes both. [11]
Compare two resections: One includes ileum and ascending colon; the other includes descending and sigmoid colon. Predict the shared arterial root within each specimen, then the parasympathetic origin. The first pair maps to SMA and vagus; the second to IMA and pelvic splanchnic nerves. For a new mixed specimen crossing the distal transverse colon, do not assign one developmental territory to every segment.
Adult vessels communicate. SMA and IMA colonic territories connect through the marginal arterial system, and rectal blood supply includes internal iliac contributions in addition to the superior rectal continuation of the IMA. A developmental map therefore predicts a principal origin, not certain tissue death after one vessel is interrupted. Perfusion depends on collateral adequacy, obstruction site, and systemic conditions. [8]
Follow the original gastric surface
Why is a left-sided nerve found anteriorly? The stomach begins as a foregut dilation. Unequal growth enlarges its dorsal border more than its ventral border, producing the greater and lesser curvatures. Its longitudinal reorientation places the original left surface anteriorly and right surface posteriorly. The associated left and right vagal contributions follow these surfaces. [4]
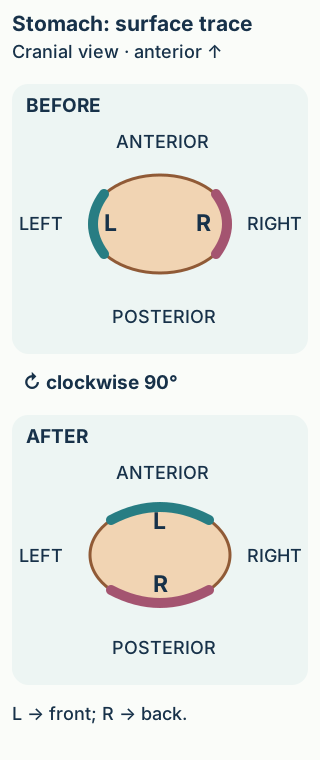
The paired cross-sections show the stomach from the cranial end, looking toward the feet. Use the patient-direction labels rather than assuming that the viewer's left is the patient's left. The anterior vagal trunk is predominantly derived from the left vagus, and the posterior trunk predominantly from the right. [4]
With the cranial view fixed, clockwise reorientation carries the left gastric surface toward the patient's anterior and the right surface toward posterior. [4]
Surface-tracing activity: Start at the marker labeled L in the first section. Trace the quarter-turn arrow without swapping the marker to the opposite wall. Where should L finish? Then independently trace R. The final diagram remains visible so that you can compare your prediction without opening anything.
Check the L marker
L finishes on the anterior surface. The surface retains its identity as its orientation changes; the left contribution therefore predominates in the anterior trunk.
Check the R marker
R finishes on the posterior surface. Reversing the rotation would reverse this prediction, which is why the viewpoint and direction matter.
The complete result is left to anterior, right to posterior. Looking from the opposite end reverses the apparent clockwise direction but does not change the final anatomical relationship. The familiar LARP reminder can confirm the answer after you derive it: Left Anterior, Right Posterior.
Now transfer the relationship to surgery. A trunk on the anterior distal esophagus is predominantly left-vagal in origin; a posterior trunk is predominantly right-vagal. Do not infer that midgut rotation determines either location. Later gastric tilting also changes the positions of the pyloric and cardiac regions, but the longitudinal rotation is the relationship needed for this nerve-localization task. [4]
Track growth, herniation, return, then fixation
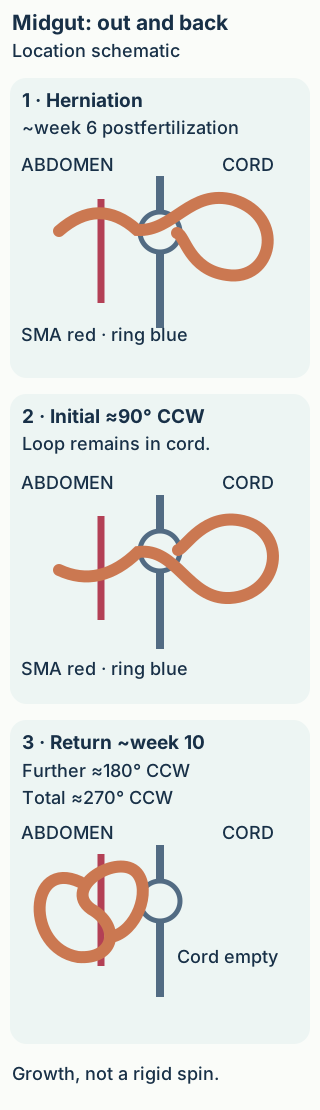
Does bowel in the umbilical cord always indicate a defect? No. Early growth briefly exceeds the space available in the embryonic abdomen. Around postfertilization week 6, the midgut loop physiologically herniates through the umbilical ring. The SMA supplies the loop, and the vitelline duct links its apex to the yolk sac. [2]
Unless explicitly stated otherwise, weeks here are counted from fertilization. Obstetric gestational age is conventionally about two weeks greater. The approximate embryology schedule is not an ultrasound diagnostic cutoff. Clinical interpretation needs the examination's dating convention and actual anatomy. [12]
In the standard anterior-view model, the loop first turns 90 degrees counterclockwise during herniation. Return around postfertilization week 10 contributes a further 180 degrees, giving 270 degrees total, not 270 additional degrees. The cranial limb forms distal duodenum, jejunum, and proximal ileum; the caudal limb forms remaining ileum and the midgut-derived colon. Small-bowel loops return before the cecal region. [2][3]
The cecum initially occupies a subhepatic position, then descends toward the right iliac fossa as growth continues. The mature attachment extends between the duodenojejunal region and ileocecal region, creating a broad mesenteric base. Return, rotation, descent, and fixation are related but are not synonyms. Bowel can be entirely inside the abdomen yet have an abnormal narrow attachment. [2][7]
Trace the timeline: In the three-state diagram, point to the umbilical ring, then the arterial axis. Compare early herniation, the initial turn, and the returned state. State what changes between the last two: location relative to the abdominal wall and the cumulative orientation. The artery remains the reference structure.
The wall and ring distinguish inside from outside; Captions use the conventional anterior-view 90 plus 180 degree account. Bowel returns around postfertilization week 10; unequal growth and fixation shape the final anatomy. [2][3][6]
Worked consequence: an early specimen with expected herniation is not equivalent to a newborn with persistent extra-abdominal viscera. Likewise, a later scan showing bowel inside the abdomen does not by itself establish normal rotation. Transfer the model by asking two separate questions of any new description: "Has the bowel returned?" and "Are its position and attachment normal?"
Organogenesis is concentrated in postfertilization weeks 3 through 8, while midgut return occurs later. Gastric remodeling and midgut growth overlap. Do not place all gastric rotation before all midgut herniation as if development were a strict list of isolated events. The sequence is a guide to relationships, with approximate timings. [1][4]
Ask which developmental process failed
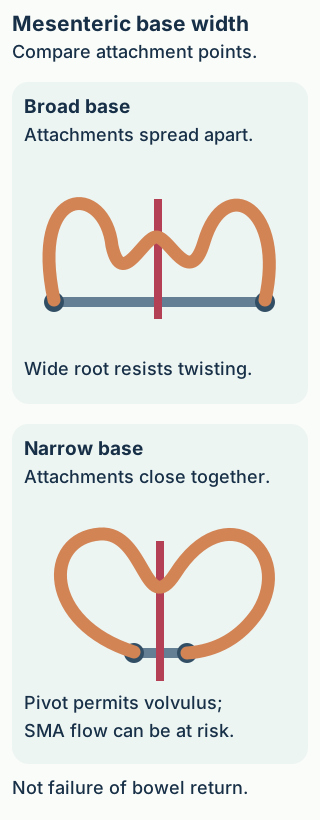
Can every congenital obstruction be explained by a lumen that failed to reopen? No. Compare the geometry of the mesenteric-base diagram with the intrinsic-obstruction examples below. An external band, a twist involving vessels, an epithelial obstruction, and a missing bowel segment require different explanations.
Rotation and fixation normally spread the mesenteric root. A narrow attachment can permit volvulus around the vessel and jeopardize perfusion. This is a fixation-related vascular risk, distinct from failure of bowel to return from the umbilical cord. [7]
Rotation and fixation are not the same as return
Malrotation can leave a narrow mesenteric base. The bowel can then twist around its vascular pedicle, causing volvulus with obstruction and potentially ischemia. Abnormal peritoneal attachments called Ladd bands can cross and compress the duodenum even without an active twist. Predict the consequence of widening the attachment: the bowel has less opportunity to rotate around a short, narrow pedicle. That geometric purpose is distinct from returning an external sac to the abdomen. [7]
A newborn with bilious vomiting needs urgent evaluation for obstruction, including malrotation with volvulus. A relatively quiet abdominal examination early in the illness does not exclude vascular danger. This is not a reason to observe until distension or bloody stool develops. [7]
Omphalocele is a midline abdominal-wall defect involving a sac containing viscera at the umbilical insertion, classically associated with failure of normal return. Gastroschisis is typically a separate defect to the right of the umbilicus with exposed bowel and no covering sac. It is not simply another name for failed rotation or failed physiological return; its causation is not fully established. A sac can rupture, so the full anatomy matters when the covering is absent. [9][10]
Separate the airway from the alimentary route
A newborn who coughs or chokes during feeding may have an abnormal tracheoesophageal communication. A catheter coiled in a blind upper esophageal pouch demonstrates esophageal atresia in this setting; gas in the stomach and bowel supports a distal tracheoesophageal fistula supplying air below the interruption. In an H-type fistula the esophagus remains continuous, so passage of a tube into the stomach does not exclude a fistula. Compare continuity of the feeding route with the separate question of an abnormal airway connection. [13]
Recanalization versus vascular continuity
Transient epithelial proliferation and reopening are relevant to the classic explanation of duodenal atresia. A newborn with a dilated stomach and proximal duodenum has a high obstruction, but that pattern alone does not prove one specific cause. A complete intrinsic duodenal obstruction with no distal gas supports atresia; additional anatomy distinguishes it from a band or twist. Obstruction distal to bile entry generally permits bilious vomiting. [1][2]
Many jejunal and ileal atresias instead reflect a fetal vascular disruption, with ischemic loss and resorption of bowel. If an operative specimen shows separated blind ends and a mesenteric gap, predict tissue loss rather than merely an intact tube with an obstructed lumen. These are standard explanatory patterns, not proof that every atresia has one cause. [1][3]
A connection that persists
The vitelline duct normally regresses during early development. Its remnants differ according to what remains patent. An ileal outpouching is a Meckel diverticulum, a true diverticulum containing all bowel-wall layers. A completely patent connection can discharge enteric contents through the umbilicus. Persistence of a middle segment can form a cyst, and a fibrous remnant can tether bowel or contribute to obstruction. [16] Ectopic gastric mucosa within a Meckel diverticulum can cause adjacent ulceration and bleeding. [2]
Transfer the distinction: Compare painless intestinal bleeding in a child with enteric fluid at a newborn's umbilicus. Both can involve the same embryonic duct, but they imply different residual anatomy. Next compare either with two disconnected ileal ends: persistence adds an abnormal connection, whereas vascular loss eliminates continuity.
Finish by describing the process before naming the condition: position and fixation, return through the abdominal wall, formation of an open lumen, maintenance of blood supply, or regression of a temporary connection. This preserves the causal distinctions that a list of diagnoses can obscure.
Apply the developmental relationships
Case 1
Show answer and explanations for case 1
A. Celiac trunk (Why this does not fit)
The celiac root fits duodenum proximal to bile entry, not the web downstream of it.
Reasoning steps for option A
Does a celiac origin match a web beyond the patent bile opening?
No. The papilla marks the foregut-midgut transition. The celiac trunk is the principal root proximally, whereas the postpapillary web lies chiefly in SMA territory.
Which root instead supplies this postpapillary duodenal segment?
The web lies in midgut duodenum, chiefly supplied from the superior mesenteric artery.
B. Inferior mesenteric artery (Why this does not fit)
The IMA supplies hindgut beginning in distal transverse colon, not postpapillary duodenum.
Reasoning steps for option B
Would an inferior mesenteric branch reach this postpapillary web as its principal root?
No. The inferior mesenteric artery serves hindgut from distal transverse colon onward.
What does bile entering upstream of the web imply about its arterial territory?
The obstruction is distal to the papilla in midgut duodenum, principally SMA territory.
C. Superior mesenteric artery (SMA) (Best answer)
Bile has entered the obstructed lumen, placing the web downstream of duct entry. That duodenal segment is midgut and chiefly belongs to the SMA root.
Reasoning steps for option C
What does the patent duct opening upstream of the web establish?
The web is postpapillary, beyond bile entry, within the midgut portion of the duodenum.
Why protect a branch of the superior mesenteric root here?
The SMA is the principal arterial root of this postpapillary midgut segment.
D. Internal iliac artery (Why this does not fit)
Pelvic contributions matter distally near rectum, not this duodenal web.
Reasoning steps for option D
Does the internal iliac artery supply the duodenal wall near this web?
No. Its pelvic branches contribute near the distal rectum rather than the postpapillary duodenum.
Which developmental territory does the web occupy instead?
Bile enters before the obstruction, locating it in midgut duodenum supplied chiefly by the SMA.
Takeaway: Bile has entered the obstructed lumen, placing the web downstream of duct entry. That duodenal segment is midgut and chiefly belongs to the SMA root.
A. P: arterial root changes; vagal source remains; Q: arterial root and parasympathetic source both change (Best answer)
The first interpretation fits: P crosses the foregut-midgut papillary boundary, changing celiac to SMA territory while both sides retain vagal parasympathetics. The second interpretation fits: Q crosses the midgut-hindgut colonic boundary, changing SMA to IMA territory and vagal to pelvic splanchnic supply.
Reasoning steps for option A
For this option, why does P change roots without changing vagal supply?
P straddles the papilla: foregut celiac becomes midgut SMA, while both ends retain vagal parasympathetics.
Why does Q change both named supplies?
From middle transverse to descending colon, Q crosses into hindgut: SMA becomes IMA and vagal becomes pelvic splanchnic.
Why does vagal input persist across P but change to pelvic splanchnic input across Q?
Yes. Only the papillary crossing retains the vagal source; the colonic crossing does not.
B. P: arterial root changes; vagal source remains; Q: arterial root changes; vagal source remains (Why this does not fit)
The first interpretation fits: P crosses the foregut-midgut papillary boundary, changing celiac to SMA territory while both sides retain vagal parasympathetics. The second interpretation fails: Q crosses the midgut-hindgut colonic boundary, changing SMA to IMA territory and vagal to pelvic splanchnic supply.
Reasoning steps for option B
Is this option right to keep vagal supply at both ends of P?
Yes. The papillary foregut-midgut boundary changes celiac to SMA but not vagal parasympathetics.
Can Q also retain vagal supply into the descending colon?
No. Its distal hindgut end receives pelvic splanchnic input, alongside the switch from SMA to IMA.
Which clause makes this proposed combination wrong?
The claim that vagal supply remains across Q ignores its midgut-hindgut neural transition.
C. P: arterial root and parasympathetic source both change; Q: arterial root and parasympathetic source both change (Why this does not fit)
The first interpretation fails: P crosses the foregut-midgut papillary boundary, changing celiac to SMA territory while both sides retain vagal parasympathetics. The second interpretation fits: Q crosses the midgut-hindgut colonic boundary, changing SMA to IMA territory and vagal to pelvic splanchnic supply.
Reasoning steps for option C
Does crossing the bile-duct opening replace vagal input in P?
No. Celiac to SMA changes at the papilla, but foregut and proximal midgut both receive vagal input.
Is the predicted double change across Q anatomically sound?
Yes. Descending colon is hindgut with IMA and pelvic splanchnic supply, unlike the proximal SMA and vagal end.
Which papillary neural prediction fails even though Q correctly changes to IMA and pelvic splanchnic supply?
It incorrectly changes the parasympathetic source in P despite correctly changing both supplies in Q.
D. P: arterial root and parasympathetic source both change; Q: arterial root changes; vagal source remains (Why this does not fit)
The first interpretation fails: P crosses the foregut-midgut papillary boundary, changing celiac to SMA territory while both sides retain vagal parasympathetics. The second interpretation fails: Q crosses the midgut-hindgut colonic boundary, changing SMA to IMA territory and vagal to pelvic splanchnic supply.
Reasoning steps for option D
Why is the proposed neural switch in P unsupported?
A to-and-beyond-papilla transition changes celiac to SMA, not the vagal source shared by both ends.
Why is retained vagal input in Q unsupported?
The descending-colon end lies beyond the midgut-hindgut boundary and receives pelvic splanchnics with IMA territory.
How does changing vagal input at P but preserving it at Q reverse the neural transitions?
P falsely changes parasympathetics; Q falsely preserves vagal input after entering hindgut.
Takeaway: P crosses the foregut-midgut papillary boundary, changing celiac to SMA territory while both sides retain vagal parasympathetics. Q crosses the midgut-hindgut colonic boundary, changing SMA to IMA territory and vagal to pelvic splanchnic supply.
A. A: proximal transverse colon also affected; B: proximal transverse colon also affected (Why this does not fit)
The first interpretation fits: Stomach and ileum share vagal input; their combined deficit with spared sigmoid localizes the affected system to vagal territories, including proximal transverse colon. The second interpretation fails: Descending colon and upper rectum share pelvic splanchnic input; spared ileum supports a hindgut distribution that includes distal transverse colon.
Reasoning steps for option A
Does A predict reduced responses in proximal rather than distal transverse colon?
Yes. Reduced stomach and ileum responses with spared sigmoid identify a vagal distribution extending into proximal transverse colon.
Would B also implicate proximal transverse colon?
No. Descending colon and upper rectum deficits with spared ileum identify pelvic splanchnic hindgut, including distal transverse colon.
Why does predicting a proximal transverse deficit for B conflict with its spared ileum?
Its B prediction places a pelvic splanchnic deficit on the vagally supplied proximal transverse segment.
B. A: distal transverse colon also affected; B: distal transverse colon also affected (Why this does not fit)
The first interpretation fails: Stomach and ileum share vagal input; their combined deficit with spared sigmoid localizes the affected system to vagal territories, including proximal transverse colon. The second interpretation fits: Descending colon and upper rectum share pelvic splanchnic input; spared ileum supports a hindgut distribution that includes distal transverse colon.
Reasoning steps for option B
Would A's vagal-pattern deficit predict reduced responses in distal transverse colon?
No. Distal transverse colon belongs to the pelvic splanchnic hindgut, spared by the vagal-pattern deficit in A.
Does B predict distal transverse-colon impairment?
Yes. Its descending-colon and upper-rectal deficit tracks pelvic splanchnic supply into distal transverse colon.
Why does the distal transverse prediction fit B but not A's stomach-and-ileum deficit?
Only B is localized correctly; A should implicate proximal rather than distal transverse colon.
C. A: distal transverse colon also affected; B: proximal transverse colon also affected (Why this does not fit)
The first interpretation fails: Stomach and ileum share vagal input; their combined deficit with spared sigmoid localizes the affected system to vagal territories, including proximal transverse colon. The second interpretation fails: Descending colon and upper rectum share pelvic splanchnic input; spared ileum supports a hindgut distribution that includes distal transverse colon.
Reasoning steps for option C
Why is distal transverse colon the wrong third site for A?
A has reduced stomach and ileum responses but spared sigmoid, identifying vagal input to proximal, not distal, transverse colon.
Why is proximal transverse colon the wrong third site for B?
B spares ileum but affects descending colon and upper rectum, identifying pelvic splanchnic hindgut distal to the colonic boundary.
Can either prediction survive the spared-site findings?
No. Both predictions reverse the vagal versus pelvic splanchnic sides of the transverse-colon boundary.
D. A: proximal transverse colon also affected; B: distal transverse colon also affected (Best answer)
The first interpretation fits: Stomach and ileum share vagal input; their combined deficit with spared sigmoid localizes the affected system to vagal territories, including proximal transverse colon. The second interpretation fits: Descending colon and upper rectum share pelvic splanchnic input; spared ileum supports a hindgut distribution that includes distal transverse colon.
Reasoning steps for option D
What reduction in responses should accompany A's vagal-pattern deficit in the proximal transverse colon?
Responses should also be reduced there because its vagal supply is shared with the affected stomach and ileum, unlike the spared sigmoid colon.
How should B's pelvic splanchnic deficit affect responses in the distal transverse colon?
Responses should also be reduced there because it shares pelvic splanchnic hindgut input with the affected descending colon and upper rectum.
How do A's spared sigmoid and B's spared ileum support the different transverse-colon predictions?
The predicted proximal vagal site for A and distal pelvic splanchnic site for B match their selective deficits.
Takeaway: Stomach and ileum share vagal input; their combined deficit with spared sigmoid localizes the affected system to vagal territories, including proximal transverse colon. Descending colon and upper rectum share pelvic splanchnic input; spared ileum supports a hindgut distribution that includes distal transverse colon.
A. A to B: celiac to SMA; anal lesion: endodermal (Why this does not fit)
The first interpretation fits: The catheter identifies the major papilla; the pyloric side is abdominal foregut and the jejunal side is midgut, so the principal roots change from celiac to SMA. The second interpretation fails: Precisely localized light-touch pain identifies the somatically supplied lower side of the anal boundary, whose lining is proctodeal ectoderm.
Reasoning steps for option A
Is the celiac-to-SMA transition across the catheter correct?
Yes. The bile-duct opening marks the papilla, separating proximal foregut celiac from distal midgut SMA territory.
Does sharply localized pain below the dentate boundary imply endodermal lining?
No. Somatic light-touch pain indicates the lower anal canal, lined by proctodeal ectoderm.
Why is endoderm the incorrect part of this celiac-to-SMA and anal-lining pair?
The arterial prediction fits, but endoderm mislabels the sensitive distal anal epithelium.
B. A to B: celiac to SMA; anal lesion lining: ectodermal (Best answer)
The first interpretation fits: The catheter identifies the major papilla; the pyloric side is abdominal foregut and the jejunal side is midgut, so the principal roots change from celiac to SMA. The second interpretation fits: Precisely localized light-touch pain identifies the somatically supplied lower side of the anal boundary, whose lining is proctodeal ectoderm.
Reasoning steps for option B
Why do samples A and B have different principal arterial roots?
A is pyloric to the papilla in celiac foregut; B is jejunal to it in SMA midgut.
What origin follows from localized touch pain at the anal lesion?
The lesion is below the dentate line in somatically innervated proctodeal ectoderm.
How do papillary position and localized anal touch pain support celiac-to-SMA supply and ectodermal lining?
Yes. It combines celiac-to-SMA across the papilla with ectoderm below the anal boundary.
C. A to B: celiac to celiac; anal lesion: ectodermal (Why this does not fit)
The first interpretation fails: The catheter identifies the major papilla; the pyloric side is abdominal foregut and the jejunal side is midgut, so the principal roots change from celiac to SMA. The second interpretation fits: Precisely localized light-touch pain identifies the somatically supplied lower side of the anal boundary, whose lining is proctodeal ectoderm.
Reasoning steps for option C
Can both duodenal samples remain in celiac territory?
No. B lies beyond the papilla toward jejunum and belongs to the SMA-supplied midgut.
Is ectoderm appropriate for the painful superficial anal lesion?
Yes. Sharp localized pain identifies the somatic lower anal compartment derived from proctodeal ectoderm.
Why does the ectoderm assignment fit while continued celiac supply to sample B does not?
Its anal origin fits, but retaining celiac supply for postpapillary B fails.
D. A to B: celiac to celiac; anal lesion: endodermal (Why this does not fit)
The first interpretation fails: The catheter identifies the major papilla; the pyloric side is abdominal foregut and the jejunal side is midgut, so the principal roots change from celiac to SMA. The second interpretation fails: Precisely localized light-touch pain identifies the somatically supplied lower side of the anal boundary, whose lining is proctodeal ectoderm.
Reasoning steps for option D
What rules out celiac supply at both ends of the duodenal specimen?
The catheter at the papilla puts distal B in SMA midgut, whereas proximal A is celiac foregut.
What rules out endoderm for this anal lesion?
Light-touch pain is sharply localized below the dentate boundary, where lining derives from ectoderm.
How do distal papillary position and somatic anal sensation refute both celiac-only supply and endoderm?
It misses both the arterial change at the papilla and the ectodermal origin of the lower anal lining.
Takeaway: The catheter identifies the major papilla; the pyloric side is abdominal foregut and the jejunal side is midgut, so the principal roots change from celiac to SMA. Precisely localized light-touch pain identifies the somatically supplied lower side of the anal boundary, whose lining is proctodeal ectoderm.
A. A lining: ectoderm; B deficient tissue: neural crest (Why this does not fit)
The first interpretation fits: Precisely localized contact pain and squamous lining at the distal outlet localize A to the somatically supplied lower anal compartment, whose lining derives from ectoderm. The second interpretation fails: Preserved epithelium and neurons with defective direct contraction and loss of contractile cells identify the smooth-muscle component, derived from mesoderm rather than neural crest.
Reasoning steps for option A
Why is ectoderm a good assignment for lining A?
Its distal squamous surface and localized contact pain indicate lower anal canal from proctodeal ectoderm.
Do preserved enteric neurons support neural crest as deficient tissue B?
No. Lost contractile spindle cells and weak direct contraction indicate smooth muscle from splanchnic mesoderm.
Why does preserved enteric innervation invalidate neural crest deficiency at B despite the correct ectoderm assignment at A?
B is deficient in mesoderm-derived muscle, not neural crest-derived enteric neurons.
B. A lining: endoderm; B deficient tissue: splanchnic mesoderm (Why this does not fit)
The first interpretation fails: Precisely localized contact pain and squamous lining at the distal outlet localize A to the somatically supplied lower anal compartment, whose lining derives from ectoderm. The second interpretation fits: Preserved epithelium and neurons with defective direct contraction and loss of contractile cells identify the smooth-muscle component, derived from mesoderm rather than neural crest.
Reasoning steps for option B
Does endoderm produce this painful distal squamous lining A?
No. Somatic sensitivity at the distal outlet points below the dentate boundary to ectoderm.
Does B fit splanchnic mesoderm-derived smooth muscle loss?
Yes. Circumferential contractile cells are depleted despite preserved neurons and epithelium.
Why does this pair fail despite identifying B?
It assigns endoderm to A even though its distal somatic squamous lining is ectodermal.
C. A lining: ectoderm; B deficient tissue: splanchnic mesoderm-derived (Best answer)
The first interpretation fits: Precisely localized contact pain and squamous lining at the distal outlet localize A to the somatically supplied lower anal compartment, whose lining derives from ectoderm. The second interpretation fits: Preserved epithelium and neurons with defective direct contraction and loss of contractile cells identify the smooth-muscle component, derived from mesoderm rather than neural crest.
Reasoning steps for option C
Which embryonic source forms the sensitive squamous lining at A?
The lower anal canal is proctodeal ectoderm, consistent with sharply localized contact pain.
Which tissue accounts for impaired direct contraction at B?
Deficient circumferential smooth muscle derives from splanchnic mesoderm; preserved neurons argue against neural crest loss.
How do A's painful distal lining and B's deficient contractile layer support ectoderm and splanchnic mesoderm?
Yes. A is ectodermal lining and B is mesodermal contractile bowel wall.
D. A lining: endoderm; B deficient tissue: neural crest (Why this does not fit)
The first interpretation fails: Precisely localized contact pain and squamous lining at the distal outlet localize A to the somatically supplied lower anal compartment, whose lining derives from ectoderm. The second interpretation fails: Preserved epithelium and neurons with defective direct contraction and loss of contractile cells identify the smooth-muscle component, derived from mesoderm rather than neural crest.
Reasoning steps for option D
Why does endoderm misidentify site A?
The painful stratified squamous distal anal lining belongs below the dentate boundary and derives from ectoderm.
Why does neural crest misidentify tissue B?
Enteric neurons are intact; missing contractile spindle cells are splanchnic mesoderm-derived smooth muscle.
What two preserved clues refute this pair?
Somatic sensation at A localizes ectodermal lining, while preserved neurons at B exclude neural crest as the missing component.
Takeaway: Precisely localized contact pain and squamous lining at the distal outlet localize A to the somatically supplied lower anal compartment, whose lining derives from ectoderm. Preserved epithelium and neurons with defective direct contraction and loss of contractile cells identify the smooth-muscle component, derived from mesoderm rather than neural crest.
A. marked wall: left-vagal contribution anteriorly; infant: band division establishes protection from vascular twisting (Why this does not fit)
The first interpretation fits: The original left gastric wall becomes anterior in the stated cranial-view rotation, carrying predominantly left-vagal contributions. The second interpretation fails: Completed return and division of one compressing band do not establish a broad root; closely spaced attachments leave a pedicle vulnerable to volvulus.
Reasoning steps for option A
Does the left-wall mark justify the anterior left-vagal claim?
Yes. The cranial-view clockwise gastric rotation takes original left wall and its predominant left vagal contribution anteriorly.
Does dividing one duodenal band eliminate twisting around the mesenteric pedicle?
No. The adjacent duodenojejunal and ileocecal attachments still form a narrow root despite complete bowel return.
Why is protection from vascular twisting the wrong second clause?
Band relief addresses compression but not the narrow attachment that permits volvulus.
B. marked wall: left-vagal contribution anteriorly; infant: vascular twisting remains possible (Best answer)
The first interpretation fits: The original left gastric wall becomes anterior in the stated cranial-view rotation, carrying predominantly left-vagal contributions. The second interpretation fits: Completed return and division of one compressing band do not establish a broad root; closely spaced attachments leave a pedicle vulnerable to volvulus.
Reasoning steps for option B
Where does the marked left gastric wall carry its vagal contribution?
Anteriorly, after the stated clockwise longitudinal rotation; left vagal contribution predominates there.
What hazard persists with close intestinal attachment points?
A narrow mesenteric base can twist around its vascular pedicle even after bowel returns and a band is divided.
Why can anterior left-vagal contribution and persistent narrow-root volvulus risk both be correct?
They distinguish gastric surface rotation from persistent malrotation-related volvulus risk.
C. marked wall: right-vagal contribution posteriorly; infant: vascular twisting remains possible (Why this does not fit)
The first interpretation fails: The original left gastric wall becomes anterior in the stated cranial-view rotation, carrying predominantly left-vagal contributions. The second interpretation fits: Completed return and division of one compressing band do not establish a broad root; closely spaced attachments leave a pedicle vulnerable to volvulus.
Reasoning steps for option C
Could a mark on the original left wall indicate right-vagal contribution posteriorly?
No. That describes the original right wall; the marked left wall and left vagal contribution rotate anteriorly.
Does the infant remain vulnerable to volvulus despite band division?
Yes. Close duodenojejunal and ileocecal attachments leave a narrow mesenteric root.
Why is posterior right-vagal labeling wrong even though persistent twisting risk is correctly predicted?
Its persistent-twisting warning fits, but its posterior right-vagal label reverses the marked gastric wall.
D. marked wall: right-vagal contribution posteriorly; infant: band division establishes protection from vascular twisting (Why this does not fit)
The first interpretation fails: The original left gastric wall becomes anterior in the stated cranial-view rotation, carrying predominantly left-vagal contributions. The second interpretation fails: Completed return and division of one compressing band do not establish a broad root; closely spaced attachments leave a pedicle vulnerable to volvulus.
Reasoning steps for option D
What is wrong with assigning the marked wall to posterior right vagus?
The original left wall becomes anterior and bears predominantly left-vagal contribution after the clockwise turn.
Can band division certify a broad stable mesenteric attachment?
No. Close attachment points persist and permit vascular-pedicle twisting despite intra-abdominal bowel.
How do the marked left wall and close intestinal attachments refute posterior right-vagal labeling and protection from twisting?
The gastric prediction swaps left for right, and the bowel prediction confuses band relief with correction of the narrow root.
Takeaway: The original left gastric wall becomes anterior in the stated cranial-view rotation, carrying predominantly left-vagal contributions. Completed return and division of one compressing band do not establish a broad root; closely spaced attachments leave a pedicle vulnerable to volvulus.
A. A: compatible with physiological herniation; B: compatible with physiological herniation (Why this does not fit)
The first interpretation fits: Eight gestational weeks corresponds to about six postfertilization weeks, when herniation through the ring is expected; this observation alone does not establish a defect. The second interpretation fails: Eighteen gestational weeks is well beyond the approximate return period, and the covered midline sac is abnormal rather than normal early herniation.
Reasoning steps for option A
Does A at eight gestational weeks fit physiological passage through the umbilical ring?
Yes. This is about six postfertilization weeks, when an umbilical loop without a separate wall defect is compatible with expected physiological herniation.
Can the same physiological label fit B at eighteen gestational weeks?
No. At about sixteen postfertilization weeks, return should have occurred; a persistent covered midline sac is abnormal.
Which time-dependent claim invalidates this option?
It extends normal early herniation to B long after the expected return interval.
B. A: already establishes failed return; B: abnormal persistent external viscera (Why this does not fit)
The first interpretation fails: Eight gestational weeks corresponds to about six postfertilization weeks, when herniation through the ring is expected; this observation alone does not establish a defect. The second interpretation fits: Eighteen gestational weeks is well beyond the approximate return period, and the covered midline sac is abnormal rather than normal early herniation.
Reasoning steps for option B
Can A already establish failed return at eight gestational weeks?
No. At about six postfertilization weeks temporary umbilical herniation is physiological.
Is B an abnormal persistence at eighteen gestational weeks?
Yes. B remains in a membrane-covered midline umbilical sac well after normal bowel return.
Why is declaring failed return premature for the eight-week examination but not for the eighteen-week sac?
The failed-return diagnosis for A ignores its early gestational age and normal route through the ring.
C. A: already establishes failed return; B: compatible with physiological herniation (Why this does not fit)
The first interpretation fails: Eight gestational weeks corresponds to about six postfertilization weeks, when herniation through the ring is expected; this observation alone does not establish a defect. The second interpretation fails: Eighteen gestational weeks is well beyond the approximate return period, and the covered midline sac is abnormal rather than normal early herniation.
Reasoning steps for option C
Why is failed return not established in examination A?
Eight gestational weeks is roughly six postfertilization weeks, within physiological umbilical herniation.
Why is physiological herniation not plausible in examination B?
Eighteen gestational weeks is roughly sixteen postfertilization weeks, too late for normal external bowel in a covered sac.
How do the eight-week and eighteen-week dates reverse the proposed abnormal-versus-physiological labels?
The option calls early expected herniation pathological and late persistent external viscera normal.
D. A: compatible with physiological herniation; B: abnormal persistent external viscera (Best answer)
The first interpretation fits: Eight gestational weeks corresponds to about six postfertilization weeks, when herniation through the ring is expected; this observation alone does not establish a defect. The second interpretation fits: Eighteen gestational weeks is well beyond the approximate return period, and the covered midline sac is abnormal rather than normal early herniation.
Reasoning steps for option D
How do date and route support the proposed interpretation of A?
At eight gestational weeks, about six after fertilization, bowel projecting through the umbilical ring without another defect is compatible with physiological herniation; this finding alone does not establish failed return.
How do date and sac support the proposed interpretation of B?
At eighteen gestational weeks, well after return, membrane-covered viscera at umbilical insertion are abnormal persistence.
Why does the return timetable permit early umbilical herniation in A but not the persistent covered sac in B?
Their gestational ages lie on opposite sides of the normal return period, despite both involving the umbilical region.
Takeaway: Eight gestational weeks corresponds to about six postfertilization weeks, when herniation through the ring is expected; this observation alone does not establish a defect. Eighteen gestational weeks is well beyond the approximate return period, and the covered midline sac is abnormal rather than normal early herniation.
A. Close a persistent umbilical sac (Why this does not fit)
No persistent extra-abdominal sac is described; closure does not correct the narrow base.
Reasoning steps for option A
Does closing an umbilical sac widen the short mesenteric root seen at exploration?
No sac remains outside the abdomen: all bowel has returned. Closing a sac would leave the narrow vascular pedicle and recurrent twisting untreated.
Which change to the narrow vascular attachment reduces the likelihood of another pedicle twist?
Broadening the mesenteric attachment increases the fixation span and reduces susceptibility to twisting; sac closure does not change that geometry.
B. Recanalize an intrinsic duodenal web (Why this does not fit)
The visible vascular-pedicle twist, not an intrinsic web, accounts for the obstruction.
Reasoning steps for option B
Could reopening a duodenal web release the segment seen rotating around its vessels?
An intrinsic web occludes a fixed duodenal lumen, whereas this segment is visibly twisting around a narrow mesenteric pedicle.
What finding redirects treatment away from luminal recanalization?
The short, narrow attachment is the rotational axis; widening it treats the recurrent volvulus mechanism, unlike opening a web.
C. Broaden the mesenteric attachment (Best answer)
Complete intra-abdominal return does not establish normal fixation. Widening the narrow attachment reduces the tendency to twist around the pedicle.
Reasoning steps for option C
Why can returned bowel still undergo volvulus around its vascular pedicle?
Return into the abdomen and mesenteric fixation are separate events. The narrow root leaves a short axis around which bowel can rotate.
How does broadening the mesenteric attachment address recurrence?
A wider fixation base reduces the tendency to rotate around a narrow pedicle. It addresses the attachment abnormality rather than an abdominal wall defect.
D. Divide a patent vitelline duct (Why this does not fit)
A patent duct would connect bowel to umbilicus; no such connection is described and division would not broaden the base.
Reasoning steps for option D
Is there an ileum-to-umbilicus channel for duct division to address?
No patent vitelline communication is described; the bowel is intra-abdominal and the observed lesion is a twisting vascular pedicle.
Why would duct division fail to prevent recurrent twisting here?
Dividing a duct cannot widen the short mesenteric attachment that permits volvulus.
Takeaway: Complete intra-abdominal return does not establish normal fixation. Widening the narrow attachment reduces the tendency to twist around the pedicle.
A. A: classically associated with failed midgut return; B: the same failed-return process as a covered umbilical sac (Why this does not fit)
The first interpretation fits: The covered midline sac with cord insertion identifies omphalocele, classically associated with abnormal return of herniated viscera. The second interpretation fails: A separate right-sided opening with uncovered bowel identifies gastroschisis; its causation is not fully established and should not be equated with failed normal return.
Reasoning steps for option A
Why does the cord entering A's membrane-covered midline sac support abnormal return of herniated midgut?
A is an omphalocele: the cord joins the covered midline sac, classically linked to abnormal return of herniated viscera.
What feature of B refutes the claim that it shares A's covered-sac return mechanism?
B has exposed bowel through a separate right paraumbilical opening; gastroschisis is not established to result from failed midgut return.
Which proposed mechanism wrongly treats B as another omphalocele?
The second claim wrongly applies the covered-sac return account to B despite its separate cord and absent covering.
B. A: classically associated with failed midgut return; B: distinct abdominal-wall defect, not simply failed physiological return (Best answer)
The first interpretation fits: The covered midline sac with cord insertion identifies omphalocele, classically associated with abnormal return of herniated viscera. The second interpretation fits: A separate right-sided opening with uncovered bowel identifies gastroschisis; its causation is not fully established and should not be equated with failed normal return.
Reasoning steps for option B
What classical return abnormality is compatible with A's cord-inserting midline sac?
The covered midline sac and cord insertion in A identify omphalocele, classically associated with abnormal midgut return.
Why should B's exposed bowel beside a separately inserted cord be classified independently?
B has an uncovered right-sided defect beside an intact umbilicus, identifying gastroschisis with a distinct, not definitively established cause.
How do the different cord insertions support the two distinct interpretations?
A fits the classical return association; B must not be assigned the same developmental mechanism merely because bowel is external.
C. A: a separate paraumbilical wall defect; B: distinct abdominal-wall defect, not simply failed physiological return (Why this does not fit)
The first interpretation fails: The covered midline sac with cord insertion identifies omphalocele, classically associated with abnormal return of herniated viscera. The second interpretation fits: A separate right-sided opening with uncovered bowel identifies gastroschisis; its causation is not fully established and should not be equated with failed normal return.
Reasoning steps for option C
Why is A not the separate paraumbilical wall defect proposed here?
A is midline and membrane covered, with the cord inserting into the sac, unlike a separate paraumbilical opening.
What about B does fit a distinct wall defect rather than failed physiological return?
B has the separate right-sided uncovered opening characteristic of gastroschisis, not simply failure of physiological return.
Which half of this pairing reverses the covered-sac versus uncovered-bowel distinction?
The A classification is wrong; the B classification recognizes the genuinely distinct wall defect.
D. A: a separate paraumbilical wall defect; B: the same failed-return process as a covered umbilical sac (Why this does not fit)
The first interpretation fails: The covered midline sac with cord insertion identifies omphalocele, classically associated with abnormal return of herniated viscera. The second interpretation fails: A separate right-sided opening with uncovered bowel identifies gastroschisis; its causation is not fully established and should not be equated with failed normal return.
Reasoning steps for option D
What does A's intact covering and sac-inserting cord rule out?
A has an omphalocele rather than an uncovered, separate paraumbilical defect.
Can uncovered bowel right of B's separate cord be explained as the same covered-sac defect?
B has gastroschisis; its uncovered bowel and separate cord distinguish it from the midline covered sac in A.
Why do both labels misclassify the two openings?
A is misidentified as the defect seen in B, and B is incorrectly assigned A's classical return association.
Takeaway: The covered midline sac with cord insertion identifies omphalocele, classically associated with abnormal return of herniated viscera. A separate right-sided opening with uncovered bowel identifies gastroschisis; its causation is not fully established and should not be equated with failed normal return.
A. A: volvulus risk from the attachment geometry; B: intrinsic occlusion consistent with impaired recanalization (Best answer)
The first interpretation fits: Patency after division identifies external compression, while the remaining narrow attachment independently preserves a risk of vascular twisting. The second interpretation fits: Failure of external release plus a directly seen mucosal diaphragm identifies an intrinsic lesion, fitting the classic recanalization account rather than an external band.
Reasoning steps for option A
Why does A's patent lumen after band division leave a vascular concern?
A's catheter traverses the lumen after band division, proving extrinsic compression was relieved; the narrow root still permits later volvulus.
What does B's persisting diaphragm after external release imply about luminal development?
B's mucosal diaphragm blocks the continuous duodenum despite external release, consistent with impaired recanalization.
How are A's narrow base and B's intrinsic membrane independent residual concerns?
The narrow fixation base threatens A's perfusion later, whereas an unreleased intrinsic lumen obstruction remains in B.
B. A: volvulus risk from the attachment geometry; B: external fixation alone explains the persistent occlusion (Why this does not fit)
The first interpretation fits: Patency after division identifies external compression, while the remaining narrow attachment independently preserves a risk of vascular twisting. The second interpretation fails: Failure of external release plus a directly seen mucosal diaphragm identifies an intrinsic lesion, fitting the classic recanalization account rather than an external band.
Reasoning steps for option B
What danger remains in A even though the catheter now passes?
A remains vulnerable to twisting about its narrow vascular pedicle even after the cecal band is divided.
Why can B's persisting blockage not be attributed to external fixation alone?
External release cannot remove B's visible diaphragm; the persistent obstruction is intrinsic.
Which proposed explanation overlooks the directly observed membrane in B?
The proposed external-only explanation for B contradicts direct inspection of the diaphragm.
C. A: persistent intrinsic diaphragm explains the relieved obstruction; B: intrinsic occlusion consistent with impaired recanalization (Why this does not fit)
The first interpretation fails: Patency after division identifies external compression, while the remaining narrow attachment independently preserves a risk of vascular twisting. The second interpretation fits: Failure of external release plus a directly seen mucosal diaphragm identifies an intrinsic lesion, fitting the classic recanalization account rather than an external band.
Reasoning steps for option C
If A had a persistent diaphragm, would dividing the cecal sheet have restored catheter passage?
No. A became patent as soon as the external sheet was divided, with no persistent diaphragm identified.
How does B's visible diaphragm support impaired recanalization?
B's continuous duodenal wall contains a blocking diaphragm, the classic luminal reopening defect.
Which infant, contrary to this pairing, has the intrinsic lesion?
B, not A, has the intrinsic diaphragm; A instead retains a narrow mesenteric root and potential volvulus risk.
D. A: persistent intrinsic diaphragm explains the relieved obstruction; B: external fixation alone explains the persistent occlusion (Why this does not fit)
The first interpretation fails: Patency after division identifies external compression, while the remaining narrow attachment independently preserves a risk of vascular twisting. The second interpretation fails: Failure of external release plus a directly seen mucosal diaphragm identifies an intrinsic lesion, fitting the classic recanalization account rather than an external band.
Reasoning steps for option D
Which event in A specifically disproves an unreleased intraluminal diaphragm?
The successful catheter passage after external division rules out a persisting occlusive membrane in A.
What in B remains after all surrounding attachments are released?
B remains occluded after external release because the diaphragm lies within its continuous wall.
Why does neither infant follow the claimed diaphragm-in-A and external-only-in-B pattern?
Both clauses invert the evidence: A's obstruction was external, while B's residual obstruction is intrinsic.
Takeaway: Patency after division identifies external compression, while the remaining narrow attachment independently preserves a risk of vascular twisting. Failure of external release plus a directly seen mucosal diaphragm identifies an intrinsic lesion, fitting the classic recanalization account rather than an external band.
A. A: impaired luminal reopening; B: impaired luminal reopening (Why this does not fit)
The first interpretation fits: An intact duodenal tube with an intrinsic diaphragm supports the classic failure-of-recanalization account, not disappearance of the whole segment. The second interpretation fails: Loss of bowel and mesentery between viable ends supports a prior ischemic interruption followed by resorption; present viability does not restore the missing segment.
Reasoning steps for option A
What preserved structures in A fit failed luminal reopening?
A retains wall and mesentery but has an epithelial diaphragm, fitting the classic failure of duodenal recanalization.
Why cannot failure to reopen B's lumen explain its absent mesentery?
B lacks an ileal segment and its mesentery; an unopened lumen alone cannot remove those tissues.
Which proposed shared mechanism fails to account for B's missing tissue?
The proposed shared luminal defect explains A but not B's tissue loss, classically associated with prior fetal vascular interruption.
B. A: fetal vascular interruption with tissue loss; B: fetal vascular interruption with tissue loss (Why this does not fit)
The first interpretation fails: An intact duodenal tube with an intrinsic diaphragm supports the classic failure-of-recanalization account, not disappearance of the whole segment. The second interpretation fits: Loss of bowel and mesentery between viable ends supports a prior ischemic interruption followed by resorption; present viability does not restore the missing segment.
Reasoning steps for option B
Why does A's continuous wall argue against vascular tissue loss?
A has no missing wall or mesentery, so vascular loss does not fit its isolated intrinsic diaphragm.
What classical event can leave B's blind ends and mesenteric gap?
B's separated blind ends and mesenteric gap fit prior fetal ischemic loss followed by resorption, even though adjacent bowel survives.
Why is a common vascular-loss explanation inappropriate for A?
Vascular interruption can account for B's absent tissue but not A's preserved tube with only a blocked lumen.
C. A: fetal vascular interruption with tissue loss; B: impaired luminal reopening (Why this does not fit)
The first interpretation fails: An intact duodenal tube with an intrinsic diaphragm supports the classic failure-of-recanalization account, not disappearance of the whole segment. The second interpretation fails: Loss of bowel and mesentery between viable ends supports a prior ischemic interruption followed by resorption; present viability does not restore the missing segment.
Reasoning steps for option C
What in A contradicts the proposed vascular interruption?
A's continuous tube and mesentery are preserved across the diaphragm, unlike a resorbed segment.
Can B's missing bowel and mesentery arise from a closed but continuous lumen alone?
B has missing tissue between blind ends, not merely epithelium that failed to reopen.
Which structural signs reverse both proposed mechanisms?
The claims swap the classic associations: A fits recanalization failure, while B fits prior vascular tissue loss.
D. A: impaired luminal reopening; B: fetal vascular interruption with tissue loss (Best answer)
The first interpretation fits: An intact duodenal tube with an intrinsic diaphragm supports the classic failure-of-recanalization account, not disappearance of the whole segment. The second interpretation fits: Loss of bowel and mesentery between viable ends supports a prior ischemic interruption followed by resorption; present viability does not restore the missing segment.
Reasoning steps for option D
How does A's epithelial diaphragm identify a lumen-specific defect?
A's obstruction is within an otherwise continuous duodenal lumen, classically attributed to incomplete recanalization.
Why do viable ends in B not exclude an earlier vascular insult?
B's present viability describes surviving ends, not the earlier event responsible for a missing segment and mesenteric gap.
Why must A and B be assigned different classical mechanisms?
A retains its tube with a diaphragm; B lost a segment and its mesentery, classically after fetal vascular interruption.
Takeaway: An intact duodenal tube with an intrinsic diaphragm supports the classic failure-of-recanalization account, not disappearance of the whole segment. Loss of bowel and mesentery between viable ends supports a prior ischemic interruption followed by resorption; present viability does not restore the missing segment.
A. Recurrent obstruction from an intrinsic duodenal web (Why this does not fit)
The described obstruction is extrinsic and is relieved by treating it; no persistent intrinsic web is described.
Reasoning steps for option A
Does the band-compressed duodenum retain an intrinsic membrane after external release?
No intrinsic diaphragm is reported. The intact duodenum is compressed by crossing peritoneal bands, so treating the bands relieves that obstruction.
What untreated structure creates the subsequent hazard instead of a web?
The narrow mesenteric root remains, allowing future rotation about the SMA even when the duodenum is patent.
B. Twisting around the SMA with loss of perfusion (Best answer)
Abnormal rotation and fixation leave a narrow mesenteric base despite absence of current twisting; later volvulus can compromise SMA perfusion.
Reasoning steps for option B
Why is volvulus still possible despite no twist at this operation?
A high cecum and right-sided duodenojejunal junction accompany a narrow fixation base; current untwisted status does not widen it.
Which vessel is endangered if this short mesenteric root twists later?
The midgut can rotate around its SMA pedicle, obstructing flow and threatening bowel perfusion.
C. Ischemia limited to a disconnected ileal segment (Why this does not fit)
No disconnected ileal segment is described. The observed obstruction is duodenal band compression, while the future vascular hazard follows from the narrow mesenteric root.
Reasoning steps for option C
Does the examination show an isolated disconnected ileal segment?
The bowel is intact and intra-abdominal; no ileal gap or blind ends establish an isolated atretic segment.
Would ischemia here necessarily remain limited to ileum?
No. A narrow midgut root permits twisting around the SMA, potentially compromising a broader vascular territory.
D. Leakage of enteric contents through the umbilicus (Why this does not fit)
A patent vitelline duct could drain at the umbilicus, but no umbilical communication is described.
Reasoning steps for option D
What anatomical communication would cause enteric leakage at the umbilicus?
A patent vitelline duct would connect ileum to the umbilicus, but none is described and all bowel is inside the abdominal wall.
Which residual risk persists after dividing the duodenal bands?
The narrow mesenteric attachment may still twist around the SMA; it does not imply an umbilical fistula.
Takeaway: Intra-abdominal bowel establishes return, not normal rotation or fixation. Bands explain current compression; the narrow base independently permits future SMA-centered volvulus.
A. ileal gap: prior fetal vascular loss; remaining attachment: future volvulus is excluded by current normal perfusion (Why this does not fit)
The first interpretation fits: A missing segment and mesenteric gap indicate loss of tissue, classically following fetal vascular interruption, rather than only luminal occlusion. The second interpretation fails: A narrow base remains mechanically vulnerable even when untwisted and perfused now; later SMA-centered volvulus could compromise a wider midgut territory.
Reasoning steps for option A
What does the missing ileal tissue and mesenteric gap suggest happened prenatally?
The absent segment and corresponding mesentery fit a past fetal vascular interruption with resorption rather than only lumen closure.
Does normal flow through the currently untwisted narrow root rule out a later SMA twist?
No. A narrow root between close attachments can still twist about the SMA despite current perfusion.
Which prediction about future perfusion conflicts with the close attachments?
Normal flow now cannot exclude future volvulus; it only establishes that a vascular compromise is not present at this instant.
B. ileal gap: a tube that only failed to reopen; remaining attachment: future volvulus can jeopardize SMA-territory bowel (Why this does not fit)
The first interpretation fails: A missing segment and mesenteric gap indicate loss of tissue, classically following fetal vascular interruption, rather than only luminal occlusion. The second interpretation fits: A narrow base remains mechanically vulnerable even when untwisted and perfused now; later SMA-centered volvulus could compromise a wider midgut territory.
Reasoning steps for option B
Would simple failed reopening remove both the ileal segment and its mesentery?
No. Failed reopening creates a lumen defect in a continuous tube, not an ileal gap and missing mesentery.
What prospective vascular event follows from the close duodenojejunal and ileocecal attachments?
The narrow attachment can permit future SMA-centered volvulus and compromise more midgut than the already missing ileal segment.
Which explanation mistakes tissue loss for a membrane while correctly noting the separate vascular risk?
The proposed lumen defect ignores missing tissue, while its separate concern about future SMA-territory ischemia is justified.
C. ileal gap: prior fetal vascular loss; remaining attachment: future volvulus can jeopardize SMA-territory bowel (Best answer)
The first interpretation fits: A missing segment and mesenteric gap indicate loss of tissue, classically following fetal vascular interruption, rather than only luminal occlusion. The second interpretation fits: A narrow base remains mechanically vulnerable even when untwisted and perfused now; later SMA-centered volvulus could compromise a wider midgut territory.
Reasoning steps for option C
Why does the ileal gap suggest prior vascular interruption rather than only lumen closure?
Loss of both ileum and mesentery is classically attributed to fetal vascular interruption and subsequent tissue resorption.
What could happen later around the narrow SMA axis despite preserved perfusion now?
A later twist around the narrow SMA pedicle could impair midgut perfusion even though no twist exists now.
How do the missing ileum and narrow attachment point to distinct past and future problems?
The gap records a likely earlier vascular loss; the still narrow attachment creates a separate prospective volvulus hazard.
D. ileal gap: a tube that only failed to reopen; remaining attachment: future volvulus is excluded by current normal perfusion (Why this does not fit)
The first interpretation fails: A missing segment and mesenteric gap indicate loss of tissue, classically following fetal vascular interruption, rather than only luminal occlusion. The second interpretation fails: A narrow base remains mechanically vulnerable even when untwisted and perfused now; later SMA-centered volvulus could compromise a wider midgut territory.
Reasoning steps for option D
Which absent tissue cannot be explained by an intact but unopened ileal tube?
Both an ileal segment and its supporting mesentery are gone; simple failure to reopen an intact tube cannot account for that.
Does currently viable bowel prove the remaining root cannot twist later?
No. Current viability cannot broaden a short mesenteric base or prevent a later turn around the SMA.
Why are both reassuring interpretations contradicted by the two operative findings?
The gap argues for past tissue loss, and close attachments preserve future volvulus risk rather than excluding it.
Takeaway: A missing segment and mesenteric gap indicate loss of tissue, classically following fetal vascular interruption, rather than only luminal occlusion. A narrow base remains mechanically vulnerable even when untwisted and perfused now; later SMA-centered volvulus could compromise a wider midgut territory.
A. relieved obstruction: extrinsic band compression; remaining hazard: persistent extra-abdominal location of the bowel (Why this does not fit)
The first interpretation fits: Restoration of passage after dividing the cecal attachment identifies external compression rather than an intrinsic diaphragm. The second interpretation fails: Repair of the sac addresses external location, not the independently abnormal mesenteric base; the narrow base can still permit volvulus.
Reasoning steps for option A
What does immediate passage after dividing the high-cecal sheet establish about the current blockage?
Passage returned immediately after the cecal sheet was divided, indicating extrinsic band compression.
Does the old sac repair leave bowel outside the abdomen as the remaining vascular hazard?
The covered midline sac was repaired at birth; external bowel position is not the remaining vascular threat.
Which residual-hazard claim confuses repaired wall position with fixation geometry?
The residual concern is a narrow mesenteric root that can twist, not persistence of the already repaired sac.
B. relieved obstruction: intrinsic failure of duodenal reopening; remaining hazard: twisting around a narrow vascular pedicle (Why this does not fit)
The first interpretation fails: Restoration of passage after dividing the cecal attachment identifies external compression rather than an intrinsic diaphragm. The second interpretation fits: Repair of the sac addresses external location, not the independently abnormal mesenteric base; the narrow base can still permit volvulus.
Reasoning steps for option B
Why is failed duodenal recanalization inconsistent with prompt passage after band release?
An intrinsic diaphragm would continue blocking the lumen after release of the outside band, unlike this case.
What twist could still develop around the narrow root after the covered sac was repaired?
The persistent narrow root permits later twisting around the vascular pedicle despite successful sac repair.
Which part of this pair mistakes external compression for an intrinsic membrane?
The intrinsic-reopening claim is wrong; the narrow-root vascular hazard is correctly identified.
C. relieved obstruction: intrinsic failure of duodenal reopening; remaining hazard: persistent extra-abdominal location of the bowel (Why this does not fit)
The first interpretation fails: Restoration of passage after dividing the cecal attachment identifies external compression rather than an intrinsic diaphragm. The second interpretation fails: Repair of the sac addresses external location, not the independently abnormal mesenteric base; the narrow base can still permit volvulus.
Reasoning steps for option C
Would a fixed epithelial diaphragm disappear simply by cutting the cecal band?
No. Band division alone restored passage, favoring external duodenal compression.
How does prior sac repair undermine the proposed ongoing extra-abdominal location?
The umbilical sac has already been repaired, so extra-abdominal location is not the residual concern described.
Why do neither the immediate mechanism nor the residual concern match these claims?
The first claim ignores the immediate response to band division, and the second ignores the narrow root.
D. relieved obstruction: extrinsic band compression; remaining hazard: twisting around a narrow vascular pedicle (Best answer)
The first interpretation fits: Restoration of passage after dividing the cecal attachment identifies external compression rather than an intrinsic diaphragm. The second interpretation fits: Repair of the sac addresses external location, not the independently abnormal mesenteric base; the narrow base can still permit volvulus.
Reasoning steps for option D
Which observed response identifies compression by the high-cecal band?
Release of the sheet from the high cecum restored passage, localizing the current obstruction to external compression.
Why does a narrow mesenteric root remain hazardous despite neonatal sac repair?
Sac repair corrected the covered wall defect, but it did not widen mesenteric fixation; later volvulus remains possible.
How do band division and persistent narrow fixation support separate diagnoses?
The band explains the acute luminal blockage, while the narrow pedicle independently predicts potential vascular twisting.
Takeaway: Restoration of passage after dividing the cecal attachment identifies external compression rather than an intrinsic diaphragm. Repair of the sac addresses external location, not the independently abnormal mesenteric base; the narrow base can still permit volvulus.
A. territory: SMA-associated midgut; mechanism: impaired luminal reopening (Best answer)
The first interpretation fits: Bile-duct entry upstream places the obstructed segment distal to the major papilla, in the midgut portion of the duodenum associated with the SMA. The second interpretation fits: The continuous wall and mesentery with a diaphragm indicate intrinsic occlusion, fitting the classic recanalization account rather than loss of a bowel segment.
Reasoning steps for option A
Where is the diaphragm relative to the catheter-marked papilla, and which arterial root chiefly supplies that side?
The duct opens before the diaphragm, placing it distal to the major papilla in the SMA-associated midgut duodenum.
Why does a diaphragm inside continuous wall and mesentery fit impaired luminal reopening?
An epithelial diaphragm within preserved wall and mesentery fits the classic failure of duodenal recanalization.
How do papillary location and preserved tissue jointly support SMA territory and recanalization failure?
The papillary landmark supports SMA territory and the intact tube supports a lumen-specific developmental defect.
B. territory: SMA-associated midgut; mechanism: fetal vascular loss with resorption (Why this does not fit)
The first interpretation fits: Bile-duct entry upstream places the obstructed segment distal to the major papilla, in the midgut portion of the duodenum associated with the SMA. The second interpretation fails: The continuous wall and mesentery with a diaphragm indicate intrinsic occlusion, fitting the classic recanalization account rather than loss of a bowel segment.
Reasoning steps for option B
Why is the obstruction on the SMA-associated side of the bile-duct opening?
Bile enters upstream; the occlusion is downstream in the midgut side of the duodenum chiefly supplied by the SMA.
What expected tissue loss is absent if fetal vascular interruption and resorption caused this lesion?
The bowel wall and mesentery continue across the diaphragm; there is no absent segment to suggest vascular loss and resorption.
Which proposed mechanism is inconsistent with the preserved wall despite the correct territory?
The territory is correct, but the proposed vascular-loss mechanism contradicts continuous tissue.
C. territory: celiac-associated foregut; mechanism: impaired luminal reopening (Why this does not fit)
The first interpretation fails: Bile-duct entry upstream places the obstructed segment distal to the major papilla, in the midgut portion of the duodenum associated with the SMA. The second interpretation fits: The continuous wall and mesentery with a diaphragm indicate intrinsic occlusion, fitting the classic recanalization account rather than loss of a bowel segment.
Reasoning steps for option C
Does a diaphragm distal to the catheter-marked papilla belong chiefly to celiac foregut territory?
No. The duct catheter marks upstream papillary entry; a distal lesion lies on the SMA-associated midgut side.
What feature nevertheless supports failed luminal reopening?
The obstructing diaphragm is inside an intact tube, fitting the classical impaired-recanalization account.
Which territory assignment conflicts with the papillary landmark despite the correct mechanism?
Recanalization failure fits the morphology, but celiac foregut supply does not fit the position beyond the papilla.
D. territory: celiac-associated foregut; mechanism: fetal vascular loss with resorption (Why this does not fit)
The first interpretation fails: Bile-duct entry upstream places the obstructed segment distal to the major papilla, in the midgut portion of the duodenum associated with the SMA. The second interpretation fails: The continuous wall and mesentery with a diaphragm indicate intrinsic occlusion, fitting the classic recanalization account rather than loss of a bowel segment.
Reasoning steps for option D
How does upstream bile entry refute proximal celiac territory for this diaphragm?
The major papilla lies before the obstruction, so the lesion is distal and chiefly SMA-associated rather than proximal foregut.
Would vascular resorption ordinarily leave a continuous mesentery spanning the lesion?
Classical vascular interruption with resorption would involve missing bowel and mesentery, neither of which is present.
Why do both the proposed foregut supply and tissue-loss mechanism conflict with these observations?
Both assignments fail: papillary position indicates midgut territory and tissue continuity indicates intrinsic luminal occlusion.
Takeaway: Bile-duct entry upstream places the obstructed segment distal to the major papilla, in the midgut portion of the duodenum associated with the SMA. The continuous wall and mesentery with a diaphragm indicate intrinsic occlusion, fitting the classic recanalization account rather than loss of a bowel segment.
A. A: prior fetal vascular loss; B: emesis is generally bilious (Why this does not fit)
The first interpretation fits: The missing jejunal and mesenteric tissue implies an earlier destructive event; viable ends at birth do not exclude prior fetal ischemia and resorption. The second interpretation fails: The obstruction is proximal to bile entry, so bile cannot normally reach the proximal obstructed lumen; this contrasts with postpapillary obstruction.
Reasoning steps for option A
Can a fetal vascular insult leave well-perfused jejunal ends after the intervening segment disappears?
The separated jejunal blind ends and mesenteric gap indicate lost tissue after fetal vascular interruption; perfusion of the remaining ends at birth does not restore that tissue.
If the papilla opens beyond the complete block, could bilious contents reach the proximal duodenal pouch?
Bilious emesis requires bile to reach the proximal lumen, which this prepapillary complete obstruction prevents.
Do the viable jejunal ends rule out prior ischemia, and can bile pass the prepapillary block?
Viable surviving ends are compatible with earlier fetal tissue loss, but a distal papilla leaves the proximal emesis nonbilious, not bilious.
B. A: persistent occlusion of an otherwise intact tube; B: emesis is generally nonbilious (Why this does not fit)
The first interpretation fails: The missing jejunal and mesenteric tissue implies an earlier destructive event; viable ends at birth do not exclude prior fetal ischemia and resorption. The second interpretation fits: The obstruction is proximal to bile entry, so bile cannot normally reach the proximal obstructed lumen; this contrasts with postpapillary obstruction.
Reasoning steps for option B
Would simple persistence of an occluded jejunal lumen account for the associated mesenteric gap?
An intact but unopened tube would retain its wall and mesentery, unlike these separated ends and missing mesentery.
What color is emesis expected to be when bile enters only distal to this obstruction?
The papilla lies distal to the complete duodenal block, so bile enters below the block and emesis upstream is generally nonbilious.
Which part of the intact-tube/nonbilious pairing is contradicted by the missing mesentery?
Nonbilious emesis follows the prepapillary block, but an intact persistently closed tube cannot explain lost jejunum and mesentery.
C. A: prior fetal vascular loss; B: emesis is generally nonbilious (Best answer)
The first interpretation fits: The missing jejunal and mesenteric tissue implies an earlier destructive event; viable ends at birth do not exclude prior fetal ischemia and resorption. The second interpretation fits: The obstruction is proximal to bile entry, so bile cannot normally reach the proximal obstructed lumen; this contrasts with postpapillary obstruction.
Reasoning steps for option C
Why does absence of jejunum and mesentery favor earlier vascular loss over a sealed intact tube?
The separated jejunal blind ends and mesenteric gap indicate lost tissue after fetal vascular interruption; perfusion of the remaining ends at birth does not restore that tissue.
Does the inaccessible distal papilla permit bile to mix with contents vomited upstream?
The papilla lies distal to the complete duodenal block, so bile enters below the block and emesis upstream is generally nonbilious.
How do the mesenteric defect and distal papilla together select this paired explanation?
Prior vascular loss accounts for the jejunal gap; bile enters beyond the complete block, so upstream emesis is generally nonbilious.
D. A: persistent occlusion of an otherwise intact tube; B: emesis is generally bilious (Why this does not fit)
The first interpretation fails: The missing jejunal and mesenteric tissue implies an earlier destructive event; viable ends at birth do not exclude prior fetal ischemia and resorption. The second interpretation fails: The obstruction is proximal to bile entry, so bile cannot normally reach the proximal obstructed lumen; this contrasts with postpapillary obstruction.
Reasoning steps for option D
Does an intact but unopened jejunal tube explain two separated blind ends?
An intact but unopened tube would retain its wall and mesentery, unlike these separated ends and missing mesentery.
Would bilious vomiting fit a complete block above the duct opening?
Bilious emesis requires bile to reach the proximal lumen, which this prepapillary complete obstruction prevents.
What two anatomic findings refute persistent luminal occlusion plus bilious emesis?
The jejunal and mesenteric defect argues against mere luminal persistence, and the papilla beyond the block argues against bilious emesis.
Takeaway: The missing jejunal and mesenteric tissue implies an earlier destructive event; viable ends at birth do not exclude prior fetal ischemia and resorption. The obstruction is proximal to bile entry, so bile cannot normally reach the proximal obstructed lumen; this contrasts with postpapillary obstruction.
A. A: impaired luminal reopening; B: impaired luminal reopening (Why this does not fit)
The first interpretation fits: An intrinsic diaphragm in a continuous duodenal tube fits impaired recanalization; no missing full-wall segment is described. The second interpretation fails: Documented perfusion loss followed by missing bowel and mesentery fits ischemic destruction and resorption, not merely persistence of a closed lumen.
Reasoning steps for option A
Is A’s intact duodenal wall with an occluding diaphragm the expected result of failed reopening?
The duodenal diaphragm sits inside a continuous postpapillary wall with intact mesentery, fitting failed luminal reopening rather than loss of full-thickness bowel.
Does B’s documented perfusion loss leave the anatomy expected of a mere persistent closed lumen?
Failure to reopen a lumen would leave an intact continuous bowel wall and mesentery, not separated ends across a gap.
Why can the same failed-reopening label not explain A’s diaphragm and B’s missing segment?
A continuous duodenal diaphragm fits failed recanalization; B instead lost perfused bowel and mesentery after ischemia.
B. A: impaired luminal reopening; B: vascular interruption followed by tissue loss (Best answer)
The first interpretation fits: An intrinsic diaphragm in a continuous duodenal tube fits impaired recanalization; no missing full-wall segment is described. The second interpretation fits: Documented perfusion loss followed by missing bowel and mesentery fits ischemic destruction and resorption, not merely persistence of a closed lumen.
Reasoning steps for option B
How does A's preserved duodenal wall favor a reopening defect over destruction and resorption?
The diaphragm blocks a continuous wall with intact mesentery. This preserved tube supports the classic recanalization account rather than loss and resorption of a bowel segment.
What event explains B’s vanished ileal tissue and mesenteric defect after fetal hypoperfusion?
Documented fetal ileal hypoperfusion followed by separated blind ends and a mesenteric defect supports ischemic loss and resorption.
What distinct mechanisms do the intact diaphragm and the ischemic ileal gap require?
A retained duodenal wall with a diaphragm supports impaired reopening, while fetal ileal hypoperfusion followed by a gap supports tissue resorption.
C. A: vascular interruption followed by tissue loss; B: vascular interruption followed by tissue loss (Why this does not fit)
The first interpretation fails: An intrinsic diaphragm in a continuous duodenal tube fits impaired recanalization; no missing full-wall segment is described. The second interpretation fits: Documented perfusion loss followed by missing bowel and mesentery fits ischemic destruction and resorption, not merely persistence of a closed lumen.
Reasoning steps for option C
What tissue-loss evidence is absent from A despite the proposed vascular destruction?
No missing duodenal segment or mesenteric gap is described. A diaphragm within the preserved tube instead fits the classic impaired-recanalization account.
Does the gap between B’s blind ends support the proposed vascular resorption mechanism?
Documented fetal ileal hypoperfusion followed by separated blind ends and a mesenteric defect supports ischemic loss and resorption.
Where does the all-vascular explanation conflict with the morphology of A?
B’s ischemic gap supports vascular interruption, but A has no missing full-thickness duodenal segment to support the same mechanism.
D. A: vascular interruption followed by tissue loss; B: impaired luminal reopening (Why this does not fit)
The first interpretation fails: An intrinsic diaphragm in a continuous duodenal tube fits impaired recanalization; no missing full-wall segment is described. The second interpretation fails: Documented perfusion loss followed by missing bowel and mesentery fits ischemic destruction and resorption, not merely persistence of a closed lumen.
Reasoning steps for option D
Why is an intact duodenal tube a poor match for vascular loss in A?
No full-thickness segment or mesentery is missing in A. Its diaphragm within a continuous duodenum favors impaired luminal reopening over the proposed vascular tissue-loss mechanism.
Could failed reopening by itself remove both ileal wall and adjacent mesentery in B?
Failure to reopen a lumen would leave an intact continuous bowel wall and mesentery, not separated ends across a gap.
Why does reversing the assignments fail at both the duodenal membrane and ileal gap?
A needs luminal recanalization failure rather than vascular loss; B needs vascular destruction rather than luminal reopening failure.
Takeaway: An intrinsic diaphragm in a continuous duodenal tube fits impaired recanalization; no missing full-wall segment is described. Documented perfusion loss followed by missing bowel and mesentery fits ischemic destruction and resorption, not merely persistence of a closed lumen.
A. Recurrent mechanical obstruction around the persistent duct remnant (Best answer)
A fibrous vitelline remnant can act as an axis or band for recurrent obstruction despite a closed lumen.
Reasoning steps for option A
Does the solid antimesenteric ileum-to-umbilicus tether provide an axis for the observed rotating loop?
Yes. A persistent nonpatent vitelline band tethers the ileum, and the loop visibly rotates beneath it; leaving the band permits recurrent mechanical obstruction.
Would the absence of a skin opening prevent another episode of band-related obstruction?
No. Luminal patency is unnecessary for a solid fibrous cord to trap or twist a bowel loop.
B. Continuous passage of stool through the umbilicus (Why this does not fit)
A patent full-length duct is necessary for enteric discharge, which the observed solid band lacks.
Reasoning steps for option B
Could this solid ileoumbilical cord transmit stool from bowel to the umbilicus?
No. Continuous fecal drainage requires a patent full-length vitelline duct and an umbilical opening; neither is present.
What does the loop rotating beneath the nonluminal band predict instead of umbilical discharge?
The remaining band forms an external pivot for recurrent mechanical obstruction, not a conduit for intestinal contents.
C. Bleeding from obligatory gastric mucosa in every such remnant (Why this does not fit)
Ectopic gastric mucosa may occur in a diverticulum but is not obligatory in a fibrous band.
Reasoning steps for option C
Does the observed fibrous cord establish ectopic gastric mucosa as an obligatory finding?
No. Gastric mucosa can occur in a Meckel diverticulum but is not required in a nonpatent fibrous remnant.
Which observed effect of this particular remnant predicts symptoms if it remains?
The ileal loop rotates beneath the taut antimesenteric-to-umbilical band, making recurrent obstruction the supported consequence, not inevitable acid-related bleeding.
D. An intrinsic duodenal occlusion proximal to bile entry (Why this does not fit)
The remote ileal tether does not create a congenital intrinsic duodenal membrane.
Reasoning steps for option D
Is the obstructing structure in the duodenal lumen proximal to bile entry?
No. Surgery locates a solid tether from the antimesenteric ileum to the deep umbilicus, with an ileal loop rotating under it.
Why would an intrinsic duodenal membrane not explain the observed intermittent episodes?
A fixed duodenal membrane would not produce visible ileal rotation around a persistent external vitelline band; the band itself can repeatedly entrap the loop.
Takeaway: Trace the solid ileum-to-umbilicus tether to a persistent but nonpatent vitelline structure. Predict its mechanical effect while distinguishing it from consequences requiring luminal patency or ectopic mucosa.
A. A: acid injury of neighboring ileal mucosa; B: telescoping of bowel led by an intraluminal remnant (Why this does not fit)
The first interpretation fits: Gastric-type mucosa adjacent to an ileal ulcer supports acid-mediated injury and bleeding, rather than inferring traction ischemia from a pouch alone. The second interpretation fails: A loop caught below an external ileoumbilical cord with sharp angulation is mechanically entrapped; this differs from bowel telescoping into an adjacent lumen.
Reasoning steps for option A
How does gastric-type mucosa beside A’s ileal ulcer account for painless bleeding?
Gastric-type mucosa in A can secrete acid; the ulcer in neighboring ileum localizes acid-mediated injury causing painless bleeding.
Is bowel passing beneath an external cord evidence that a segment telescoped into another?
Intussusception would show one bowel segment telescoping into another, not a loop caught beneath an external cord.
Why does A’s acid source fit while B’s proposed intraluminal lead point does not?
A’s gastric mucosa and adjacent ulcer support acid bleeding, but B’s externally trapped loop does not telescope into another lumen.
B. A: ischemia from traction at the pouch attachment; B: entrapment beneath an embryonic fibrous remnant (Why this does not fit)
The first interpretation fails: Gastric-type mucosa adjacent to an ileal ulcer supports acid-mediated injury and bleeding, rather than inferring traction ischemia from a pouch alone. The second interpretation fits: A loop caught below an external ileoumbilical cord with sharp angulation is mechanically entrapped; this differs from bowel telescoping into an adjacent lumen.
Reasoning steps for option B
Does a blind pouch alone establish ischemic traction when an acid-producing mucosa borders the ulcer?
The pouch attachment alone cannot establish traction ischemia when the observed injury is an ulcer beside gastric-type mucosa.
What mechanical role does B’s taut ileoumbilical cord play at the sharp angulation?
In B the viable loop passes under an external ileum-to-umbilicus cord and kinks sharply, demonstrating band entrapment.
Which findings favor acid injury in A and demonstrate band entrapment in B?
A's ulcer beside gastric mucosa favors acid injury over unsupported traction ischemia; B's cord visibly catches and angulates the loop.
C. A: ischemia from traction at the pouch attachment; B: telescoping of bowel led by an intraluminal remnant (Why this does not fit)
The first interpretation fails: Gastric-type mucosa adjacent to an ileal ulcer supports acid-mediated injury and bleeding, rather than inferring traction ischemia from a pouch alone. The second interpretation fails: A loop caught below an external ileoumbilical cord with sharp angulation is mechanically entrapped; this differs from bowel telescoping into an adjacent lumen.
Reasoning steps for option C
Which lesion favors acid injury over inferred attachment traction in A?
The pouch attachment alone cannot establish traction ischemia when the observed injury is an ulcer beside gastric-type mucosa.
Can intussusception explain the visible external band trapping B’s viable loop?
Intussusception would show one bowel segment telescoping into another, not a loop caught beneath an external cord.
Why do both proposed mechanisms miss the respective ulcer and external cord?
The adjacent ulcer favors acid injury rather than traction, and the external ileoumbilical cord favors entrapment rather than intussusception.
D. A: acid injury of neighboring ileal mucosa; B: entrapment beneath an embryonic fibrous remnant (Best answer)
The first interpretation fits: Gastric-type mucosa adjacent to an ileal ulcer supports acid-mediated injury and bleeding, rather than inferring traction ischemia from a pouch alone. The second interpretation fits: A loop caught below an external ileoumbilical cord with sharp angulation is mechanically entrapped; this differs from bowel telescoping into an adjacent lumen.
Reasoning steps for option D
Why is acid injury more direct than traction for A’s mucosa-adjacent ulcer?
Gastric-type mucosa in A can secrete acid; the ulcer in neighboring ileum localizes acid-mediated injury causing painless bleeding.
How does the loop’s position beneath the cord identify external entrapment?
In B the viable loop passes under an external ileum-to-umbilicus cord and kinks sharply, demonstrating band entrapment.
How do adjacent acid injury and a cord-trapped loop jointly explain the two presentations?
Ectopic gastric mucosa provides an acid source for A’s ileal ulcer; the band under which B’s loop passes supplies the external obstructive pivot.
Takeaway: Gastric-type mucosa adjacent to an ileal ulcer supports acid-mediated injury and bleeding, rather than inferring traction ischemia from a pouch alone. A loop caught below an external ileoumbilical cord with sharp angulation is mechanically entrapped; this differs from bowel telescoping into an adjacent lumen.
A. A deficient bud: dorsal; B emesis: generally nonbilious (Best answer)
The first interpretation fits: Absent body and tail with a preserved uncinate process localize the deficient pancreatic contribution to the dorsal bud, while the ventral contribution is represented. The second interpretation fits: Bile enters below a complete obstruction and cannot normally reach the proximal lumen; emesis is therefore generally nonbilious rather than bilious.
Reasoning steps for option A
Which bud contributes the absent body and tail despite a preserved uncinate process?
Loss of pancreatic body and tail with a preserved uncinate process implicates the dorsal bud; the uncinate process represents preserved ventral contribution.
What does bile entry distal to B’s complete block predict for proximal vomitus?
The catheter identifies bile entry distal to the complete duodenal obstruction, so proximal emesis is generally nonbilious.
How do the preserved uncinate process and distal bile entry support both proposed claims?
The intact uncinate process and absent body/tail point to dorsal deficiency; bile entering below the block predicts nonbilious emesis.
B. A deficient bud: dorsal; B emesis: generally bilious (Why this does not fit)
The first interpretation fits: Absent body and tail with a preserved uncinate process localize the deficient pancreatic contribution to the dorsal bud, while the ventral contribution is represented. The second interpretation fails: Bile enters below a complete obstruction and cannot normally reach the proximal lumen; emesis is therefore generally nonbilious rather than bilious.
Reasoning steps for option B
Why does the intact uncinate process support dorsal rather than ventral deficiency?
The preserved uncinate process represents ventral contribution, while the missing body and tail are dorsal derivatives. The regional deficit therefore supports the dorsal-bud assignment.
Could bile reach the vomiting side when its duct opening lies beyond an impassable obstruction?
Bilious emesis would require bile to enter proximal to the blockage; here duct entry is beyond the impassable obstruction.
Which part of the dorsal-bud/bilious pairing violates B’s duct position?
The pancreatic assignment fits dorsal-derived body/tail loss, but bile downstream of complete obstruction cannot color upstream vomitus.
C. A deficient bud: ventral; B emesis: generally nonbilious (Why this does not fit)
The first interpretation fails: Absent body and tail with a preserved uncinate process localize the deficient pancreatic contribution to the dorsal bud, while the ventral contribution is represented. The second interpretation fits: Bile enters below a complete obstruction and cannot normally reach the proximal lumen; emesis is therefore generally nonbilious rather than bilious.
Reasoning steps for option C
Could ventral bud deficiency selectively remove the dorsal-derived body and tail?
A deficient ventral bud would not explain a preserved uncinate process with missing body and tail derived from the dorsal bud.
Does nonbilious emesis follow from B’s duct opening on the distal side?
The catheter identifies bile entry distal to the complete duodenal obstruction, so proximal emesis is generally nonbilious.
Why is the emesis prediction sound but the proposed ventral bud deficit unsound?
B’s nonbilious prediction fits distal bile entry, but preservation of the ventral-derived uncinate process refutes ventral bud loss.
D. A deficient bud: ventral; B emesis: generally bilious (Why this does not fit)
The first interpretation fails: Absent body and tail with a preserved uncinate process localize the deficient pancreatic contribution to the dorsal bud, while the ventral contribution is represented. The second interpretation fails: Bile enters below a complete obstruction and cannot normally reach the proximal lumen; emesis is therefore generally nonbilious rather than bilious.
Reasoning steps for option D
Why does the preserved uncinate process exclude loss of the ventral contribution?
A deficient ventral bud would not explain a preserved uncinate process with missing body and tail derived from the dorsal bud.
Would a distal duct opening make the upstream vomitus bilious despite complete obstruction?
Bilious emesis would require bile to enter proximal to the blockage; here duct entry is beyond the impassable obstruction.
Which separate anatomic observations refute both the ventral assignment and bilious prediction?
The absent dorsal-derived body/tail refutes a ventral deficit, and the distal bile opening refutes bilious proximal emesis.
Takeaway: Absent body and tail with a preserved uncinate process localize the deficient pancreatic contribution to the dorsal bud, while the ventral contribution is represented. Bile enters below a complete obstruction and cannot normally reach the proximal lumen; emesis is therefore generally nonbilious rather than bilious.
A. A persistent portion: central duct segment after both ends close; B mechanism: traction-related ischemia at the pouch attachment (Why this does not fit)
The first interpretation fits: A closed central lumen suspended between two nonluminal ends identifies persistence of the middle portion after terminal closure, unlike an ileal lumen opening into a diverticulum. The second interpretation fails: The gastric-type mucosa and adjacent ileal ulcer support acid injury associated with an ileal diverticulum; a pouch by itself does not establish traction ischemia.
Reasoning steps for option A
Which segment persists when A’s cyst has a lumen but both connecting cords are solid?
The epithelial cyst between two nonluminal cords retains a central vitelline-duct segment after closure of both ends.
Does B’s neighboring ileal ulcer arise most directly from mechanical traction or the gastric-type mucosa?
The adjacent ulcer and gastric-type mucosa provide an acid source and target, not evidence for traction-related ischemia.
Why is central duct persistence correct but traction ischemia unsupported in the separate child?
A’s closed terminal cords isolate a persistent central duct cyst, but B’s acid-secreting mucosa and nearby ulcer do not establish traction ischemia.
B. A persistent portion: ileal end remaining open as a blind diverticulum; B mechanism: acid-mediated injury to adjacent ileum (Why this does not fit)
The first interpretation fails: A closed central lumen suspended between two nonluminal ends identifies persistence of the middle portion after terminal closure, unlike an ileal lumen opening into a diverticulum. The second interpretation fits: The gastric-type mucosa and adjacent ileal ulcer support acid injury associated with an ileal diverticulum; a pouch by itself does not establish traction ischemia.
Reasoning steps for option B
Would an open ileal-end diverticulum be isolated from ileum by a nonluminal cord?
An ileal-end diverticulum would communicate with the ileal lumen rather than hang between two solid nonluminal attachments.
What local source can injure ileal mucosa adjacent to B’s antimesenteric pouch?
Gastric-type mucosa within B's ileal pouch can injure the neighboring ileal mucosa with acid, matching the observed ulcer and bleeding.
Which of the proposed cyst and bleeding mechanisms survives the solid-cord and ulcer evidence?
B’s gastric mucosa explains acid injury; A’s solid ileal connection excludes a pouch continuous with ileal lumen.
C. A persistent portion: central duct segment after both ends close; B mechanism: acid-mediated injury to adjacent ileum (Best answer)
The first interpretation fits: A closed central lumen suspended between two nonluminal ends identifies persistence of the middle portion after terminal closure, unlike an ileal lumen opening into a diverticulum. The second interpretation fits: The gastric-type mucosa and adjacent ileal ulcer support acid injury associated with an ileal diverticulum; a pouch by itself does not establish traction ischemia.
Reasoning steps for option C
How does closure of both terminal duct ends leave A’s epithelial-lined central cyst?
The epithelial cyst between two nonluminal cords retains a central vitelline-duct segment after closure of both ends.
How can ectopic gastric secretion account for B’s ulcer and painless bleeding?
Gastric-type mucosa within B's ileal pouch can injure the neighboring ileal mucosa with acid, matching the observed ulcer and bleeding.
How do the isolated cyst and adjacent ulcer support both selected mechanisms?
The isolated epithelial-lined cyst retains the middle vitelline duct; ectopic gastric secretion damages adjacent ileum in B.
D. A persistent portion: ileal end remaining open as a blind diverticulum; B mechanism: traction-related ischemia at the pouch attachment (Why this does not fit)
The first interpretation fails: A closed central lumen suspended between two nonluminal ends identifies persistence of the middle portion after terminal closure, unlike an ileal lumen opening into a diverticulum. The second interpretation fails: The gastric-type mucosa and adjacent ileal ulcer support acid injury associated with an ileal diverticulum; a pouch by itself does not establish traction ischemia.
Reasoning steps for option D
Why does A’s solid ileal attachment rule out an ileal-end blind diverticulum?
An ileal-end diverticulum would communicate with the ileal lumen rather than hang between two solid nonluminal attachments.
Is pouch attachment traction supported when gastric mucosa and an adjacent ulcer are identified?
The adjacent ulcer and gastric-type mucosa provide an acid source and target, not evidence for traction-related ischemia.
Why does an ileal-end diverticulum with traction injury fail both anatomic tests?
The central cyst lacks an open ileal diverticular neck, and B’s mucosa-adjacent ulcer favors acid rather than traction.
Takeaway: A closed central lumen suspended between two nonluminal ends identifies persistence of the middle portion after terminal closure, unlike an ileal lumen opening into a diverticulum. The gastric-type mucosa and adjacent ileal ulcer support acid injury associated with an ileal diverticulum; a pouch by itself does not establish traction ischemia.
A. root threat: terminal ileum and ascending colon; IMA injection: cecum and proximal transverse colon (Why this does not fit)
The first interpretation fits: The twisted SMA root supplies midgut structures including terminal ileum and ascending colon; foregut gastric/proximal-duodenal tissue belongs principally to the celiac root. The second interpretation fails: The independently injected IMA corresponds to hindgut, including descending and sigmoid colon, not the cecum and proximal transverse colon supplied principally by the SMA.
Reasoning steps for option A
Does twisting the SMA root directly jeopardize terminal ileum and ascending colon?
A twisted SMA root threatens its midgut territory including terminal ileum and ascending colon.
Would IMA injection principally opacify cecum and proximal transverse colon?
Cecum and proximal transverse colon are principally SMA midgut territories, not the expected IMA hindgut injection territory.
Why is the SMA threat correct but the proposed IMA filling territory misplaced?
Terminal ileum and ascending colon are threatened by the SMA twist, whereas cecum and proximal transverse colon are not principally IMA territories.
B. root threat: terminal ileum and ascending colon; IMA injection: descending and sigmoid colon (Best answer)
The first interpretation fits: The twisted SMA root supplies midgut structures including terminal ileum and ascending colon; foregut gastric/proximal-duodenal tissue belongs principally to the celiac root. The second interpretation fits: The independently injected IMA corresponds to hindgut, including descending and sigmoid colon, not the cecum and proximal transverse colon supplied principally by the SMA.
Reasoning steps for option B
Why do terminal ileum and ascending colon, rather than stomach and proximal duodenum, track the twisted SMA root?
Terminal ileum and ascending colon are midgut structures supplied principally by the SMA; stomach and proximal duodenum belong chiefly to celiac foregut territory.
Which hindgut colonic segments should fill from the separately injected IMA?
IMA injection outlines hindgut territory including descending and sigmoid colon.
How do the twisted SMA root and separate IMA study partition midgut from hindgut?
SMA root twisting threatens terminal ileum and ascending colon; IMA injection instead outlines descending and sigmoid hindgut.
C. root threat: stomach and proximal duodenum; IMA injection: descending and sigmoid colon (Why this does not fit)
The first interpretation fails: The twisted SMA root supplies midgut structures including terminal ileum and ascending colon; foregut gastric/proximal-duodenal tissue belongs principally to the celiac root. The second interpretation fits: The independently injected IMA corresponds to hindgut, including descending and sigmoid colon, not the cecum and proximal transverse colon supplied principally by the SMA.
Reasoning steps for option C
Which embryonic arterial root principally supplies the proposed stomach and proximal duodenum?
Stomach and proximal duodenum are principally foregut supplied by celiac branches, not the directly threatened SMA midgut territory.
Does descending and sigmoid filling follow from the IMA angiogram?
IMA injection outlines hindgut territory including descending and sigmoid colon.
Which half of this pair misattributes celiac foregut to an SMA-root twist?
IMA filling of descending and sigmoid is sound, but stomach and proximal duodenum chiefly belong to the celiac foregut root.
D. root threat: stomach and proximal duodenum; IMA injection: cecum and proximal transverse colon (Why this does not fit)
The first interpretation fails: The twisted SMA root supplies midgut structures including terminal ileum and ascending colon; foregut gastric/proximal-duodenal tissue belongs principally to the celiac root. The second interpretation fails: The independently injected IMA corresponds to hindgut, including descending and sigmoid colon, not the cecum and proximal transverse colon supplied principally by the SMA.
Reasoning steps for option D
Why does the proposed foregut territory not track the twisted SMA pedicle?
Stomach and proximal duodenum are principally foregut supplied by celiac branches, not the directly threatened SMA midgut territory.
Are cecum and proximal transverse colon downstream of the injected IMA or principally SMA?
Cecum and proximal transverse colon are principally SMA midgut territories, not the expected IMA hindgut injection territory.
Why do neither the proposed threat nor the proposed IMA filling territory follow their arterial roots?
The gastric and proximal duodenal territory is chiefly celiac, while the proposed cecal and proximal transverse filling is chiefly SMA, not IMA.
Takeaway: The twisted SMA root supplies midgut structures including terminal ileum and ascending colon; foregut gastric/proximal-duodenal tissue belongs principally to the celiac root. The independently injected IMA corresponds to hindgut, including descending and sigmoid colon, not the cecum and proximal transverse colon supplied principally by the SMA.
A. neural deficit: pelvic splanchnic pathway injury; observed flow: restored antegrade flow through the native proximal IMA (Why this does not fit)
The first interpretation fits: Affected hindgut sites with preserved midgut responses localize the parasympathetic deficit to pelvic rather than vagal pathways; preserved blood flow does not repair that neural interruption. The second interpretation fails: An occluded proximal IMA plus SMA-injected contrast traveling along the colonic edge into distal branches in reverse identifies collateral filling through the marginal arterial system, not reopened native IMA inflow.
Reasoning steps for option A
Which parasympathetic pathway serves the impaired descending colon and upper rectum?
Descending colon and upper rectum have reduced parasympathetic responses while ileum and ascending colon retain them, localizing injury to pelvic splanchnic hindgut pathways.
Can contrast move antegrade through the proximal IMA that remains occluded?
Antegrade native proximal IMA inflow cannot explain reverse filling from SMA injection through the marginal route while that proximal root remains occluded.
Why can pelvic autonomic injury coexist with perfusion yet not with the proposed antegrade IMA route?
The hindgut-selective deficit supports pelvic splanchnic injury, but an occluded proximal IMA cannot provide restored native antegrade flow.
B. neural deficit: vagal pathway injury; observed flow: retrograde marginal arterial collateral supply (Why this does not fit)
The first interpretation fails: Affected hindgut sites with preserved midgut responses localize the parasympathetic deficit to pelvic rather than vagal pathways; preserved blood flow does not repair that neural interruption. The second interpretation fits: An occluded proximal IMA plus SMA-injected contrast traveling along the colonic edge into distal branches in reverse identifies collateral filling through the marginal arterial system, not reopened native IMA inflow.
Reasoning steps for option B
Can vagal injury spare ileum and ascending colon yet selectively impair the stated hindgut sites?
Vagal injury should affect midgut responses in ileum and ascending colon, which remain preserved here.
What route permits SMA contrast to reach distal IMA branches backward along the colonic edge?
With proximal IMA still occluded, SMA contrast reaching distal IMA branches backward along the colonic edge demonstrates retrograde marginal arterial collateral flow.
What evidence refutes vagal deficit but confirms retrograde collateral perfusion?
Preserved midgut responses oppose vagal injury; reverse distal IMA filling from SMA contrast confirms marginal arterial collaterals.
C. neural deficit: vagal pathway injury; observed flow: restored antegrade flow through the native proximal IMA (Why this does not fit)
The first interpretation fails: Affected hindgut sites with preserved midgut responses localize the parasympathetic deficit to pelvic rather than vagal pathways; preserved blood flow does not repair that neural interruption. The second interpretation fails: An occluded proximal IMA plus SMA-injected contrast traveling along the colonic edge into distal branches in reverse identifies collateral filling through the marginal arterial system, not reopened native IMA inflow.
Reasoning steps for option C
Does a preserved midgut response support assigning the deficit to a damaged vagus?
Vagal injury should affect midgut responses in ileum and ascending colon, which remain preserved here.
Does reverse distal-branch filling indicate a reopened proximal IMA?
Antegrade native proximal IMA inflow cannot explain reverse filling from SMA injection through the marginal route while that proximal root remains occluded.
Why do preserved midgut responses and proximal IMA occlusion reject both claims?
Reduced hindgut responses with spared midgut opposes vagal injury, and reverse filling despite proximal IMA occlusion opposes native antegrade inflow.
The first interpretation fits: Affected hindgut sites with preserved midgut responses localize the parasympathetic deficit to pelvic rather than vagal pathways; preserved blood flow does not repair that neural interruption. The second interpretation fits: An occluded proximal IMA plus SMA-injected contrast traveling along the colonic edge into distal branches in reverse identifies collateral filling through the marginal arterial system, not reopened native IMA inflow.
Reasoning steps for option D
Why do reduced responses confined to descending colon and upper rectum favor pelvic splanchnic injury?
Descending colon and upper rectum have reduced parasympathetic responses while ileum and ascending colon retain them, localizing injury to pelvic splanchnic hindgut pathways.
How does the occluded root distinguish marginal collateral filling from native antegrade inflow?
With proximal IMA still occluded, SMA contrast reaching distal IMA branches backward along the colonic edge demonstrates retrograde marginal arterial collateral flow.
How do separate neural and arterial findings support pelvic injury with marginal collateral flow?
Pelvic splanchnic injury explains the impaired descending colon and upper rectum; SMA-fed marginal vessels preserve perfusion by retrograde filling.
Takeaway: Affected hindgut sites with preserved midgut responses localize the parasympathetic deficit to pelvic rather than vagal pathways; preserved blood flow does not repair that neural interruption. An occluded proximal IMA plus SMA-injected contrast traveling along the colonic edge into distal branches in reverse identifies collateral filling through the marginal arterial system, not reopened native IMA inflow.
A. A: interrupted esophagus with distal fistula; B: continuous esophagus with fistula (Best answer)
The upper pouch establishes interruption in A, while distal gas supports a distal airway communication. Passage into the stomach in B establishes esophageal continuity; demonstrated tracheal communication supports an H-type fistula.
Reasoning steps for option A
Does the upper pouch plus distal bowel gas in A support interruption with a distal airway fistula?
Yes. A catheter coils above the interrupted esophagus, while airway gas can reach the distal gut through a distal tracheoesophageal connection.
Does stomach catheter passage in B rule out the directly visualized tracheal communication?
No. It establishes esophageal continuity, while contrast crossing into trachea independently proves an H-type fistula.
Can this pair account for both A’s gas-filled distal gut and B’s contrast crossing?
Yes. A has atresia with distal fistula, whereas B has a continuous esophagus with an abnormal airway tract.
B. A: interrupted esophagus without fistula; B: continuous esophagus with fistula (Why this does not fit)
The interpretation of B fits, but isolated esophageal atresia without an airway connection does not account for the gas-filled distal gut in A.
Reasoning steps for option B
Can isolated esophageal interruption without fistula explain A’s abdominal gas?
No. Coiling confirms the upper pouch, but without a distal airway connection swallowed air cannot reach stomach and bowel across complete atresia.
Is a continuous esophagus with fistula compatible with B’s two tests?
Yes. The catheter reaches stomach and contrast is seen crossing a separate tract into the trachea.
Why is this proposed combination incomplete despite correctly describing B?
It leaves A’s distal gas unexplained: a distal tracheoesophageal fistula must provide an airway-to-distal-esophagus route.
C. A: interrupted esophagus with distal fistula; B: interrupted esophagus with proximal fistula (Why this does not fit)
The interpretation of A fits. In B, successful catheter passage into the stomach contradicts a complete interruption, while the contrast study establishes an abnormal communication.
Reasoning steps for option C
Do A’s catheter coil and bowel gas support an interrupted esophagus with distal fistula?
Yes. The pouch blocks catheter advancement, and the distal airway connection accounts for gas in stomach and bowel.
Could B have complete interruption with only a proximal fistula when its catheter reaches stomach?
No. Passage to stomach demonstrates an uninterrupted esophageal route, although contrast confirms an additional airway tract.
Which part of this paired proposal conflicts with B’s directly tested continuity?
The proposed atresia in B conflicts with stomach catheter passage; B instead has a continuous esophagus and fistula.
D. A: continuous esophagus with fistula; B: continuous esophagus without fistula (Why this does not fit)
A blind upper pouch is inconsistent with a continuous esophagus in A. In B, direct contrast passage to the trachea documents a communication despite esophageal continuity.
Reasoning steps for option D
Could A have a continuous esophagus despite catheter coiling in a blind upper pouch?
No. The upper pouch documents esophageal interruption, and distal gas indicates an additional distal fistula.
Can B lack a fistula if contrast is directly observed entering its trachea from esophagus?
No. Stomach catheter passage shows continuity, but the visualized contrast crossing establishes an H-type communication.
Why do both proposed anatomy labels fail the two independent studies?
A is interrupted with distal fistula, not continuous; B is continuous with fistula, not fistula-free.
Takeaway: Assess esophageal continuity and airway communication separately. A tube reaching the stomach excludes complete atresia along its course, not an H-type fistula.