
Gastrointestinal
Antacids
Choose antacids by the cation, kidney function, symptom pattern, and interacting medicines while distinguishing brief relief from sustained acid control.
The antacid can relieve heartburn and still be the wrong product for the patient. Start with the ingredient, kidney function, and medication schedule. A familiar bottle can contain a clinically important mineral load.
Acid neutralization happens in the stomach. Drug binding happens in the gut. Toxicity can appear in the blood, brain, heart, or kidneys.
Neutralize existing acid, then ask why symptoms recur
Connect what changed
Make a prediction, then open one question. Earlier answers stay available.
What is an antacid reacting with?
It reacts with acid already present in the stomach lumen, the space inside the stomach.
What did adding base change in the picture?
Some acid particles became neutralization products. The model now contains less unneutralized acid.
Did the action switch off the acid-producing cell?
No. Neutralization happens in the lumen. Acid secretion can continue.
Why can symptoms return?
Newly secreted acid can replenish acid in the lumen after the antacid effect wears off.
Break it down: Neutralizing existing acid does not switch off acid secretion.
Read the complete worked reasoning
What is an antacid reacting with? It reacts with acid already present in the stomach lumen, the space inside the stomach.
What did adding base change in the picture? Some acid particles became neutralization products. The model now contains less unneutralized acid.
Did the action switch off the acid-producing cell? No. Neutralization happens in the lumen. Acid secretion can continue.
Why can symptoms return? Newly secreted acid can replenish acid in the lumen after the antacid effect wears off.
Neutralizing existing acid does not switch off acid secretion.
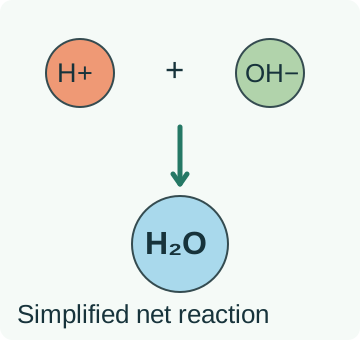
Swipe sideways or use arrow keys to view a wider diagram.
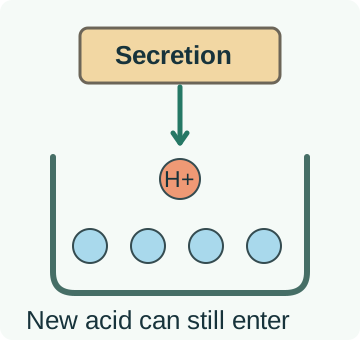
Swipe sideways or use arrow keys to view a wider diagram.
An antacid is a base that reacts with acid already in the gastric lumen. Raising luminal pH can relieve an acid-associated burning sensation and reduce the activity of acid-dependent pepsin. [13] The reaction does not require a drug to bind the parietal-cell histamine receptor or disable the proton pump. That explains the early onset of relief. It also explains why the effect is limited as the stomach empties and further acid is secreted. [1]
Keep three strategies separate. Antacids neutralize existing acid. H2-receptor antagonists reduce histamine-stimulated acid secretion. Proton pump inhibitors suppress secretion at the final pump and have a different administration schedule and treatment role. An antacid may help an occasional symptom, but relief after a dose does not prove GERD, establish an ulcer diagnosis, or demonstrate that mucosal injury has healed. Persistent symptoms need their cause reassessed. [1] [2]
- Stomach contents
Antacid base meets acid. Luminal pH rises and symptoms may improve.
- Intestinal contents
Aluminum, magnesium, or calcium can bind a susceptible oral medicine and reduce the amount absorbed.
- Absorbed mineral load
Some mineral reaches the circulation. Kidney function and total intake influence accumulation.
- Clinical result
Local relief and systemic harm can occur in the same person. A local site of therapeutic action does not mean zero absorption.
Neutralizing capacity depends on the active salt, amount, formulation, and dose. Do not rank every calcium product above every magnesium or aluminum product “per dose” when the doses and formulations differ. Nor should an attractive onset be translated into durable acid suppression. The practical question is whether brief relief is enough for the patient's actual disease. [1] [3] [4]
Read the measurement before drawing a clinical conclusion. Acid-neutralizing capacity is the number of milliequivalents of acid neutralized by a tested dose under a defined procedure. It does not by itself measure onset, symptom duration, suppression of newly secreted acid, systemic absorption, or mucosal healing. [26]
The ingredient predicts the liability
Connect what changed
Make a prediction, then open one question. Earlier answers stay available.
What is the cation?
The cation is the positively charged mineral component, such as magnesium, aluminum, calcium, or sodium.
Why can two antacids change stool differently?
They share acid-neutralizing activity, but their mineral components have different effects in the gut.
What happens when unabsorbed magnesium stays in the bowel?
It retains water in the bowel. More water can make stool loose.
Does a formed stool show that a combination is safe for the kidneys?
No. Stool consistency does not measure mineral absorption or kidney clearance.
Break it down: The same acid benefit can come with different mineral risks.
Read the complete worked reasoning
What is the cation? The cation is the positively charged mineral component, such as magnesium, aluminum, calcium, or sodium.
Why can two antacids change stool differently? They share acid-neutralizing activity, but their mineral components have different effects in the gut.
What happens when unabsorbed magnesium stays in the bowel? It retains water in the bowel. More water can make stool loose.
Does a formed stool show that a combination is safe for the kidneys? No. Stool consistency does not measure mineral absorption or kidney clearance.
The same acid benefit can come with different mineral risks.
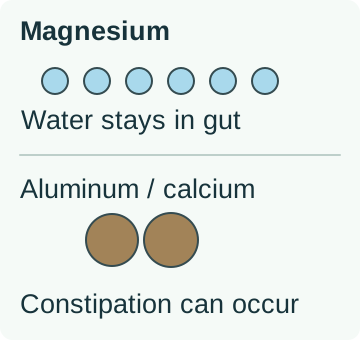
Swipe sideways or use arrow keys to view a wider diagram.
Aluminum hydroxide
Often causes constipation. It binds dietary phosphate, reducing intestinal phosphate absorption. Sustained exposure can produce phosphate depletion. Poor kidney function also increases concern about aluminum accumulation.
Magnesium hydroxide
Unabsorbed magnesium salts retain water in the intestine, so loose stool or diarrhea is a predictable effect. Absorbed magnesium is normally cleared by the kidneys. Advanced kidney disease changes the risk from bothersome diarrhea to systemic toxicity.
Calcium carbonate
Can cause constipation and adds absorbable calcium. Excess calcium and alkali can produce hypercalcemia, metabolic alkalosis, and kidney injury. Include both supplements and antacids when estimating exposure. Higher supplemental calcium intake may increase kidney-stone risk in some settings, so a stone history adds reason to review the total load. [12]
Sodium bicarbonate
Adds sodium and absorbable alkali. Sodium restriction, edema, and alkalosis risk matter. Carbon dioxide generation can cause belching. A household product is still a pharmacologically active exposure.
These are tendencies, not diagnostic proofs based on stool consistency alone. A constipated patient could be taking aluminum, calcium, another constipating medicine, or no antacid at all. Use the ingredient history and appropriate laboratory findings to distinguish them. Hypophosphatemia points toward phosphate binding; a calcium-alkali pattern requires hypercalcemia and alkalosis with renal involvement. [5] [6] [7] [11]
Combining aluminum and magnesium can partially offset their opposite bowel effects. That combination does not cancel mineral absorption, prevent drug binding, or make the product safe for unsupervised use in advanced kidney disease. “Balanced” bowel effects are a formulation feature, not a renal-protection mechanism. The MAG-AL label specifically calls for medical review with kidney disease and prescription medicines. [3]
Read the entire active-ingredient list. Brand names may cover multiple formulations, tablet strengths, and combination products. The amount of calcium carbonate is not the same as the amount of elemental calcium, and the volume of a suspension is not its active-drug mass. Use the units printed on the actual label rather than transferring a tablet count or spoonful count from another product.
Salt mass and elemental mineral are different quantities. When a label states the elemental amount, use that value and add the elemental mineral from every antacid and supplement. Only after calculating the total should you compare it with the patient’s laboratory pattern and risk factors. [4] [12]