A normal-looking cerebrospinal fluid sample does not make meningitis harmless. The first decision is whether treatment or resuscitation must begin before the diagnostic work is complete. Then combine the time course, host, examination and CSF findings to identify what the initial regimen might miss.
Stabilize the patient while preserving the diagnosis Keep treatment and evidence in parallel Read the question, predict, then check the reasoning.
What changes first when meningitis is accompanied by shock?
Reveal this step Resuscitation and effective intravenous antibiotics become immediate priorities.
What evidence can be collected without delaying those priorities?
Reveal this step Obtain blood cultures promptly when collection will not delay treatment.
What happens if lumbar puncture is unsafe right now?
Reveal this step Collect CSF after the contraindication resolves rather than postponing lifesaving care.
Why are these tasks shown beside each other?
Reveal this step Diagnostic yield matters, but treatment does not wait for every test.
Start this reasoning again Sources [1] [3]
Fever, headache, neck stiffness and altered thinking suggest meningeal inflammation, but the full combination is often absent. Infants may instead feed poorly, become irritable or have temperature instability. Older or immunosuppressed adults may have little fever or stiffness. A negative Kernig or Brudzinski sign cannot clear a patient with a concerning history.
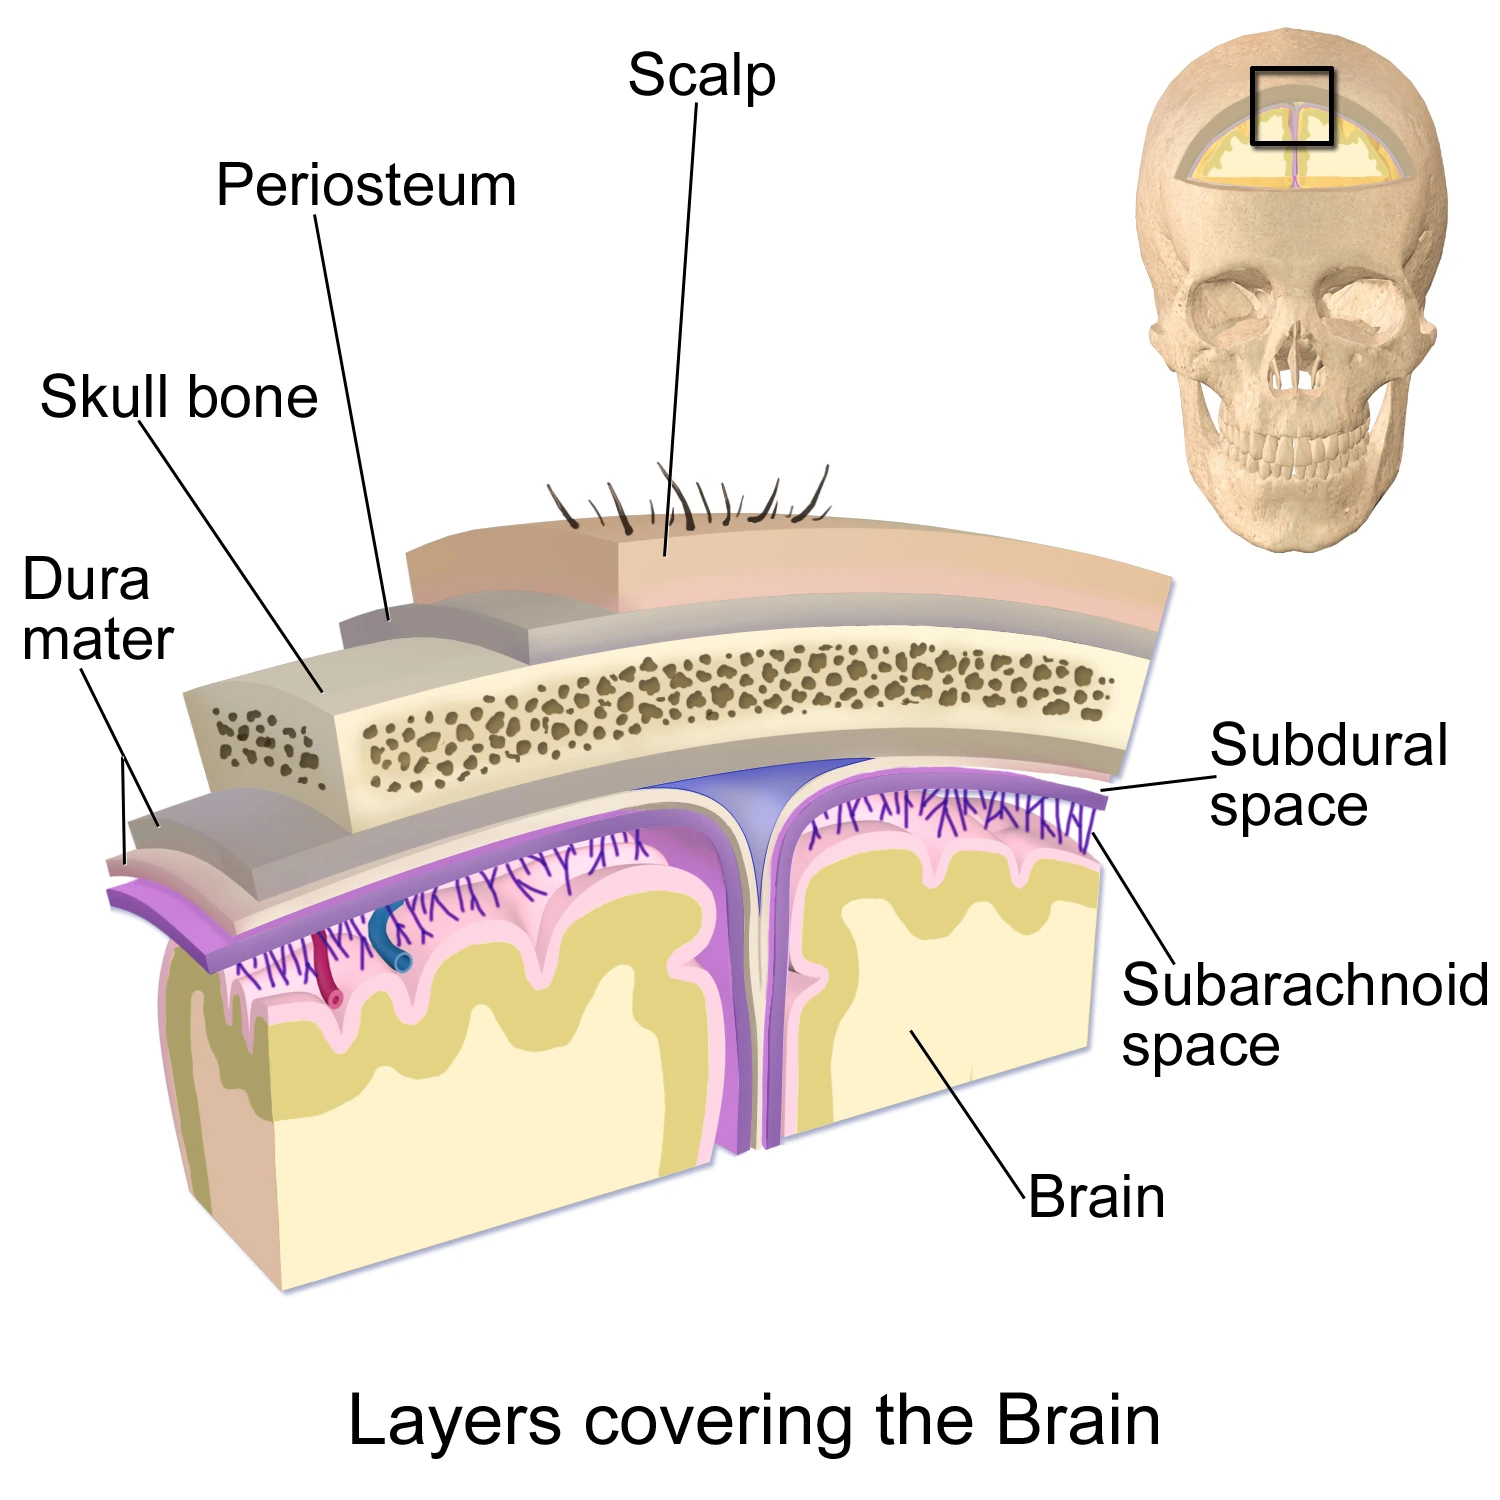
Open whole image Find the fluid-filled space around the brain before interpreting a CSF sample. Image: Blausen.com staff / BruceBlaus (2014). CC BY 3.0 . Original source . Image converted to WebP without resizing.
Whole image Close
Rebuild the emergency handoff Arrange the priorities for a patient with fever, purpura and shock. This is an untimed teaching sequence. Emergency care and prompt cultures run in parallel; collecting a sample must not delay treatment.
Use microbiology to refine ongoing treatment Collect CSF once the procedure is safe Give empiric antibiotics while obtaining prompt blood cultures Recognize the threat and start resuscitation
Try again Read the worked solution Recognize the threat and start resuscitation Support airway, breathing and perfusion while urgently assessing the patient. Do not wait for the full meningeal symptom combination. [1]
Give empiric antibiotics while obtaining prompt blood cultures Antibiotics and resuscitation cannot wait for CT or lumbar puncture. Obtain cultures only if doing so does not delay treatment. [1]
Collect CSF once the procedure is safe Reassess stability, bleeding risk and imaging indications. CSF collected after initial treatment can still be diagnostically useful. [1]
Use microbiology to refine ongoing treatment The evolving syndrome and susceptibility results guide targeted therapy, rather than keeping every empiric drug indefinitely. [1]
For Kernig testing, flex the hip and knee, then gently extend the knee. Pain or resistance is a positive response. With Brudzinski testing, passive neck flexion produces involuntary hip and knee flexion. Both findings support irritation rather than identifying an organism. Avoid forcing the examination in an unstable patient. [12]
Two simultaneous tasks when bacterial meningitis is plausible Protect circulation and brain Assess airway, breathing, perfusion, glucose and seizures. Treat shock and give empiric intravenous antibiotics promptly. Give appropriate adjunctive dexamethasone with the first dose when feasible.
Obtain evidence without delay Obtain blood cultures promptly. Perform lumbar puncture immediately if safe and feasible. If stabilization or imaging must come first, collect CSF afterward when the contraindication resolves.
These tasks run together. A scan appointment, a difficult blood draw or an unavailable lumbar puncture must not become a prerequisite for lifesaving treatment. [1]
New purpura with fever and shock strongly raises concern for meningococcemia. Endotoxin-driven inflammation can produce endothelial injury, disseminated intravascular coagulation and rapidly failing circulation. Other infections can also cause purpura. Waterhouse-Friderichsen syndrome specifically involves adrenal hemorrhage with adrenal insufficiency; a rash alone does not establish it. Use appropriate isolation and treat the sepsis immediately. [3] [13]
Try it here · Checkpoint 1 of 3
Make your prediction before reading the choices. A first attempt is just a starting point.
Case 1
Show answer and explanations for case 1
A. Complete lumbar puncture before antibiotics (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
What makes lumbar puncture unsafe at this moment?
Reveal this step The patient has profound hemodynamic instability.
What must happen instead of waiting for CSF?
Reveal this step Resuscitation and effective intravenous antibiotics must begin promptly.
Start this reasoning again Sources [1] [3]
Read the complete explanation Hemodynamic instability makes lumbar puncture unsafe now, and waiting delays treatment of possible meningococcemia.
B. Wait for a meningococcal PCR result (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
What can meningococcal PCR add to this evaluation?
Reveal this step It can help identify the infecting organism.
Can organism confirmation come before treatment of rapidly progressive shock?
Reveal this step No. Treatment cannot wait for the PCR result.
Start this reasoning again Sources [1] [3]
Read the complete explanation PCR can clarify the organism but cannot be a prerequisite for treating rapidly progressive shock.
C. Give oral rifampin alone (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
Who is oral rifampin commonly meant to protect here?
Reveal this step It is used for selected exposed contacts.
Does contact prophylaxis treat this patient's invasive septic illness?
Reveal this step No. This patient needs intravenous treatment and circulatory support.
Start this reasoning again Sources [1] [3]
Read the complete explanation Rifampin is used for selected contact prophylaxis, not as sole treatment for this invasive septic illness.
D. Begin resuscitation and intravenous ceftriaxone promptly (Best answer)
Reason through this option Read the question, predict, then check the reasoning.
Which findings demand action before diagnostic completion?
Reveal this step Shock and rapidly spreading purpura signal a life-threatening invasive illness.
What two immediate needs run together?
Reveal this step The patient needs circulatory resuscitation and effective intravenous antibiotics.
Which option meets both needs without waiting?
Reveal this step Prompt resuscitation with intravenous ceftriaxone is the best choice.
Start this reasoning again Sources [1] [3]
Read the complete explanation Shock with possible meningococcal disease requires immediate effective antibiotics and circulatory support. Obtain cultures if this does not delay treatment.
Takeaway: Treatment and stabilization take priority when meningitis accompanies shock.
Case sources: [1] [3]
Save this spot
Try a question on this topic A 43-year-old man with HIV and a CD4 count of 45 cells/uL reports 2 weeks of worsening headache and nausea. Lumbar puncture shows an opening pressure of 38 cm H2O, lymphocytic pleocytosis, and a positive cerebrospinal fluid cryptococcal antigen. He has not received antifungal therapy. He has been off antiretroviral therapy for several months. Temperature is 38.2 C and pulse is 102/min. He is alert, has mild neck stiffness, and has no focal neurologic deficit. Serum glucose is 82 mg/dL; cerebrospinal fluid glucose is 40 mg/dL and protein is 65 mg/dL. Head imaging shows no mass lesion. The admitting team plans serial neurologic assessment and management of raised intracranial pressure in addition to antifungal therapy. Renal function and complete blood count will be monitored during treatment. The patient has no known allergy to antifungal drugs and can receive a standard induction combination before subsequent consolidation therapy.
Which induction antifungal regimen is most appropriate?
A. Fluconazole alone B. Amphotericin B alone C. Amphotericin plus flucytosine D. Voriconazole with caspofungin E. Pyrimethamine with sulfadiazine
Choose an answer before revealing the reasoning.
Get one of these every morning · Practice more in the QBank
Decide whether lumbar puncture is safe now Separate imaging need from treatment need Read the question, predict, then check the reasoning.
What question does head imaging answer before puncture?
Reveal this step It assesses possible mass effect when clinical risk findings are present.
Which examination pattern makes imaging first more important?
Reveal this step A focal deficit, papilledema, marked impaired consciousness, or a new adult seizure raises concern.
Can a reassuring scan correct shock or coagulopathy?
Reveal this step No. Procedural safety still depends on the whole patient.
What continues while imaging or stabilization is arranged?
Reveal this step Prompt cultures and empiric treatment continue when bacterial meningitis is plausible.
Start this reasoning again Sources [1] [14]
Explore the reasoning
Why a normal scan is not permission for every puncture
Work through the reasoning
What question does a reassuring CT leave unanswered?
Whether the patient is physiologically stable enough and has no other contraindication to lumbar puncture.
Show all answers
Focus on one step
Earlier step Following step
What has the scan helped assess? A possible intracranial mass effect, not every cause of unsafe lumbar puncture.
What remains abnormal here? Hypotension and inadequate stability. Those do not disappear when an image is reassuring.
What happens to antimicrobial treatment? It continues promptly while resuscitation and further assessment proceed; CSF is collected when safe.
A clear doorway does not make an unstable floor safe to cross. The scan and the patient assessment address different hazards.
Where the comparison stops. This is an organizational comparison, not a substitute for actual lumbar-puncture criteria or clinical assessment.
Assess intracranial risk. Assess systemic stability. Treat promptly; sample when safe. Imaging is one part of procedure safety, not the entire decision.
Sources [1]
Compare both answers Continue stabilization and reassess all contraindications
Why it fits. A scan can address some intracranial risks but does not correct hemodynamic instability. Continue necessary treatment while the procedure is deferred.
A stable patient without an imaging indication may have prompt lumbar puncture; this patient is still unstable.
A normal CT is not a complete safety assessment.
Proceed because normal CT removes all reasons to defer
Why it is tempting. The image does not restore circulation or eliminate bleeding and respiratory risks. These are independent procedural considerations.
Imaging findings and whole-patient stability answer different safety questions.
Assess instability and bleeding risk as well as intracranial findings.
Routine head CT before every lumbar puncture adds delay without answering the central question. Look for a possible intracranial mass effect or other contraindication. WHO recommends imaging first when findings include marked impairment of consciousness, focal neurologic signs, cranial nerve deficits, papilledema, a new adult seizure or severe immunocompromise. Its consciousness threshold is a Glasgow Coma Scale score below 10. Local protocols may use additional criteria. Well-controlled HIV alone is not equivalent to severe immunocompromise. [1]
Scan or sample? An adult with suspected meningitis has a new seizure and focal arm weakness. Imaging is being arranged. Choose the plan that protects treatment without overlooking procedural risk.
Give prompt empiric treatment; defer the puncture pending assessment Wait for CT and CSF results before giving antibiotics Skip assessment and perform lumbar puncture immediately
Try again Read the worked solution Give prompt empiric treatment; defer the puncture pending assessment Best fit. The focal findings and new seizure support imaging before lumbar puncture. Treatment should not be withheld while the scan is arranged. [1]
Wait for CT and CSF results before giving antibiotics Compare this alternative. This makes diagnostic sequencing a treatment delay during a time-sensitive suspected infection. [1]
Skip assessment and perform lumbar puncture immediately Compare this alternative. Focal findings and a new adult seizure require assessment for an intracranial contraindication first. [1]
Hemodynamic or respiratory instability, important bleeding risk and infection over the puncture site are independent reasons to defer the procedure. A reassuring CT does not correct shock, coagulopathy or all causes of raised intracranial pressure. Reassess the whole patient before proceeding. Conversely, headache alone does not prove a dangerous pressure gradient.
Measure opening pressure when feasible, and send CSF cell count with differential, protein, glucose, Gram stain and culture. Obtain a blood glucose close to the puncture. Add pathogen-specific molecular or antigen tests based on the syndrome. Antibiotics may reduce culture yield, but prior treatment does not make subsequent CSF collection useless. Molecular testing and the remaining biochemical pattern may still establish the diagnosis.
A thunderclap headache requires a hemorrhage assessment even without fever. Xanthochromia can support subarachnoid hemorrhage in the appropriate testing sequence, but yellow CSF is not an organism test and is not uniquely caused by bleeding. Markedly increased protein and other conditions can also alter CSF color. The clinical timeline and imaging determine the next investigation. [14]
Save this spot
Read CSF as a pattern with exceptions Read paired values without overcalling them Read the question, predict, then check the reasoning.
Why pair CSF glucose with blood glucose?
Reveal this step The absolute CSF value is harder to interpret when blood glucose is abnormal.
What does the paired calculation produce?
Reveal this step Divide CSF glucose by the nearby blood glucose to obtain the ratio.
What does a ratio at or below 0.4 support?
Reveal this step It supports an abnormal pattern that includes bacterial, fungal, or tuberculous disease in context.
What does a ratio above 0.4 fail to exclude?
Reveal this step It does not safely exclude bacterial meningitis.
Why must the cell differential remain probabilistic?
Reveal this step Early viral disease can be neutrophilic, while Listeria or treated bacterial disease can be lymphocytic.
Start this reasoning again Sources [1]
Typical untreated patterns, not exclusion rules Pattern Cells Glucose and protein Interpretation Pattern Acute bacterialCells Often many neutrophilsGlucose and protein Low glucose ratio, high proteinInterpretation Prompt antibacterial treatmentPattern ViralCells Usually lymphocytes, sometimes early neutrophilsGlucose and protein Usually preserved glucose, modest protein increaseInterpretation Establish cause and exclude dangerous alternativesPattern Tuberculous or fungalCells Often lymphocytes, sometimes few cellsGlucose and protein Often low glucose and high proteinInterpretation Specific microbiology and pressure assessment
Normal adult CSF has very few leukocytes, generally no more than 5 per microliter. Interpret neonatal results using neonatal reference ranges. A paired CSF-to-blood glucose ratio at or below 0.4 is abnormal and supports bacterial, fungal or tuberculous disease in context. Absolute CSF glucose is harder to interpret when blood glucose is abnormal. Barrier dysfunction, altered glucose transport and metabolism by host cells and pathogens all contribute to low CSF glucose. The explanation is broader than organisms consuming sugar. [1]
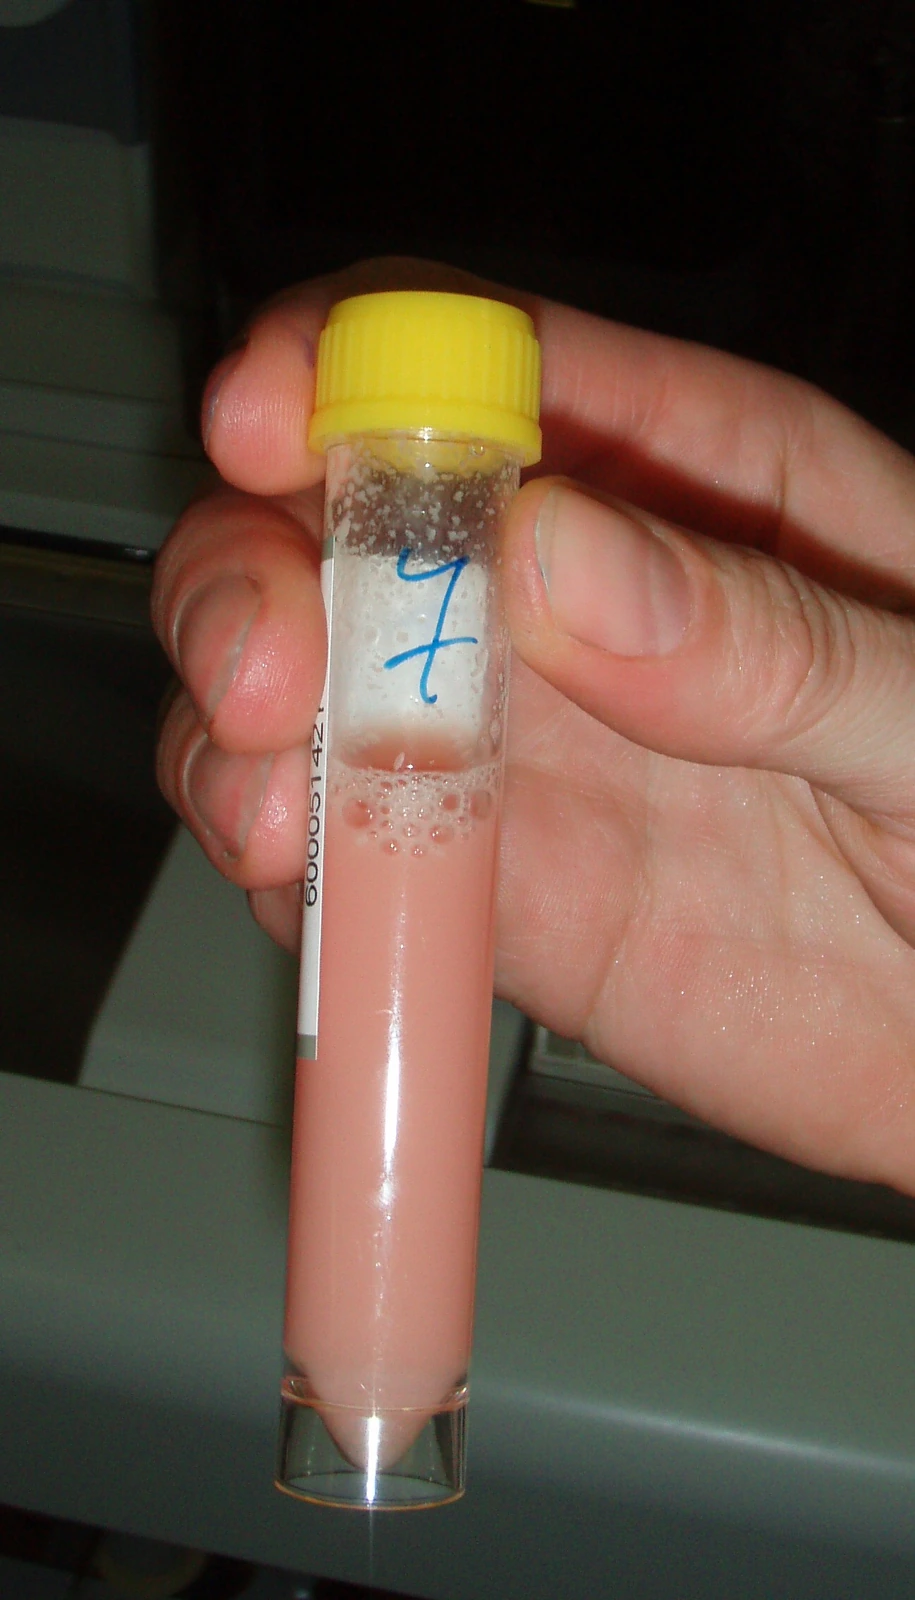
Open whole image This sample is visibly cloudy; appearance alone does not identify a pathogen, and clear fluid does not rule out meningitis. Image: MyName ( Whein ( talk )). CC BY 3.0 de . Original source . Image resized and converted to WebP.
Whole image Close
CSF lab: match the exception Match each result with what it actually permits you to conclude. Pick a result, then its interpretation. A mismatch explains the distinction; nothing is timed.
Neutrophils early in the illness Few CSF cells in advanced immunosuppression CSF glucose 38; blood glucose 190 mg/dL Lymphocyte-predominant CSF
Viral, tuberculous or fungal causes are possible; Listeria and partially treated bacterial disease remain possible too. The ratio is 0.20. Interpret the paired value rather than calling the absolute CSF number reassuring. A weak cell response does not exclude serious infection, including cryptococcal meningitis. Bacterial disease needs assessment, but early viral meningitis can also show neutrophils.
Try again Read the worked solution Neutrophils early in the illness Bacterial disease needs assessment, but early viral meningitis can also show neutrophils. [1]
Few CSF cells in advanced immunosuppression A weak cell response does not exclude serious infection, including cryptococcal meningitis. [1] [2]
CSF glucose 38; blood glucose 190 mg/dL The ratio is 0.20. Interpret the paired value rather than calling the absolute CSF number reassuring. [1]
Lymphocyte-predominant CSF Viral, tuberculous or fungal causes are possible; Listeria and partially treated bacterial disease remain possible too. [1]
Early enteroviral disease can have neutrophils. Listeria and partially treated bacterial disease may have a lymphocytic pattern. Profound immunosuppression may produce cryptococcal meningitis with little pleocytosis. Therefore, normal glucose does not safely exclude bacterial disease, and lymphocytes do not eliminate it. Use microbiology and clinical evolution before narrowing therapy.
Pair the specimen with the question being asked. Gram stain can rapidly suggest bacterial morphology but a negative result is not a rule-out test. Culture provides an isolate for susceptibility testing. A molecular panel is useful only for organisms included in that panel and can also be falsely negative. A positive result must fit the syndrome rather than replace its interpretation.
Try it here · Checkpoint 2 of 3
Make your prediction before reading the choices. A first attempt is just a starting point.
Case 4
Show answer and explanations for case 4
A. The CSF-to-serum ratio is 0.20 and supports abnormal glucose handling (Best answer)
Reason through this option Read the question, predict, then check the reasoning.
How is the paired glucose ratio calculated?
Reveal this step Divide CSF glucose 38 by serum glucose 190.
What ratio does that produce?
Reveal this step The CSF-to-serum glucose ratio is 0.20.
How should 0.20 be interpreted here?
Reveal this step It is markedly low and supports abnormal glucose handling in meningitis.
Start this reasoning again Sources [1]
Read the complete explanation The paired ratio is markedly low. Inflammation, transport changes and cellular metabolism contribute.
B. The glucose is reassuring because it is above 30 mg/dL (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
Why is 38 mg/dL not reassuring by itself?
Reveal this step The simultaneous serum glucose is unusually high at 190 mg/dL.
What comparison reveals the abnormality?
Reveal this step The paired ratio is only 0.20, which is markedly low.
Start this reasoning again Sources [1]
Read the complete explanation An isolated cutoff ignores the high serum glucose and very low paired ratio.
C. Only bacterial consumption can explain the finding (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
Do bacteria alone determine low CSF glucose?
Reveal this step No. Inflammation and altered glucose transport also contribute.
Can this value be reduced to bacterial sugar consumption?
Reveal this step No. That explanation is too narrow for the observed physiology.
Start this reasoning again Sources [1]
Read the complete explanation Host inflammation and altered transport also contribute, and nonbacterial causes can lower CSF glucose.
D. The ratio establishes pneumococcal infection (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
What does a low CSF-to-serum glucose ratio identify?
Reveal this step It identifies an abnormal inflammatory biochemical pattern.
Does that pattern distinguish pneumococcus from every other cause?
Reveal this step No. The ratio does not identify a species.
Start this reasoning again Sources [1]
Read the complete explanation The ratio supports an inflammatory pattern but does not identify a species.
Takeaway: Calculate the paired ratio and keep the organism question separate.
Case sources: [1]
Save this spot
Cover the host-specific gap Find the organism the backbone misses Read the question, predict, then check the reasoning.
What forms the common community-acquired antibacterial backbone?
Reveal this step A third-generation cephalosporin supplies broad CNS-active coverage.
Why is vancomycin often added in United States protocols?
Reveal this step It addresses concern for resistant pneumococcus during empiric treatment.
Which important organism remains outside cephalosporin coverage?
Reveal this step Listeria is the important cephalosporin gap.
Which addition addresses that host-specific gap?
Reveal this step Ampicillin supplies Listeria coverage when relevant risk is present.
What should happen after susceptibility results return?
Reveal this step Narrow the regimen instead of continuing every empiric drug indefinitely.
Start this reasoning again Sources [1] [8]
Explore the reasoning
Broader does not mean complete
Work through the reasoning
What is the missing relationship?
Host factors change the probability of Listeria; that organism changes which empiric drug is needed.
Show all answers
Focus on one step
Earlier step Following step
Which host details matter? The patient is older and immunosuppressed, both relevant to the Listeria assessment.
Why is ceftriaxone not the solution by itself? Listeria is the important cephalosporin gap; escalating that drug does not supply the missing spectrum.
What happens once microbiology returns? Use the organism and susceptibility information to narrow treatment appropriately.
Packing several tools does not help when the task needs a different fitting. Choose the addition for the uncovered organism.
Where the comparison stops. Antimicrobial activity is not binary in every clinical setting; dosing, susceptibility and the infection site still require assessment.
Identify the host risk. Find the coverage gap. Add the appropriate coverage. The missing organism matters more than how broad a regimen sounds.
Sources [1]
Compare both answers The host has Listeria risk and the regimen needs that coverage
Why it fits. Older age and impaired immunity create a specific empiric coverage need. Ampicillin addresses the important cephalosporin gap.
Adding drugs by count is different from checking which organism remains insufficiently covered.
Match each empiric addition to a host-specific organism gap.
Two broad drugs guarantee coverage of every meningeal pathogen
Why it is tempting. Broad activity is not universal activity. The host and the infection site determine what remains missing.
A cephalosporin backbone with resistant-pneumococcal coverage does not remove Listeria risk.
Check spectrum, not the number of antibiotics.
For many children beyond the neonatal period and adults with community-acquired bacterial meningitis, a third-generation cephalosporin such as ceftriaxone is the backbone. Add vancomycin when resistant pneumococcus is a concern, as in common United States empiric protocols. Choose meningitis dosing and adapt to local susceptibility data. Once culture and susceptibility results return, narrow the regimen rather than keeping every empiric drug indefinitely. [1]
Find the antibiotic gap A 74-year-old taking immunosuppressive therapy has suspected bacterial meningitis and is receiving ceftriaxone plus vancomycin. Which additional coverage addresses the host-specific gap?
Add ampicillin for Listeria coverage Increase ceftriaxone alone to cover Listeria Wait for a positive culture before considering Listeria
Try again Read the worked solution Add ampicillin for Listeria coverage Best fit. Older age and impaired immunity increase Listeria concern. A cephalosporin does not provide the needed Listeria coverage. [1]
Increase ceftriaxone alone to cover Listeria Compare this alternative. An important spectrum gap is not repaired simply by increasing a drug that lacks reliable activity against that organism. [1]
Wait for a positive culture before considering Listeria Compare this alternative. Host risk can justify empiric coverage while microbiology is pending. A negative or delayed initial test does not remove that risk. [1]
Listeria is the important cephalosporin gap. Add ampicillin for relevant risk, including older age, pregnancy and impaired immunity. WHO uses age over 60 among its risk criteria; some local protocols use over 50. Alcohol use disorder, cirrhosis and diabetes also affect assessment. The threshold belongs to a guideline, not to a sudden biological change on a birthday. Listeria is a gram-positive rod with intracellular survival and actin-based cell-to-cell spread; tumbling motility at room temperature is a traditional laboratory observation.
Neonates are infants in the first 28 days, not everyone younger than three months. Group B streptococcus, enteric gram-negative organisms including E. coli and Listeria matter in this period. Suspected neonatal meningitis needs a CNS-active neonatal regimen, commonly ampicillin or amoxicillin plus cefotaxime under local guidance. Ampicillin plus gentamicin is familiar for neonatal sepsis, but it should not be treated as an interchangeable default for established CNS infection. Ceftriaxone has neonatal bilirubin and intravenous calcium safety restrictions. [8]
Pneumococcus is an encapsulated, lancet-shaped gram-positive diplococcus. Asplenia, sickle cell disease and some CSF leaks increase invasive disease risk. Meningococcus is a gram-negative diplococcus associated with respiratory spread and outbreaks. Hib remains relevant with incomplete immunization. Age changes probability; it does not identify a pathogen by itself. [3] [10]
Dexamethasone is ideally given before or with the first antibiotic dose. If that opportunity was missed, WHO advises giving it as soon as possible after antibiotics when indicated, rather than declaring all later use futile. Reassess continuation using CSF and the identified organism, with pneumococcal and Hib disease supporting continuation. Neonatal use is not a routine extension of adult practice. [1]
Save this spot
Try these without looking Why does a normal CT not clear every patient for lumbar puncture? It does not correct instability, bleeding risk or every intracranial concern. Assess the whole patient while avoiding treatment delay.
Revisit this explanation [1]
Why can ceftriaxone plus vancomycin still leave an important host-specific coverage gap? Older or immunocompromised patients may need Listeria coverage with ampicillin. The number of antibiotics does not establish complete spectrum.
Revisit this explanation [1]
Does waiting for safer CSF collection mean waiting to start antibiotics? No. Give indicated empiric treatment promptly while stabilizing the patient and arranging the appropriate diagnostic sequence.
Revisit this explanation [1]
When the course is slower, change the tests Let the time course select the test Read the question, predict, then check the reasoning.
What does a course measured in weeks change first?
Reveal this step It increases the importance of chronic fungal, tuberculous, malignant, and inflammatory causes.
Which cryptococcal test outweighs a negative India ink preparation?
Reveal this step A compatible positive CSF cryptococcal antigen supports CNS infection.
What directly treats symptomatic cryptococcal intracranial pressure?
Reveal this step Therapeutic lumbar punctures provide pressure control when appropriate.
Which specimens address suspected tuberculous meningitis?
Reveal this step Send CSF nucleic acid testing and mycobacterial culture.
What cannot wait when HSV encephalitis is plausible?
Reveal this step Begin intravenous acyclovir promptly while confirmation is pending.
Start this reasoning again Sources [2] [6] [7]
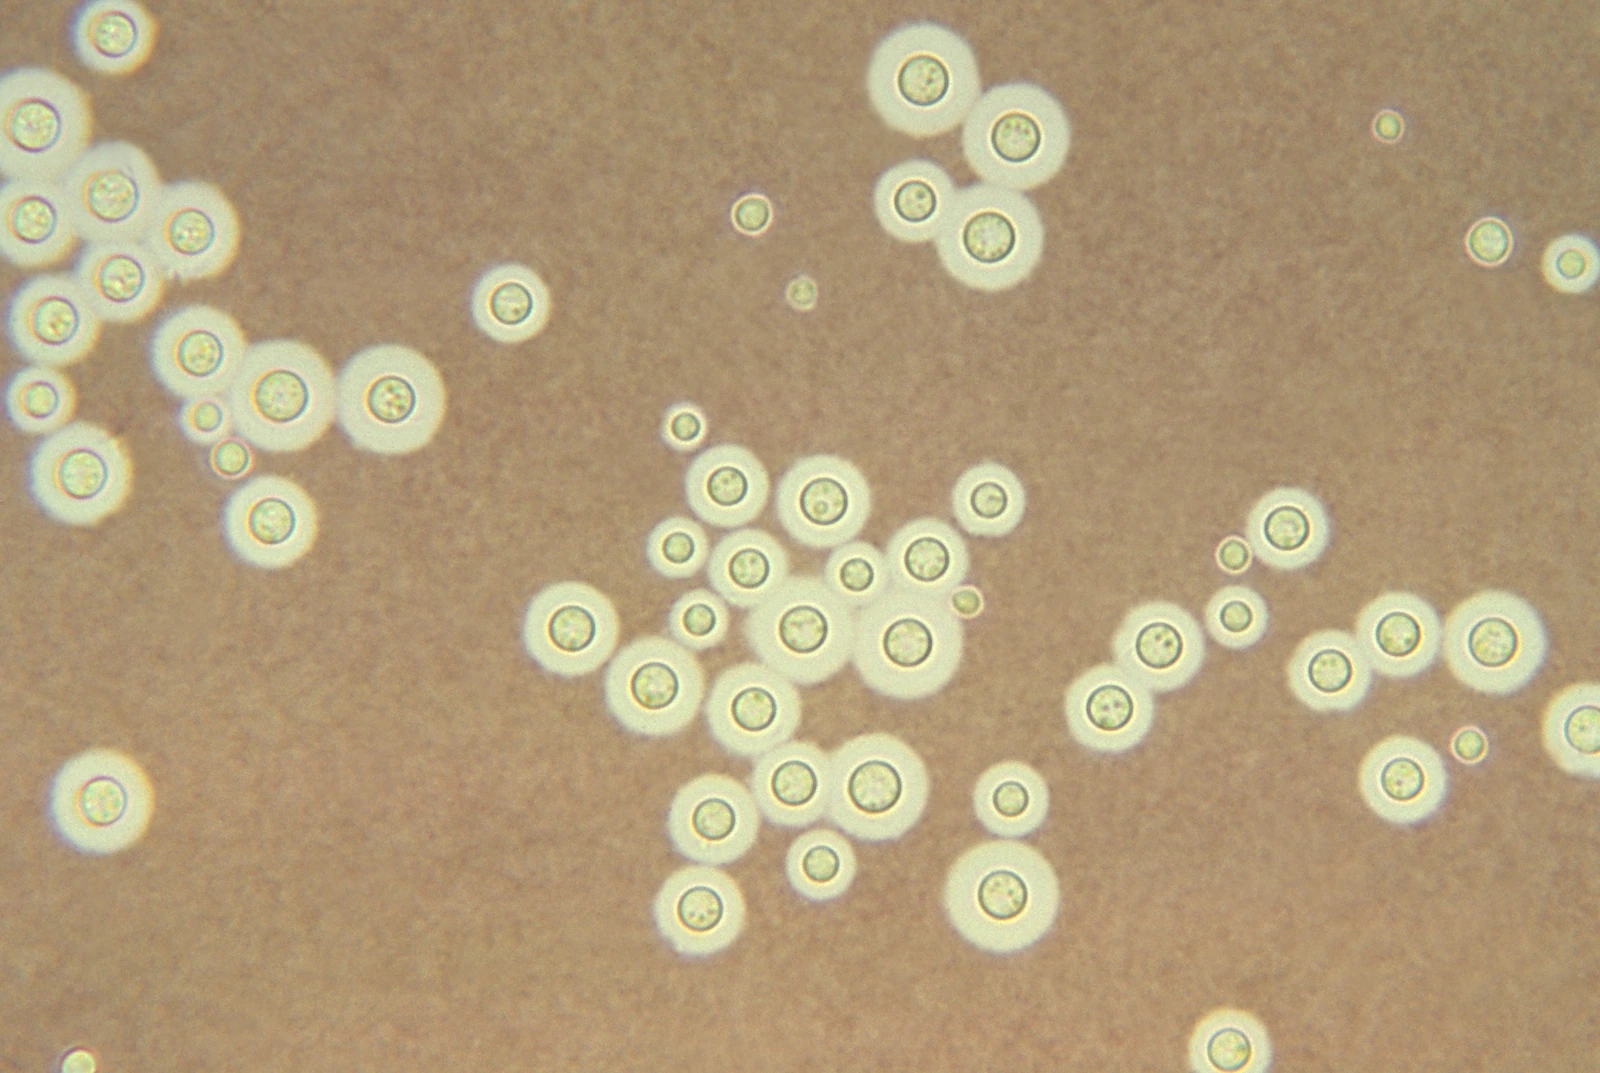
Weeks of headache, visual symptoms and raised opening pressure in advanced HIV suggest cryptococcosis. CSF cryptococcal antigen is more sensitive than India ink. A negative ink preparation therefore does not outweigh a compatible positive antigen result. In a resource-rich setting, HIV-associated CNS disease commonly receives liposomal amphotericin B plus flucytosine induction, then fluconazole consolidation and maintenance. Non-HIV hosts and complicated disease require individualized induction duration. [2]
Open whole image India ink can show the capsule around Cryptococcus; a negative preparation does not exclude infection. Image: Photo Credit: Content Providers(s): CDC/Dr. Leanor Haley. Public domain . Original source . Image resized and converted to WebP.
Whole image Close
Choose the next diagnostic lens Match each presentation with the focused concern or action. These are patterns to investigate, not diagnoses made from one finding.
Advanced HIV, raised pressure, positive CSF cryptococcal antigen Basilar inflammation with cranial nerve palsy Altered behavior, focal seizures and temporal lobe abnormalities Coccidioidal meningitis improving on fluconazole
Clinical improvement does not support stopping treatment; lifelong azole suppression addresses the relapse risk. Suspect encephalitis and start prompt intravenous acyclovir when HSV is plausible. Investigate tuberculosis with CSF molecular testing and culture; a negative single test does not reliably exclude it. CNS cryptococcosis needs antifungal induction and pressure assessment; a negative India ink result does not outweigh the antigen result.
Try again Read the worked solution Advanced HIV, raised pressure, positive CSF cryptococcal antigen CNS cryptococcosis needs antifungal induction and pressure assessment; a negative India ink result does not outweigh the antigen result. [2]
Basilar inflammation with cranial nerve palsy Investigate tuberculosis with CSF molecular testing and culture; a negative single test does not reliably exclude it. [7]
Altered behavior, focal seizures and temporal lobe abnormalities Suspect encephalitis and start prompt intravenous acyclovir when HSV is plausible. [6]
Coccidioidal meningitis improving on fluconazole Clinical improvement does not support stopping treatment; lifelong azole suppression addresses the relapse risk. [11]
Positive CSF cryptococcal antigen represents CNS infection even when symptoms are slight. Fluconazole preemptive therapy for selected isolated serum antigenemia is a different situation. Measure and treat symptomatic intracranial pressure, often with therapeutic lumbar punctures. Routine corticosteroids do not substitute for pressure control. In HIV-associated cryptococcal meningitis, defer ART for approximately four to six weeks after antifungal treatment begins to reduce harmful inflammatory complications. [2]
Basilar meningeal inflammation, cranial nerve palsies, hydrocephalus and low CSF glucose raise concern for tuberculosis. Send CSF nucleic acid amplification testing and mycobacterial culture; a negative smear or molecular test cannot reliably exclude it. Blood IGRA, skin testing and CSF adenosine deaminase do not establish active CNS tuberculosis. Consider malignant meningitis and neurosarcoidosis when appropriate, while pursuing infection urgently. TB meningitis requires multidrug therapy and adjunctive corticosteroids with specialist guidance. [7]
Recurrent aseptic meningitis can be caused by HSV-2. CSF PCR helps identify it. Encephalitis is suggested by sustained altered behavior, seizures or focal brain dysfunction, with temporal involvement particularly suggestive of HSV. Begin intravenous acyclovir promptly when HSV encephalitis is plausible. HSV-2 meningitis can also need antiviral treatment; calling recurrent episodes self-limited does not justify ignoring a severe new episode. Enteroviruses commonly cause meningitis treated supportively after bacterial disease is adequately assessed. [6]
Geography can refine chronic meningitis testing. Coccidioidal meningitis after exposure in an endemic region generally requires fluconazole-based treatment and lifelong azole suppression because relapse is common after stopping therapy. Do not copy the cryptococcal induction sequence onto every fungal meningitis. [11]
Try it here · Checkpoint 3 of 3
Make your prediction before reading the choices. A first attempt is just a starting point.
Case 13
Show answer and explanations for case 13
A. Start ART before the first antifungal dose (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
What remains high before the first antifungal dose?
Reveal this step The CNS fungal burden remains untreated.
Why can immediate immune restoration be dangerous?
Reveal this step It can provoke harmful inflammation in the infected CNS.
Start this reasoning again Sources [2]
Read the complete explanation Untreated CNS fungal burden makes immediate immune restoration hazardous.
B. Wait until the full year of maintenance is complete (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
How long is ART generally deferred here?
Reveal this step The delay is usually about four to six weeks.
Is the full maintenance year the intended delay?
Reveal this step No. That would postpone essential HIV treatment far too long.
Start this reasoning again Sources [2]
Read the complete explanation The recommended delay is measured in weeks, not the entire maintenance course.
C. Avoid ART permanently because of IRIS risk (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
Is ART still needed after cryptococcal treatment begins?
Reveal this step Yes. It is essential for long-term immune recovery.
Does inflammatory risk justify permanent avoidance?
Reveal this step No. It changes timing rather than eliminating ART.
Start this reasoning again Sources [2]
Read the complete explanation ART remains essential for long-term survival and immune recovery.
D. Generally defer ART for four to six weeks after antifungal initiation (Best answer)
Reason through this option Read the question, predict, then check the reasoning.
What complication drives special ART timing in CNS cryptococcosis?
Reveal this step Early immune restoration can trigger harmful intracranial inflammation.
What must begin before immune restoration?
Reveal this step Effective antifungal therapy must begin first.
What timing balances those needs?
Reveal this step Generally start ART four to six weeks after antifungal initiation.
Start this reasoning again Sources [2]
Read the complete explanation Early CNS inflammatory deterioration is a particular concern in cryptococcal meningitis.
Takeaway: ART timing depends on the opportunistic infection and its anatomic site.
Case sources: [2]
Save this spot
Practice the diagnostic and treatment decisions
Case 2
Show answer and explanations for case 2
A. Wait for symptoms to persist for 24 hours (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
Has this acute syndrome already crossed the threshold for evaluation?
Reveal this step Yes. Fever with meningismus needs urgent evaluation now.
What would a 24-hour wait add?
Reveal this step It would add delay without making the current syndrome safer.
Start this reasoning again Sources [1]
Read the complete explanation The acute syndrome already warrants urgent evaluation and treatment.
B. Use a normal neurologic examination to exclude meningitis (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
What does the normal focal examination tell us?
Reveal this step It lowers concern for a focal mass effect indication.
Does it rule out meningeal infection?
Reveal this step No. Meningitis can occur without focal neurologic deficits.
Start this reasoning again Sources [1]
Read the complete explanation A normal focal examination does not exclude meningeal infection.
C. Obtain blood cultures and perform prompt lumbar puncture without routine CT (Best answer)
Reason through this option Read the question, predict, then check the reasoning.
Which imaging warning findings are absent?
Reveal this step There is no focal deficit, papilledema, seizure, severe immunocompromise, or instability.
What diagnostic sample is immediately available?
Reveal this step Blood cultures and CSF can be obtained promptly.
What sequence preserves yield without routine delay?
Reveal this step Obtain blood cultures and perform lumbar puncture without routine CT.
Start this reasoning again Sources [1]
Read the complete explanation There is no stated imaging indication. Prompt CSF collection preserves diagnostic yield without delaying treatment.
D. Require CT before every lumbar puncture (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
Does every suspected meningitis case require CT before puncture?
Reveal this step No. Imaging is reserved for specific safety concerns.
What would automatic CT do in this low-risk presentation?
Reveal this step It would delay CSF collection and potentially delay treatment.
Start this reasoning again Sources [1]
Read the complete explanation Routine imaging in this low-risk presentation creates unnecessary delay.
Takeaway: Screen for imaging indications rather than ordering CT automatically.
Case sources: [1]
Case 3
Show answer and explanations for case 3
A. Give dexamethasone alone until CSF is obtained (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
What role does dexamethasone have in bacterial meningitis?
Reveal this step It is an adjunct that limits harmful inflammation.
Can an anti-inflammatory adjunct eradicate bacteria?
Reveal this step No. It cannot replace prompt antimicrobial therapy.
Start this reasoning again Sources [1]
Read the complete explanation An adjunct cannot replace antimicrobial treatment of suspected bacterial meningitis.
B. Obtain blood cultures if prompt and give empiric antibiotics (Best answer)
Reason through this option Read the question, predict, then check the reasoning.
Why is imaging needed before lumbar puncture?
Reveal this step The new seizure and focal weakness suggest a possible intracranial contraindication.
Which treatment must not wait for that scan?
Reveal this step Empiric intravenous antibiotics must begin promptly.
When should blood cultures be collected?
Reveal this step Before antibiotics only when prompt collection will not delay treatment.
Start this reasoning again Sources [1]
Read the complete explanation Focal findings and severe immunocompromise justify imaging first, but not delaying antibacterial therapy.
C. Perform lumbar puncture to avoid reduced culture yield (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
Why is pretreatment CSF usually valuable?
Reveal this step It can improve microbiologic yield before antibiotics.
Why does that benefit not control this decision?
Reveal this step Possible intracranial mass effect makes immediate puncture unsafe.
Start this reasoning again Sources [1]
Read the complete explanation Possible mass effect makes immediate puncture inappropriate despite the value of pretreatment CSF.
D. Withhold antibiotics until imaging excludes a mass (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
What question will CT help answer?
Reveal this step It helps assess whether lumbar puncture may be unsafe.
What question does CT not need to answer first?
Reveal this step It need not confirm infection before urgent antibiotics begin.
Start this reasoning again Sources [1]
Read the complete explanation Imaging determines procedural safety; it does not determine whether urgent infection treatment can begin.
Takeaway: Imaging can precede puncture while antibiotics precede imaging.
Case sources: [1]
Case 5
Show answer and explanations for case 5
A. Neutrophils prove bacterial meningitis (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
Which diseases can produce early CSF neutrophils?
Reveal this step Bacterial meningitis and early viral meningitis can both do so.
Do neutrophils alone prove a bacterial cause?
Reveal this step No. They raise probability but are not organism proof.
Start this reasoning again Sources [1]
Read the complete explanation They favor that pattern but occur early in viral meningitis too.
B. Normal glucose permits immediate discontinuation of empiric antibiotics (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
Can bacterial meningitis ever have preserved CSF glucose?
Reveal this step Yes. CSF patterns overlap, especially early in disease.
Is normal glucose enough to stop empiric antibiotics now?
Reveal this step No. It cannot safely exclude bacterial infection by itself.
Start this reasoning again Sources [1]
Read the complete explanation That biochemical result alone is insufficient to safely narrow treatment.
C. A negative Gram stain proves there are no bacteria (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
What does a negative Gram stain mean?
Reveal this step No bacteria were visualized in that specimen.
Why is that not a bacterial rule-out?
Reveal this step Gram stain sensitivity varies with organism burden and prior treatment.
Start this reasoning again Sources [1]
Read the complete explanation Gram stain sensitivity is incomplete and depends on organism burden and prior treatment.
D. Early viral disease is possible, but bacterial meningitis remains under evaluation (Best answer)
Reason through this option Read the question, predict, then check the reasoning.
Which findings allow an early viral possibility?
Reveal this step Early illness, preserved glucose, and neutrophilic CSF can occur in viral meningitis.
Which findings fail to exclude bacterial disease?
Reveal this step Preserved glucose and a negative Gram stain are not definitive rule-outs.
What conclusion keeps both facts intact?
Reveal this step Viral disease is possible while bacterial meningitis remains under evaluation.
Start this reasoning again Sources [1]
Read the complete explanation Early viral infection may be neutrophilic; normal glucose and negative Gram stain do not independently exclude bacterial disease.
Takeaway: A CSF pattern guides probability rather than functioning as a rule-out test.
Case sources: [1]
Case 6
Show answer and explanations for case 6
A. Fluconazole (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
What type of pathogen does fluconazole target?
Reveal this step It is an antifungal drug used for susceptible fungal disease.
What uncovered threat is created by this patient's host risk?
Reveal this step The missing empiric coverage is for Listeria, a bacterium.
Start this reasoning again Sources [1]
Read the complete explanation There is no evidence of an azole-susceptible fungal cause to replace the missing antibacterial coverage.
B. Azithromycin (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
Is azithromycin the standard CNS-active drug for Listeria meningitis?
Reveal this step No. A macrolide is not the standard addition for this gap.
What does this regimen still need?
Reveal this step It needs an active Listeria agent such as ampicillin.
Start this reasoning again Sources [1]
Read the complete explanation A macrolide is not the standard CNS-active addition for suspected Listeria meningitis.
C. Ampicillin (Best answer)
Reason through this option Read the question, predict, then check the reasoning.
Which host features increase concern for Listeria?
Reveal this step Older age and diabetes raise the concern in this case.
Does ceftriaxone reliably cover Listeria?
Reveal this step No. Cephalosporins leave an important Listeria gap.
Which added drug closes that gap?
Reveal this step Ampicillin supplies the needed Listeria coverage.
Start this reasoning again Sources [1]
Read the complete explanation Older age and diabetes raise Listeria risk; ampicillin supplies coverage missing from ceftriaxone.
D. Metronidazole (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
What organisms is metronidazole mainly chosen to cover?
Reveal this step It is mainly used for anaerobic organisms in appropriate syndromes.
Does that match the host-specific meningitis gap?
Reveal this step No. It does not supply the needed Listeria coverage.
Start this reasoning again Sources [1]
Read the complete explanation Anaerobic coverage does not address the specific Listeria gap in this community-acquired syndrome.
Takeaway: Identify the empiric coverage gap using host risk.
Case sources: [1]
Case 7
Show answer and explanations for case 7
A. Ceftriaxone alone supplies reliable targeted treatment (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
Which organism fits small gram-positive rods in this host?
Reveal this step Listeria is strongly supported by the morphology and immunosuppression.
Why is ceftriaxone alone inadequate?
Reveal this step Listeria is intrinsically resistant to cephalosporins.
Start this reasoning again Sources [1]
Read the complete explanation Listeria is intrinsically resistant to cephalosporins; a susceptible active agent such as ampicillin is needed.
B. Listeria remains likely despite the lymphocyte predominance (Best answer)
Reason through this option Read the question, predict, then check the reasoning.
Can Listeria meningitis have lymphocyte-predominant CSF?
Reveal this step Yes. Its cell differential is not always classically neutrophilic.
What additional evidence points toward Listeria?
Reveal this step Prednisone exposure and small gram-positive rods support it.
What interpretation best integrates the pattern?
Reveal this step Listeria remains likely despite the lymphocyte predominance.
Start this reasoning again Sources [1]
Read the complete explanation The host and rod morphology fit Listeria; its CSF differential need not be classically neutrophilic.
C. The differential excludes any bacterial cause (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
Is a lymphocytic CSF pattern unique to nonbacterial disease?
Reveal this step No. Listeria and partially treated bacterial meningitis can show it.
Can the differential exclude bacteria in this patient?
Reveal this step No. The Gram stain directly supports a bacterial rod.
Start this reasoning again Sources [1]
Read the complete explanation Lymphocytes cannot exclude Listeria or partially treated bacterial meningitis.
D. The rods identify Cryptococcus (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
What microbial form is Cryptococcus?
Reveal this step Does yeast match small gram-positive bacterial rods?
Reveal this step No. The reported morphology points away from Cryptococcus.
Start this reasoning again Sources [1]
Read the complete explanation Cryptococcus is a yeast, not a small gram-positive bacterial rod.
Takeaway: Microbiology and host risk can outweigh a stereotyped cell differential.
Case sources: [1]
Case 8
Show answer and explanations for case 8
A. Ampicillin plus cefotaxime under neonatal guidance (Best answer)
Reason through this option Read the question, predict, then check the reasoning.
Which pathogen gap must a neonatal regimen cover?
Reveal this step Listeria is one important neonatal meningitis pathogen.
What additional coverage does cefotaxime provide?
Reveal this step It supplies neonatal CNS coverage for susceptible gram-negative organisms.
Which regimen combines those needs?
Reveal this step Ampicillin plus cefotaxime under neonatal guidance fits the case.
Start this reasoning again Sources [8]
Read the complete explanation This covers Listeria and supplies a cephalosporin with neonatal CNS use for susceptible gram-negative organisms.
B. Ceftriaxone alone as for an otherwise healthy adult (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
What key neonatal pathogen does ceftriaxone miss?
Reveal this step It does not cover Listeria.
Why else is ceftriaxone not the adult-like default here?
Reveal this step Neonates have bilirubin and intravenous calcium safety restrictions.
Start this reasoning again Sources [8]
Read the complete explanation It misses Listeria and has important neonatal bilirubin and calcium safety restrictions.
C. Oral amoxicillin alone (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
What treatment route does suspected neonatal meningitis require?
Reveal this step It requires prompt intravenous therapy.
Why is oral amoxicillin alone insufficient?
Reveal this step It is neither the appropriate route nor broad enough empirically.
Start this reasoning again Sources [8]
Read the complete explanation Suspected neonatal meningitis requires intravenous treatment and broader initial coverage.
D. Gentamicin alone (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
Can gentamicin alone provide reliable meningitis treatment?
Reveal this step No. Aminoglycoside monotherapy has important CNS penetration limits.
What is missing from gentamicin monotherapy?
Reveal this step A CNS-active neonatal combination covering the major likely pathogens.
Start this reasoning again Sources [8]
Read the complete explanation Aminoglycoside monotherapy is inadequate for empiric neonatal meningitis, including its CNS penetration limitations.
Takeaway: A sepsis mnemonic cannot replace a neonatal meningitis regimen.
Case sources: [8]
Case 9
Show answer and explanations for case 9
A. Escherichia coli (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
What Gram reaction and shape define E. coli?
Reveal this step E. coli is a gram-negative rod.
Does that match gram-positive cocci with group B antigen?
Reveal this step No. The isolate is incompatible with E. coli.
Start this reasoning again Sources [8] [15]
Read the complete explanation E. coli is a gram-negative rod, incompatible with the described isolate.
B. Listeria monocytogenes (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
What bacterial shape does Listeria have?
Reveal this step Listeria is a gram-positive rod.
Does it carry group B streptococcal antigen?
Reveal this step No. The isolate's coccal shape and antigen point elsewhere.
Start this reasoning again Sources [8] [15]
Read the complete explanation Listeria is a gram-positive rod rather than a group B streptococcus.
C. Neisseria meningitidis (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
What morphology is typical of meningococcus?
Reveal this step It is a gram-negative diplococcus.
How does that compare with this isolate?
Reveal this step This isolate is gram-positive and has group B streptococcal antigen.
Start this reasoning again Sources [8] [15]
Read the complete explanation Meningococcus is a gram-negative diplococcus and lacks group B streptococcal antigen.
D. Streptococcus agalactiae (Best answer)
Reason through this option Read the question, predict, then check the reasoning.
Which organism is called group B streptococcus?
Reveal this step Streptococcus agalactiae is group B streptococcus.
Which isolate findings support that identity?
Reveal this step Beta hemolysis, catalase negativity, and group B antigen support it.
What is the best identification?
Reveal this step The neonatal isolate is Streptococcus agalactiae.
Start this reasoning again Sources [8] [15]
Read the complete explanation Group B antigen and the neonatal syndrome identify GBS.
Takeaway: Use actual isolate characteristics rather than age alone.
Case sources: [8] [9]
Case 10
Show answer and explanations for case 10
A. The positive antigen indicates only prior exposure (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
Where was cryptococcal antigen detected?
Reveal this step It was detected in the cerebrospinal fluid.
What does CSF antigen mean in this compatible syndrome?
Reveal this step It supports active CNS infection, not merely prior exposure.
Start this reasoning again Sources [2]
Read the complete explanation Positive CSF antigen in this setting supports CNS infection, not a harmless exposure marker.
B. Normalizing pressure alone will eradicate the infection (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
What problem does therapeutic pressure control address?
Reveal this step It relieves symptomatic intracranial hypertension.
What problem does drainage not eradicate?
Reveal this step It does not eliminate the underlying fungal infection.
Start this reasoning again Sources [2]
Read the complete explanation Pressure control is essential but must accompany effective antifungal treatment.
C. Treat cryptococcal CNS disease despite the negative ink preparation (Best answer)
Reason through this option Read the question, predict, then check the reasoning.
Which test is more sensitive in CSF, antigen or India ink?
Reveal this step Cryptococcal antigen is more sensitive than India ink.
Does a negative less-sensitive test cancel a positive stronger test?
Reveal this step No. The negative ink preparation does not negate positive CSF antigen.
What treatment conclusion follows?
Reveal this step Treat cryptococcal CNS disease and manage the raised pressure.
Start this reasoning again Sources [2]
Read the complete explanation CSF antigen is more sensitive than India ink, and the subacute high-pressure syndrome is compatible.
D. The ink result excludes cryptococcosis (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
Can India ink miss cryptococcal meningitis?
Reveal this step Yes. It can be negative when organism burden is lower.
What evidence outweighs the negative ink here?
Reveal this step Positive CSF antigen with a compatible high-pressure syndrome.
Start this reasoning again Sources [2]
Read the complete explanation India ink can miss infection, especially with lower organism burden.
Takeaway: A less sensitive negative test does not negate a compatible positive CrAg.
Case sources: [2]
Case 11
Show answer and explanations for case 11
A. Immediate ART without antifungal therapy (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
Does antiretroviral therapy kill Cryptococcus?
Reveal this step No. ART restores immunity but is not antifungal treatment.
Why is immediate ART alone hazardous here?
Reveal this step Untreated CNS infection can worsen with an abrupt inflammatory response.
Start this reasoning again Sources [2]
Read the complete explanation ART does not eradicate Cryptococcus and can worsen inflammatory complications in untreated CNS disease.
B. CNS-directed antifungal induction (Best answer)
Reason through this option Read the question, predict, then check the reasoning.
What does positive CSF cryptococcal antigen establish?
Reveal this step It establishes cryptococcal involvement of the central nervous system.
Are headaches required for CNS infection to exist?
Reveal this step No. CNS infection may be present without prominent symptoms.
Which treatment category matches the involved compartment?
Reveal this step CNS-directed antifungal induction is appropriate.
Start this reasoning again Sources [2]
Read the complete explanation Positive CSF antigen identifies CNS involvement even without prominent symptoms.
C. Preemptive fluconazole for isolated serum antigenemia only (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
When is a serum-only preemptive pathway considered?
Reveal this step It applies after CNS disease has been excluded.
Has CNS disease been excluded in this patient?
Reveal this step No. The CSF antigen is positive.
Start this reasoning again Sources [2]
Read the complete explanation That pathway requires exclusion of CNS disease, which this puncture has demonstrated.
D. Observation until headache appears (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
Does absence of headache make positive CSF antigen harmless?
Reveal this step No. The laboratory result identifies CNS infection.
What is the risk of waiting for symptoms?
Reveal this step Untreated cryptococcal CNS disease may progress.
Start this reasoning again Sources [2]
Read the complete explanation Waiting permits untreated CNS infection to progress.
Takeaway: Asymptomatic CNS infection is still CNS infection.
Case sources: [2]
Case 12
Show answer and explanations for case 12
A. Therapeutic CSF drainage with repeat lumbar punctures as indicated (Best answer)
Reason through this option Read the question, predict, then check the reasoning.
What measured finding explains the recurrent severe headache?
Reveal this step Opening pressure is markedly elevated at 36 cm H2O.
What intervention directly removes excess CSF pressure?
Reveal this step Therapeutic lumbar puncture drains cerebrospinal fluid.
What plan fits recurrent symptomatic pressure?
Reveal this step Repeat therapeutic drainage as clinically indicated.
Start this reasoning again Sources [2]
Read the complete explanation Repeated drainage is a central treatment for symptomatic cryptococcal intracranial hypertension.
B. Routine dexamethasone instead of drainage (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
Are corticosteroids routine pressure therapy in cryptococcal meningitis?
Reveal this step No. Routine dexamethasone can cause harm in this setting.
What directly addresses the measured pressure instead?
Reveal this step Therapeutic CSF drainage addresses it.
Start this reasoning again Sources [2]
Read the complete explanation Steroids are not routine pressure treatment for cryptococcal meningitis and can cause harm.
C. Stop antifungals because headache proves drug toxicity (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
What objective disease finding accompanies the headache?
Reveal this step The opening pressure is 36 cm H2O.
Does that finding prove antifungal toxicity?
Reveal this step No. It supports disease-related intracranial hypertension requiring treatment.
Start this reasoning again Sources [2]
Read the complete explanation Raised opening pressure provides a disease-related explanation requiring management, not automatic withdrawal.
D. Use acetazolamide instead of CSF drainage (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
What is the established direct treatment for symptomatic cryptococcal pressure?
Reveal this step Therapeutic lumbar puncture with CSF drainage.
Can acetazolamide replace that drainage?
Reveal this step No. It is not recommended as a substitute here.
Start this reasoning again Sources [2]
Read the complete explanation Acetazolamide is not recommended as a substitute for therapeutic drainage in cryptococcal intracranial hypertension.
Takeaway: Antifungal activity and intracranial pressure control are separate therapeutic needs.
Case sources: [2]
Case 14
Show answer and explanations for case 14
A. CSF adenosine deaminase alone (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
Can CSF adenosine deaminase establish CNS tuberculosis alone?
Reveal this step No. Its diagnostic accuracy is insufficient by itself.
What testing should directly target the suspected organism?
Reveal this step CSF molecular testing and mycobacterial culture should be used.
Start this reasoning again Sources [7]
Read the complete explanation ADA is insufficiently specific and sensitive to establish this diagnosis by itself.
B. One negative CSF acid-fast smear to exclude TB (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
Why may a CSF acid-fast smear be negative in TB meningitis?
Reveal this step CNS tuberculosis can contain few organisms in the specimen.
Can one negative smear exclude this compatible syndrome?
Reveal this step No. Its sensitivity is too limited.
Start this reasoning again Sources [7]
Read the complete explanation Smear sensitivity is poor in paucibacillary CNS infection.
C. CSF mycobacterial nucleic acid testing plus culture (Best answer)
Reason through this option Read the question, predict, then check the reasoning.
Which compartment is clinically involved?
Reveal this step The meninges and cerebrospinal fluid compartment are involved.
Which tests seek organism evidence in that compartment?
Reveal this step CSF nucleic acid testing and mycobacterial culture do so.
What added value does culture provide?
Reveal this step It can support susceptibility assessment despite its slow yield.
Start this reasoning again Sources [7]
Read the complete explanation These test the affected compartment; culture also supports susceptibility assessment. Negative results still need clinical interpretation.
D. Blood IGRA alone (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
What does a blood IGRA detect?
Reveal this step It detects immune sensitization to tuberculosis antigens.
Does sensitization prove active infection in the CNS?
Reveal this step No. It cannot establish active TB meningitis.
Start this reasoning again Sources [7]
Read the complete explanation IGRA indicates immune sensitization and cannot establish active CNS disease.
Takeaway: Investigate active CNS tuberculosis in CSF rather than substituting a sensitization test.
Case sources: [7]
Case 15
Show answer and explanations for case 15
A. A noninfectious headache because the glucose is normal (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
Is preserved CSF glucose compatible with viral meningitis?
Reveal this step Yes. Viral meningitis often preserves CSF glucose.
What finding proves this is more than a noninfectious headache?
Reveal this step The CSF is inflamed and contains HSV-2 DNA.
Start this reasoning again Sources [6]
Read the complete explanation Normal glucose is compatible with viral meningitis and does not erase CSF inflammation.
B. HSV-2 meningitis (Best answer)
Reason through this option Read the question, predict, then check the reasoning.
Which compartment do headache, photophobia, and neck stiffness implicate?
Reveal this step They indicate meningeal irritation.
What identifies the likely infectious cause?
Reveal this step CSF PCR detects HSV-2 during the episode.
What diagnosis integrates recurrence without sustained brain dysfunction?
Reveal this step HSV-2 meningitis best fits.
Start this reasoning again Sources [6]
Read the complete explanation Recurrent aseptic meningeal episodes with compatible CSF PCR fit HSV-2; severity still guides antiviral care.
C. HSV encephalitis solely because HSV DNA is present (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
What distinguishes encephalitis from meningitis?
Reveal this step Encephalitis requires sustained brain dysfunction such as altered behavior, seizures, or focal deficits.
Is that brain dysfunction present here?
Reveal this step No. A positive HSV test alone does not establish encephalitis.
Start this reasoning again Sources [6]
Read the complete explanation Encephalitis requires evidence of brain dysfunction, not merely a positive viral test.
D. Untreated pneumococcal meningitis established by recurrence (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
What organism was actually detected in CSF?
Reveal this step HSV-2 was detected by PCR.
Does the recurrent lymphocytic pattern establish pneumococcus?
Reveal this step No. It supports the detected viral cause instead.
Start this reasoning again Sources [6]
Read the complete explanation The recurrent pattern and positive HSV-2 PCR do not establish pneumococcus.
Takeaway: Distinguish meningeal inflammation from encephalitic brain dysfunction.
Case sources: [6]
Case 16
Show answer and explanations for case 16
A. Intravenous acyclovir (Best answer)
Reason through this option Read the question, predict, then check the reasoning.
Which findings indicate inflammation of brain tissue?
Reveal this step Personality change, focal seizures, and temporal MRI abnormalities indicate encephalitis.
Which treatable cause is especially suggested by temporal involvement?
Reveal this step HSV encephalitis is strongly suggested.
What should begin before PCR returns?
Reveal this step Intravenous acyclovir should begin promptly.
Start this reasoning again Sources [6] [16]
Read the complete explanation The encephalitic syndrome is concerning for HSV and warrants treatment before PCR confirmation.
B. Oral rifampin alone (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
What is oral rifampin used for in meningococcal care?
Reveal this step It is used for selected contact prophylaxis.
Does that role match suspected HSV brain infection?
Reveal this step No. It does not treat HSV encephalitis.
Start this reasoning again Sources [6] [16]
Read the complete explanation Contact prophylaxis does not treat suspected HSV encephalitis.
C. Fluconazole as the sole empiric agent (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
What pattern would make a fungal syndrome more likely?
Reveal this step A subacute course with organism-specific evidence would be needed.
What does this acute temporal syndrome favor instead?
Reveal this step It favors HSV encephalitis requiring acyclovir.
Start this reasoning again Sources [6] [16]
Read the complete explanation The acute temporal encephalitic pattern points toward HSV rather than an isolated fungal syndrome.
D. Supportive care only until PCR returns (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
Is the suspected cause treatable before confirmation?
Reveal this step Yes. HSV encephalitis has effective intravenous antiviral therapy.
Why not wait for PCR?
Reveal this step Delay risks preventable neurologic injury.
Start this reasoning again Sources [6] [16]
Read the complete explanation Delay risks neurologic injury when treatable HSV encephalitis is strongly suspected.
Takeaway: Treat plausible HSV encephalitis while the diagnostic result is pending.
Case sources: [6]
Case 17
Show answer and explanations for case 17
A. Any prior antibiotic dose permanently rules out dexamethasone (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
When is dexamethasone ideally given?
Reveal this step It is ideally given before or with the first antibiotic dose.
Does a brief missed window create a permanent prohibition?
Reveal this step No. WHO permits prompt later administration when otherwise indicated.
Start this reasoning again Sources [1]
Read the complete explanation That categorical rule is stricter than current WHO guidance.
B. Delay further antibiotics until a steroid dose has circulated (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
Which treatment directly eradicates suspected bacteria?
Reveal this step Antibiotics directly treat the bacterial infection.
Should antibiotic dosing wait for the adjunct?
Reveal this step No. Steroid logistics must not delay antibacterial therapy.
Start this reasoning again Sources [1]
Read the complete explanation Antibiotic timing should not be sacrificed to the adjunct.
C. Continue dexamethasone for every organism regardless of results (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
What should determine dexamethasone continuation?
Reveal this step CSF findings and the identified organism should guide it.
Is continuation automatic for every organism?
Reveal this step No. The adjunct should be reassessed when results return.
Start this reasoning again Sources [1]
Read the complete explanation CSF findings and the identified pathogen should guide continuation.
D. Give dexamethasone as soon as possible if otherwise indicated (Best answer)
Reason through this option Read the question, predict, then check the reasoning.
Was dexamethasone given at the ideal time?
Reveal this step No. Ceftriaxone was given a few minutes earlier.
What does WHO allow after that short delay?
Reveal this step Give dexamethasone as soon as possible if it remains indicated.
Which choice follows that guidance without delaying antibiotics?
Reveal this step Administer the steroid promptly now.
Start this reasoning again Sources [1]
Read the complete explanation Before or with antibiotics is ideal, but a short delay is not an absolute prohibition.
Takeaway: Ideal timing should not be misrepresented as an absolute late-dose ban.
Case sources: [1]
Case 18
Show answer and explanations for case 18
A. It should become lifelong maintenance treatment (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
What is dexamethasone's role in this infection?
Reveal this step It is a short adjunctive treatment for inflammatory injury.
Does that role require lifelong maintenance?
Reveal this step No. It is not chronic suppressive therapy.
Start this reasoning again Sources [1]
Read the complete explanation Adjunctive meningitis treatment is a short course, not chronic suppression.
B. Continue it indefinitely if CSF protein remains elevated (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
Can CSF protein remain abnormal during recovery?
Reveal this step Yes. A laboratory abnormality can outlast the initial treatment window.
Does elevated protein justify indefinite steroid exposure?
Reveal this step No. It does not define a maintenance indication.
Start this reasoning again Sources [1]
Read the complete explanation Persistent protein elevation is not an indication for prolonged steroid maintenance after the short adjunctive course.
C. Pneumococcal identification supports completing the indicated short adjunctive course (Best answer)
Reason through this option Read the question, predict, then check the reasoning.
Which organism was confirmed?
Reveal this step The culture confirmed susceptible pneumococcus.
Does pneumococcal meningitis support continued adjunctive corticosteroids?
Reveal this step Yes. It supports completing the indicated short course.
What is the appropriate interpretation?
Reveal this step Complete the short adjunctive course while continuing effective antibiotics.
Start this reasoning again Sources [1]
Read the complete explanation This is one of the etiologies for which continuing adjunctive corticosteroids is supported.
D. It replaces the need for antibacterial therapy after culture identification (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
What does dexamethasone change?
Reveal this step It modifies the host inflammatory response.
What can it not do to pneumococcus?
Reveal this step It cannot eradicate the organism or replace antibiotics.
Start this reasoning again Sources [1]
Read the complete explanation The steroid limits inflammation but does not eradicate pneumococcus.
Takeaway: Reassess adjunctive therapy when the pathogen becomes known.
Case sources: [1]
Case 19
Show answer and explanations for case 19
A. Wait for a throat culture before considering prophylaxis (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
What decision is already supported by household exposure?
Reveal this step The student qualifies for prompt prophylaxis assessment.
Should a throat culture delay that prevention?
Reveal this step No. Carriage testing is not a prerequisite.
Start this reasoning again Sources [4] [5]
Read the complete explanation Carriage testing should not delay indicated prophylaxis.
B. Prompt assessment and provision of indicated antibiotic prophylaxis (Best answer)
Reason through this option Read the question, predict, then check the reasoning.
Does household exposure count as close contact?
Reveal this step Yes. It is a qualifying meningococcal exposure.
Does prior vaccination remove all exposure risk?
Reveal this step No. Vaccination and antibiotic prophylaxis serve different purposes.
What should happen now?
Reveal this step Provide prompt assessment and indicated antibiotic prophylaxis.
Start this reasoning again Sources [4] [5]
Read the complete explanation Household exposure qualifies despite vaccination because the interventions are complementary.
C. No action because vaccination eliminates the need for prophylaxis (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
What protection does meningococcal vaccination provide?
Reveal this step It reduces risk from covered meningococcal types.
Why is prophylaxis still needed after household exposure?
Reveal this step Vaccination does not replace immediate postexposure antibiotic prevention.
Start this reasoning again Sources [4] [5]
Read the complete explanation Vaccination does not remove the recommendation after qualifying exposure.
D. A full intravenous meningitis regimen despite no symptoms (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
Does the student have symptoms of invasive meningococcal disease?
Reveal this step No symptoms are described.
What intensity of treatment fits an asymptomatic exposed contact?
Reveal this step Prophylaxis fits, not a full intravenous meningitis regimen.
Start this reasoning again Sources [4] [5]
Read the complete explanation An asymptomatic contact generally needs prophylaxis rather than treatment for established invasive disease.
Takeaway: Vaccination status does not cancel prophylaxis after qualifying meningococcal exposure.
Case sources: [4] [5]
Case 20
Show answer and explanations for case 20
A. The intubating nurse with direct secretion exposure (Best answer)
Reason through this option Read the question, predict, then check the reasoning.
Which procedure created direct oral secretion exposure?
Reveal this step The unprotected emergency intubation did.
Why does that exposure matter?
Reveal this step Meningococcus can spread through respiratory and oral secretions.
Who therefore needs prophylaxis assessment?
Reveal this step The intubating nurse with direct secretion exposure.
Start this reasoning again Sources [4]
Read the complete explanation Unprotected airway procedures with secretion exposure meet the relevant occupational risk pattern.
B. Only the nurse who delivered the meal (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
What exposure occurred during meal delivery?
Reveal this step Only routine room contact is described.
Does routine care without secretion exposure qualify here?
Reveal this step No. The intubating nurse has the relevant exposure.
Start this reasoning again Sources [4]
Read the complete explanation Routine care without secretion exposure is not the qualifying exposure described here.
C. Neither because transmission occurs only in households (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
Can health care workers have qualifying meningococcal exposure?
Reveal this step Yes. Direct respiratory secretion exposure can qualify.
Which worker had that exposure?
Reveal this step The nurse who performed unprotected intubation.
Start this reasoning again Sources [4]
Read the complete explanation Health care personnel can qualify when directly exposed to respiratory secretions.
D. Both solely because they entered the room (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
Is entering the same room enough for prophylaxis?
Reveal this step No. Prophylaxis depends on the nature of exposure.
How do the two nurses differ?
Reveal this step Only one had direct contact with oral secretions.
Start this reasoning again Sources [4]
Read the complete explanation Room entry without a qualifying exposure does not by itself establish a prophylaxis indication.
Takeaway: The nature of secretion exposure matters more than the job title.
Case sources: [4]
Case 21
Show answer and explanations for case 21
A. Give ciprofloxacin regardless of susceptibility trends (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
What local finding changes ciprofloxacin reliability?
Reveal this step Local meningococcal isolates are ciprofloxacin-resistant.
Should a resistant drug be used automatically?
Reveal this step No. Prophylaxis must reflect local susceptibility guidance.
Start this reasoning again Sources [5]
Read the complete explanation Local resistance is directly relevant to prophylactic efficacy.
B. Substitute a meningococcal vaccine as the sole immediate intervention (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
What immediate problem follows a qualifying exposure?
Reveal this step The contact may already carry the organism.
Can vaccination replace postexposure antibiotics?
Reveal this step No. The two interventions address different prevention needs.
Start this reasoning again Sources [5]
Read the complete explanation Vaccination does not replace antibiotics after qualifying exposure.
C. Select prophylaxis based only on the contact’s vaccine history (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
Does vaccine history determine antibiotic susceptibility?
Reveal this step No. It does not predict local ciprofloxacin resistance.
What should guide prophylactic drug choice?
Reveal this step Current local resistance recommendations should guide it.
Start this reasoning again Sources [5]
Read the complete explanation A qualifying contact needs effective antibiotic prophylaxis irrespective of vaccination, and local resistance remains relevant.
D. Use a recommended alternative such as ceftriaxone according to local guidance (Best answer)
Reason through this option Read the question, predict, then check the reasoning.
Why is ciprofloxacin unreliable in this setting?
Reveal this step Local resistant meningococcal cases have been identified.
What property must the selected prophylaxis have?
Reveal this step It must remain effective against the local strains.
Which choice follows that requirement?
Reveal this step Use a recommended alternative such as ceftriaxone.
Start this reasoning again Sources [5]
Read the complete explanation Resistance can make the usual oral ciprofloxacin option unreliable.
Takeaway: Contact prophylaxis must account for local resistance.
Case sources: [5]
Case 22
Show answer and explanations for case 22
A. A gram-negative outer membrane endotoxin (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
What Gram reaction was observed?
Reveal this step The organism is gram-positive.
Can a gram-positive pneumococcus have a gram-negative outer membrane?
Reveal this step No. That structure does not fit this isolate.
Start this reasoning again Sources [10]
Read the complete explanation The isolate is gram-positive and does not possess that outer membrane.
B. A beta-lactamase that destroys complement proteins (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
What is pneumococcus's usual penicillin resistance mechanism?
Reveal this step It mainly uses altered penicillin-binding proteins, not beta-lactamase.
Does beta-lactamase explain the invasive risk after splenectomy?
Reveal this step No. Capsule-mediated evasion of clearance does.
Start this reasoning again Sources [10]
Read the complete explanation Pneumococcal invasive risk is linked to capsule-mediated clearance resistance; beta-lactamase is neither its usual resistance mechanism nor a complement-destroying enzyme.
C. A polysaccharide capsule that impairs phagocytic clearance (Best answer)
Reason through this option Read the question, predict, then check the reasoning.
Which bacterial structure impairs phagocytic clearance?
Reveal this step The pneumococcal polysaccharide capsule does.
Which organ is especially important for clearing encapsulated bacteria?
Reveal this step The spleen is especially important.
Why is this organism dangerous after splenectomy?
Reveal this step Loss of splenic clearance magnifies the capsule's antiphagocytic effect.
Start this reasoning again Sources [10]
Read the complete explanation Splenic clearance is especially important for encapsulated organisms such as pneumococcus.
D. An obligate intracellular growth requirement (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
Must pneumococcus grow inside host cells?
Reveal this step No. It is not an obligate intracellular organism.
What feature better explains invasive disease in asplenia?
Reveal this step Its polysaccharide capsule resists phagocytic clearance.
Start this reasoning again Sources [10]
Read the complete explanation Pneumococcus is not an obligate intracellular organism.
Takeaway: Host splenic function and bacterial capsule interact to determine invasive risk.
Case sources: [10]
Case 23
Show answer and explanations for case 23
A. It replaces evaluation of fever in the newborn (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
What does maternal screening assess?
Reveal this step It assesses maternal group B streptococcal colonization near delivery.
Does a negative screen make newborn fever safe?
Reveal this step No. A symptomatic newborn still needs urgent evaluation.
Start this reasoning again Sources [9]
Read the complete explanation A symptomatic newborn still needs urgent assessment regardless of maternal screening.
B. It guides intrapartum prophylaxis to reduce early-onset newborn infection (Best answer)
Reason through this option Read the question, predict, then check the reasoning.
When is group B streptococcal screening performed?
Reveal this step It is performed at 36 or 37 weeks of pregnancy.
What action can a positive result guide?
Reveal this step It guides maternal antibiotic prophylaxis during labor.
Which disease period does that strategy reduce?
Reveal this step It reduces early-onset newborn group B streptococcal infection.
Start this reasoning again Sources [9]
Read the complete explanation Colonization status near delivery informs maternal antibiotics during labor.
C. It eliminates all late-onset GBS meningitis (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
Which disease period is targeted by intrapartum prophylaxis?
Reveal this step It mainly targets early-onset neonatal disease.
Does it prevent every later infant infection?
Reveal this step No. Late-onset GBS meningitis can still occur.
Start this reasoning again Sources [9]
Read the complete explanation Intrapartum prophylaxis does not prevent every later infant infection.
D. It diagnoses fetal meningitis before delivery (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
What body site does maternal screening sample?
Reveal this step It samples maternal colonization sites, not fetal cerebrospinal fluid.
Can it diagnose fetal meningitis?
Reveal this step No. It guides prevention rather than diagnosing fetal CNS infection.
Start this reasoning again Sources [9]
Read the complete explanation A maternal screening specimen assesses colonization, not fetal CSF infection.
Takeaway: Prevention of early-onset GBS disease is not universal protection throughout infancy.
Case sources: [9]
Case 24
Show answer and explanations for case 24
A. Waterhouse-Friderichsen syndrome (Best answer)
Reason through this option Read the question, predict, then check the reasoning.
What two adrenal findings are present?
Reveal this step There is bilateral adrenal hemorrhage with acute adrenal insufficiency.
Which invasive infection accompanies them?
Reveal this step The patient has meningococcemia with shock and DIC.
What named complication combines these findings?
Reveal this step This is Waterhouse-Friderichsen syndrome.
Start this reasoning again Sources [3] [13]
Read the complete explanation The combination of adrenal hemorrhage and adrenal insufficiency establishes the named complication.
B. SIADH (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
What organ is structurally injured on imaging?
Reveal this step Both adrenal glands are hemorrhagic.
Does SIADH explain adrenal hemorrhagic destruction?
Reveal this step No. SIADH is a water-balance disorder.
Start this reasoning again Sources [3] [13]
Read the complete explanation SIADH concerns inappropriate water retention and does not account for hemorrhagic adrenal destruction.
C. Subdural empyema (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
Where is the demonstrated hemorrhage?
Reveal this step It is in the adrenal glands.
Does a subdural empyema explain adrenal insufficiency?
Reveal this step No. It is an intracranial purulent collection.
Start this reasoning again Sources [3] [13]
Read the complete explanation An intracranial purulent collection does not explain the adrenal imaging findings.
D. Uncomplicated viral meningitis (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
Is this illness confined to uncomplicated meningeal inflammation?
Reveal this step No. It includes invasive bloodstream infection, DIC, shock, and adrenal injury.
Can uncomplicated viral meningitis account for that pattern?
Reveal this step No. The systemic destructive findings contradict it.
Start this reasoning again Sources [3] [13]
Read the complete explanation The invasive bloodstream infection, DIC and adrenal injury are incompatible with that description.
Takeaway: Do not diagnose adrenal hemorrhage from a purpuric rash alone.
Case sources: [3] [13]
Case 25
Show answer and explanations for case 25
A. Reassurance that defervescence excludes neurologic complications (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
What has improved during recovery?
Reveal this step Fever and cognition have improved.
Does improvement in those areas prove normal hearing?
Reveal this step No. Hearing impairment can persist independently.
Start this reasoning again Sources [1]
Read the complete explanation Resolution of fever does not establish normal hearing or cognitive function.
B. Wait until another infection occurs before assessing hearing (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
When did the conversation difficulty appear?
Reveal this step It is present during the current recovery period.
Should assessment wait for another infection?
Reveal this step No. The symptom warrants evaluation now.
Start this reasoning again Sources [1]
Read the complete explanation The current symptom warrants assessment during recovery.
C. Restart broad antibiotics solely because hearing is impaired (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
Does hearing difficulty prove bacteria are still present?
Reveal this step No. It can be a sequela after infection control.
Should broad antibiotics be restarted from this symptom alone?
Reveal this step No. The symptom calls for hearing assessment instead.
Start this reasoning again Sources [1]
Read the complete explanation Hearing loss alone does not demonstrate ongoing susceptible bacterial infection or justify empiric retreatment.
D. Formal hearing assessment and review of neurologic recovery (Best answer)
Reason through this option Read the question, predict, then check the reasoning.
Which new functional problem is reported?
Reveal this step The patient struggles to follow conversation.
What complication can cause that difficulty after meningitis?
Reveal this step Persistent hearing impairment can do so.
What follow-up directly evaluates it?
Reveal this step Formal hearing testing with neurologic recovery review.
Start this reasoning again Sources [1]
Read the complete explanation Hearing impairment can persist despite microbiologic and systemic improvement.
Takeaway: Recovery assessment includes hearing and function, not only infection markers.
Case sources: [1]
Case 26
Show answer and explanations for case 26
A. Use only intermittent antibacterial prophylaxis (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
What type of organism causes coccidioidal meningitis?
Reveal this step Coccidioides is a fungus.
Can antibacterial prophylaxis suppress this CNS infection?
Reveal this step No. It does not target the fungal cause.
Start this reasoning again Sources [11]
Read the complete explanation Antibacterial prophylaxis does not suppress Coccidioides.
B. Stop once the first headache-free week occurs (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
Does early headache relief prove CNS eradication?
Reveal this step No. Clinical improvement can occur before relapse risk is gone.
What happens when suppressive therapy is stopped?
Reveal this step Coccidioidal meningitis commonly relapses.
Start this reasoning again Sources [11]
Read the complete explanation Symptom improvement does not demonstrate durable eradication of CNS coccidioidomycosis.
C. Continue lifelong azole suppression with specialist follow-up (Best answer)
Reason through this option Read the question, predict, then check the reasoning.
What long-term behavior characterizes coccidioidal meningitis?
Reveal this step It commonly relapses after antifungal therapy is stopped.
Which drug class provides ongoing suppression?
Reveal this step Azole antifungal therapy provides suppression.
What plan addresses the relapse risk?
Reveal this step Continue lifelong azole suppression with specialist follow-up.
Start this reasoning again Sources [11]
Read the complete explanation Coccidioidal meningitis commonly relapses if antifungal suppression is stopped.
D. Stop after the short induction used for uncomplicated candidemia (Why this does not fit)
Reason through this option Read the question, predict, then check the reasoning.
Is candidemia the same infection as coccidioidal meningitis?
Reveal this step No. They involve different fungi and disease compartments.
Can a short candidemia course define this CNS treatment?
Reveal this step No. Coccidioidal meningitis requires organism-specific long-term suppression.
Start this reasoning again Sources [11]
Read the complete explanation A bloodstream Candida duration cannot be transferred to chronic coccidioidal CNS infection.
Takeaway: Fungal meningitis treatment must be organism-specific.
Case sources: [11]