Urea cycle: localize the block and protect the brain
Follow nitrogen through the urea cycle, localize defects with citrulline and orotate, and act quickly during hyperammonemic crises.
A rising ammonia concentration is a brain emergency, not merely an abnormal chemistry value. The fastest safe approach is to recognize the physiologic pattern, stop catabolism, and localize the disrupted step while treatment is already underway. [2]
Recognize the crisis before localization is complete
A newborn who feeds poorly, vomits, becomes sleepy, and then hyperventilates may be showing early hyperammonemia. Hyperventilation often produces respiratory alkalosis, whereas a large anion-gap acidosis with ketosis points more strongly toward an organic acidemia. [2]
Use a concrete comparison: ammonia 420 micromol/L, pH 7.53, low PCO2, absent ketones, and no major anion gap form a different pattern from ketotic acidosis. The first pattern requires an immediate urea-cycle evaluation while sepsis and other causes are assessed in parallel. [2]
Before reading further, classify three findings as crisis signals or localization findings: altered consciousness, urine orotate, and plasma citrulline. Altered consciousness determines urgency; orotate and citrulline help identify the site of failure after emergency care begins.
Reveal the urgency rule
A symptomatic patient with a markedly abnormal result should receive ammonia-lowering treatment without waiting for a genetic label. A questionable mild result from difficult collection or delayed processing should be repeated promptly under validated handling, but uncertainty is not a reason to ignore symptoms. [2]
Ammonia drives astrocytic glutamine accumulation, which contributes to cell swelling and cerebral edema. Neurologic decline can therefore accelerate even while the exact inherited or acquired cause remains unknown. [2]
Transfer this rule beyond infancy: partial defects can first appear after illness, fasting, surgery, the peripartum period, or a large protein load. A previously healthy adolescent or adult can therefore have a genuine cycle disorder. [2][3]
Try it here · Checkpoint 1 of 3
Make your prediction before reading the choices. A first attempt is just a starting point.
Case 1
Show answer and explanations for case 1
A. Diabetic ketoacidosis requiring insulin before any ammonia-directed therapy (Why this does not fit)
The tachypnea and altered consciousness can resemble metabolic decompensation. The alkalemic pH, absent ketones, and marked hyperammonemia argue against ketoacidosis and require a different emergency plan.
Reasoning steps for option A
Why might a vomiting, tachypneic, drowsy newborn prompt thoughts of ketoacidosis?
Rapid breathing with vomiting and falling alertness is the familiar picture of Kussmaul respiration in diabetic ketoacidosis.
What do the pH of 7.53 and the absent urine ketones show about the breathing?
The blood is alkalemic with no ketones, so the fast breathing is primary hyperventilation driven by ammonia, not compensation for an acid load.
B. Sepsis alone, with ammonia treatment deferred until cultures identify an organism (Why this does not fit)
Sepsis can cause poor feeding and encephalopathy in a newborn. The respiratory alkalosis and severe ammonia abnormality still require immediate parallel treatment rather than waiting for culture results.
Reasoning steps for option B
Why is sepsis a reasonable worry in this 3-day-old?
Vomiting, lethargy and poor feeding in the first days of life are common presentations of neonatal sepsis, so cultures and antibiotics are appropriate.
Why can ammonia treatment not wait for the culture report?
At 420 micromol/L with declining consciousness, brain injury accrues by the hour, so ammonia-lowering therapy runs alongside antibiotics rather than after them.
C. A suspected urea-cycle crisis requiring catabolism reversal, ammonia-lowering therapy, and simultaneous diagnostic sampling (Best answer)
Early hyperventilation with respiratory alkalosis is characteristic of severe hyperammonemia. The neurologic decline and ammonia concentration justify urgent treatment while amino acids, urine orotate, and other causes are assessed.
Reasoning steps for option C
What does hyperventilation with a pH of 7.53 suggest in a vomiting newborn?
Early hyperventilation with respiratory alkalosis is characteristic of severe hyperammonemia.
Why must treatment start before the exact urea-cycle defect is known?
The neurologic decline and ammonia concentration justify urgent treatment while amino acids, urine orotate, and other causes are assessed.
D. An isolated respiratory infection suitable for outpatient repeat testing after feeding improves (Why this does not fit)
Tachypnea could initially suggest pulmonary illness. Somnolence plus marked hyperammonemia makes outpatient observation unsafe even if lung findings are mild.
Reasoning steps for option D
Why might fast breathing in a newborn first suggest a respiratory infection?
Tachypnea is the most common sign of neonatal pneumonia, and a low PCO2 can look like simple overbreathing from lung irritation.
Which findings rule out sending this baby home for later testing?
A somnolent newborn with an ammonia of 420 micromol/L has a neurologic emergency that needs inpatient treatment within hours, whatever the chest shows.
Takeaway: Respiratory alkalosis with marked hyperammonemia in a deteriorating newborn is an emergency pattern that should be treated before the exact defect is known.
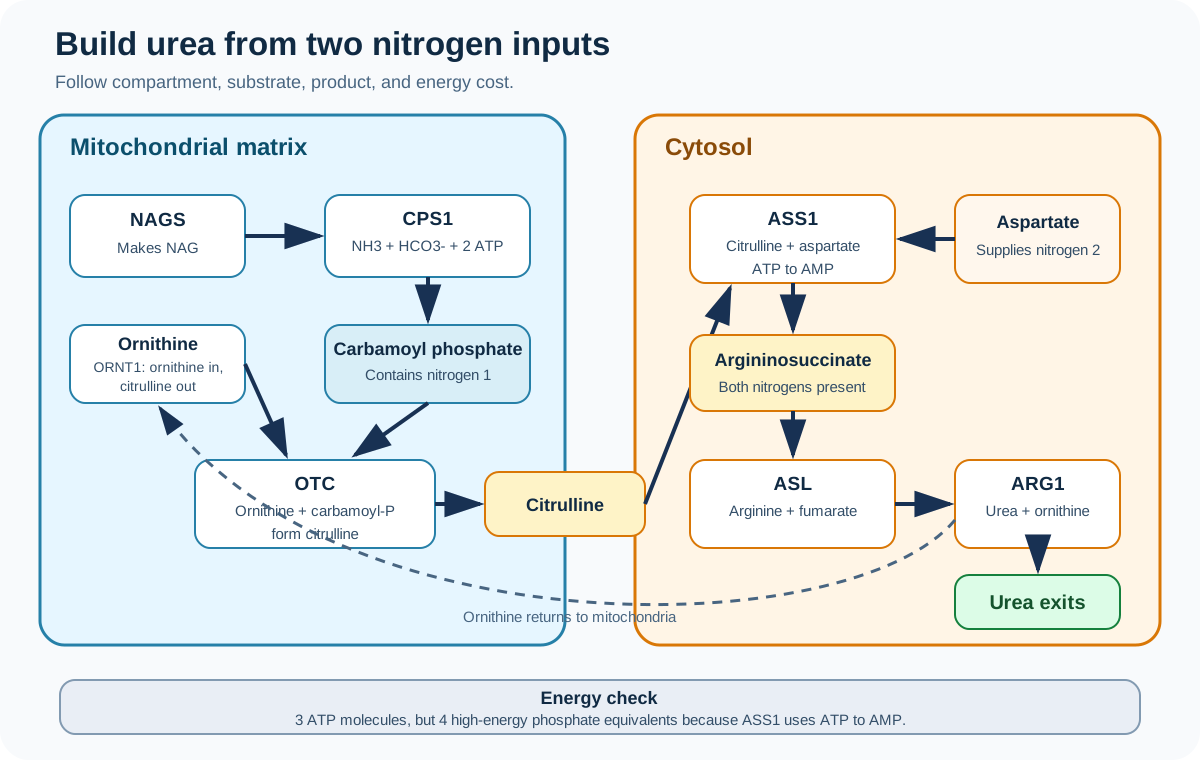
The cycle packages two nitrogen atoms into urea. Free ammonia enters through mitochondrial CPS1, while aspartate nitrogen joins later when ASS1 forms argininosuccinate; bicarbonate supplies the carbonyl carbon. [1]
Trace the two nitrogen inputs, the mitochondrial to cytosolic transition, ornithine return, and the four high-energy phosphate equivalents. [1][2]
Trace the mitochondrial half first: NAGS makes N-acetylglutamate, which activates CPS1; CPS1 forms carbamoyl phosphate; then OTC combines carbamoyl phosphate with ornithine to make citrulline. Citrulline then reaches the cytosol. [1][2]
In the cytosol, ASS1 adds aspartate to citrulline, ASL separates argininosuccinate into arginine and fumarate, and ARG1 releases urea while regenerating ornithine. Fumarate reconnects nitrogen disposal with intermediary metabolism. [1]
Place three ATP tokens beside the pathway, then count bond equivalents: CPS1 consumes two ATP, while ASS1 converts ATP to AMP and pyrophosphate. The result is three ATP molecules but four high-energy phosphate equivalents. [1]
Reveal the compartment check
CPS1 is mitochondrial and uses free ammonia for urea synthesis. CPS2 is cytosolic, uses glutamine nitrogen, and supports pyrimidine synthesis; confusing them reverses both compartment and purpose. [1]
Apply the map to transport: ORNT1 carries ornithine into mitochondria in exchange for citrulline, whereas citrin supplies mitochondrial export of aspartate for the cytosolic ASS1 reaction. Enzyme failure and transporter failure can therefore create overlapping but distinguishable metabolite patterns. [2][7]
Localize the block with metabolite patterns
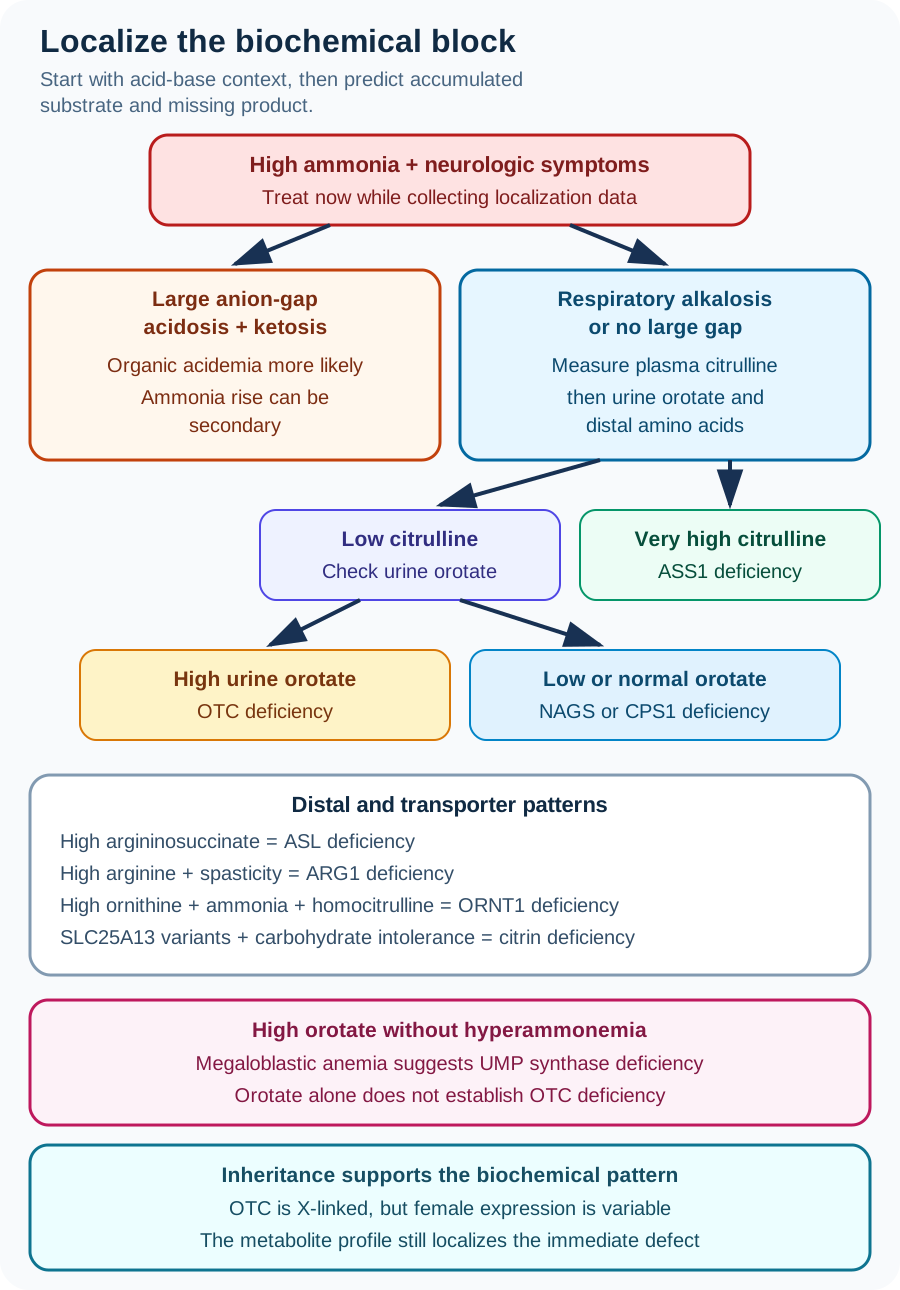
Start upstream. Low citrulline with low or normal urine orotate favors CPS1 or NAGS deficiency; low citrulline with high urine orotate favors OTC deficiency because excess mitochondrial carbamoyl phosphate reaches cytosolic pyrimidine synthesis. [2][3]
Pattern
Most useful localization
PatternVery high citrulline
Most useful localizationASS1 deficiency
PatternHigh argininosuccinate
Most useful localizationASL deficiency
PatternHigh arginine with progressive spasticity
Most useful localizationARG1 deficiency
PatternHigh ornithine, ammonia, and homocitrulline
Most useful localizationORNT1 deficiency
Use the table as a prediction tool. If the blocked reaction consumes citrulline, its substrate should rise; if it produces citrulline, citrulline should fall. Substrate accumulation and product depletion turn memorized names into a repeatable method. [2][4][5][6]
Start with acid-base context, then use substrate accumulation and product depletion to narrow the blocked step. [2][3][4][5][6][7]Reveal the distal-pattern check
ASS1 deficiency produces striking citrullinemia, ASL deficiency produces argininosuccinate and may include brittle hair or hypertension, and ARG1 deficiency often foregrounds progressive spasticity with less dramatic hyperammonemia. [4][5][6]
Do not confuse high urine orotate with a cycle disorder automatically. UMP synthase deficiency causes orotic aciduria with megaloblastic anemia and usually no hyperammonemia, while an organic acidemia more often adds metabolic acidosis and ketosis. [2]
Transient hyperammonemia of the newborn remains a diagnosis of exclusion after urgent evaluation for cycle defects, organic acidemias, liver disease, infection, and other causes. A temporary fall in ammonia does not erase the need for etiologic assessment. [2]
Inheritance modifies probability but does not replace biochemistry. OTC deficiency is X-linked, and heterozygous females can range from asymptomatic to severe because tissue expression varies; a fixed half-normal activity assumption is unsafe. [3]
Try it here · Checkpoint 2 of 3
Make your prediction before reading the choices. A first attempt is just a starting point.
Case 8
Show answer and explanations for case 8
A. NAGS deficiency preventing activation of CPS1 before citrulline can form (Why this does not fit)
A proximal activation defect lowers carbamoyl phosphate production. Citrulline would be low rather than massively high.
Reasoning steps for option A
What does a NAGS activation defect do to carbamoyl phosphate production?
A proximal activation defect lowers carbamoyl phosphate production.
How would citrulline look after a proximal activation defect?
Citrulline would be low rather than massively high.
B. ASS1 deficiency preventing citrulline from combining with aspartate (Best answer)
ASS1 consumes citrulline in the cytosol. Its failure causes striking citrulline accumulation with reduced downstream argininosuccinate and arginine.
Reasoning steps for option B
What does ASS1 normally do with citrulline?
In the cytosol it joins citrulline to aspartate to form argininosuccinate, the only route by which citrulline moves forward in the cycle.
How does the metabolite profile localize the block?
Citrulline at 1,850 micromol/L is dammed up behind the block, while absent argininosuccinate and low arginine show that nothing passes beyond ASS1.
C. ASL deficiency preventing argininosuccinate from yielding arginine and fumarate (Why this does not fit)
ASL deficiency causes argininosuccinate accumulation. The absence of that metabolite localizes the block one reaction earlier.
Reasoning steps for option C
Which metabolite accumulates in ASL deficiency?
ASL deficiency causes argininosuccinate accumulation.
What does the absence of argininosuccinate say about the block site?
The absence of that metabolite localizes the block one reaction earlier.
D. ORNT1 deficiency preventing mitochondrial ornithine entry and producing the full hyperornithinemia, hyperammonemia, homocitrullinuria pattern (Why this does not fit)
ORNT1 failure lowers effective mitochondrial ornithine supply and produces a transporter triad. It does not usually cause the extreme isolated citrulline accumulation supplied here.
Reasoning steps for option D
Which triad does ORNT1 deficiency produce?
ORNT1 failure lowers effective mitochondrial ornithine supply and produces a transporter triad.
Does ORNT1 failure cause extreme isolated citrullinemia?
It does not usually cause the extreme isolated citrulline accumulation supplied here.
E. ARG1 deficiency preventing urea release after arginine becomes markedly high (Why this does not fit)
ARG1 deficiency raises arginine and often presents with progressive spasticity. The low arginine value argues against the final reaction as the blocked step.
Reasoning steps for option E
Which amino acid rises in ARG1 deficiency?
ARG1 deficiency raises arginine and often presents with progressive spasticity.
Which result argues against a block at the last reaction?
The low arginine value argues against the final reaction as the blocked step.
Takeaway: A very high citrulline concentration with absent argininosuccinate localizes the defect to ASS1.
Treat in parallel: prevent production, create exits, clear ammonia
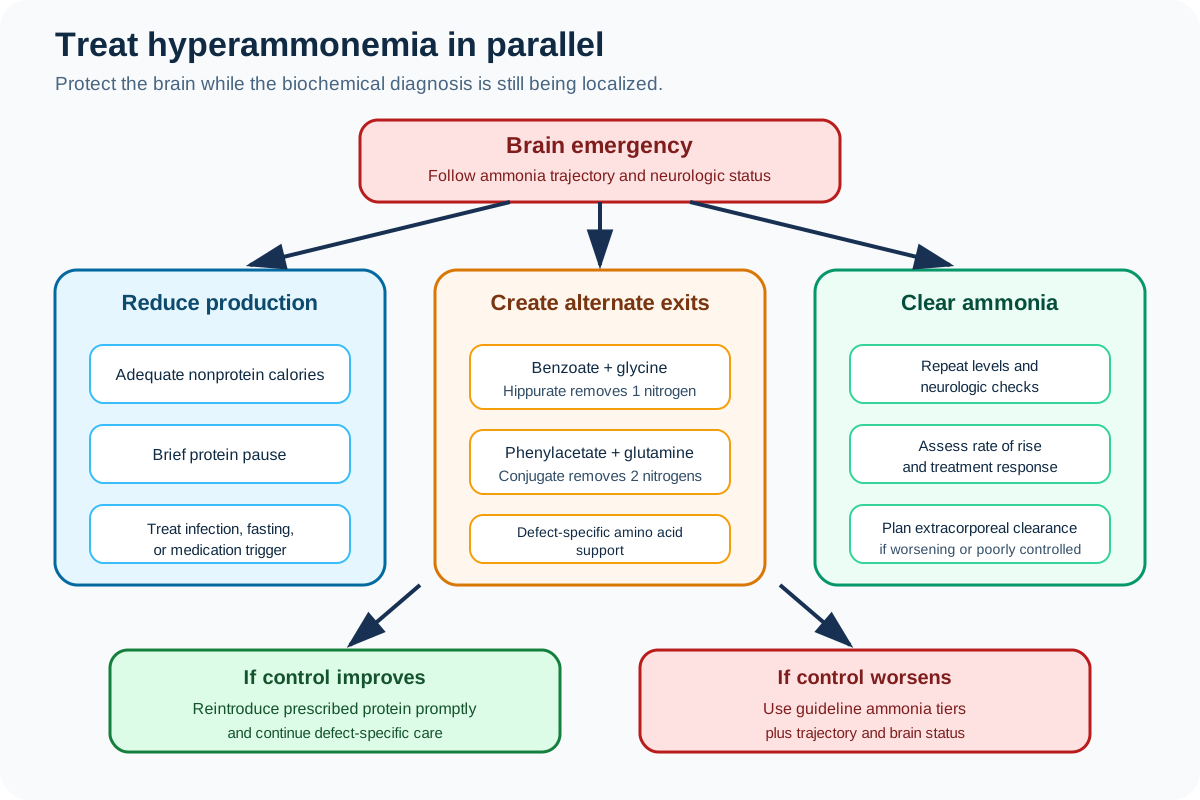
First reduce new nitrogen production by reversing catabolism with adequate nonprotein calories and briefly pausing protein. This pause is temporary; prolonged protein elimination can worsen tissue breakdown, so planned reintroduction begins as control is restored. [2]
Coordinate anti-catabolic care, nitrogen scavenging, serial neurologic assessment, and timely extracorporeal clearance planning. [2][8][9][12]
Alternative exits bypass the blocked cycle. Sodium benzoate couples with glycine to form hippurate and removes one nitrogen, while phenylacetate couples with glutamine to form phenylacetylglutamine and removes two nitrogens. [8]
Choose supplements by the defect. Arginine or citrulline may restore downstream intermediates in selected disorders, but arginine should not be added routinely in ARG1 deficiency because the blocked product is already high. [2][6]
Carglumic acid acts as a NAG analogue that activates CPS1. A response supports restored flux, but it does not by itself prove NAGS deficiency because the drug also has labeled use in acute hyperammonemia from propionic or methylmalonic acidemia. [9]
Reveal the escalation rule
Consensus guidelines for symptomatic patients give tiered thresholds for extracorporeal ammonia clearance: with ammonia 250 to 500 micromol/L, prepare hemodiafiltration when encephalopathy is significant, ammonia is high early, or onset is on day 1 or 2, and begin it if ammonia does not fall rapidly within 3 to 6 hours; at 500 micromol/L or more, start immediately; in adults, consider it once ammonia exceeds 200 micromol/L. Worsening encephalopathy or a rapid rise justifies escalation even below these values. [2][15]
Separate acute and chronic scavenger roles. Intravenous phenylacetate plus benzoate is used as an adjunct in crisis, whereas sodium phenylbutyrate is a chronic adjunct and is not acute rescue. Glycerol phenylbutyrate is another oral chronic scavenger that also forms phenylacetylglutamine. [8][12][15]
Try it here · Checkpoint 3 of 3
Make your prediction before reading the choices. A first attempt is just a starting point.
Case 17
Show answer and explanations for case 17
A. Continue the same therapy alone until a single universal dialysis threshold is crossed, regardless of neurologic decline or the rate of rise (Why this does not fit)
Ongoing medical therapy remains important. Consensus guidance uses tiered thresholds rather than one universal number, and this child is above the immediate-start tier with coma and a steep rise, so waiting only delays clearance.
Reasoning steps for option A
Why is it tempting to keep going with the current medical therapy alone?
Calories and scavengers still limit new nitrogen production and must continue alongside any escalation.
How do guideline tiers apply to this child?
This child is above 500 micromol/L, rising steeply, and comatose, so consensus tiers already call for immediate extracorporeal clearance rather than more waiting.
B. Stop calories to avoid worsening hyperglycemia and allow endogenous protein breakdown to provide essential amino acids (Why this does not fit)
Stopping calories increases catabolism and adds nitrogen to the crisis. Glucose management should be adjusted without sacrificing the anti-catabolic strategy.
Reasoning steps for option B
What happens to nitrogen load if calories are stopped?
Stopping calories increases catabolism and adds nitrogen to the crisis.
How should high glucose be managed without losing the anti-catabolic plan?
Glucose management should be adjusted without sacrificing the anti-catabolic strategy.
C. Arrange urgent extracorporeal ammonia clearance while continuing the medical measures already started (Best answer)
Rapidly rising ammonia with coma indicates inadequate control and high neurologic risk, and a concentration above 500 micromol/L already meets consensus criteria for starting extracorporeal clearance at once. Clearance should begin while scavengers, calories, and defect-specific treatment continue.
Reasoning steps for option C
Which two findings show that control has failed?
Ammonia rose from 540 to 760 micromol/L in 90 minutes despite scavengers and calories, and the child became comatose.
Should medical therapy stop once clearance begins?
No; extracorporeal clearance starts while scavengers, calories, and defect-specific treatment continue.
D. Delay all escalation until the exact pathogenic variant is confirmed (Why this does not fit)
Genetic confirmation can define long-term care. It is not required before treating a life-threatening biochemical emergency.
Reasoning steps for option D
What is genetic confirmation useful for?
Knowing the exact variant guides long-term diet, transplant decisions and family counseling.
Why can escalation not wait for the variant report?
Genetic results take days to weeks, while an ammonia above 700 micromol/L with coma causes irreversible brain injury within hours.
Takeaway: Ammonia above 500 micromol/L that keeps rising with worsening encephalopathy calls for starting extracorporeal clearance at once alongside ongoing medical therapy.
Prevent recurrence and separate inherited from acquired causes
Long-term care pairs an individualized protein prescription with enough energy, essential amino acids when needed, laboratory monitoring, and a written illness plan. The purpose is to preserve growth while preventing catabolic crises, not to remove protein indefinitely. [2]
Citrin deficiency is the major nutrition exception. Because impaired aspartate transport changes redox and substrate handling, a large carbohydrate load can worsen adult disease; specialist plans favor relatively higher protein and fat with lower carbohydrate. [2][7]
For ARG1 deficiency, pegzilarginase-nbln received accelerated approval in the United States on February 23, 2026 for hyperargininemia in patients age 2 years and older with dietary protein restriction. It lowers arginine but does not replace standard emergency treatment for a hyperammonemic crisis. [2][6][14]
Liver transplantation can restore hepatic nitrogen disposal and prevent future crises, but it does not alter germline inheritance or guarantee reversal of established neurologic injury. Extrahepatic features can also persist in disorders such as ASL deficiency. [2][3][5]
Acquired hyperammonemia requires cause-specific treatment. In cirrhosis, identify and correct the precipitant, use lactulose for episodic overt encephalopathy, and add rifaximin to reduce recurrence when indicated. [10]
Normal liver tests do not exclude medication-related disease. Valproate can produce hyperammonemia despite normal transaminases and can expose an underlying cycle disorder, so new confusion warrants ammonia assessment and medication review. [11]
Reveal the final nitrogen distinction
The liver converts waste nitrogen into urea, while the kidney can increase urinary ammonium excretion during metabolic acidosis. These processes share nitrogen but answer different physiologic problems. [13]
Transfer the full method to any vignette: recognize urgency, sort acid-base context, use citrulline and orotate to localize, predict the accumulated substrate, and match therapy to the specific defect. That sequence protects the brain while preserving diagnostic precision. [1][2]
Practice the full reasoning sequence
Case 2
Show answer and explanations for case 2
A. Repeat plasma ammonia promptly using the laboratory validated collection and processing method (Best answer)
The collection and transport history can falsely raise ammonia. Prompt confirmation under validated conditions resolves the measurement problem without dismissing a potentially important result.
Reasoning steps for option A
How could the blood draw and transport explain this mildly high ammonia?
A long tourniquet time, a struggling child and a sample left standing before analysis can all raise the measured ammonia, so a modest value such as 82 micromol/L may be spurious.
What does a properly handled repeat sample accomplish?
A free-flowing sample kept on ice and analyzed promptly shows whether the elevation is real, without either labeling the child or ignoring a true abnormality.
B. Diagnose an inherited urea-cycle disorder from this single result and begin lifelong restriction (Why this does not fit)
A mild isolated value can occur with preanalytic error. One compromised specimen cannot establish a genetic disorder or justify a permanent nutrition plan.
Reasoning steps for option B
Why might a raised ammonia prompt thoughts of an inherited cycle disorder?
A raised ammonia value is the laboratory hallmark of a cycle disorder, so any abnormal result can seem to point there.
Why can one compromised sample not support a lifelong diagnosis?
The child is well, the liver tests are normal and the sample was handled poorly, so true hyperammonemia is not yet shown; diagnosis needs a confirmed elevation plus amino acids, urine orotate and genetic testing.
C. Ignore the result because an asymptomatic child cannot have an abnormal ammonia concentration (Why this does not fit)
A well appearance lowers immediate concern but does not prove the number is false. The safe response is verification, not automatic dismissal.
Reasoning steps for option C
Does a well-appearing child make an abnormal ammonia impossible?
A well appearance lowers immediate concern but does not prove the number is false.
What is the safe response to an uncertain value in a well child?
The safe response is verification, not automatic dismissal.
D. Begin chronic sodium phenylbutyrate immediately and repeat testing only after several weeks of treatment (Why this does not fit)
A scavenger can lower ammonia in selected disorders. Starting long-term drug therapy before confirming the abnormality obscures the diagnosis and exposes the child to unnecessary treatment.
Reasoning steps for option D
Why might starting a scavenger seem proactive here?
Phenylbutyrate is a standard long-term drug in cycle disorders, so starting it early can look like protective caution.
What would treating now do to the diagnostic picture?
Removing nitrogen before a real elevation is confirmed can mask the abnormality on later tests and exposes a possibly healthy child to a drug with side effects and a large sodium load.
Takeaway: A questionable mild ammonia value should be verified promptly, while a symptomatic marked abnormality should be treated without delay.
A. Propionic acidemia presenting for the first time with a large anion-gap acidosis and ketonuria (Why this does not fit)
Organic acidemias can produce secondary hyperammonemia during catabolism. The supplied alkalosis, absent ketosis, low citrulline, and high orotate do not fit the proposed acidotic pattern.
Reasoning steps for option A
Why do organic acidemias belong in the differential of this adult episode?
Propionic acidemia can present late, and its accumulating metabolites inhibit N-acetylglutamate synthesis, so it can cause catabolic hyperammonemia in an adult.
Which acid-base and metabolite findings rule propionic acidemia out?
Her pH of 7.49 is alkalemic and ketones are absent, whereas propionic acidemia decompensates with a ketotic anion-gap acidosis; low citrulline with high orotate instead points inside the cycle.
B. ASS1 deficiency causing marked citrulline accumulation during a postpartum stressor (Why this does not fit)
A partial distal defect can appear during physiologic stress. ASS1 deficiency should raise citrulline markedly rather than produce the low value given here.
Reasoning steps for option B
Why might a partial distal defect be considered after delivery?
Late-onset citrullinemia type 1 can first decompensate under postpartum catabolism, just as other partial cycle defects can.
What would plasma citrulline look like if ASS1 were the block?
Citrulline builds up behind an ASS1 block, often to many times normal, so her low citrulline places the defect before citrulline is made.
C. CPS1 deficiency causing excess mitochondrial carbamoyl phosphate to enter pyrimidine synthesis (Why this does not fit)
CPS1 deficiency can cause low citrulline and severe hyperammonemia. It produces too little carbamoyl phosphate, so high urine orotate is not the expected consequence.
Reasoning steps for option C
Which features of this episode are compatible with CPS1 deficiency?
CPS1 deficiency can cause low citrulline and severe hyperammonemia.
Why does high urine orotate argue against a CPS1 block?
It produces too little carbamoyl phosphate, so high urine orotate is not the expected consequence.
D. Partial ornithine transcarbamylase deficiency unmasked by postpartum catabolism (Best answer)
The peripartum period and poor intake can expose a partial defect. Low citrulline plus high urine orotate localizes the block to OTC because carbamoyl phosphate spills toward pyrimidine synthesis.
Reasoning steps for option D
Why can a cycle defect first present 6 days after delivery?
Uterine involution and poor intake after delivery drive protein catabolism, raising the nitrogen load beyond what a partially active enzyme can clear.
How do low citrulline and high orotate together localize the block?
Low citrulline means the OTC product is not being made, and high orotate means carbamoyl phosphate is present but unused, so the failing step lies between them at OTC.
Takeaway: Postpartum catabolism can expose partial OTC deficiency, and the low-citrulline high-orotate pattern provides the localization.
A. The response proves OTC deficiency because carglumic acid directly replaces ornithine transcarbamylase (Why this does not fit)
Improved ureagenesis can occur after CPS1 activation. Carglumic acid does not replace OTC, and low urine orotate also argues against the classic OTC pattern.
Reasoning steps for option A
Why might a rapid response seem to identify a specific enzyme defect?
A dramatic fall in ammonia after one drug seems to point at the step the drug acts on, and OTC deficiency is the most common cycle defect.
What do the drug's target and the orotate result say about OTC?
Carglumic acid acts at CPS1, not at OTC, and an OTC block would push urine orotate up rather than leave it low.
B. The response shows that activating CPS1 can restore flux, but it does not by itself establish NAGS deficiency (Best answer)
Carglumic acid is a structural analogue of N-acetylglutamate and activates CPS1. A favorable response is mechanistically useful but not uniquely diagnostic because selected organic acidemias can also respond.
Reasoning steps for option B
Which step does carglumic acid act on?
It mimics N-acetylglutamate, the obligatory allosteric activator of CPS1, so it restores flux when that activator is missing or suppressed.
Why can this response not stand alone as proof of NAGS deficiency?
Propionic and methylmalonic acidemias also suppress N-acetylglutamate synthesis and also respond, so enzyme, metabolite or genetic testing must still confirm the cause.
C. The response identifies ASS1 deficiency because citrulline should rise after every effective treatment (Why this does not fit)
Ammonia can fall when an upstream step is restored. ASS1 deficiency usually presents with very high baseline citrulline, not the low value in this newborn.
Reasoning steps for option C
Why might ASS1 deficiency be proposed after a good treatment response?
ASS1 deficiency is a common neonatal cycle defect, and restoring upstream flux might seem able to relieve any downstream block.
Which pretreatment result makes ASS1 deficiency unlikely?
Newborns with an ASS1 block start with citrulline many times normal because it cannot move forward, yet this baby's citrulline was low before any drug was given.
D. The response excludes every organic acidemia and makes acid-base testing unnecessary (Why this does not fit)
Carglumic acid has labeled use for acute hyperammonemia in propionic and methylmalonic acidemia. Treatment response therefore cannot replace acid-base, acylcarnitine, and organic acid evaluation.
Reasoning steps for option D
Which approved uses of carglumic acid matter when interpreting a response?
Carglumic acid has labeled use for acute hyperammonemia in propionic and methylmalonic acidemia.
E. Stop all other ammonia-lowering measures immediately after the first lower value, before serial assessment or neurologic recovery (Why this does not fit)
A falling concentration is encouraging during a crisis. Standard care still depends on the trajectory, neurologic status, nutrition, and the need for additional clearance support.
Reasoning steps for option E
Why might the first lower value tempt the team to stop other measures?
A falling ammonia after carglumic acid looks like the problem is solved, and scavengers and dialysis carry their own risks.
What must be confirmed before any therapy is withdrawn?
The team needs a sustained downward trend, neurologic recovery and adequate calorie intake, because one lower number can rebound if catabolism resumes.
Takeaway: Carglumic acid activates CPS1, but a response is a physiologic observation rather than a stand-alone etiologic diagnosis.
A. ARG1 hydrolysis of arginine to ornithine and urea in the cytosol (Why this does not fit)
ARG1 releases the completed urea molecule and regenerates ornithine. Both urea nitrogens have already been incorporated before this hydrolysis step.
Reasoning steps for option A
What does ARG1 do with the two nitrogens already in arginine?
ARG1 releases the completed urea molecule and regenerates ornithine.
When were both urea nitrogens incorporated relative to ARG1?
Both urea nitrogens have already been incorporated before this hydrolysis step.
B. OTC condensation of ornithine with carbamoyl phosphate inside mitochondria (Why this does not fit)
OTC transfers the nitrogen already present in carbamoyl phosphate into citrulline. It does not add the separate aspartate-derived nitrogen requested in the study.
Reasoning steps for option B
Which nitrogen does OTC move into citrulline?
OTC transfers the nitrogen already present in carbamoyl phosphate into citrulline.
Does OTC add the second, aspartate-derived nitrogen?
It does not add the separate aspartate-derived nitrogen requested in the study.
C. ASS1 condensation of citrulline with aspartate in the cytosol (Best answer)
Aspartate supplies the second urea nitrogen. ASS1 joins aspartate to citrulline, creating argininosuccinate and committing that nitrogen to the final urea product.
Reasoning steps for option C
Which molecule carries the second urea nitrogen into the cycle?
Aspartate, formed by transamination of oxaloacetate, brings the second nitrogen from the general amino acid pool.
At which reaction does that nitrogen join a cycle intermediate?
In the cytosol, ASS1 condenses aspartate with citrulline into argininosuccinate, so the second nitrogen is in place before ASL and ARG1 act.
D. ASL separation of argininosuccinate into arginine and fumarate after both nitrogens are present (Why this does not fit)
ASL preserves both nitrogens in arginine while releasing fumarate. The second nitrogen entered one reaction earlier through the aspartate substrate.
Reasoning steps for option D
What happens to both nitrogens when ASL cleaves argininosuccinate?
ASL preserves both nitrogens in arginine while releasing fumarate.
Where did the second nitrogen enter before the ASL step?
The second nitrogen entered one reaction earlier through the aspartate substrate.
Takeaway: Free ammonia supplies one urea nitrogen through CPS1, and aspartate supplies the second through ASS1.
A. CPS1 consumes two ATP, and ASS1 cleaves a third ATP to AMP plus pyrophosphate, which costs two phosphate equivalents (Best answer)
CPS1 uses two ATP to form carbamoyl phosphate. ASS1 then uses ATP to AMP rather than ATP to ADP, so that single molecule contributes two additional high-energy phosphate equivalents.
Reasoning steps for option A
Which reaction spends the first two ATP?
CPS1 uses one ATP to activate bicarbonate and a second to phosphorylate carbamate, forming carbamoyl phosphate from free ammonia.
Why does the third ATP count as two equivalents?
ASS1 splits ATP into AMP and pyrophosphate, and hydrolysis of that pyrophosphate breaks a second phosphoanhydride bond, so one molecule costs two.
B. OTC consumes one ATP and ARG1 consumes three ATP during urea release (Why this does not fit)
OTC and ARG1 do not account for four ATP-derived bonds in the cycle. Their reactions use carbamoyl phosphate transfer and hydrolysis rather than the stated ATP pattern.
Reasoning steps for option B
Do OTC and ARG1 consume ATP in the cycle?
OTC and ARG1 do not account for four ATP-derived bonds in the cycle.
What kinds of reactions do OTC and ARG1 perform instead?
Their reactions use carbamoyl phosphate transfer and hydrolysis rather than the stated ATP pattern.
C. ASL uses all four phosphate equivalents when fumarate leaves argininosuccinate (Why this does not fit)
ASL separates argininosuccinate without direct ATP consumption. The energy was spent before fumarate and arginine are formed.
Reasoning steps for option C
Does ASL consume ATP when it releases fumarate?
ASL separates argininosuccinate without direct ATP consumption.
When was the energy for argininosuccinate formation spent?
The energy was spent before fumarate and arginine are formed.
D. One ATP is counted twice because urea contains two nitrogen atoms (Why this does not fit)
Nitrogen count does not duplicate an ATP molecule. The extra energetic equivalent comes from cleavage to AMP and pyrophosphate.
Reasoning steps for option D
Why might the two nitrogens seem to explain the fourth phosphate?
Urea has two nitrogens, so a charge of one extra bond per nitrogen looks like a tidy way to count.
What actually produces the fourth high-energy phosphate equivalent?
The ASS1 reaction takes ATP all the way to AMP, and returning AMP to ATP needs two phosphorylations, regardless of how many nitrogens are handled.
Takeaway: The cycle consumes three ATP molecules but four high-energy phosphate equivalents because the ASS1 reaction uses ATP to AMP.
A. Cytosolic CPS2 uses glutamine to increase pyrimidine synthesis independently of the mitochondrial defect (Why this does not fit)
CPS2 normally supplies carbamoyl phosphate for cytosolic pyrimidine synthesis. The marked orotate signal in this case comes from excess mitochondrial substrate reaching that pathway, not primary CPS2 activation alone.
Reasoning steps for option A
Why might CPS2 seem responsible for the extra orotate?
CPS2 makes the carbamoyl phosphate that normally feeds orotate synthesis in the cytosol, so more orotate can seem to mean more CPS2 activity.
Where does the surplus carbamoyl phosphate come from in this baby?
Low citrulline with severe hyperammonemia shows that OTC is not using the carbamoyl phosphate made by CPS1, and that mitochondrial surplus leaks into the cytosol beyond CPS2 regulation.
B. ASS1 failure traps citrulline in the cytosol and converts it directly into orotate (Why this does not fit)
ASS1 deficiency causes marked citrulline accumulation. Citrulline is not converted directly into orotate, and the stem instead reports a low concentration.
Reasoning steps for option B
Why might an ASS1 block be considered in this newborn?
ASS1 deficiency is a common cause of severe neonatal hyperammonemia, so it is an early candidate at an ammonia of 690 micromol/L.
Which blood result excludes ASS1 as the source of the orotate?
An ASS1 block piles citrulline up to very high values, but this baby's citrulline is low, and orotate is made from carbamoyl phosphate rather than from citrulline.
C. ARG1 failure raises arginine, which is then degraded into orotic acid by the kidney (Why this does not fit)
ARG1 deficiency produces hyperargininemia and a chronic spastic phenotype. Arginine is not the source of the high urine orotate described here.
Reasoning steps for option C
What is the main biochemical and clinical sign of ARG1 deficiency?
ARG1 deficiency produces hyperargininemia and a chronic spastic phenotype.
Is arginine the source of urinary orotate?
Arginine is not the source of the high urine orotate described here.
D. Unconsumed mitochondrial carbamoyl phosphate reaches cytosolic pyrimidine synthesis after OTC failure (Best answer)
OTC normally transfers carbamoyl phosphate nitrogen to ornithine. When OTC is deficient, excess carbamoyl phosphate can feed pyrimidine synthesis and increase orotate excretion.
Reasoning steps for option D
What does OTC normally do with mitochondrial carbamoyl phosphate?
It combines carbamoyl phosphate with ornithine to make citrulline, which then leaves the mitochondrion.
Why does urine orotate rise when OTC fails?
Unused carbamoyl phosphate reaches the cytosol, where the pyrimidine pathway converts it to orotate faster than UMP synthase can use it, and the excess spills into urine.
Takeaway: Low citrulline plus high urine orotate points to OTC failure and diversion of carbamoyl phosphate toward pyrimidine synthesis.
A. ARG1 deficiency causing hyperargininemia, progressive lower-extremity spasticity, and relatively infrequent severe neonatal crises (Why this does not fit)
ARG1 deficiency can produce a chronic neurologic phenotype with less dramatic ammonia abnormalities. It should raise arginine rather than argininosuccinate and does not best explain the hair pattern.
Reasoning steps for option A
Why might ARG1 deficiency be considered in a child with episodic hyperammonemia?
ARG1 deficiency can produce a chronic neurologic phenotype with less dramatic ammonia abnormalities.
Which metabolite and hair findings point away from ARG1 deficiency?
It should raise arginine rather than argininosuccinate and does not best explain the hair pattern.
B. ASS1 deficiency causing isolated high citrulline without argininosuccinate production (Why this does not fit)
ASS1 failure prevents argininosuccinate formation. The measured accumulation proves that ASS1 has already acted.
Reasoning steps for option B
What does ASS1 failure do to argininosuccinate formation?
What does a high argininosuccinate level prove about ASS1?
The measured accumulation proves that ASS1 has already acted.
C. ASL deficiency causing argininosuccinate accumulation with hair, liver, and vascular complications (Best answer)
ASL normally separates argininosuccinate into arginine and fumarate. Its failure explains the named metabolite plus brittle hair, liver disease, and hypertension.
Reasoning steps for option C
Which reaction fails in ASL deficiency?
ASL normally separates argininosuccinate into arginine and fumarate.
Which extrahepatic findings in this child fit ASL deficiency?
Its failure explains the named metabolite plus brittle hair, liver disease, and hypertension.
D. OTC deficiency causing high urine orotate with low citrulline and no distal metabolite production (Why this does not fit)
OTC deficiency is a proximal block with low citrulline. A large argininosuccinate concentration localizes much farther downstream.
Reasoning steps for option D
Where is the OTC block located in the cycle?
OTC deficiency is a proximal block with low citrulline.
Why does a high argininosuccinate level exclude OTC deficiency?
A large argininosuccinate concentration localizes much farther downstream.
Takeaway: Argininosuccinate accumulation with brittle hair, liver disease, or hypertension supports ASL deficiency.
A. ARG1 deficiency, with avoidance of routine arginine supplementation (Best answer)
The progressive spastic phenotype and hyperargininemia identify failure of the final cycle reaction. Giving more arginine would add the substrate that already cannot be cleared normally.
Reasoning steps for option A
Which clinical and biochemical features point to ARG1 deficiency?
The progressive spastic phenotype and hyperargininemia identify failure of the final cycle reaction.
Why should routine arginine supplements be avoided here?
Giving more arginine would add the substrate that already cannot be cleared normally.
B. OTC deficiency, with routine arginine loading regardless of the measured amino acid profile (Why this does not fit)
OTC deficiency more often causes low citrulline and episodic severe hyperammonemia. The high arginine and chronic spasticity localize the disorder to ARG1 instead.
Reasoning steps for option B
What pattern does OTC deficiency usually produce?
OTC deficiency more often causes low citrulline and episodic severe hyperammonemia.
Which findings localize this child's disorder to ARG1 instead?
The high arginine and chronic spasticity localize the disorder to ARG1 instead.
C. ASS1 deficiency, with treatment aimed at increasing citrulline accumulation further (Why this does not fit)
ASS1 deficiency is marked by severe citrullinemia rather than hyperargininemia. Deliberately increasing the blocked substrate would not fit the supplied pattern.
Reasoning steps for option C
Which amino acid defines ASS1 deficiency?
ASS1 deficiency is marked by severe citrullinemia rather than hyperargininemia.
Why would raising citrulline further not fit this child?
Deliberately increasing the blocked substrate would not fit the supplied pattern.
D. ASL deficiency, with automatic high-dose arginine because every distal cycle disorder benefits from the same supplement plan (Why this does not fit)
ASL deficiency raises argininosuccinate and may include hair or vascular findings. Supplement choice is defect-specific, so a universal arginine plan is unsafe in a child whose arginine is already high.
Reasoning steps for option D
Which features characterize ASL deficiency?
ASL deficiency raises argininosuccinate and may include hair or vascular findings.
Why is a universal arginine plan unsafe for this child?
Supplement choice is defect-specific, so a universal arginine plan is unsafe in a child whose arginine is already high.
Takeaway: Progressive spasticity plus hyperargininemia points to ARG1 deficiency, where routine arginine supplementation is inappropriate.
A. Failure of citrin to export aspartate from mitochondria for cytosolic ASS1 (Why this does not fit)
Citrin deficiency can cause adult hyperammonemia and unusual food preferences. The defining hyperornithinemia and homocitrullinuria instead point to impaired ornithine transport.
Reasoning steps for option A
Why might citrin deficiency fit an adolescent with fasting-related confusion?
Citrin deficiency can cause adult hyperammonemia and unusual food preferences.
Which metabolites point to an ornithine transport defect instead?
The defining hyperornithinemia and homocitrullinuria instead point to impaired ornithine transport.
B. Loss of cytosolic ASS1 activity with extreme citrulline accumulation (Why this does not fit)
ASS1 deficiency raises citrulline because the substrate cannot be consumed. It does not produce the named ornithine and homocitrulline triad.
Reasoning steps for option B
What does ASS1 deficiency do to citrulline?
ASS1 deficiency raises citrulline because the substrate cannot be consumed.
Can ASS1 deficiency produce the ornithine and homocitrulline triad?
It does not produce the named ornithine and homocitrulline triad.
C. Failure of ARG1 to hydrolyze arginine after urea has nearly formed (Why this does not fit)
ARG1 deficiency raises arginine and causes progressive spasticity. The supplied metabolites localize before OTC rather than at the final hydrolysis step.
Reasoning steps for option C
Which amino acid and neurologic sign define ARG1 deficiency?
ARG1 deficiency raises arginine and causes progressive spasticity.
Where do this adolescent's metabolites localize the defect?
The supplied metabolites localize before OTC rather than at the final hydrolysis step.
D. Loss of the mitochondrial ornithine transporter ORNT1, limiting ornithine delivery to OTC and producing the HHH triad (Best answer)
ORNT1 normally brings ornithine into the mitochondrial matrix for the OTC reaction. Its failure explains hyperornithinemia, reduced ureagenesis with hyperammonemia, and homocitrullinuria as a linked transporter phenotype.
Reasoning steps for option D
What does ORNT1 normally transport?
It exchanges cytosolic ornithine for mitochondrial citrulline, supplying the ornithine that OTC needs.
How does ORNT1 failure produce each part of the triad?
Ornithine stays in the blood, OTC lacks ornithine so ammonia rises, and unused carbamoyl phosphate reacts with lysine to form homocitrulline that appears in urine.
Takeaway: Hyperornithinemia, hyperammonemia, and homocitrullinuria identify ORNT1 deficiency rather than a catalytic enzyme block.
A. OTC deficiency with ongoing severe hyperammonemia (Why this does not fit)
OTC failure can raise urine orotate. A severe active episode should also disturb ammonia handling and usually lowers citrulline, which are not present here.
Reasoning steps for option A
Why does high urine orotate first raise concern for OTC deficiency?
Orotic aciduria is the classic urine clue to OTC deficiency, the most common cycle disorder.
Which normal results argue against OTC deficiency here?
OTC deficiency spills orotate because carbamoyl phosphate backs up alongside ammonia, but this infant's ammonia and citrulline are normal and the dominant problem is a megaloblastic anemia.
B. UMP synthase deficiency causing hereditary orotic aciduria (Best answer)
UMP synthase failure blocks pyrimidine synthesis and produces orotic aciduria. Refractory megaloblastic anemia with normal ammonia distinguishes it from a urea-cycle block.
Reasoning steps for option B
Which pathway is blocked in UMP synthase deficiency?
UMP synthase failure blocks pyrimidine synthesis and produces orotic aciduria.
Which features separate hereditary orotic aciduria from a cycle block?
Refractory megaloblastic anemia with normal ammonia distinguishes it from a urea-cycle block.
C. CPS1 deficiency with absent mitochondrial carbamoyl phosphate production (Why this does not fit)
CPS1 failure causes hyperammonemia with low citrulline and low or normal orotate. It cannot explain isolated high orotate plus megaloblastic anemia.
Reasoning steps for option C
What pattern does CPS1 deficiency produce?
CPS1 failure causes hyperammonemia with low citrulline and low or normal orotate.
Can CPS1 deficiency explain isolated orotic aciduria with anemia?
It cannot explain isolated high orotate plus megaloblastic anemia.
D. ASS1 deficiency with extreme citrullinemia and reduced argininosuccinate (Why this does not fit)
ASS1 failure raises citrulline markedly during decompensation. The normal amino acid profile and anemia pattern do not fit that reaction.
Reasoning steps for option D
What happens to citrulline in ASS1 deficiency?
ASS1 failure raises citrulline markedly during decompensation.
Which features of this infant do not fit ASS1 deficiency?
The normal amino acid profile and anemia pattern do not fit that reaction.
E. ASL deficiency causing argininosuccinate accumulation, brittle hair, liver disease, and secondary megaloblastosis (Why this does not fit)
ASL deficiency can involve liver and hair abnormalities. It should produce high argininosuccinate and hyperammonemia rather than isolated orotic aciduria with normal cycle markers.
Reasoning steps for option E
Why might ASL deficiency come to mind in this infant?
ASL deficiency is the cycle disorder with the most prominent features outside the liver, and failure to thrive fits a chronic course.
What laboratory results would ASL deficiency show instead?
Plasma argininosuccinic acid would be high, usually with raised citrulline and episodic hyperammonemia, none of which appears in this child's normal cycle markers.
Takeaway: Orotic aciduria with refractory megaloblastic anemia and no hyperammonemia points to UMP synthase deficiency.
A. Primary OTC deficiency because every neonatal hyperammonemia with altered consciousness originates in the urea cycle (Why this does not fit)
OTC deficiency is an important neonatal cause of hyperammonemia. The marked anion-gap acidosis, ketosis, and propionylcarnitine signal identify a competing metabolic mechanism.
Reasoning steps for option A
Why is OTC deficiency a leading consideration in a lethargic newborn with high ammonia?
It is the most common urea-cycle disorder and classically presents in the first days of life with hyperammonemic coma.
Which findings point to a different primary mechanism?
A pH of 7.21 with a large anion gap and ketonuria signals an acid-producing disorder, whereas primary cycle defects usually give respiratory alkalosis, and the raised propionylcarnitine points to propionyl-CoA accumulation.
B. Primary CPS1 deficiency because low bicarbonate is produced directly by carbamoyl phosphate failure (Why this does not fit)
CPS1 deficiency usually produces respiratory alkalosis early rather than a ketotic organic acidosis. Low bicarbonate here reflects the acid load, not failure to consume bicarbonate in the cycle.
Reasoning steps for option B
What acid-base pattern does CPS1 deficiency usually produce early?
CPS1 deficiency usually produces respiratory alkalosis early rather than a ketotic organic acidosis.
What does the low bicarbonate reflect here?
Low bicarbonate here reflects the acid load, not failure to consume bicarbonate in the cycle.
C. An organic acidemia causing secondary inhibition of ureagenesis and hyperammonemia (Best answer)
Propionylcarnitine plus ketotic anion-gap acidosis localizes the primary problem to organic acid metabolism. Secondary disruption of NAG and cycle flux can then raise ammonia.
Reasoning steps for option C
Which findings place the primary problem outside the urea cycle?
A ketotic anion-gap acidosis with high propionylcarnitine is the signature of propionic or methylmalonic acidemia.
How can an organic acidemia raise ammonia?
Accumulated propionyl-CoA inhibits N-acetylglutamate synthase, so CPS1 is under-activated and ureagenesis slows.
D. Isolated respiratory alkalosis from hyperventilation with no metabolic acid accumulation (Why this does not fit)
The low pH, low bicarbonate, anion gap, and ketones establish metabolic acidosis. Hyperventilation may compensate but does not erase the primary acid disorder.
Reasoning steps for option D
Which findings establish a primary metabolic acidosis?
The low pH, low bicarbonate, anion gap, and ketones establish metabolic acidosis.
Can hyperventilation explain the whole acid-base picture?
Hyperventilation may compensate but does not erase the primary acid disorder.
Takeaway: Hyperammonemia with ketotic anion-gap acidosis and a diagnostic acylcarnitine pattern favors an organic acidemia with secondary cycle inhibition.
A. Variable X-chromosome inactivation can produce widely different hepatic OTC activity in heterozygous females (Best answer)
OTC deficiency is X-linked and female expression depends partly on tissue-specific X inactivation. Two carriers can therefore have very different clinical severity even within one family.
Reasoning steps for option A
What inheritance pattern does OTC deficiency follow?
OTC deficiency is X-linked and female expression depends partly on tissue-specific X inactivation.
Why can mother and daughter with the same variant have different courses?
Two carriers can therefore have very different clinical severity even within one family.
B. Every heterozygous female has exactly half-normal liver enzyme activity and identical risk (Why this does not fit)
A simple fixed percentage does not capture mosaic hepatic expression. The mother and daughter demonstrate why phenotype cannot be predicted from carrier status alone.
Reasoning steps for option B
Does every heterozygous female have exactly half-normal hepatic OTC activity?
A simple fixed percentage does not capture mosaic hepatic expression.
What does this family show about predicting phenotype from carrier status?
The mother and daughter demonstrate why phenotype cannot be predicted from carrier status alone.
C. The daughter must have a second autosomal recessive cycle disorder because female carriers remain asymptomatic (Why this does not fit)
Heterozygous females can have late or severe OTC manifestations. A second diagnosis is not required to explain symptoms in a documented carrier.
Reasoning steps for option C
Can heterozygous females have serious OTC symptoms?
Heterozygous females can have late or severe OTC manifestations.
Is a second diagnosis needed to explain the daughter's episodes?
A second diagnosis is not required to explain symptoms in a documented carrier.
D. The mother cannot truly carry the variant because absence of a prior crisis excludes biochemical vulnerability during future catabolic stress (Why this does not fit)
Some carriers remain clinically quiet for years or have subtle effects. Lack of a recognized episode does not eliminate future risk during illness, fasting, surgery, or the peripartum period.
Reasoning steps for option D
Why might a crisis-free mother seem not to carry the variant?
She has lived for decades without a recognized episode, so her daughter's severe course can seem incompatible with the same variant.
When could her carrier status still matter?
Favorable X inactivation can keep a carrier well until a major catabolic stress such as surgery, prolonged fasting or childbirth, and each of her sons has a 50% chance of inheriting the variant.
Takeaway: OTC expression in heterozygous females is variable, so carrier status does not predict a fixed enzyme activity or uniform severity.
A. Phenylacetylglutamine, removing two nitrogens after conjugation with glutamine (Why this does not fit)
Phenylacetate uses glutamine and produces phenylacetylglutamine. That is the paired pathway, not the product of benzoate.
Reasoning steps for option A
Which scavenger forms phenylacetylglutamine?
Phenylacetate uses glutamine and produces phenylacetylglutamine.
Why is phenylacetylglutamine not the benzoate product?
That is the paired pathway, not the product of benzoate.
B. Argininosuccinate, removing two nitrogens through direct renal filtration of a cycle intermediate (Why this does not fit)
Argininosuccinate is an internal cycle intermediate and can accumulate in ASL deficiency. It is not the renal conjugate generated by benzoate treatment.
Reasoning steps for option B
Where does argininosuccinate accumulate?
Argininosuccinate is an internal cycle intermediate and can accumulate in ASL deficiency.
Is argininosuccinate the conjugate formed by benzoate?
It is not the renal conjugate generated by benzoate treatment.
C. Urea, removing one nitrogen because benzoate directly substitutes for ARG1 (Why this does not fit)
Urea contains two nitrogens and is generated by the cycle itself. Benzoate bypasses the blocked cycle rather than replacing ARG1.
Reasoning steps for option C
How many nitrogens does urea carry, and where is it made?
Urea contains two nitrogens and is generated by the cycle itself.
Does benzoate replace ARG1?
Benzoate bypasses the blocked cycle rather than replacing ARG1.
D. Hippurate, removing one nitrogen after benzoate conjugates with glycine (Best answer)
Benzoate couples with glycine to form hippurate, which is excreted by the kidney. Glycine contributes one nitrogen, so each conjugate removes one waste nitrogen.
Reasoning steps for option D
Which amino acid does benzoate conjugate with?
Benzoate couples with glycine to form hippurate, which is excreted by the kidney.
How many nitrogens does each hippurate molecule remove?
Glycine contributes one nitrogen, so each conjugate removes one waste nitrogen.
Takeaway: Benzoate uses glycine to form hippurate and removes one nitrogen per conjugate.
A. Hippurate formed with glycine, carrying one nitrogen per molecule (Why this does not fit)
Hippurate is the product of benzoate conjugation with glycine. It removes one nitrogen and does not describe phenylacetate metabolism.
Reasoning steps for option A
Which scavenger forms hippurate?
Hippurate is the product of benzoate conjugation with glycine.
Does hippurate describe phenylacetate metabolism?
It removes one nitrogen and does not describe phenylacetate metabolism.
B. Phenylacetylglutamine formed with glutamine, carrying two nitrogens per molecule (Best answer)
Phenylbutyrate is converted to phenylacetate, which couples with glutamine. Because glutamine contains two nitrogens, each phenylacetylglutamine molecule removes two waste nitrogens.
Reasoning steps for option B
What does phenylbutyrate become before conjugation?
Phenylbutyrate is converted to phenylacetate, which couples with glutamine.
Why does each phenylacetylglutamine remove two nitrogens?
Because glutamine contains two nitrogens, each phenylacetylglutamine molecule removes two waste nitrogens.
C. Citrulline formed with ornithine, carrying one nitrogen to the kidney (Why this does not fit)
OTC forms citrulline inside the cycle. Citrulline is not the excreted conjugate created by phenylacetate.
Reasoning steps for option C
Why might citrulline seem like a nitrogen carrier for excretion?
Citrulline holds the nitrogen from carbamoyl phosphate and is exported from the mitochondrion, so it can look like a waste-nitrogen vehicle.
What does phenylacetate actually conjugate with?
Phenylacetate joins glutamine, not ornithine, and citrulline is recycled inside the cycle rather than excreted as a drug conjugate.
D. Arginine formed with fumarate, carrying two nitrogens out of the cycle (Why this does not fit)
ASL produces arginine and fumarate rather than joining them. Arginine remains a cycle intermediate and is not the named renal disposal product.
Reasoning steps for option D
What does ASL do with arginine and fumarate?
ASL produces arginine and fumarate rather than joining them.
Is arginine a renal disposal product?
Arginine remains a cycle intermediate and is not the named renal disposal product.
Takeaway: Phenylacetate couples with glutamine to form phenylacetylglutamine and removes two nitrogens per conjugate.
A. Begin planned protein reintroduction promptly under metabolic guidance while maintaining adequate calories (Best answer)
Temporary protein cessation reduces immediate nitrogen entry. Once control is established, carefully prescribed protein should return to support growth and prevent endogenous protein breakdown.
Reasoning steps for option A
What does a temporary protein pause achieve during a crisis?
It removes dietary nitrogen while calories and scavengers bring ammonia down, and guidelines limit it to about 24 to 48 hours.
Why restart protein now rather than wait longer?
After 18 hours with falling ammonia and clearing mental status, further restriction would make the body break down its own muscle protein, which releases nitrogen and can restart the crisis.
B. Continue zero protein until every plasma amino acid concentration is below the laboratory range (Why this does not fit)
Prolonged complete restriction can deepen essential amino acid deficiency and catabolism. The goal is safe protein provision, not suppression of all amino acids.
Reasoning steps for option B
What does prolonged zero protein do to amino acid balance?
Prolonged complete restriction can deepen essential amino acid deficiency and catabolism.
What is the real goal of protein management?
The goal is safe protein provision, not suppression of all amino acids.
C. Give an unrestricted high-protein meal to test whether the crisis has completely resolved (Why this does not fit)
Abruptly increasing nitrogen load can trigger renewed hyperammonemia. Reintroduction should be planned and monitored rather than used as a stress test.
Reasoning steps for option C
What can an abrupt high-protein meal do after a crisis?
Abruptly increasing nitrogen load can trigger renewed hyperammonemia.
How should protein be reintroduced instead?
Reintroduction should be planned and monitored rather than used as a stress test.
D. Replace all protein indefinitely with carbohydrate because permanent protein elimination prevents every future crisis in every cycle disorder (Why this does not fit)
Patients need individualized protein and essential amino acid intake for growth and tissue maintenance. Permanent elimination can worsen nutrition and does not remove illness-related catabolic risk.
Reasoning steps for option D
Why do patients need an individualized protein intake?
Patients need individualized protein and essential amino acid intake for growth and tissue maintenance.
What does permanent protein elimination fail to prevent?
Permanent elimination can worsen nutrition and does not remove illness-related catabolic risk.
Takeaway: Protein withholding during crisis is brief; timely prescribed reintroduction helps prevent malnutrition and renewed catabolism.
A. Treat the infection only because ARG1 deficiency never causes clinically important hyperammonemia (Why this does not fit)
ARG1 disease often foregrounds chronic spasticity, but acute ammonia rises can still occur. Neurologic symptoms and the measured concentration require emergency metabolic treatment.
Reasoning steps for option A
Can ARG1 deficiency cause acute hyperammonemia?
ARG1 disease often foregrounds chronic spasticity, but acute ammonia rises can still occur.
What do this child's symptoms require?
Neurologic symptoms and the measured concentration require emergency metabolic treatment.
B. Give high-dose arginine with no scavenger because every cycle defect benefits from replacing the final amino acid in the pathway (Why this does not fit)
Arginine can be useful in selected proximal and intermediate defects. In ARG1 deficiency the substrate is already high, so routine loading ignores the blocked final reaction and leaves the crisis untreated.
Reasoning steps for option B
In which cycle defects does arginine supplementation help?
In ASS1 and ASL deficiency arginine becomes an essential amino acid, and supplements regenerate ornithine so nitrogen can leave as citrulline or argininosuccinate.
Why does that logic fail in this child?
Arginase is the missing enzyme, so extra arginine cannot be cleaved and only raises an already high plasma arginine, while nitrogen still needs a scavenger route out.
C. Use lactulose alone because all causes of hyperammonemia respond to the same intestinal regimen (Why this does not fit)
Lactulose is used in cirrhosis-related encephalopathy. An inherited cycle crisis requires catabolism reversal, nitrogen disposal support, and defect-specific supplementation decisions.
Reasoning steps for option C
Why might lactulose seem a reasonable choice?
Lactulose is the standard first-line drug for high ammonia in cirrhosis and is familiar from adult practice.
Why is gut-directed therapy not enough for this child?
The ammonia comes from a blocked hepatic pathway during catabolic stress, so the child needs calories to stop protein breakdown and scavengers to open an alternative nitrogen exit.
D. Reverse catabolism, use appropriate ammonia-lowering therapy, treat the trigger, and avoid routine extra arginine (Best answer)
The child needs the same urgent brain-protective principles used for other cycle crises. The high arginine concentration adds a defect-specific caution against routine arginine supplementation.
Reasoning steps for option D
Which crisis principles apply to every cycle disorder?
The child needs the same urgent brain-protective principles used for other cycle crises.
Which defect-specific caution does the high arginine add?
The high arginine concentration adds a defect-specific caution against routine arginine supplementation.
Takeaway: Acute ARG1 crises require standard ammonia control plus avoidance of routine arginine loading.
A. Increase the glucose infusion further because every cycle disorder improves when carbohydrate becomes the sole calorie source (Why this does not fit)
Nonprotein calories often help reverse catabolism in many disorders. Citrin deficiency is a recognized exception in which excessive carbohydrate can worsen metabolic handling.
Reasoning steps for option A
Why do nonprotein calories usually help in a cycle crisis?
Glucose and lipid supply energy that halts muscle breakdown, which cuts the endogenous nitrogen load in most cycle disorders.
Why does extra glucose backfire in this patient?
Citrin loss disables the malate-aspartate shuttle, so glycolysis builds up cytosolic NADH that cannot be reoxidized, which impairs ureagenesis and can raise ammonia.
B. Reassess the calorie strategy with a metabolic specialist and avoid forcing a high-carbohydrate regimen (Best answer)
SLC25A13 loss impairs mitochondrial aspartate and redox handling. Adult citrin deficiency often requires a relatively lower-carbohydrate plan with higher protein and fat rather than universal glucose loading.
Reasoning steps for option B
What does SLC25A13 encode, and why does it matter?
It encodes citrin, the mitochondrial aspartate-glutamate carrier that supplies aspartate to ASS1 and moves reducing equivalents into mitochondria.
How should the calorie plan change?
A metabolic team should shift energy toward protein and fat and limit carbohydrate, the opposite of the usual glucose-heavy crisis regimen.
C. Diagnose ASS1 deficiency instead because any high citrulline value proves loss of the citrulline-consuming enzyme (Why this does not fit)
ASS1 deficiency can cause very high citrulline, but the confirmed transporter variants and carbohydrate intolerance support citrin deficiency. Shared metabolites do not erase genetic and physiologic context.
Reasoning steps for option C
Why might high citrulline point to ASS1 deficiency?
Marked citrullinemia is the classic signature of an ASS1 block, and the two conditions were once both called citrullinemia.
What outweighs the shared citrulline finding here?
Biallelic SLC25A13 variants establish the diagnosis, and worsening after a glucose load is a feature of citrin deficiency rather than ASS1 deficiency.
D. Stop all calories and allow fasting to lower the citrulline concentration (Why this does not fit)
Fasting increases catabolism and can worsen ammonia generation. The calorie composition should be corrected without removing energy support.
Reasoning steps for option D
What does fasting do to ammonia generation?
Fasting increases catabolism and can worsen ammonia generation.
How should the calorie plan be corrected?
The calorie composition should be corrected without removing energy support.
E. Use an unrestricted carbohydrate challenge at every follow-up to determine whether the transporter defect has spontaneously resolved (Why this does not fit)
Citrin deficiency is inherited and does not resolve through repeated substrate loading. Provoking recurrent decompensation would add risk without supplying useful routine management information.
Reasoning steps for option E
Can repeated carbohydrate loads reveal resolution of citrin deficiency?
Citrin deficiency is inherited and does not resolve through repeated substrate loading.
Why is a routine carbohydrate challenge harmful?
Provoking recurrent decompensation would add risk without supplying useful routine management information.
Takeaway: Citrin deficiency is a nutrition exception in which excessive carbohydrate can worsen adult hyperammonemia.
A. Use intravenous sodium phenylacetate and benzoate as the sole treatment for every episode (Why this does not fit)
Nitrogen scavengers have a defined role in acute cycle crises. Cirrhosis-related encephalopathy first requires correction of the precipitant and gut-directed therapy.
They lower ammonia directly in urea-cycle crises, and this patient's encephalopathy is also ammonia-related.
What should come first in cirrhosis-related encephalopathy?
Controlling the bleed and other precipitants and starting lactulose resolves most episodes; intravenous scavengers are not part of standard cirrhosis care.
B. Begin lifelong severe protein restriction and avoid investigating the gastrointestinal bleed (Why this does not fit)
Excessive restriction risks malnutrition and sarcopenia in cirrhosis. The bleed is a major precipitant and should be treated rather than ignored.
Reasoning steps for option B
What risk does severe protein restriction carry in cirrhosis?
Excessive restriction risks malnutrition and sarcopenia in cirrhosis.
Why must the gastrointestinal bleed be treated?
The bleed is a major precipitant and should be treated rather than ignored.
C. Treat the bleed and other precipitants, give lactulose for the overt episode, and use rifaximin as indicated to reduce recurrence (Best answer)
The gastrointestinal bleed increases intestinal nitrogen burden in a patient with impaired hepatic clearance. Cause correction plus lactulose treats the episode, while rifaximin has a role in preventing recurrent overt encephalopathy.
Reasoning steps for option C
How does a gastrointestinal bleed precipitate encephalopathy in cirrhosis?
The gastrointestinal bleed increases intestinal nitrogen burden in a patient with impaired hepatic clearance.
Which treatments manage the episode and prevent recurrence?
Cause correction plus lactulose treats the episode, while rifaximin has a role in preventing recurrent overt encephalopathy.
D. Order family testing for OTC variants before giving any encephalopathy treatment (Why this does not fit)
Inherited disease can present late, but the supplied cirrhosis and clear precipitant provide a more direct explanation. Therapy should not wait for an unrelated genetic workup.
Reasoning steps for option D
Why might an inherited cycle disorder be considered in an adult?
Partial OTC deficiency and other cycle defects can first present in adulthood after a protein load such as a gastrointestinal bleed.
Why should treatment not wait for OTC testing?
Known cirrhosis plus a bleed fully explains the episode and the encephalopathy needs treatment now; genetic testing is reserved for hyperammonemia without a liver explanation.
Takeaway: Cirrhosis-related encephalopathy is treated by correcting precipitants and using lactulose, with rifaximin for recurrence prevention when indicated.
A. Valproate-associated hyperammonemia remains possible and should prompt medication action plus evaluation for metabolic vulnerability (Best answer)
Valproate can raise ammonia even when routine liver tests are normal. New encephalopathy warrants urgent management, drug review, and consideration of an underlying cycle disorder.
Reasoning steps for option A
How can valproate raise ammonia while liver tests stay normal?
Valproate metabolites deplete carnitine and inhibit N-acetylglutamate synthesis, which slows CPS1 without injuring hepatocytes.
What should new lethargy and vomiting on valproate prompt?
Treat the ammonia, reduce or stop the drug with the prescriber, and consider carnitine, then look for a partial cycle defect such as OTC deficiency that valproate may have unmasked.
B. Normal liver tests exclude a medication effect, so the ammonia result can be disregarded (Why this does not fit)
Valproate-related hyperammonemia does not require hepatocellular injury. The neurologic symptoms make the abnormality clinically important despite normal transaminases.
Reasoning steps for option B
Does valproate hyperammonemia require liver injury?
Valproate-related hyperammonemia does not require hepatocellular injury.
Why does this ammonia result matter despite normal transaminases?
The neurologic symptoms make the abnormality clinically important despite normal transaminases.
C. The patient must have cirrhosis because every acquired hyperammonemia originates in advanced liver failure (Why this does not fit)
Cirrhosis is one acquired cause but is not established by this laboratory pattern. The medication exposure provides a recognized alternative mechanism.
Reasoning steps for option C
Does this laboratory pattern establish cirrhosis?
Cirrhosis is one acquired cause but is not established by this laboratory pattern.
Which exposure offers a better explanation?
The medication exposure provides a recognized alternative mechanism.
D. Valproate should continue unchanged until a liver biopsy proves drug toxicity, because stopping or revising therapy before histology would obscure the diagnosis (Why this does not fit)
A biopsy is not required to suspect this adverse effect. Continuing the implicated drug during symptomatic hyperammonemia can prolong harm while urgent management is delayed.
Reasoning steps for option D
Why might a biopsy seem necessary before blaming valproate?
Drug-induced liver injury is often confirmed histologically, and changing an effective antiseizure drug is a serious step.
Why is it unsafe to continue valproate unchanged?
Valproate hyperammonemia is diagnosed from the drug history and the ammonia level, and keeping the drug while the patient is encephalopathic can progress to coma.
Takeaway: Valproate can cause hyperammonemia despite normal routine liver tests and may expose an underlying cycle vulnerability.
A. It removes the pathogenic variant from every cell and prevents transmission to future children (Why this does not fit)
A liver graft changes hepatic enzyme capacity. It does not alter the recipient germline or inherited recurrence risk for descendants.
Reasoning steps for option A
Why might a transplant seem to cure the disease completely?
After transplant the new liver makes normal OTC and crises stop, so the disorder can seem gone.
Why does the risk for the child's own future children remain?
Eggs or sperm arise from the recipient's own germ cells, which still carry the OTC variant.
B. It guarantees reversal of every established cognitive and motor deficit, removes all extrahepatic consequences, and eliminates the need for future neurologic follow-up (Why this does not fit)
Preventing future crises differs from repairing prior brain injury. A hepatic graft also cannot promise resolution of manifestations generated outside the liver.
Reasoning steps for option B
What is the difference between preventing crises and repairing past injury?
Preventing future crises differs from repairing prior brain injury.
Can a liver graft resolve manifestations generated outside the liver?
A hepatic graft also cannot promise resolution of manifestations generated outside the liver.
C. It is useful only if all neurologic injury has already reversed before surgery (Why this does not fit)
Transplantation can be considered to prevent additional hyperammonemic injury. Existing deficits affect counseling but do not make improved hepatic disposal meaningless.
Reasoning steps for option C
Why can transplantation be considered despite existing deficits?
Transplantation can be considered to prevent additional hyperammonemic injury.
How do existing deficits affect counseling?
Existing deficits affect counseling but do not make improved hepatic disposal meaningless.
D. It can restore hepatic nitrogen disposal and prevent future crises, but it cannot change germline inheritance or guarantee recovery from prior brain injury (Best answer)
The new liver supplies functional ureagenesis and can stabilize ammonia control. Genetic transmission and established neurologic damage remain separate issues that require explicit counseling.
Reasoning steps for option D
What does a new liver provide for ammonia control?
The new liver supplies functional ureagenesis and can stabilize ammonia control.
Which two issues remain after transplantation?
Genetic transmission and established neurologic damage remain separate issues that require explicit counseling.
Takeaway: Liver transplantation can correct hepatic nitrogen disposal without changing germline inheritance or reliably reversing established neurologic injury.
A. CPS1 is cytosolic and uses glutamine for pyrimidines, while CPS2 is mitochondrial and uses free ammonia for urea (Why this does not fit)
The two enzymes are assigned to the opposite compartments and pathways. This reversal would incorrectly place ammonia disposal in the cytosolic pyrimidine system.
Reasoning steps for option A
Which compartments does this pairing give CPS1 and CPS2?
The two enzymes are assigned to the opposite compartments and pathways.
What would that reversal imply about ammonia disposal?
This reversal would incorrectly place ammonia disposal in the cytosolic pyrimidine system.
B. CPS1 is mitochondrial and uses free ammonia for ureagenesis, while CPS2 is cytosolic and uses glutamine for pyrimidine synthesis (Best answer)
CPS1 begins mitochondrial nitrogen disposal and depends on N-acetylglutamate activation. CPS2 belongs to the cytosolic multifunctional pyrimidine pathway and draws nitrogen from glutamine.
Reasoning steps for option B
Where does CPS1 act, and what activates it?
CPS1 begins mitochondrial nitrogen disposal and depends on N-acetylglutamate activation.
Where does CPS2 act, and which nitrogen source does it use?
CPS2 belongs to the cytosolic multifunctional pyrimidine pathway and draws nitrogen from glutamine.
C. Both enzymes are mitochondrial, but only CPS2 requires N-acetylglutamate (Why this does not fit)
CPS2 is cytosolic and is regulated differently from CPS1. N-acetylglutamate is the essential activator of CPS1.
Reasoning steps for option C
Where is CPS2 located?
CPS2 is cytosolic and is regulated differently from CPS1.
Which enzyme requires N-acetylglutamate?
N-acetylglutamate is the essential activator of CPS1.
D. Both enzymes use free ammonia, and their names differ only because one is expressed after birth (Why this does not fit)
The enzymes differ in substrate, compartment, regulation, and pathway. CPS2 uses glutamine nitrogen rather than serving as a developmental duplicate of CPS1.
Reasoning steps for option D
Do CPS1 and CPS2 differ only by developmental timing?
The enzymes differ in substrate, compartment, regulation, and pathway.
Which nitrogen source separates CPS2 from CPS1?
CPS2 uses glutamine nitrogen rather than serving as a developmental duplicate of CPS1.
E. CPS1 is a renal acid-excretion enzyme, while CPS2 converts circulating ammonia directly into urinary ammonium during chronic metabolic acidosis (Why this does not fit)
Neither assignment describes renal ammonium trapping. CPS1 and CPS2 synthesize carbamoyl phosphate for hepatic ureagenesis and cytosolic pyrimidine synthesis, respectively.
Reasoning steps for option E
Why might a carbamoyl phosphate synthetase seem linked to renal acid excretion?
Both enzymes handle nitrogen from ammonia or glutamine, the same substrates the kidney uses to excrete acid as ammonium.
Which organs and pathways do the two enzymes actually serve?
CPS1 works in liver mitochondria to start urea synthesis, and CPS2, part of the CAD protein, starts pyrimidine synthesis in nearly all cells; neither traps ammonium in urine.
Takeaway: CPS1 is the mitochondrial ammonia-using urea-cycle enzyme, whereas CPS2 is the cytosolic glutamine-using pyrimidine enzyme.
A. Urinary urea is the main adaptable acid-trapping mechanism, so hepatic ureagenesis directly determines every change in net renal acid excretion (Why this does not fit)
Urea carries a large daily nitrogen load and reflects hepatic disposal. It is not the principal adaptable urinary buffer that increases to excrete an acid load.
Reasoning steps for option A
Why might urea seem to be the main acid-excretion route?
Urea carries a large daily nitrogen load and reflects hepatic disposal.
Is urea the adaptable urinary buffer for an acid load?
It is not the principal adaptable urinary buffer that increases to excrete an acid load.
B. Urinary creatinine rises to bind hydrogen ions and replaces the need for bicarbonate regeneration (Why this does not fit)
Creatinine excretion is useful for assessing filtration and collection adequacy. It does not serve as the major inducible nitrogen buffer for chronic acid excretion.
Reasoning steps for option B
What is urinary creatinine useful for?
Creatinine excretion is useful for assessing filtration and collection adequacy.
Is creatinine an inducible nitrogen buffer?
It does not serve as the major inducible nitrogen buffer for chronic acid excretion.
C. Urinary ammonium rises as an adaptable route for net acid excretion, distinct from hepatic conversion of waste nitrogen into urea (Best answer)
The kidney metabolizes glutamine and excretes NH4+ with accompanying new bicarbonate generation. This renal response shares nitrogen chemistry with ureagenesis but solves an acid-base problem.
Reasoning steps for option C
What does renal glutamine metabolism produce during chronic acidosis?
The kidney metabolizes glutamine and excretes NH4+ with accompanying new bicarbonate generation.
How does renal ammonium excretion differ from hepatic ureagenesis?
This renal response shares nitrogen chemistry with ureagenesis but solves an acid-base problem.
D. Plasma alanine is filtered unchanged to neutralize urine, making renal ammoniagenesis unnecessary (Why this does not fit)
Alanine transports carbon and nitrogen between tissues. It does not replace renal glutamine metabolism and ammonium excretion during chronic acidosis.
Reasoning steps for option D
What does alanine do in nitrogen transport?
In the glucose-alanine cycle, muscle sends amino nitrogen to the liver as alanine, making it a major nitrogen carrier in blood.
Why can filtered alanine not buffer an acid load?
The proximal tubule reabsorbs nearly all filtered alanine and it carries no protons out; net acid excretion rises through ammonium made from glutamine and through titratable acid.
Takeaway: Renal ammonium excretion adapts to metabolic acidosis and is physiologically distinct from hepatic urea production.