
GI
Gallstones and Biliary Colic
Explain how gallstones form, locate the obstruction behind biliary pain, and distinguish observation or planned surgery from complications needing urgent care.
Finding a gallstone is not the same as finding the cause of every abdominal symptom. Start with the location of the stone, the pattern of illness, and whether obstruction has resolved.
Separate a gallbladder stone from a duct stone
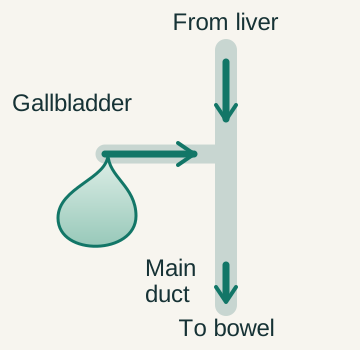
The liver produces bile. The gallbladder stores and concentrates it between meals, then releases it through the cystic duct. Bile from the liver and gallbladder reaches the intestine through the common bile duct. These connected spaces have different clinical roles, so a report of stones should always specify where they are located. [2] [7]
 Enlarge the whole image
The gallbladder joins a shared liver-to-bowel route through a side branch. This is a functional map, not a scaled anatomical atlas.
Bone Wizardry. Original educational schematic. Source and provenance
Cholelithiasis means gallstones, usually within the gallbladder. Many remain silent. Biliary colic is pain associated with transient obstruction of gallbladder outflow, often when a stone lodges near the gallbladder neck or cystic duct. When that obstruction resolves, the attack can settle. The stone may remain available to cause another episode. [2] [3]
Choledocholithiasis means a stone in the common bile duct. It may impair drainage from the liver, increase conjugated bilirubin, and predispose to cholangitis or pancreatitis. A silent common-duct stone is not managed by automatically applying the reassurance used for an incidental stone in a normal gallbladder and normal biliary tree. [1] [6]
A useful location map separates the gallbladder reservoir, its outlet, and the shared downstream duct. A stone can migrate between locations, so its site of formation does not guarantee its final location. The same patient may have a gallbladder source of stones and a separate retained stone in the common duct. [4] [6]
Build a cholesterol stone from three cooperating processes
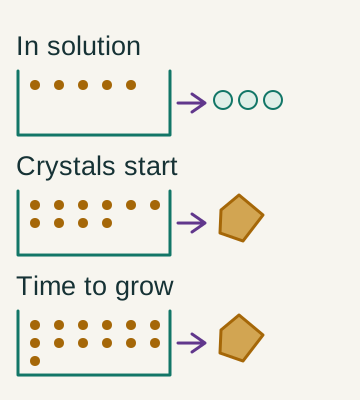
Cholesterol is carried in bile alongside bile salts and phospholipids. These components help keep cholesterol dispersed. When cholesterol exceeds the capacity of the surrounding bile to maintain it in solution, the bile is supersaturated. Supersaturation creates an opportunity for crystals; it does not guarantee that a clinically important stone immediately appears. [2] [4]
 Enlarge the whole image
Composition, crystal formation and time for aggregation cooperate. Symbols are qualitative, not cholesterol measurements or a prediction of stone growth.
Bone Wizardry. Original educational schematic. Source and provenance
Crystal formation also needs a place to begin and time to grow. Gallbladder mucus can provide a matrix on which material collects. Reduced gallbladder emptying allows crystals to remain and aggregate rather than being cleared. Composition, nucleation, and stasis therefore cooperate. A single risk factor helps explain one part of this process, but does not explain every stone. [2] [4] [5]
Obesity and metabolic factors can increase biliary cholesterol and alter gallbladder function. Estrogen exposure, including pregnancy or estrogen-containing medicines, is associated with increased risk. A family history and increasing age can also contribute. These associations are not diagnostic requirements. A person without the familiar risk profile can still have symptomatic gallstones. [2]
Rapid weight loss can also raise risk, despite the long-term benefits of appropriate weight management. During rapid weight loss or prolonged inadequate intake, the liver may release more cholesterol into bile while the gallbladder empties less effectively. Avoid presenting crash dieting as a reliable gallstone-prevention strategy. Selected prevention during medically supervised rapid weight loss is different from treating every established stone with a dissolving medicine. [5]
- Supersaturation More cholesterol is present than the bile mixture can reliably keep dispersed. [2] [4]
- Nucleation A matrix permits crystals to begin collecting. [4]
- Retention and growth Poor emptying gives crystals time to aggregate into stones. [2] [5]
Compare black and brown pigment without confusing formation with destination
Pigment stones contain calcium bilirubinate rather than being predominantly cholesterol. Bilirubin availability and the environment in which it is processed influence their formation. Black and brown are useful names for characteristic material, but a color label does not by itself tell you whether a patient currently has obstruction or infection. [4]
 Enlarge the whole image
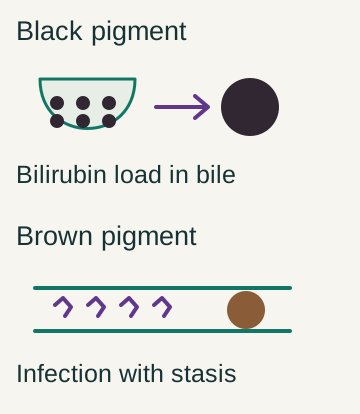
Black pigment is linked to bilirubin loading of usually sterile gallbladder bile. Brown pigment is linked to infection and stasis. Formation site is not a permanent location restriction.
Bone Wizardry. Original educational schematic. Source and provenance
Black pigment stones classically form in sterile gallbladder bile. Increased bilirubin delivery into bile during chronic hemolysis or ineffective red-cell production can promote their formation. Cirrhosis and altered intestinal bilirubin cycling can also contribute. Hereditary spherocytosis and sickle cell disease therefore supply a mechanistic explanation through ongoing red-cell turnover, not through a requirement for infected bile. [4]
Brown pigment stones are associated with stagnant, often infected bile. Bacterial beta-glucuronidase can remove glucuronic acid from bilirubin, allowing poorly soluble pigment to precipitate with calcium. Other bacterial enzymes release fatty acids that form calcium soaps. Duct strictures and some biliary parasites can create the stasis and infection that support this process. [4]
Black stones most often originate in the gallbladder, but can migrate into a duct. Brown stones often arise in the ducts, but may occur elsewhere in the biliary tree, including the gallbladder. Ileal disease or resection can alter both bile-salt recycling and bilirubin cycling, so that history does not prove a cholesterol composition. Distinguish the mechanism that formed a stone from the complication caused by where it is now. [4]
Black pigment
Bilirubin loading favors formation in sterile gallbladder bile; later migration is possible. [4]
Brown pigment
Stasis and bacterial processing favor pigment and calcium-soap precipitation. [4]
Recognize an attack and identify evidence that it is no longer uncomplicated
An uncomplicated biliary attack commonly produces sustained upper abdominal or right upper abdominal pain, sometimes after a substantial meal. Despite the word colic, the pain need not rise and fall in repeated waves. Nausea may accompany it. Relief occurs when the obstruction resolves, and recurrent attacks are common when the gallbladder still contains stones. [3]
Duration is informative but not a permission slip to wait. Pain lasting several hours, increasing tenderness, fever or chills, persistent vomiting, jaundice, dark urine, or pale stools should prompt medical assessment. An ill patient does not need to reach a memorized six-hour mark before evaluation. Similarly, a brief episode does not establish a benign cause solely because it stopped. [3]
Acute cholecystitis is inflammation of the gallbladder, commonly after persistent outlet obstruction. Ongoing pain, localized tenderness, an inspiratory pause during palpation over the gallbladder region, and inflammatory findings support the diagnosis in context. Ultrasound may show wall thickening or surrounding fluid. No single symptom, examination sign, or duration independently settles every case. [1] [2]
Jaundice or a cholestatic laboratory pattern raises concern for a common-duct problem rather than simple transient cystic-duct obstruction alone. Fever with duct obstruction raises concern for cholangitis. Severe epigastric pain with evidence of pancreatic injury raises a pancreatitis question. These are related complications, but naming all of them biliary colic loses the decision that matters. [2] [3] [6]
Transient episode
Pain resolves after temporary outflow obstruction clears. [3]
Start with ultrasound and use further tests selectively
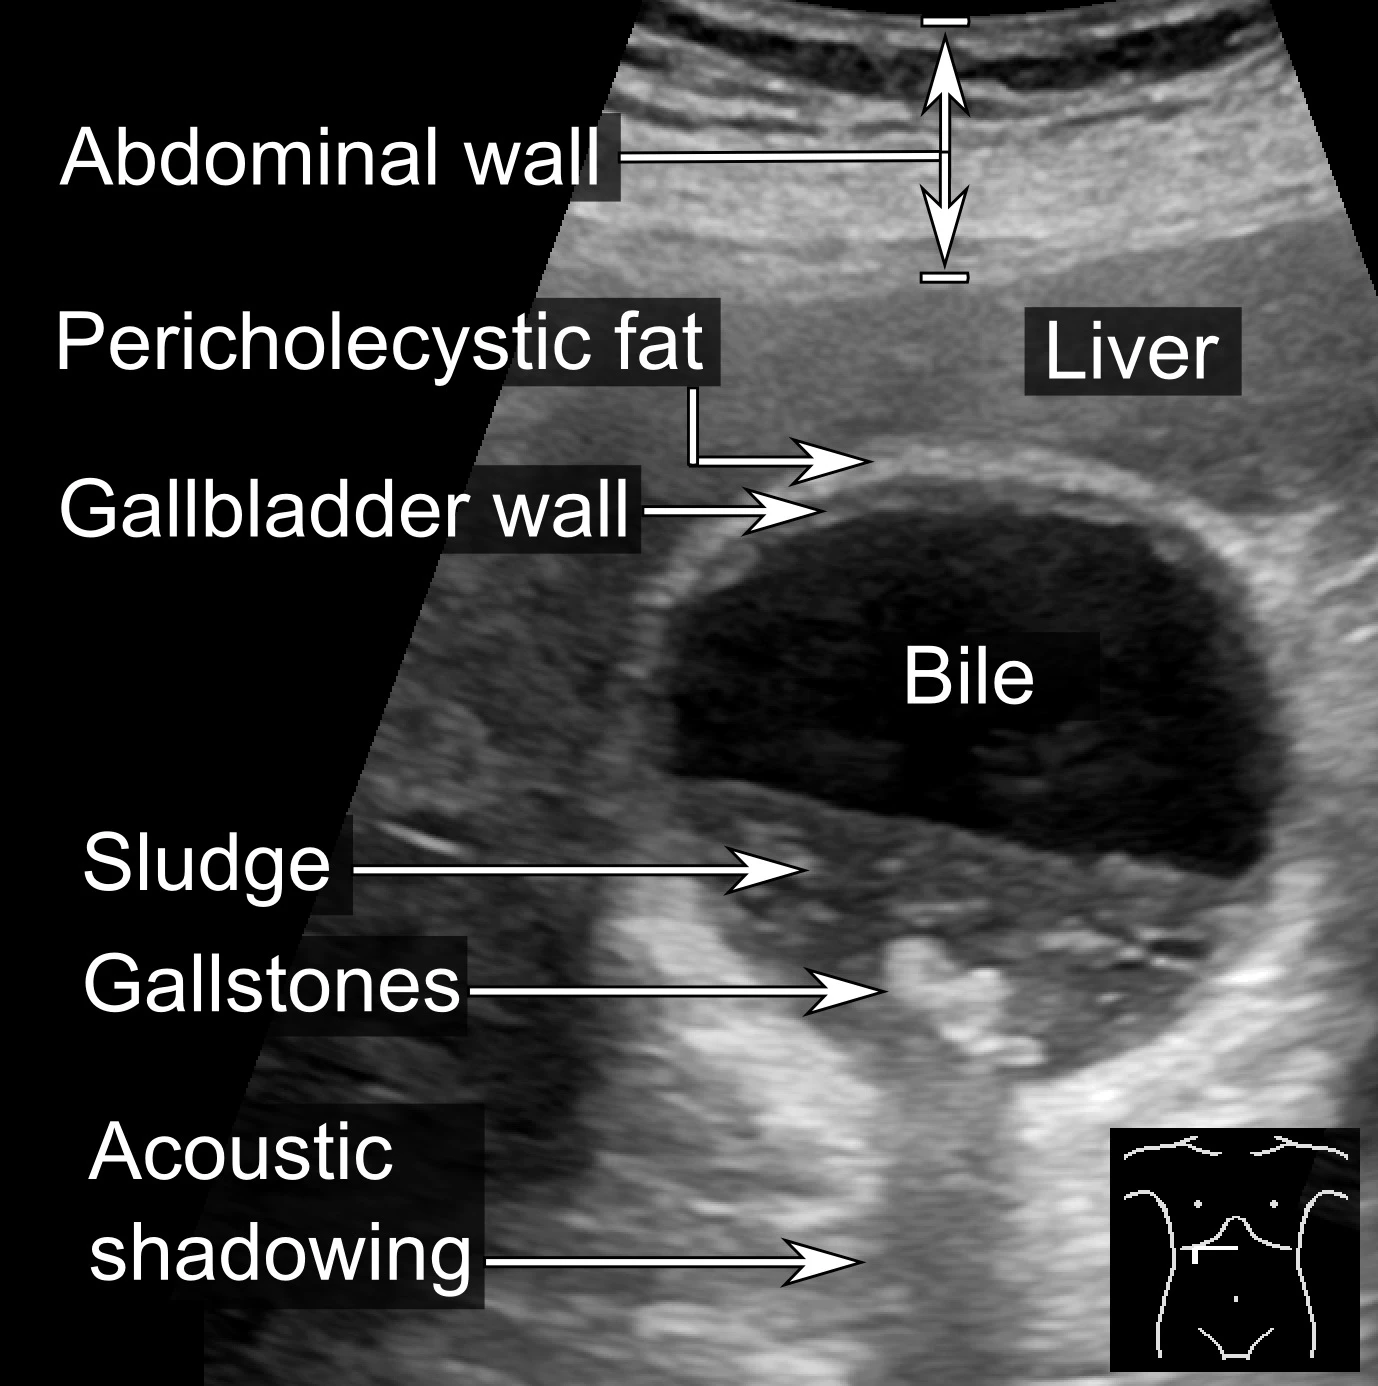
For suspected gallstone disease, NICE recommends liver blood tests and abdominal ultrasound. Ultrasound can establish whether gallbladder stones are present and assess gallbladder and duct features. A typical stone may cast an acoustic shadow, but the full interpretation includes mobility, location, wall appearance, and the surrounding clinical findings rather than one image feature alone. [1]
 Enlarge the whole image
Published gallbladder ultrasound showing stones, acoustic shadows and sludge. The source reports no current cholecystitis. The image supports recognition, not diagnosis from a single finding. Whole image retained.
Mikael Haggstrom. CC0 1.0. Source and provenance

A scan showing gallstones does not prove that nonspecific bloating, reflux, or every episode of abdominal discomfort is caused by them. Compare the symptoms with the anatomic findings and consider other diagnoses when the presentation does not fit. Removing an incidental finding is not guaranteed to solve an unrelated symptom. [1] [2]
When ultrasound does not show a common-duct stone but the duct is dilated or liver tests are abnormal, NICE recommends considering MRCP. This magnetic resonance study maps the ducts without entering them. EUS may help when the diagnosis remains uncertain. EUS requires an endoscope and is minimally invasive rather than an external scan. [1] [6]
ERCP is most useful when duct therapy or focused sampling is needed. It can extract a retained duct stone or drain an obstructed system, but has procedural risks and is not required for every gallbladder stone. In intermediate-risk adults, MRCP or EUS can avoid an unnecessary diagnostic ERCP. A demonstrated duct stone or cholangitis changes the need for intervention. [6]
- Gallbladder question Use ultrasound with symptoms and liver tests. [1]
- Uncertain common-duct question Use MRCP or EUS when the probability warrants confirmation. [1] [6]
- Established therapeutic need Use the appropriate endoscopic or surgical clearance pathway. [1] [6]