Pancreatic Pseudocyst and Pancreatitis Complications
Classify pancreatic collections by wall and contents, identify the complication, and choose observation, drainage or urgent vascular treatment.
A pancreatic collection is a description, not an instruction to insert a drain. First establish what occupies the space. Then decide what harm it is causing, whether the patient can safely wait, and which route can address the problem without injuring a vessel or creating a persistent leak.
Does every patient need another CT? No. Improving pain and successful feeding are different from recurrent pain, fever, vomiting, jaundice, declining hemoglobin or new organ dysfunction. Choose imaging to answer the new clinical question, rather than to follow the lipase concentration or repeatedly measure an uncomplicated collection. An early scan can underestimate evolving necrosis. [2][8]
Contrast-enhanced CT shows where pancreatic tissue fails to enhance, the distribution of collections, gas, obstruction and vascular complications. A collection can involve the pancreas, surrounding tissues, or both. Contrast use and urgency require assessment of kidney function, allergy and the patient's stability. Suspected arterial bleeding needs an arterial imaging strategy, often CT angiography when the patient can tolerate it, not an elective fluid aspiration. [1][4]
MRI can distinguish liquid from internal nonliquid material when CT is uncertain. MRCP maps the pancreatic duct and possible leakage, communication or disconnection. EUS views the collection from the stomach or duodenum and uses Doppler to identify intervening vessels. These tests answer complementary questions: contents, duct continuity, and safe access. No single reassuring slice establishes all three. [4]
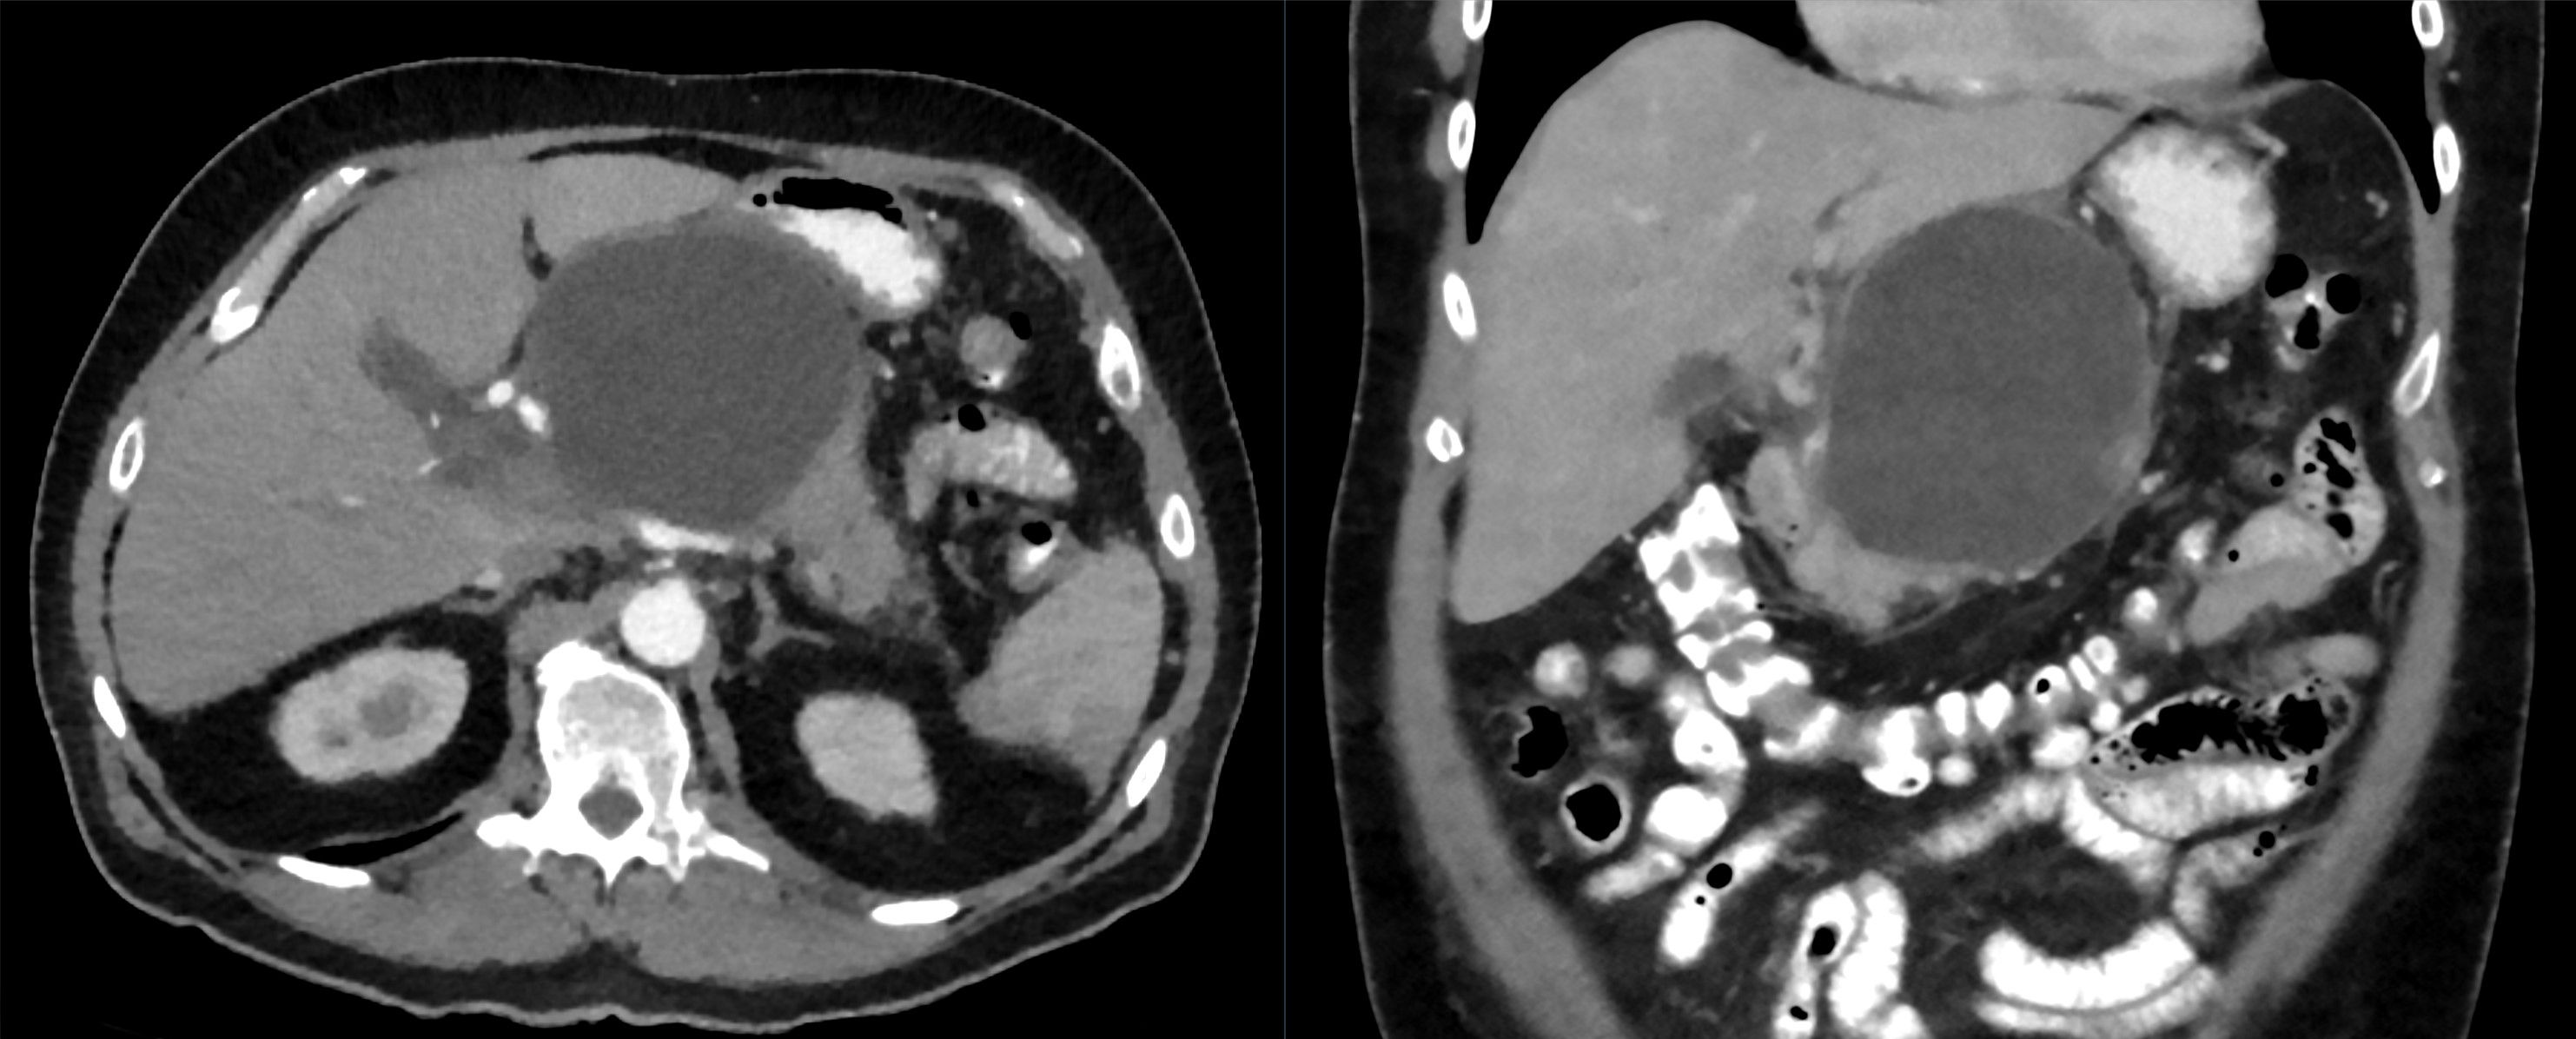
Compare the clinical CT provided with this section with its source description. Identify the large fluid-density space and the nearby contrast-containing stomach. The source reports a pseudocyst suitable for transgastric drainage. This example explains proximity; it does not let you determine infection, symptom duration, complete duct anatomy or the safety of every possible needle trajectory from the displayed images alone.
Identify the collection and the neighboring stomach. These displayed images alone do not establish infection, timing, complete duct continuity or the safety of a particular puncture path. Image: Hellerhoff; original source; CC BY-SA 4.0.
Choose the unanswered question: six weeks after pancreatitis, CT shows a mature collection but cannot resolve internal particles. Would another diameter measurement or better characterization of the contents be more useful before planning treatment?
Check the imaging choice
MRI or EUS can clarify whether solid debris is present. That distinction changes whether drainage alone is likely to suffice.
Now change the presentation: sudden blood loss and hypotension replace early satiety. The important unknown is the bleeding source, so vascular assessment and resuscitation take priority over fine characterization of debris. Before drainage, also reconsider a cystic neoplasm when the history or imaging does not fit an inflammatory collection. [9]
Separate the clock, the wall and the contents
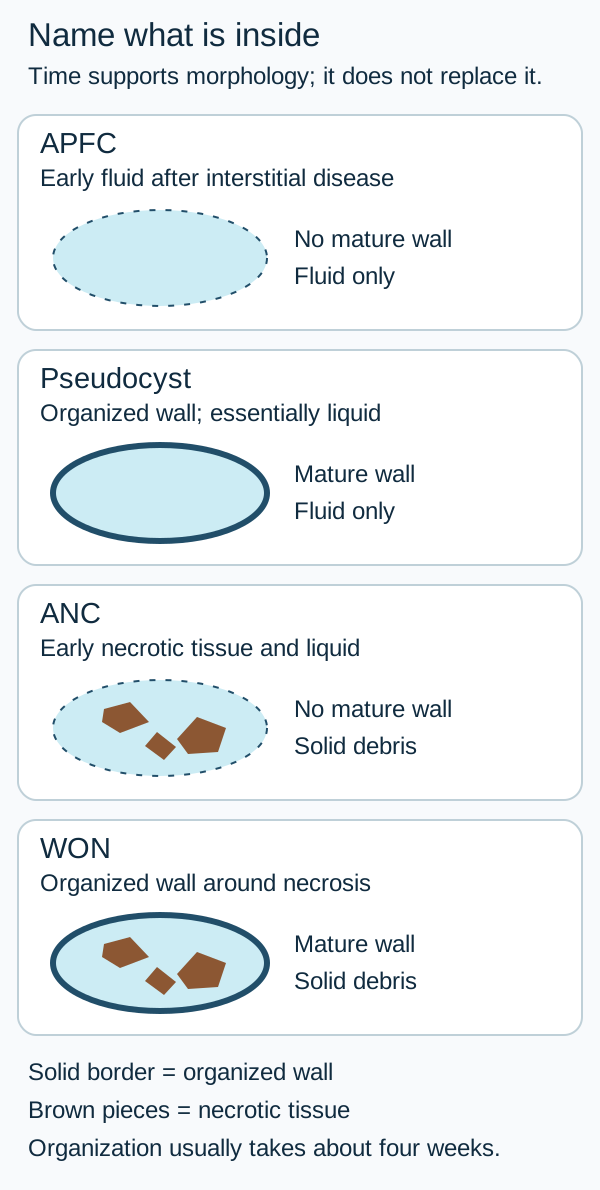
Can every collection after pancreatitis be called a pseudocyst? No. Interstitial edematous pancreatitis leaves viable inflamed tissue. Necrotizing pancreatitis adds dead pancreatic or peripancreatic tissue. A mature capsule can enclose either mostly liquid or a mixture containing necrotic solids. These are different targets even when they look similarly round. [1]
Use time from symptom onset, then confirm morphology
Contents
Early, without a mature wall
Encapsulated, usually after about four weeks
ContentsEssentially fluid only
Early, without a mature wallAcute peripancreatic fluid collection, or APFC, after interstitial pancreatitis
Encapsulated, usually after about four weeksPancreatic pseudocyst
ContentsNecrotic tissue with variable fluid
Early, without a mature wallAcute necrotic collection, or ANC
Encapsulated, usually after about four weeksWalled-off necrosis, or WON
Use the accompanying four-cavity schematic to trace one variable at a time. A solid outline represents an organized wall; irregular internal pieces represent necrotic debris. A border alone does not turn debris into fluid. The four-week interval describes typical maturation, not a biological switch at midnight. Record the actual wall and contents when the calendar and the image disagree. [1]
Classify using wall and contents. Dashed boundaries indicate an incompletely organized collection, not a literal perforation. The schematic does not impose a rigid four-week cutoff. [1]
Sort a six-week encapsulated collection containing solid particles into the map. Keep its date and wall fixed, then imagine the particles were absent on a sufficiently detailed study. Which name changes?
First comparison: retain the particles
A mature cavity containing necrotic material is WON. Its liquid portion does not make the entire cavity a pseudocyst.
Second comparison: change only the contents
A mature inflammatory cavity containing essentially fluid only fits a pseudocyst. A drainage plan for the first cavity must account for tissue that may remain after liquid exits.
Two cautions prevent overconfidence. During the first week, an ANC may appear deceptively fluid-like; known necrotizing disease and later imaging help resolve the distinction. Also, after necrotic tissue has been cleared, leakage from a disconnected but viable distal gland can form a new fluid-only pseudocyst. Do not rename residual necrosis as a pseudocyst merely because some material has liquefied. [1]
Transfer the map to a day-10 patient with a homogeneous, nonencapsulated collection after interstitial pancreatitis. That morphology fits APFC. If the patient is eating and improving, the name provides no independent reason to drain. Classification describes the cavity; the next section evaluates the patient.
A safer wall is not a treatment indication
Must a collection be drained when it reaches a certain size or age? No. An asymptomatic shrinking pseudocyst can be observed even when it is large. Important pain attributable to the collection, infection, vomiting, nutritional failure, gastric or biliary obstruction, recurrent pancreatitis, fistula or persistent systemic illness can justify intervention. Bleeding and peritonitis demand a different urgent pathway. [3][4]
Consider two patients at seven weeks. One has a 10 cm collection but eats normally, gains weight and has decreasing cavity size. The other has a 5 cm collection compressing the gastric outlet and cannot retain food. Compare nutritional function rather than diameter: the second patient has an active problem that the first does not.
For stable necrosis, delaying intervention until organization, commonly about four weeks after onset, makes tissue boundaries clearer and access more controlled. Debridement is particularly undesirable in the early acute period. Waiting is active care: support nutrition, monitor organ function, reassess infection, and arrange drainage capability if the trajectory worsens. [2][5]
Keep the same day-19 infected collection in mind. First, the patient improves with antibiotics and has stable perfusion. Then imagine rising vasopressor requirements despite appropriate antibiotics and resuscitation. Decide whether the benefit of waiting still outweighs the danger.
Compare the two trajectories
Improvement supports monitored postponement. Deterioration supports earlier source control with a feasible drainage route; it does not automatically require early open necrosectomy. Wall maturity influences how to intervene, but cannot excuse uncontrolled sepsis.
A selected stable patient with infected necrosis may improve sufficiently on antibiotics to avoid drainage. In POINTER, immediate drainage did not improve the overall complication burden compared with postponement, and the postponed group underwent fewer interventions. This does not support withholding source control from a deteriorating patient. [6]
As a separate assessment, distinguish local anatomy from pancreatitis severity. A collection without persistent organ failure makes the episode at least moderately severe, not automatically severe. Persistent organ failure lasting more than 48 hours defines severe acute pancreatitis. A small collection can coexist with severe physiology. [1]
Trace an exit that the anatomy can support
Is the shortest route always the safest? A mature symptomatic cavity closely apposed to the stomach or duodenum can often be drained internally under EUS guidance. The path must avoid vessels and provide stable access. A fluid-only pseudocyst needs an outlet when treatment is indicated; it has no necrotic tissue target for debridement. For WON, the outlet may be only the first part of treatment. [4][9]
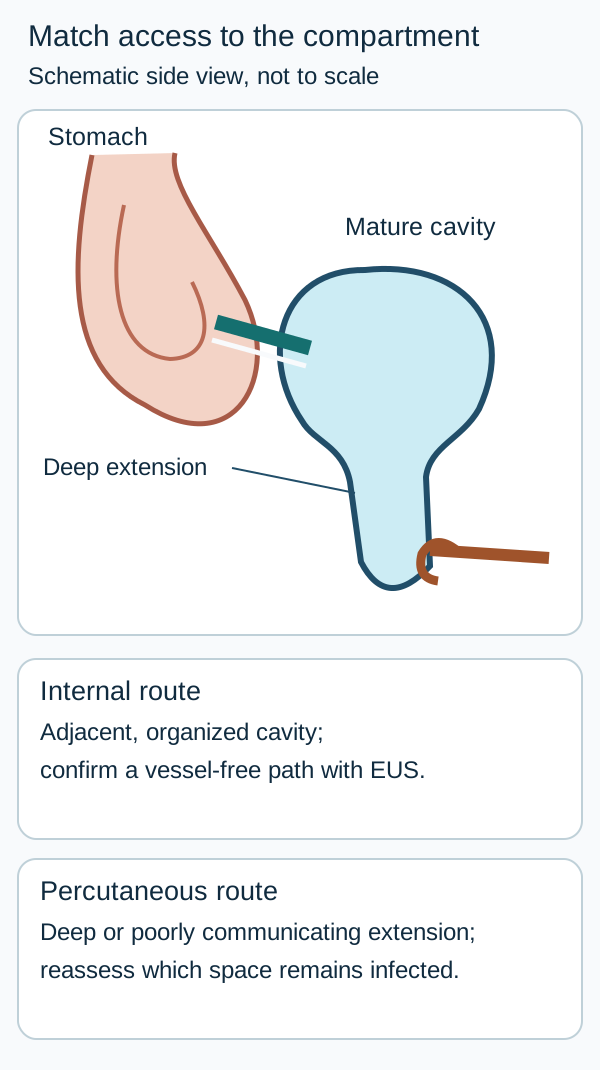
In the access schematic, trace a route from the gastric lumen into the adjacent mature cavity. Then follow the dependent extension toward the pelvis. One opening near the stomach may not empty that distant compartment. Percutaneous drainage can complement internal drainage for paracolic or pelvic extensions, and can provide source control in selected early infected collections or patients too ill for other approaches. [3]
A patent internal outlet may not adequately drain a distant compartment. Route selection also requires real cross-sectional imaging, vessel assessment and procedural expertise. [3][4][5]
Before creating any route, evaluate pseudoaneurysm, collateral veins, bowel interposition and the duct. A venous collateral crossing an otherwise short EUS path is not harmless because it is not an artery. Contrast studies and Doppler guide route selection; safe endoscopic treatment requires appropriate expertise with interventional radiology and surgical support. [4][9]
The upper cavity has decompressed after transgastric drainage, but an infected pelvic extension remains and fever persists. Trace which compartment still lacks effective drainage. Would enlarging the same gastric opening necessarily drain the dependent space?
Check the remaining compartment
A separate percutaneous route may be needed for the deep extension. The remaining collection's location, not a preference for one procedure name, determines the next access plan.
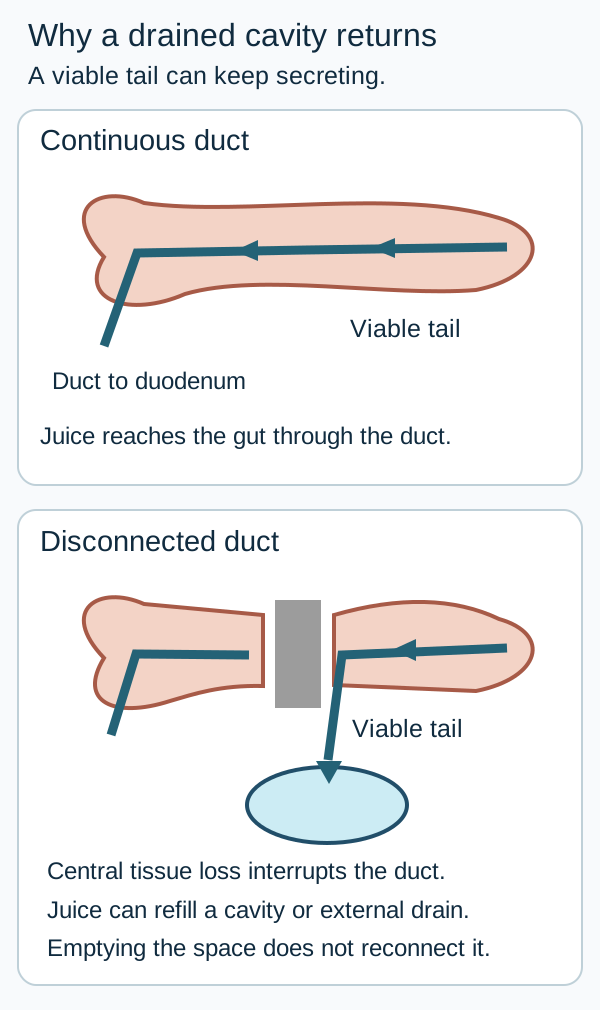
A different reason for recurrence is disconnected pancreatic duct syndrome. Necrosis across the neck or body can isolate a viable tail. That tail continues producing pancreatic juice but lacks continuity with the duct draining into the duodenum. Fluid can reaccumulate after a cavity is emptied or escape through a persistent external fistula. The duct diagram shows why treating the cavity does not necessarily correct the source. [1][5]
The schematic distinguishes a continuing pancreatic source from its fluid destination. It does not imply that every anatomical disconnection is symptomatic or requires surgery. [1][3][5]
Partial duct disruption may be bridgeable with a transpapillary stent; a complete disconnection is not simply bridged in the same way. Persistent leakage, distal disease or recurrent collections require a multidisciplinary plan that may include durable internal drainage or surgery according to anatomy, expertise and operative fitness. A suspected neoplasm also requires diagnostic evaluation rather than routine cyst drainage. [4][9]
For transfer, imagine that the entire cavity resolves but a high-output external drain remains and imaging shows an isolated enhancing tail. Repeating cavity drainage without investigating the duct would address the destination of the fluid, not its continuing origin.
Identify what the collection is injuring
Does fever prove that necrosis is infected? Inflammation itself can produce fever and leukocytosis. New deterioration after improvement, bacteremia without another source, or gas within an untreated necrotic collection strengthens the infection assessment. Recent drainage can introduce gas, and an enteric fistula can also explain it. Interpret gas in context instead of diagnosing infection from that sign alone. Routine needle aspiration is unnecessary in most cases when clinical and imaging evidence already supports treatment. [3][5]
Hemorrhage is a different problem. Inflammation and pancreatic enzymes can injure an adjacent artery, producing a pseudoaneurysm that may bleed into a collection, the gastrointestinal tract or the peritoneum. Sudden pain, a substantial hemoglobin decline, hematemesis or shock demands resuscitation and urgent hemostatic assessment. Angiographic embolization is often the preferred vascular treatment when feasible. Do not puncture or drain a cavity across an untreated pseudoaneurysm. If bleeding cannot be controlled endovascularly, urgent surgery may be necessary. [4][8]
Connect the injured structure to the consequence
Structure
Possible consequence
Question to resolve
StructureSplenic or other nearby artery
Possible consequencePseudoaneurysm and major bleeding
Question to resolveWhere is the active arterial source?
StructureSplenic vein
Possible consequenceVenous obstruction with gastric collateral veins
Question to resolveAre collaterals or varices present along a proposed route?
StructurePortal or mesenteric venous system
Possible consequenceThrombosis with possible venous congestion
Question to resolveHow extensive is thrombosis and is bowel threatened?
StructureStomach, duodenum or bile duct
Possible consequenceVomiting, feeding failure or obstructive jaundice
Question to resolveIs the collection compressing the lumen?
StructurePancreatic duct or bowel wall
Possible consequencePancreatic ascites, external or enteric fistula, peritonitis
Question to resolveWhere is fluid escaping, and is there ischemia or perforation?
Splenic vein thrombosis can redirect splenic venous drainage through short gastric collaterals and cause isolated gastric varices without cirrhosis. Portal extension and bleeding risk affect management; anticoagulation is not a universal answer for every pancreatitis-associated venous thrombosis. Colonic ischemia or perforation, particularly near a diseased adjacent pancreatic region, needs urgent surgical assessment. A fistula without peritonitis still needs anatomical and infection assessment rather than an automatic identical operation. [5][8]
A patient awaiting drainage develops hypotension and a rapid hemoglobin decline. The vascular study shows arterial contrast entering the cavity. Identify what must be controlled before making an outlet.
Check the treatment order
Control the bleeding vessel while resuscitating. A drain does not repair an arterial defect and can worsen hemorrhage.
Now substitute gastric varices with a patent portal vein and normal liver architecture. Trace the splenic venous drainage instead of assuming arterial erosion or generalized cirrhosis. The complication's anatomy changes the assessment even though pancreatitis remains the initiating illness.
Escalate only for an unresolved problem
Does every necrotic cavity need its tissue extracted? Start with the least invasive effective strategy and reassess the result. Observation is appropriate for uncomplicated improving collections. For infected necrosis, provide appropriate intravenous antibiotics, nutrition and supportive care; arrange drainage when infection is not controlled or important complications require it. Stable patients can often await organization. [3][5]
Antibiotic selection should cover likely organisms, penetrate necrotic tissue, and reflect cultures, renal function, allergy and local resistance. A carbapenem or another appropriate broad-spectrum regimen may be selected; metronidazole alone does not provide adequate enteric gram-negative coverage. Neither prophylactic antibiotics for sterile necrosis nor routine empirical antifungal therapy is recommended. Treat an infection elsewhere on its own merits rather than labeling every fever as pancreatic infection. [2][3][8]
Maintain oral intake when tolerated. If vomiting, ileus or obstruction prevents adequate intake, use an appropriate enteral route when feasible, such as feeding beyond a gastric outlet obstruction. Parenteral nutrition is reserved for patients in whom oral or enteral feeding is not feasible or tolerated. Prolonged fasting solely to suppress pancreatic activity is not the treatment goal. [2][3]
After drainage, reassess clinical improvement, drain function, cavity compartments and residual solids. Persistent illness can reflect inadequate drainage, retained infected debris, a different infection or a bowel complication. In suitable WON, irrigation and direct endoscopic necrosectomy can address tissue that remains after an adequate outlet. Minimally invasive surgery is another escalation option. Open surgery retains a role for inaccessible disease, failed less invasive treatment or a separate surgical emergency. [3][8]
PANTER compared a drainage-first step-up strategy with initial open necrosectomy. The step-up group had fewer events in the composite of major complications or death; the trial did not demonstrate a significant difference in mortality alone. The practical lesson is not that surgery is forbidden, but that some patients recover without its added burden. [7]
After drainage of infected WON, one patient becomes afebrile, eats and no longer needs organ support despite residual debris. Another remains septic after drain patency and other infection sources have been assessed. Predict who needs further evaluation for debridement.
Compare response rather than scan perfection
The improving patient does not need debridement merely to clear every residual particle. Persistent sepsis attributable to retained infected tissue supports escalation after checking whether a drainable compartment has been missed.
Follow recovery beyond the procedure: pain, oral intake, weight, infection, bleeding, recurrent collection and signs of pancreatic endocrine or exocrine dysfunction all matter. Persistent or recurrent fluid prompts a duct assessment. Address the cause of pancreatitis and arrange individualized clinical follow-up with selective imaging; no single scan interval or device duration fits every collection. [5]
Name the cavity, identify the harm, assess whether waiting is safe, map the anatomy, and judge the response. A large diameter, a four-week birthday or residual debris cannot replace those decisions.
Apply the lesson
Case 1
Show answer and explanations for case 1
A. Arrange transgastric drainage this admission (Why this does not fit)
Internal drainage can treat a symptomatic mature inflammatory collection. This patient is improving and the collection lacks an organized wall. A visible fluid collection is not itself an intervention indication.
Reasoning steps for option A
Could transgastric drainage treat a symptomatic mature inflammatory collection?
Yes, but this patient is eating normally, needs less analgesia, and has a wall-free collection rather than a mature symptomatic one.
Does the CT support transgastric drainage during this admission?
No. The homogeneous collection has no definable wall, and the patient is improving.
Does seeing this peripancreatic fluid alone justify internal drainage?
No. Without obstruction or another demonstrated complication, the collection itself is not an indication to intervene.
B. Continue clinical observation and oral nutrition (Best answer)
An uncomplicated APFC commonly resolves without intervention. Interstitial disease, homogeneous wall-free fluid and recovering intake support observation. Interpret collection morphology together with current function.
Reasoning steps for option B
Is observation reasonable for this uncomplicated acute peripancreatic fluid collection?
Yes. Such collections commonly resolve without intervention, and this patient is recovering.
Which case findings support continued oral nutrition and observation?
The pancreas enhances throughout, the fluid is homogeneous and wall-free, and the patient is eating normally with less pain.
How should the CT finding affect care while this patient improves?
Its uncomplicated morphology should be considered alongside recovering function, supporting clinical observation rather than a procedure.
C. Begin antibiotics and obtain interval imaging (Why this does not fit)
Antibiotics are useful for suspected infection, with reassessment of response. There is no supplied infection evidence and recovery is progressing. Sterile fluid does not need prophylactic antimicrobial treatment.
Reasoning steps for option C
When would antibiotics and reassessment fit a peripancreatic collection?
They would fit suspected infection, but this collection has no gas or other supplied evidence of infection.
Do these findings support starting antibiotics now?
No. The patient is improving, and the CT shows no evidence of an infected collection.
Does this apparently sterile collection need prophylactic antibiotics while intake recovers?
No. The fluid finding alone does not warrant antimicrobial treatment.
D. Place a percutaneous catheter for decompression (Why this does not fit)
Percutaneous drainage can treat infected or otherwise troublesome collections. Neither infection nor a pressure-related complication is present here. Choose drainage for a demonstrated problem rather than early fluid accumulation.
Reasoning steps for option D
Could a percutaneous catheter treat a troublesome peripancreatic collection?
Yes, if infection or another complication required drainage, neither of which is identified here.
Is decompression needed for this collection at day 10?
No pressure-related complication or obstruction is identified, and the patient is improving.
What would justify catheter drainage instead of observing this early fluid collection?
A demonstrated problem such as infection or symptomatic compression, not the presence of fluid alone.
Takeaway: An improving early fluid-only collection after interstitial pancreatitis can be observed.
A. Transgastric drainage with tissue clearance if response is inadequate (Best answer)
An internal outlet can drain WON, with later debridement when necessary. The mature symptomatic cavity has a safe gastric route but contains solid necrotic material. Liquid drainage and extraction of retained necrotic tissue are different tasks.
Reasoning steps for option A
Can a transgastric outlet treat this mature, symptomatic collection?
Yes. Its apposition to the stomach and vascular mapping support an internal route for draining walled-off necrosis.
How should the MRI findings affect the transgastric plan?
Substantial nonenhancing solid fragments mean drainage may need to be followed by tissue clearance if the response is inadequate.
Why might drainage alone fail to resolve this patient's vomiting and weight loss?
The cavity contains retained necrotic tissue as well as liquid, and tissue extraction is a different task from liquid drainage.
B. Needle aspiration followed by removal of the needle (Why this does not fit)
Aspiration can sample a cavity or temporarily evacuate liquid. A symptomatic debris-containing cavity requires a durable treatment plan rather than a single aspiration. The contents and clinical burden determine whether sampling is enough.
Reasoning steps for option B
What could needle aspiration accomplish in this cavity?
It could sample the contents or temporarily remove liquid, but it would not provide durable treatment for the symptomatic debris-containing cavity.
Would a single aspiration adequately address this patient's collection?
Unlikely. Persistent vomiting and weight loss accompany substantial solid material that a single aspiration would leave behind.
Why is sampling alone insufficient as the procedural plan here?
MRI shows solid fragments and the cavity is causing ongoing symptoms, so its contents and clinical burden call for more than sampling.
C. Transpapillary stenting without cavity drainage (Why this does not fit)
Duct-directed therapy can help selected communicating collections or bridgeable leaks. The supplied treatment target is a large obstructing cavity with substantial solids and favorable transmural access. A duct procedure does not automatically decompress a debris-rich cavity.
Reasoning steps for option C
When might transpapillary stenting help a pancreatic collection?
It can help selected communicating collections or bridgeable duct leaks, but neither is supplied as the treatment target here.
Does duct stenting alone address the described obstruction?
No. The described target is a large symptomatic cavity with substantial solids and favorable transmural access.
Why not assume a duct procedure will empty this cavity?
A transpapillary stent does not automatically decompress the debris-rich cavity associated with this patient's vomiting.
D. Primary open necrosectomy with postoperative drainage (Why this does not fit)
Open surgery can address necrotic tissue when less invasive approaches are unsuitable. An organized cavity with safe gastric access supports a less invasive initial strategy. Presence of solid tissue does not make open surgery the default first procedure.
Reasoning steps for option D
Could open necrosectomy remove this patient's solid necrotic tissue?
Yes, if less invasive approaches were unsuitable, but the organized cavity has a safe gastric route.
Which access findings favor transgastric drainage over primary open necrosectomy?
The seven-week encapsulated cavity is apposed to the stomach, with no mapped pseudoaneurysm or intervening vessels, supporting a less invasive initial approach.
Does MRI evidence of solid fragments require open surgery first?
No. Solid tissue may require later clearance, but it does not make primary open necrosectomy the default.
E. Percutaneous drainage followed by scheduled distal resection (Why this does not fit)
External drainage and resection can have roles in selected anatomy or persistent duct disease. No distal disconnection is described, while a direct internal route is available. Do not add gland resection without an anatomical indication.
Reasoning steps for option E
When might external drainage and distal resection have a role?
They can be useful in selected anatomy or persistent duct disease, neither of which is established here.
What argues against scheduled distal resection in this patient?
No distal duct disconnection is described, and a direct internal route to the cavity is available.
Why not add gland resection to the drainage plan now?
The imaging describes a symptomatic debris-containing cavity, not an anatomical indication for distal resection.
Takeaway: A mature debris-containing cavity is WON, even when much of it is liquid.
A. Persistence of the collection at the next visit (Why this does not fit)
Persistent collections deserve follow-up. Persistence without symptoms or a complication does not establish a need for intervention. Age of a cavity is not a substitute for clinical consequence.
Reasoning steps for option A
Does persistence of this collection warrant attention at follow-up?
Yes, it warrants follow-up, but persistence alone would not require intervention while the patient remains well.
Would persistence of the collection at the next visit, without new symptoms, overturn observation?
No. Without symptoms or a complication, persistence does not establish a need to intervene.
Why is the collection's continued presence insufficient here?
At eight weeks the patient is eating, regaining weight, and free of pain or obstruction, so cavity age is not a substitute for clinical consequence.
B. A diameter still exceeding 6 cm (Why this does not fit)
Size helps describe anatomy and procedural planning. This large cavity is shrinking without impairing function. A historical size threshold is not an absolute drainage criterion.
Reasoning steps for option B
Does a diameter above 6 cm describe a reason to plan drainage?
Size informs anatomy and procedural planning, but it does not by itself require drainage.
Why does the current 9 cm diameter not change the plan?
The collection has shrunk from 12 cm, and the patient eats full meals without pain or functional impairment.
Is exceeding the historical 6 cm threshold an absolute indication in this case?
No. Despite remaining above 6 cm, this asymptomatic collection is shrinking without a complication.
C. A visibly thicker mature capsule (Why this does not fit)
Wall organization may make drainage technically more feasible. Feasibility has improved but no treatment indication has appeared. A safer route does not create a reason to use it.
Reasoning steps for option C
What would a thicker capsule change about draining this asymptomatic collection?
It could make drainage technically more feasible, but would not itself create a treatment indication.
Does greater wall organization outweigh this patient's recovery?
No. The patient is eating, gaining weight, and has no identified obstruction or other complication.
Why not drain solely because the capsule offers a safer route?
A safer route addresses how to intervene, not why to intervene in this asymptomatic, shrinking collection.
D. Repeated vomiting from new duodenal compression (Best answer)
Luminal obstruction can prevent adequate nutrition. This new finding would convert an asymptomatic cavity into one causing a clinically important complication. Treat the consequence rather than the largest measurement.
Reasoning steps for option D
Would repeated vomiting from new duodenal compression justify intervention?
Yes. Luminal obstruction could prevent adequate nutrition, unlike the patient's current ability to eat full meals.
How would new duodenal compression change this case?
It would turn the currently asymptomatic collection into one causing a clinically important complication.
Why would vomiting matter more than the remaining 9 cm diameter?
Vomiting from compression would demonstrate impaired function, whereas size alone has not impaired this patient's recovery.
Takeaway: New functional obstruction changes management more than persistent size alone.
A. Perform open necrosectomy before discharge (Why this does not fit)
Surgical tissue clearance can control infection that persists despite less invasive care. Infection and clinical function are improving without a current surgical complication. Confirmed infection does not make immediate open debridement necessary.
Reasoning steps for option A
Can open necrosectomy control an infected necrotic collection?
Yes, particularly if infection persists despite less invasive care, but this patient's fever and bacteremia have resolved.
Is open necrosectomy needed before discharge based on the current course?
Not on the supplied findings. Intake is improving, and there is no organ failure, obstruction, or bleeding.
Does confirmed infection require immediate open debridement here?
No. Gas and bacteremia established infection, but the patient is responding to antibiotics without a current surgical complication.
B. Insert a transgastric stent within the next day (Why this does not fit)
Transmural drainage can provide source control in anatomically suitable infected collections. The patient is improving and the wall is not fully organized. The availability of drainage does not establish an advantage to immediate intervention.
Reasoning steps for option B
Could transgastric drainage provide source control for an infected collection?
Yes, when anatomy is suitable, but this patient is improving and the collection has only partial encapsulation.
Do the findings support placing a transgastric stent within the next day?
Not currently. Fever has resolved, cultures have cleared, and the wall is not fully organized.
Why not drain immediately despite the documented infection?
The favorable response gives no clear advantage to immediate intervention while the necrotic collection remains only partly encapsulated.
C. Continue monitored treatment and reassess drainage need (Best answer)
Postponement permits organization and some patients recover without drainage. Cleared bacteremia, improving intake and stable organ function support continued conservative treatment. Delay is justified by a safe trajectory, not by ignoring infection.
Reasoning steps for option C
Can drainage be deferred after this response to antibiotics?
Yes. Postponement allows further organization, and some patients recover without drainage.
Which infection and organ-function trends support postponing drainage of the partially encapsulated necrosis?
Blood cultures have cleared, fever has resolved, oral intake is improving, and there is no organ failure or obstructive or bleeding complication.
Why is reassessment rather than immediate drainage appropriate despite infection?
The choice rests on this patient's safe, improving trajectory; monitoring preserves the option to drain if that trajectory changes.
D. Obtain needle cultures before continuing antibiotics (Why this does not fit)
Sampling can help when diagnostic uncertainty would alter treatment. Bacteremia, gas and clinical response already support the diagnosis and treatment. Do not interrupt appropriate care merely to obtain routine confirmation from the cavity.
Reasoning steps for option D
When could needle sampling help manage this collection?
It could help if diagnostic uncertainty would change treatment, but gas, bacteremia, and the antibiotic response already support the diagnosis.
Are cavity cultures needed before continuing antibiotics?
No. Blood cultures have cleared and the patient is improving on appropriate antibiotics.
Why not pause effective treatment for routine cavity confirmation?
The infection is already supported by case findings, and needle sampling is not needed merely to confirm it while treatment is working.
Takeaway: Improving infected necrosis can be managed with monitored postponement of intervention.
A. Continue antibiotics until a complete wall is visible (Why this does not fit)
Delayed intervention can reduce procedural injury when patients remain stable. Escalating vasopressor requirements show that infection is not controlled. Wall maturation is a preference when waiting remains safe.
Reasoning steps for option A
When might waiting for a complete wall reduce procedural risk?
Waiting can reduce procedural injury in a stable patient with necrotizing pancreatitis.
Why do rising vasopressor needs make waiting for a complete wall unsafe?
Fever and increasing vasopressor needs despite antibiotics indicate uncontrolled infection.
Does incomplete encapsulation justify delaying intervention here?
No. Wall maturation is desirable only when waiting is safe, and this patient is deteriorating.
B. Place an image-guided percutaneous drain (Best answer)
A catheter can provide early source control through a feasible retroperitoneal route. The infected cavity is inaccessible transgastrically and the patient is deteriorating. Match urgent drainage to both physiology and anatomy.
Reasoning steps for option B
What can an image-guided catheter accomplish in this case?
It can provide early source control through the feasible left retroperitoneal route.
Why is percutaneous drainage preferable to transgastric access?
The infected necrosis is not apposed to the stomach, while interventional radiology has identified a catheter route.
Why is percutaneous drainage the best next intervention?
It addresses worsening sepsis now using the available route, without requiring a mature wall or open debridement.
C. Perform endoscopic transgastric necrosectomy (Why this does not fit)
Endoscopic debridement can treat organized necrosis accessible from the gastrointestinal tract. The collection is incompletely encapsulated and lacks gastric apposition. A route suitable for mature central WON is not suitable for every early cavity.
Reasoning steps for option C
When can transgastric necrosectomy treat pancreatic necrosis?
It can treat organized necrosis that is accessible from the gastrointestinal tract.
Which wall and apposition findings make transgastric necrosectomy unsuitable?
The necrosis is incompletely encapsulated and is not apposed to the stomach.
Why should transgastric necrosectomy not be chosen for this patient?
The early, left retroperitoneal cavity lacks the wall and gastric access needed for that route.
D. Perform an immediate open pancreatic debridement (Why this does not fit)
Open debridement can be necessary when less invasive treatment fails or anatomy demands it. A feasible catheter route provides a less invasive source-control step before open tissue clearance. Deterioration calls for effective source control, not automatic maximal surgery.
Reasoning steps for option D
When might open pancreatic debridement become necessary?
It may be needed if less invasive source control fails or the anatomy requires surgery.
What access finding permits source control before open debridement?
Interventional radiology has identified a feasible catheter route into the infected necrosis.
Why does deterioration not mandate immediate open debridement?
The rising vasopressor requirement calls for prompt source control, which the feasible percutaneous drain can provide first.
E. Obtain CT-guided aspiration and await cultures (Why this does not fit)
Aspiration may clarify uncertain infection when the result would alter care. Gas, persistent sepsis and deterioration already support intervention. Sampling should not postpone needed source control.
Reasoning steps for option E
When could CT-guided aspiration clarify suspected infection in pancreatic necrosis?
It may help when infection is uncertain and a culture result would change treatment.
Why is diagnostic aspiration insufficient here?
Gas in the necrosis, persistent fever and increasing vasopressor needs already support infected necrosis requiring intervention.
Why should cultures not be awaited before drainage?
Waiting for aspirate results would delay source control in a patient whose sepsis is worsening despite antibiotics.
Takeaway: Uncontrolled sepsis can require drainage before full wall maturation.
A. Urgent transgastric drainage of the cavity (Why this does not fit)
Internal drainage can relieve symptoms caused by an inflammatory collection. The immediate problem is an actively bleeding artery. Drainage must not precede control of a demonstrated arterial source.
Reasoning steps for option A
What could transgastric drainage address after the splenic arterial bleeding is controlled?
It could relieve symptoms caused by the pancreatic collection.
Which CT angiography finding takes priority over transgastric cavity drainage?
CT angiography shows a splenic artery lesion actively bleeding into the cavity.
Why must the splenic arterial hemorrhage be controlled before transgastric drainage?
The patient has hematemesis, hypotension and a marked hemoglobin fall from arterial bleeding that must be controlled before the cavity is drained.
B. Endoscopic injection into the gastric wall (Why this does not fit)
Endoscopic hemostasis treats accessible gastrointestinal mucosal bleeding. The demonstrated source is a splenic arterial lesion bleeding into the pancreatic cavity. Localize the vessel before choosing a hemostatic route.
Reasoning steps for option B
What type of gastrointestinal bleeding is amenable to injection into the gastric wall?
It can treat an accessible bleeding site in the gastrointestinal wall.
Why does the imaging argue against gastric wall injection?
CT angiography identifies a splenic artery outpouching with contrast entering the pancreatic cavity.
Why is endoscopic injection not the targeted treatment?
The demonstrated bleeding source is a splenic arterial lesion, not a gastric wall site.
C. Open pancreatic necrosectomy as the first procedure (Why this does not fit)
Surgery may be required for bleeding that cannot be controlled endovascularly. Immediate embolization is feasible and no other surgical emergency is supplied. Use the available targeted vascular treatment before a more extensive operation.
Reasoning steps for option C
When might surgery be needed for this hemorrhage?
It may be needed if endovascular control of the splenic arterial bleeding fails or is unavailable.
What makes open necrosectomy a poor first procedure?
Interventional radiology can immediately treat the identified bleeding vessel.
Why should embolization precede an open operation here?
The active splenic artery lesion has a feasible targeted treatment, and no other surgical emergency is described.
D. Percutaneous catheter drainage of bloody fluid (Why this does not fit)
A catheter can decompress an infected or obstructing cavity. Evacuating blood does not close the arterial defect and may worsen hemorrhage. Treat the bleeding source rather than its fluid collection.
Reasoning steps for option D
What can a percutaneous catheter accomplish for a pancreatic cavity?
It can decompress a cavity that is infected or causing obstruction.
Why would draining bloody fluid not control this emergency?
Removing fluid would not close the splenic arterial defect and could worsen hemorrhage.
What finding makes arterial treatment the priority over drainage?
CT angiography shows arterial contrast entering the cavity in a patient with hypotension and a large hemoglobin drop.
E. Urgent angiography with embolization (Best answer)
Transcatheter embolization can directly control a bleeding pseudoaneurysm. Active arterial extravasation and substantial blood loss identify the vascular target. Resuscitate and secure the artery before treating the cavity.
Reasoning steps for option E
How can angiography with embolization address this lesion?
It can identify and directly occlude the bleeding splenic arterial lesion.
What findings support urgent embolization?
CT angiography shows arterial contrast entering the cavity, alongside hematemesis, hypotension and a hemoglobin fall from 11.8 to 7.9 g/dL.
Why is angiographic embolization the next treatment for the splenic artery lesion?
Resuscitation is underway, and an immediately available interventional radiology team can control the demonstrated arterial source before the cavity is treated.
Takeaway: A bleeding pseudoaneurysm requires vascular control before collection drainage.
A. Delay invasive treatment until the fourth week (Why this does not fit)
Delayed intervention generally lowers harm when treating stable pancreatic necrosis. The patient has uncontrolled hemorrhage rather than a stable indication for elective debridement. The timing preference for necrosis does not override a separate emergency.
Reasoning steps for option A
Why might treatment of pancreatic necrosis ordinarily wait until about week four?
In a stable patient, waiting allows the necrotic collection to develop a mature wall and generally reduces the harm of intervention.
Why is waiting inappropriate for this patient on day 12?
The patient has ongoing arterial hemorrhage and rising transfusion requirements, not a stable indication for elective necrosis treatment.
Does the immature collection wall justify delaying bleeding control?
No. The preference to delay necrosis intervention does not override uncontrolled hemorrhage after failed embolization.
B. Drain the collection to reduce its pressure (Why this does not fit)
Decompression can treat some symptomatic collections. Pressure reduction cannot reliably secure an arterial source after failed embolization. A drainage catheter is not an alternative to hemostasis.
Reasoning steps for option B
What problem could drainage of the pancreatic collection potentially address?
Drainage could decompress a symptomatic collection, but it would not directly control this patient's arterial hemorrhage.
Why is collection drainage insufficient after the failed catheter procedure?
Lowering collection pressure cannot reliably secure the arterial bleeding source that repeat angiography could not control.
Can a drainage catheter substitute for hemostasis in this case?
No. The patient's continuing bleeding and increasing transfusion needs require direct bleeding control.
C. Proceed with urgent operative bleeding control (Best answer)
Surgery remains necessary when endovascular control of ongoing bleeding fails. Increasing transfusion needs and failed catheter treatment establish the need for escalation. Treat the emergency without assuming that all pancreatic necrosis must also be debrided.
Reasoning steps for option C
Why is urgent operative bleeding control the best next step?
The patient's transfusion requirements are increasing, endovascular treatment has failed, and the surgical team is available.
Does urgent surgery require debridement of the immature necrotic collection?
No. The operation should control the hemorrhage without assuming that the day-12 necrosis must also be debrided.
D. Repeat vascular imaging after transfusion stabilizes hemoglobin (Why this does not fit)
Repeat imaging can guide management when bleeding is uncertain or controlled. Active bleeding and failed hemostasis are already established. Resuscitation supports definitive control but does not replace it.
Reasoning steps for option D
When could repeat vascular imaging be appropriate instead of immediate operative bleeding control?
It could help if the bleeding source were uncertain or hemorrhage were controlled, neither of which describes this patient.
Why should the team not wait for transfusion to stabilize hemoglobin before acting?
Ongoing arterial bleeding and failure of repeat angiography to achieve hemostasis are already established.
What role does transfusion have while this patient continues to bleed?
Transfusion supports resuscitation, but the rising requirement makes definitive bleeding control more urgent, not less.
Takeaway: Failed endovascular hemostasis can require surgery before collection maturation.
A. Image-guided drainage of the dependent extension (Best answer)
Percutaneous access can treat deep compartments not effectively reached by gastric drainage. The central cavity has decompressed while the infected pelvic extension remains. Reassess compartment anatomy before escalating tissue extraction.
Reasoning steps for option A
Why is image-guided drainage suited to the remaining infected collection?
It can access the right paracolic gutter extension reaching the pelvis, a deep compartment not effectively emptied through the gastric stent.
What imaging findings identify the source that still needs drainage?
The central cavity has substantially decreased, while a separate 9 cm infected extension remains in the right paracolic gutter.
Why should the compartment anatomy guide the next procedure?
Persistent fever coincides with an undrained pelvic extension, whereas the gastric stent is patent and the central cavity contains little debris.
B. Direct endoscopic necrosectomy of the central cavity (Why this does not fit)
Necrosectomy can help when retained infected solids maintain illness. The central cavity contains little debris and is draining; the major residual source is distant. Do not treat the already controlled compartment while another remains undrained.
Reasoning steps for option B
When would direct endoscopic necrosectomy address persistent infection?
It could help if retained infected solid material remained in the central cavity, but this cavity contains little residual debris.
Why is central-cavity necrosectomy a poor match for the CT findings?
The central cavity has decompressed through a patent stent; the substantial residual infected collection lies in the paracolic gutter.
What source would central-cavity necrosectomy leave untreated?
It would leave the separate 9 cm infected extension reaching the pelvis, the likely cause of fever despite central drainage.
C. Exchange the gastric stent for a larger device (Why this does not fit)
A larger outlet can help inadequate central drainage. The current stent is patent and the central cavity has already decreased. Device diameter does not overcome unfavorable compartment communication.
Reasoning steps for option C
When might a larger gastric stent improve drainage?
It might help if outflow from the central cavity were inadequate, but this patient's stent is patent and that cavity has shrunk.
Why is stent exchange unlikely to resolve the persistent fever?
The central cavity is already draining, while CT shows a separate infected extension in the right paracolic gutter.
Why would increasing gastric stent diameter not drain the pelvic extension?
A larger stent would not correct the unfavorable communication between the decompressed central cavity and the separate dependent collection.
D. Place a transpapillary pancreatic duct stent (Why this does not fit)
Duct stenting can help selected leaks or strictures. The supplied unresolved problem is a deep infected collection, not an identified bridgeable duct lesion. Treat the demonstrated source while evaluating duct issues separately.
Reasoning steps for option D
What finding would make a transpapillary pancreatic duct stent more relevant?
An identified duct leak or stricture suitable for stenting would support it, but no such lesion is described in this case.
Why does duct stenting not address the demonstrated residual source?
CT identifies a 9 cm infected paracolic extension reaching the pelvis, rather than a bridgeable pancreatic duct lesion.
How should possible duct issues affect the next step?
They can be evaluated separately, while the persistent fever and undrained infected pelvic extension call for drainage of that collection.
Takeaway: Persistent sepsis after central drainage may come from an undrained dependent compartment.
A. Residual infected solid tissue obstructing the drain (Why this does not fit)
Retained infected debris can sustain a collection after drainage. The new cavity is fluid-only and the key persistent abnormality is duct interruption with a viable tail. Recurrent liquid after clearance of solids should prompt a duct assessment.
Reasoning steps for option A
How could retained infected tissue cause a collection to recur after drainage?
Infected debris left behind after treatment of pancreatic necrosis could continue to sustain a collection.
What findings argue against retained infected tissue as the main cause here?
The recurrent collection is fluid-only, while the persistent findings are a high-amylase drain output and an interrupted pancreatic duct.
What should the fluid-only recurrence after necrosis treatment prompt instead?
The fluid-only recurrence after clearance of necrotic solids, together with a viable tail and abrupt duct interruption, points to continuing pancreatic juice leakage.
B. Reduced secretion from an atrophic distal gland (Why this does not fit)
A severely atrophic gland may have diminished exocrine output. The distal gland remains viable and the external output is persistently high in amylase. Ongoing secretion requires living pancreatic tissue.
Reasoning steps for option B
How would an atrophic distal gland affect pancreatic secretion?
A severely atrophic tail would be expected to produce less pancreatic juice.
Why does distal gland atrophy not fit this case?
The tail still enhances, and the external drain continues to produce high-amylase fluid.
What does the persistent amylase-rich output indicate about the tail?
The enhancing distal tail remains capable of secreting juice despite its loss of duct communication with the head.
C. Portal venous obstruction raising hydrostatic pressure (Why this does not fit)
Portal obstruction can cause ascites through venous hypertension. The localized recurrent cavity and isolated tail duct provide a direct source of pancreatic juice. Distinguish pancreatic leakage from generalized portal-pressure fluid accumulation.
Reasoning steps for option C
How might portal venous obstruction produce fluid accumulation?
Portal venous hypertension can cause ascites.
Which findings favor pancreatic leakage over portal venous obstruction?
The patient has a localized recurrent collection, high-amylase drain output and an isolated tail duct.
Why is portal-pressure fluid accumulation an unlikely explanation for this recurrence?
The interrupted pancreatic duct and viable tail provide a direct source for the localized amylase-rich fluid.
D. Continued secretion from a disconnected viable tail (Best answer)
Viable distal pancreatic tissue can keep secreting despite loss of duct continuity. The tail duct cannot empty through the duct in the head, so juice returns to the cavity or drain. Draining the destination does not restore the duct connection.
Reasoning steps for option D
How can a disconnected viable tail cause a collection to recur?
The viable distal pancreas can continue secreting juice after its duct loses continuity with the duct in the head.
Where can the tail's secretions go in this patient?
Because the dilated tail duct does not communicate with the head duct, pancreatic juice can flow into the recurrent cavity or external drain.
Why did successful cavity drainage not prevent recurrence?
Drainage emptied the collection but did not reconnect the secreting tail duct across the prior necrotic segment.
E. Persistent distal bile duct obstruction (Why this does not fit)
Biliary obstruction can cause jaundice and upstream biliary dilation. The demonstrated interrupted structure is the pancreatic duct, with amylase-rich external fluid. Use the affected duct and fluid composition to localize the problem.
Reasoning steps for option E
What findings would distal bile duct obstruction typically produce?
It could cause jaundice and dilation of the upstream biliary ducts.
Which findings instead identify a pancreatic duct problem?
MRCP shows pancreatic duct interruption, and the external drain fluid remains high in amylase.
Why does bile duct obstruction not explain this recurrent collection?
The demonstrated duct defect is pancreatic, and the fluid composition identifies pancreatic juice as the source.
Takeaway: A viable disconnected pancreatic remnant can sustain recurrent collections or an external fistula.
A. Distal pancreatectomy for complete duct disconnection (Why this does not fit)
Resection may be considered for symptomatic disconnected distal disease. Contrast and a guidewire cross the partial disruption, so complete disconnection is not established. Duct continuity distinguishes a bridgeable leak from an isolated remnant.
Reasoning steps for option A
When might distal pancreatectomy address a persistent pancreatic leak?
Resection may be considered for symptomatic disease arising from a completely disconnected distal pancreas.
Why is complete duct disconnection not established here?
Contrast reaches the upstream duct, and a guidewire passes across the short partial disruption into the tail duct.
Which finding makes resection for a disconnected remnant less fitting than a duct-bridging approach?
The guidewire crosses the defect, demonstrating continuity that can be used to bridge this patient's leak.
B. Transpapillary stenting across the disruption (Best answer)
A stent can direct drainage across a bridgeable partial duct leak. The upstream duct is accessible across a short defect and the cavity has already decompressed. Correct the demonstrated leak rather than repeatedly draining its destination.
Reasoning steps for option B
How can transpapillary stenting treat a partial pancreatic duct leak?
A stent placed across the disruption can direct pancreatic drainage through the duct.
Why is this patient's disruption suitable for transpapillary stenting?
The defect is short, contrast reaches the upstream duct, and a guidewire passes into the tail duct.
Why does stenting address the source more directly than further cavity drainage?
The collection has already decompressed, while a stent can bridge the demonstrated duct leak that continues to supply it.
C. Another percutaneous drain into the resolved cavity (Why this does not fit)
External drainage can evacuate an existing collection. There is no residual large cavity to target and the leak source remains in the duct. An additional outlet does not bridge a duct defect.
Reasoning steps for option C
What can a second percutaneous drain accomplish if a pancreatic collection remains?
It can evacuate fluid from an existing pancreatic collection.
Why is another drain poorly matched to this patient's findings?
There is no residual large cavity to drain, and the persistent leak arises from a partial duct disruption.
Why would an additional external outlet leave the source untreated?
It would not bridge the short duct defect that contrast and the guidewire can cross.
D. Direct endoscopic necrosectomy through the prior tract (Why this does not fit)
Necrosectomy addresses retained necrotic tissue. No residual necrotic segment or solid cavity target is described. Differentiate a duct problem from a tissue-clearance problem.
Reasoning steps for option D
What tissue target would justify necrosectomy through a prior drainage tract?
It removes retained necrotic tissue from a collection.
Why is necrosectomy not indicated by the described imaging?
No intervening necrotic segment or residual solid cavity target is described.
What makes a duct intervention more appropriate than tissue removal here?
The persistent leak comes from a short, guidewire-accessible duct disruption, not retained necrotic tissue.
Takeaway: A bridgeable partial duct disruption differs from complete disconnection.
A. Endoscopic drainage followed by interval cytology (Why this does not fit)
Drainage can treat a confirmed symptomatic inflammatory collection. An enhancing mural nodule raises a competing neoplastic explanation that must be assessed before drainage. Symptoms do not establish that a pancreatic cyst is inflammatory.
Reasoning steps for option A
When could endoscopic drainage be appropriate for this patient's 4 cm cystic lesion?
It could treat a confirmed symptomatic inflammatory collection, but this lesion has not been confirmed as one.
Why should drainage not precede evaluation of the enhancing mural nodule?
The nodule raises concern for a cystic neoplasm that needs assessment before drainage.
Does the patient's discomfort establish that the lesion is a pseudocyst?
No. Discomfort can occur with a neoplastic cyst, and the enhancing nodule argues against assuming an inflammatory cavity.
B. Antibiotics followed by drainage if discomfort persists (Why this does not fit)
Antibiotics are useful for a suspected infected collection. No infection is supplied and a mural nodule is not explained by presumed infection. Match treatment to evidence rather than to a cyst label.
Reasoning steps for option B
When would antibiotics be relevant to this patient's cystic lesion?
They would be relevant if the collection were suspected to be infected, which is not the case here.
Does presumed infection explain the enhancing mural nodule or justify antibiotics before drainage?
No. There is no evidence of infection, and presumed infection does not account for the nodule.
Why is antibiotic treatment based on the cyst label inappropriate here?
The patient has no signs of infection, while the enhancing nodule requires evaluation for neoplasia.
C. Percutaneous aspiration as definitive treatment (Why this does not fit)
Aspiration may temporarily reduce a simple fluid cavity. A potentially neoplastic cyst requires characterization and a management plan, not empirical decompression. A temporary decrease in volume does not settle the diagnosis.
Reasoning steps for option C
What could percutaneous aspiration accomplish for this lesion?
It might temporarily reduce the volume of a simple fluid cavity, but it would not establish what this lesion is.
Why is aspiration insufficient as definitive treatment?
The enhancing mural nodule makes a neoplastic cyst possible, requiring characterization and a management plan rather than empirical decompression.
Would a smaller lesion after aspiration resolve the diagnostic concern?
No. Volume reduction would not explain the mural nodule or establish that this 4 cm lesion is a pseudocyst.
D. Observation until exactly four weeks after the attack (Why this does not fit)
Organization over time helps classify inflammatory collections. A mural nodule remains concerning irrespective of a four-week date. A calendar interval does not exclude neoplasia.
Reasoning steps for option D
How can time since pancreatitis help assess a possible inflammatory collection?
It can help determine whether an inflammatory collection has organized, but the prior scan is unavailable here.
Would waiting until exactly four weeks address the mural nodule?
No. The enhancing nodule remains concerning regardless of that date.
Would reaching four weeks after the attack exclude a neoplasm in this patient?
No. A calendar interval cannot resolve the concern raised by this lesion's enhancing mural nodule.
E. Specialist cyst evaluation, including EUS assessment (Best answer)
Pancreatic cystic neoplasms can coexist with or cause pancreatitis. The enhancing nodule and uncertain prior history make routine pseudocyst drainage inappropriate without further evaluation. Reassess the diagnosis when the morphology does not fit an inflammatory cavity.
Reasoning steps for option E
Why is specialist cyst evaluation relevant after this patient's pancreatitis episode?
A pancreatic cystic neoplasm can coexist with or cause pancreatitis, so the episode does not establish a pseudocyst.
Why should EUS assessment come before routine pseudocyst drainage?
The enhancing mural nodule and unavailable prior scan leave the lesion's nature uncertain.
Which cyst morphology makes diagnostic reassessment preferable to routine pseudocyst drainage?
The enhancing mural nodule, without a surrounding inflammatory collection, makes a simple pseudocyst diagnosis unreliable.
Takeaway: Recent pancreatitis does not prove that every pancreatic cystic lesion is a pseudocyst.
A. Gas now establishes infected pancreatic necrosis (Why this does not fit)
Gas in an untreated necrotic collection can strongly support infection. This fluid-only cavity was recently connected to the stomach and the patient is improving. Interpret gas alongside instrumentation, cavity contents and clinical trajectory.
Reasoning steps for option A
When can gas support infected pancreatic necrosis?
Gas in an untreated necrotic collection can support infection, but this patient's collection was fluid-only and recently drained.
Why does the new gas not establish infected necrosis here?
A patent stent connects the shrinking cavity to the stomach, and the patient is afebrile with a falling leukocyte count.
Which case findings matter when interpreting this gas?
The fluid-only contents, recent gastric drainage and clinical improvement favor introduced luminal gas over infected necrosis.
B. Gas proves a colonic fistula requiring surgery (Why this does not fit)
An enteric fistula can introduce gas into a collection. A known gastric drainage route already explains gas, and no colonic communication or peritonitis is supplied. Do not infer a second fistula from gas alone after planned internal drainage.
Reasoning steps for option B
Could a fistula introduce gas into a pancreatic collection?
Yes, but this patient already has a known stent connection between the cavity and stomach.
Why does the CT not prove a colonic fistula requiring surgery?
No colonic communication, extraluminal contrast leak or peritonitis is reported; the gastric stent explains the gas.
Why is a second fistula an unsupported inference in this patient?
Gas appeared after planned internal drainage through a patent gastric stent, while the cavity is smaller and the patient is improving.
C. Gas can reflect the drainage communication (Best answer)
An internal stent permits luminal gas to enter the treated cavity. A smaller cavity, patent gastric connection and clinical improvement support this explanation. A new image finding may reflect treatment rather than a new infection.
Reasoning steps for option C
How can the new gas enter this treated cavity?
The internal stent permits gas from the stomach to enter the drained cavity.
Which findings favor gas from the drainage communication?
CT shows a smaller cavity and patent gastric connection, while fever is absent and the leukocyte count is falling.
What does the new gas most likely reflect in this case?
It likely reflects the recent EUS-guided drainage connection rather than a new infection in an improving patient.
D. Gas indicates that the cavity has become WON (Why this does not fit)
WON is defined by encapsulated necrotic material rather than gas. The cavity remains fluid-only and has a known new luminal connection. Collection contents and organization determine its name.
Reasoning steps for option D
Does gas define walled-off necrosis, or WON?
No. WON requires an organized collection containing necrotic material, not merely gas.
Why has this cavity not become WON based on the CT finding?
It remains fluid-only, and its new gas has a plausible route through the gastric stent.
Which contents and wall features, rather than new gas, distinguish a pseudocyst from WON?
A pseudocyst contains essentially fluid within an organized wall; WON contains encapsulated necrotic material. This fluid-only cavity has no demonstrated necrotic solids, and gastric communication explains the gas.
Takeaway: After internal drainage, gas alone does not establish infection.
A. Severe pancreatitis because organ failure persisted beyond 48 hours (Best answer)
Persistent organ failure defines severe acute pancreatitis. Respiratory failure lasts 72 hours even though the cavity is small and sterile. Physiological duration determines severe disease, not collection diameter.
Reasoning steps for option A
What revised Atlanta severity category applies when organ failure persists beyond 48 hours?
Severe acute pancreatitis applies because this patient's respiratory organ failure has lasted 72 hours.
Do the small collection and absence of infection change that classification?
No. Persistent respiratory failure establishes severe disease despite the small, sterile necrotic collection.
Which organ-failure duration makes this attack severe despite the small collection?
The 72-hour duration of respiratory organ failure determines severe pancreatitis, not the collection's size.
B. Moderately severe pancreatitis because the shock resolved (Why this does not fit)
Transient organ failure can fit moderately severe pancreatitis. Another organ system continues to fail beyond 48 hours. Assess every affected organ system rather than the first one to recover.
Reasoning steps for option B
When could resolved cardiovascular failure support a moderately severe classification?
Its resolution within 30 hours would fit transient organ failure if no other organ failure persisted.
Why is moderately severe pancreatitis incorrect here?
Respiratory organ failure has continued for 72 hours, beyond the 48-hour threshold.
Why is the recovery from shock not enough to classify this attack?
The cardiovascular failure resolved, but the ongoing respiratory failure makes this attack severe.
C. Mild pancreatitis because the collection is not infected (Why this does not fit)
Mild pancreatitis excludes organ failure and local complications. Both organ failure and a necrotic collection are present despite absence of infection. Sterility does not define a mild attack.
Reasoning steps for option C
Does the absence of infection make this attack mild?
No. Mild pancreatitis has no organ failure or local complications, and this patient has both.
Which findings rule out mild pancreatitis?
The patient has a necrotic collection and respiratory organ failure lasting 72 hours.
What does the sterile collection tell us about severity?
Its lack of identified infection does not negate the persistent respiratory failure that makes this attack severe.
D. Moderately severe pancreatitis until the collection encapsulates (Why this does not fit)
Local complications without persistent organ failure fit moderately severe disease. The patient already has persistent respiratory failure; wall formation is irrelevant to that severity criterion. Collection maturation and systemic severity are separate assessments.
Reasoning steps for option D
When would a local complication support moderately severe pancreatitis?
It could do so without persistent organ failure, but this patient has 72 hours of respiratory failure.
Must the acute necrotic collection encapsulate before this attack is classified as severe?
No. Persistent respiratory failure already establishes severe pancreatitis, regardless of wall formation.
How are collection maturation and severity distinguished here?
The day 9 collection is acute and not yet encapsulated, while the 72-hour respiratory failure independently establishes severe disease.
Takeaway: Persistent failure of any qualifying organ system beyond 48 hours defines severe pancreatitis.
A. Begin a carbapenem until the necrosis has resolved (Why this does not fit)
Broad-spectrum antibiotics can treat infected necrosis. The improving early inflammatory course provides no current evidence of infection. Necrosis alone is not a prophylactic antibiotic indication.
Reasoning steps for option A
When would a carbapenem be justified for pancreatic necrosis?
Broad-spectrum antibiotics can treat infected necrosis.
Do the falling fever and leukocytosis justify carbapenem prophylaxis on day 5?
The improving early inflammatory course provides no current evidence of infection.
Why not continue carbapenem until all necrosis resolves?
Sterile necrosis alone does not warrant carbapenem prophylaxis until radiographic resolution.
B. Begin fluconazole while monitoring bacterial cultures (Why this does not fit)
Antifungal treatment has a role in selected documented or strongly suspected fungal infection. No fungal infection is supplied, and routine empirical antifungal therapy is unsupported. Use a demonstrated infectious problem to select antimicrobial coverage.
Reasoning steps for option B
When would fluconazole be relevant to this pancreatic illness?
Antifungal treatment has a role in selected documented or strongly suspected fungal infection.
What fungal evidence supports fluconazole in this improving patient?
No fungal infection is supplied, and routine empirical antifungal therapy is unsupported.
What should determine antifungal rather than antibacterial coverage here?
No fungal infection is shown; fluconazole should follow documented or strongly suspected fungal disease.
C. Obtain a needle aspirate before making any plan (Why this does not fit)
Aspiration can clarify selected unresolved diagnostic questions. The patient is improving without a strong infection signal or a management-changing uncertainty. Do not make routine invasive sampling part of stable sterile-necrosis care.
Reasoning steps for option C
What could needle aspiration establish in an uncertain necrotic collection?
Aspiration could help establish infection if that uncertainty would change management; this improving patient has no strong infection signal.
What unresolved infection question would aspiration change in this stable patient?
The patient is improving without a strong infection signal or a management-changing uncertainty.
Why avoid routine needle sampling of improving early necrosis?
Stable improving necrosis without a management-changing infection concern does not warrant routine aspiration.
D. Withhold prophylaxis and reassess for new infection (Best answer)
Sterile necrosis does not benefit from routine prophylactic antibiotics. Falling temperature and leukocytes with stable organs and improving intake favor continued supportive care. An early inflammatory fever requires context rather than automatic antibiotic treatment.
Reasoning steps for option D
Why is withholding prophylactic antibiotics reasonable in sterile necrosis?
Sterile necrosis does not benefit from routine prophylactic antibiotics.
Which day-5 trends support reassessment rather than prophylactic antibiotics?
Falling temperature and leukocytes with stable organs and improving intake favor continued supportive care.
How should the temperature of 38.0 C be interpreted alongside stable organ function?
The day-5 temperature of 38.0 C may reflect inflammation; falling counts, stable organs and improving intake favor reassessment.
Takeaway: Early improving inflammation without evidence of infection does not require antibiotic prophylaxis.
A. Provide parenteral nutrition as the first route (Why this does not fit)
Parenteral nutrition can support patients unable to use the gastrointestinal tract. A functioning bowel can be reached beyond the obstruction. Use feasible enteral access before choosing an intravenous nutrition route.
Reasoning steps for option A
When is intravenous parenteral nutrition useful during pancreatic illness?
Parenteral nutrition can support patients unable to use the gastrointestinal tract.
Can this patient receive feed beyond the compressed gastric outlet?
A functioning bowel can be reached beyond the obstruction.
Why is parenteral feeding not the first route here?
Postpyloric access to functioning bowel makes parenteral nutrition unnecessary as the first route.
B. Provide postpyloric enteral nutrition (Best answer)
Feeding beyond the obstruction can use the functioning small bowel. Gastric emptying is impaired but distal enteral delivery remains feasible. Select the feeding route according to the site of the limitation.
Reasoning steps for option B
How can postpyloric feeding bypass this patient’s outlet compression?
Feeding beyond the obstruction can use the functioning small bowel.
Does gastric vomiting preclude delivery to the functioning small bowel?
Gastric emptying is impaired but distal enteral delivery remains feasible.
How does gastric outlet compression determine the enteral feeding-tube position?
Place the feeding tube beyond the obstructed gastric outlet into functioning small bowel.
C. Use nasogastric feeding into the obstructed stomach (Why this does not fit)
Gastric feeding is appropriate when gastric delivery is tolerated. Persistent outlet obstruction and vomiting make gastric delivery unsuccessful here. An enteral route must reach a segment that can accept and transmit the feed.
Reasoning steps for option C
Under what circumstance could nasogastric feeding work?
Gastric feeding is appropriate when gastric delivery is tolerated.
What does persistent vomiting despite decompression imply for gastric feeding?
Persistent outlet obstruction and vomiting make gastric delivery unsuccessful here.
Where must feed be delivered when gastric feeding fails because of outlet obstruction?
Feeds must bypass the vomiting, obstructed stomach to reach distal functioning bowel.
D. Continue intravenous fluids without nutrition until drainage (Why this does not fit)
Intravenous fluids can support hydration during acute illness. Ongoing nutritional failure has a feasible enteral solution and should not await indefinite fasting. Support hydration and nutrition as distinct needs.
Reasoning steps for option D
What can intravenous fluids accomplish during the feeding interruption?
Intravenous fluids can support hydration during acute illness.
Why does persistent inability to eat not justify awaiting drainage without nutrition?
Ongoing nutritional failure has a feasible enteral solution and should not await indefinite fasting.
What need remains unmet by hydration alone?
Intravenous fluids hydrate but do not meet this patient’s nutritional needs; postpyloric feeding can.
Takeaway: A functioning distal gut can be fed beyond a gastric outlet obstruction.
A. Mortality fell by 29 percentage points (Why this does not fit)
An absolute percentage-point difference compares the same outcome between groups. The 29-point difference belongs to the composite, not mortality alone. Name the outcome before describing its treatment effect.
Reasoning steps for option A
What would a 29-percentage-point mortality reduction require?
Mortality with step-up treatment would have to be 29 percentage points lower than with open surgery. The reported mortality was instead 19% versus 16%; the 29-point reduction applies to the composite.
Which PANTER endpoint differs by 69% minus 40%?
The 29-point difference belongs to the composite, not mortality alone.
Why must mortality and composite outcome differences be labeled separately?
The 29-point reduction belongs to major complications or death, not mortality, which was 19% versus 16%.
B. The composite fell by 29 percent relative to surgery (Why this does not fit)
A relative reduction divides the absolute difference by the comparator risk. Twenty-nine divided by 69 is about 42%, not 29%. Keep absolute percentage points distinct from relative percentage change.
Reasoning steps for option B
How is relative reduction in the composite calculated using open surgery as comparator?
Divide the absolute composite reduction by the open-surgery risk: (69% - 40%)/69%, approximately 42%.
What does 29 divided by 69 yield approximately?
Twenty-nine divided by 69 is about 42%, not 29%.
Why is calling the PANTER composite improvement 29% relative misleading?
The composite improved by 29 percentage points, approximately 42% relative to 69% in the surgery group.
C. The composite fell by 29 percentage points (Best answer)
The absolute difference is 69 minus 40, or 29 percentage points. The mortality comparison did not demonstrate a separate significant survival benefit. A composite benefit does not establish a benefit in every component.
Reasoning steps for option C
What is the absolute composite-event difference between step-up and open surgery?
The absolute difference is 69 minus 40, or 29 percentage points.
Does the mortality comparison of 19% versus 16%, P=0.70, show survival improvement?
The mortality comparison did not demonstrate a separate significant survival benefit.
Does the reduced PANTER composite establish a mortality benefit as well?
The composite reduction does not establish a mortality benefit or benefit in each component.
D. The two strategies produced equivalent mortality (Why this does not fit)
Equivalence requires a prespecified margin and an appropriate study design. A nonsignificant mortality comparison does not prove equivalence. Failure to demonstrate superiority is not evidence of equivalence.
Reasoning steps for option D
What trial framework would establish mortality equivalence?
Equivalence requires a prespecified margin and an appropriate study design.
Does P=0.70 for 19% versus 16% establish equivalent mortality?
A nonsignificant mortality comparison does not prove equivalence.
How should the absence of demonstrated mortality superiority be described?
P=0.70 does not establish equivalence; no prespecified equivalence margin is supplied.
Takeaway: A reduction in a composite outcome is not proof of a mortality reduction.
A. Remove the drain and continue the same antibiotics (Why this does not fit)
Antibiotics alone may suffice in selected improving patients. Sepsis persists despite treatment and a substantial residual tissue target remains. Persistent source-related illness changes the threshold for intervention.
Reasoning steps for option A
When might antibiotics without tissue removal suffice for infected WON?
Antibiotics alone may suffice in selected improving patients.
What makes unchanged antibiotics inadequate despite a patent transgastric drain?
Sepsis persists despite treatment and a substantial residual tissue target remains.
How does persistent sepsis with retained solids alter management?
Persistent sepsis with retained solid necrosis after patent drainage warrants tissue-directed escalation.
B. Repeat a small-volume diagnostic aspiration (Why this does not fit)
Aspiration may establish uncertain infection. Infected WON is established and the unresolved issue is retained tissue rather than diagnosis. Sampling cannot substitute for a needed therapeutic intervention.
Reasoning steps for option B
What uncertainty could aspiration address in pancreatic necrosis?
Aspiration may establish uncertain infection.
Is infection still uncertain in this patient with established infected WON?
Infected WON is established and the unresolved issue is retained tissue rather than diagnosis.
Why cannot another diagnostic aspirate remove the likely remaining source?
A diagnostic aspirate cannot clear the established infected WON’s retained solids.
C. Place an external drain into the same decompressed liquid space (Why this does not fit)
Another catheter may help an undrained fluid compartment. No missed fluid compartment is identified and the existing outlet is patent. A new drain does not necessarily extract obstructing or infected solids.
Reasoning steps for option C
When could an additional external catheter help after transgastric drainage?
Another catheter may help an undrained fluid compartment.
Does imaging identify a separate undrained fluid extension?
No missed fluid compartment is identified and the existing outlet is patent.
Why may draining the same liquid space leave solid necrosis behind?
Another drain into the same decompressed space need not remove retained necrotic tissue.
D. Perform direct endoscopic necrosectomy (Best answer)
Endoscopic debridement can clear residual infected tissue after drainage is inadequate clinically. The mature accessible cavity contains retained solids and no alternative source explains persistent sepsis. Escalate for persistent illness after reassessing drainage and anatomy.
Reasoning steps for option D
What is the therapeutic purpose of direct endoscopic necrosectomy?
Endoscopic debridement can clear residual infected tissue after drainage is inadequate clinically.
Which findings identify retained tissue as the likely source despite adequate drainage?
The mature accessible cavity contains retained solids and no alternative source explains persistent sepsis.
Why is debridement now a reasonable step-up rather than automatic first-line treatment?
After checking patent drainage and other sources, debride accessible retained solids driving sepsis.
E. Perform pancreatic duct stenting before further cavity treatment (Why this does not fit)
Duct-directed treatment can help a demonstrated bridgeable leak. No duct defect is identified as the persistent infectious source. Choose an intervention for the lesion actually demonstrated.
Reasoning steps for option E
What duct finding would make transpapillary stenting relevant to persistent illness after WON drainage?
Duct-directed treatment can help a demonstrated bridgeable leak.
Is a bridgeable duct leak shown as the source of ongoing sepsis?
No duct defect is identified as the persistent infectious source.
Why address the accessible infected solids before an unsupported duct intervention?
Treat demonstrated retained infected solids, not an unshown duct defect.
Takeaway: Persistent sepsis from retained infected tissue can justify necrosectomy after adequate drainage.
A. Schedule open necrosectomy to normalize the scan (Why this does not fit)
Open debridement can clear residual necrosis when clinically necessary. The patient is recovering without a residual complication requiring surgery. Radiographic residue is not itself a surgical indication.
Reasoning steps for option A
When might open necrosectomy be necessary after WON drainage?
Open debridement can clear residual necrosis when clinically necessary.
Does this shrinking cavity cause a residual clinical complication?
The patient is recovering without a residual complication requiring surgery.
Why is remaining material on imaging insufficient reason for open surgery?
Residual material in a shrinking cavity without an ongoing complication is not by itself an indication for open necrosectomy.
B. Perform endoscopic necrosectomy before discharge (Why this does not fit)
Endoscopic tissue clearance can help patients not improving after drainage. The supplied trajectory demonstrates substantial clinical improvement. Judge a need for further debridement by response and complications.
Reasoning steps for option B
When does endoscopic necrosectomy add value after drainage?
Endoscopic tissue clearance can help patients not improving after drainage.
What do five afebrile days and weight gain say about response?
The supplied trajectory demonstrates substantial clinical improvement.
Why not debride solely to clear the remaining nonliquid material before discharge?
Improvement after drainage, rather than visible residue alone, determines whether debridement is needed.
C. Add an external drain to the residual cavity (Why this does not fit)
An additional drain can help ineffective or incomplete drainage. The stent is patent and the cavity is shrinking without an undrained extension. More access is not necessarily more effective treatment.
Reasoning steps for option C
What drainage failure would warrant an additional external catheter?
An additional drain can help ineffective or incomplete drainage.
Is the existing stent blocked or a new extension present?
The stent is patent and the cavity is shrinking without an undrained extension.
Why does a smaller cavity argue against reflexively adding access?
With a patent stent and shrinking cavity, another drain has no demonstrated target.
D. Restart empirical antifungal treatment (Why this does not fit)
Antifungals can treat a relevant fungal infection. No fungal infection or unexplained ongoing sepsis is present. Avoid expanding antimicrobial treatment for residual sterile-appearing tissue alone.
Reasoning steps for option D
What finding would support antifungal treatment after infected WON?
Antifungals can treat a relevant fungal infection.
Do cleared cultures and resolved sepsis suggest a fungal target?
No fungal infection or unexplained ongoing sepsis is present.
Why is imaging residue alone not a reason to restart empirical antifungal treatment?
Residual nonliquid material alone does not justify empirical antifungal treatment.
E. Continue planned follow-up without immediate debridement (Best answer)
Some patients recover after drainage without tissue extraction. Clinical recovery and absence of ongoing complications support reassessment rather than automatic escalation. A treatment goal is recovery, not immediate disappearance of all debris.
Reasoning steps for option E
Can successful drainage leave some necrotic material temporarily?
Some patients recover after drainage without tissue extraction.
Which clinical and imaging findings support follow-up rather than immediate debridement?
Five afebrile days, weight gain, cleared cultures, no ongoing organ support, and a shrinking cavity with a patent stent support follow-up despite residual debris.
What outcome should guide debridement decisions when residual WON debris remains?
Clinical recovery and absence of complications matter more than immediate disappearance of all debris.
Takeaway: Residual debris does not require debridement when clinical recovery is sustained.
A. Splenic outflow is redirected through short gastric veins (Best answer)
Splenic venous obstruction can produce localized collateral drainage through the stomach. Isolated splenic vein thrombosis with fundal varices and a patent portal vein fits this route. Gastric varices can arise from localized venous obstruction without cirrhosis.
Reasoning steps for option A
How does splenic vein thrombosis redirect venous return from the spleen?
Obstructed splenic venous outflow is diverted through short gastric collateral veins, producing fundal varices.
Why do isolated fundal varices with a patent portal vein fit short-gastric collaterals?
Splenic vein thrombosis redirects splenic outflow through short gastric veins. Fundal varices with a patent main portal vein and normal liver fit this localized mechanism.
Can localized gastric varices occur with normal liver architecture?
Yes: splenic vein thrombosis can produce fundal gastric varices despite normal liver architecture.
B. Generalized portal pressure rises from hepatic fibrosis (Why this does not fit)
Cirrhosis can produce portal hypertension and gastroesophageal varices. Normal liver architecture and isolated splenic venous obstruction support a more localized process. Localize the obstructed venous segment rather than assuming diffuse liver disease.
Reasoning steps for option B
What pattern might generalized cirrhotic portal hypertension produce?
Cirrhosis can produce portal hypertension and gastroesophageal varices.
Do normal liver architecture and absent esophageal varices favor generalized cirrhotic portal hypertension?
Normal liver architecture, absent esophageal varices and isolated splenic vein thrombosis favor a localized process.
Which venous lesion explains fundal varices better than hepatic fibrosis in this patient?
The demonstrated obstructed segment is the splenic vein, not diffuse hepatic portal circulation.
C. A splenic artery defect empties into the gastric lumen (Why this does not fit)
A pseudoaneurysm can cause severe gastrointestinal bleeding. The demonstrated lesions are venous fundal collaterals with splenic vein thrombosis. Arterial hemorrhage and variceal bleeding require different anatomical explanations.
Reasoning steps for option C
How might a splenic artery pseudoaneurysm cause GI bleeding?
A splenic artery pseudoaneurysm can bleed into a pancreatic cavity or gastrointestinal tract, but the lesions demonstrated here are venous fundal collaterals.
Are the observed fundal varices arterial or venous lesions?
The demonstrated lesions are venous fundal collaterals with splenic vein thrombosis.
Why is an arterial defect not the mechanism demonstrated by this CT?
The demonstrated mechanism is splenic venous obstruction with fundal collateral flow, not arterial hemorrhage.
D. Inferior vena cava obstruction raises hepatic venous pressure (Why this does not fit)
Hepatic outflow obstruction can create systemic and portal venous congestion. The supplied obstruction is in splenic venous drainage, without a hepatic outflow lesion. The distribution of collateral vessels helps identify the obstructed segment.
Reasoning steps for option D
How could hepatic outflow obstruction affect venous pressures?
Hepatic outflow obstruction can cause venous congestion, but it is not documented here.
Where is the documented thrombosis rather than a caval obstruction?
The obstruction is in the splenic vein, not the inferior vena cava or hepatic outflow.
What does the fundal collateral distribution localize?
Isolated fundal collaterals point to splenic venous outflow obstruction, not the inferior vena cava.
Takeaway: Splenic vein thrombosis can produce isolated gastric varices through short gastric collaterals.
A. Ongoing hemolysis with excess unconjugated bilirubin (Why this does not fit)
Hemolysis can cause jaundice by increasing bilirubin production. The imaging demonstrates a mechanically narrowed bile duct with upstream dilation. Anatomical obstruction is more explanatory than increased pigment production here.
Reasoning steps for option A
How could hemolysis produce jaundice without biliary blockage?
Hemolysis can cause jaundice by increasing bilirubin production.
What do distal duct narrowing and upstream dilation show instead?
The imaging demonstrates a mechanically narrowed bile duct with upstream dilation.
Why does the imaging favor obstruction over excess bilirubin production?
The narrowed distal duct with upstream dilation supports mechanical obstruction rather than hemolysis.
B. Extrinsic biliary obstruction from the collection (Best answer)
An adjacent collection can compress the bile duct and impair bile flow. The narrowing occurs at the point of contact, with dilation upstream and no stone or mass. Persistent biliary obstruction can be an intervention indication even without infection.
Reasoning steps for option B
How could a pancreatic-head collection obstruct bile flow?
An adjacent collection can compress the bile duct and impair bile flow.
Where is the narrowing relative to the mature cavity and proximal dilation?
The narrowing occurs at the point of contact, with dilation upstream and no stone or mass.
Can this biliary complication matter even without fever or hypotension?
Persistent compression-related biliary obstruction can warrant intervention even without fever or shock.
C. Primary hepatocellular injury from recurrent pancreatitis (Why this does not fit)
Hepatocellular injury can produce jaundice without an obstructed duct. A focal narrowing and proximal duct dilation directly support mechanical obstruction. Use the duct pattern to distinguish obstruction from parenchymal liver injury.
Reasoning steps for option C
How could hepatocellular injury cause jaundice?
Hepatocellular injury can impair bilirubin handling without obstructing the bile duct; it does not explain the focal narrowing with upstream dilation shown here.
Why does focal distal duct narrowing argue against a primary hepatic mechanism?
A focal narrowing and proximal duct dilation directly support mechanical obstruction.
Which duct pattern distinguishes collection-related obstruction from hepatocellular injury?
Focal duct narrowing and upstream dilation favor obstruction over hepatocellular injury.
D. Occult distal common duct stone (Why this does not fit)
A common duct stone is a plausible cause of jaundice in pancreatic disease. The supplied MRCP excludes a visible stone and shows an alternative mechanical cause. Prefer the demonstrated cause rather than importing a familiar one.
Reasoning steps for option D
Why might a common duct stone be considered after pancreatitis?
A common duct stone is a plausible cause of jaundice in pancreatic disease.
What does MRCP show about stones and the alternative cause?
MRCP shows no duct stone or pancreatic mass, while the collection narrows the distal common bile duct with upstream dilation.
Why not infer an occult stone over the observed compression?
MRCP shows collection-related duct narrowing but no stone; do not substitute an unshown stone.
E. Portal venous thrombosis with diffuse collateral compression (Why this does not fit)
Venous disease can sometimes alter biliary drainage. No venous lesion is supplied and the collection directly narrows the duct. Localize the actual point and cause of obstruction.
Reasoning steps for option E
Could portal venous collateral disease affect the bile duct?
Venous disease can sometimes alter biliary drainage.
What venous finding is actually supplied in this patient?
No portal venous lesion is supplied; the collection directly narrows the distal duct.
What anatomic finding localizes jaundice to the collection rather than portal venous collaterals?
The collection itself narrows the distal common bile duct; no venous lesion is identified.
Takeaway: A pancreatic collection can cause clinically important biliary obstruction without infection.
A. Defer all procedures until the pancreatic wall matures (Why this does not fit)
Delaying necrosis intervention can reduce harm in stable patients. Peritonitis with bowel ischemia and perforation is a separate urgent problem. The necrosis calendar does not override a bowel emergency.
Reasoning steps for option A
Why are interventions on immature pancreatic necrosis often delayed?
Delaying necrosis intervention can reduce harm in stable patients.
What makes day-16 bowel perforation an exception to waiting?
Peritonitis with bowel ischemia and perforation is a separate urgent problem.
Which emergency overrides the pancreatic wall-maturation timeline?
Ischemic colonic perforation with peritonitis requires urgent care despite immature pancreatic necrosis.
B. Perform transgastric drainage as the definitive intervention (Why this does not fit)
Internal drainage can control a suitable symptomatic collection. A nonviable perforated colon requires evaluation beyond drainage of the pancreatic cavity. Identify which structure is failing before choosing a procedure.
Reasoning steps for option B
What does transgastric drainage treat in an appropriate collection?
Transgastric drainage treats a suitable pancreatic collection, not a perforated ischemic colon.
Would draining necrosis repair a nonenhancing perforated colon?
Which failing structure requires source control beyond transgastric drainage?
The failing structure is the ischemic perforated colon; pancreatic cavity drainage cannot repair it.
C. Arrange urgent operative assessment and source control (Best answer)
Ischemic perforated bowel with peritonitis generally requires urgent surgical treatment. The wall defect, free air and shock demonstrate a surgical emergency. Treat bowel injury promptly without assuming routine early pancreatic necrosectomy is also required.
Reasoning steps for option C
What urgent intervention does ischemic perforated bowel usually require?
Ischemic perforated bowel with peritonitis generally requires urgent surgical treatment.
Which CT and examination findings establish this surgical emergency?
The wall defect, free air and shock demonstrate a surgical emergency.
Does urgent bowel source control mandate routine early pancreatic necrosectomy?
Urgent bowel source control does not automatically require early pancreatic necrosectomy.
D. Repeat CT after an additional antibiotic trial (Why this does not fit)
Repeat imaging can clarify uncertain deterioration. The existing study already demonstrates perforation and threatened nonviable bowel. Do not delay established source control to confirm an already demonstrated emergency.
Reasoning steps for option D
When could repeat CT clarify deterioration before deciding on bowel source control?
Repeat imaging can clarify uncertain deterioration.
What has the current CT already shown about bowel viability and free air?
CT shows colonic nonenhancement, a focal wall defect and free intraperitoneal air; the examination and clinical course add rigidity and worsening shock.
Why is another antibiotic trial unsafe as the sole next plan?
The CT already demonstrates perforation and nonviable bowel; another antibiotic trial delays source control.
Takeaway: Bowel ischemia or perforation with peritonitis is not subject to an elective four-week delay.
A. Hepatic venous pressure measurement (Why this does not fit)
Pressure measurements can help assess uncertain portal hypertension. Normal portal and hepatic findings plus amylase-rich fluid instead suggest a pancreatic source. The fluid composition and prior injury should guide the anatomical question.
Reasoning steps for option A
What question would hepatic venous pressure measurement answer?
Pressure measurements can help assess uncertain portal hypertension.
How do normal portal flow and markedly amylase-rich ascites shift suspicion?
Normal liver architecture and portal flow, plus amylase-rich ascites, favor pancreatic leakage over portal hypertension.
Which anatomical source should be investigated instead of portal hypertension?
Investigate pancreatic duct leakage, suggested by amylase-rich ascites, rather than portal hypertension.
B. Repeat CT limited to collection diameter (Why this does not fit)
CT can assess changes in a known cavity. No large encapsulated cavity is present; the unresolved issue is a possible duct leak. Choose a study that answers the missing question rather than repeats a measurement.
Reasoning steps for option B
What can repeat CT diameter measurements monitor?
CT could monitor a known cavity, but this case needs assessment of pancreatic duct continuity.
Is a large cavity the unresolved abnormality on this CT?
No large cavity is present; the missing information is pancreatic duct continuity.
Why does another size measurement not identify a pancreatic juice leak?
Measuring cavity diameter again would not answer whether a pancreatic duct disruption is supplying the ascites; the initial CT could not adequately define that duct.
C. Diagnostic arterial angiography (Why this does not fit)
Angiography can localize and treat arterial hemorrhage. There is no blood-loss syndrome and the recurrent fluid is amylase-rich. Differentiate a pancreatic secretion leak from vascular bleeding.
Reasoning steps for option C
What clinical problem is diagnostic arterial angiography suited to?
Angiography can localize and treat arterial hemorrhage.
Does recurrent amylase-rich ascites indicate an arterial hemorrhage?
There is no blood-loss syndrome and the recurrent fluid is amylase-rich.
What distinguishes the likely duct leak from bleeding here?
Amylase-rich recurrent ascites suggests pancreatic secretion leakage rather than arterial bleeding.
D. MRCP focused on duct continuity and leakage (Best answer)
MRCP can assess pancreatic duct anatomy and possible disruption. Pancreatitis followed by recurrent amylase-rich ascites raises concern for escape of pancreatic juice. Investigate the continuing source when fluid recurs without a large cavity.
Reasoning steps for option D
What pancreatic anatomy can duct-focused MRCP demonstrate?
MRCP can assess pancreatic duct anatomy and possible disruption.
Why does recurrent amylase-rich ascites suggest duct disruption?
Pancreatitis followed by recurrent amylase-rich ascites raises concern for escape of pancreatic juice.
What duct information should MRCP seek when amylase-rich ascites recurs without a large cavity?
MRCP should assess pancreatic duct continuity and possible leakage as the continuing source of the amylase-rich ascites.
Takeaway: Recurrent pancreatic fluid in the peritoneum warrants duct evaluation, not only cavity measurements.
A. An early necrotic collection became easier to characterize (Best answer)
Necrotic collections can resemble simple fluid during the first week. Early pancreatic nonenhancement and later solids support evolving visualization of ANC. Do not exclude necrosis solely because early fluid looks homogeneous.
Necrotic collections can resemble simple fluid during the first week.
How do nonenhancing pancreas and day-11 solids support ANC?
Early pancreatic nonenhancement and later solids support evolving visualization of ANC.
Why is early homogeneous appearance not proof of a simple fluid collection?
Early homogeneous appearance does not exclude necrosis when day-4 pancreatic nonenhancement and day-11 debris are present.
B. An APFC became a pseudocyst within the first week (Why this does not fit)
A pseudocyst is an organized inflammatory cavity containing essentially liquid. The later study shows solids and no mature wall. Both contents and organization must fit the proposed collection name.
Reasoning steps for option B
What wall and contents define a pseudocyst?
A pseudocyst is an organized inflammatory cavity containing essentially liquid.
Does day-11 debris without a wall fit a pseudocyst?
The later study shows solids and no mature wall.
Why cannot the early collection be called a newly mature pseudocyst?
Day-11 solids and absence of a mature wall rule out a pseudocyst designation.
C. A pseudocyst became infected and generated solid tissue (Why this does not fit)
Infection can complicate a collection but does not define its necrotic content. No initial mature wall is supplied, and necrosis was suggested by nonenhancing pancreatic tissue. Distinguish evolving recognition of necrosis from an unsupported infection explanation.
Reasoning steps for option C
Can infection alone explain formation of solid necrotic tissue?
Infection can complicate a collection but does not define its necrotic content.
What initial evidence already favors necrosis over a preexisting pseudocyst?
Day-4 pancreatic nonenhancement supports necrosis, and no mature pseudocyst wall is shown.
Why is infection an unsupported explanation of the imaging change?
Evolving recognition of necrotic debris is supported; infection is not supplied.
D. WON lost its capsule during spontaneous resolution (Why this does not fit)
WON is encapsulated necrotic tissue, usually later in the course. Neither study demonstrates a mature capsule, and the early course supports ANC. A collection cannot lose a documented feature that was never shown.
Reasoning steps for option D
What distinguishes walled-off necrosis from early ANC?
WON is encapsulated necrotic tissue, usually later in the course.
Was a capsule present on either day 4 or day 11?
Neither study demonstrates a mature capsule, and the early course supports ANC.
Why is spontaneous loss of a WON capsule implausible here?
No capsule is shown at either time, so the finding is early ANC rather than WON that lost its wall.
Takeaway: A homogeneous early appearance does not exclude an acute necrotic collection.
A. Use the shortest path with a smaller needle (Why this does not fit)
A shorter path may improve technical access. The proposed path crosses collateral veins regardless of needle size. Short distance cannot neutralize an intervening vascular hazard.
Reasoning steps for option A
What technical advantage might a short transgastric route offer?
A shorter path may improve technical access.
What does Doppler show crossing even a short needle path?
The proposed path crosses collateral veins regardless of needle size.
Why does reducing needle size not remove collateral-vein bleeding risk?
Short access and a small needle still cross collateral veins and risk bleeding.
B. Proceed because arterial Doppler is negative (Why this does not fit)
Excluding an artery or pseudoaneurysm is an important safety check. Venous collaterals can also cause significant bleeding when traversed. A negative arterial finding is not a complete vascular safety assessment.
Reasoning steps for option B
Why check for arterial lesions before pseudocyst puncture?
Puncturing an artery or pseudoaneurysm can cause bleeding. Here the arterial assessment is negative, but Doppler still shows venous collaterals across the proposed route.
Does absence of pseudoaneurysm exclude venous collateral bleeding?
No: the negative pseudoaneurysm assessment does not remove Doppler-visible venous collaterals.
What vascular hazard remains despite negative arterial Doppler?
Negative arterial assessment does not eliminate the venous collaterals across this path.
C. Reassess for a vessel-free or alternative route (Best answer)
Route planning can identify safer access or a different drainage method. The preferred trajectory crosses veins associated with splenic outflow obstruction. Preserve the treatment indication while changing an unsafe access plan.
Reasoning steps for option C
What should EUS route planning do when veins cross the proposed path?
Route planning can identify safer access or a different drainage method.
How does splenic vein thrombosis affect the proposed gastric trajectory?
The preferred trajectory crosses veins associated with splenic outflow obstruction.
Can the symptomatic pseudocyst still warrant drainage by a safer route?
The symptomatic pseudocyst can still warrant drainage, but through a vessel-free or alternative route.
D. Aspirate the cavity first to shrink the path (Why this does not fit)
Aspiration can transiently reduce cavity volume. Reaching the cavity would still require traversing the hazardous region. A preliminary puncture is not safe simply because it precedes definitive drainage.
Reasoning steps for option D
Could preliminary aspiration reduce pseudocyst volume?
Aspiration may temporarily reduce cavity volume but would still require puncture through collaterals.
Must the aspiration needle still traverse the collaterals?
Reaching the cavity would still require traversing the hazardous region.
Why does a preliminary puncture fail to solve the route hazard?
A preliminary aspiration requires the same hazardous puncture through venous collaterals.
E. Start anticoagulation and use the same path (Why this does not fit)
Anticoagulation may be considered for selected venous thromboses after balancing risks. It neither immediately eliminates the collaterals nor makes puncture through them safe. Thrombosis treatment and procedural vessel avoidance are separate decisions.
Reasoning steps for option E
When might anticoagulation for splenic vein thrombosis be considered?
Anticoagulation may be considered for selected venous thromboses after balancing risks.
Would anticoagulation immediately clear collaterals from this puncture route?
No: anticoagulation does not immediately eliminate collateral veins from the planned path.
Why must thrombosis management be separated from procedural access safety?
Anticoagulation decisions do not replace vessel avoidance during pseudocyst drainage.
Takeaway: A safe drainage path must avoid venous collaterals as well as arteries.
A. Metronidazole monotherapy (Why this does not fit)
Metronidazole provides anaerobic coverage. It does not adequately cover the demonstrated enteric aerobic gram-negative infection by itself. Pancreatic tissue penetration does not replace a sufficient antimicrobial spectrum.
Reasoning steps for option A
What organisms does metronidazole primarily cover?
Metronidazole provides anaerobic coverage.
Would metronidazole alone cover the enteric gram-negative bacteremia?
It does not adequately cover the demonstrated enteric aerobic gram-negative infection by itself.
Why is penetration insufficient without aerobic gram-negative activity?
Metronidazole penetration cannot compensate for absent aerobic gram-negative coverage in this bacteremia.
B. Vancomycin monotherapy (Why this does not fit)
Vancomycin treats susceptible gram-positive organisms. The identified bloodstream organisms are enteric gram-negative bacteria. Choose a spectrum matching the source and microbiological evidence.
Reasoning steps for option B
Which organisms does vancomycin principally treat?
Do these blood cultures identify organisms covered by vancomycin monotherapy?
The identified bloodstream organisms are enteric gram-negative bacteria.
Why would vancomycin alone miss the documented source?
Vancomycin alone misses the documented enteric gram-negative bloodstream organisms.
C. Fluconazole monotherapy (Why this does not fit)
Fluconazole can treat susceptible fungal infection. The evidence indicates bacterial infection, not an established fungal process. Routine antifungal treatment cannot substitute for antibacterial coverage.
Reasoning steps for option C
What infection would justify fluconazole?
Fluconazole can treat susceptible fungal infection.
What evidence instead identifies bacteria in this necrotic collection?
Enteric gram-negative bacteremia, new fever and gas in an undrained necrotic collection support bacterial infection; no fungal process is established.
Fluconazole cannot replace antibacterial treatment for documented gram-negative infected necrosis.
D. Cefazolin monotherapy (Why this does not fit)
Cefazolin is useful for selected susceptible infections and prophylactic settings. Its spectrum is not an adequate broad initial choice for the supplied infected necrosis scenario. A familiar surgical antibiotic is not automatically suitable for a complex enteric infection.
Reasoning steps for option D
For what kinds of infection is cefazolin useful?
Cefazolin is useful for selected susceptible infections and prophylactic settings.
Does it provide the required broad initial coverage for infected pancreatic necrosis?
Its spectrum is not an adequate broad initial choice for the supplied infected necrosis scenario.
Why is surgical familiarity not a substitute for source-appropriate spectrum?
Cefazolin is not broad enough as initial monotherapy for this enteric infected-necrosis scenario.
E. Meropenem monotherapy (Best answer)
Meropenem provides broad enteric antibacterial coverage and penetrates necrotic pancreatic tissue. The clinical evidence supports infected necrosis and the stated allergy, renal and local resistance conditions permit this choice. Start appropriate therapy, then tailor to cultures and the source-control response.
Reasoning steps for option E
What coverage and tissue access make meropenem plausible?
Which infection findings, renal function, allergy history and susceptibility data support meropenem?
New fever, enteric gram-negative bacteremia and gas in undrained necrosis support infection. Normal renal function, no beta-lactam allergy and local carbapenem susceptibility support meropenem as the broad initial choice.
How should antibiotics be adjusted after cultures and source-control response?
Start meropenem with source control, then tailor it to cultures and clinical response.
Takeaway: Select effective antibacterial coverage for suspected infected necrosis; penetration alone is insufficient.
A. Percutaneous external catheter drainage (Why this does not fit)
External drainage can be useful when internal access is unavailable or unsuitable. This mature symptomatic cavity has a demonstrated safe gastric route. Prefer a suitable internal route when it can address the collection without an external fistula.
Reasoning steps for option A
When might an external percutaneous drain be appropriate?
External drainage can be useful when internal access is unavailable or unsuitable.
What safe internal route does this mature pseudocyst already offer?
This mature symptomatic cavity has a demonstrated safe gastric route.
Why avoid an external catheter as the initial route here?
A safe internal gastric route can decompress this pseudocyst without initially creating an external fistula.
B. EUS-guided transgastric drainage (Best answer)
Internal drainage can relieve obstruction from a mature symptomatic pseudocyst. The fluid-only cavity has a complete wall, gastric apposition and a vessel-free path. Combine the treatment indication with wall, contents and access anatomy.
Reasoning steps for option B
Why can transgastric drainage relieve these outlet symptoms?
Internal drainage can relieve obstruction from a mature symptomatic pseudocyst.
Which wall, contents, apposition, and Doppler findings favor EUS access?
The fluid-only cavity has a complete wall, gastric apposition and a vessel-free path.
How do the seven-week course and persistent vomiting establish both anatomy and indication?
Persistent outlet symptoms warrant drainage; mature fluid-only anatomy and vessel-free gastric apposition favor EUS transgastric access.
C. Direct endoscopic necrosectomy (Why this does not fit)
Necrosectomy extracts retained necrotic tissue in selected WON. Repeated imaging shows a fluid-only cavity without a solid tissue target. Do not treat a pseudocyst as if it were debris-containing WON.
Reasoning steps for option C
What tissue does direct endoscopic necrosectomy remove?
Necrosectomy extracts retained necrotic tissue in selected WON.
Is any solid necrosis visible on CT or MRI in this patient?
Repeated imaging shows a fluid-only cavity without a solid tissue target.
Why does a fluid-only pseudocyst not call for necrosectomy?
A fluid-only pseudocyst has no solid necrotic tissue for necrosectomy to remove.
D. Open surgical cystogastrostomy (Why this does not fit)
Surgery can provide internal drainage when less invasive approaches are unsuitable or fail. A safe EUS-guided route is available for the initial intervention. An effective less invasive option can precede an open operation.
Reasoning steps for option D
When would open cystogastrostomy be considered?
Surgery can provide internal drainage when less invasive approaches are unsuitable or fail.
What less invasive route has been confirmed safe by EUS Doppler?
EUS Doppler confirms a vessel-free transgastric path to the mature cavity apposed to the posterior stomach.
Why reserve surgery rather than use it as the initial intervention?
The safe less invasive EUS route makes initial open cystogastrostomy unnecessary.
E. Transpapillary pancreatic duct stenting (Why this does not fit)
Duct stenting can help selected leaks and communicating collections. No bridgeable duct defect is identified and direct decompression of the obstructing cavity is needed. Do not substitute an unindicated duct procedure for a demonstrated cavity target.
Reasoning steps for option E
When could transpapillary duct stenting address a collection?
Duct stenting can help selected leaks and communicating collections.
Is a bridgeable duct defect demonstrated in this obstructing pseudocyst?
No bridgeable duct defect is identified; the demonstrated issue is outlet compression by the cavity.
Why is direct cavity decompression more fitting than duct stenting here?
No bridgeable duct defect is shown; direct drainage addresses the obstructing cavity.
Takeaway: A mature symptomatic fluid-only cavity with safe gastric apposition is suited to EUS-guided internal drainage.