Localize gallbladder calcium, interpret the tissue pattern and cancer evidence, and choose individualized care for symptoms, suspicious tissue, or operative risk.
A calcified gallbladder raises two different questions: where is the calcium, and what does this patient need now? Calcium in a scarred wall is not the same finding as stones in the lumen or an invasive soft-tissue mass. Confirm the compartment before discussing cancer risk or surgery. [1][2]
By the end, you should be able to separate wall calcification from its mimics, connect the calcification pattern to the tissue that remains, interpret the limits of cancer-risk estimates, and choose between clarification, elective surgical discussion, observation, and urgent assessment. The central decision is not simply whether calcium is present. It is whether symptoms, suspicious tissue, or the balance of operative benefit and harm justify intervention. [3][4]
Is the calcium in the wall or inside the lumen?
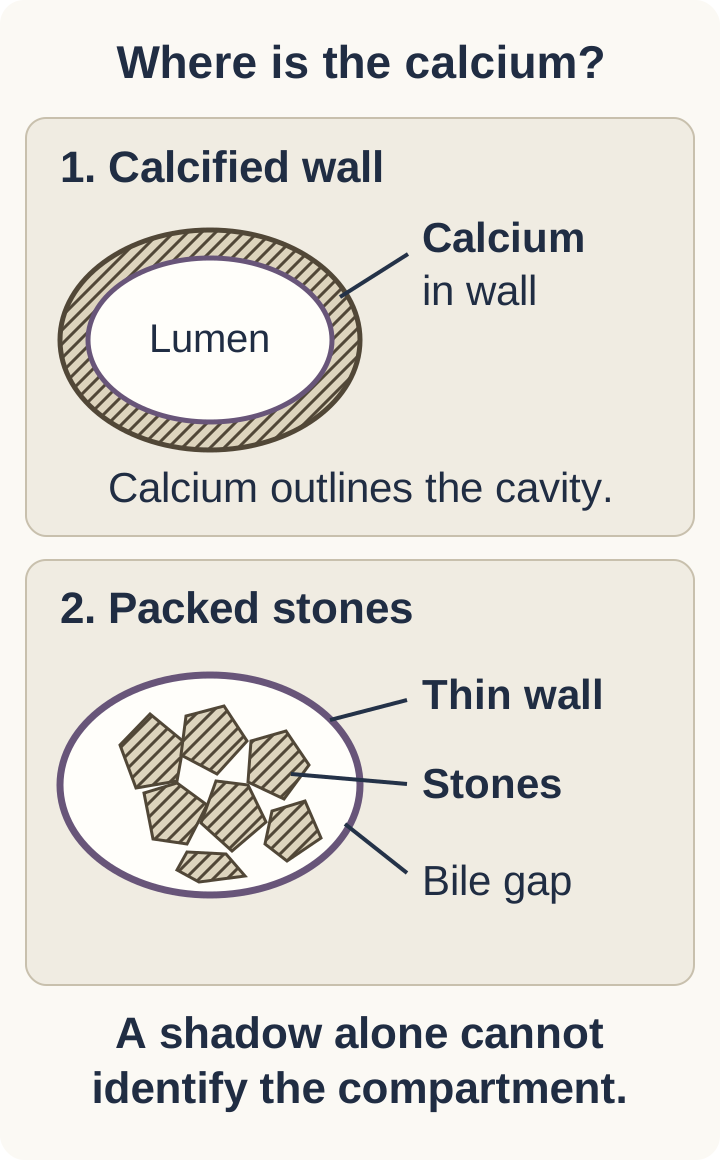
Picture the gallbladder as a fluid-containing sac. Its wall is the boundary; its lumen is the space inside. Porcelain gallbladder describes calcification of that wall. A continuous or patchy dense outline can represent mural calcium. Rounded or faceted objects occupying the cavity can instead be stones. Both may cast an ultrasound shadow, so a shadow alone does not establish the diagnosis. [1][3]
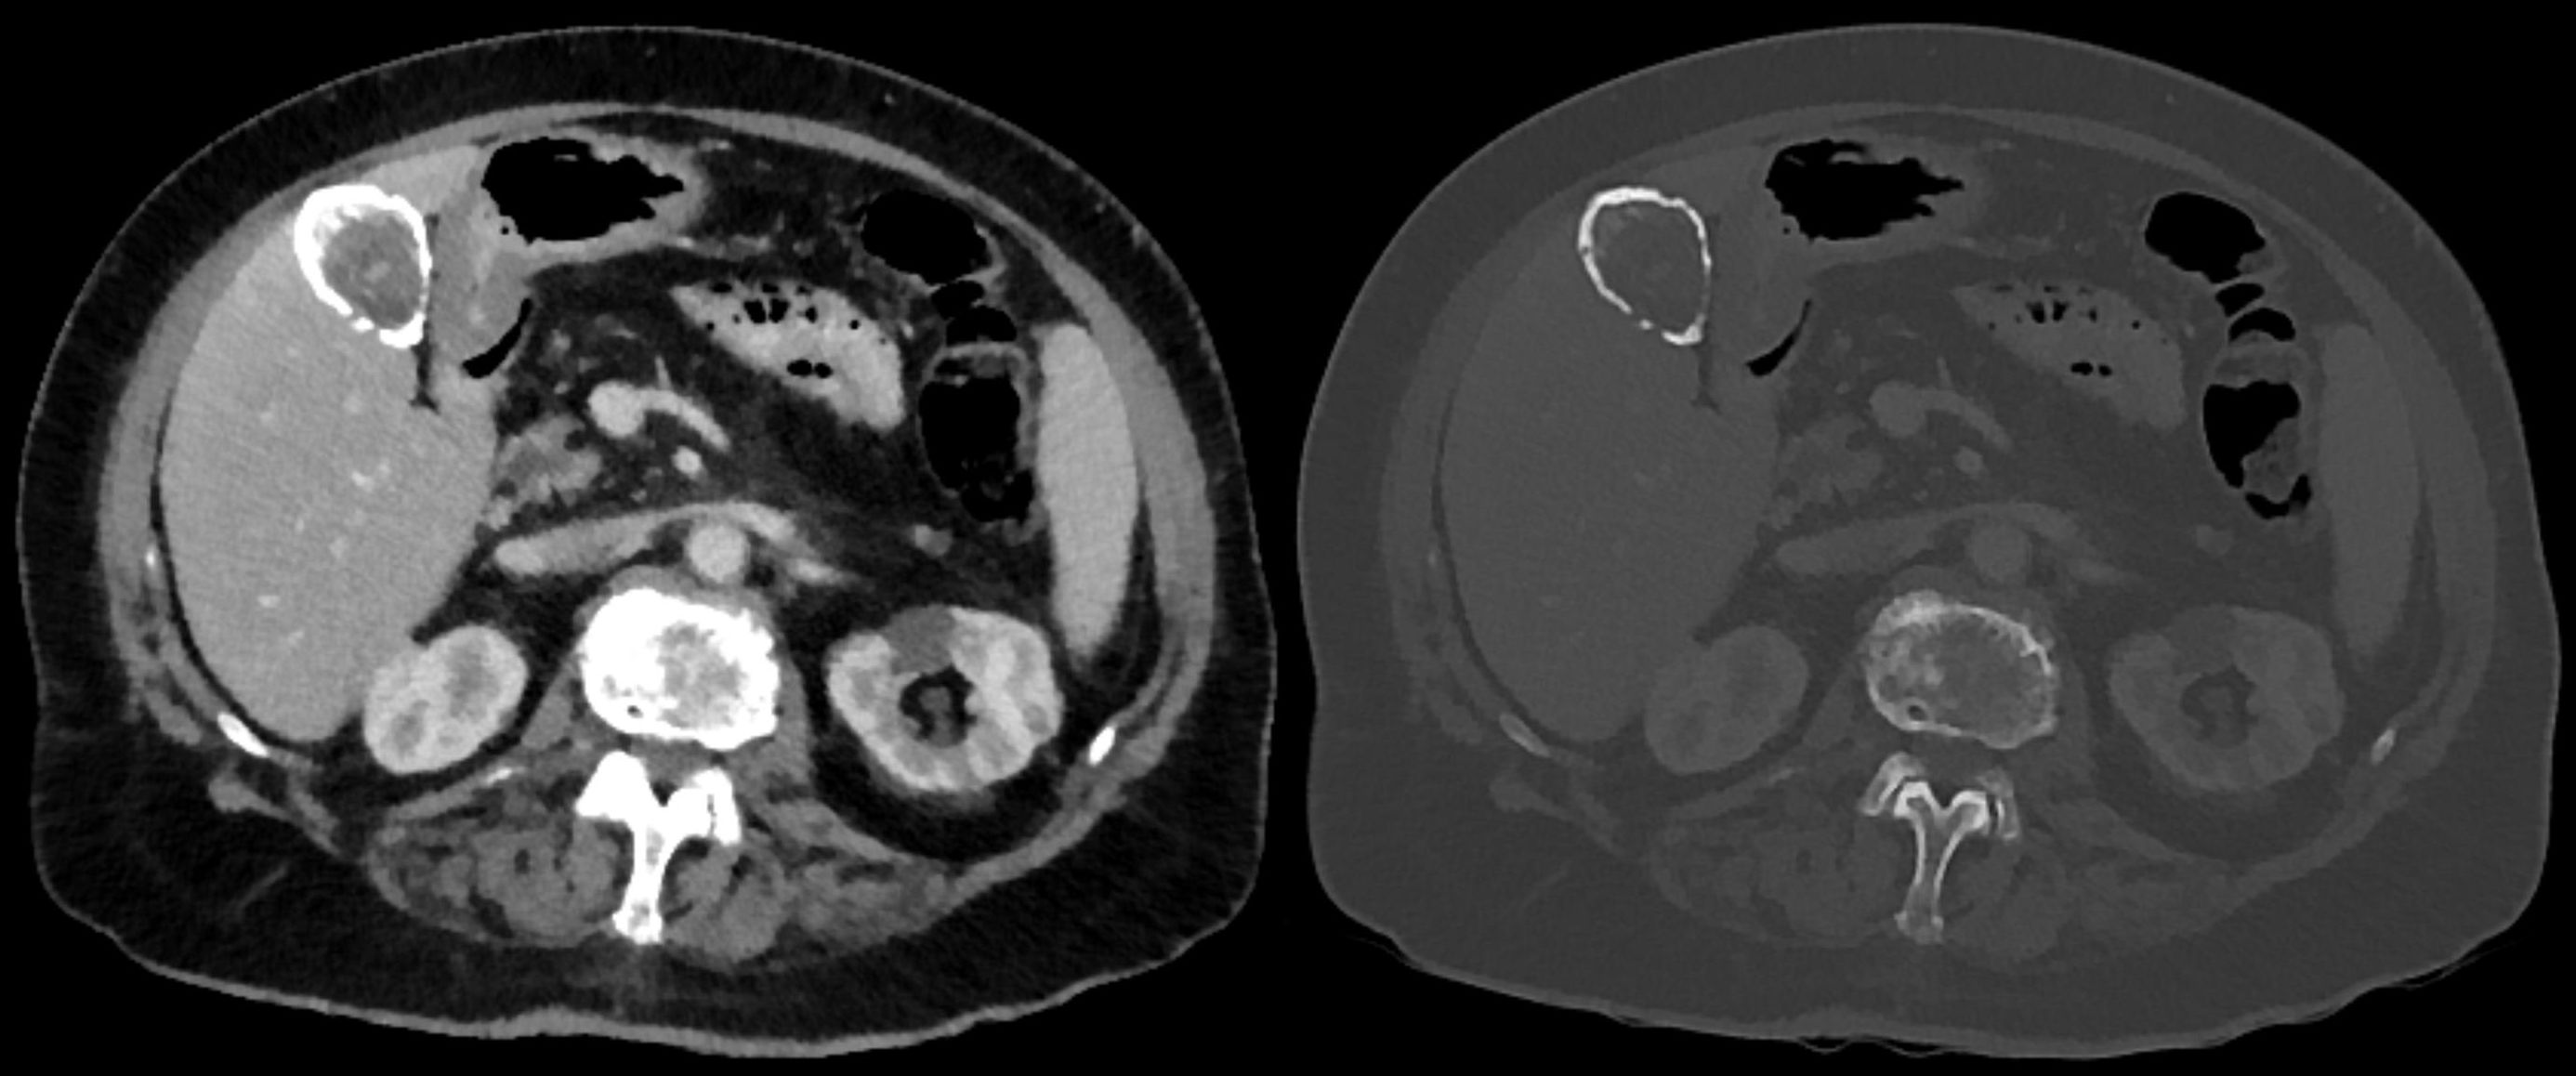
Trace the boundary in the compartment drawing, then inspect the clinical CT pair. In that clinical example, the soft-tissue window is on the left and the bone window is on the right. The dense material outlines the gallbladder beside the liver. Window settings alter conspicuity, not the anatomic compartment. This is a localization example, not proof of microscopic subtype or absence of cancer elsewhere in the examination. [8]
Purpose: locate the dense material before assigning a porcelain label. The upper boundary contains calcium; the lower cavity contains stones. Hatching denotes mineral and does not indicate cancer. [1][3][1][3]
Purpose: follow the calcified boundary across two window settings instead of mistaking a luminal stone for wall calcium. This single illustrated level establishes neither microscopic subtype nor the absence of malignancy elsewhere in the examination. Image: Hellerhoff, CC BY-SA 3.0. [8] Hellerhoff; original source; CC BY-SA 3.0.
On ultrasound, the wall-echo-shadow sign describes a wall echo, a thin intervening bile space, and an echo from stones with posterior shadowing. It supports a stone-filled lumen. Stones can also coexist with true wall calcification. On CT, review the actual images, appropriate windows, available unenhanced images, and earlier examinations rather than acting on the report label alone. Dense sludge and enhancing mucosa are additional pitfalls. Calcium-rich bile may layer inside the lumen; adjacent renal or other abdominal calcification belongs to a different organ. [1][3]
Try the distinction: A report says porcelain gallbladder, but ultrasound shows a thin bile space between the wall and a packed layer of stones. The CT wall itself is not calcified. Name the compartment that explains the density, then decide whether the porcelain-specific risk discussion still applies.
Compare your interpretation
The density is intraluminal. Packed stones explain the report, so correct the diagnosis before discussing porcelain-specific cancer risk. That correction does not decide whether the stones need treatment: recurrent biliary symptoms would provide a separate reason for surgical assessment. [1][3]
Transfer: If both the boundary and separate luminal stones are calcified, retain both findings. Do not let one cancel the other. An uncertain image calls for targeted radiology clarification, not a cancer diagnosis or prophylactic operation by default. [1]
How can chronic injury leave a calcified wall?
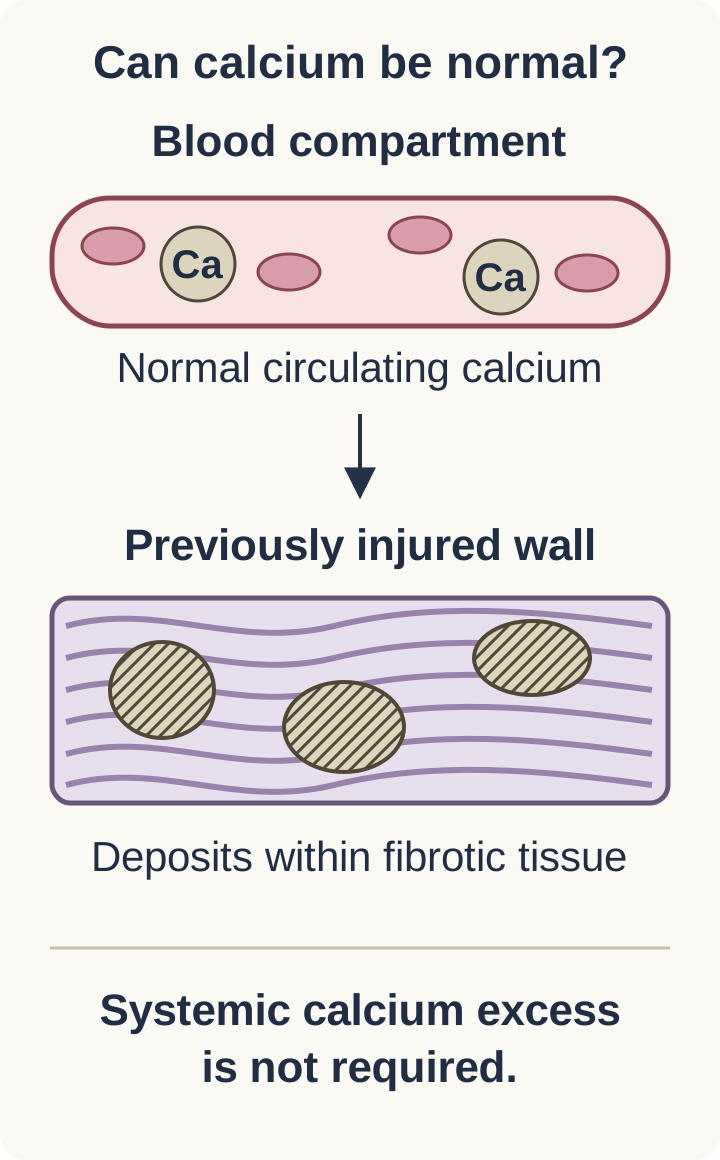
A normal serum calcium level does not contradict a calcified gallbladder. The useful model is local tissue injury followed by dystrophic calcification: damaged tissue becomes a site for calcium deposition without requiring systemic calcium excess. Chronic cholecystitis, fibrosis, and calcification often occur together, although the precise origin of every calcified gallbladder is not established. [3]
In the tissue drawing, separate the blood compartment from the injured wall. Then locate calcium deposits among the fibrotic bands. Repeated gallstone-related irritation, cystic duct obstruction, and bile stasis can sustain inflammation. Scarring and hyalinization alter the wall. Ischemic injury may contribute. This is a proposed biological sequence, not a fixed timetable that every patient follows, and not an inevitable sequence ending in cancer. [3][5]
Purpose: connect normal serum calcium with dystrophic deposition in locally damaged tissue. The arrow relates circulating mineral to a susceptible tissue site; it is not a measured flux, timeline, treatment target, or inevitable progression to cancer. [3][3]
The name porcelain reflects the hard, brittle appearance of an extensively calcified specimen. It does not mean the tissue is normal bone. Nor does a calcified wall establish metastatic cancer: metastatic calcification, a calcium-metabolism term, and cancer metastasis, tumor spread, describe different processes. The local distribution and tissue context matter more than the shared word. [3]
Predict the result: A specimen contains broad fibrotic bands with calcium deposits. The patient's calcium and phosphate measurements are normal. Would correction of serum calcium be expected to reverse this established scar?
Explain the tissue prediction
No. Normal circulating measurements fit deposition in previously damaged tissue. The structural abnormality is a scarred, calcified wall, not evidence that excess circulating calcium is currently driving the finding. Do not invent a calcium-lowering treatment for this imaging diagnosis. [3]
Transfer: A patient need not have a visible obstructing stone today for prior chronic injury to have occurred. Conversely, finding stones today does not prove that the wall is calcified. Keep the history of injury and the present anatomic finding distinct. [1][3]
Which tissue remains between the calcium deposits?
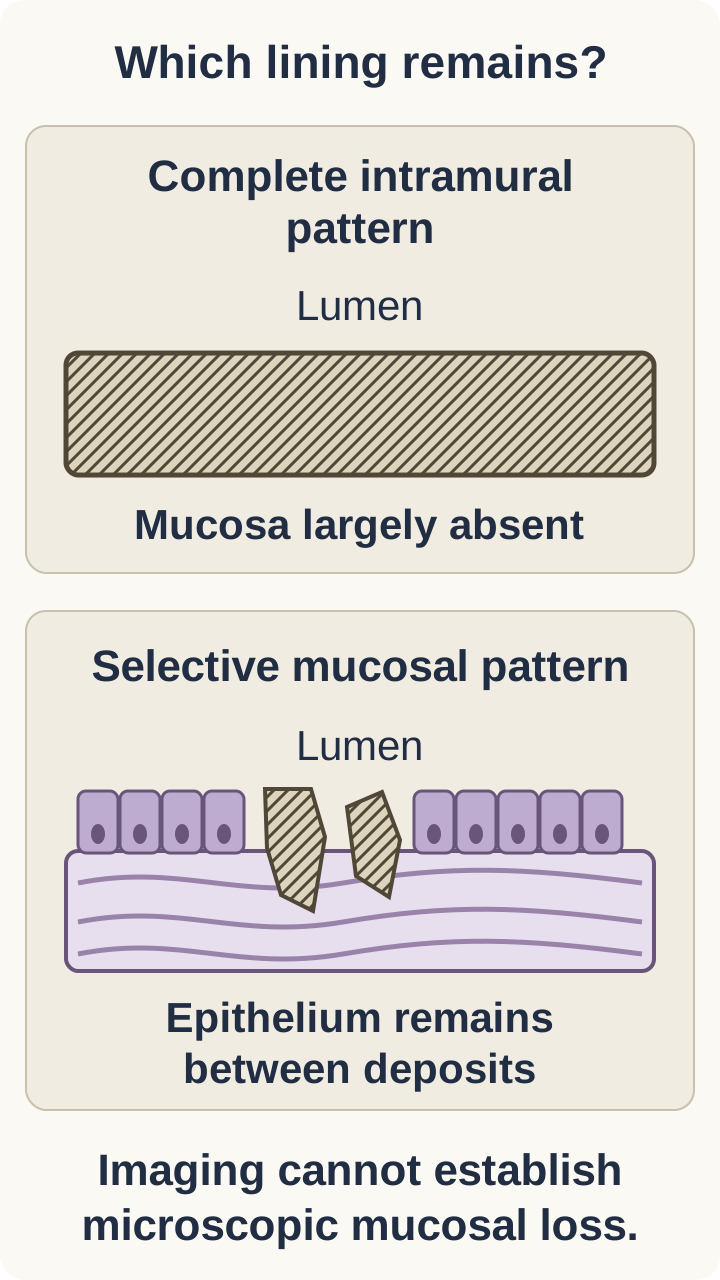
More extensive calcium does not necessarily mean more cancer risk. Two pathological patterns help explain why. Complete intramural calcification extensively involves the fibrotic wall and may be accompanied by loss of the mucosal lining. Selective mucosal calcification is more limited, leaving areas of epithelium between deposits. Retained, chronically injured epithelium is a plausible substrate for dysplasia and carcinoma. This biological explanation supports an association; it does not prove a causal sequence in an individual. [2][3]
Compare the two wall cross-sections in the mucosal-pattern drawing. First identify the lumen, then trace the epithelial lining. In the complete pattern, the lining is largely absent. In the selective pattern, islands of lining remain beside deposits. The important distinction is the tissue left at risk, not simply the amount of white material in the picture. These are idealized pathological patterns, not CT criteria that establish histology. [2][3]
Purpose: explain why retained chronically injured epithelium, rather than total calcium burden, offers a plausible substrate for carcinoma. These idealized tissue patterns explain an association; they do not diagnose malignancy or prove microscopic subtype in a given patient from imaging. [2][3][2][3]
In the Stephen and Berger surgical series, cancer was found in 2 of 27 selectively calcified gallbladders and in 0 of 17 with complete intramural calcification. Those small groups support a difference in association, but zero observed cancers in 17 specimens cannot guarantee zero risk. The study also does not supply an annual risk for an untreated patient. [2]
Predict before checking: Two specimens have chronic inflammation. One has nearly complete replacement of the wall; the other has patchy deposits with surviving mucosal epithelium. Which retains the more plausible epithelial substrate for carcinoma, and why?
Compare the two tissue patterns
The patchy, selectively calcified specimen retains more mucosal epithelium. Cells capable of dysplasia remain within a chronically injured environment. This explains the observed association better than a rule that more calcium means more cancer. Neither pattern alone diagnoses malignancy. [2][3]
Transfer: An imaging report can suggest a complete or selective pattern, but microscopic classification is not guaranteed. Do not require surgery or needle sampling merely to turn an imaging impression into a histological label. Use the best available imaging description, its uncertainty, the clinical findings, and the patient's operative risk. [1][3][4]
What does a cancer percentage actually measure?
The historical concern about malignancy is real, but older selected surgical series are not interchangeable with today's incidentally detected population. A series enriched for symptoms or known cancer can overstate the risk faced by an asymptomatic person. Small denominators also make a reported percentage sensitive to one or two additional cases. Modern retrospective evidence challenges automatic surgery for the label alone without proving that calcification is harmless. [2][4][5]
Keep three denominators separate: all scans originally labeled porcelain, scans confirmed after review, and patients without cancer at the initial examination who are subsequently followed. In the Appel study, 90 of 133 reported cases were confirmed, 42 were false positives, and one remained indeterminate. Five of the 90 confirmed patients had cancer already visible at the initial CT assessment. The reported approximately 6% therefore describes concurrent cancer in that cohort, not a 6% annual conversion rate. [1]
No subsequent gallbladder cancers were observed in the study during a mean follow-up of 6.6 years, with substantial variation in follow-up time. That finding is reassuring for selected patients but cannot establish a lifetime risk of zero. Retrospective ascertainment, limited sample size, variable follow-up, and deaths from other causes limit the inference. Do not calculate an individual's cumulative future risk by repeatedly applying the concurrent-cancer percentage. [1]
Test the interpretation: A patient reads that five cancers were found among 90 confirmed cases and concludes that five new cancers will occur for every 90 patients during each subsequent year. Which part of the study would be needed to support that statement?
Check the denominator and timing
It would require new cancers arising during a defined follow-up interval among patients initially free of cancer. Cancers present at the first examination are not new follow-up events. The actual cohort reported no subsequent cancers, which is different from both a fixed annual rate and proof of no future risk. [1]
Transfer: A nonsignificant comparison of observation and surgery does not establish equivalence. In the DesJardins cohort, treatment was not randomized and the observed patients were older with more comorbidities. Use that study to support thoughtful selection, not a claim that either strategy has proven superior survival. [4]
Is this background calcification, suspected cancer, or acute infection?
Separate a background association with future disease from findings that suggest disease is already present. An enhancing soft-tissue mass, focal disruption by abnormal tissue, extension into the liver, or suspicious regional nodes needs a different response from an isolated calcified outline. Progressive jaundice and unexplained weight loss increase concern, but neither symptom alone proves cancer. Assess the complete clinical and imaging context. [1][6]
Consider three examples. An asymptomatic person has a smooth calcified wall and no mass. Another has patchy calcium but no abnormal enhancing tissue. A third has calcium plus an enlarging enhancing mass crossing the gallbladder-liver interface. The first two require individualized risk-benefit decisions; the third requires prompt hepatobiliary assessment and staging for suspected malignancy. The amount of calcium cannot override the new soft-tissue finding. [2][3][6]
Gas is not calcium. Ultrasound reverberation or dirty shadowing can resemble a bright calcified boundary. On CT, intramural gas has air density rather than calcium density. In a patient with fever, severe right upper quadrant pain, inflammatory changes, and hemodynamic instability, that combination suggests emphysematous cholecystitis. It requires emergency assessment, resuscitation, antimicrobial treatment, and urgent source-control evaluation, not an outpatient cancer-risk discussion. The definitive procedure depends on stability and operative suitability. [3][7]
Change one finding: Keep a patient's longstanding calcified outline unchanged, but add a new enhancing nodule that extends into adjacent liver. Does stability of the calcium justify continued routine observation?
Explain why the new tissue matters
No. The stable calcium and new soft tissue describe different processes. New invasive-appearing tissue requires assessment for existing malignancy. A low-risk calcification pattern is not a reason to disregard it, although the final diagnosis and treatment plan require specialist evaluation. [6]
Transfer: A new fever with persistent pain during observation also changes the decision, but toward urgent assessment for infection rather than automatic cancer staging. First identify which new problem requires care. There is no validated four-level numerical porcelain score that substitutes for this assessment. [3][7]
Match the plan to the patient, not the label
Begin by confirming what the images show. If wall calcification remains uncertain, obtain focused radiology review or additional appropriate imaging before making a porcelain-specific treatment decision. Once the finding is credible, consider symptoms or complications, suspicious tissue, the likely pattern, life expectancy, comorbidities, and patient preferences together. No single percentage supplies the answer. [1][3][4]
Recurrent biliary symptoms in an operatively suitable patient generally support surgical assessment for cholecystectomy, even when the wall appears completely calcified and no mass is present. The indication is treatment of gallbladder disease, not proof of cancer. Establish that the symptoms are compatible with biliary disease: meal-related right upper quadrant episodes are different from isolated reflux-related burning. A coincidental calcified wall need not explain every upper abdominal symptom. [3][5]
An asymptomatic, operatively suitable patient with a selective or patchy pattern merits a shared discussion of elective cholecystectomy because of the associated malignancy concern. This is not an emergency cancer operation. Explain that the imaging subtype is imperfect and the evidence is largely retrospective. For an asymptomatic patient with extensive homogeneous calcification, no suspicious mass, and substantial operative risk, informed observation can be appropriate. Even a potentially higher-risk pattern does not automatically outweigh severe operative risk. [2][3][4]
When surgery is selected, a laparoscopic approach can be feasible with appropriate expertise. Fibrosis and a brittle wall may make dissection and identification of biliary anatomy difficult. Plan for safe alternatives when anatomy cannot be established; calcification alone is not an indication for an oncologic liver resection. Resected tissue needs pathological assessment. Unexpected invasive cancer changes the subsequent plan to specialist staging and consideration of additional treatment. [5][6][7]
Make the comparison: Two patients have confirmed calcification and no mass. One is healthy but has repeated biliary pain; the other is asymptomatic with severe cardiopulmonary disease. State the intended benefit of surgery for the first patient and the main reason to consider observation for the second.
Compare the treatment goals
For the symptomatic patient, surgery can treat recurrent gallbladder disease. For the asymptomatic patient, the uncertain preventive benefit may be outweighed by operative harm. Observation is an active, documented decision, not a declaration that cancer is impossible. [3][4][5]
Transfer into a follow-up plan: Document who will review the patient and what would prompt repeat assessment or imaging. There is no validated universal surveillance interval for every conservatively managed porcelain gallbladder. Persistent or severe pain, fever, or jaundice warrants prompt medical assessment rather than waiting for a routine appointment; systemic illness or instability warrants emergency care. Unexplained weight loss or a new mass also requires reassessment. Revisit the plan when symptoms, imaging, health status, or preferences change. [3][4][6][7]
Independent clinical practice
For each case, state the anatomic finding, identify the new inference it requires, and choose the action or interpretation that follows. The questions test the distinction between a risk association and disease requiring care now.
Case 1
Show answer and explanations for case 1
A. Discuss elective cholecystectomy for selective mural calcification (Why this does not fit)
Confirmed selective mural calcification can justify an elective surgical discussion in a suitable patient. The CT wall is not calcified, and the separated ultrasound echoes identify stones within the cavity. A surgical discussion about porcelain-specific risk requires a credible mural diagnosis. [1] [3]
Reasoning steps for option A
When would selective mural calcification make an elective cholecystectomy discussion reasonable?
Confirmed selective mural calcification can justify an elective surgical discussion in a suitable patient. [1] [3]
Why do the CT wall and separated ultrasound echoes undermine selective mural calcification in this woman?
The CT wall is not calcified, and the separated ultrasound echoes identify stones within the cavity. [1] [3]
Why must the mural location be credible before invoking porcelain-specific surgical risk?
A surgical discussion about porcelain-specific risk requires a credible mural diagnosis. [1] [3]
B. Correct the diagnosis to a stone-filled gallbladder lumen (Best answer)
The faceted densities are inside a thin, noncalcified wall; ultrasound separates the wall from the stone echo. The combined studies support intraluminal stones rather than porcelain gallbladder. Correct the anatomic diagnosis before discussing its implications; asymptomatic stones and mural calcification are not interchangeable. [1] [3]
Reasoning steps for option B
How do the faceted CT densities and intervening bile space locate the calcium?
The faceted densities are inside a thin, noncalcified wall; ultrasound separates the wall from the stone echo. [1] [3]
Why does concordant CT and ultrasound favor stones over porcelain gallbladder?
The combined studies support intraluminal stones rather than porcelain gallbladder. [1] [3]
Why should the diagnosis be corrected before counseling this asymptomatic woman about risk?
Correct the anatomic diagnosis before discussing its implications; asymptomatic stones and mural calcification are not interchangeable. [1] [3]
C. Refer for hepatobiliary staging of a calcified wall tumor (Why this does not fit)
A calcified gallbladder with an associated enhancing mass or invasion needs assessment for malignancy. The supplied images show stones, not abnormal mural soft tissue, and there is no jaundice. Calcific density in the lumen does not establish a gallbladder tumor. [1] [3]
Reasoning steps for option C
What additional tissue finding would make hepatobiliary staging appropriate despite gallbladder calcification?
A calcified gallbladder with an associated enhancing mass or invasion needs assessment for malignancy. [1] [3]
Why do the observed stones and absence of abnormal mural tissue argue against staging a wall tumor?
The supplied images show stones, not abnormal mural soft tissue, and there is no jaundice. [1] [3]
Why does calcium confined to the lumen not establish a gallbladder tumor?
Calcific density in the lumen does not establish a gallbladder tumor. [1] [3]
D. Obtain MR cholangiography for a retained common duct stone (Why this does not fit)
Duct imaging can help when symptoms, laboratory findings, or duct abnormalities raise concern for obstruction. This incidental finding is localized to the gallbladder lumen, with no symptoms or bilirubin abnormality suggesting duct obstruction. Do not change a localized gallbladder finding into a duct diagnosis without supporting evidence. [1] [3]
Reasoning steps for option D
What evidence of duct obstruction would make MR cholangiography useful?
Duct imaging can help when symptoms, laboratory findings, or duct abnormalities raise concern for obstruction. [1] [3]
Why do this woman's incidental luminal stones and normal bilirubin not suggest a retained duct stone?
This incidental finding is localized to the gallbladder lumen, with no symptoms or bilirubin abnormality suggesting duct obstruction. [1] [3]
Why should a gallbladder-lumen finding not be recast as common duct disease?
Do not change a localized gallbladder finding into a duct diagnosis without supporting evidence. [1] [3]
Takeaway: Confirm the anatomic compartment before applying a porcelain-specific cancer-risk discussion. [1] [3]
A. Start a surgical consultation for presumed selective wall calcification (Why this does not fit)
A verified selective calcification pattern may support discussion of elective surgery. The line appears only after contrast and is not supported by a calcific ultrasound finding. An unconfirmed report label should not become the premise for preventive surgery. [1] [3]
Reasoning steps for option A
When would a selective wall-calcification pattern justify discussing elective surgery?
A verified selective calcification pattern may support discussion of elective surgery. [1] [3]
Why does a rim visible only after contrast, without an ultrasound calcific shadow, weaken the surgical premise?
The line appears only after contrast and is not supported by a calcific ultrasound finding. [1] [3]
Why should the preliminary porcelain label be checked before preventive surgery is proposed?
An unconfirmed report label should not become the premise for preventive surgery. [1] [3]
B. Obtain oncologic staging for a presumptive calcified gallbladder malignancy (Why this does not fit)
A suspicious enhancing mass can warrant staging even when calcium is also present. Here the enhancement is a smooth line without a focal mass or invasive finding. Enhancement and calcification must be distinguished before assigning tumor risk. [1] [3]
Reasoning steps for option B
What sort of enhancing gallbladder finding would justify oncologic staging even if calcium were present?
A suspicious enhancing mass can warrant staging even when calcium is also present. [1] [3]
Why does the smooth enhancing line here fail to establish a malignancy requiring staging?
Here the enhancement is a smooth line without a focal mass or invasive finding. [1] [3]
Why must enhancement be distinguished from calcification before inferring tumor risk?
Enhancement and calcification must be distinguished before assigning tumor risk. [1] [3]
C. Arrange endoscopic ultrasonography to sample presumed mural calcified tissue (Why this does not fit)
Targeted tissue acquisition can be considered for selected indeterminate lesions in a specialist diagnostic plan. There is no defined target mass, and the first unresolved question is whether the rim is calcium at all. Needle sampling is not required merely to confirm a porcelain imaging label. [1] [3]
Reasoning steps for option C
When might targeted tissue acquisition be considered for an indeterminate gallbladder lesion?
Targeted tissue acquisition can be considered for selected indeterminate lesions in a specialist diagnostic plan. [1] [3]
Why is endoscopic sampling premature when no target mass is defined and the rim may not be calcium?
There is no defined target mass, and the first unresolved question is whether the rim is calcium at all. [1] [3]
Why is a porcelain imaging label alone insufficient reason for needle sampling?
Needle sampling is not required merely to confirm a porcelain imaging label. [1] [3]
D. Request radiology reassessment for enhancement rather than gallbladder wall calcium (Best answer)
The line is absent without contrast and appears after contrast administration. That phase dependence, together with the smooth nonshadowing wall, supports mucosal enhancement as the imaging pitfall. Reviewing the paired images resolves the specific discrepancy before ordering invasive care. [1] [3]
Reasoning steps for option D
What difference between the unenhanced and enhanced CT images calls the reported calcification into question?
The line is absent without contrast and appears after contrast administration. [1] [3]
How do phase dependence and the nonshadowing smooth wall explain the bright rim?
That phase dependence, together with the smooth nonshadowing wall, supports mucosal enhancement as the imaging pitfall. [1] [3]
Why review the paired CT images before pursuing invasive gallbladder care?
Reviewing the paired images resolves the specific discrepancy before ordering invasive care. [1] [3]
Takeaway: A bright enhanced rim is not automatically mural calcium. [1] [3]
A. Dependent dense material within the gallbladder lumen (Best answer)
The dense material changes its dependent distribution while the surrounding wall remains unchanged. This behavior places the material in the cavity rather than within fixed wall tissue. Describe the intraluminal material and clarify its composition separately; density alone does not diagnose porcelain gallbladder. [1] [3]
Reasoning steps for option A
What does redistribution of the dense material while the wall stays unchanged show?
The dense material changes its dependent distribution while the surrounding wall remains unchanged. [1] [3]
Why does a position-dependent level place this material in the gallbladder cavity?
This behavior places the material in the cavity rather than within fixed wall tissue. [1] [3]
How should the report describe the dense material without prematurely diagnosing porcelain gallbladder?
Describe the intraluminal material and clarify its composition separately; density alone does not diagnose porcelain gallbladder. [1] [3]
B. Selective calcium deposits fixed within gallbladder mucosa (Why this does not fit)
Selective calcification can appear as discontinuous deposits associated with the wall. The described material redistributes with positioning instead of remaining fixed to the same wall segments. A changing fluid level is different from a fixed mucosal plaque. [1] [3]
Reasoning steps for option B
How could selective mucosal calcium appear if it actually involved the wall?
Selective calcification can appear as discontinuous deposits associated with the wall. [1] [3]
Why does movement to the newly dependent surface contradict fixed mucosal deposits?
The described material redistributes with positioning instead of remaining fixed to the same wall segments. [1] [3]
What distinguishes the changing horizontal level from a mucosal calcium plaque?
A changing fluid level is different from a fixed mucosal plaque. [1] [3]
C. Complete calcium replacement of the fibrotic gallbladder wall (Why this does not fit)
Extensive intramural calcification produces a dense boundary around the cavity. The actual outer wall is not calcified, and the density follows gravity inside it. The amount of dense material cannot substitute for establishing mural location. [1] [3]
Reasoning steps for option C
What boundary would complete intramural calcification create around the cavity?
Extensive intramural calcification produces a dense boundary around the cavity. [1] [3]
Why do the noncalcified outer wall and gravity-dependent density refute complete wall replacement?
The actual outer wall is not calcified, and the density follows gravity inside it. [1] [3]
Why cannot a large amount of dense material by itself establish mural calcification?
The amount of dense material cannot substitute for establishing mural location. [1] [3]
D. Mineralized soft tissue invading the adjacent liver surface (Why this does not fit)
A calcified tumor can coexist with an enhancing soft-tissue lesion and local invasion. There is no nodule or invasive tissue; instead there is a positional level within the cavity. Interpret soft-tissue behavior separately from the mere presence of density. [1] [3]
Reasoning steps for option D
What accompanying findings would make mineralized invasive tumor plausible?
A calcified tumor can coexist with an enhancing soft-tissue lesion and local invasion. [1] [3]
Why does a positional cavity level without a nodule argue against liver-invasive tissue?
There is no nodule or invasive tissue; instead there is a positional level within the cavity. [1] [3]
Why must soft-tissue behavior be assessed separately from the density of this gallbladder finding?
Interpret soft-tissue behavior separately from the mere presence of density. [1] [3]
Takeaway: Fixed wall calcium and dependent intraluminal material have different spatial behavior. [1] [3]
A. Calcium precipitation in normal tissue from sustained systemic hypercalcemia (Why this does not fit)
Metabolic calcium excess can promote mineral deposition in otherwise uninjured tissues. The circulating measurements are normal and the deposits are localized to an injured fibrotic wall. The tissue setting distinguishes local dystrophic deposition from a systemic metabolic explanation. [3]
Reasoning steps for option A
Under what systemic condition can calcium precipitate in otherwise uninjured tissue?
Metabolic calcium excess can promote mineral deposition in otherwise uninjured tissues. [3]
Why do normal circulating mineral measurements and localized fibrotic injury oppose systemic hypercalcemia as the explanation?
The circulating measurements are normal and the deposits are localized to an injured fibrotic wall. [3]
How does the injured tissue context distinguish dystrophic deposition from a metabolic cause?
The tissue setting distinguishes local dystrophic deposition from a systemic metabolic explanation. [3]
B. Retention of a calcified luminal stone against an intact wall (Why this does not fit)
A stone pressed against the wall can mimic mural calcium on imaging. Histology places these deposits within hyalinized tissue and separately identifies the luminal stones. A radiological mimic cannot explain deposits demonstrated inside injured wall tissue. [3]
Reasoning steps for option B
How might a stone pressed against the gallbladder wall imitate mural calcium on imaging?
A stone pressed against the wall can mimic mural calcium on imaging. [3]
Why does histology rule out the separate luminal stones as the source of these wall deposits?
Histology places these deposits within hyalinized tissue and separately identifies the luminal stones. [3]
Why cannot a stone-related imaging mimic explain mineral inside the injured wall?
C. Calcium deposition in a chronically injured and fibrotic wall (Best answer)
Chronic inflammation and fibrosis establish a local site of tissue injury. Calcium deposition in that damaged tissue can occur despite normal serum calcium and phosphate. The combination supports dystrophic calcification rather than ongoing systemic calcium excess. [3]
Reasoning steps for option C
What local changes in this specimen provide a site for mineral deposition?
Chronic inflammation and fibrosis establish a local site of tissue injury. [3]
Why can calcium accumulate in the damaged wall despite normal serum calcium and phosphate?
Calcium deposition in that damaged tissue can occur despite normal serum calcium and phosphate. [3]
Which mechanism best combines the scarred wall and normal metabolic measurements?
The combination supports dystrophic calcification rather than ongoing systemic calcium excess. [3]
D. Formation of organized bone through metaplasia of stromal tissue (Why this does not fit)
Osseous metaplasia produces organized bone structures rather than calcium deposits alone. No osteoid is seen, while the mineral is embedded in scarred tissue. The hard consistency implied by porcelain does not establish bone formation. [3]
Reasoning steps for option D
What organized structures would support osseous metaplasia rather than simple calcium deposition?
Osseous metaplasia produces organized bone structures rather than calcium deposits alone. [3]
Why do absent osteoid and mineral in scarred tissue oppose bone formation?
No osteoid is seen, while the mineral is embedded in scarred tissue. [3]
Why does the porcelain-like hardness not establish osseous metaplasia?
The hard consistency implied by porcelain does not establish bone formation. [3]
Takeaway: Local dystrophic calcification does not require hypercalcemia. [3]
A. Specimen X has greater concern because its total mineral burden is larger (Why this does not fit)
A larger imaging abnormality can appear more concerning when size is used as a general risk heuristic. Here extensive calcification coincides with loss of the epithelial substrate rather than a larger population of at-risk mucosal cells. Mineral quantity is not a validated surrogate for malignant potential. [2] [3]
Reasoning steps for option A
Why might the extensively calcified specimen X initially appear more concerning?
A larger imaging abnormality can appear more concerning when size is used as a general risk heuristic. [2] [3]
How does X's mucosal loss undermine the inference that its larger calcium burden means more epithelial risk?
Here extensive calcification coincides with loss of the epithelial substrate rather than a larger population of at-risk mucosal cells. [2] [3]
Why is total mineral quantity an unreliable substitute for malignant potential?
Mineral quantity is not a validated surrogate for malignant potential. [2] [3]
B. Specimen Y has greater concern because patchy deposits establish existing epithelial invasion (Why this does not fit)
Patchy calcification can coexist with carcinoma in selected cases. The histological sections explicitly show no invasion; the question concerns association, not a current cancer diagnosis. A risk-associated pattern cannot establish invasive disease. [2] [3]
Reasoning steps for option B
Why might patchy calcium in specimen Y raise concern about coexisting carcinoma?
Patchy calcification can coexist with carcinoma in selected cases. [2] [3]
Why does the absence of invasion on the examined sections defeat a claim of existing invasive cancer?
The histological sections explicitly show no invasion; the question concerns association, not a current cancer diagnosis. [2] [3]
Why cannot a risk-associated patchy pattern itself establish epithelial invasion?
A risk-associated pattern cannot establish invasive disease. [2] [3]
C. Both specimens have equal concern because their biliary symptom histories are comparable (Why this does not fit)
Similar symptoms may reflect similar gallbladder dysfunction and can support treatment of symptomatic disease. The remaining epithelial tissue differs despite comparable symptom histories. The indication to treat symptoms and the biology of malignancy association are separate questions. [2] [3]
Reasoning steps for option C
What clinical decision could the specimens' similar biliary pain histories support?
Similar symptoms may reflect similar gallbladder dysfunction and can support treatment of symptomatic disease. [2] [3]
Why do comparable symptoms not erase the specimens' difference in remaining epithelium?
Why should an indication to treat biliary symptoms not be confused with the pattern's cancer association?
The indication to treat symptoms and the biology of malignancy association are separate questions. [2] [3]
D. Specimen Y has greater concern because surviving mucosa remains exposed to chronic injury (Best answer)
Specimen Y retains epithelium between calcium deposits, whereas specimen X has extensive mucosal loss. Retained epithelium provides a plausible substrate for dysplasia within the chronically injured wall. This supports the reported association without diagnosing cancer or proving an individual's future outcome. [2] [3]
Reasoning steps for option D
What epithelial difference between Y and X matters more than their total calcium burden?
Specimen Y retains epithelium between calcium deposits, whereas specimen X has extensive mucosal loss. [2] [3]
Why is retained, chronically injured epithelium a plausible substrate for dysplasia?
Retained epithelium provides a plausible substrate for dysplasia within the chronically injured wall. [2] [3]
What can the selective pattern's reported association imply without diagnosing cancer or predicting this patient's outcome?
This supports the reported association without diagnosing cancer or proving an individual's future outcome. [2] [3]
Takeaway: Retained epithelium explains the pattern association better than the amount of calcium. [2] [3]
A. Imaging establishes diffuse fibrosis and excludes residual dysplastic mucosal tissue (Why this does not fit)
A complete pathological pattern can include extensive fibrosis and mucosal loss. CT shows the distribution of macroscopic calcium, not every residual epithelial cell or focus of dysplasia. Do not substitute an imaging pattern for microscopic examination. [1] [2] [3]
Reasoning steps for option A
What mucosal change may accompany a truly complete pathological calcification pattern?
A complete pathological pattern can include extensive fibrosis and mucosal loss. [1] [2] [3]
Why cannot serial CT demonstrate that every dysplastic epithelial focus has disappeared?
CT shows the distribution of macroscopic calcium, not every residual epithelial cell or focus of dysplasia. [1] [2] [3]
Why should an apparently complete CT pattern not be treated as microscopic proof of fibrosis and mucosal loss?
Do not substitute an imaging pattern for microscopic examination. [1] [2] [3]
B. Imaging supports mural calcification but cannot establish complete mucosal loss (Best answer)
The density follows the wall on serial examinations, supporting a genuine mural finding. The apparently complete distribution suggests a pattern but does not prove microscopic elimination of mucosa. Counsel using the likely pattern and its uncertainty rather than guaranteeing absence of malignancy. [1] [2] [3]
Reasoning steps for option B
Why does a calcific outline following the wall on two CT examinations support true mural calcification?
The density follows the wall on serial examinations, supporting a genuine mural finding. [1] [2] [3]
What does the apparently complete outline suggest but fail to prove about residual mucosa?
The apparently complete distribution suggests a pattern but does not prove microscopic elimination of mucosa. [1] [2] [3]
How should uncertainty in the CT pattern shape counseling about malignancy?
Counsel using the likely pattern and its uncertainty rather than guaranteeing absence of malignancy. [1] [2] [3]
C. Imaging excludes occult carcinoma because the calcific rim is circumferential (Why this does not fit)
A circumferential pattern without an obvious mass can be reassuring compared with invasive-appearing tissue. Neither that pattern nor stability establishes the absence of every small or microscopic tumor. Lower concern is not the same as exclusion of occult disease. [1] [2] [3]
Reasoning steps for option C
Why is a stable circumferential rim without a mass somewhat reassuring?
A circumferential pattern without an obvious mass can be reassuring compared with invasive-appearing tissue. [1] [2] [3]
Why can neither circumferential calcium nor 18-month stability exclude microscopic tumor?
Neither that pattern nor stability establishes the absence of every small or microscopic tumor. [1] [2] [3]
Why does lower concern from the CT appearance not amount to exclusion of occult cancer?
Lower concern is not the same as exclusion of occult disease. [1] [2] [3]
D. Imaging demonstrates carcinoma in situ because calcium involves the gallbladder wall (Why this does not fit)
Wall calcification has a reported association with carcinoma in some populations. An association is not histological evidence of malignant epithelium, and there is no focal mass here. Carcinoma in situ requires tissue criteria rather than the porcelain label. [1] [2] [3]
Reasoning steps for option D
Why might a trainee associate gallbladder wall calcium with carcinoma?
Wall calcification has a reported association with carcinoma in some populations. [1] [2] [3]
Why do an association and absence of a focal mass not demonstrate carcinoma in situ?
An association is not histological evidence of malignant epithelium, and there is no focal mass here. [1] [2] [3]
What evidence, rather than the porcelain label, is needed to establish carcinoma in situ?
Carcinoma in situ requires tissue criteria rather than the porcelain label. [1] [2] [3]
Takeaway: CT may suggest the pattern but cannot prove total mucosal loss or zero cancer risk. [1] [2] [3]
A. Plan elective cholecystectomy after further cardiopulmonary optimization (Why this does not fit)
Elective surgery can be reasonable when preventive or symptomatic benefit exceeds operative harm. He has no symptoms or suspicious tissue, while substantial operative risk and his preference weigh against a preventive operation. Optimization does not by itself create a net benefit for surgery. [3] [4] [7]
Reasoning steps for option A
When might elective cholecystectomy outweigh operative harm in a patient with wall calcification?
Elective surgery can be reasonable when preventive or symptomatic benefit exceeds operative harm. [3] [4] [7]
Why do absent symptoms, high cardiopulmonary risk, and this man's preference argue against preventive surgery?
He has no symptoms or suspicious tissue, while substantial operative risk and his preference weigh against a preventive operation. [3] [4] [7]
Why would cardiopulmonary optimization alone not establish a net benefit from cholecystectomy?
Optimization does not by itself create a net benefit for surgery. [3] [4] [7]
B. Arrange hepatobiliary staging before an oncologic operation (Why this does not fit)
A mass, invasion, or other concerning evidence would warrant assessment for an existing malignancy. Expert review finds none of those features; the finding is isolated homogeneous calcification. A cancer association is not sufficient evidence to plan an oncologic operation. [3] [4] [7]
Reasoning steps for option B
What additional findings would warrant staging for an existing gallbladder malignancy?
A mass, invasion, or other concerning evidence would warrant assessment for an existing malignancy. [3] [4] [7]
Why does expert review of isolated homogeneous calcium not support oncologic staging?
Expert review finds none of those features; the finding is isolated homogeneous calcification. [3] [4] [7]
Why does an association with cancer not itself warrant an oncologic operation?
A cancer association is not sufficient evidence to plan an oncologic operation. [3] [4] [7]
C. Plan informed observation with individualized clinical follow-up (Best answer)
The finding is asymptomatic, homogeneous, and not accompanied by a suspicious mass. Potential preventive benefit is uncertain and must be weighed against his substantial operative risk and expressed preference. Observation should include a documented reassessment plan and symptoms that require prompt care. [3] [4] [7]
Reasoning steps for option C
Which features of the calcified gallbladder make immediate intervention less compelling?
The finding is asymptomatic, homogeneous, and not accompanied by a suspicious mass. [3] [4] [7]
How do uncertain preventive benefit, serious operative risk, and expressed preference favor observation?
Potential preventive benefit is uncertain and must be weighed against his substantial operative risk and expressed preference. [3] [4] [7]
What should informed observation include so changes prompt appropriate care?
Observation should include a documented reassessment plan and symptoms that require prompt care. [3] [4] [7]
D. Arrange percutaneous drainage to avoid general anesthesia (Why this does not fit)
Gallbladder drainage may be needed for selected patients with acute infection who are unsuitable for surgery. This patient has no infected or obstructed acute gallbladder syndrome requiring source control. High surgical risk alone is not an indication to drain an asymptomatic gallbladder. [3] [4] [7]
Reasoning steps for option D
When could percutaneous gallbladder drainage help a patient unsuitable for surgery?
Gallbladder drainage may be needed for selected patients with acute infection who are unsuitable for surgery. [3] [4] [7]
Why is drainage unnecessary in this asymptomatic man with no acute infected or obstructed gallbladder?
This patient has no infected or obstructed acute gallbladder syndrome requiring source control. [3] [4] [7]
Why does high anesthetic risk alone not create an indication for gallbladder drainage?
High surgical risk alone is not an indication to drain an asymptomatic gallbladder. [3] [4] [7]
Takeaway: Selected high-risk asymptomatic patients can be observed without declaring the finding risk-free. [3] [4] [7]
A. Arrange an elective surgical consultation for risk-benefit discussion (Best answer)
The selective-appearing pattern raises an association-based concern despite the absence of symptoms. Her good operative suitability makes an elective discussion of cholecystectomy and observation appropriate. A shared preventive decision is different from treatment of established malignancy. [2] [3] [4]
Reasoning steps for option A
Why does selective-appearing calcification warrant consideration despite no biliary symptoms?
The selective-appearing pattern raises an association-based concern despite the absence of symptoms. [2] [3] [4]
How does this woman's operative suitability affect the choice between elective cholecystectomy and observation?
Her good operative suitability makes an elective discussion of cholecystectomy and observation appropriate. [2] [3] [4]
Why is a shared elective decision different from treatment for proven malignancy?
A shared preventive decision is different from treatment of established malignancy. [2] [3] [4]
B. Arrange urgent surgical admission for presumed invasive gallbladder carcinoma (Why this does not fit)
Urgent specialist assessment is appropriate when findings suggest active invasive disease or an acute complication. The images show no mass or invasion, and she has no acute symptoms. Patchy calcification alone is not a diagnosis of invasive carcinoma. [2] [3] [4]
Reasoning steps for option B
What evidence of invasive disease or acute complication would justify urgent specialist assessment?
Urgent specialist assessment is appropriate when findings suggest active invasive disease or an acute complication. [2] [3] [4]
Why do absent mass, invasion, and acute symptoms oppose urgent admission for presumed carcinoma?
The images show no mass or invasion, and she has no acute symptoms. [2] [3] [4]
Patchy calcification alone is not a diagnosis of invasive carcinoma. [2] [3] [4]
C. Arrange discharge from follow-up after reassuring assessment of symptoms (Why this does not fit)
Lack of symptoms lowers concern for current biliary complications. Symptoms are only one consideration; the confirmed patchy mural pattern and her operative suitability still warrant discussion. An asymptomatic presentation does not complete the risk-benefit assessment. [2] [3] [4]
Reasoning steps for option C
What does the absence of biliary symptoms suggest about current complications?
Lack of symptoms lowers concern for current biliary complications. [2] [3] [4]
Why do confirmed patchy mural calcium and operative fitness still merit discussion despite no symptoms?
Symptoms are only one consideration; the confirmed patchy mural pattern and her operative suitability still warrant discussion. [2] [3] [4]
Why does an asymptomatic assessment alone not settle whether follow-up can end?
An asymptomatic presentation does not complete the risk-benefit assessment. [2] [3] [4]
D. Arrange percutaneous wall sampling to establish indications for preventive surgery (Why this does not fit)
Histology can establish microscopic tissue characteristics when tissue is obtained for a clinical indication. There is no target mass, and routine sampling is not required merely to classify calcification before discussion. Do not require a needle procedure just to resolve a preventive decision that can be considered from available clinical data. [2] [3] [4]
Reasoning steps for option D
What could histology establish if gallbladder tissue were obtained for a clinical indication?
Histology can establish microscopic tissue characteristics when tissue is obtained for a clinical indication. [2] [3] [4]
Why does the absence of a target mass make routine wall sampling unnecessary before counseling?
There is no target mass, and routine sampling is not required merely to classify calcification before discussion. [2] [3] [4]
Why can the preventive decision be discussed without a needle procedure to classify the calcification?
Do not require a needle procedure just to resolve a preventive decision that can be considered from available clinical data. [2] [3] [4]
Takeaway: Selective-appearing calcification supports elective discussion, not automatic emergency cancer surgery. [2] [3] [4]
A. Relief of persistent common bile duct obstruction (Why this does not fit)
Duct obstruction can require intervention when supported by duct imaging or cholestatic findings. The pain resolves between episodes, bilirubin is normal, and the common duct is not dilated. Gallbladder symptoms do not by themselves establish persistent duct obstruction. [3] [5] [7]
Reasoning steps for option A
What evidence would make persistent common-duct obstruction an intervention target?
Duct obstruction can require intervention when supported by duct imaging or cholestatic findings. [3] [5] [7]
How do normal bilirubin and a nondilated duct challenge persistent obstruction here?
The pain resolves between episodes, bilirubin is normal, and the common duct is not dilated. [3] [5] [7]
Why does episodic gallbladder pain not establish a retained duct stone?
Gallbladder symptoms do not by themselves establish persistent duct obstruction. [3] [5] [7]
B. Source control for acute infected gallbladder contents (Why this does not fit)
Persistent pain with fever and inflammatory findings can indicate acute gallbladder infection. He has intermittent self-limited episodes without fever or pericholecystic inflammation. Recurrent biliary symptoms and acute infected disease have different immediate treatment goals. [3] [5] [7]
Reasoning steps for option B
What presentation would make infected gallbladder contents require source control?
Persistent pain with fever and inflammatory findings can indicate acute gallbladder infection. [3] [5] [7]
Which features distinguish his resolving episodes from acute infection?
He has intermittent self-limited episodes without fever or pericholecystic inflammation. [3] [5] [7]
How does the treatment goal differ between recurrent biliary pain and infected gallbladder disease?
Recurrent biliary symptoms and acute infected disease have different immediate treatment goals. [3] [5] [7]
C. Resection of an established invasive gallbladder tumor (Why this does not fit)
A proven or strongly suspected invasive tumor changes surgical planning. No mass or invasion is demonstrated; mural calcium is an association-based finding. Do not call symptom-directed surgery an oncologic operation without evidence of cancer. [3] [5] [7]
Reasoning steps for option C
When would suspected invasive gallbladder cancer alter the operation?
A proven or strongly suspected invasive tumor changes surgical planning. [3] [5] [7]
Why does wall calcium without a mass not establish an invasive tumor?
No mass or invasion is demonstrated; mural calcium is an association-based finding. [3] [5] [7]
Why should this proposed operation not be framed as oncologic resection?
Do not call symptom-directed surgery an oncologic operation without evidence of cancer. [3] [5] [7]
D. Treatment of recurrent symptomatic gallbladder disease (Best answer)
The episodic meal-related right upper quadrant pain and gallstones fit recurrent biliary symptoms. That symptomatic burden provides a treatment indication despite a complete-appearing pattern without cancer findings. A lower-associated-risk calcification pattern does not erase the benefit of treating recurrent gallbladder symptoms. [3] [5] [7]
Reasoning steps for option D
Which features link his postprandial episodes to symptomatic gallbladder disease?
The episodic meal-related right upper quadrant pain and gallstones fit recurrent biliary symptoms. [3] [5] [7]
Why do recurrent symptoms support surgery despite complete-appearing calcification?
That symptomatic burden provides a treatment indication despite a complete-appearing pattern without cancer findings. [3] [5] [7]
Why does the apparently lower-risk mural pattern not eliminate symptom-directed benefit?
A lower-associated-risk calcification pattern does not erase the benefit of treating recurrent gallbladder symptoms. [3] [5] [7]
Takeaway: Symptom-directed cholecystectomy does not require a high cancer-risk pattern. [3] [5] [7]
A. Arrange outpatient imaging review and elective preventive surgical counseling (Why this does not fit)
Outpatient review is reasonable for a stable incidental calcification finding. Hypotension, confusion, fever, and intramural air indicate an acute dangerous process rather than a stable calcified wall. The acute physiology determines urgency even when the ultrasound boundary looks bright. [3] [7]
Reasoning steps for option A
When would outpatient review of a bright gallbladder boundary be reasonable?
Outpatient review is reasonable for a stable incidental calcification finding. [3] [7]
What do intramural air, fever, confusion, and hypotension indicate instead?
Hypotension, confusion, fever, and intramural air indicate an acute dangerous process rather than a stable calcified wall. [3] [7]
Why must the unstable physiology override the bright ultrasound appearance?
The acute physiology determines urgency even when the ultrasound boundary looks bright. [3] [7]
B. Begin resuscitation, intravenous antibiotics, and urgent source-control assessment (Best answer)
Intramural air with inflammatory change indicates a gas-forming gallbladder infection in this clinical setting. Hypotension and altered mental status require emergency care rather than delayed preventive discussion. Treat suspected emphysematous cholecystitis urgently; the source-control procedure is selected according to stability and operative suitability. [3] [7]
Reasoning steps for option B
What does CT air in an inflamed gallbladder wall suggest in this patient?
Intramural air with inflammatory change indicates a gas-forming gallbladder infection in this clinical setting. [3] [7]
Why do hypotension and confusion require immediate rather than elective care?
Hypotension and altered mental status require emergency care rather than delayed preventive discussion. [3] [7]
How should urgency and procedure selection be approached for suspected emphysematous cholecystitis?
Treat suspected emphysematous cholecystitis urgently; the source-control procedure is selected according to stability and operative suitability. [3] [7]
C. Begin hepatobiliary cancer staging and plan an oncologic resection (Why this does not fit)
An invasive soft-tissue mass with compatible findings would warrant cancer staging. The key CT abnormality is intramural air, accompanied by fever and circulatory instability, not a described invasive mass. Do not redirect a septic presentation into an elective malignancy workup. [3] [7]
Reasoning steps for option C
What finding would justify hepatobiliary cancer staging?
An invasive soft-tissue mass with compatible findings would warrant cancer staging. [3] [7]
Why do air-density pockets and sepsis favor infection over an invasive mass?
The key CT abnormality is intramural air, accompanied by fever and circulatory instability, not a described invasive mass. [3] [7]
Why would oncologic staging misprioritize this presentation?
Do not redirect a septic presentation into an elective malignancy workup. [3] [7]
D. Begin oral antibiotics and reassess after interval outpatient imaging (Why this does not fit)
Outpatient reassessment can fit some mild, stable problems without systemic deterioration. This patient has shock physiology and altered mental status, so oral treatment with delayed imaging is inadequate. A gas-forming gallbladder infection with instability requires hospital-level resuscitation and source-control assessment. [3] [7]
Reasoning steps for option D
When might oral antibiotics and outpatient reassessment be acceptable?
Outpatient reassessment can fit some mild, stable problems without systemic deterioration. [3] [7]
Why are oral treatment and delayed imaging inadequate with shock and confusion?
This patient has shock physiology and altered mental status, so oral treatment with delayed imaging is inadequate. [3] [7]
What level of care does an unstable gas-forming gallbladder infection require?
A gas-forming gallbladder infection with instability requires hospital-level resuscitation and source-control assessment. [3] [7]
Takeaway: Intramural gas plus systemic illness is an emergency, not an incidental porcelain risk discussion. [3] [7]
A. Obtain hepatobiliary staging and specialist oncologic surgical assessment (Best answer)
The enhancing invasive-appearing tissue and regional nodes raise concern for an existing malignancy. Progressive painless jaundice and weight loss reinforce that concern beyond the background calcification finding. Define disease extent and specialist treatment options rather than proceeding as routine preventive cholecystectomy. [6]
Reasoning steps for option A
What do enhancing tissue extending into liver and enlarged nodes suggest?
The enhancing invasive-appearing tissue and regional nodes raise concern for an existing malignancy. [6]
How do painless jaundice and weight loss add to concern about the new tissue?
Progressive painless jaundice and weight loss reinforce that concern beyond the background calcification finding. [6]
Why is staging preferable to routine preventive cholecystectomy now?
Define disease extent and specialist treatment options rather than proceeding as routine preventive cholecystectomy. [6]
B. Continue calcification surveillance while monitoring the bilirubin level (Why this does not fit)
Observation can fit selected patients with isolated calcification and no concerning clinical findings. This patient now has invasive-appearing soft tissue, nodes, jaundice, and weight loss. A prior surveillance decision must be reconsidered when evidence of active disease appears. [6]
Reasoning steps for option B
In what setting could isolated wall calcification be observed?
Observation can fit selected patients with isolated calcification and no concerning clinical findings. [6]
Which new findings make continued surveillance inappropriate here?
This patient now has invasive-appearing soft tissue, nodes, jaundice, and weight loss. [6]
Why must the earlier observation decision be revisited?
A prior surveillance decision must be reconsidered when evidence of active disease appears. [6]
C. Schedule routine cholecystectomy for symptomatic nonmalignant gallbladder disease (Why this does not fit)
Routine cholecystectomy can address recurrent biliary symptoms without suspicious tissue. Possible liver invasion and nodal disease require a cancer-oriented assessment before selecting an operation. Do not let the old porcelain label conceal a new oncologic problem. [6]
Reasoning steps for option C
When would routine cholecystectomy address gallbladder symptoms?
Routine cholecystectomy can address recurrent biliary symptoms without suspicious tissue. [6]
Why do possible liver invasion and nodes change surgical planning?
Possible liver invasion and nodal disease require a cancer-oriented assessment before selecting an operation. [6]
How should the prior porcelain label affect interpretation of the new mass?
Do not let the old porcelain label conceal a new oncologic problem. [6]
D. Repeat ultrasound after a course of oral antibiotic treatment (Why this does not fit)
Antimicrobial treatment with reassessment may be considered when an infectious process is the working diagnosis. The afebrile progressive presentation and invasive mass with nodes require prompt malignancy assessment, not an empirical delay. Assess the dominant clinical and imaging pattern rather than treating every abnormal wall as uncomplicated inflammation. [6]
Reasoning steps for option D
When might antibiotics followed by imaging address a gallbladder wall abnormality?
Antimicrobial treatment with reassessment may be considered when an infectious process is the working diagnosis. [6]
Why does this afebrile progressive mass-and-node presentation not support empirical delay?
The afebrile progressive presentation and invasive mass with nodes require prompt malignancy assessment, not an empirical delay. [6]
Which dominant findings should direct assessment instead of presumed inflammation?
Assess the dominant clinical and imaging pattern rather than treating every abnormal wall as uncomplicated inflammation. [6]
Takeaway: An invasive-appearing mass changes the problem from future risk to assessment of existing cancer. [6]
A. Continue the prior observation plan because the calcific outline is stable (Why this does not fit)
Serial stability can reassure when the relevant abnormality itself remains unchanged. The calcium is stable, but the enhancing soft tissue is a separate new abnormality. Stability of one imaging component does not establish stability of the entire lesion. [1] [6]
Reasoning steps for option A
When can stability on serial imaging support continued observation?
Serial stability can reassure when the relevant abnormality itself remains unchanged. [1] [6]
Why does unchanged calcium not account for the new enhancing nodule?
The calcium is stable, but the enhancing soft tissue is a separate new abnormality. [1] [6]
Why cannot stability of the outline establish stability of the whole finding?
Stability of one imaging component does not establish stability of the entire lesion. [1] [6]
B. Discuss routine prophylactic surgery because the nodule changes the calcification subtype (Why this does not fit)
Calcification pattern can influence an elective risk-benefit discussion when no suspicious tissue is present. A new enhancing nodule is not simply a switch between complete and selective calcium patterns. Evaluate abnormal soft tissue as a potential current lesion rather than reducing it to a risk category. [1] [6]
Reasoning steps for option B
When does calcium pattern guide an elective surgical discussion?
Calcification pattern can influence an elective risk-benefit discussion when no suspicious tissue is present. [1] [6]
Why is a new enhancing nodule not merely a change in calcification subtype?
A new enhancing nodule is not simply a switch between complete and selective calcium patterns. [1] [6]
Why should the nodule be assessed as possible current disease rather than preventive risk?
Evaluate abnormal soft tissue as a potential current lesion rather than reducing it to a risk category. [1] [6]
C. Arrange prompt specialist assessment of a new soft-tissue lesion despite stable calcium (Best answer)
Comparison with the prior CT establishes that the enhancing nodule is new. That development warrants assessment for an existing lesion even without pain or a change in calcium. Prompt specialist imaging and hepatobiliary evaluation should address the new tissue rather than repeat the old observation rationale. [1] [6]
Reasoning steps for option C
What does comparison with the earlier CT establish about the 14-mm nodule?
Comparison with the prior CT establishes that the enhancing nodule is new. [1] [6]
Why does the new enhancing tissue require assessment despite no symptoms or calcium change?
That development warrants assessment for an existing lesion even without pain or a change in calcium. [1] [6]
Which prompt evaluation addresses the nodule rather than repeating the old observation rationale?
Prompt specialist imaging and hepatobiliary evaluation should address the new tissue rather than repeat the old observation rationale. [1] [6]
D. Repeat the risk discussion after biliary symptoms establish the lesion's significance (Why this does not fit)
Symptoms can provide important evidence that a gallbladder problem needs intervention. An irregular new enhancing lesion already provides a reason for evaluation; symptoms need not appear first. Absence of symptoms does not negate a new suspicious soft-tissue finding. [1] [6]
Reasoning steps for option D
When can biliary symptoms contribute to an intervention decision?
Symptoms can provide important evidence that a gallbladder problem needs intervention. [1] [6]
Why need this new irregular enhancing lesion not wait for symptoms?
An irregular new enhancing lesion already provides a reason for evaluation; symptoms need not appear first. [1] [6]
What does absence of pain fail to exclude about new gallbladder soft tissue?
Absence of symptoms does not negate a new suspicious soft-tissue finding. [1] [6]
Takeaway: New soft tissue can change management even when old calcification is stable. [1] [6]
A. About six percent of initially cancer-free patients developed cancer during each follow-up year (Why this does not fit)
An annual incidence requires new events in an initially cancer-free population during measured follow-up. The five reported cancers were already present at the initial assessment, not new events in each later year. Do not turn a prevalence at diagnosis into a recurring annual probability. [1]
Reasoning steps for option A
What numerator and time period would support an annual cancer incidence?
An annual incidence requires new events in an initially cancer-free population during measured follow-up. [1]
When were the five cancers actually identified in the confirmed cohort?
The five reported cancers were already present at the initial assessment, not new events in each later year. [1]
Why cannot the index percentage be applied anew each follow-up year?
Do not turn a prevalence at diagnosis into a recurring annual probability. [1]
B. About six percent of confirmed cases had cancer already present at the initial clinical assessment (Best answer)
The relevant fraction is five cancers divided by 90 confirmed cases, approximately 5.6%. Those cancers occurred at the index assessment, so the percentage describes concurrent disease in that cohort. The result is not a personal annual or lifetime risk estimate for a patient with a mass-free initial scan. [1]
Reasoning steps for option B
Which numerator and denominator produce approximately 6%?
The relevant fraction is five cancers divided by 90 confirmed cases, approximately 5.6%. [1]
What does cancer present at the initial CT make this percentage measure?
Those cancers occurred at the index assessment, so the percentage describes concurrent disease in that cohort. [1]
Why is that cohort fraction not this mass-free patient’s annual or lifetime risk?
The result is not a personal annual or lifetime risk estimate for a patient with a mass-free initial scan. [1]
C. About six percent of patients with a negative initial scan developed cancer during follow-up (Why this does not fit)
That statement would describe cumulative incident cancer among those initially without cancer. The cohort reported no subsequent cancers; the five cancers belonged to the initial assessment. Keep baseline disease and later incident disease in different outcome categories. [1]
Reasoning steps for option C
What would a follow-up cancer percentage among initially negative patients measure?
That statement would describe cumulative incident cancer among those initially without cancer. [1]
How many subsequent cancers were observed, and when were the five found?
The cohort reported no subsequent cancers; the five cancers belonged to the initial assessment. [1]
Why must baseline and later cancers be kept separate?
Keep baseline disease and later incident disease in different outcome categories. [1]
D. About six percent of all originally reported cases had cancer at the initial assessment (Why this does not fit)
A fraction using all original reports would use 133 as its denominator. Five divided by 133 is approximately 3.8%, whereas the approximately 6% figure uses the 90 confirmed cases. State which diagnostic population forms the denominator before communicating a percentage. [1]
Reasoning steps for option D
Which denominator would an estimate among all original reports use?
A fraction using all original reports would use 133 as its denominator. [1]
How does five divided by 133 compare with five divided by 90?
Five divided by 133 is approximately 3.8%, whereas the approximately 6% figure uses the 90 confirmed cases. [1]
Why must the denominator be specified when reporting the approximate 6%?
State which diagnostic population forms the denominator before communicating a percentage. [1]
Takeaway: The cohort's approximately 6% figure concerns concurrent cancer among confirmed cases, not annual conversion. [1]
A. About 32% of the positive CT reports were false-positive diagnostic labels on review (Best answer)
The denominator contains the 133 reports originally labeled positive for porcelain gallbladder. Forty-two false-positive labels divided by 133 reports is approximately 31.6%. This describes overcalling among positive reports, not the conventional false-positive rate among disease-free patients. [1]
Reasoning steps for option A
Which reports form the denominator for this overcalling calculation?
The denominator contains the 133 reports originally labeled positive for porcelain gallbladder. [1]
What percentage results from 42 false labels among 133 positive reports?
Forty-two false-positive labels divided by 133 reports is approximately 31.6%. [1]
Why is that fraction not the conventional false-positive rate among disease-free patients?
This describes overcalling among positive reports, not the conventional false-positive rate among disease-free patients. [1]
B. About 32% of all patients undergoing CT received a false-positive diagnosis (Why this does not fit)
The burden among all scanned patients would require the full population undergoing CT. Only reports labeled porcelain gallbladder were assembled, so the denominator is not all CT recipients. Do not generalize a selected positive-report sample to every patient tested. [1]
Reasoning steps for option B
What population would be required to estimate false diagnoses among everyone scanned?
The burden among all scanned patients would require the full population undergoing CT. [1]
Why cannot 133 positive reports represent all CT recipients?
Only reports labeled porcelain gallbladder were assembled, so the denominator is not all CT recipients. [1]
Why should this selected-report fraction not be generalized to all scanned patients?
Do not generalize a selected positive-report sample to every patient tested. [1]
C. The CT method had approximately 68% sensitivity for gallbladder wall calcification (Why this does not fit)
Sensitivity asks how many patients with the disease were detected by the test. The number of truly affected patients whose reports were negative is not available. A confirmation fraction among positive reports is not sensitivity. [1]
Reasoning steps for option C
What population and outcomes define CT sensitivity?
Sensitivity asks how many patients with the disease were detected by the test. [1]
Which missed true cases are absent from this positive-report sample?
The number of truly affected patients whose reports were negative is not available. [1]
Why cannot a positive-report confirmation fraction be called sensitivity?
A confirmation fraction among positive reports is not sensitivity. [1]
D. The CT method had approximately 68% specificity for gallbladder wall calcification (Why this does not fit)
Specificity asks how many patients without the disease were correctly reported negative. The study description supplies neither all disease-free patients nor their negative reports. Specificity cannot be calculated from the positive-report group alone. [1]
Reasoning steps for option D
Which true-negative information is needed to calculate specificity?
Specificity asks how many patients without the disease were correctly reported negative. [1]
What disease-free and negative-report counts does this sample omit?
The study description supplies neither all disease-free patients nor their negative reports. [1]
Why cannot specificity be derived from positive reports alone?
Specificity cannot be calculated from the positive-report group alone. [1]
Takeaway: A false-positive proportion among positive reports uses a different denominator from specificity. [1]
A. Confounding is unlikely because both groups were recruited from the same institution (Why this does not fit)
A common institution may reduce some differences in referral environment or local practice. The groups still differed in age and comorbidity before treatment, and strategy selection was not randomized. A shared institution does not neutralize confounding by patient selection. [4]
Reasoning steps for option A
What comparability might recruitment at one institution provide?
A common institution may reduce some differences in referral environment or local practice. [4]
Which baseline and allocation differences remain despite shared recruitment?
The groups still differed in age and comorbidity before treatment, and strategy selection was not randomized. [4]
Why does a single institution not remove treatment-selection confounding?
A shared institution does not neutralize confounding by patient selection. [4]
B. Equivalence is supported because the adverse-event difference did not reach statistical significance (Why this does not fit)
A nonsignificant test indicates that this analysis did not establish the tested difference. Small groups and limited precision do not demonstrate equivalence, which requires a suitable design and margin. Failure to establish a difference is not proof of equal safety. [4]
Reasoning steps for option B
What does p = 0.15 permit one to conclude about the observed adverse-event difference?
A nonsignificant test indicates that this analysis did not establish the tested difference. [4]
Why do small groups and no equivalence margin preclude an equivalence claim?
Small groups and limited precision do not demonstrate equivalence, which requires a suitable design and margin. [4]
Why is a nonsignificant difference not proof that the strategies are equally safe?
Failure to establish a difference is not proof of equal safety. [4]
C. Generalizability is adequate because most enrolled patients were assigned to the observation group (Why this does not fit)
A larger observed group can provide useful descriptive experience with selected observation. The selection of older, more comorbid patients still limits extension to all patients and risk patterns. The proportion receiving a strategy does not establish that it suits every patient. [4]
Reasoning steps for option C
What descriptive information can the larger observation group provide?
A larger observed group can provide useful descriptive experience with selected observation. [4]
Why do age and comorbidity differences limit extrapolation to everyone?
The selection of older, more comorbid patients still limits extension to all patients and risk patterns. [4]
Why does the majority receiving observation not make it suitable for all?
The proportion receiving a strategy does not establish that it suits every patient. [4]
D. Causal comparison is limited because the groups differed before their treatment was selected (Best answer)
Older age and greater comorbidity show that baseline risks differed between groups. Nonrandom selection and a nonsignificant result in a small cohort prevent a definitive causal safety comparison. The study supports considering observation in selected patients, not an all-patient rule or a claim of equivalence. [4]
Reasoning steps for option D
Which baseline characteristics differed between the treatment groups?
Older age and greater comorbidity show that baseline risks differed between groups. [4]
Why do nonrandom treatment selection and limited precision constrain causal comparison?
Nonrandom selection and a nonsignificant result in a small cohort prevent a definitive causal safety comparison. [4]
How can these data inform selected observation without proving universal superiority or equivalence?
The study supports considering observation in selected patients, not an all-patient rule or a claim of equivalence. [4]
A. The initial cancer cases should be counted again as events in the follow-up population (Why this does not fit)
Baseline cancers belong in an assessment of cancer already present at diagnosis. Counting them again as new cancers would mix prevalent and incident disease and misrepresent the follow-up result. Uncertainty about future risk is not a reason to reclassify baseline events. [1] [4]
Reasoning steps for option A
Where should cancers already present at initial assessment be counted?
Baseline cancers belong in an assessment of cancer already present at diagnosis. [1] [4]
Why would recounting baseline cancers as follow-up events distort the result?
Counting them again as new cancers would mix prevalent and incident disease and misrepresent the follow-up result. [1] [4]
Why does uncertainty about future cancer not justify changing event timing?
Uncertainty about future risk is not a reason to reclassify baseline events. [1] [4]
B. The zero-event result is invalid because the patients were not randomized to surgery (Why this does not fit)
Randomization would help compare the effects of alternative treatment strategies. Its absence does not invalidate a descriptive observation that no new cancers were recorded during the available follow-up. Distinguish limited evidence from evidence with no descriptive value. [1] [4]
Reasoning steps for option B
What question would randomization help answer in a treatment study?
Randomization would help compare the effects of alternative treatment strategies. [1] [4]
Why can nonrandom follow-up still describe zero observed new cancers?
Its absence does not invalidate a descriptive observation that no new cancers were recorded during the available follow-up. [1] [4]
How is limited descriptive evidence different from a wholly invalid observation?
Distinguish limited evidence from evidence with no descriptive value. [1] [4]
C. Limited observation and competing deaths restrict what zero recorded events can establish (Best answer)
Zero recorded events describes what happened during finite, variable periods of follow-up. Small numbers and deaths from other causes limit the opportunity to observe a later cancer and prevent a lifetime guarantee. Use the finding as reassurance within a documented follow-up decision, not proof of biological impossibility. [1] [4]
Reasoning steps for option C
What exactly does zero observed cancers describe over variable follow-up?
Zero recorded events describes what happened during finite, variable periods of follow-up. [1] [4]
How do limited numbers and competing deaths undermine a lifetime zero-risk claim?
Small numbers and deaths from other causes limit the opportunity to observe a later cancer and prevent a lifetime guarantee. [1] [4]
How should this reassuring observation inform a documented reassessment plan?
Use the finding as reassurance within a documented follow-up decision, not proof of biological impossibility. [1] [4]
D. The mean follow-up converts the baseline prevalence into an annual incidence estimate (Why this does not fit)
Annual incidence requires incident events related to person-time or a defined follow-up interval. Dividing a baseline prevalence by the mean follow-up would not create a valid incidence measure. Timing and population definitions must match before a risk estimate is calculated. [1] [4]
Reasoning steps for option D
What event and time data are required for annual incidence?
Annual incidence requires incident events related to person-time or a defined follow-up interval. [1] [4]
Why cannot dividing baseline prevalence by mean follow-up yield incidence?
Dividing a baseline prevalence by the mean follow-up would not create a valid incidence measure. [1] [4]
What timing distinction must be preserved when communicating future risk?
Timing and population definitions must match before a risk estimate is calculated. [1] [4]
Takeaway: A zero-event cohort can be reassuring without proving zero lifetime risk. [1] [4]
A. The symptoms have an established esophageal source rather than a typical biliary pattern (Best answer)
The location, recumbent association, endoscopic finding, and treatment response converge on an esophageal explanation. The calcified wall may be incidental rather than the cause of the symptoms attributed to it. Evaluate any preventive gallbladder decision separately instead of promising that cholecystectomy will relieve esophageal burning. [1] [3] [5]
Reasoning steps for option A
How do recumbent retrosternal burning, esophagitis, and acid-suppression response localize his symptoms?
The location, recumbent association, endoscopic finding, and treatment response converge on an esophageal explanation. [1] [3] [5]
Why might homogeneous gallbladder wall calcium be incidental to this burning?
The calcified wall may be incidental rather than the cause of the symptoms attributed to it. [1] [3] [5]
How should the esophageal diagnosis affect promises of symptom relief from cholecystectomy?
Evaluate any preventive gallbladder decision separately instead of promising that cholecystectomy will relieve esophageal burning. [1] [3] [5]
B. The calcified wall explains postprandial symptoms regardless of their site or treatment response (Why this does not fit)
Biliary pain may occur after meals, making the timing superficially compatible. The retrosternal pattern, demonstrated esophagitis, and resolution with acid suppression provide a more coherent explanation. Meal association alone does not localize symptoms to the gallbladder. [1] [3] [5]
Reasoning steps for option B
Why can postprandial timing initially suggest biliary pain?
Biliary pain may occur after meals, making the timing superficially compatible. [1] [3] [5]
Why do the location, endoscopy, and acid-suppression response outweigh meal timing?
The retrosternal pattern, demonstrated esophagitis, and resolution with acid suppression provide a more coherent explanation. [1] [3] [5]
Why is eating before pain insufficient to attribute this burning to mural calcium?
Meal association alone does not localize symptoms to the gallbladder. [1] [3] [5]
C. The esophageal findings lower the need to assess any new abnormal gallbladder soft tissue (Why this does not fit)
A demonstrated alternative cause can explain the patient's current discomfort. It would not make a future new mass or invasive finding unimportant; different conditions can coexist. Correct symptom attribution does not cancel independent imaging abnormalities. [1] [3] [5]
Reasoning steps for option C
What does documented esophagitis explain about his current discomfort?
A demonstrated alternative cause can explain the patient's current discomfort. [1] [3] [5]
Would an esophageal cause make a newly detected gallbladder mass or invasion harmless?
It would not make a future new mass or invasive finding unimportant; different conditions can coexist. [1] [3] [5]
Why must new gallbladder soft tissue be assessed independently of symptom attribution?
Correct symptom attribution does not cancel independent imaging abnormalities. [1] [3] [5]
D. The absence of luminal stones makes the confirmed mural calcification diagnosis unreliable (Why this does not fit)
Stones commonly coexist with a chronically injured calcified gallbladder. The CT directly demonstrates mural calcium; the absence of stones today does not contradict that localization. Association with stones is not a requirement for proving calcium in the wall. [1] [3] [5]
Reasoning steps for option D
Why might stones be expected alongside chronic calcified gallbladder disease?
Stones commonly coexist with a chronically injured calcified gallbladder. [1] [3] [5]
How does CT establish mural calcium even though no luminal stones are seen?
The CT directly demonstrates mural calcium; the absence of stones today does not contradict that localization. [1] [3] [5]
Are stones necessary to confirm that calcium is in the gallbladder wall?
Association with stones is not a requirement for proving calcium in the wall. [1] [3] [5]
Takeaway: Treating an incidental image finding does not necessarily treat the patient's symptoms. [1] [3] [5]
A. Choose elective cholecystectomy based on the outside CT report (Why this does not fit)
A confirmed mural diagnosis can contribute to an elective surgery discussion. The outside report explicitly leaves wall calcification and packed stones unresolved, and the images are not yet available. Operative suitability does not make an uncertain anatomic label sufficient for preventive surgery. [1] [3]
Reasoning steps for option A
When could confirmed mural calcification justify an elective surgery discussion?
A confirmed mural diagnosis can contribute to an elective surgery discussion. [1] [3]
What unresolved wall-versus-lumen distinction remains in the unavailable outside CT report?
The outside report explicitly leaves wall calcification and packed stones unresolved, and the images are not yet available. [1] [3]
Why does being fit for surgery not justify operating on this equivocal report?
Operative suitability does not make an uncertain anatomic label sufficient for preventive surgery. [1] [3]
B. Choose observation because the current ultrasound did not show calcification (Why this does not fit)
A well-visualized noncalcified wall could help refute the outside label. This ultrasound did not adequately visualize the gallbladder, so nonvisualization is not a reliable negative result. A technically limited test should not be interpreted as exclusion. [1] [3]
Reasoning steps for option B
What would an adequately visualized noncalcified wall contribute to the diagnosis?
A well-visualized noncalcified wall could help refute the outside label. [1] [3]
Why does bowel-gas-limited nonvisualization fail to exclude mural calcium?
This ultrasound did not adequately visualize the gallbladder, so nonvisualization is not a reliable negative result. [1] [3]
How should a nondiagnostic ultrasound affect the decision to observe?
A technically limited test should not be interpreted as exclusion. [1] [3]
C. Choose an oncologic pathway because CT is more sensitive than ultrasound (Why this does not fit)
CT can depict calcium well and may show suspicious tissue missed on a limited examination. Greater calcium sensitivity does not establish whether these particular densities are in the wall or lumen, and no mass is described. Test capability does not resolve uncertainty in an unavailable, equivocal examination. [1] [3]
Reasoning steps for option C
What can CT potentially show that a bowel-gas-limited ultrasound misses?
CT can depict calcium well and may show suspicious tissue missed on a limited examination. [1] [3]
Why do CT sensitivity and an equivocal report not establish cancer or mural origin here?
Greater calcium sensitivity does not establish whether these particular densities are in the wall or lumen, and no mass is described. [1] [3]
Why can the capability of CT not substitute for review of the unavailable images?
Test capability does not resolve uncertainty in an unavailable, equivocal examination. [1] [3]
D. Clarify the anatomy before choosing a porcelain-specific management pathway (Best answer)
The CT report is equivocal and the follow-up ultrasound is nondiagnostic. Obtain review of the original images and appropriate targeted imaging if needed to establish wall versus lumen. Only then combine the verified finding with symptoms, pattern, operative risk, and preferences. [1] [3]
Reasoning steps for option D
Why do the equivocal outside report and limited local ultrasound leave anatomy unresolved?
The CT report is equivocal and the follow-up ultrasound is nondiagnostic. [1] [3]
What review or targeted imaging can distinguish calcium in the wall from packed stones?
Obtain review of the original images and appropriate targeted imaging if needed to establish wall versus lumen. [1] [3]
Which clinical and operative factors become relevant once wall versus lumen is verified?
Only then combine the verified finding with symptoms, pattern, operative risk, and preferences. [1] [3]
Takeaway: Uncertain localization calls for clarification, not an automatic operation or a falsely reassuring negative test. [1] [3]
A. Avoid surgical referral because the porcelain diagnosis was disproved (Why this does not fit)
Correcting a porcelain label eliminates that specific rationale for preventive treatment. She still has recurrent typical biliary episodes with documented stones. Refuting one indication does not erase a separate symptom-based indication. [1] [3] [5]
Reasoning steps for option A
What porcelain-specific reason for preventive surgery disappears after image review?
Correcting a porcelain label eliminates that specific rationale for preventive treatment. [1] [3] [5]
Why do recurrent one-to-two-hour biliary episodes and confirmed stones still justify referral?
She still has recurrent typical biliary episodes with documented stones. [1] [3] [5]
Why should disproving porcelain not erase the symptomatic gallstone indication?
Refuting one indication does not erase a separate symptom-based indication. [1] [3] [5]
B. Perform oncologic staging because calcified stones imply a mural tumor (Why this does not fit)
Gallstones can coexist with gallbladder carcinoma in some patients. The supplied studies show luminal stones without a mass or mural invasion. A stone association is not evidence of an existing tumor requiring staging. [1] [3] [5]
Reasoning steps for option B
Why might a history of gallstones raise awareness of gallbladder carcinoma?
Gallstones can coexist with gallbladder carcinoma in some patients. [1] [3] [5]
Which reviewed imaging findings argue against a mural tumor in this patient?
The supplied studies show luminal stones without a mass or mural invasion. [1] [3] [5]
Why does association between stones and cancer not amount to a staging diagnosis?
A stone association is not evidence of an existing tumor requiring staging. [1] [3] [5]
C. Offer surgical assessment for recurrent symptomatic gallstone disease (Best answer)
The corrected images identify stones, and the recurrent meal-related episodes fit symptomatic gallbladder disease. Those two findings support surgical assessment independently of the disproved porcelain label. Treat the clinically supported disease rather than treating or dismissing the original report wording. [1] [3] [5]
Reasoning steps for option C
How do recurrent postprandial right upper quadrant pain and the wall-echo-shadow pattern fit together?
The corrected images identify stones, and the recurrent meal-related episodes fit symptomatic gallbladder disease. [1] [3] [5]
Why is surgical assessment supported without mural calcification?
Those two findings support surgical assessment independently of the disproved porcelain label. [1] [3] [5]
Which verified disease, rather than the original report label, should guide care?
Treat the clinically supported disease rather than treating or dismissing the original report wording. [1] [3] [5]
D. Use functional gallbladder testing as the prerequisite for surgical referral (Why this does not fit)
Functional testing may address selected biliary-type symptoms when structural explanations are not established. This case already provides gallstones and a compatible recurrent symptom pattern. A functional test is not required merely because the wall itself is not calcified. [1] [3] [5]
Reasoning steps for option D
When might functional testing clarify biliary-type pain?
Functional testing may address selected biliary-type symptoms when structural explanations are not established. [1] [3] [5]
What structural explanation for her episodes is already established by CT and ultrasound?
This case already provides gallstones and a compatible recurrent symptom pattern. [1] [3] [5]
Why is a noncalcified wall not a reason to require functional testing before referral?
A functional test is not required merely because the wall itself is not calcified. [1] [3] [5]
Takeaway: A corrected porcelain label does not cancel treatment of symptomatic gallstones. [1] [3] [5]
A. Continue observation because the calcific outline remains homogeneous and stable (Why this does not fit)
Stable homogeneous calcification can support observation when the patient remains asymptomatic. Persistent pain, fever, leukocytosis, an impacted stone, and inflammatory findings establish a new acute problem. A prior preventive decision does not determine treatment of a later complication. [3] [7]
Reasoning steps for option A
Under what symptom status could stable homogeneous calcification support observation?
Stable homogeneous calcification can support observation when the patient remains asymptomatic. [3] [7]
Which new systemic and imaging findings make continued observation unsafe?
Persistent pain, fever, leukocytosis, an impacted stone, and inflammatory findings establish a new acute problem. [3] [7]
Why does the earlier preventive choice not govern this febrile episode?
A prior preventive decision does not determine treatment of a later complication. [3] [7]
B. Arrange urgent assessment and treatment of acute cholecystitis (Best answer)
The local symptoms, systemic inflammation, and gallbladder imaging findings combine to support acute cholecystitis. Urgent assessment should address supportive care, antimicrobial needs, and definitive treatment according to operative suitability. Do not delay acute care because the older calcification pattern was considered relatively reassuring. [3] [7]
Reasoning steps for option B
How do persistent right upper quadrant pain, fever, leukocytosis, and neck stone support acute cholecystitis?
The local symptoms, systemic inflammation, and gallbladder imaging findings combine to support acute cholecystitis. [3] [7]
What urgent care considerations follow from this inflammatory presentation?
Urgent assessment should address supportive care, antimicrobial needs, and definitive treatment according to operative suitability. [3] [7]
Why must acute management proceed despite the previously reassuring calcification pattern?
Do not delay acute care because the older calcification pattern was considered relatively reassuring. [3] [7]
C. Arrange cancer staging before initiating gallbladder-directed acute treatment (Why this does not fit)
An enhancing mass or invasive tissue would call for cancer-oriented assessment. The new evidence instead points to an acute inflammatory complication with a neck stone and no mass. Choose the immediate pathway from the current disease evidence, not from an association attached to calcium. [3] [7]
Reasoning steps for option C
What imaging change would favor cancer-oriented assessment instead?
An enhancing mass or invasive tissue would call for cancer-oriented assessment. [3] [7]
How do the impacted stone, pericholecystic fluid, and absent mass redirect priority?
The new evidence instead points to an acute inflammatory complication with a neck stone and no mass. [3] [7]
Why should calcium-associated cancer risk not delay treatment of demonstrated inflammation?
Choose the immediate pathway from the current disease evidence, not from an association attached to calcium. [3] [7]
D. Arrange elective outpatient surgery after completion of routine calcification surveillance (Why this does not fit)
An elective plan can fit recurrent biliary symptoms without an acute inflammatory syndrome. The current persistent febrile episode with leukocytosis and pericholecystic fluid requires timely acute assessment. A surveillance schedule must not postpone care for a new symptomatic complication. [3] [7]
Reasoning steps for option D
When would outpatient elective surgery be reasonable for biliary symptoms?
An elective plan can fit recurrent biliary symptoms without an acute inflammatory syndrome. [3] [7]
Why do fever, leukocytosis, and pericholecystic fluid require earlier assessment?
The current persistent febrile episode with leukocytosis and pericholecystic fluid requires timely acute assessment. [3] [7]
Why cannot scheduled calcification surveillance determine the timing of acute care?
A surveillance schedule must not postpone care for a new symptomatic complication. [3] [7]
Takeaway: New inflammatory symptoms override the previous observation plan for an incidental calcified wall. [3] [7]
A. Schedule annual contrast CT as an evidence-validated standard for every observed patient (Why this does not fit)
A clinician may choose repeat imaging when it can address a particular uncertainty or change management. The available porcelain gallbladder evidence does not establish annual contrast CT as a universal validated schedule. An individualized imaging decision should not be presented as a proven all-patient protocol. [3] [4]
Reasoning steps for option A
When might repeat imaging be selected during observation?
A clinician may choose repeat imaging when it can address a particular uncertainty or change management. [3] [4]
Does evidence for porcelain gallbladder establish annual contrast CT for every patient?
The available porcelain gallbladder evidence does not establish annual contrast CT as a universal validated schedule. [3] [4]
How should a chosen scan interval be described if it is not validated universally?
An individualized imaging decision should not be presented as a proven all-patient protocol. [3] [4]
B. Schedule serial tumor markers as a validated replacement for clinical and imaging reassessment (Why this does not fit)
Tumor markers may contribute to selected specialist evaluations when there is a defined clinical question. They are not a validated replacement for reassessment of symptoms or suspicious imaging findings in this setting. A convenient measurement does not establish an effective surveillance strategy. [3] [4]
Reasoning steps for option B
When could tumor markers contribute to a specialist evaluation?
Tumor markers may contribute to selected specialist evaluations when there is a defined clinical question. [3] [4]
Why can serial markers not replace review of new symptoms or suspicious imaging?
They are not a validated replacement for reassessment of symptoms or suspicious imaging findings in this setting. [3] [4]
Why does availability of a blood test not validate it as surveillance?
A convenient measurement does not establish an effective surveillance strategy. [3] [4]
C. End clinical review after a stable scan because subsequent gallbladder complications are negligible (Why this does not fit)
A stable examination can support continued observation when no new concerns are present. Stability does not eliminate the possibility of later symptoms, infection, or an imaging change. Observation should include a way to reassess new problems rather than terminate clinical responsibility. [3] [4]
Reasoning steps for option C
What can a stable scan support in an asymptomatic observed patient?
A stable examination can support continued observation when no new concerns are present. [3] [4]
Which later complications remain possible despite stable wall calcification?
Stability does not eliminate the possibility of later symptoms, infection, or an imaging change. [3] [4]
Why must an observation plan retain a route for reassessment?
Observation should include a way to reassess new problems rather than terminate clinical responsibility. [3] [4]
D. Specify individual follow-up and return precautions because no universal schedule is validated (Best answer)
Evidence supporting observation is largely retrospective and does not supply a validated universal surveillance interval. The plan should identify a responsible clinician, individualized review, and symptoms or findings requiring earlier assessment. Do not invent a standard CT interval or substitute tumor markers for appropriate clinical follow-up. [3] [4]
Reasoning steps for option D
Why can retrospective observation evidence not specify a universal surveillance interval?
Evidence supporting observation is largely retrospective and does not supply a validated universal surveillance interval. [3] [4]
What responsible clinician, review, and return precautions belong in her written plan?
The plan should identify a responsible clinician, individualized review, and symptoms or findings requiring earlier assessment. [3] [4]
Why should neither fixed annual CT nor tumor markers be claimed as established surveillance?
Do not invent a standard CT interval or substitute tumor markers for appropriate clinical follow-up. [3] [4]
Takeaway: Individualize observation and specify return precautions; no universal porcelain surveillance interval is validated. [3] [4]
A. Plan laparoscopic surgery with an experienced team and a safe bailout strategy (Best answer)
There is a symptom-based indication without imaging evidence requiring an oncologic operation. A laparoscopic approach can be feasible, but fibrosis and a brittle wall require preparation for difficult anatomy and safe alternatives. Operative safety depends on establishing anatomy and adapting the procedure, not treating calcification as an absolute laparoscopic prohibition. [3] [5] [7]
Reasoning steps for option A
What establishes surgery for recurrent pain without a visible tumor?
There is a symptom-based indication without imaging evidence requiring an oncologic operation. [3] [5] [7]
How do a brittle wall and fibrosis change preparation for laparoscopy?
A laparoscopic approach can be feasible, but fibrosis and a brittle wall require preparation for difficult anatomy and safe alternatives. [3] [5] [7]
Why should identification of anatomy and a bailout option matter more than an absolute laparoscopy ban?
Operative safety depends on establishing anatomy and adapting the procedure, not treating calcification as an absolute laparoscopic prohibition. [3] [5] [7]
B. Plan formal liver-bed resection because wall calcification establishes invasive gallbladder cancer (Why this does not fit)
Liver-bed resection may form part of treatment for selected invasive gallbladder cancers. No mass or invasion is demonstrated, and calcium alone does not establish carcinoma. Do not convert a benign-appearing symptomatic indication into an oncologic resection solely from calcium. [3] [5] [7]
Reasoning steps for option B
When might liver-bed resection be appropriate in gallbladder cancer?
Liver-bed resection may form part of treatment for selected invasive gallbladder cancers. [3] [5] [7]
What is missing from CT to diagnose invasive cancer in this calcified wall?
No mass or invasion is demonstrated, and calcium alone does not establish carcinoma. [3] [5] [7]
Why should calcium alone not trigger an oncologic resection?
Do not convert a benign-appearing symptomatic indication into an oncologic resection solely from calcium. [3] [5] [7]
C. Plan routine percutaneous drainage because a brittle wall precludes an elective surgical approach (Why this does not fit)
Drainage can address selected acute infections when surgery is unsuitable. He has recurrent biliary pain without an acute infected presentation and is an acceptable operative candidate. Technical difficulty requires planning; it does not by itself create an indication for drainage. [3] [5] [7]
Reasoning steps for option C
When is gallbladder drainage a reasonable alternative?
Drainage can address selected acute infections when surgery is unsuitable. [3] [5] [7]
Why do elective symptoms and acceptable operative fitness argue against routine drainage?
He has recurrent biliary pain without an acute infected presentation and is an acceptable operative candidate. [3] [5] [7]
How should anticipated brittle anatomy affect surgical planning rather than indication for drainage?
Technical difficulty requires planning; it does not by itself create an indication for drainage. [3] [5] [7]
D. Plan preoperative duct clearance because wall calcium predicts retained common bile duct stones (Why this does not fit)
Documented or strongly suspected common duct stones can warrant duct clearance. The common duct has no identified stone and bilirubin is normal; wall calcification is not proof of duct contents. Gallbladder wall disease and common duct obstruction must be assessed separately. [3] [5] [7]
Reasoning steps for option D
What evidence would justify clearing a common duct stone before surgery?
Documented or strongly suspected common duct stones can warrant duct clearance. [3] [5] [7]
How do normal bilirubin and no duct stone undermine presumptive duct clearance?
The common duct has no identified stone and bilirubin is normal; wall calcification is not proof of duct contents. [3] [5] [7]
Why does gallbladder wall calcium say nothing definitive about common duct contents?
Gallbladder wall disease and common duct obstruction must be assessed separately. [3] [5] [7]
Takeaway: A laparoscopic approach may be appropriate, with preparation for difficult anatomy and safe alternatives. [3] [5] [7]
A. Proceed with preventive surgery because the selective pattern outweighs operative comorbidity (Why this does not fit)
Selective-appearing calcification can strengthen the rationale for discussing preventive surgery. It does not establish that an uncertain preventive benefit exceeds her specifically documented high operative risk. A pattern-associated risk is one input to the decision, not an overriding instruction. [2] [3] [4]
Reasoning steps for option A
Why does patchy selective-appearing calcification merit a preventive surgery discussion?
Selective-appearing calcification can strengthen the rationale for discussing preventive surgery. [2] [3] [4]
How does decompensated cirrhosis with refractory ascites change the benefit-harm balance?
It does not establish that an uncertain preventive benefit exceeds her specifically documented high operative risk. [2] [3] [4]
Why is selective calcification not an absolute mandate for surgery?
A pattern-associated risk is one input to the decision, not an overriding instruction. [2] [3] [4]
B. Defer preventive surgery and arrange individualized clinical follow-up (Best answer)
The patient has no symptoms or suspicious mass, while the operative risk is substantial. Her preference and the unfavorable current balance support observation despite the selective-appearing pattern. Reassess if symptoms, imaging, health status, or preferences change rather than treating the pattern as an absolute mandate. [2] [3] [4]
Reasoning steps for option B
Which absence of symptoms or mass and which operative hazard favor observation?
The patient has no symptoms or suspicious mass, while the operative risk is substantial. [2] [3] [4]
How do her preferences and uncertain benefit support deferring elective surgery?
Her preference and the unfavorable current balance support observation despite the selective-appearing pattern. [2] [3] [4]
What changes in symptoms, imaging, health, or preferences would warrant reassessment?
Reassess if symptoms, imaging, health status, or preferences change rather than treating the pattern as an absolute mandate. [2] [3] [4]
C. Obtain routine wall sampling before acknowledging the option of nonoperative care (Why this does not fit)
Histology can answer microscopic questions when tissue is obtained for a clinical indication. There is no target mass, and tissue sampling is not a necessary condition for a shared risk-benefit decision. Avoid an invasive procedure solely to replace uncertainty that can be discussed explicitly. [2] [3] [4]
Reasoning steps for option C
When can histology answer a clinically indicated tissue question?
Histology can answer microscopic questions when tissue is obtained for a clinical indication. [2] [3] [4]
Why is routine sampling unjustified without a mass or required diagnostic target?
There is no target mass, and tissue sampling is not a necessary condition for a shared risk-benefit decision. [2] [3] [4]
Why can shared decision-making address uncertainty without invasive sampling?
Avoid an invasive procedure solely to replace uncertainty that can be discussed explicitly. [2] [3] [4]
D. Start oncologic staging because selective calcification establishes occult invasive carcinoma (Why this does not fit)
A suspicious mass or demonstrated invasive carcinoma would warrant staging. The selective-appearing pattern alone does not establish invasive cancer, and imaging shows no mass or invasion. An association should not be rewritten as a confirmed malignancy. [2] [3] [4]
Reasoning steps for option D
What evidence would warrant staging for invasive gallbladder carcinoma?
A suspicious mass or demonstrated invasive carcinoma would warrant staging. [2] [3] [4]
Why do patchy calcium and mass-free imaging not establish occult invasion?
The selective-appearing pattern alone does not establish invasive cancer, and imaging shows no mass or invasion. [2] [3] [4]
How should cancer association be distinguished from a confirmed malignancy?
An association should not be rewritten as a confirmed malignancy. [2] [3] [4]
Takeaway: No calcification pattern automatically overrides serious operative harm and informed preferences. [2] [3] [4]
A. Continue observation because the cystic duct resection margin is negative (Why this does not fit)
A negative margin is useful information about the tissue at that particular resection edge. It does not establish that an invasive tumor extending beyond muscle has been fully staged or that no additional oncologic treatment is needed. A margin result and the depth of invasion answer different questions. [6]
Reasoning steps for option A
What does the negative cystic duct margin actually establish?
A negative margin is useful information about the tissue at that particular resection edge. [6]
Why does perimuscular invasion still require staging despite that margin?
It does not establish that an invasive tumor extending beyond muscle has been fully staged or that no additional oncologic treatment is needed. [6]
How do margin status and tumor depth answer different oncologic questions?
A margin result and the depth of invasion answer different questions. [6]
B. Obtain serial ultrasound without staging because CT showed no focal mass (Why this does not fit)
Preoperative absence of a visible mass can make an incidental tumor unexpected. Definitive pathology now demonstrates invasion, which supersedes the prior mass-free imaging impression. Do not allow a negative earlier image to cancel a positive tissue diagnosis. [6]
Reasoning steps for option B
Why might invasive carcinoma be an unexpected postoperative finding after the mass-free CT?
Preoperative absence of a visible mass can make an incidental tumor unexpected. [6]
Which postoperative tissue finding overrides the earlier negative CT impression?
Definitive pathology now demonstrates invasion, which supersedes the prior mass-free imaging impression. [6]
Why must pathology, rather than a prior mass-free scan, guide staging?
Do not allow a negative earlier image to cancel a positive tissue diagnosis. [6]
C. Refer for staging and assessment of additional oncologic treatment (Best answer)
The tumor extends beyond muscle into perimuscular tissue, so it is not merely an incidental mucosal abnormality. Specialist staging and assessment of additional resection or other treatment are needed despite the negative cystic duct margin. Use the actual invasive pathology to plan care rather than continue a porcelain-only follow-up pathway. [6]
Reasoning steps for option C
What does extension beyond muscle into perimuscular tissue establish?
The tumor extends beyond muscle into perimuscular tissue, so it is not merely an incidental mucosal abnormality. [6]
Why consider further staging and treatment despite a negative cystic duct margin?
Specialist staging and assessment of additional resection or other treatment are needed despite the negative cystic duct margin. [6]
Why should invasive pathology replace a porcelain-only follow-up pathway?
Use the actual invasive pathology to plan care rather than continue a porcelain-only follow-up pathway. [6]
D. Treat with radiation alone because the primary gallbladder has been excised (Why this does not fit)
Radiation may have a role in selected cancer treatment plans. Choosing it as the sole next treatment skips staging and assessment of potentially indicated additional surgery. Treatment of incidental invasive cancer should follow a specialist stage-directed plan. [6]
Reasoning steps for option D
When might radiation contribute to a gallbladder cancer treatment plan?
Radiation may have a role in selected cancer treatment plans. [6]
What staging and surgical assessment would radiation alone prematurely bypass?
Choosing it as the sole next treatment skips staging and assessment of potentially indicated additional surgery. [6]
Why should treatment after incidental invasive pathology be stage-directed?
Treatment of incidental invasive cancer should follow a specialist stage-directed plan. [6]
Takeaway: Unexpected invasive cancer requires stage-directed specialist assessment, not calcification-only observation. [6]
A. Offer preventive surgery for confirmed gallbladder wall calcification (Why this does not fit)
Preventive surgery may be discussed when a true mural gallbladder finding and the patient's risk-benefit balance support it. The cross-sectional images localize the rim to a renal structure, not to the separately visible gallbladder wall. A projected right upper quadrant density does not establish gallbladder origin. [3]
Reasoning steps for option A
When might true gallbladder mural calcification merit preventive discussion?
Preventive surgery may be discussed when a true mural gallbladder finding and the patient's risk-benefit balance support it. [3]
Where does coronal CT place the rim relative to the separately seen gallbladder?
The cross-sectional images localize the rim to a renal structure, not to the separately visible gallbladder wall. [3]
Why cannot a right upper quadrant radiographic projection prove gallbladder origin?
A projected right upper quadrant density does not establish gallbladder origin. [3]
B. Use functional gallbladder testing to determine the anatomic source of calcium (Why this does not fit)
Functional gallbladder testing can address selected questions about emptying or cystic duct function. CT has already shown where the calcified structure is located; a functional test would not change that localization. Choose a test that addresses the unresolved question rather than a nearby organ. [3]
Reasoning steps for option B
What clinical question can functional gallbladder testing answer?
Functional gallbladder testing can address selected questions about emptying or cystic duct function. [3]
Why is emptying testing unnecessary after CT localizes calcium to a renal structure?
CT has already shown where the calcified structure is located; a functional test would not change that localization. [3]
Why must testing address organ localization rather than gallbladder function here?
Choose a test that addresses the unresolved question rather than a nearby organ. [3]
C. Reassign the finding to its renal origin before planning further care (Best answer)
The calcified rim is continuous with the renal cortex while the gallbladder is separately identified. The renal-origin finding should be characterized in its own context rather than prompting porcelain-specific treatment. Correct organ localization before assigning malignancy associations or selecting an operation. [3]
Reasoning steps for option C
What CT continuity establishes the renal origin of the calcified rim?
The calcified rim is continuous with the renal cortex while the gallbladder is separately identified. [3]
Why should this renal finding be characterized outside a porcelain pathway?
The renal-origin finding should be characterized in its own context rather than prompting porcelain-specific treatment. [3]
Why must organ localization precede assigning gallbladder cancer risk or surgery?
Correct organ localization before assigning malignancy associations or selecting an operation. [3]
D. Stage presumed gallbladder malignancy because calcification is close to the liver (Why this does not fit)
A mass arising from the gallbladder with invasive features can warrant staging. Proximity on a radiograph is contradicted by the CT localization, and no gallbladder mass is shown. Anatomic proximity is not evidence of origin or invasion. [3]
Reasoning steps for option D
What gallbladder finding would justify malignancy staging?
A mass arising from the gallbladder with invasive features can warrant staging. [3]
How does CT contradict a gallbladder origin inferred from proximity to the liver?
Proximity on a radiograph is contradicted by the CT localization, and no gallbladder mass is shown. [3]
Why does nearby calcification not establish gallbladder invasion?
Anatomic proximity is not evidence of origin or invasion. [3]
Takeaway: A right upper quadrant calcification may belong to a neighboring organ rather than the gallbladder. [3]