
GI
Small-Bowel Obstruction
Locate a small-bowel blockage, assess blood supply, replace losses, and choose monitored observation, contrast assessment or surgery with a clear exit plan.
A swollen bowel can be blocked, poorly perfused, or both. Start with two questions. Where does forward passage stop? Is the trapped bowel still getting blood? Finding the blockage does not answer the second question. As you work through the examples, keep the location and the blood supply separate.
Blocked passage or slowed propulsion?
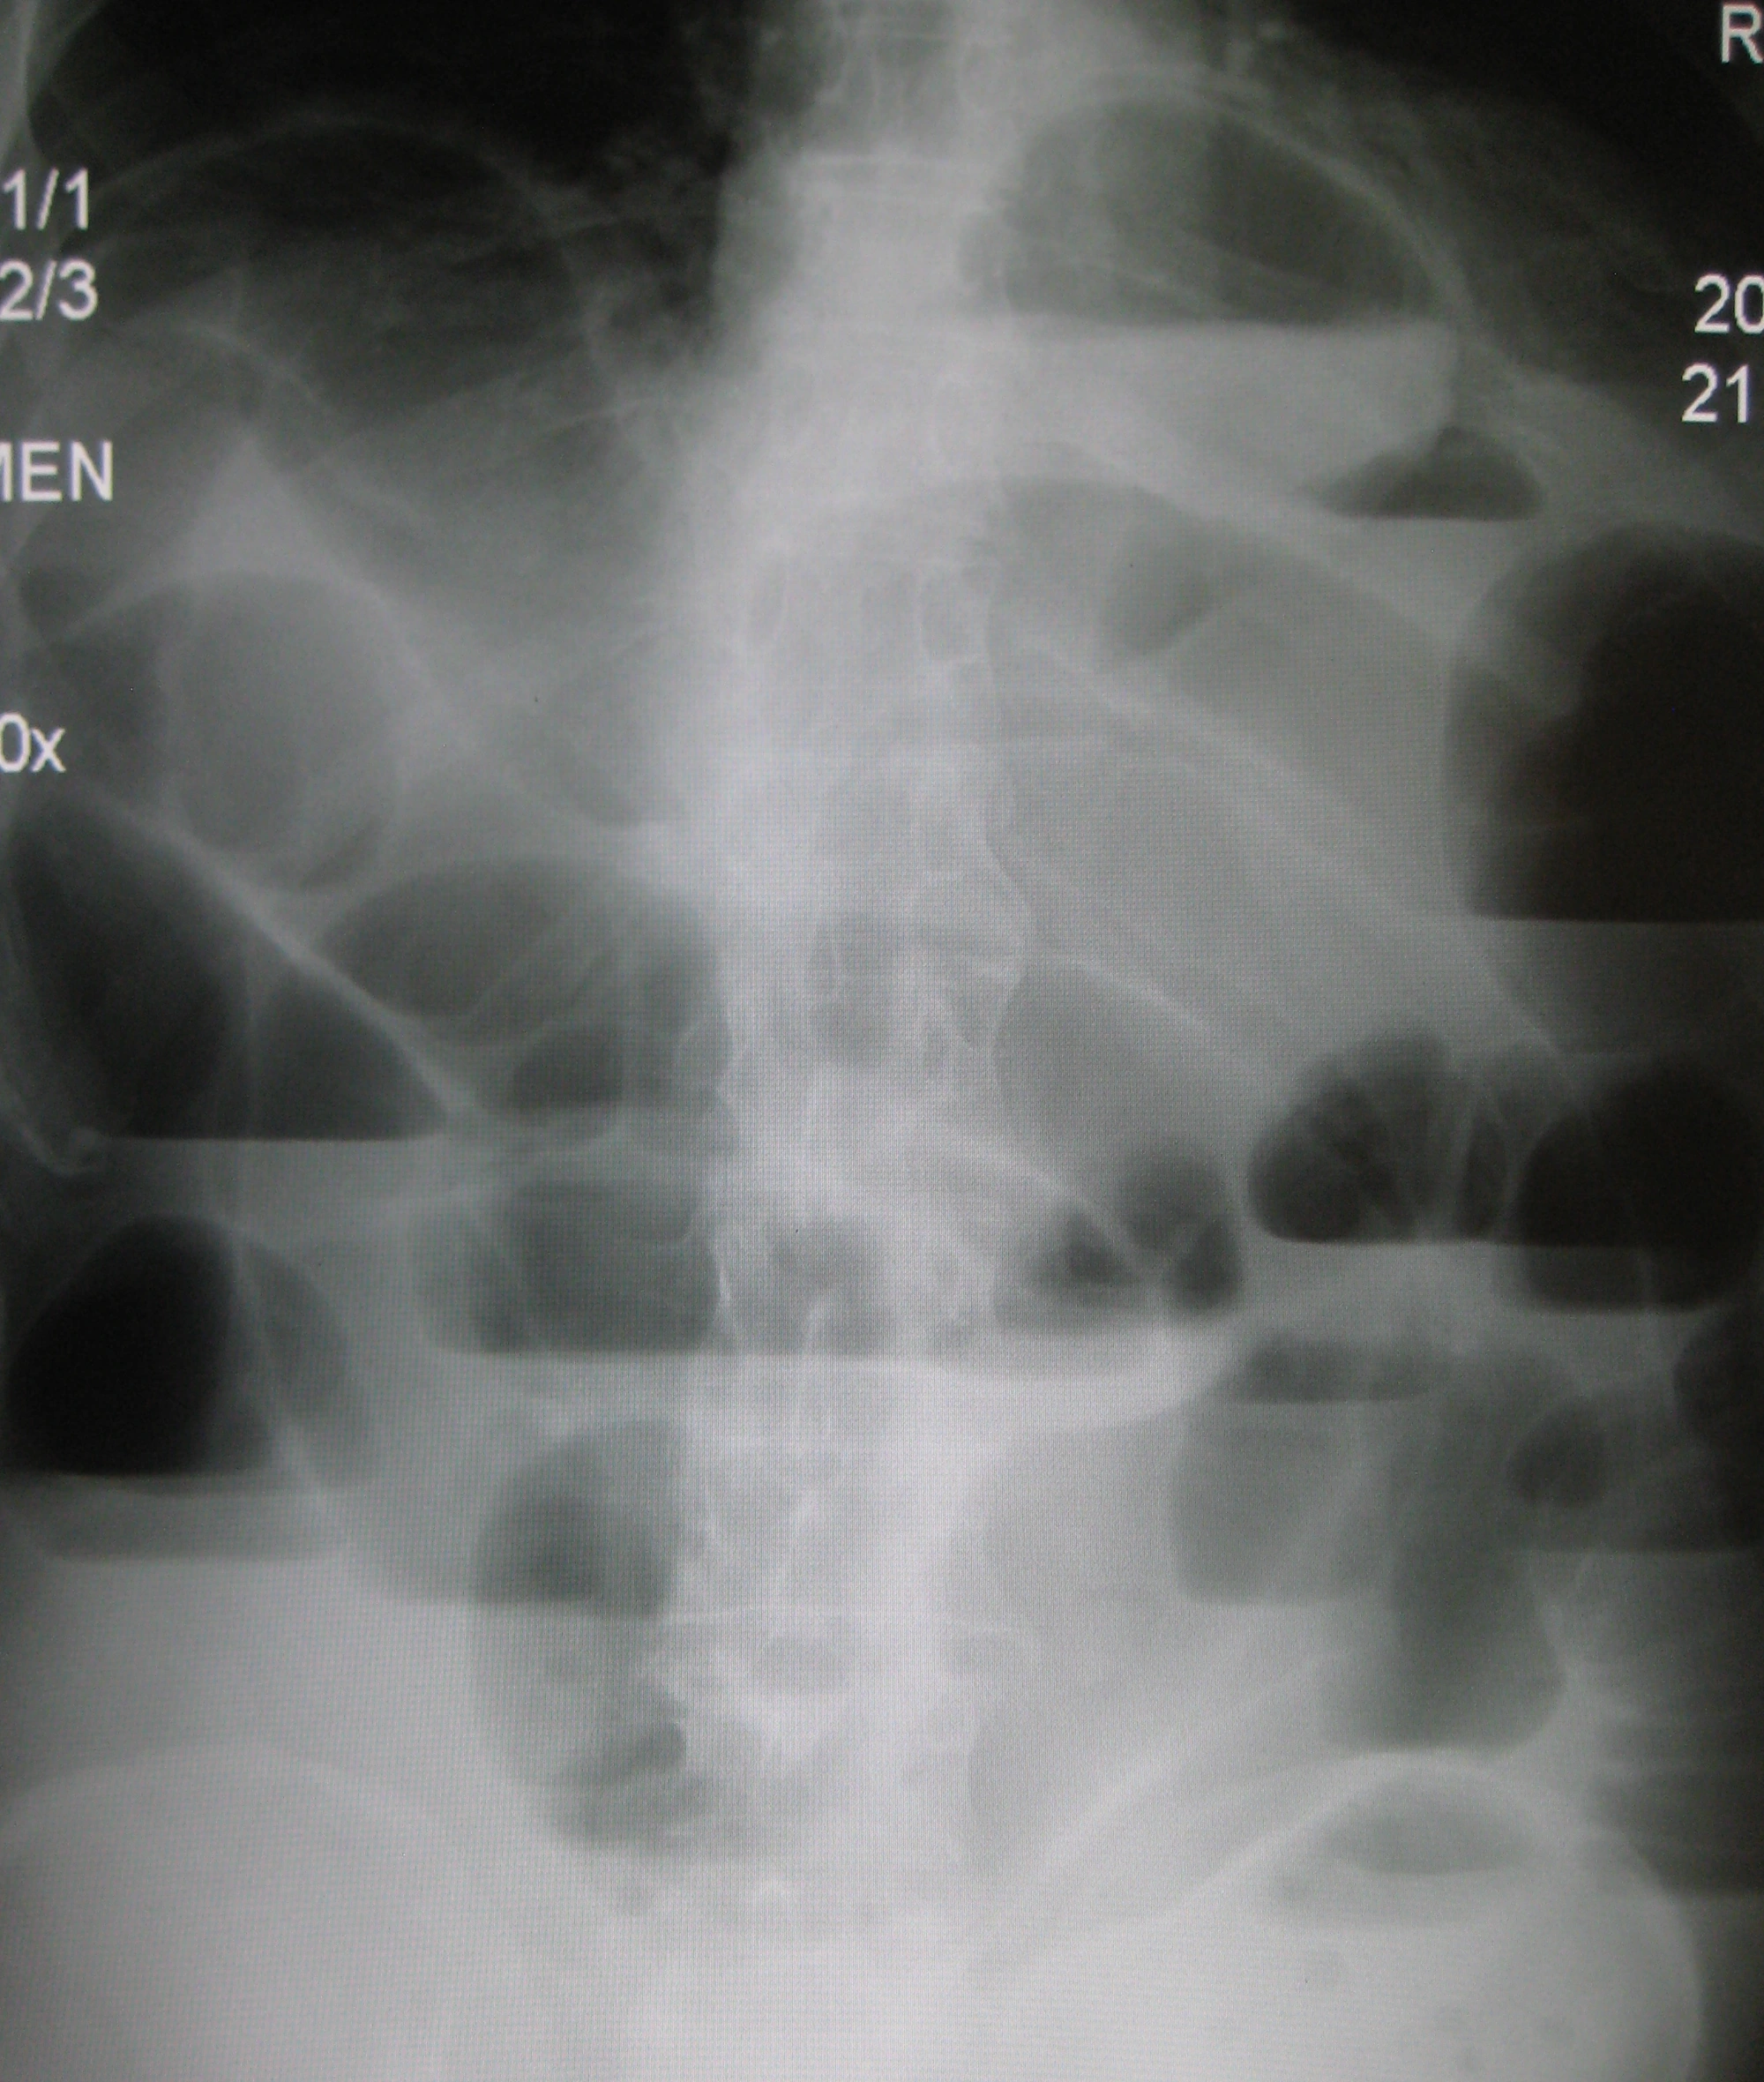
In mechanical small-bowel obstruction, a physical barrier interrupts forward passage. Bowel above the barrier fills with gas and secretions. Bowel beyond it often becomes less distended. The change between those segments is the transition point. Imagine traffic backing up before a closed lane while the road beyond it empties. The comparison explains distribution, not whether the bowel is safe to observe. [1] [2]
 Enlarge the whole image
Notice the different horizontal air-fluid levels. This real radiograph illustrates obstruction; it does not by itself determine the cause or bowel viability.
James Heilman, MD. CC BY-SA 3.0. Source and provenance

Read the pattern, not one symptom
Cramping pain, vomiting, distention, and reduced stool or flatus fit obstruction, but not every finding must be present. Passing stool does not exclude an early or partial obstruction. Contents already downstream can still leave, and an incomplete obstruction can sometimes produce watery diarrhea. An older patient may have less striking pain than expected. [1]
Ileus means impaired propulsion rather than a focal barrier. Dilation can involve small bowel and colon without a convincing transition. Early or partial obstruction can overlap with that appearance, so interpretation still needs the history, examination, and imaging. Neither quiet nor high-pitched bowel sounds can safely settle the distinction alone. [1] [4]
Mechanical obstruction
Look for proximal dilation, an anatomical transition, and relatively decompressed distal bowel. [2]
Generalized ileus
Look for a broader motility problem and its trigger rather than assuming that every dilated loop is blocked. [4]
Remember the contrast. A transition localizes a barrier. Dilation alone does not. [2]
Use the history to investigate the barrier
Adhesions are fibrous attachments between surfaces that normally remain separate. After abdominal or pelvic surgery, an adhesive band can kink or trap bowel. The operation need not be recent. A patient can develop adhesive obstruction years later. On CT, adhesions are often inferred from the transition and exclusion of another cause rather than directly seen as a clearly labeled band. [1]
No previous surgery does not mean no adhesions
A previously unoperated abdomen still needs a broad cause assessment. Hernia, tumor, inflammatory stricture, and less common intraluminal causes matter. However, congenital bands or previous inflammation can also produce adhesions. The WSES position paper does not support mandatory surgery solely because a patient has never had an operation. The examination, CT findings, and response to treatment determine the next step. [2]
Examine the groins and abdominal wall. A painful irreducible hernia with obstruction and poor bowel enhancement raises concern for strangulation. A nasogastric tube will not release a tight hernia neck. In Crohn disease, a fixed narrowed segment with upstream dilation suggests a mechanical stricture. With a mass at the transition, treatment needs a cause-specific surgical and oncologic plan rather than an assumption that all obstructions behave like adhesions. [1] [2] [5]
Previous laparotomy
Adhesions become a leading explanation, but inspect for competing causes. [1]
No previous operation
Investigate structural causes without excluding adhesions. Unexplained resolution still needs appropriate follow-up. [2]
Gallstone ileus
Despite its name, this is mechanical obstruction by an ectopic gallstone, not generalized paralytic ileus. [2]
The cause changes the plan. Decompressing bowel can relieve symptoms without removing a hernia, mass, or fixed stricture. [1]
Why a full abdomen can have an empty circulation
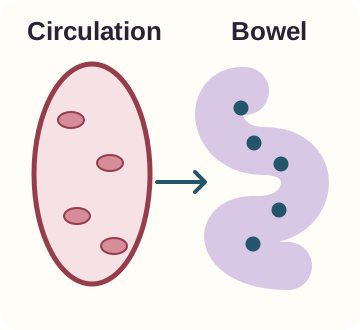
Fluid trapped inside distended bowel is not available to circulate normally. Vomiting and poor intake add further losses. The patient can therefore look markedly bloated while being intravascularly depleted. Low urine output, tachycardia, hypotension, and worsening kidney function are reasons to reassess perfusion, not reassurance that the abdomen already contains plenty of fluid. [1] [2]
 Enlarge the whole image
Fluid inside bowel is not the same compartment as circulating volume. The drawing is qualitative and has no fluid-volume scale.
Bone Wizardry. Original Bone Wizardry schematic. Source and provenance
Replace losses and check the response
Assess electrolytes, kidney function, blood count, and lactate along with the examination. Potassium depletion is common and needs correction. Vomiting or continued tube losses can keep changing the replacement requirement. Use appropriate isotonic crystalloid and reassess rather than giving a preset volume to everyone. Heart or kidney disease, frailty, and ongoing losses influence the plan. [1]
Nasogastric decompression removes accumulated upper gastrointestinal contents and can reduce vomiting and aspiration risk. It is support for the obstructed patient, not proof that the obstruction has resolved. Falling discomfort after tube placement can coexist with an unreleased barrier. Continue examining the abdomen and reviewing the clinical trajectory. [1]
- Passage is blocked. Secretions and gas accumulate above the barrier. [1]
- Usable circulating volume falls. Luminal sequestration, vomiting, and poor intake reduce effective hydration. [1]
- Organ perfusion can suffer. Follow circulation, urine output, and kidney function while replacing losses. [1]
Support is active treatment. Fluid replacement, electrolyte correction, decompression, and reassessment happen together. [1]
Find the loop that cannot safely wait
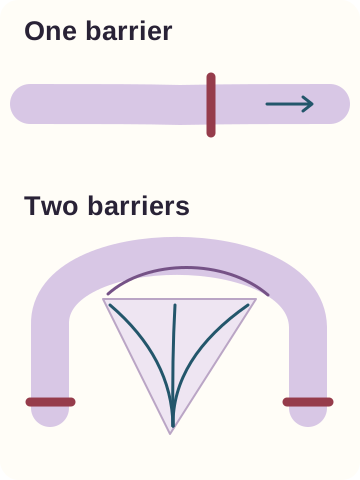
A closed-loop obstruction traps the same bowel segment at two points. Distention can compromise mesenteric venous drainage, producing congestion and edema. As pressure and vascular compromise worsen, arterial supply can fail too. Strangulation means the obstruction has compromised blood flow. These terms are related, but a closed-loop shape and established dead bowel are not identical findings. [1] [2]
 Enlarge the whole image
One transition and a loop trapped at two ends create different anatomical problems. The drawing identifies trapping, not irreversible necrosis.
Bone Wizardry. Original Bone Wizardry schematic. Source and provenance
Combine anatomy with the patient's condition
CT can show two transition points, a curved trapped loop, twisting mesentery, edema, free fluid, and reduced bowel-wall enhancement. Concern rises when these findings accompany increasing continuous pain, guarding, fever, tachycardia, acidosis, or shock. Free air suggests perforation. The purpose of imaging is not merely to confirm that the bowel is large; it is to identify the cause and whether urgent intervention is needed. [1] [2]
A normal lactate does not exclude early or localized ischemia. Neither does a relatively modest initial examination. The WSES position paper specifically cautions that normal laboratory values cannot exclude ischemia. A rising lactate strengthens concern in the right setting, but treatment should not wait for a laboratory result to become dramatic when the clinical and imaging evidence already indicates danger. [2]
Uncomplicated pattern
Stable physiology, preserved enhancement, and no peritoneal signs may support a monitored trial when the cause is appropriate. [1]
Threatened bowel
Peritonitis, vascular compromise, perforation, or deterioration requires urgent surgical assessment and treatment. [1]
Do not wait for all warning signs. One convincing ischemic or perforation pattern can change the plan before a full checklist develops. [1] [2]