Match 5-ASA delivery to UC extent, distinguish carrier effects from renal injury, and recognize when adequate treatment needs escalation.
Two patients receive medicines that deliver the same anti-inflammatory molecule. One needs better treatment of the rectum; the other needs relief from a carrier-related adverse effect. A larger oral dose is not the answer to both problems. Follow the molecule to its destination, identify what else travels with it, and then match treatment to disease activity.
One medicine becomes two molecules
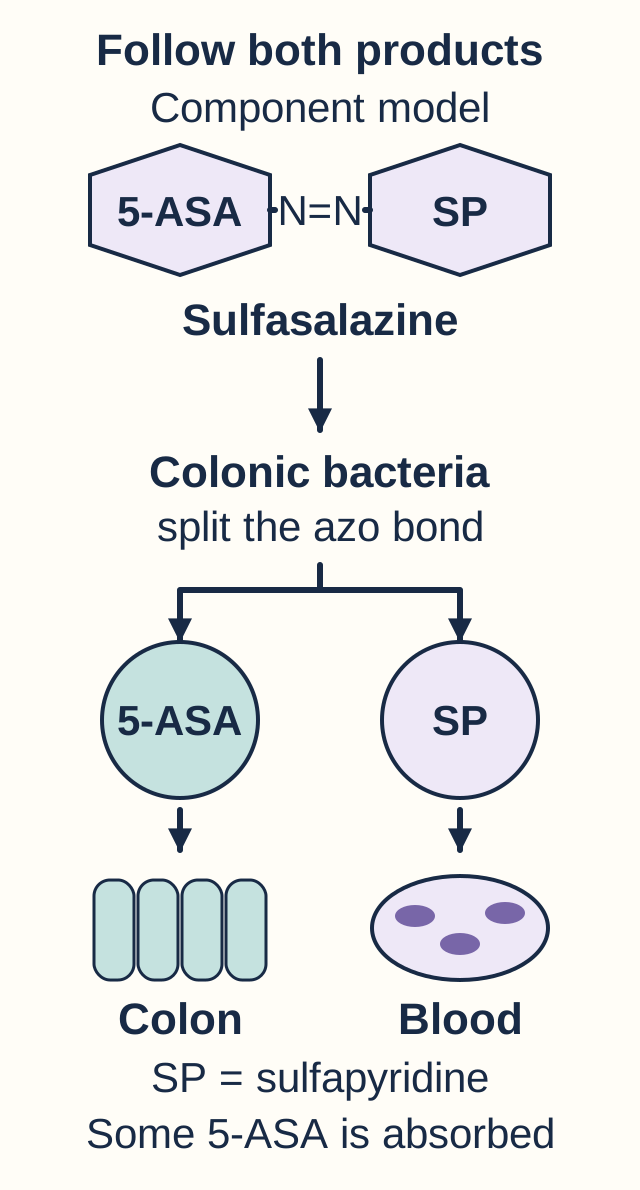
Why can sulfasalazine help the colon and affect organs elsewhere? Sulfasalazine joins 5-aminosalicylic acid, or 5-ASA, to sulfapyridine through an azo bond. Most intact sulfasalazine escapes absorption in the upper gut. Bacterial enzymes in the colon split the bond. The resulting 5-ASA supplies much of the local anti-inflammatory effect in ulcerative colitis, while sulfapyridine is readily absorbed. Mesalamine is 5-ASA without that sulfapyridine partner. [3]
In the accompanying molecular diagram, follow the solid path toward the colonic lining and the other path toward the circulation. Neither path is absolute: some mesalamine is absorbed and its metabolites are cleared through the kidneys. Local therapeutic action therefore does not mean zero systemic exposure. A patient who changes from sulfasalazine to mesalamine may avoid a carrier-related problem while still needing kidney surveillance. [3][4]
Original component model. The separated destinations emphasize predominant effects, not exclusive distribution. Read SP as sulfapyridine. [3][4][3][4]
The precise anti-inflammatory mechanism is not fully established. Proposed effects involve arachidonic-acid mediators from cyclooxygenase and lipoxygenase pathways, inflammatory signaling, and cellular immune activity. Experimental work supports a contribution from the nuclear receptor PPAR-gamma: genetically reduced receptor function weakened the response in a mouse colitis model, and epithelial-cell and human-biopsy experiments supported receptor activation. That evidence does not prove one exclusive mechanism in every treated patient. [3][4][8]
Change one component and predict what follows
Change
What changes, and what does not?
ChangeSulfasalazine to an appropriate mesalamine formulation
What changes, and what does not?Sulfapyridine exposure ends; delivery of 5-ASA can continue. Kidney risk is not abolished.
ChangeUncoated to enteric-coated sulfasalazine
What changes, and what does not?Gastric disintegration changes, but the azo bond and sulfapyridine product remain.
ChangeOral to rectal mesalamine
What changes, and what does not?The delivery route changes; the active molecule does not become a different drug class.
Trace the two products with your finger or cursor. Now consider someone with dose-related nausea on sulfasalazine but no fever, rash, organ injury, or abnormal blood count. Which part of the map could explain the symptoms?
Compare the carrier explanation
Absorbed sulfapyridine can contribute to dose-related nausea. Review dose, timing, and tolerability rather than assuming intestinal inflammation has worsened. [3][5]
Enteric coating can help selected gastric-intolerance problems, but it does not prevent systemic hypersensitivity or the formation of sulfapyridine. Slower acetylation can produce higher sulfapyridine exposure; it does not establish that every symptom is caused by the drug. For transfer, explain why a coated tablet is not a solution to a previous severe sulfasalazine reaction. [3][5]
Put the active drug where inflammation is present
Does every mesalamine tablet reach the same location? No. The formulation is part of the prescription. Azo-linked sulfasalazine uses bacterial activation; mesalamine products use delivery systems that do not require release of sulfapyridine. Some delayed-release coatings open at a specified pH, often near the terminal ileum, and a matrix then prolongs release. PENTASA uses controlled-release particles that release drug throughout the gastrointestinal tract. Drug delivery to an anatomic site is not, by itself, proof of clinical efficacy for every disease there. [3][4][6]
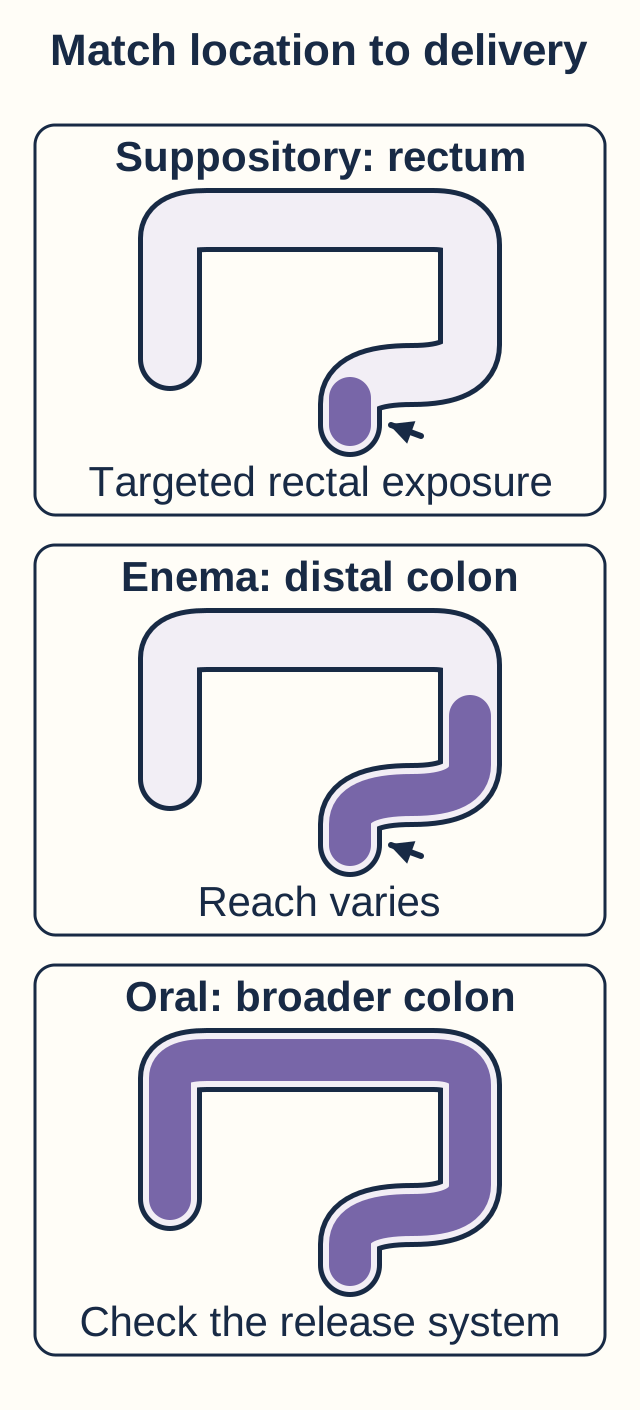
The route diagram compares three areas of contact. A suppository primarily treats the rectum. An enema reaches farther into the distal or left colon, with distribution affected by administration and retention. Oral therapy is needed to cover more extensive disease. These are practical coverage patterns, not perfectly sharp boundaries or promises that every enema reaches the same distance. [1][7]
Original anatomic coverage model. Purple segments indicate principal areas of drug contact, not an invariant boundary. Enema reach varies; oral release depends on the product. [1][4][6][7][1][4][6][7]
Match an adult patient's mild-to-moderate UC distribution to delivery
Inflammation
Usual 5-ASA approach
InflammationRectum only
Usual 5-ASA approachRectal mesalamine, commonly a 1-g daily suppository.
InflammationLeft-sided colon
Usual 5-ASA approachOral mesalamine at least 2 g daily plus a rectal enema at least 1 g daily.
InflammationExtensive colon
Usual 5-ASA approachOral mesalamine at least 2 g daily; rectal treatment can supplement distal coverage.
These are guideline-level adult treatment ranges, not instructions to exchange equal tablet counts. Specific products differ in strength, release, indications, and administration. The cited 1.2-g delayed-release tablet is taken whole with food. PENTASA capsules may be opened and their contents sprinkled onto applesauce or yogurt, but the particles must not be crushed or chewed. A patient with swallowing difficulty needs a compatible preparation, not destruction of the delivery system. [4][6]
A suppository has improved rectal bleeding, but repeat assessment still shows active inflammation in the descending colon. Point to the area outside the suppository's main coverage before checking the treatment implication.
Check the coverage mismatch
The descending colon needs more proximal delivery. An oral-plus-enema strategy addresses left-sided disease more appropriately than a larger suppository alone. [1]
Now change the situation: oral therapy has controlled proximal disease, but inflammation persists only in the distal rectum. Direct rectal delivery can address that remaining site. Neither example proves that all nonresponse is a delivery problem; the next step is to check actual exposure and disease severity. [1]
Separate inadequate exposure from treatment failure
When does persistent bleeding call for more 5-ASA, and when does it call for a different plan? Establish disease extent and activity, then check what the patient actually takes. Three tablets prescribed are not three tablets swallowed. Ask about missed doses, cost, retention of rectal treatment, and tolerability. Once-daily oral dosing can improve the practicality of a regimen; guidance does not claim that once-daily dosing is inherently more effective than divided dosing at equivalent exposure. Use a schedule compatible with the selected product. [1]
For example, someone prescribed two 1.2-g tablets each day but consistently taking only one has received 1.2 g, not an adequate trial of the intended 2.4 g. Correcting the administration problem is different from relabeling the disease as drug-resistant. In contrast, documented adherence to appropriate oral and rectal doses with persistent objective inflammation warrants reassessment and escalation. Test for infection, especially Clostridioides difficile, rather than assuming every increase in diarrhea is an inflammatory relapse. [1][4]
For responsive mild-to-moderate UC, mesalamine can induce remission and then maintain it. Guideline maintenance doses include rectal 5-ASA 1 g daily for proctitis and oral 5-ASA at least 1.5 g daily for left-sided or extensive disease. Apply the actual product label: the cited 1.2-g delayed-release tablet has an adult induction dose of 2.4 to 4.8 g once daily and a maintenance dose of 2.4 g once daily. These values are not interchangeable with every other preparation. A maximum dose is not automatically necessary for every mildly active case. [1][4]
After appropriately dosed therapy fails, cycling indefinitely through mesalamine brands is not the recommended solution. Budesonide MMX is an induction option for appropriate mild-to-moderate UC after 5-ASA nonresponse; ileal-release budesonide is a different formulation with a different target. Systemic corticosteroids or advanced therapies may be needed according to severity and prior response. Corticosteroids, including budesonide MMX and rectal steroids, are not maintenance therapy. Steroid dependence should prompt a steroid-sparing strategy rather than repeated reassurance that 5-ASA will eventually suffice. [1]
Frequent bloody stools with fever, tachycardia, anemia, dehydration, or severe abdominal symptoms require urgent assessment. Acute severe UC needs hospital-based evaluation and treatment, including infection testing and intravenous corticosteroids when appropriate, with timely assessment for rescue therapy or surgery. Do not delay this pathway to try a different 5-ASA brand. Stool frequency alone does not define the full severity assessment. [1]
Compare two patients with the same prescribed dose: one misses half the tablets; the other takes the full oral-plus-rectal regimen and still has active disease on reassessment. Name the first problem in each.
Check the two explanations
The first has inadequate actual exposure; the second has persistent disease despite an adequate trial. Those findings justify different next steps. [1]
For transfer, ask what sustained steroid-free remission should change. It can permit an appropriate maintenance regimen, but it does not make a chronic disease disappear or justify automatic cessation of effective therapy. [1]
Do not transfer UC evidence to Crohn disease
If mesalamine reaches the ileum, why is it not a routine treatment for ileal Crohn disease? An anatomic route and an effective treatment are separate questions. UC primarily involves colonic mucosa; Crohn disease has a different distribution and can involve the full bowel wall. These differences help organize the reasoning, but treatment recommendations come from clinical evidence, not from anatomy alone. The 2025 ACG guidance recommends against oral mesalamine for induction or maintenance of luminal Crohn disease. [2]
Sulfasalazine has a limited place in selected patients with symptomatic, mildly active colonic Crohn disease. That is not permission to use it for isolated ileal disease, fistulas, strictures, progressive disease, or every patient with colonic involvement. Less diarrhea does not establish mucosal healing. Continued objective activity still needs reassessment and an effective disease-control plan. [2]
Contrast an adult with mild disease confined to the ileocecal region, without obstructive or penetrating complications, with an adult who has a draining fistula and weight loss. Ileal-release budesonide can be an induction option in the first setting; it is not maintenance therapy. The second setting requires specialist evaluation for a substantially different treatment strategy rather than extension of the mild-colonic sulfasalazine exception. [2]
A patient with mild colonic Crohn disease has fewer stools on sulfasalazine, but repeat endoscopy shows persistent ulcers. Predict which conclusion is justified before checking.
Check symptom response against tissue response
Symptoms improved, but the ulcers show ongoing disease. The observation does not establish mucosal healing or justify indefinite treatment without reassessment. [2]
Carry this distinction back to UC as well: the therapeutic goal is durable control assessed with symptoms and appropriate objective measures, not a drug name on a medication list. [1][2]
Distinguish tolerability from organ injury
Which adverse effects change the next dose, and which require immediate evaluation? Sulfasalazine can cause dose-related nausea and headache, and the absorbed sulfapyridine component contributes to many tolerability problems. A cautious clinician-supervised titration can help selected patients without warning features. Fever, a new significant rash, facial swelling, mucosal lesions, jaundice, purpura, or sore throat are different findings: serious hypersensitivity, liver injury, or blood disorders must be considered. Do not treat these as ordinary dose-related nausea. [3][5]
Severe sulfasalazine hypersensitivity can affect multiple organs. Drug reaction with eosinophilia and systemic symptoms may begin with fever or lymphadenopathy before a rash appears. Stevens-Johnson syndrome and toxic epidermal necrolysis are other serious risks. Promptly stop the suspected drug and obtain urgent clinical evaluation for these syndromes. A previous severe reaction is not a reason to try an enteric-coated version at home. [3][5]
Blood findings separate several mechanisms. In G6PD deficiency, oxidant injury can produce hemolysis, with falling hemoglobin, increased reticulocytes and indirect bilirubin, and low haptoglobin. Reduced folate absorption can instead impair red-cell production, producing macrocytosis and an inadequate reticulocyte response. Severe neutropenia or broader cytopenias raise concern for marrow toxicity. These patterns require evaluation; folate should not be used to explain away every abnormal blood count. Review folate supplementation particularly when deficiency risk or pregnancy planning is present, while coordinating ongoing disease treatment. [3]
Sulfasalazine-associated reductions in sperm count and quality are often reversible after withdrawal. A supervised change to an appropriate mesalamine regimen may preserve UC control while avoiding sulfapyridine. Fertility has other determinants, and mesalamine labeling also includes rare reports of reversible oligospermia, so do not promise recovery or claim that fertility effects are exclusive to one drug. Reassessment belongs in the plan. [3][4]
A serious sulfasalazine reaction does not automatically make mesalamine a safe substitute. Some patients react to shared aminosalicylate exposure, so the nature of the original reaction and specialist assessment matter. [4]
Mesalamine can cause an acute intolerance syndrome with cramps, abdominal pain, bloody diarrhea, and sometimes fever, headache, or rash. The presentation can resemble a UC flare. A close temporal relationship to starting treatment is a reason to reconsider the drug, not automatically increase it. Stop mesalamine when acute intolerance is suspected and assess competing explanations, including infection. Severe upper abdominal pain with substantially increased lipase requires evaluation for pancreatitis, which has also been reported with mesalamine. [4]
Compare a patient with mild nausea after a dose increase and normal examination and tests with a patient who develops fever, facial swelling, and abnormal liver tests after three weeks. Which finding makes a simple dose-titration plan unsafe?
Check the safety distinction
Fever with facial swelling and liver injury suggests systemic hypersensitivity. Stop the suspected drug and arrange urgent assessment rather than merely lowering the dose. [3][5]
For a new situation, consider sudden worsening of diarrhea soon after mesalamine starts. The symptoms can belong to the treatment rather than the disease; timing and the rest of the evaluation determine the next step. [4]
Monitor the patient beyond the bowel
Can a medicine acting mainly at the mucosa still injure the kidneys? Yes. Mesalamine and products converted to mesalamine have been associated with acute or chronic interstitial nephritis and other renal injury. Assess renal function before treatment and periodically during it, including with rectal preparations. Pre-existing renal disease and concurrent nephrotoxic medicines affect the benefit-risk assessment and the monitoring plan. The labels do not establish one universal renal testing interval for every patient. [3][4][7]
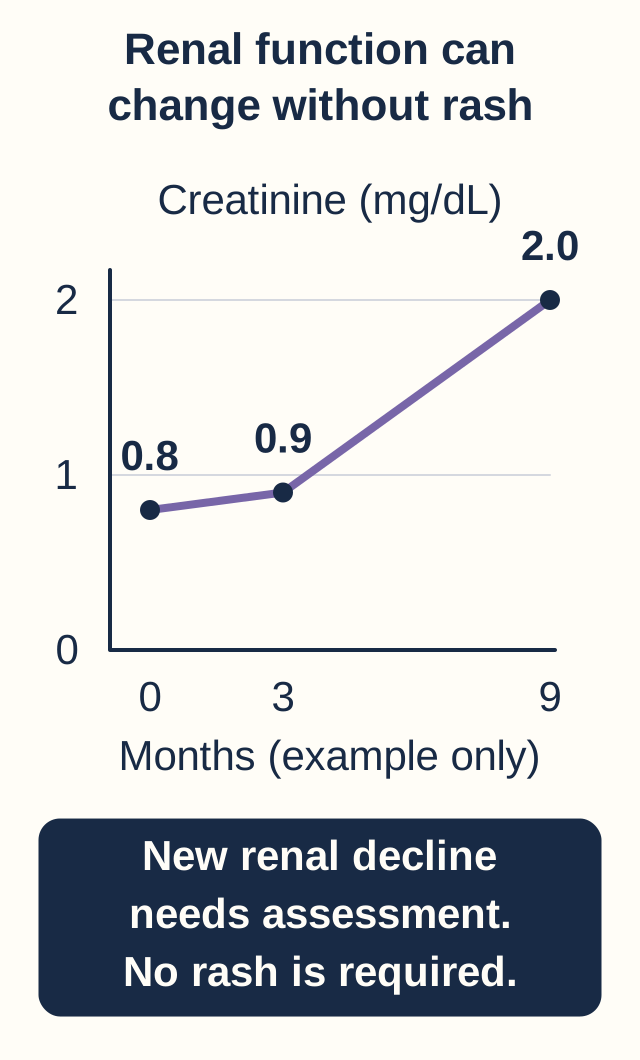
Read the accompanying renal trend: creatinine is 0.8 mg/dL before treatment, 0.9 at an early review, and 2.0 later. The important observation is deterioration during exposure, not simply whether the patient has a rash. Sterile pyuria can support interstitial inflammation but does not prove drug-induced nephritis. Stop mesalamine when renal function deteriorates, assess volume status and other nephrotoxins, and obtain further evaluation appropriate to the severity and persistence of injury. A rectal substitution does not eliminate exposure to the suspected molecule. [4][7]
A rising creatinine prompts assessment; it does not independently diagnose drug-induced nephritis. [4][7][4][7]
Sulfasalazine also requires blood-count and hepatic surveillance. Its US label specifies a CBC with differential and liver tests before treatment, every two weeks for the first three months, monthly for the next three months, and every three months thereafter or as clinically indicated. Urinalysis and renal assessment are also needed periodically. New fever, sore throat, pallor, purpura, or jaundice warrants prompt assessment rather than waiting for the next scheduled test. Contraindications include relevant sulfonamide or salicylate hypersensitivity, intestinal or urinary obstruction, and porphyria. [3][5]
Medication reconciliation changes the plan. NSAIDs can add renal risk to mesalamine. Azathioprine or 6-mercaptopurine with mesalamine can increase blood-disorder risk, so CBC and platelet monitoring become especially important; a normal pretreatment pharmacogenetic result does not cancel a drug interaction. Sulfasalazine can reduce absorption of folic acid and digoxin. Review clinical response and appropriate drug measurements rather than assuming a falling digoxin concentration represents kidney failure. [3][4]
For a patient using warfarin, coordinate INR follow-up when sulfasalazine is started, stopped, or changed. Published case reports describe both increased and reduced anticoagulant effect. Those reports justify vigilance, not a guaranteed direction, frequency estimate, or automatic dose change for everyone. An abnormal INR requires individualized anticoagulation management; do not permanently abandon anticoagulation needed for a mechanical valve simply to avoid reviewing an interaction. [9][10]
Compare a normal CBC with a new creatinine rise during mesalamine treatment. Which result addresses the principal concern in the renal graph?
Check what the normal test does not exclude
A normal CBC does not exclude renal injury. The creatinine change needs its own assessment and medication decision. [4]
For transfer, a patient using only a rectal suppository still needs baseline and periodic renal assessment. Route selection, disease control, and surveillance are separate tasks; success in one does not replace the others. [7]
Apply the lesson
Use distribution, actual exposure, and the pattern of response or injury to choose a next step. Review every alternative, including why it would fit a different patient.
Case 1
Show answer and explanations for case 1
A. Mesalamine suppository, 1 g nightly (Best answer)
A suppository provides direct exposure to the rectal mucosa. Only the distal 10 cm remains active despite reliable oral therapy. Use direct rectal delivery for residual proctitis rather than assuming global treatment failure.
Reasoning steps for option A
Where does a suppository deliver mesalamine?
A suppository provides direct exposure to the rectal mucosa.
Where does objective inflammation remain?
Only the distal 10 cm remains active despite reliable oral therapy.
Why does a nightly mesalamine suppository target the residual distal 10 cm?
A nightly mesalamine suppository directly exposes the still-inflamed distal 10 cm of rectum after oral therapy healed mucosa above it.
B. Ileal-release budesonide, 9 mg daily (Why this does not fit)
This preparation targets the ileum and proximal colon. The documented disease is confined to the rectum, not the ileocecal region. Match the formulation to the affected segment.
Reasoning steps for option B
What region is ileal-release budesonide intended to treat?
This preparation targets the ileum and proximal colon.
Does that region match the remaining inflammation?
The documented disease is confined to the rectum, not the ileocecal region.
Why does ileal-release budesonide miss this rectal-only activity?
Ileal-release budesonide favors the ileum and proximal colon, whereas this patient has residual inflammation only in the rectum.
C. Prednisone, 40 mg daily (Why this does not fit)
Systemic corticosteroids can induce remission when severity or treatment failure warrants them. No rectal 5-ASA trial is described, and the residual disease is limited without systemic illness. Optimize appropriate local treatment before unnecessary systemic steroid exposure.
Reasoning steps for option C
When can systemic prednisone induce remission?
Systemic corticosteroids can induce remission when severity or treatment failure warrants them.
Has direct rectal treatment failed here?
No rectal 5-ASA trial is described, and the residual disease is limited without systemic illness.
Why is prednisone premature before a rectal 5-ASA trial in limited proctitis?
Prednisone adds systemic steroid exposure before a direct rectal 5-ASA trial for limited proctitis without systemic illness.
D. Azathioprine, 2 mg/kg daily (Why this does not fit)
Thiopurines are not effective rapid induction monotherapy. Persistent distal inflammation has not received direct rectal 5-ASA. Do not substitute a slow steroid-sparing strategy for an untried appropriate local treatment.
Reasoning steps for option D
What is the limitation of thiopurines for active UC?
Thiopurines are not effective rapid induction monotherapy.
What is the immediate, localized problem?
Persistent distal inflammation has not received direct rectal 5-ASA.
Why would azathioprine not promptly treat the untreated distal inflammation?
Azathioprine is too slow for rapid induction and does not replace untried rectal 5-ASA for persistent distal inflammation.
E. Sulfasalazine, 1 g twice daily (Why this does not fit)
Sulfasalazine is converted to 5-ASA in the colon. It adds carrier exposure without directly addressing the untreated rectal route. A different carrier is not the same as targeted rectal delivery.
Reasoning steps for option E
What active intestinal product does sulfasalazine supply?
Sulfasalazine is converted to 5-ASA in the colon.
Does adding another oral 5-ASA source solve the demonstrated mismatch?
It adds carrier exposure without directly addressing the untreated rectal route.
Why does adding oral sulfasalazine fail to correct the rectal delivery gap?
Oral sulfasalazine adds another 5-ASA source and sulfapyridine exposure but not the targeted rectal delivery missing here.
Takeaway: Use direct rectal delivery for residual proctitis rather than assuming global treatment failure.
A. Mesalamine suppository 1 g twice daily (Why this does not fit)
It increases exposure principally in the rectum. The sigmoid and descending colon lie beyond the suppository's main treatment area. More distal dosing does not reliably provide more proximal coverage.
Reasoning steps for option A
What coverage does increasing suppository frequency add?
It increases exposure principally in the rectum.
Which segments remain inflamed?
The sigmoid and descending colon lie beyond the suppository's main treatment area.
Why will twice-daily suppositories inadequately cover sigmoid and descending inflammation?
Twice-daily suppositories increase rectal exposure but do not reliably reach the still-inflamed sigmoid and descending colon.
B. Oral mesalamine 2.4 g daily plus mesalamine enema (Best answer)
It combines proximal delivery with direct distal colonic exposure. Left-sided inflammation persists beyond an improving rectum, and the patient can use an enema. For left-sided UC, match both oral and rectal coverage to disease extent.
Reasoning steps for option B
What does oral-plus-enema treatment provide?
It combines proximal delivery with direct distal colonic exposure.
Why is that combination appropriate here?
Left-sided inflammation persists beyond an improving rectum, and the patient can use an enema.
Why pair oral mesalamine 2.4 g with an enema for disease to the splenic flexure?
Oral mesalamine 2.4 g supplies broader colonic coverage while an enema directly treats the active left colon beyond the improving rectum.
C. Ileal-release budesonide 9 mg daily plus suppository (Why this does not fit)
It favors the ileocecal region rather than the descending colon. The suppository still focuses on the rectum while the active left colon remains poorly targeted. Different budesonide formulations should not be treated as interchangeable.
Reasoning steps for option C
What distribution does ileal-release budesonide favor?
It favors the ileocecal region rather than the descending colon.
What gap remains in this proposed regimen?
The suppository still focuses on the rectum while the active left colon remains poorly targeted.
Why does ileal-release budesonide plus a suppository poorly target left-colon activity?
Ileal-release budesonide favors ileocecal delivery, and the retained suppository mainly reaches the rectum, leaving the active left colon poorly covered.
D. Oral prednisone 10 mg daily plus suppository (Why this does not fit)
They may induce remission when indicated but are not maintenance treatment. The patient has not received appropriate oral-plus-enema 5-ASA and has no severe features. Correct an identifiable delivery gap before committing to chronic low-dose steroid exposure.
Reasoning steps for option D
What role do systemic steroids have in UC?
They may induce remission when indicated but are not maintenance treatment.
Why is this not the best initial correction?
The patient has not received appropriate oral-plus-enema 5-ASA and has no severe features.
Why is chronic prednisone 10 mg inappropriate before oral-plus-enema induction?
Chronic prednisone 10 mg is not maintenance therapy and is premature before appropriate oral-plus-enema 5-ASA in this nonsevere presentation.
E. Oral mesalamine 1.2 g daily plus suppository (Why this does not fit)
It is below the guideline oral induction threshold of at least 2 g daily. It remains primarily rectal despite active sigmoid and descending disease. Check both dose adequacy and the reach of the rectal preparation.
Reasoning steps for option E
How does this oral dose compare with left-sided induction guidance?
It is below the guideline oral induction threshold of at least 2 g daily.
Does the retained suppository add broader distal coverage?
It remains primarily rectal despite active sigmoid and descending disease.
Which two coverage deficits remain with oral mesalamine 1.2 g and a suppository?
Oral mesalamine 1.2 g is below the at-least-2-g induction threshold, while a suppository still misses much of the active sigmoid and descending colon.
Takeaway: For left-sided UC, match both oral and rectal coverage to disease extent.
A. Increase the frequency of the same enema (Why this does not fit)
Enemas mainly provide distal colonic exposure. The transverse and ascending colon remain active above the main area of rectal treatment. More frequent distal treatment does not substitute for extensive-colitis coverage.
Reasoning steps for option A
What portion of the colon does an enema mainly expose?
Enemas mainly provide distal colonic exposure.
Where is inflammation now documented?
The transverse and ascending colon remain active above the main area of rectal treatment.
Why cannot more frequent enemas reliably reach active transverse and ascending colon?
More frequent enemas chiefly increase distal exposure and cannot substitute for treatment of active transverse and ascending colon.
B. Replace the enema with a rectal suppository (Why this does not fit)
A suppository generally treats a shorter distal segment. The active inflammation is proximal, while the rectum is already healing. Choose delivery based on the active segment rather than the easiest formulation alone.
Reasoning steps for option B
How does suppository coverage compare with an enema?
A suppository generally treats a shorter distal segment.
Would narrowing coverage address the current disease?
The active inflammation is proximal, while the rectum is already healing.
Why does replacing an enema with a suppository narrow coverage when proximal disease persists?
A suppository reaches less distal colon than an enema, so replacing it narrows exposure while transverse and ascending inflammation persists.
C. Add oral mesalamine at an adequate induction dose (Best answer)
An appropriate oral formulation supplies exposure to more proximal colonic mucosa. The proximal colon remains active after improvement limited to the rectal treatment area. Partial regional response can reveal inadequate anatomic coverage rather than class failure.
Reasoning steps for option C
What does oral treatment add to an enema?
An appropriate oral formulation supplies exposure to more proximal colonic mucosa.
Why is that addition justified here?
The proximal colon remains active after improvement limited to the rectal treatment area.
Why add adequately dosed oral mesalamine after rectosigmoid healing on an enema?
Adequately dosed oral mesalamine reaches the active proximal colon that the enema did not adequately cover, while the rectum and sigmoid are healing.
D. Substitute long-term low-dose oral prednisone (Why this does not fit)
Prednisone is not a maintenance treatment for UC. Only an enema has been used, leaving extensive disease insufficiently covered. Do not use chronic steroids to compensate for an uncorrected first-line delivery gap.
Reasoning steps for option D
Can prednisone maintain steroid-free remission?
Prednisone is not a maintenance treatment for UC.
Has an appropriate oral 5-ASA regimen already failed?
Only an enema has been used, leaving extensive disease insufficiently covered.
Why is long-term prednisone an unsuitable substitute for missing proximal 5-ASA delivery?
Long-term prednisone is not UC maintenance and should not replace an adequate oral 5-ASA trial for extensive disease still outside enema reach.
E. Replace the enema with oral mesalamine 1.2 g daily (Why this does not fit)
It can provide exposure to more proximal colonic mucosa. The 1.2-g daily amount is below the guideline oral induction threshold for extensive UC. Correcting the route requires an adequate dose as well as broader coverage.
Reasoning steps for option E
Why would an oral route be attractive here?
It can provide exposure to more proximal colonic mucosa.
What is inadequate about this specific proposed induction regimen?
The 1.2-g daily amount is below the guideline oral induction threshold for extensive UC.
Why is oral mesalamine 1.2 g insufficient despite correcting the route for extensive UC?
Oral mesalamine addresses proximal reach, but 1.2 g daily is below the guideline induction dose for extensive UC.
Takeaway: Partial regional response can reveal inadequate anatomic coverage rather than class failure.
A. Increase to four tablets while retaining the two-dose schedule (Why this does not fit)
It can increase exposure when the patient takes the additional tablets. The evening dose is repeatedly missed, so the current intended daily exposure has not been tested. Correct actual administration before equating a prescription with an adequate trial.
Reasoning steps for option A
What can a higher prescribed dose accomplish?
It can increase exposure when the patient takes the additional tablets.
What documented barrier would this leave unchanged?
The evening dose is repeatedly missed, so the current intended daily exposure has not been tested.
Why would four tablets on the same twice-daily schedule not solve missed evening doses?
Four tablets do not correct the repeated missed evening administration; first establish actual adherence to the prescribed schedule.
B. Replace mesalamine with budesonide MMX for induction (Why this does not fit)
It can induce remission after appropriate 5-ASA nonresponse in suitable UC. Frequent omissions mean that the intended 2.4-g daily exposure was not achieved. Separate nonadherence from pharmacologic nonresponse before escalation.
Reasoning steps for option B
When is budesonide MMX a reasonable option?
It can induce remission after appropriate 5-ASA nonresponse in suitable UC.
What prevents calling this an adequate mesalamine trial?
Frequent omissions mean that the intended 2.4-g daily exposure was not achieved.
What must be corrected before labeling the prescribed 2.4 g mesalamine a failure and switching to MMX budesonide?
Budesonide MMX escalation is premature because missing the evening tablet five days weekly means the intended 2.4-g mesalamine trial has not occurred.
C. Add sulfasalazine while retaining the current mesalamine doses (Why this does not fit)
It supplies additional 5-ASA with sulfapyridine exposure. It increases regimen complexity without resolving the repeatedly missed evening medicine. Avoid unnecessary duplicate 5-ASA treatment when the primary issue is administration.
Reasoning steps for option C
What does adding sulfasalazine supply?
It supplies additional 5-ASA with sulfapyridine exposure.
Does it address the documented reason for low exposure?
It increases regimen complexity without resolving the repeatedly missed evening medicine.
Why does adding sulfasalazine complicate rather than solve the missed-dose problem?
Sulfasalazine duplicates 5-ASA with added sulfapyridine and regimen complexity without fixing the missed evening dose.
D. Take both tablets once daily and reassess the treatment response (Best answer)
Two 1.2-g tablets provide 2.4 g daily. The supported once-daily schedule eliminates the specifically missed evening administration without changing the intended total dose. A simpler compatible schedule can improve actual exposure without being intrinsically more potent.
Reasoning steps for option D
What is the intended total daily mesalamine dose?
Two 1.2-g tablets provide 2.4 g daily.
Why can this change make the trial interpretable?
The supported once-daily schedule eliminates the specifically missed evening administration without changing the intended total dose.
How does taking both 1.2-g tablets together address the documented five missed evenings weekly?
Taking both 1.2-g tablets once daily preserves the intended 2.4-g total and removes the specifically missed evening dose in a product that permits once-daily use. The simpler schedule improves actual exposure without being intrinsically more potent.
E. Change to another mesalamine product given twice daily (Why this does not fit)
It can change release characteristics, tablet burden, or tolerability. The timing of the evening dose is the barrier, not an adverse effect or incompatible release system. Target the identified adherence barrier rather than changing brands by default.
Reasoning steps for option E
What might a product change alter?
It can change release characteristics, tablet burden, or tolerability.
Which relevant problem is already demonstrated here?
The timing of the evening dose is the barrier, not an adverse effect or incompatible release system.
Why is another twice-daily mesalamine product unlikely to fix a timing barrier?
Changing to another twice-daily product retains the demonstrated evening-timing barrier, without evidence of release or tolerability problems.
Takeaway: A simpler compatible schedule can improve actual exposure without being intrinsically more potent.
A. Exchange the oral product for another mesalamine brand at 4.8 g daily (Why this does not fit)
It may address a release, administration, or tolerability problem. Adequate oral and rectal exposure has not controlled objective disease, without a stated delivery or adherence problem. After an adequate trial fails, another treatment class is more appropriate than routine brand cycling.
Reasoning steps for option A
When can a formulation change be useful?
It may address a release, administration, or tolerability problem.
Which problem is demonstrated after this trial?
Adequate oral and rectal exposure has not controlled objective disease, without a stated delivery or adherence problem.
Why is another mesalamine brand unlikely to resolve persistent endoscopic activity after eight adherent weeks?
After eight adherent weeks of oral mesalamine 4.8 g plus nightly enema, another brand changes delivery rather than treating demonstrated 5-ASA nonresponse.
B. Replace oral mesalamine with sulfasalazine 4 g daily (Why this does not fit)
It generates 5-ASA after bacterial cleavage. No; it replaces the delivery and carrier rather than addressing persistent disease after adequate 5-ASA. A different carrier is not necessarily an appropriate escalation after class nonresponse.
Reasoning steps for option B
What therapeutic intestinal product does sulfasalazine generate?
It generates 5-ASA after bacterial cleavage.
Would this constitute a different anti-inflammatory class for the demonstrated failure?
No; it replaces the delivery and carrier rather than addressing persistent disease after adequate 5-ASA.
Why is sulfasalazine not a new anti-inflammatory class after adequate oral and rectal mesalamine?
Sulfasalazine still yields 5-ASA, adding a different carrier rather than a new anti-inflammatory class after adequate oral and rectal 5-ASA failed.
C. Reduce oral mesalamine to 2.4 g daily and continue the enema (Why this does not fit)
It may suit mild responsive disease or a product-specific maintenance regimen. Ongoing bleeding and endoscopic activity show failure to induce remission. Do not interpret a maintenance dose as the answer to persistent active disease.
Reasoning steps for option C
When can a lower mesalamine dose be appropriate?
It may suit mild responsive disease or a product-specific maintenance regimen.
Has this patient reached a response that supports de-escalation?
Ongoing bleeding and endoscopic activity show failure to induce remission.
Why is reducing oral mesalamine to 2.4 g inappropriate while bleeding continues?
Persistent bleeding and active endoscopy show that remission has not been induced, so reducing oral mesalamine from 4.8 to 2.4 g does not address the active disease.
D. Add ileal-release budesonide 9 mg daily to the existing regimen (Why this does not fit)
It is designed for the ileocecal region. The active disease is left-sided UC, for which the colonic MMX formulation is the relevant budesonide option. The same steroid name does not make its formulations equivalent.
Reasoning steps for option D
Where is ileal-release budesonide intended to act?
It is designed for the ileocecal region.
What distribution requires additional treatment here?
The active disease is left-sided UC, for which the colonic MMX formulation is the relevant budesonide option.
Why is ileal-release budesonide the wrong steroid formulation for active left-sided UC?
Ileal-release budesonide targets the ileocecal region, not the active left colon for which colonic MMX is relevant.
E. Add budesonide MMX 9 mg daily to the existing regimen (Best answer)
It is an induction option for appropriate UC that remains active after 5-ASA treatment. Adherent, adequately dosed oral-plus-rectal treatment has failed, infection testing is negative, and no acute severe features are supplied. Use a colonic induction strategy after adequate 5-ASA nonresponse, then plan steroid-free maintenance.
Reasoning steps for option E
What is the role of budesonide MMX in this setting?
It is an induction option for appropriate UC that remains active after 5-ASA treatment.
What findings establish that situation here?
Adherent, adequately dosed oral-plus-rectal treatment has failed, infection testing is negative, and no acute severe features are supplied.
Why does budesonide MMX fit stable left-sided UC after adequate oral-plus-enema 5-ASA fails?
Budesonide MMX is a colonic induction option after adherent, adequately dosed oral-plus-rectal 5-ASA fails in stable, nonsevere left-sided UC; plan steroid-free maintenance.
Takeaway: Use a colonic induction strategy after adequate 5-ASA nonresponse, then plan steroid-free maintenance.
A. Oral controlled-release mesalamine, 1 g four times daily (Why this does not fit)
Controlled-release mesalamine can provide small-bowel exposure. No. Oral mesalamine is not recommended for luminal Crohn induction despite anatomic delivery. Drug arrival at a site does not establish disease-specific efficacy.
Reasoning steps for option A
Can this formulation release mesalamine in the small bowel?
Controlled-release mesalamine can provide small-bowel exposure.
Does that establish effective Crohn induction?
No. Oral mesalamine is not recommended for luminal Crohn induction despite anatomic delivery.
Why does small-bowel release of mesalamine not establish efficacy for luminal ileocecal Crohn disease?
Although controlled-release mesalamine can reach small bowel, oral mesalamine lacks recommended induction efficacy for luminal Crohn disease.
B. Budesonide MMX, 9 mg once daily (Why this does not fit)
It is a colonic formulation used for UC induction. The terminal ileum and cecum, rather than diffuse UC, are involved. Select both the drug and its delivery system for the stated disease.
Reasoning steps for option B
What disease distribution is MMX budesonide used for?
It is a colonic formulation used for UC induction.
Which distribution is central in this Crohn presentation?
The terminal ileum and cecum, rather than diffuse UC, are involved.
Why does colonic budesonide MMX not match mild terminal ileal and cecal Crohn disease?
Budesonide MMX is a colonic UC formulation, whereas this mild Crohn presentation prominently involves the terminal ileum and cecum.
C. Ileal-release budesonide, 9 mg once daily (Best answer)
Mild ileocecal Crohn disease without the supplied high-risk complications fits this option. Mesalamine release in the ileum does not overcome its lack of recommended luminal Crohn efficacy. Use disease-specific evidence and anatomic delivery together; budesonide is not maintenance therapy.
Reasoning steps for option C
What setting fits ileal-release budesonide induction?
Mild ileocecal Crohn disease without the supplied high-risk complications fits this option.
What competing assumption needs rejection?
Mesalamine release in the ileum does not overcome its lack of recommended luminal Crohn efficacy.
Which disease and location features support ileal-release budesonide induction here?
Mild uncomplicated terminal ileal and cecal Crohn disease fits ileal-release budesonide induction, unlike mesalamine despite its possible ileal release; budesonide is not maintenance.
D. Sulfasalazine, 1 g three times daily (Why this does not fit)
It is limited to selected symptomatic, mildly active colonic disease. The terminal ileum is a principal disease site, and isolated colonic treatment logic does not cover it. Do not extend a narrow colonic exception to ileal Crohn disease.
Reasoning steps for option D
Where does the sulfasalazine exception apply in Crohn disease?
It is limited to selected symptomatic, mildly active colonic disease.
Why is that exception insufficient for this patient?
The terminal ileum is a principal disease site, and isolated colonic treatment logic does not cover it.
Why does the narrow colonic sulfasalazine exception not extend to this terminal ileal disease?
Sulfasalazine has only a narrow role in selected mildly active colonic Crohn symptoms and cannot be extrapolated to this principal terminal ileal involvement.
E. Mesalamine suppository, 1 g nightly (Why this does not fit)
The rectum receives the primary local exposure. The rectum is normal while the terminal ileum and cecum are active. A rectal preparation cannot substitute for treatment of ileocecal disease.
Reasoning steps for option E
Which site receives direct suppository treatment?
The rectum receives the primary local exposure.
Is rectal disease present here?
The rectum is normal while the terminal ileum and cecum are active.
Why would rectal mesalamine miss the active terminal ileum and cecum?
A suppository directly treats the rectum, which is normal here, rather than the active terminal ileum and cecum.
Takeaway: Use disease-specific evidence and anatomic delivery together; budesonide is not maintenance therapy.
A. Symptoms improved, but persistent inflammation still needs reassessment (Best answer)
They demonstrate a symptomatic response. They show that symptom improvement has not established inflammatory control. Keep the narrow symptomatic sulfasalazine role separate from a claim of mucosal healing.
Reasoning steps for option A
What do fewer stools and less discomfort demonstrate?
They demonstrate a symptomatic response.
What do persistent ulcers and high calprotectin add?
They show that symptom improvement has not established inflammatory control.
How should falling stool frequency be weighed against persistent ulcers and high calprotectin?
Fewer stools and less discomfort show symptomatic benefit from sulfasalazine, but persistent ulcers and high calprotectin require objective reassessment rather than a claim of healing.
B. Both symptoms and mucosal disease are controlled on the current regimen (Why this does not fit)
Objective reassessment would need to show resolution of relevant inflammatory lesions. Ulcers persist despite the improved symptoms. Clinical comfort alone is not proof of tissue healing.
Reasoning steps for option B
What would establish mucosal healing?
Objective reassessment would need to show resolution of relevant inflammatory lesions.
What does this reassessment show instead?
Ulcers persist despite the improved symptoms.
Why cannot symptom relief on sulfasalazine be called mucosal healing here?
Repeat endoscopy still shows ulcers and calprotectin remains high, so improved Crohn symptoms do not establish mucosal healing.
C. The response supports substitution of mesalamine for Crohn maintenance (Why this does not fit)
It is an established maintenance option in responsive UC. No. Oral mesalamine is not recommended for luminal Crohn maintenance, and inflammation is still present. Do not transfer UC maintenance evidence to active Crohn disease.
Reasoning steps for option C
When can mesalamine maintain remission?
It is an established maintenance option in responsive UC.
Can that UC role be imported into this Crohn scenario?
No. Oral mesalamine is not recommended for luminal Crohn maintenance, and inflammation is still present.
Why does the UC maintenance role of mesalamine not justify Crohn substitution with ulcers still present?
Mesalamine maintenance evidence in UC does not transfer to luminal Crohn disease, especially while ulcers and inflammation persist.
D. The objective findings establish acute intolerance to sulfasalazine (Why this does not fit)
New or worsening symptoms after exposure can prompt evaluation for intolerance. Symptoms improved while pre-existing inflammatory lesions persist. Persistent disease and acute treatment intolerance are different explanations.
Reasoning steps for option D
What temporal pattern can support acute drug intolerance?
New or worsening symptoms after exposure can prompt evaluation for intolerance.
Is that the pattern supplied here?
Symptoms improved while pre-existing inflammatory lesions persist.
Why do persistent ulcers despite improved symptoms not establish acute sulfasalazine intolerance?
Acute drug intolerance would require a compatible new symptom pattern after exposure; here symptoms improved while pre-existing ulcers persist.
E. The persistent ulcers justify chronic prednisone after symptoms resolve (Why this does not fit)
It may induce remission when disease severity warrants systemic treatment. No. Corticosteroids are not maintenance treatment, and a durable steroid-sparing plan is needed. Treat ongoing inflammation without converting an induction drug into chronic maintenance.
Reasoning steps for option E
What useful role can prednisone have in Crohn disease?
It may induce remission when disease severity warrants systemic treatment.
Does that support indefinite use after induction?
No. Corticosteroids are not maintenance treatment, and a durable steroid-sparing plan is needed.
Prednisone can induce remission when warranted but cannot be continued indefinitely to maintain Crohn control; persistent ulcers need a durable steroid-sparing plan.
Takeaway: Keep the narrow symptomatic sulfasalazine role separate from a claim of mucosal healing.
A. Outpatient mesalamine escalation with reassessment in four weeks (Why this does not fit)
It can address inadequate dosing in suitable mild-to-moderate UC. Frequent bloody stools with fever, tachycardia, and anemia indicate a severe illness requiring urgent assessment. Severity takes priority over another outpatient 5-ASA trial.
Reasoning steps for option A
When can oral mesalamine escalation be reasonable?
It can address inadequate dosing in suitable mild-to-moderate UC.
Why is outpatient waiting unsafe in this presentation?
Frequent bloody stools with fever, tachycardia, and anemia indicate a severe illness requiring urgent assessment.
Which fever, pulse, stool-count and hemoglobin findings rule out waiting four weeks on outpatient mesalamine?
Eight bloody stools daily with fever 38.2 C, pulse 116/min and hemoglobin 9.1 g/dL require urgent severe-colitis assessment, not a four-week outpatient mesalamine wait.
B. Outpatient budesonide MMX with continued oral mesalamine (Why this does not fit)
It can be used for induction in appropriate nonsevere UC after 5-ASA nonresponse. Systemic toxicity and substantial bleeding require hospital-based evaluation. Do not apply a mild-disease induction plan to acute severe colitis.
Reasoning steps for option B
What setting can fit budesonide MMX?
It can be used for induction in appropriate nonsevere UC after 5-ASA nonresponse.
What findings place this patient outside that simple outpatient pathway?
Systemic toxicity and substantial bleeding require hospital-based evaluation.
Why is outpatient MMX budesonide inadequate with systemic toxicity and eight bloody stools daily?
Budesonide MMX is for appropriate nonsevere UC induction, not outpatient management of eight bloody stools with fever, tachycardia and anemia.
C. Outpatient sulfasalazine substitution with a higher daily dose (Why this does not fit)
It changes the delivery compound and adds sulfapyridine exposure. The immediate problem is severe colitis with systemic features, not selection of another 5-ASA carrier. Do not delay urgent care for within-class substitution.
Reasoning steps for option C
What does sulfasalazine change relative to mesalamine?
It changes the delivery compound and adds sulfapyridine exposure.
Does that address the current clinical priority?
The immediate problem is severe colitis with systemic features, not selection of another 5-ASA carrier.
Why is sulfasalazine substitution not the immediate priority for this severe presentation?
Switching to sulfasalazine merely changes the 5-ASA carrier and delays hospital assessment of severe colitis with systemic features.
D. Hospital admission for mesalamine-only treatment and observation (Why this does not fit)
Systemic features and substantial bloody diarrhea need hospital care. Acute severe UC generally requires a hospital induction pathway, including intravenous corticosteroids when appropriate. The correct setting must be paired with treatment adequate for disease severity.
Reasoning steps for option D
Why is admission justified?
Systemic features and substantial bloody diarrhea need hospital care.
What is inadequate about mesalamine-only treatment here?
Acute severe UC generally requires a hospital induction pathway, including intravenous corticosteroids when appropriate.
Why is admission with mesalamine alone inadequate for suspected acute severe UC?
Hospital admission is appropriate, but mesalamine alone is inadequate for acute severe UC, which generally requires intravenous corticosteroid induction when appropriate.
E. Hospital care with infection testing and intravenous corticosteroids (Best answer)
The combination of frequent bloody stools, fever, tachycardia, and anemia indicates severe colitis. Assess infection and complications and initiate appropriate intravenous corticosteroid treatment, with early reassessment for rescue or surgery. Do not let a proposed 5-ASA brand change delay care for acute severe UC.
Reasoning steps for option E
What establishes the need for hospital treatment?
The combination of frequent bloody stools, fever, tachycardia, and anemia indicates severe colitis.
What should the initial pathway include?
Assess infection and complications and initiate appropriate intravenous corticosteroid treatment, with early reassessment for rescue or surgery.
What makes hospital assessment, infection testing and intravenous steroids the priority now?
Eight bloody stools daily, fever, tachycardia and anemia warrant hospital infection and complication assessment with appropriate intravenous corticosteroids and early rescue-or-surgery reassessment.
Takeaway: Do not let a proposed 5-ASA brand change delay care for acute severe UC.
A. Less intact sulfasalazine, more 5-ASA, and more sulfapyridine (Why this does not fit)
More free 5-ASA and sulfapyridine would imply greater cleavage of the parent compound. The relevant cleavage enzyme was inhibited, not activated. Predict substrate and product changes from the direction of enzyme activity.
Reasoning steps for option A
What would greater product generation imply?
More free 5-ASA and sulfapyridine would imply greater cleavage of the parent compound.
What intervention was actually applied?
The relevant cleavage enzyme was inhibited, not activated.
Why would enzyme inhibition not produce more of both free cleavage products?
Inhibiting bacterial azoreductase reduces azo-bond cleavage, leaving more intact sulfasalazine and producing less free 5-ASA and sulfapyridine, not more of both.
B. More intact sulfasalazine, less 5-ASA, and less sulfapyridine (Best answer)
Bacterial cleavage of the azo bond releases 5-ASA and sulfapyridine together. More parent compound remains while formation of both free products decreases. The azo bond is a delivery mechanism requiring bacterial activation, not simple tablet dissolution.
Reasoning steps for option B
What reaction releases both products?
Bacterial cleavage of the azo bond releases 5-ASA and sulfapyridine together.
What does inhibiting that reaction predict?
More parent compound remains while formation of both free products decreases.
What happens to parent sulfasalazine and both products when bacterial azoreductase is inhibited?
Azoreductase inhibition preserves more parent sulfasalazine while decreasing formation of both linked products, free 5-ASA and sulfapyridine.
C. More intact sulfasalazine, more 5-ASA, and less sulfapyridine (Why this does not fit)
Cleavage releases the two linked products in the same reaction. The preparation supplies no separate process that generates additional 5-ASA despite reduced cleavage. Distinguish formation of a product from later absorption or metabolism.
Reasoning steps for option C
Can the inhibited azo-cleavage reaction selectively increase one free product?
Cleavage releases the two linked products in the same reaction.
Why does the proposed selective increase fail?
The preparation supplies no separate process that generates additional 5-ASA despite reduced cleavage.
Why cannot less azo cleavage selectively raise free 5-ASA while sulfapyridine falls?
Both free 5-ASA and sulfapyridine arise from the same inhibited azo cleavage; without another source, free 5-ASA cannot selectively rise as sulfapyridine falls.
D. Less intact sulfasalazine, less 5-ASA, and more sulfapyridine (Why this does not fit)
Its formation from sulfasalazine still requires splitting the shared bond. Azoreductase inhibition decreases formation rather than increasing sulfapyridine. Keep the shared chemical source of the two products in view.
Reasoning steps for option D
What does selective sulfapyridine appearance require?
Its formation from sulfasalazine still requires splitting the shared bond.
What happens to that source under the stated intervention?
Azoreductase inhibition decreases formation rather than increasing sulfapyridine.
Why cannot inhibition of the shared azo cleavage increase free sulfapyridine?
The inhibited shared azo cleavage is the source of sulfapyridine as well as 5-ASA, so sulfapyridine formation decreases rather than increasing.
E. Unchanged intact sulfasalazine, unchanged 5-ASA, and unchanged sulfapyridine (Why this does not fit)
They could remain unchanged if the inhibited enzyme were irrelevant to release. No. It mediates the reaction whose products are being measured. Do not confuse pH-dependent mesalamine delivery with azo-linked sulfasalazine activation.
Reasoning steps for option E
When would unchanged products be plausible?
They could remain unchanged if the inhibited enzyme were irrelevant to release.
Is azoreductase irrelevant in the supplied preparation?
No. It mediates the reaction whose products are being measured.
Why should the parent and product levels change despite unchanged pH and incubation time?
Because azoreductase drives the measured cleavage, inhibiting it changes parent and product amounts even though pH, incubation time and drug concentration remain fixed.
Takeaway: The azo bond is a delivery mechanism requiring bacterial activation, not simple tablet dissolution.
A. Crush the delayed-release tablets and mix the powder with yogurt (Why this does not fit)
It reduces the size of the solid preparation. It would disrupt a tablet designed to remain intact until its specified release conditions. Swallowing convenience must not defeat a formulation's delivery system.
Reasoning steps for option A
Why does crushing make a tablet easier to swallow?
It reduces the size of the solid preparation.
What important feature would it disrupt here?
It would disrupt a tablet designed to remain intact until its specified release conditions.
Why does crushing the intact delayed-release 1.2-g tablet sacrifice its release control?
Crushing the delayed-release 1.2-g mesalamine tablet disrupts its specified intact release system despite making it easier to swallow.
B. Split the delayed-release tablets before each scheduled dose (Why this does not fit)
Smaller pieces may be easier to swallow. The specified delayed-release tablets must not be split or crushed. Apply the actual product instructions rather than a general rule about tablets.
Reasoning steps for option B
What advantage might tablet splitting offer?
Smaller pieces may be easier to swallow.
Why is that unsuitable for this product?
The specified delayed-release tablets must not be split or crushed.
Why is splitting this specifically labeled delayed-release mesalamine tablet unsuitable?
This delayed-release product must remain intact; splitting its tablets may ease swallowing but violates its administration instructions.
C. Dissolve the delayed-release tablets fully before taking them (Why this does not fit)
It would eliminate the need to swallow an intact tablet. The intact coating and matrix are part of the prescribed release system. Do not replace controlled intestinal release with unvalidated predissolution.
Reasoning steps for option C
What would dissolving the tablet accomplish?
It would eliminate the need to swallow an intact tablet.
Why would that be a delivery problem?
The intact coating and matrix are part of the prescribed release system.
Why does predissolving the tablet defeat its intended intestinal release?
Predissolving the delayed-release tablet destroys the intact coating and matrix needed for its prescribed release pattern.
D. Switch to capsules permitting sprinkling of intact release particles (Best answer)
The capsule can be opened and its contents placed on an approved soft food. The controlled-release particles must not be crushed or chewed, and the full mixture is taken as directed. Change to a compatible formulation under supervision rather than damaging the current delivery system.
Reasoning steps for option D
What does the compatible capsule instruction allow?
The capsule can be opened and its contents placed on an approved soft food.
Which part must remain intact?
The controlled-release particles must not be crushed or chewed, and the full mixture is taken as directed.
Which portion of the sprinkle-compatible capsule must stay intact on soft food?
The alternative capsule may be opened onto approved soft food, but its controlled-release particles must remain uncrushed and unchewed and the full mixture taken as directed.
E. Chew the alternative capsule contents thoroughly with soft food (Why this does not fit)
It could make the swallowed material feel finer. Its particles must not be crushed or chewed despite permission to open the capsule. Opening a capsule and destroying its release particles are different actions.
Reasoning steps for option E
Why might someone propose chewing the particles?
It could make the swallowed material feel finer.
What does the alternative product still require?
Its particles must not be crushed or chewed despite permission to open the capsule.
Why is chewing sprinkled controlled-release particles different from opening their capsule?
Opening the compatible capsule is permitted, but chewing its controlled-release particles damages the very delivery system that must remain intact.
Takeaway: Change to a compatible formulation under supervision rather than damaging the current delivery system.
A. Folate depletion causing impaired red-cell production (Why this does not fit)
It can cause macrocytic anemia with an inadequate reticulocyte response. Reticulocytes are increased and the bilirubin-haptoglobin pattern supports red-cell destruction. Distinguish impaired production from hemolysis before attributing anemia to folate.
Reasoning steps for option A
What pattern can folate deficiency produce?
It can cause macrocytic anemia with an inadequate reticulocyte response.
What feature instead indicates brisk red-cell replacement here?
Reticulocytes are increased and the bilirubin-haptoglobin pattern supports red-cell destruction.
Why do reticulocytes of 9% and low haptoglobin argue against folate-related underproduction?
Reticulocytes at 9% show brisk replacement, and low haptoglobin with high indirect bilirubin supports hemolysis rather than folate-related impaired production.
B. Immune red-cell destruction driven by antibody binding (Why this does not fit)
It can produce anemia with reticulocytosis and biochemical hemolysis. The antiglobulin test is negative and a known oxidant susceptibility is paired with recent sulfasalazine exposure. Use the immune test and exposure context to distinguish hemolysis mechanisms.
Reasoning steps for option B
What can antibody-mediated hemolysis produce?
It can produce anemia with reticulocytosis and biochemical hemolysis.
Which supplied findings favor another cause?
The antiglobulin test is negative and a known oxidant susceptibility is paired with recent sulfasalazine exposure.
How do a negative antiglobulin test and G6PD deficiency distinguish this from immune hemolysis?
A negative direct antiglobulin test weighs against antibody-mediated hemolysis, while recent sulfasalazine exposure in G6PD deficiency supports oxidative injury.
C. Oxidative red-cell injury in a susceptible host (Best answer)
Together they support hemolysis rather than deficient production. G6PD deficiency increases susceptibility to sulfasalazine-associated oxidative hemolysis. A falling hemoglobin during sulfasalazine needs mechanism-specific assessment and prompt drug review.
Reasoning steps for option C
What do reticulocytosis, indirect bilirubin, and low haptoglobin indicate?
Together they support hemolysis rather than deficient production.
What links this pattern to the new medicine?
G6PD deficiency increases susceptibility to sulfasalazine-associated oxidative hemolysis.
How does recent sulfasalazine exposure explain dark urine and hemolysis in G6PD deficiency?
Sulfasalazine exposure in a G6PD-deficient patient can precipitate oxidative hemolysis, explaining the rapid hemoglobin fall, dark urine, reticulocytosis and destruction markers. The falling hemoglobin warrants prompt drug review.
D. Suppression of multiple marrow cell lines by the drug (Why this does not fit)
It would tend to reduce production and may affect more than one cell line. Reticulocytes are high, other counts are normal, and biochemical markers indicate destruction. Interpret the whole blood-count pattern rather than grouping every drug-associated anemia together.
Reasoning steps for option D
What pattern would broad marrow suppression suggest?
It would tend to reduce production and may affect more than one cell line.
What evidence argues against that explanation here?
Reticulocytes are high, other counts are normal, and biochemical markers indicate destruction.
Why do high reticulocytes and normal other cell counts oppose multilineage marrow suppression?
High reticulocytes demonstrate active marrow response, and normal white cells and platelets oppose broad marrow suppression; bilirubin and haptoglobin indicate red-cell destruction.
E. Continued colonic blood loss causing iron depletion (Why this does not fit)
It can produce anemia and eventual iron depletion. The indirect hyperbilirubinemia and low haptoglobin indicate hemolysis in this oxidant-susceptible patient. Prefer the mechanism that explains the discriminating laboratory pattern.
Reasoning steps for option E
Can gastrointestinal blood loss lower hemoglobin?
It can produce anemia and eventual iron depletion.
What is not explained by blood loss alone?
The indirect hyperbilirubinemia and low haptoglobin indicate hemolysis in this oxidant-susceptible patient.
Why do indirect bilirubin elevation and depleted haptoglobin favor hemolysis over intestinal blood loss?
Blood loss alone does not explain high indirect bilirubin and low haptoglobin, which identify hemolysis in this G6PD-deficient patient after sulfasalazine exposure.
Takeaway: A falling hemoglobin during sulfasalazine needs mechanism-specific assessment and prompt drug review.
A. Accelerated oxidative destruction of mature red cells (Why this does not fit)
It would produce biochemical evidence of red-cell destruction and, with an intact marrow, reticulocytosis. Reticulocytes are low, hemolysis markers are normal, and folate is deficient. Use the production-versus-destruction distinction before assigning a sulfasalazine adverse effect.
Reasoning steps for option A
What would oxidant hemolysis usually produce?
It would produce biochemical evidence of red-cell destruction and, with an intact marrow, reticulocytosis.
Which findings oppose that explanation here?
Reticulocytes are low, hemolysis markers are normal, and folate is deficient.
Why do low reticulocytes and normal hemolysis markers oppose oxidative red-cell destruction?
Oxidative hemolysis would raise destruction markers and usually reticulocytes; here both bilirubin and haptoglobin are normal, reticulocytes are low, and folate is deficient.
B. Impaired intrinsic-factor secretion causing cobalamin deficiency (Why this does not fit)
It can produce macrocytosis and impaired DNA synthesis. Vitamin B12 and methylmalonic acid are normal while folate is low. Distinguish the deficient nutrient rather than treating all macrocytosis as vitamin B12 deficiency.
Reasoning steps for option B
What can cobalamin deficiency produce?
It can produce macrocytosis and impaired DNA synthesis.
What laboratory evidence makes it less likely here?
Vitamin B12 and methylmalonic acid are normal while folate is low.
Why do normal B12 and methylmalonic acid argue against cobalamin deficiency here?
Normal vitamin B12 and methylmalonic acid oppose cobalamin deficiency, whereas measured low folate explains impaired DNA synthesis and macrocytosis.
C. Chronic mucosal blood loss causing depleted iron stores (Why this does not fit)
It tends toward iron-restricted production and eventual microcytosis. Marked macrocytosis with low folate is present without active bleeding or a hemolytic pattern. Identify the demonstrated nutrient problem rather than assuming every UC-associated anemia is blood loss.
Reasoning steps for option C
What is the usual anemia pattern from sustained iron depletion?
It tends toward iron-restricted production and eventual microcytosis.
What pattern is actually supplied?
Marked macrocytosis with low folate is present without active bleeding or a hemolytic pattern.
Why does MCV 113 fL with low folate oppose iron depletion from chronic bleeding?
Iron loss generally leads toward microcytosis, but this patient has MCV 113 fL, low folate and no active bleeding or hemolytic evidence.
D. Drug-dependent antibody binding causing immune hemolysis (Why this does not fit)
It would increase destruction and commonly produce hemolysis markers. Low reticulocytes with normal haptoglobin and indirect bilirubin favor impaired production. A medication can cause different anemia mechanisms; the laboratory pattern determines which is supported.
Reasoning steps for option D
How would immune destruction affect red-cell turnover?
It would increase destruction and commonly produce hemolysis markers.
Which measurements favor a production problem instead?
Low reticulocytes with normal haptoglobin and indirect bilirubin favor impaired production.
Why do normal haptoglobin and indirect bilirubin argue against immune hemolysis?
Immune hemolysis would show increased red-cell destruction; low reticulocytes with normal bilirubin and haptoglobin instead favor impaired production.
E. Impaired folate absorption causing reduced nucleotide synthesis (Best answer)
It can impair folate absorption and contribute to deficiency. Impaired nucleotide synthesis explains macrocytosis and a weak reticulocyte response with low folate and no evidence of hemolysis. Evaluate and correct folate deficiency without overlooking other causes or broader marrow toxicity.
Reasoning steps for option E
What effect can sulfasalazine have on folate?
It can impair folate absorption and contribute to deficiency.
How does deficiency fit the measured blood pattern?
Impaired nucleotide synthesis explains macrocytosis and a weak reticulocyte response with low folate and no evidence of hemolysis.
How does sulfasalazine-related folate malabsorption explain macrocytosis and low reticulocytes?
Sulfasalazine can impair folate absorption; low folate reduces nucleotide synthesis, producing MCV 113 fL and a weak reticulocyte response without hemolysis, while other causes or broader marrow toxicity still merit assessment.
Takeaway: Evaluate and correct folate deficiency without overlooking other causes or broader marrow toxicity.
A. Arrange a mesalamine substitution and repeat the fertility assessment (Best answer)
Reduced sperm count and quality can be drug related and often improve after withdrawal. An appropriate mesalamine regimen can retain 5-ASA treatment while ending the sulfasalazine carrier exposure. Use a supervised substitution and reassessment rather than promising that fertility will normalize.
Reasoning steps for option A
What adverse effect is well described with sulfasalazine?
Reduced sperm count and quality can be drug related and often improve after withdrawal.
How can bowel treatment continue without sulfapyridine?
An appropriate mesalamine regimen can retain 5-ASA treatment while ending the sulfasalazine carrier exposure.
Why can switching from sulfasalazine to mesalamine preserve UC control while assessing sperm recovery?
An appropriate mesalamine regimen can maintain 5-ASA treatment while removing sulfasalazine-associated carrier exposure; reassess sperm count and motility without promising recovery.
B. Change to enteric-coated sulfasalazine and repeat the fertility assessment (Why this does not fit)
It changes the timing of gastric disintegration. The azo-linked drug still generates sulfapyridine, so the suspected carrier-related problem is not eliminated. A coating change is not equivalent to a change in the active delivery compound.
Reasoning steps for option B
What does enteric coating change?
It changes the timing of gastric disintegration.
What relevant exposure remains after the change?
The azo-linked drug still generates sulfapyridine, so the suspected carrier-related problem is not eliminated.
Why will enteric coating not eliminate exposure to sulfasalazine-derived sulfapyridine?
Enteric coating changes disintegration timing but does not remove the azo-linked compound that generates sulfapyridine and may contribute to the sperm changes.
C. Replace sulfasalazine with prednisone and continue long-term maintenance (Why this does not fit)
It can induce remission when appropriate. Corticosteroids are not maintenance treatment, and a suitable 5-ASA alternative can preserve disease control. Do not trade a potentially reversible adverse effect for inappropriate chronic steroid therapy.
Reasoning steps for option C
What can prednisone accomplish in active UC?
It can induce remission when appropriate.
Why does that not fit sustained remission here?
Corticosteroids are not maintenance treatment, and a suitable 5-ASA alternative can preserve disease control.
Why is long-term prednisone inappropriate for UC in remission during fertility evaluation?
Prednisone may induce active UC remission but is not suitable long-term maintenance for a patient already in remission who can use a 5-ASA alternative.
D. Add testosterone while retaining the current sulfasalazine regimen (Why this does not fit)
It would require evaluation showing an endocrine indication. Gonadotropins and testosterone are normal while a relevant medication exposure is present. Address the supported cause rather than treating a low sperm count as automatic androgen deficiency.
Reasoning steps for option D
When would an endocrine treatment require a specific rationale?
It would require evaluation showing an endocrine indication.
What findings fail to establish that indication here?
Gonadotropins and testosterone are normal while a relevant medication exposure is present.
Why do normal gonadotropins and testosterone not support adding testosterone for low sperm count?
Normal testosterone and gonadotropins do not establish an androgen deficiency indication; first address the plausible sulfasalazine-related sperm changes.
E. Stop UC medication and repeat the fertility assessment after relapse (Why this does not fit)
It could help assess whether the medicine contributes to the fertility findings. Effective bowel treatment can be maintained with an appropriate alternative instead of leaving UC untreated. Preserve disease control while assessing a suspected reversible adverse effect.
Reasoning steps for option E
What could stopping sulfasalazine clarify?
It could help assess whether the medicine contributes to the fertility findings.
Why is waiting for relapse an inappropriate way to do that?
Effective bowel treatment can be maintained with an appropriate alternative instead of leaving UC untreated.
Why should UC treatment continue with an alternative instead of waiting for relapse after stopping medication?
Stopping all UC therapy until relapse risks avoidable disease recurrence when an appropriate mesalamine substitution can preserve control during fertility reassessment.
Takeaway: Use a supervised substitution and reassessment rather than promising that fertility will normalize.
A. Continue the dose and review the CBC at the scheduled visit (Why this does not fit)
It checks for toxicity at planned intervals in a stable patient. New fever and sore throat can signal infection or serious blood toxicity and need prompt assessment. A warning symptom overrides the routine monitoring calendar.
Reasoning steps for option A
What does routine monitoring accomplish?
It checks for toxicity at planned intervals in a stable patient.
Why is the next scheduled visit insufficient now?
New fever and sore throat can signal infection or serious blood toxicity and need prompt assessment.
Why does a ten-day wait for the planned CBC fail to address fever and sore throat today?
Fever and sore throat require urgent CBC and infection assessment, not a ten-day wait.
B. Halve the dose and wait for the fever to resolve (Why this does not fit)
It may help uncomplicated dose-related tolerability problems. Fever and sore throat can reflect a serious blood disorder or infection, not simple nausea. Do not manage possible marrow toxicity as ordinary dose intolerance.
Reasoning steps for option B
When can dose reduction help?
It may help uncomplicated dose-related tolerability problems.
Why does this presentation require a different response?
Fever and sore throat can reflect a serious blood disorder or infection, not simple nausea.
Why is halving sulfasalazine inadequate when a new sore throat could herald neutropenia?
Possible marrow toxicity is not uncomplicated dose intolerance; halving the drug and waiting is unsafe.
C. Use an enteric-coated product while awaiting blood results (Why this does not fit)
It may reduce selected gastric irritation. It still exposes the patient to sulfasalazine and its metabolites. Changing gastric disintegration does not make continued exposure safe during evaluation of serious toxicity.
Reasoning steps for option C
What problem might an enteric coating address?
It may reduce selected gastric irritation.
Would it prevent the suspected hematologic risk?
It still exposes the patient to sulfasalazine and its metabolites.
Would enteric coating remove the potential hematologic danger behind this febrile presentation?
No; coating changes gastric disintegration, not the serious risk of continued exposure.
D. Hold sulfasalazine for urgent CBC and infection assessment (Best answer)
Fever and sore throat can accompany a blood disorder, including neutropenia with infection. A normal baseline count and absent rash do not exclude a new serious reaction; the label advises stopping while relevant blood tests are pending. Promptly assess warning symptoms during treatment rather than relying on a previous normal test.
Reasoning steps for option D
What serious possibility links the new symptoms to sulfasalazine?
Fever and sore throat can accompany a blood disorder, including neutropenia with infection.
Why not await the next routine visit or require a rash?
A normal baseline count and absent rash do not exclude a new serious reaction; the label advises stopping while relevant blood tests are pending.
What immediate medication and diagnostic response is warranted before the pending CBC returns?
Hold sulfasalazine and urgently assess CBC and infection despite the normal baseline result.
E. Continue treatment and add folic acid before repeating the CBC (Why this does not fit)
It can address folate deficiency risk associated with sulfasalazine. It does not evaluate fever, possible infection, or neutropenia. Folate support does not replace evaluation for blood toxicity.
Reasoning steps for option E
What risk can folate supplementation address?
It can address folate deficiency risk associated with sulfasalazine.
Does it address the urgent differential here?
It does not evaluate fever, possible infection, or neutropenia.
Can adding folate establish that this febrile patient has no acute blood-count abnormality?
No; folate does not rule out acute cytopenia or replace urgent assessment.
Takeaway: Promptly assess warning symptoms during treatment rather than relying on a previous normal test.
A. Dose-related gastric intolerance; reduce the daily sulfasalazine dose (Why this does not fit)
Nausea and headache can occur with dose-related sulfapyridine exposure. Facial edema, lymphadenopathy, eosinophilia, and liver injury indicate a systemic process. Do not treat organ injury as an ordinary titration problem.
Reasoning steps for option A
What symptoms can uncomplicated dose intolerance cause?
Nausea and headache can occur with dose-related sulfapyridine exposure.
What findings are not explained by that benign pattern?
Facial edema, lymphadenopathy, eosinophilia, and liver injury indicate a systemic process.
How do ALT 470 U/L and eosinophilia distinguish this illness from dose-related nausea?
ALT 470 and eosinophilia with fever and rash imply systemic injury, not simple nausea.
B. Systemic drug hypersensitivity; stop the drug and obtain urgent care (Best answer)
A delayed febrile eruption with facial edema, lymphadenopathy, eosinophilia, and hepatic injury fits that pattern. Stop the suspected medicine and urgently assess organ involvement rather than continuing exposure. Multisystem findings after a new drug require a safety response, not an empiric lower dose.
Reasoning steps for option B
What pattern supports a systemic hypersensitivity syndrome?
A delayed febrile eruption with facial edema, lymphadenopathy, eosinophilia, and hepatic injury fits that pattern.
How should suspected sulfasalazine involvement affect immediate treatment?
Stop the suspected medicine and urgently assess organ involvement rather than continuing exposure.
What do fever, facial edema, rash, eosinophilia, and hepatitis together demand after a new sulfasalazine exposure?
Stop sulfasalazine and urgently evaluate suspected multisystem hypersensitivity.
C. Isolated contact dermatitis; continue sulfasalazine with topical therapy (Why this does not fit)
It can explain a skin eruption limited to an exposure pattern. Systemic fever, eosinophilia, lymphadenopathy, and liver injury accompany the generalized eruption. A skin finding with systemic organ abnormalities is not an isolated dermatologic complaint.
Reasoning steps for option C
What would localized contact dermatitis usually explain?
It can explain a skin eruption limited to an exposure pattern.
What makes that explanation inadequate here?
Systemic fever, eosinophilia, lymphadenopathy, and liver injury accompany the generalized eruption.
Why does cervical lymphadenopathy plus hepatitis rule against treating the rash as contact dermatitis alone?
Lymphadenopathy and hepatitis accompanying rash preclude treating it as isolated dermatitis.
D. Active colonic inflammation; increase the sulfasalazine induction dose (Why this does not fit)
It can produce bleeding, diarrhea, and systemic inflammatory illness when severe. The new drug precedes facial edema, a generalized rash, eosinophilia, and hepatic injury. Do not escalate the suspected medicine when its toxicity better explains the new syndrome.
Reasoning steps for option D
What symptoms can active UC produce?
It can produce bleeding, diarrhea, and systemic inflammatory illness when severe.
What temporal and laboratory pattern points elsewhere?
The new drug precedes facial edema, a generalized rash, eosinophilia, and hepatic injury.
Why do new eosinophilia and facial edema argue against increasing sulfasalazine for presumed colitis?
Eosinophilia and facial edema alongside rash and hepatitis suggest drug hypersensitivity, not colitis requiring more sulfasalazine.
E. Carrier-related folate depletion; continue treatment with folate support (Why this does not fit)
It can impair blood-cell production and produce macrocytosis. It does not explain the febrile rash, facial edema, lymphadenopathy, and acute hepatic injury. Choose the syndrome explaining the full pattern before selecting supportive treatment.
Reasoning steps for option E
What consequence can folate depletion cause?
It can impair blood-cell production and produce macrocytosis.
Does that account for this presentation?
It does not explain the febrile rash, facial edema, lymphadenopathy, and acute hepatic injury.
Does folate depletion explain the simultaneous fever, rash, eosinophilia, and liver injury?
No; folate depletion does not explain fever, rash, eosinophilia, edema and hepatitis.
Takeaway: Multisystem findings after a new drug require a safety response, not an empiric lower dose.
A. Inadequate treatment intensity; increase the mesalamine dose (Why this does not fit)
It may help an appropriate patient who has inadequate exposure or persistent inflammatory disease. New systemic and intestinal symptoms began soon after exposure and fit mesalamine acute intolerance. Consider treatment-induced worsening before increasing the suspected medicine.
Reasoning steps for option A
When can a higher dose help?
It may help an appropriate patient who has inadequate exposure or persistent inflammatory disease.
What important alternative does immediate escalation neglect here?
New systemic and intestinal symptoms began soon after exposure and fit mesalamine acute intolerance.
Why is escalating mesalamine risky when bloody cramps and fever appeared five days after initiation?
Abrupt cramps, bloody diarrhea and fever five days after initiation suggest intolerance; increasing the suspected drug risks worsening it.
B. Insufficient distal delivery; add a higher-dose rectal preparation (Why this does not fit)
It can address a demonstrated distal coverage gap in UC. Headache and fever accompany abrupt worsening shortly after the medicine starts. A delivery explanation should not displace evaluation for acute intolerance.
Reasoning steps for option B
When does additional rectal treatment help?
It can address a demonstrated distal coverage gap in UC.
What new findings are not explained by location alone?
Headache and fever accompany abrupt worsening shortly after the medicine starts.
What feature makes an anatomic coverage adjustment less compelling than acute drug intolerance here?
Early systemic symptoms and worsening despite confirmed dosing favor intolerance over an isolated distal delivery gap.
C. Sulfapyridine accumulation; use an enteric-coated sulfasalazine product (Why this does not fit)
Sulfasalazine, not mesalamine itself, generates that carrier. The patient has received mesalamine without sulfapyridine, and adding sulfasalazine would not resolve the suspected shared 5-ASA intolerance. Identify the actual compound before attributing an adverse effect to its carrier.
Reasoning steps for option C
Which medicine generates sulfapyridine?
Sulfasalazine, not mesalamine itself, generates that carrier.
Why does the proposed explanation fail here?
The patient has received mesalamine without sulfapyridine, and adding sulfasalazine would not resolve the suspected shared 5-ASA intolerance.
Which medication generates sulfapyridine, and is this patient taking it?
Sulfapyridine comes from sulfasalazine, not the mesalamine this patient takes.
D. Unrecognized bacterial infection; continue mesalamine with empiric antibiotics (Why this does not fit)
Infection can produce diarrhea and fever in a patient with UC. Testing is negative and the close exposure relationship with headache and intestinal worsening supports acute intolerance. Evaluate infection without overlooking a temporally plausible treatment reaction.
Reasoning steps for option D
Why is infection an important competing diagnosis?
Infection can produce diarrhea and fever in a patient with UC.
What supports another immediate medication concern in this case?
Testing is negative and the close exposure relationship with headache and intestinal worsening supports acute intolerance.
How do negative stool pathogen and C. difficile tests affect empiric antibiotic justification?
Negative pathogen and C. difficile tests weaken empiric antibiotic rationale; evaluate the temporally plausible reaction.
E. Mesalamine acute intolerance; withhold the drug and reassess (Best answer)
Mesalamine acute intolerance can cause cramps, bloody diarrhea, fever, and headache. Symptoms worsened soon after exposure despite initial improvement, with no demonstrated infection or dosing gap. When acute intolerance is suspected, stop mesalamine and assess alternatives rather than automatically escalating it.
Reasoning steps for option E
What syndrome can mimic a UC flare after mesalamine begins?
Mesalamine acute intolerance can cause cramps, bloody diarrhea, fever, and headache.
What makes it important to address before escalation here?
Symptoms worsened soon after exposure despite initial improvement, with no demonstrated infection or dosing gap.
What does early worsening after initial improvement suggest despite confirmed dosing and negative infection tests?
Early worsening despite initial improvement and confirmed exposure suggests acute intolerance; withhold mesalamine and reassess.
Takeaway: When acute intolerance is suspected, stop mesalamine and assess alternatives rather than automatically escalating it.
A. Continue mesalamine and repeat renal tests at the annual visit (Why this does not fit)
They can detect toxicity even when bowel symptoms are controlled. Renal function has already deteriorated substantially during treatment. An abnormal surveillance result requires action rather than another routine interval.
Reasoning steps for option A
Why are periodic renal tests used?
They can detect toxicity even when bowel symptoms are controlled.
What makes routine delayed follow-up inadequate now?
Renal function has already deteriorated substantially during treatment.
Why is waiting until the annual renal review unsafe after creatinine rises from 0.8 to 2.0?
Creatinine rose from 0.8 to 2.0 during exposure; annual follow-up delays needed renal evaluation.
B. Lower the oral dose and defer evaluation until symptoms appear (Why this does not fit)
It can occur without an obvious rash or symptomatic change. The creatinine change is objective evidence of current injury, and dose reduction alone does not address its cause. Do not require a classic hypersensitivity presentation before acting on renal deterioration.
Reasoning steps for option B
Can kidney injury be clinically silent?
It can occur without an obvious rash or symptomatic change.
Why is waiting for symptoms inappropriate here?
The creatinine change is objective evidence of current injury, and dose reduction alone does not address its cause.
Does absence of rash or eosinophilia make the current renal decline safe to observe on a lower dose?
No; renal injury need not cause rash or eosinophilia, so a lower dose with deferred assessment is unsafe.
C. Stop mesalamine and promptly assess the renal injury (Best answer)
Mesalamine-associated interstitial nephritis belongs in the differential of this renal decline. Stop it while promptly evaluating the injury; sterile pyuria supports concern but does not by itself prove the cause. Renal deterioration warrants drug review and assessment without assuming that absent rash excludes nephritis.
Reasoning steps for option C
What medication-related diagnosis belongs in the differential?
Mesalamine-associated interstitial nephritis belongs in the differential of this renal decline.
How should the drug be handled before the diagnosis is fully established?
Stop it while promptly evaluating the injury; sterile pyuria supports concern but does not by itself prove the cause.
What should happen to the suspected mesalamine while sterile pyuria and rising creatinine are assessed?
Stop mesalamine and promptly assess renal injury and competing causes.
D. Replace oral mesalamine with a rectal mesalamine regimen (Why this does not fit)
The delivery route and degree of absorption change. The active molecule remains mesalamine, and rectal products also carry renal precautions. A route change is not a safe default response to suspected toxicity from the shared molecule.
Reasoning steps for option D
What exposure changes with a rectal preparation?
The delivery route and degree of absorption change.
Why does the substitution not eliminate the suspected risk?
The active molecule remains mesalamine, and rectal products also carry renal precautions.
Would rectal delivery remove exposure to the 5-ASA molecule implicated in renal injury?
No; rectal mesalamine still exposes the patient to the suspected molecule.
E. Start antibiotics for urinary leukocytes while retaining mesalamine (Why this does not fit)
They can occur with infection or noninfectious interstitial inflammation. Culture is negative, obstruction is absent, and a marked creatinine rise requires a renal differential. Pyuria is a finding to interpret, not a diagnosis that cancels drug-related renal risk.
Reasoning steps for option E
What can urinary leukocytes suggest?
They can occur with infection or noninfectious interstitial inflammation.
What evidence does not support treating this as an uncomplicated urinary infection?
Culture is negative, obstruction is absent, and a marked creatinine rise requires a renal differential.
Why does culture-negative pyuria not by itself justify antibiotics instead of renal assessment?
Culture-negative pyuria does not establish bacterial infection; assess it with the creatinine rise and drug exposure.
Takeaway: Renal deterioration warrants drug review and assessment without assuming that absent rash excludes nephritis.
A. Withhold mesalamine and evaluate and treat acute pancreatitis (Best answer)
Characteristic persistent pain with lipase more than three times the upper limit supports acute pancreatitis. Mesalamine-associated pancreatitis is reported, and its recent introduction warrants withholding it while other causes and the acute illness are assessed. Recognize the organ-specific syndrome and consider the drug without declaring the temporal association definitive.
Reasoning steps for option A
What do the pain pattern and lipase result indicate?
Characteristic persistent pain with lipase more than three times the upper limit supports acute pancreatitis.
Why is the new medication relevant without proving causation?
Mesalamine-associated pancreatitis is reported, and its recent introduction warrants withholding it while other causes and the acute illness are assessed.
What do back-radiating epigastric pain and lipase more than ten times the upper limit require?
Characteristic pain and markedly elevated lipase warrant withholding mesalamine and assessing and treating pancreatitis without assuming definitive causation.
B. Increase mesalamine to treat a presumed intestinal flare (Why this does not fit)
It can cause intestinal pain and increased bloody diarrhea. The marked lipase increase and characteristic epigastric pain support pancreatitis while intestinal bleeding is improving. Do not intensify the suspected drug when a different acute syndrome is present.
Reasoning steps for option B
What can a UC flare cause?
It can cause intestinal pain and increased bloody diarrhea.
What finding directs attention to another organ?
The marked lipase increase and characteristic epigastric pain support pancreatitis while intestinal bleeding is improving.
Why does improved intestinal bleeding argue against treating this pain as an intestinal flare?
Bleeding improved, while back-radiating pain and high lipase indicate pancreatic rather than escalating colonic disease.
C. Use rectal mesalamine while continuing the pancreatitis workup (Why this does not fit)
It can alter the main delivery site. The same active molecule remains present during evaluation of a potentially serious adverse effect. Changing route does not automatically eliminate molecule-related toxicity.
Reasoning steps for option C
What can rectal treatment change?
It can alter the main delivery site.
Why is it not the best way to address a suspected mesalamine reaction?
The same active molecule remains present during evaluation of a potentially serious adverse effect.
Can changing to rectal mesalamine rule out toxicity involving the same active molecule?
No; rectal mesalamine retains exposure to the same molecule.
D. Reduce the mesalamine dose and observe for routine nausea (Why this does not fit)
It can cause nausea or nonspecific gastrointestinal discomfort. Persistent radiating pain and markedly increased lipase indicate an acute pancreatic syndrome. Organ-specific findings require appropriate acute assessment, not simple tolerability adjustment.
Reasoning steps for option D
What can uncomplicated intolerance cause?
It can cause nausea or nonspecific gastrointestinal discomfort.
What prevents treating this episode as uncomplicated nausea?
Persistent radiating pain and markedly increased lipase indicate an acute pancreatic syndrome.
Which objective finding makes a routine nausea dose adjustment inappropriate?
Lipase 690 with characteristic pain and vomiting is not ordinary nausea; assess pancreatitis.
E. Add budesonide MMX while retaining mesalamine for colitis (Why this does not fit)
It can induce remission in suitable UC after 5-ASA nonresponse. The new problem is pancreatitis with improving intestinal bleeding, not demonstrated colonic nonresponse. Choose treatment for the demonstrated syndrome rather than automatically escalating UC therapy.
Reasoning steps for option E
When can budesonide MMX be useful?
It can induce remission in suitable UC after 5-ASA nonresponse.
What does that strategy fail to address here?
The new problem is pancreatitis with improving intestinal bleeding, not demonstrated colonic nonresponse.
Would adding colitis induction therapy address the demonstrated pancreatic syndrome?
No; budesonide MMX does not address the demonstrated pancreatic syndrome.
Takeaway: Recognize the organ-specific syndrome and consider the drug without declaring the temporal association definitive.
A. Check only a CBC because the added risk is principally marrow suppression (Why this does not fit)
A thiopurine or another marrow-toxic medicine raises that concern. Ibuprofen is a nephrotoxic coexposure in a patient with pre-existing renal impairment. Match the surveillance test to the actual interacting exposure.
Reasoning steps for option A
What combination especially raises a blood-monitoring concern with mesalamine?
A thiopurine or another marrow-toxic medicine raises that concern.
Which risk is added by the medicine in this case?
Ibuprofen is a nephrotoxic coexposure in a patient with pre-existing renal impairment.
Which organ needs surveillance after frequent ibuprofen is added to mesalamine in chronic kidney disease?
Renal function, not just CBC, needs reassessment after ibuprofen is added to mesalamine in CKD.
B. Review NSAID use and arrange renal reassessment with follow-up (Best answer)
The patient already has chronic kidney disease. It adds nephrotoxic exposure to mesalamine, so medication review and renal reassessment are warranted. Renal risk depends on comorbidity and co-medications as well as the 5-ASA prescription.
Reasoning steps for option B
What baseline feature increases the need for renal caution?
The patient already has chronic kidney disease.
How does repeated ibuprofen change the assessment?
It adds nephrotoxic exposure to mesalamine, so medication review and renal reassessment are warranted.
How do eGFR 43 and repeated NSAID doses change the urgency of renal medication review?
eGFR 43 plus frequent NSAIDs warrants reviewing ibuprofen and arranging timely renal testing.
C. Change to a suppository and retain the existing renal testing schedule (Why this does not fit)
It can reduce or redistribute exposure depending on the product and patient. Rectal mesalamine still requires renal monitoring, and the NSAID remains a nephrotoxic exposure. A route change cannot substitute for review of a new renal risk.
Reasoning steps for option C
What might rectal administration change?
It can reduce or redistribute exposure depending on the product and patient.
Why does it not eliminate the new safety issue?
Rectal mesalamine still requires renal monitoring, and the NSAID remains a nephrotoxic exposure.
Why would a suppository switch not resolve the need to reassess renal function after NSAID initiation?
A suppository does not eliminate renal exposure or obviate reassessment after NSAID initiation.
D. Increase fluid intake and wait for a rash before ordering renal tests (Why this does not fit)
Adequate hydration is advised with mesalamine treatment. Drug-associated renal injury need not produce a rash, and combined renal risks are already present. Do not require a skin reaction before assessing possible kidney injury.
Reasoning steps for option D
Why is hydration relevant?
Adequate hydration is advised with mesalamine treatment.
Why is hydration alone inadequate as the monitoring plan?
Drug-associated renal injury need not produce a rash, and combined renal risks are already present.
Is a rash necessary before checking creatinine in a patient with new combined nephrotoxic exposure?
No; renal injury need not cause rash, and the combined exposures merit kidney testing.
E. Measure sulfapyridine levels before deciding about kidney monitoring (Why this does not fit)
Sulfasalazine generates sulfapyridine; mesalamine does not. The patient receives mesalamine and ibuprofen, with a renal rather than carrier-concentration concern. Identify the actual drug exposure before choosing a monitoring measurement.
Reasoning steps for option E
What medicine generates sulfapyridine?
Sulfasalazine generates sulfapyridine; mesalamine does not.
What makes that measurement irrelevant to the supplied regimen?
The patient receives mesalamine and ibuprofen, with a renal rather than carrier-concentration concern.
Is sulfapyridine a relevant analyte for a patient taking mesalamine rather than sulfasalazine?
Sulfapyridine comes from sulfasalazine, not this mesalamine regimen; review renal risk instead.
Takeaway: Renal risk depends on comorbidity and co-medications as well as the 5-ASA prescription.
A. Reduced renal clearance is the demonstrated cause of both cytopenias (Why this does not fit)
Renal impairment changes the safety assessment and can complicate drug exposure. Creatinine is unchanged, whereas two blood-cell lines decline after a relevant combination begins. Do not substitute an unobserved renal change for a recognized blood-toxicity interaction.
Reasoning steps for option A
Why can renal function matter during mesalamine treatment?
Renal impairment changes the safety assessment and can complicate drug exposure.
What evidence for new renal impairment is provided here?
Creatinine is unchanged, whereas two blood-cell lines decline after a relevant combination begins.
Does unchanged creatinine support reduced renal clearance as the observed cause of both falling counts?
No; unchanged creatinine does not demonstrate reduced renal clearance; review the drug combination.
B. Folate deficiency is established by the concurrent platelet decline (Why this does not fit)
Severe deficiency can impair blood-cell production. There is no macrocytosis or supplied folate deficiency, while the new drug combination is associated with blood disorders. Do not label cytopenias as nutrient deficiency without the supporting pattern.
Reasoning steps for option B
Can folate deficiency affect more than red cells?
Severe deficiency can impair blood-cell production.
What makes it unproven as the explanation here?
There is no macrocytosis or supplied folate deficiency, while the new drug combination is associated with blood disorders.
Do leukopenia and thrombocytopenia without macrocytosis establish folate deficiency?
No; falling white cells and platelets without macrocytosis do not establish folate deficiency.
C. Normal pharmacogenetic testing excludes a medication-related blood disorder (Why this does not fit)
It assesses selected inherited risks relevant to thiopurine treatment. No. A new interacting medicine can increase blood-disorder risk despite a previously reassuring result. A normal pretreatment test does not replace ongoing blood-count monitoring.
Reasoning steps for option C
What does pretreatment pharmacogenetic testing address?
It assesses selected inherited risks relevant to thiopurine treatment.
Does it eliminate all subsequent marrow toxicity or interactions?
No. A new interacting medicine can increase blood-disorder risk despite a previously reassuring result.
Can a normal pretreatment thiopurine pharmacogenetic result exclude later cytopenias on combination therapy?
No; pretreatment pharmacogenetics cannot exclude later combination-associated cytopenias.
D. Combined mesalamine and thiopurine exposure increases marrow-toxicity risk (Best answer)
Mesalamine with azathioprine or 6-mercaptopurine can increase the risk of blood disorders. Two cell lines decline after mesalamine is added while renal function remains stable. Promptly review the combination and blood counts; inherited-risk testing does not exclude acquired toxicity.
Reasoning steps for option D
Which labeled interaction is relevant to the new regimen?
Mesalamine with azathioprine or 6-mercaptopurine can increase the risk of blood disorders.
What pattern makes it important to assess now?
Two cell lines decline after mesalamine is added while renal function remains stable.
Which newly added agent warrants interaction review alongside azathioprine after both counts fall?
Added mesalamine with azathioprine raises blood-disorder risk; promptly review medication and counts.
E. Sulfapyridine accumulation explains the decline despite unchanged renal function (Why this does not fit)
Sulfasalazine generates that compound. No sulfasalazine is supplied; the relevant exposure is mesalamine with a thiopurine. Choose the interaction based on the actual drugs rather than the broad 5-ASA category.
Reasoning steps for option E
Which drug generates sulfapyridine?
Sulfasalazine generates that compound.
Is that carrier part of this regimen?
No sulfasalazine is supplied; the relevant exposure is mesalamine with a thiopurine.
Where would sulfapyridine originate in this mesalamine-plus-azathioprine regimen?
Neither drug provides sulfapyridine, a product of sulfasalazine cleavage.
Takeaway: Promptly review the combination and blood counts; inherited-risk testing does not exclude acquired toxicity.
A. Retain both regimens unchanged until the next routine six-week INR check (Why this does not fit)
They are used when anticoagulation and relevant exposures are stable. A new drug exposure is followed by an INR outside the prior stable range. An altered anticoagulant response calls for timely review rather than an unchanged routine interval.
Reasoning steps for option A
Why are routine INR intervals used during stable treatment?
They are used when anticoagulation and relevant exposures are stable.
What has changed in this patient?
A new drug exposure is followed by an INR outside the prior stable range.
Why is a six-week routine INR interval inappropriate after the value rises from about 3.0 to 4.2?
INR rose from about 3.0 to 4.2 after sulfasalazine began; timely review supersedes a six-week interval.
B. Stop sulfasalazine and immediately return to routine INR testing intervals (Why this does not fit)
It may be appropriate after coordinated review of a suspected interaction and the UC plan. The warfarin response can change again as the co-medication is discontinued. Both starting and stopping a potentially interacting drug require anticoagulation follow-up.
Reasoning steps for option B
Why might sulfasalazine discontinuation be considered?
It may be appropriate after coordinated review of a suspected interaction and the UC plan.
Why does stopping it not end the monitoring issue immediately?
The warfarin response can change again as the co-medication is discontinued.
If sulfasalazine is stopped, can INR surveillance immediately revert to its old schedule?
No; stopping the possible interacting medicine also warrants coordinated INR follow-up.
C. Use rectal mesalamine and omit INR checks during the transition (Why this does not fit)
It could permit continued bowel treatment without sulfasalazine. Ending sulfasalazine exposure can alter anticoagulant requirements; a route substitution does not establish stable warfarin effect. Coordinate medication changes with INR reassessment rather than treating them as isolated prescriptions.
Reasoning steps for option C
What might an alternative UC regimen accomplish?
It could permit continued bowel treatment without sulfasalazine.
Why are INR checks still important during the transition?
Ending sulfasalazine exposure can alter anticoagulant requirements; a route substitution does not establish stable warfarin effect.
Does changing bowel treatment to rectal mesalamine eliminate the need to follow INR during the transition?
No; a bowel-drug change does not resolve the elevated INR or negate transition monitoring.
D. Replace warfarin with aspirin while the bowel regimen is adjusted (Why this does not fit)
A mechanical mitral valve requires an appropriate anticoagulation strategy. It abandons the required warfarin-based valve-protection plan instead of managing the abnormal anticoagulant response. Do not permanently sacrifice necessary anticoagulation to avoid an interaction review.
Reasoning steps for option D
What protection is needed for the supplied valve condition?
A mechanical mitral valve requires an appropriate anticoagulation strategy.
Why is aspirin substitution not an adequate response to this INR change?
It abandons the required warfarin-based valve-protection plan instead of managing the abnormal anticoagulant response.
What mechanical-valve risk makes replacing warfarin with aspirin inappropriate here?
A mechanical mitral valve requires effective anticoagulation; aspirin is not a substitute here.
E. Arrange medication review and closer INR checks with the treating team (Best answer)
The anticoagulant response has changed after sulfasalazine initiation and warrants review. Published reports describe both potentiation and resistance, and the patient still needs valve protection. Manage the actual INR and clinical situation with coordinated follow-up during medication changes.
Reasoning steps for option E
What is supported by the observed INR change?
The anticoagulant response has changed after sulfasalazine initiation and warrants review.
Why should the plan be individualized rather than use a fixed dose rule?
Published reports describe both potentiation and resistance, and the patient still needs valve protection.
How should the team respond to INR 4.2 without bleeding after a recent sulfasalazine start?
Coordinate medication review and closer INR testing, managing the actual value without assuming a fixed interaction direction.
Takeaway: Manage the actual INR and clinical situation with coordinated follow-up during medication changes.
A. Slower acetylation of absorbed sulfapyridine in patient X (Best answer)
It supports slower conversion of sulfapyridine to its acetylated metabolite. Higher sulfapyridine exposure with similar colonic 5-ASA and renal function fits a carrier-handling difference rather than greater local drug delivery. Interpret carrier exposure separately from intestinal 5-ASA exposure; this model does not establish a need for routine genotype testing.
Reasoning steps for option A
What does a high parent-to-acetylated-metabolite ratio suggest?
It supports slower conversion of sulfapyridine to its acetylated metabolite.
How does that fit the rest of the comparison?
Higher sulfapyridine exposure with similar colonic 5-ASA and renal function fits a carrier-handling difference rather than greater local drug delivery.
Which metabolic step could raise both sulfapyridine concentration and its ratio to acetylated metabolite?
Slower sulfapyridine acetylation raises parent concentration and parent-to-acetylated-metabolite ratio despite similar colonic 5-ASA. This comparison does not establish a need for routine genotype testing.
B. Greater bacterial cleavage of the azo bond in patient X (Why this does not fit)
It would increase generation of both free 5-ASA and sulfapyridine. Colonic 5-ASA is similar, and the specific difference is the parent-to-acetylated-sulfapyridine ratio. Separate formation of the carrier from its subsequent metabolism.
Reasoning steps for option B
What would greater cleavage tend to increase?
It would increase generation of both free 5-ASA and sulfapyridine.
What does that fail to explain as well here?
Colonic 5-ASA is similar, and the specific difference is the parent-to-acetylated-sulfapyridine ratio.
Would greater azo cleavage alone explain a higher parent-to-acetylated-metabolite ratio with similar colonic 5-ASA?
More cleavage alone does not account for the shifted metabolite ratio with similar colonic 5-ASA; subsequent metabolism does.
C. Faster renal elimination of sulfapyridine in patient X (Why this does not fit)
It would tend to lower the concentration for a comparable input. Patient X has a higher concentration despite comparable renal function. Check whether the proposed clearance change predicts the observed concentration direction.
Reasoning steps for option C
What would faster elimination usually do to plasma exposure?
It would tend to lower the concentration for a comparable input.
What is the direction of the measured difference?
Patient X has a higher concentration despite comparable renal function.
Would faster sulfapyridine renal elimination raise or lower its circulating concentration?
Faster renal elimination predicts lower, not higher, parent concentration.
D. Earlier disintegration of an enteric coating in patient X (Why this does not fit)
It can change where and when the tablet disintegrates. The sulfapyridine-to-acetylated-metabolite ratio points to handling of the absorbed carrier. Tablet disintegration and hepatic metabolite formation are different processes.
Reasoning steps for option D
What can a coating change affect?
It can change where and when the tablet disintegrates.
What discriminating measurement is more directly metabolic?
The sulfapyridine-to-acetylated-metabolite ratio points to handling of the absorbed carrier.
Can enteric-coating disintegration directly explain a shifted hepatic acetylation ratio?
No; coating disintegration does not directly alter hepatic acetylation ratio.
E. Greater topical potency of colonic 5-ASA in patient X (Why this does not fit)
It would concern the intestinal response to 5-ASA. Plasma sulfapyridine and its metabolite ratio differ despite similar local 5-ASA exposure. Do not use intestinal drug potency to explain a measured carrier-metabolism pattern.
Reasoning steps for option E
What would greater local anti-inflammatory potency address?
It would concern the intestinal response to 5-ASA.
What findings require an exposure rather than potency explanation?
Plasma sulfapyridine and its metabolite ratio differ despite similar local 5-ASA exposure.
Why can greater colonic 5-ASA potency not account for plasma sulfapyridine metabolite ratios?
Colonic 5-ASA potency does not determine plasma sulfapyridine metabolism.
Takeaway: Interpret carrier exposure separately from intestinal 5-ASA exposure; this model does not establish a need for routine genotype testing.
A. One 1.2-g tablet every other day (Why this does not fit)
It would average 0.6 g daily. It is below the specified 2.4-g daily dose and uses a different schedule. Convert tablet strength and frequency into the intended daily exposure.
Reasoning steps for option A
What average daily amount would this supply?
It would average 0.6 g daily.
How does that compare with the chosen maintenance regimen?
It is below the specified 2.4-g daily dose and uses a different schedule.
What average daily amount does one 1.2-g tablet every other day provide versus 2.4 g daily?
One 1.2-g tablet every other day averages 0.6 g/day, one quarter of 2.4 g/day.
B. One 1.2-g tablet each day (Why this does not fit)
It provides 1.2 g daily. No. The selected labeled regimen is 2.4 g daily. Do not substitute a general minimum or tablet count for the actual product regimen.
Reasoning steps for option B
What total does one tablet provide?
It provides 1.2 g daily.
Does that equal the selected product's maintenance dose?
No. The selected labeled regimen is 2.4 g daily.
How much daily mesalamine does one tablet supply relative to this product’s labeled maintenance dose?
One 1.2-g tablet gives 1.2 g/day, half the chosen maintenance dose.
C. Three 1.2-g tablets each day (Why this does not fit)
They provide 3.6 g daily. It exceeds the explicitly selected 2.4-g daily regimen. A clinically possible dose and the requested labeled dose are not the same question.
Reasoning steps for option C
What total do three tablets provide?
They provide 3.6 g daily.
Does that match the chosen maintenance amount?
It exceeds the explicitly selected 2.4-g daily regimen.
Does three 1.2-g tablets yield the specifically requested 2.4-g maintenance regimen?
No; three 1.2-g tablets give 3.6 g/day, not 2.4 g/day.
D. Two 1.2-g tablets each day (Best answer)
Two tablets provide the selected daily amount. The patient has achieved steroid-free remission and is transitioning to this product's chosen maintenance regimen. Identify the treatment phase, then apply the specific product strength and dose.
Reasoning steps for option D
How many 1.2-g tablets provide 2.4 g?
Two tablets provide the selected daily amount.
Why is the lower amount being considered here?
The patient has achieved steroid-free remission and is transitioning to this product's chosen maintenance regimen.
How many 1.2-g tablets produce 2.4 g once daily after induction ends?
Two 1.2-g tablets once daily give the specified 2.4-g maintenance dose.
E. Four 1.2-g tablets each day (Why this does not fit)
It supplies 4.8 g daily, an induction dose for this product. No. The question specifies a change to the labeled 2.4-g maintenance amount. Do not retain an induction tablet count automatically after a specific maintenance plan is chosen.
Reasoning steps for option E
What total does the current four-tablet plan supply?
It supplies 4.8 g daily, an induction dose for this product.
Does it match the maintenance regimen the prescriber selected?
No. The question specifies a change to the labeled 2.4-g maintenance amount.
Why should four 1.2-g induction tablets not automatically remain the maintenance schedule?
Four 1.2-g tablets give 4.8 g/day, the prior induction dose rather than chosen maintenance.
Takeaway: Identify the treatment phase, then apply the specific product strength and dose.
A. Primary 5-ASA failure; increase mesalamine before treating another cause (Why this does not fit)
Persistent UC activity despite adequate exposure and evaluation of competing causes would support it. Symptomatic toxin-positive C. difficile infection is present after antibiotic exposure. Do not classify a previously stable regimen as ineffective before addressing a documented infection.
Reasoning steps for option A
What evidence would help establish true 5-ASA failure?
Persistent UC activity despite adequate exposure and evaluation of competing causes would support it.
What competing cause is already demonstrated?
Symptomatic toxin-positive C. difficile infection is present after antibiotic exposure.
What documented finding must be addressed before declaring failure of a previously effective 5-ASA regimen?
Positive C. difficile toxin after antibiotics requires treatment before declaring 5-ASA failure.
B. Acute mesalamine intolerance; stop all aminosalicylates as the first response (Why this does not fit)
New symptoms closely following initiation can support that possibility. The mesalamine regimen has been unchanged for a year, while recent antibiotics and toxin-positive diarrhea support infection. Use the complete timeline and testing rather than equating every episode of diarrhea with a drug reaction.
Reasoning steps for option B
What timing can support acute mesalamine intolerance?
New symptoms closely following initiation can support that possibility.
What exposure and test pattern instead matters here?
The mesalamine regimen has been unchanged for a year, while recent antibiotics and toxin-positive diarrhea support infection.
How does a full year on unchanged mesalamine distinguish this episode from intolerance soon after starting?
A year of stable mesalamine followed by antibiotic exposure and toxin positivity weighs against new-onset drug intolerance.
C. Intercurrent infection; treat it and reassess inflammatory disease activity (Best answer)
Symptomatic C. difficile infection is demonstrated by the toxin result in this clinical context. The episode cannot be assumed to establish mesalamine failure; infection treatment and reassessment of UC are needed. Treat documented infection while evaluating coexisting inflammation rather than forcing a single-cause assumption.
Reasoning steps for option C
What explains the new symptoms beyond a presumed UC relapse?
Symptomatic C. difficile infection is demonstrated by the toxin result in this clinical context.
What does that mean for judging the maintenance regimen?
The episode cannot be assumed to establish mesalamine failure; infection treatment and reassessment of UC are needed.
What does toxin positivity after antibiotics require while concurrent UC activity remains possible?
Treat documented C. difficile and reassess possible coexisting UC activity.
D. Loss of distal drug delivery; substitute a higher-dose mesalamine enema (Why this does not fit)
It can add direct distal exposure when disease distribution and current treatment show a gap. A symptomatic enteric infection is established, and a route change would not treat it. A delivery problem should be demonstrated rather than assumed in every new flare-like episode.
Reasoning steps for option D
When can an enema correct a treatment gap?
It can add direct distal exposure when disease distribution and current treatment show a gap.
What new finding should take priority here?
A symptomatic enteric infection is established, and a route change would not treat it.
Is there evidence that mesalamine has newly failed to reach the distal colon?
No new delivery defect is demonstrated; documented infection needs attention first.
E. Inadequate anti-inflammatory potency; begin budesonide MMX without infection treatment (Why this does not fit)
It is an induction option for suitable active UC after appropriate assessment. The patient has documented symptomatic C. difficile infection that requires treatment. Address infection and assess inflammation together before labeling the event simple 5-ASA nonresponse.
Reasoning steps for option E
When can budesonide MMX be considered?
It is an induction option for suitable active UC after appropriate assessment.
What makes ignoring infection inappropriate?
The patient has documented symptomatic C. difficile infection that requires treatment.
Why is budesonide MMX without C. difficile treatment an incomplete response to this episode?
A. Reduced renal elimination of digoxin after sulfasalazine begins (Why this does not fit)
It would tend to increase concentrations for the same dose. The concentrations fall while renal function remains unchanged. Check the direction of the predicted pharmacokinetic effect against the data.
Reasoning steps for option A
What would reduced elimination tend to do to digoxin exposure?
It would tend to increase concentrations for the same dose.
How does that compare with the observed change?
The concentrations fall while renal function remains unchanged.
Would reduced digoxin renal elimination predict lower measured concentrations with unchanged kidney function?
No; reduced renal elimination predicts higher rather than lower digoxin exposure, and renal function is stable.
B. Reduced gastrointestinal absorption of the digoxin dose (Best answer)
Reduced digoxin absorption has been reported during concomitant treatment. Comparable dose timing and adherence with stable renal function accompany lower, not higher, concentrations. Review absorption interactions and clinical response rather than automatically assuming a renal cause.
Reasoning steps for option B
What interaction is reported with sulfasalazine?
Reduced digoxin absorption has been reported during concomitant treatment.
Why does it fit this pattern better than renal retention?
Comparable dose timing and adherence with stable renal function accompany lower, not higher, concentrations.
Which sulfasalazine interaction could lower reproducibly timed digoxin levels despite confirmed adherence?
Sulfasalazine can reduce digoxin absorption; review clinical response and appropriately timed levels.
C. Increased renal clearance after recovery from renal impairment (Why this does not fit)
It could lower concentrations for the same dose. Renal function is stable, while the concentration change follows sulfasalazine initiation. Separate a plausible pharmacokinetic direction from a mechanism supported by the patient data.
Reasoning steps for option C
What could improved renal elimination do to digoxin concentrations?
It could lower concentrations for the same dose.
What evidence does not support that explanation here?
Renal function is stable, while the concentration change follows sulfasalazine initiation.
What evidence for improved kidney function would support a new increase in digoxin clearance?
No improvement in renal function is shown, so recovery-related increased clearance is unsupported.
D. Reduced digoxin intake after the treatment schedule becomes more complex (Why this does not fit)
It can lead to missed doses and lower concentrations. Adherence is confirmed on repeated assessment with comparable sampling. Check actual intake, then assess a recognized absorption interaction when dosing is reliable.
Reasoning steps for option D
Why can regimen complexity affect measured exposure?
It can lead to missed doses and lower concentrations.
What feature makes that explanation less supported here?
Adherence is confirmed on repeated assessment with comparable sampling.
Does confirmed adherence support attributing the lower level to missed digoxin doses?
Confirmed adherence argues against reduced intake; examine the absorption interaction.
E. A new timing artifact from measuring only early post-dose peaks (Why this does not fit)
Concentrations vary with time after a dose. Repeated measurements use the same appropriate post-dose interval with confirmed adherence. Assess sampling validity before attributing a reproducible concentration change to timing alone.
Reasoning steps for option E
Why can sampling time affect digoxin interpretation?
Concentrations vary with time after a dose.
What feature reduces that explanation here?
Repeated measurements use the same appropriate post-dose interval with confirmed adherence.
Can a new peak-sampling artifact explain lower repeat levels drawn at the same appropriate interval?
No; repeat measurements used the same appropriate post-dose timing, not a new peak artifact.
Takeaway: Review absorption interactions and clinical response rather than automatically assuming a renal cause.
A. Receptor function contributes to response at comparable tissue exposure (Best answer)
It argues against lower local drug delivery as the explanation for the group difference. It supports a contribution from PPAR-gamma-dependent pharmacodynamic activity in this experimental setting. Experimental pathway dependence supports a mechanism without proving exclusive clinical action in every patient.
Reasoning steps for option A
What does comparable tissue concentration help rule against?
It argues against lower local drug delivery as the explanation for the group difference.
What does the difference in response therefore support?
It supports a contribution from PPAR-gamma-dependent pharmacodynamic activity in this experimental setting.
What does loss of anti-inflammatory response with reduced PPAR-gamma imply when colonic 5-ASA exposure matches?
Reduced PPAR-gamma function diminishes experimental 5-ASA response at similar colonic exposure, supporting a contribution without proving exclusive clinical action.
B. Lower intestinal delivery accounts for the response difference between groups (Why this does not fit)
It would predict lower relevant local drug exposure in the less responsive group. Measured colonic 5-ASA concentrations are comparable. Use exposure measurements to distinguish pharmacokinetic from pharmacodynamic explanations.
Reasoning steps for option B
What would a delivery explanation predict?
It would predict lower relevant local drug exposure in the less responsive group.
What observation contradicts that prediction?
Measured colonic 5-ASA concentrations are comparable.
Can lower intestinal 5-ASA delivery explain different responses when measured colonic concentrations are comparable?
No; comparable measured colonic concentrations argue against a delivery difference.
C. Sulfapyridine accumulation accounts for the receptor-dependent response pattern (Why this does not fit)
Sulfasalazine supplies it after azo cleavage. The preparation uses 5-ASA, so the response difference is not explained by its carrier. Keep active-molecule experiments separate from carrier-exposure explanations.
Reasoning steps for option C
Which treatment would supply sulfapyridine?
Sulfasalazine supplies it after azo cleavage.
Is sulfapyridine part of this experimental intervention?
The preparation uses 5-ASA, so the response difference is not explained by its carrier.
Is sulfapyridine involved in the stated experiment administering 5-ASA to both genotypes?
No; mice received 5-ASA, not sulfasalazine, so sulfapyridine is not the explanation.
D. The two genotypes show equivalent anti-inflammatory pharmacodynamic activity (Why this does not fit)
Comparable exposure would produce a similar measured response under the tested conditions. Only the normal-function group shows reduced inflammation. A measured response difference should not be discarded because drug concentrations are similar.
Reasoning steps for option D
What would equivalent pharmacodynamic activity imply?
Comparable exposure would produce a similar measured response under the tested conditions.
Do the reported outcomes show that equivalence?
Only the normal-function group shows reduced inflammation.
How does the observed inflammation difference contradict equivalent pharmacodynamic activity?
Inflammation decreases only with normal receptor function despite comparable exposure, indicating unequal pharmacodynamic response.
E. A systemic concentration threshold explains both groups' intestinal responses (Why this does not fit)
It would require relevant systemic exposure data linked to response. The comparison concerns receptor function, comparable local exposure, and differing intestinal outcomes. Do not infer an unmeasured plasma target or a clinical monitoring rule from this experiment.
Reasoning steps for option E
What information would support a systemic threshold model?
It would require relevant systemic exposure data linked to response.
What data are actually supplied?
The comparison concerns receptor function, comparable local exposure, and differing intestinal outcomes.
Why can this experiment not establish a systemic 5-ASA concentration threshold?
No plasma threshold was measured; the experiment cannot establish a systemic target or clinical monitoring rule.
Takeaway: Experimental pathway dependence supports a mechanism without proving exclusive clinical action in every patient.