T-Cell Costimulation, Immune Tolerance and Checkpoints
Distinguish recognition, costimulation, anergy, deletion, and regulation, then predict checkpoint drug effects and interpret immune toxicity in clinical cases.
A patient with arthritis receives a CTLA-4 fusion protein, while a patient with melanoma receives an antibody against CTLA-4. Should both treatments increase T-cell activity? Predict the direction before reading the binding targets.
By the end, explain why recognizing self need not cause disease, distinguish a quiet cell from a deleted cell, and predict whether a treatment lowers or releases immune restraint.
Why can a T cell recognize a peptide yet remain quiet? Recognition identifies a target; costimulation helps determine whether a naive cell should respond.
Locate each partner
The T-cell receptor, or TCR, recognizes a peptide displayed by major histocompatibility complex, or MHC, on an antigen-presenting cell. CD4 T cells recognize peptide with MHC class II; CD8 T cells recognize peptide with MHC class I. This is signal 1. It identifies what the cell recognizes, not whether that target warrants an inflammatory response.
CD28 on the T cell binds B7 molecules, CD80 and CD86, on the antigen-presenting cell. This supplies the classic costimulatory signal 2. Together, appropriate antigen recognition and costimulation support IL-2 production, survival, and proliferation. Cytokines further shape differentiation, so two signals are an entry model rather than a complete inventory of immune regulation. [1]
Trace two separate contacts
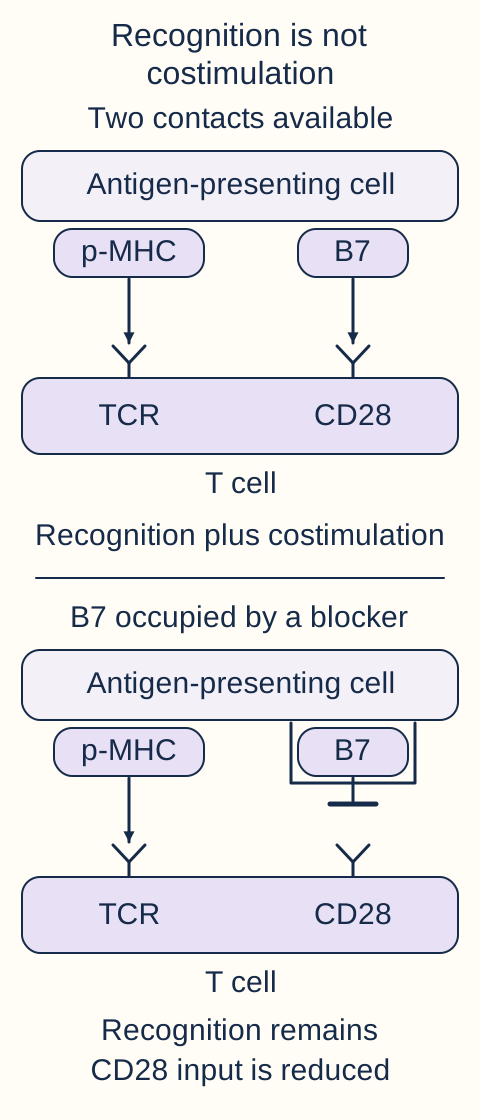
In the contact diagram, follow peptide-MHC to TCR, then follow B7 to CD28. Cover the B7 contact with a finger or a piece of paper without covering peptide-MHC. Predict which input remains before comparing the two pictured states.
Trace each contact and cover only B7. Antigen recognition remains possible while classic CD28 costimulation falls. This schematic isolates contacts, not a guaranteed fate for every lymphocyte. [1][2]
Recognition still occurs, but the classic CD28 costimulatory input is reduced. The diagram changes one contact, not the identity of the peptide or the survival of the cell. [1]
Controlled comparisons for a naive T-cell clone
Encounter
What it establishes
EncounterCognate peptide with B7
What it establishesRecognition with costimulation supports activation.
EncounterCognate peptide with little B7
What it establishesRecognition without adequate costimulation can promote anergy.
EncounterUnrelated peptide with B7
What it establishesB7 does not supply the missing antigen specificity.
Predict the missing-signal result
Antigen recognition without sufficient costimulation can produce anergy, a living but hyporesponsive state. It is different from apoptosis, which eliminates the cell. Without relevant antigen recognition, costimulation alone does not create a conventional antigen-specific response. In a healthy immune response, antigen-presenting cells integrate innate inflammatory information rather than treating every encountered peptide as dangerous.
Think of recognition as a key and costimulation as permission to start an engine. A matching key does not guarantee permission. The limit is that a lymphocyte is not a binary switch. Prior activation, signal strength, cytokines, and inhibitory receptors alter its response.
For a worked example, a viable T-cell population recognizes peptide on cells lacking effective B7 stimulation, then responds poorly at restimulation. Functional anergy fits better than loss of the receptor or deletion. Anergy can persist, but experimental IL-2 stimulation can reverse some forms. Do not label every anergic cell permanently incapable of responding. [2]
Ask whether the cell recognized antigen, received costimulation, and remained alive.
Apply the distinction: a living cell that responds poorly after a prior antigen encounter is not equivalent to a cell that never recognized that peptide.
Compare a restimulation prediction
A fresh competent antigen-presenting cell supplies both contacts. Persistent poor response from the surviving previously exposed clone supports hyporesponsiveness rather than simple absence of antigen. Its ability to recover under other conditions must be tested rather than assumed. [2]
Central tolerance changes the developing repertoire
Where was the self-reactive cell when its fate changed? During development, central tolerance alters the repertoire in the thymus or bone marrow. The same outcome in a mature peripheral cell belongs to a different setting.
A thymic sample of self
Positive selection preserves thymocytes able to recognize self MHC sufficiently to function. Negative selection eliminates many thymocytes that react too strongly to self peptide with MHC. These processes answer different questions. A cell that cannot use self MHC is ineffective; a strongly self-reactive cell may be dangerous.
AIRE supports expression of many tissue-restricted antigens in medullary thymic epithelial cells. Developing T cells can therefore encounter proteins associated with organs far from the thymus. AIRE deficiency impairs this display and permits some autoreactive cells to escape. It does not erase every mechanism of negative selection or every peripheral safeguard. [3]
Predict what escapes when a sample is missing
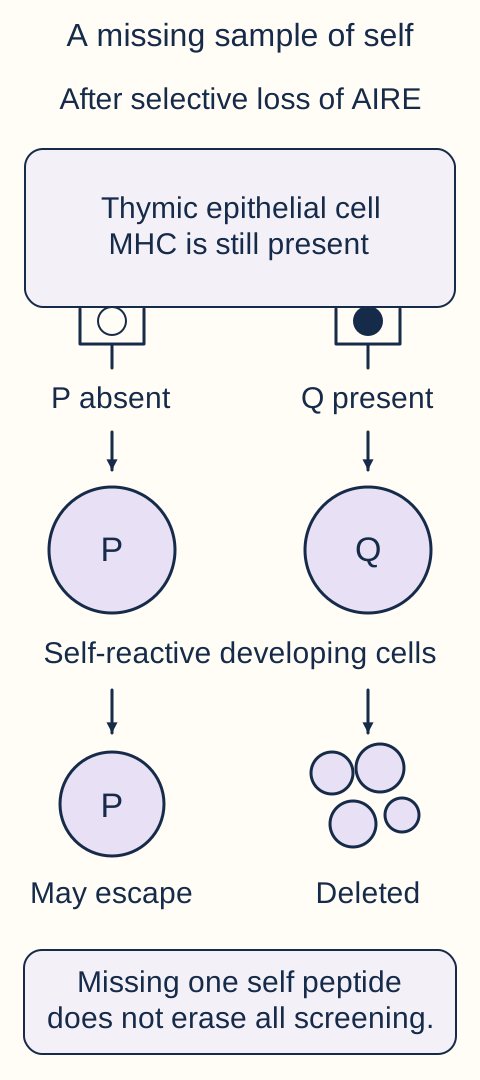
The thymic diagram follows two self-reactive clones. Trace the clone whose peptide depends on AIRE, then compare it with the clone whose peptide remains displayed without AIRE. Which survival change should be selective rather than universal?
Predict which of two self-reactive clones escapes when only one self-peptide sample is lost. P is AIRE-dependent in this controlled example; Q is not. The cell fragments depict deletion, not a measured count. [3]
Loss of the AIRE-dependent sample can let its matching clone escape. A different clone can still undergo negative selection if its self peptide remains available. This is failure to display part of self, not loss of all MHC or all apoptosis. [3]
A B cell can revise its receptor
In bone marrow, a self-reactive immature B cell may undergo receptor editing through additional immunoglobulin kappa or lambda gene rearrangement. A changed receptor can reduce self recognition. Deletion eliminates a cell; editing changes its specificity. Some self-reactive B cells also become anergic. Central B-cell tolerance is therefore more than a single deletion filter. [4]
The analogy is a workshop inspection before a product is released. A faulty part may be discarded or revised. The limit is that lymphocytes are selected through molecular interactions, and no finite thymic sample represents every later tissue condition.
Clinically, chronic mucocutaneous candidiasis with hypoparathyroidism and primary adrenal insufficiency suggests APECED, also called autoimmune polyendocrine syndrome type 1. This is the AIRE-associated pattern. Endocrine injury and candidiasis are not evidence that all T cells are absent. The syndrome connects impaired self-tolerance to organ-specific disease. [14]
A developing cell in thymus or marrow indicates central tolerance. A mature cell in a lymph node indicates a peripheral setting.
Ectodermal findings, including nail dystrophy, can accompany APECED. Interpret the full clinical pattern and confirmatory testing rather than treating a single antibody result as a universal exclusion. [14]
Compare receptor revision with isotype change
An immature B cell that remains alive but develops a new kappa or lambda variable sequence with less self binding has revised its specificity. If its mu constant region remains, it has not switched away from the IgM isotype. This separates receptor editing from deletion and from later class switching. [4]
Peripheral tolerance keeps mature cells under control
Does a low response mean the cell is quiet, suppressed by a neighbor, or gone? Peripheral tolerance can produce all three patterns, but they require different evidence.
Three outcomes that should stay separate
Some autoreactive cells leave primary lymphoid organs. Peripheral tolerance limits their activation through inadequate costimulation, inhibitory receptors, active suppression, and deletion. A mature cell becoming unresponsive in a lymph node is not undergoing thymic negative selection merely because the node is a lymphoid organ.
Anergy leaves a living cell hyporesponsive. Suppression restrains a responder through another cell or its products. Deletion eliminates the cell by apoptosis. Count viable responders, test their function, and change their cellular neighbors before assigning a mechanism.
Use a cell-swap experiment
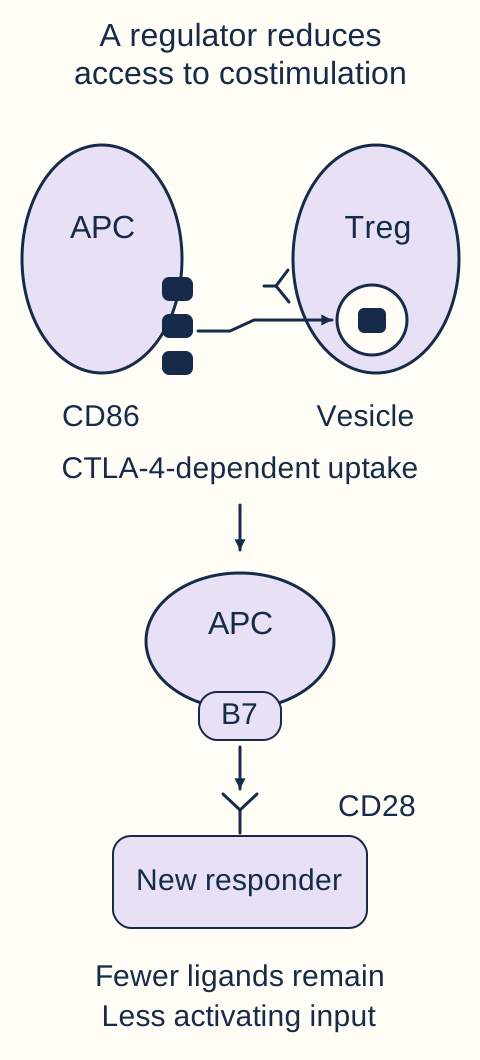
Compare two cultures with the same responders and antigen-presenting cells. One contains effective regulatory T cells; the other does not. The ligand-transfer diagram shows CTLA-4-associated acquisition of APC B7 into a regulatory cell. Trace how that leaves less ligand for a later responder.
Follow the ligand from the antigen-presenting cell, abbreviated APC, into the regulatory T cell, or Treg. The later responder receives less costimulation. Compare ligand engagement rather than icon size. [7]
When fewer CD80/CD86 molecules remain accessible, subsequent CD28 costimulation is reduced. A regulatory cell can therefore alter the environment for a different responding cell. This is not the same as deletion of that responder. [7]
What regulatory T cells contribute
Regulatory T cells, or Tregs, commonly express CD4, high CD25, and FOXP3. CD25 is the alpha subunit of the high-affinity IL-2 receptor. FOXP3 is a transcription factor crucial for regulatory function. CD25 alone is not a unique identity tag because activated conventional T cells can also express it. Tregs depend on IL-2 support while restraining other immune responses. [5]
Tregs can use CTLA-4 to reduce available CD80 and CD86 on antigen-presenting cells, limiting CD28 costimulation of other T cells. Suppressive cytokines such as IL-10 and TGF-beta also contribute in relevant contexts. [19][20] Think of a supervisor limiting access to a shared resource. The limit is that regulation uses several overlapping mechanisms, not one supervisor issuing a universal stop command. [7]
Recognize failed regulation
A male infant with persistent enteropathy, eczema, and insulin-requiring diabetes suggests IPEX, a FOXP3-associated disorder. The defect concerns regulatory function, not failure to display tissue antigens in the thymus. Presentation and measured Treg numbers vary, so a detectable regulatory population does not exclude dysfunctional regulation. [5]
A useful transfer question is whether normal lymphocyte counts guarantee tolerance. They do not. A cell count measures presence; a functional assay asks what those cells actually do. When the disorder is suppression, a numerically present population can still fail its job.
Pause here if useful. On return, compare a surviving unresponsive cell with a cell that suppresses its neighbors.
CTLA4 haploinsufficiency provides another human example: inadequate checkpoint function can combine autoimmunity and lymphocytic organ infiltration with antibody deficiency or infections. The name of an inhibitory receptor does not mean losing it simply causes a stronger, healthier immune system. [21]
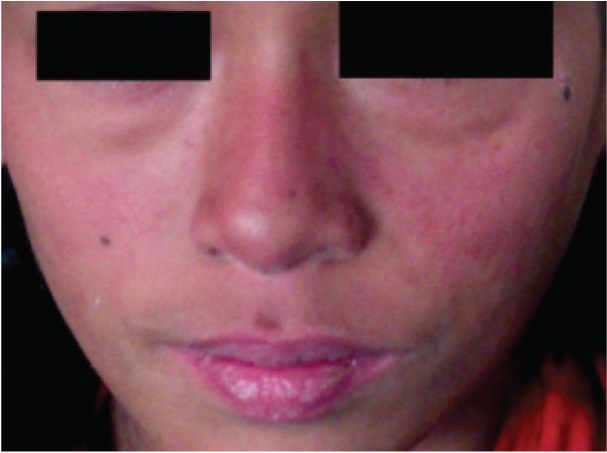
The source-labeled lupus photograph illustrates a malar distribution of autoimmune skin inflammation. Its appearance does not identify an AIRE, FOXP3, CTLA4, or FAS defect. Clinical phenotype and molecular localization are different questions.
Source-labeled lupus malar rash. Describe its distribution, then distinguish a clinical phenotype from localization of an AIRE, FOXP3, CTLA4, or FAS defect. The photograph alone cannot identify the failed tolerance pathway. Image: CNX OpenStax; original source; CC BY 4.0.Localize a failed suppression result
If normal regulators restrain patient responders but patient regulators fail to restrain normal responders, the comparison points to the regulatory compartment. A normal cell count cannot overturn that functional result. [5]
Fas-dependent deletion and the ALPS pattern
What would happen if activated lymphocytes survived a death signal? Fas-pathway failure can permit inappropriate persistence, which differs from a living cell that has become functionally anergic.
Follow the death signal
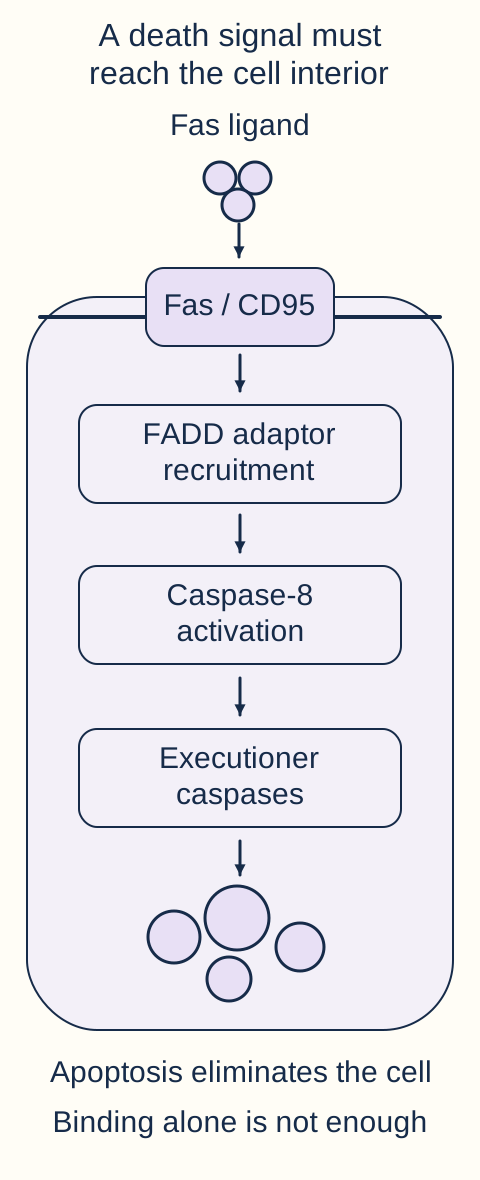
Fas, also called CD95, is a death receptor. Fas ligand engagement can recruit intracellular death-signaling machinery and activate caspases, leading to apoptosis. This pathway contributes to activation-induced cell death after repeated stimulation. It is one route of peripheral deletion, not the sole mechanism responsible for contraction of every immune response. [6]
Locate the interruption, not just the receptor
Trace Fas ligand to Fas, then the intracellular adaptor and caspase steps in the diagram. Imagine ligand binding is preserved but initiator-caspase activation is absent. Predict whether a normal amount of surface receptor would rule out a signaling defect.
Cover the step after surface binding. A visible Fas receptor can coexist with failed intracellular death signaling. This is one extrinsic apoptotic route, not the complete set of lymphocyte contraction pathways. [6]
It would not. Fas recruits death-signaling machinery, including FADD and initiator caspases such as caspase-8, before executioner caspases produce apoptosis. A block after binding can preserve surface recognition while preventing death. Other apoptotic routes provide useful functional comparisons. [6]
Persistence plus autoimmunity
Autoimmune lymphoproliferative syndrome, or ALPS, combines chronic nonmalignant lymphadenopathy or splenomegaly with immune dysregulation. Autoimmune hemolytic anemia, thrombocytopenia, or neutropenia may occur. Characteristic expanded cells express CD3 and an alpha-beta TCR but lack both CD4 and CD8. Specifying alpha-beta prevents confusion with other double-negative populations. [6]
Think of apoptosis as scheduled retirement of cells after their work. Failure permits accumulation. The analogy stops at diagnosis. Enlarged nodes alone do not prove ALPS, and abnormal cell survival must be interpreted alongside phenotype, functional studies, and genetic findings.
FAS is a major implicated gene, but pathway defects are not restricted to a single inherited receptor mutation. Somatic FAS variants can also cause disease. A negative family history therefore does not exclude ALPS. Nor does a normal vaccine response establish that every aspect of immune function is normal. [6][24]
For a different application, new asymmetric nodal enlargement in someone with established ALPS should not automatically be attributed to their baseline condition. Lymphoma risk is increased and requires appropriate evaluation. Avoid describing that risk as merely modest or assuming that every later node remains nonmalignant. [6]
Cytopenias with persistent enlarged lymphoid tissue suggest failed immune regulation. Alpha-beta double-negative T cells help focus the ALPS evaluation.
Supportive findings can include high soluble Fas ligand, vitamin B12, or IL-10 and polyclonal hypergammaglobulinemia. None is sufficient alone. Fas-pathway evaluations have included FAS, FASLG, and CASP10; a gene name or an unclassified variant is not a diagnosis. Interpret the phenotype, function, and the significance of the particular variant together. [6]
Somatic disease can be concentrated in selected lymphocyte populations. Some patients have unrevealing unselected-cell apoptosis studies, and testing a relevant sorted population can be informative. A negative bulk assay is not equivalent to proving that every population is normal. [24]
Compare two apoptosis tests
If Fas ligation fails to activate caspase-8 but a mitochondrial stimulus still activates executioner caspases and causes death, the comparison points toward the proximal Fas route rather than a universal inability to execute apoptosis. [6]
Checkpoint treatment depends on what the drug binds
Why can two treatments associated with CTLA-4 have opposite effects? Blocking an activating contact lowers stimulation; blocking an inhibitory receptor can release restraint. Predict from the binding target, not the shared name.
Separate receptor from ligand
CD28 and CTLA-4 both bind CD80 and CD86. CTLA-4 binds these ligands more avidly and restricts costimulation, including through ligand removal from antigen-presenting cells. It is prominent on Tregs and induced in conventional T cells after activation. Its importance during priming is useful to remember, but it is not confined to one anatomical compartment. [7]
PD-1 is an inhibitory receptor on activated T cells. PD-L1 on tumor cells or other cells can engage it and reduce T-cell activity. PD-1 also binds PD-L2. [26][27] Persistent antigen exposure can generate a broader exhaustion program; one inhibitory contact is not equivalent to complete exhaustion or cell death. Experimental checkpoint blockade can restore some functions without erasing the exhausted state. [8][9]
Trace the target before predicting the output
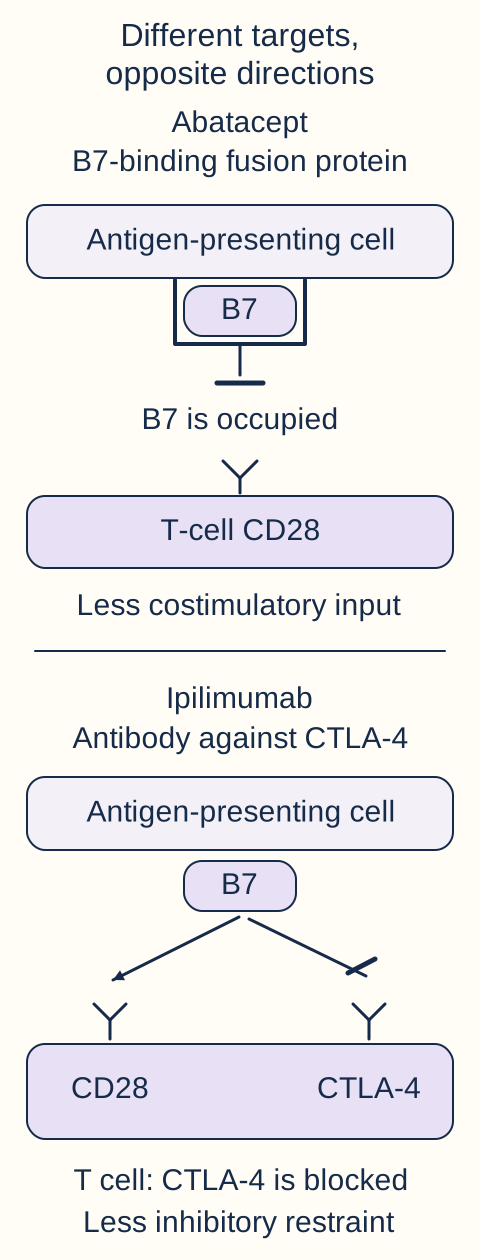
In the drug-contact diagram, locate the binding site of the fusion protein and the binding site of the antibody. Trace from each occupied site to the CD28 contact that remains available. Predict whether access to activating costimulation decreases or inhibitory restraint is released.
Compare the occupied sites before predicting direction. A ligand-binding fusion protein reduces costimulatory input; an antibody against an inhibitory receptor reduces restraint. Arrows show functional contacts, not guaranteed tumor responses. [1][7][28]
The ligand-binding fusion protein prevents CD28 access to B7. An antibody against CTLA-4 instead prevents the inhibitory receptor from using B7. Both can change the same immune conversation, but they do not interrupt the same molecular contact. [1][7][28]
Abatacept is a soluble CTLA-4 immunoglobulin fusion protein that occupies CD80/CD86 and prevents their interaction with CD28. It lowers costimulation. Ipilimumab is an antibody against CTLA-4 and releases inhibitory restraint. They have different targets and opposite intended immune directions despite sharing CTLA-4 in their descriptions. [1][28]
Examples of anti-PD-1 antibodies include pembrolizumab, nivolumab, and cemiplimab. [26][27][18] Atezolizumab, durvalumab, and avelumab target PD-L1. Blocking the receptor and blocking one ligand are related strategies, not identical molecular contacts. Cancer type, biomarkers, regimen, and patient factors govern treatment selection; this map does not select an oncology regimen. [8][15][16][17][18]
A brake analogy helps predict direction. Preventing a brake from engaging can permit stronger activity, but it does not supply a missing engine. Likewise, checkpoint inhibition does not create an antigen-specific receptor or guarantee tumor clearance. [9]
Activated cytotoxic CD8 T cells can kill recognized targets through granule-mediated pathways involving perforin and granzymes. These effector proteins participate in target-cell injury and apoptosis; a checkpoint antibody does not itself supply the missing antigen-specific receptor or substitute for every effector function. [29][30]
Predict a change in the inhibitory ligand
Replace PD-L1 with PD-L2 while retaining PD-1 on the responding cell. An antibody to PD-L1 no longer blocks that PD-L2 contact, whereas an antibody to their shared receptor can interfere with both. This is a molecular comparison, not a rule for choosing a cancer regimen. [15][26][27]
Apply the mechanism without overreading the finding
Can a treatment help a tumor while harming a normal organ? Yes. New organ symptoms require evaluation for immune toxicity and competing causes; tumor response or a skin change cannot establish safety elsewhere.
Recognize organ-specific toxicity
Checkpoint therapy can inflame normal tissues. New diarrhea suggests possible colitis; cough or dyspnea raises concern for pneumonitis. Hepatitis may present through abnormal liver tests. Thyroid dysfunction and hypophysitis can produce fatigue or other nonspecific symptoms. Dermatitis and pigment changes may occur. Symptoms can appear during treatment or afterward, and new or worsening symptoms should be reported promptly to the treating team. [10]
Compare benefit and toxicity as separate observations
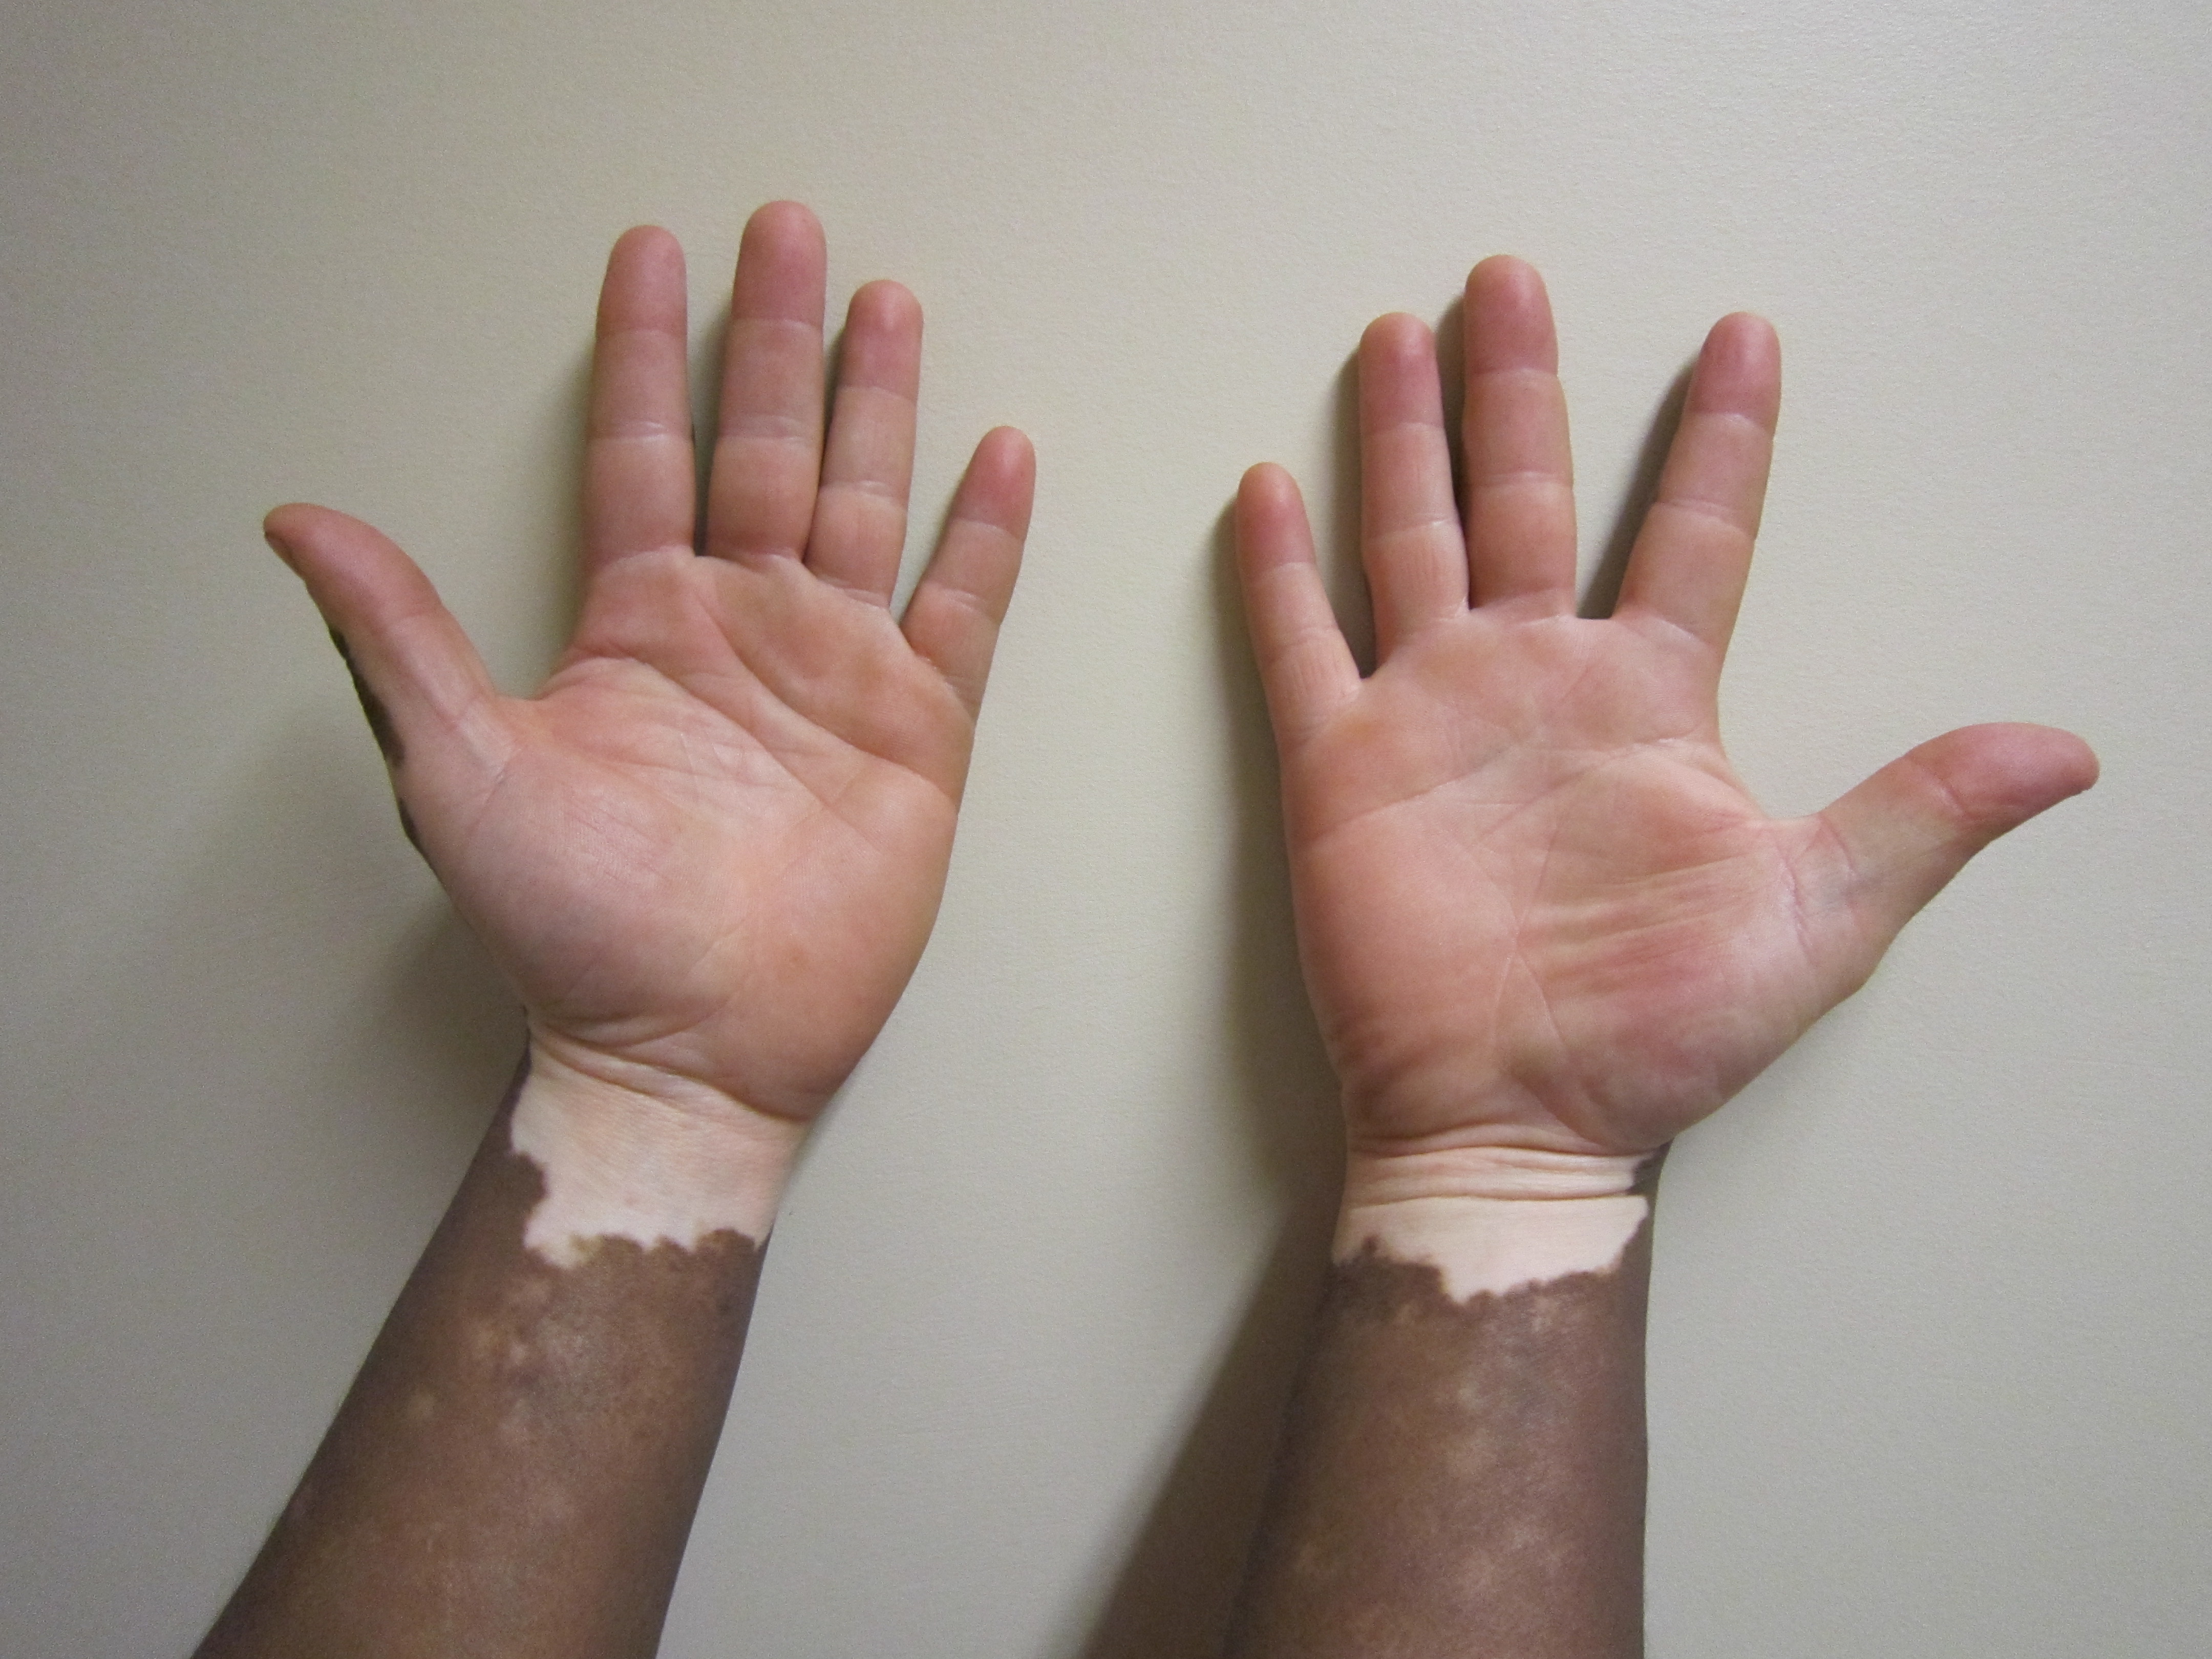
Use the vitiligo photograph to identify loss of pigment rather than redness. Then consider a different patient whose melanoma is shrinking but who develops diarrhea or breathlessness. What information does the skin finding fail to provide?
Compare pigment loss with inflammatory redness. This is an appearance example only: checkpoint exposure, melanoma, and tumor response are not documented for the pictured person. Pigment loss does not establish an individual cancer response. Image: James Heilman, MD; original source; CC BY-SA 3.0.
It does not establish tumor response, stool etiology, oxygenation, or the safety of another treatment dose. The photograph documents an appearance only; it does not document checkpoint exposure or cancer outcomes for the pictured person.
Vitiligo during melanoma treatment can accompany immunity involving normal melanocytes. A pembrolizumab cohort found responses in 12 of 17 patients with vitiligo and 14 of 50 without it. This is an association, not an individual guarantee of tumor control, and it does not justify dismissing new diarrhea or breathlessness. [22] Management of an immune-related adverse event depends on the organ and severity; a universal instruction to continue, stop, or give one steroid dose would be misleading. [10][23]
Keep adjacent receptor systems separate
Tacrolimus acts inside the cell through FKBP12 and inhibition of calcineurin. NFAT then remains phosphorylated and its nuclear translocation is reduced, decreasing transcription of IL-2 and other cytokines. Calcium and calmodulin normally activate calcineurin, which supports NFAT dephosphorylation and nuclear entry. Cyclosporine uses cyclophilin rather than FKBP12, but the drug-protein complexes converge on calcineurin. This is an intracellular signaling intervention, not physical blockade of B7. [11][25]
CD40 ligand, also called CD154, on activated helper T cells binds CD40 on B cells and, with appropriate cytokines, supports class switching and effective humoral help. A boy with recurrent infections, low IgG and IgA, preserved or increased IgM, low IgE, and present B cells fits impaired helper signaling better than absent B-cell development. Do not substitute CD28/B7 for CD40L/CD40 merely because both involve two contacting immune cells. [12]
Superantigens produce a different error in activation. They connect MHC class II with particular TCR V-beta regions outside ordinary peptide-specific recognition, stimulating a broad T-cell population. A patient with toxin-mediated shock is experiencing excessive inflammatory activation, not a newly protective tolerance mechanism. The key contrast is broad V-beta recruitment versus conventional peptide-specific recognition. Staphylococcal toxic shock syndrome toxin and streptococcal pyrogenic exotoxins illustrate this category. Inflammatory cytokines, including IL-2, interferon-gamma, and TNF, contribute to systemic illness and shock. Broad recruitment does not make costimulation irrelevant: experimental superantigen responses can depend importantly on B7-2/CD28. [13]
Use a wiring-diagram analogy. The same reduced output can come from a disconnected surface contact or an interrupted intracellular relay. The limit is that a clinical drug affects a biological network, so one laboratory change rarely identifies its mechanism without exposure information.
For any new case, locate the cell, name the interacting molecules, identify the measured outcome, and then predict what blocking that contact would change.
Report new or worsening symptoms promptly. Marked breathlessness, hypoxemia, or circulatory instability requires urgent assessment. Clinicians evaluate infection and other competing causes while addressing possible immune toxicity; organ findings and severity determine treatment withholding, immunosuppression, hormone replacement, and whether treatment can later resume. [10][23]
Apply the distinction to two contact systems
A B cell that can switch isotype after direct CD40 stimulation with cytokines has an intact tested response pathway. Failure when its helper T cells are used points toward inadequate helper signaling. This differs from B7/CD28 costimulation of a naive T cell and from NFAT-dependent cytokine transcription inside that cell. [11][12]
Case practice
Case 1
Show answer and explanations for case 1
A. Add an antibody that blocks lymphocyte Fas (Why this does not fit)
Fas blockade can interrupt death-receptor-mediated apoptosis. Cell viability is unchanged; the measured defect is reduced activation rather than excessive cell death.
Reasoning steps for option A
What process does Fas blockade interrupt?
Fas blockade can interrupt death-receptor-mediated apoptosis.
Which observation argues against that being the needed rescue?
Cell viability is unchanged; the measured defect is reduced activation rather than excessive cell death.
B. Provide an agonist that directly stimulates CD28 (Best answer)
The fusion protein occupies CD80 and CD86 on the antigen-presenting cell, limiting their interaction with T-cell CD28. It supplies costimulatory signaling without needing unoccupied B7; this is an experimental rescue, not a treatment recommendation.
Reasoning steps for option B
Which contact is lost despite preserved TCR binding?
The fusion protein occupies CD80 and CD86 on the antigen-presenting cell, limiting their interaction with T-cell CD28.
Why would direct CD28 stimulation bypass that loss?
It supplies costimulatory signaling without needing unoccupied B7; this is an experimental rescue, not a treatment recommendation.
C. Increase peptide loading on the antigen-presenting cells (Why this does not fit)
Additional peptide would increase antigen-specific TCR engagement, the recognition input. Recognition is already preserved; increasing it does not directly replace the missing CD28 costimulatory contact.
Reasoning steps for option C
Which input would additional peptide primarily strengthen?
Additional peptide would increase antigen-specific TCR engagement, the recognition input.
Why is that not the targeted bypass here?
Recognition is already preserved; increasing it does not directly replace the missing CD28 costimulatory contact.
D. Add an antibody that blocks T-cell PD-1 (Why this does not fit)
It would reduce signaling through the PD-1 inhibitory pathway. No. B7 would remain occupied, so reducing a separate inhibitory pathway is not the direct replacement for CD28 stimulation.
Reasoning steps for option D
Which restraint would a PD-1 antibody reduce?
It would reduce signaling through the PD-1 inhibitory pathway.
Does that restore the contact occupied by this fusion protein?
No. B7 would remain occupied, so reducing a separate inhibitory pathway is not the direct replacement for CD28 stimulation.
Takeaway: Identify the contact removed by a drug before choosing an experimental bypass.
A. Continuing suppression by contaminating regulatory T cells (Why this does not fit)
They could suppress otherwise responsive T cells through contact-dependent and soluble mechanisms. Removing the regulatory-enriched population does not restore IL-2 or division, and the responder defect persists with fresh antigen-presenting cells.
Reasoning steps for option A
How could regulatory cells lower the measured response?
They could suppress otherwise responsive T cells through contact-dependent and soluble mechanisms.
What makes that explanation less likely here?
Removing the regulatory-enriched population does not restore IL-2 or division, and the responder defect persists with fresh antigen-presenting cells.
B. Persistent hyporesponsiveness within the responding T-cell population (Best answer)
The cells remain present but respond poorly after an inadequately costimulated antigen encounter, fitting anergy. Fresh competent antigen-presenting cells and lack of rescue after regulatory-cell removal support persistent responder hyporesponsiveness rather than an ongoing external suppressor.
Reasoning steps for option B
What does survival with reduced restimulation indicate?
The cells remain present but respond poorly after an inadequately costimulated antigen encounter, fitting anergy.
How do the replacement and depletion controls refine the conclusion?
Fresh competent antigen-presenting cells and lack of rescue after regulatory-cell removal support persistent responder hyporesponsiveness rather than an ongoing external suppressor.
C. Failure of the initial cells to display the cognate peptide (Why this does not fit)
It would prevent the initial antigen-specific encounter and leave cells ignorant of that peptide. The initial peptide encounter is established, and subsequent competent stimulation reveals persistent poor responsiveness rather than a normal first response.
Reasoning steps for option C
What would absent cognate display prevent?
It would prevent the initial antigen-specific encounter and leave cells ignorant of that peptide.
Why does the experiment favor a different state?
The initial peptide encounter is established, and subsequent competent stimulation reveals persistent poor responsiveness rather than a normal first response.
D. Selective apoptotic deletion of the antigen-specific T cells (Why this does not fit)
Deletion would reduce the number of viable antigen-specific cells through apoptosis. Viable numbers and TCR expression are preserved, so loss of function cannot be explained chiefly by disappearance of those cells.
Reasoning steps for option D
What measurement would support deletion?
Deletion would reduce the number of viable antigen-specific cells through apoptosis.
Does the observed cell population show that loss?
Viable numbers and TCR expression are preserved, so loss of function cannot be explained chiefly by disappearance of those cells.
Takeaway: Anergy describes function, whereas deletion describes loss of the cell.
A. Low response in A; strong response in B (Best answer)
A recognized its antigen without effective costimulation, whereas B lacked cognate recognition despite abundant B7. A remains hyporesponsive in the stated model; B can now receive both appropriate inputs and respond.
Reasoning steps for option A
How did the two initial encounters differ?
A recognized its antigen without effective costimulation, whereas B lacked cognate recognition despite abundant B7.
How does that history affect the later challenge?
A remains hyporesponsive in the stated model; B can now receive both appropriate inputs and respond.
B. Low response in A; low response in B (Why this does not fit)
Its prior cognate encounter without sufficient costimulation induced anergy. B7 with an unrelated peptide does not reproduce that antigen-specific encounter for this clone.
Reasoning steps for option B
Why is a low response in A reasonable?
Its prior cognate encounter without sufficient costimulation induced anergy.
Why should the same conclusion not be transferred to B?
B7 with an unrelated peptide does not reproduce that antigen-specific encounter for this clone.
C. Strong response in A; low response in B (Why this does not fit)
It would assume the initial encounter left A fully responsive despite the preceding inadequately costimulated encounter. Unrelated peptide with B7 did not provide the cognate recognition needed to induce the stated antigen-specific hyporesponsive state.
Reasoning steps for option C
What would a strong response in A assume?
It would assume the initial encounter left A fully responsive despite the preceding inadequately costimulated encounter.
Why is a low response in B unsupported?
Unrelated peptide with B7 did not provide the cognate recognition needed to induce the stated antigen-specific hyporesponsive state.
D. Strong response in A; strong response in B (Why this does not fit)
The second encounter is its first opportunity to receive cognate recognition with sufficient costimulation. A previously encountered cognate antigen without effective costimulation; later provision of both contacts does not automatically establish reversal in this experiment.
Reasoning steps for option D
Why can B respond at the second encounter?
The second encounter is its first opportunity to receive cognate recognition with sufficient costimulation.
Why does A not have the same starting state?
A previously encountered cognate antigen without effective costimulation; later provision of both contacts does not automatically establish reversal in this experiment.
Takeaway: Costimulation cannot substitute for antigen specificity.
A. Responsiveness was restored under the tested culture conditions (Best answer)
Equal numbers of viable cells show greater antigen-driven proliferation after IL-2 has been removed. The tracked clone regained responsiveness in these conditions; the result does not establish universal reversal or a clinical IL-2 treatment plan.
Reasoning steps for option A
Which result shows more than simple expansion?
Equal numbers of viable cells show greater antigen-driven proliferation after IL-2 has been removed.
How broad is the supported conclusion?
The tracked clone regained responsiveness in these conditions; the result does not establish universal reversal or a clinical IL-2 treatment plan.
B. A different antigen-specific clone replaced the anergic cells (Why this does not fit)
An initially responsive contaminant could expand and dominate the later response. Lineage tracking identifies the same clone before and after treatment, rather than replacement by a different clone.
Reasoning steps for option B
How could selection of a new clone mimic recovery?
An initially responsive contaminant could expand and dominate the later response.
Which observation opposes that account?
Lineage tracking identifies the same clone before and after treatment, rather than replacement by a different clone.
C. Differential apoptosis explains the increased responding fraction (Why this does not fit)
Preferential loss of nonresponders could enrich surviving responsive cells without restoring their function. Matched survival, equal viable replating, and recovery in the tracked clone favor altered responsiveness over differential cell loss.
Reasoning steps for option C
How could selective death change the measured fraction?
Preferential loss of nonresponders could enrich surviving responsive cells without restoring their function.
Why is that not the leading explanation here?
Matched survival, equal viable replating, and recovery in the tracked clone favor altered responsiveness over differential cell loss.
D. The apparent recovery reflects a larger starting cell number (Why this does not fit)
More starting cells could produce a greater total signal even without improved responsiveness per cell. Equal viable numbers were replated, so the difference reflects the responding fraction rather than a larger inoculum.
Reasoning steps for option D
How could cell number inflate an unnormalized proliferation assay?
More starting cells could produce a greater total signal even without improved responsiveness per cell.
Which design feature addresses that explanation?
Equal viable numbers were replated, so the difference reflects the responding fraction rather than a larger inoculum.
Takeaway: An experimental reversal defines what happened in that model, not what every anergic cell will do.
A. Restore pancreatic self-peptide display in the altered thymic epithelium (Best answer)
Changing only the thymic epithelial environment changes deletion of the pancreatic-reactive clone. Restoring the missing self-peptide display allows that clone to encounter its self target during negative selection.
Reasoning steps for option A
Which experimental component determines whether the clone survives?
Changing only the thymic epithelial environment changes deletion of the pancreatic-reactive clone.
What correction targets that component?
Restoring the missing self-peptide display allows that clone to encounter its self target during negative selection.
B. Reduce Fas expression on the otherwise normal developing T cells (Why this does not fit)
Reduced Fas signaling can favor persistence of susceptible lymphocytes rather than their elimination. Excess survival follows altered epithelial display, and the same developing cells are deleted in a normal environment.
Reasoning steps for option B
What would lower death-receptor availability tend to favor?
Reduced Fas signaling can favor persistence of susceptible lymphocytes rather than their elimination.
Why is that the wrong corrective direction here?
Excess survival follows altered epithelial display, and the same developing cells are deleted in a normal environment.
C. Suppress immunoglobulin rearrangement in developing bone marrow B cells (Why this does not fit)
It would interfere with B-cell receptor generation and editing in bone marrow. The experiment varies thymic epithelium and measures survival of T cells, with no B-cell developmental defect supplied.
Reasoning steps for option C
Which developmental process would this intervention affect?
It would interfere with B-cell receptor generation and editing in bone marrow.
Why is that compartment not responsible for this result?
The experiment varies thymic epithelium and measures survival of T cells, with no B-cell developmental defect supplied.
D. Increase CD28 stimulation after the cells enter peripheral lymph nodes (Why this does not fit)
It would strengthen activation of mature cells encountering antigen with available costimulation. The abnormality occurs before thymic export, when selective self-peptide display is missing; stronger later activation does not replace that screening.
Reasoning steps for option D
What would peripheral CD28 stimulation change?
It would strengthen activation of mature cells encountering antigen with available costimulation.
Why does that not repair the demonstrated selection failure?
The abnormality occurs before thymic export, when selective self-peptide display is missing; stronger later activation does not replace that screening.
Takeaway: The thymic environment can alter which self-reactive cells survive without changing their receptors.
A. Reduced suppression by circulating FOXP3-associated regulatory T cells (Why this does not fit)
Early enteropathy, eczema, and insulin-deficient diabetes, particularly in boys, suggest IPEX. The combination of candidiasis, hypoparathyroidism, and primary adrenal insufficiency specifically favors AIRE-associated central tolerance failure.
Reasoning steps for option A
Which phenotype commonly raises concern for FOXP3 dysfunction?
Early enteropathy, eczema, and insulin-deficient diabetes, particularly in boys, suggest IPEX.
Why is that not the best connection for this patient?
The combination of candidiasis, hypoparathyroidism, and primary adrenal insufficiency specifically favors AIRE-associated central tolerance failure.
B. Reduced expression of selected self antigens by thymic epithelial cells (Best answer)
Candidiasis, hypoparathyroidism, and primary adrenal insufficiency form the characteristic APECED pattern. AIRE dysfunction reduces expression of selected tissue-restricted antigens in medullary thymic epithelium, impairing screening of the relevant self-reactive T cells.
Reasoning steps for option B
What does the combined clinical pattern suggest?
Candidiasis, hypoparathyroidism, and primary adrenal insufficiency form the characteristic APECED pattern.
How does that pattern connect to thymic biology?
AIRE dysfunction reduces expression of selected tissue-restricted antigens in medullary thymic epithelium, impairing screening of the relevant self-reactive T cells.
C. Reduced class switching despite preserved numbers of circulating B cells (Why this does not fit)
CD40 ligand deficiency can leave B cells present with low switched isotypes and normal or increased IgM. A helper-signaling deficiency favors recurrent infections, but it does not account for this characteristic combination of primary autoimmune endocrine failures.
Reasoning steps for option C
Which disorder could produce that laboratory finding?
CD40 ligand deficiency can leave B cells present with low switched isotypes and normal or increased IgM.
Why does that not explain the endocrine pattern well?
A helper-signaling deficiency favors recurrent infections, but it does not account for this characteristic combination of primary autoimmune endocrine failures.
D. Reduced apoptosis after Fas ligation in repeatedly stimulated lymphocytes (Why this does not fit)
Persistent lymphadenopathy, splenomegaly, autoimmune cytopenias, and alpha-beta double-negative T cells would support ALPS. Candidiasis with primary parathyroid and adrenal failure is the APECED pattern, rather than the lymphoproliferative pattern supplied by Fas failure.
Reasoning steps for option D
Which clinical pattern would support a Fas-associated defect?
Persistent lymphadenopathy, splenomegaly, autoimmune cytopenias, and alpha-beta double-negative T cells would support ALPS.
Which supplied combination instead favors the thymic display pathway?
Candidiasis with primary parathyroid and adrenal failure is the APECED pattern, rather than the lymphoproliferative pattern supplied by Fas failure.
Takeaway: Candidiasis with primary endocrine failure suggests impaired self-antigen screening, not absence of all lymphocytes.
A. Both clones are deleted because their receptors are unchanged (Why this does not fit)
A receptor must encounter its ligand; intrinsic recognition capacity is not equivalent to actual thymic exposure. Loss of the P peptide deprives clone P of its deleting stimulus despite an unchanged receptor.
Reasoning steps for option A
Why do unchanged receptors not guarantee an unchanged fate?
A receptor must encounter its ligand; intrinsic recognition capacity is not equivalent to actual thymic exposure.
Which environmental change alters that encounter?
Loss of the P peptide deprives clone P of its deleting stimulus despite an unchanged receptor.
B. More clone P cells escape; clone Q deletion persists (Best answer)
Only the thymic display needed to expose clone P to its self peptide depends on AIRE in this experiment. Its peptide remains displayed and its death machinery is unchanged, so deletion can continue while more clone P cells escape.
Reasoning steps for option B
Which deleting stimulus is lost after the intervention?
Only the thymic display needed to expose clone P to its self peptide depends on AIRE in this experiment.
What happens to clone Q?
Its peptide remains displayed and its death machinery is unchanged, so deletion can continue while more clone P cells escape.
C. Clone P deletion increases; more clone Q cells escape (Why this does not fit)
Increased effective display of its self peptide could increase its deleting stimulus. It reduces the P peptide while leaving the Q peptide unchanged, predicting the opposite selective effect.
Reasoning steps for option C
What would increase deletion of clone P?
Increased effective display of its self peptide could increase its deleting stimulus.
Does loss of epithelial AIRE produce that change here?
It reduces the P peptide while leaving the Q peptide unchanged, predicting the opposite selective effect.
D. Both clones escape because their self MHC is absent (Why this does not fit)
Without the relevant MHC, neither clone could receive its usual peptide-MHC recognition signal. MHC expression is explicitly unchanged; the intervention selectively alters expression of the P peptide.
Reasoning steps for option D
Why would loss of MHC affect more than one clone?
Without the relevant MHC, neither clone could receive its usual peptide-MHC recognition signal.
Why is that explanation inconsistent with the conditions?
MHC expression is explicitly unchanged; the intervention selectively alters expression of the P peptide.
Takeaway: Loss of one antigen-display pathway does not erase all negative selection.
A. Class switching changed isotype while preserving antigen-binding specificity (Why this does not fit)
It changes the immunoglobulin immunoglobulin constant region while retaining the rearranged antigen-binding specificity. The mu constant region is unchanged while a variable sequence and self-antigen binding both change.
Reasoning steps for option A
What would class switching change?
It changes the immunoglobulin immunoglobulin constant region while retaining the rearranged antigen-binding specificity.
Which findings contradict that interpretation here?
The mu constant region is unchanged while a variable sequence and self-antigen binding both change.
B. Functional anergy suppressed signaling while preserving receptor specificity (Why this does not fit)
It reduces functional responsiveness without requiring a new antigen-binding specificity. Renewed rearrangement and altered self-antigen binding demonstrate receptor revision, not merely reduced signaling through an unchanged receptor.
Reasoning steps for option B
What would anergy primarily change?
It reduces functional responsiveness without requiring a new antigen-binding specificity.
What additional observation requires a different explanation?
Renewed rearrangement and altered self-antigen binding demonstrate receptor revision, not merely reduced signaling through an unchanged receptor.
C. Receptor editing changed specificity while preserving the IgM isotype (Best answer)
A new kappa variable sequence accompanies reduced binding to the original self antigen. The mu constant region and viable descendants remain, supporting receptor editing rather than an isotype change or elimination of the cell.
Reasoning steps for option C
Which observation identifies a specificity-changing event?
A new kappa variable sequence accompanies reduced binding to the original self antigen.
Why is this not class switching or deletion?
The mu constant region and viable descendants remain, supporting receptor editing rather than an isotype change or elimination of the cell.
D. Negative selection deleted the cells while preserving their receptor sequence (Why this does not fit)
The selected self-reactive cell is eliminated rather than maintained as viable descendants with a revised receptor. The tracked descendants survive and carry a new kappa variable sequence with lower self binding.
Reasoning steps for option D
What is the outcome of deletion?
The selected self-reactive cell is eliminated rather than maintained as viable descendants with a revised receptor.
What directly opposes that explanation?
The tracked descendants survive and carry a new kappa variable sequence with lower self binding.
A. Persistent intrinsic anergy of the mature responder (Why this does not fit)
The responder would remain hyporesponsive even without the external suppressive population. Removing the other population restores division and adding it back suppresses division, favoring an external regulatory effect.
Reasoning steps for option A
What would persistent intrinsic anergy predict after purification?
The responder would remain hyporesponsive even without the external suppressive population.
How does the observed recovery distinguish this experiment?
Removing the other population restores division and adding it back suppresses division, favoring an external regulatory effect.
B. Loss of cognate recognition through receptor editing (Why this does not fit)
It would revise antigen-binding specificity, classically in developing B cells. The same mature T-cell clone responds to the same peptide after population removal, showing that recognition was not lost.
Reasoning steps for option B
What would receptor editing change?
It would revise antigen-binding specificity, classically in developing B cells.
Why does unchanged recognition not fit this explanation?
The same mature T-cell clone responds to the same peptide after population removal, showing that recognition was not lost.
C. Peripheral suppression of a viable mature responder (Best answer)
Responsiveness follows the presence of another lymphocyte population rather than a change in peptide display or responder survival. The experiment involves a mature clone in a lymph node, not selection of a developing thymocyte.
Reasoning steps for option C
What does the removal and add-back experiment localize?
Responsiveness follows the presence of another lymphocyte population rather than a change in peptide display or responder survival.
Why is the effect peripheral rather than central?
The experiment involves a mature clone in a lymph node, not selection of a developing thymocyte.
D. Central deletion of a developing self-reactive thymocyte (Why this does not fit)
It would eliminate a developing self-reactive thymocyte during repertoire selection. This clone is mature, remains viable, and resumes division when a separate population is removed.
Reasoning steps for option D
What would central deletion do to the tested clone?
It would eliminate a developing self-reactive thymocyte during repertoire selection.
Why can that not explain the add-back result?
This clone is mature, remains viable, and resumes division when a separate population is removed.
Takeaway: A reversible add-back effect identifies an external regulator of a living responder.
A. Poor deletion after Fas ligation in repeatedly stimulated lymphocytes (Why this does not fit)
A Fas-pathway defect suggests ALPS with chronic lymphoproliferation and autoimmune cytopenias. Early enteropathy, eczema, and insulin-deficient diabetes form the IPEX pattern rather than the typical ALPS presentation.
Reasoning steps for option A
What disorder is suggested by defective Fas-induced deletion?
A Fas-pathway defect suggests ALPS with chronic lymphoproliferation and autoimmune cytopenias.
Why is that a less direct explanation for this infant?
Early enteropathy, eczema, and insulin-deficient diabetes form the IPEX pattern rather than the typical ALPS presentation.
B. Poor suppression of responder T-cell proliferation by the regulatory fraction (Best answer)
The combination in a young boy strongly suggests IPEX, a FOXP3-associated disorder of immune regulation. A suppression assay measures whether the regulatory fraction restrains responders; counts alone can be normal despite defective regulatory function.
Reasoning steps for option B
What unifies the endocrine, intestinal, and skin findings?
The combination in a young boy strongly suggests IPEX, a FOXP3-associated disorder of immune regulation.
Which assay tests the affected function rather than cell presence?
A suppression assay measures whether the regulatory fraction restrains responders; counts alone can be normal despite defective regulatory function.
C. Poor presentation of tissue-restricted self peptides by thymic epithelial cells (Why this does not fit)
AIRE-associated APECED impairs thymic display of selected tissue-restricted self antigens. The male-infant combination of enteropathy, eczema, and insulin-deficient diabetes favors IPEX over candidiasis with parathyroid and adrenal failure.
Reasoning steps for option C
Which tolerance disorder impairs that display?
AIRE-associated APECED impairs thymic display of selected tissue-restricted self antigens.
Which clinical distinction favors regulatory failure here?
The male-infant combination of enteropathy, eczema, and insulin-deficient diabetes favors IPEX over candidiasis with parathyroid and adrenal failure.
D. Poor class switching after helper T cells contact otherwise competent B cells (Why this does not fit)
CD40 ligand deficiency can impair class switching despite preserved B-cell numbers. Counts do not decide between these disorders; the infant has prominent early multisystem autoimmunity rather than the characteristic switched-isotype deficiency and infection pattern.
Reasoning steps for option D
What would a failure of the helper contact suggest?
CD40 ligand deficiency can impair class switching despite preserved B-cell numbers.
Why do normal counts not make that the preferred answer?
Counts do not decide between these disorders; the infant has prominent early multisystem autoimmunity rather than the characteristic switched-isotype deficiency and infection pattern.
Takeaway: Preserved lymphocyte numbers do not establish effective immune regulation.
A. The common antigen-presenting cells lack sufficient costimulatory capacity (Why this does not fit)
It would tend to lower activation across cultures using the same antigen-presenting cells. Responder-only division is high, and suppression changes specifically with the source of regulatory cells.
Reasoning steps for option A
How would poor costimulation affect responder-only cultures?
It would tend to lower activation across cultures using the same antigen-presenting cells.
Which measurements argue against that as the principal defect?
Responder-only division is high, and suppression changes specifically with the source of regulatory cells.
B. The patient responders lack an adequate proliferative response (Why this does not fit)
Patient responders would divide poorly even without regulatory cells. Patient responders divide at 77% alone, comparable with the 80% normal-responder baseline.
Reasoning steps for option B
What would a primary proliferative defect predict?
Patient responders would divide poorly even without regulatory cells.
Which control excludes that explanation for this assay?
Patient responders divide at 77% alone, comparable with the 80% normal-responder baseline.
C. The patient responders are intrinsically resistant to suppression (Why this does not fit)
Normal regulatory cells would fail to restrain patient responders. No. Normal regulators reduce patient-responder division to 20%, close to the suppressed normal-responder value.
Reasoning steps for option C
What would responder resistance predict?
Normal regulatory cells would fail to restrain patient responders.
Does the observed reciprocal culture show resistance?
No. Normal regulators reduce patient-responder division to 20%, close to the suppressed normal-responder value.
D. The patient regulatory cells have deficient suppressive function (Best answer)
The patient responders can still be restrained, since their division falls from 77% to 20%. Patient regulators leave normal responders near their unsuppressed baseline, localizing the measured defect to regulatory function.
Reasoning steps for option D
What does suppression of patient responders by normal regulators show?
The patient responders can still be restrained, since their division falls from 77% to 20%.
Which reciprocal result identifies the deficient compartment?
Patient regulators leave normal responders near their unsuppressed baseline, localizing the measured defect to regulatory function.
Takeaway: Reciprocal substitution separates defective regulators from responders that resist regulation.
A. The CD25-positive count overestimates the functional regulatory population (Best answer)
Activated conventional T cells as well as regulatory T cells can express CD25. Most sorted cells fail to restrain independent responders, so labeling the entire CD25-positive population regulatory overstates the functional population.
Reasoning steps for option A
Why can CD25 positivity rise after an infection?
Activated conventional T cells as well as regulatory T cells can express CD25.
What does the suppression assay add to the count?
Most sorted cells fail to restrain independent responders, so labeling the entire CD25-positive population regulatory overstates the functional population.
B. The entire CD25-positive population consists of functional regulatory cells (Why this does not fit)
High CD25 expression is commonly included in the phenotype used to enrich regulatory T cells. Most of the population lacks demonstrated suppressive function and the full regulatory phenotype.
Reasoning steps for option B
Why might that classification initially appear plausible?
High CD25 expression is commonly included in the phenotype used to enrich regulatory T cells.
Which finding prevents applying that label to every sorted cell?
Most of the population lacks demonstrated suppressive function and the full regulatory phenotype.
C. The postinfection rise establishes defective thymic self-antigen display (Why this does not fit)
It could alter developmental selection of self-reactive T cells before they enter the periphery. It measures a transient peripheral marker-positive population and its suppressive function, not thymic antigen expression or negative selection.
Reasoning steps for option C
What would impaired thymic self-antigen display affect?
It could alter developmental selection of self-reactive T cells before they enter the periphery.
What does this study actually measure?
It measures a transient peripheral marker-positive population and its suppressive function, not thymic antigen expression or negative selection.
D. The CD25 increase establishes loss of Fas-dependent cell deletion (Why this does not fit)
Persistent lymphoproliferation, autoimmune cytopenias, and an abnormal Fas-pathway evaluation would support such a defect. CD25 expression after infection identifies an activation-associated phenotype, not a demonstrated apoptosis defect.
Reasoning steps for option D
What else would support a Fas-associated survival defect?
Persistent lymphoproliferation, autoimmune cytopenias, and an abnormal Fas-pathway evaluation would support such a defect.
Why does this observation not establish that mechanism?
CD25 expression after infection identifies an activation-associated phenotype, not a demonstrated apoptosis defect.
Takeaway: A shared surface marker cannot replace a functional definition.
A. Fas signaling kills the APCs, reducing the number of peptide-bearing cells (Why this does not fit)
Fewer viable peptide-bearing cells could reduce stimulation of fresh responders. Antigen presentation remains intact, and selectively blocking CTLA-4 internalization prevents CD86 transfer and suppression.
Reasoning steps for option A
How could loss of antigen-presenting cells reduce IL-2?
Fewer viable peptide-bearing cells could reduce stimulation of fresh responders.
Why does the evidence instead favor ligand trafficking?
Antigen presentation remains intact, and selectively blocking CTLA-4 internalization prevents CD86 transfer and suppression.
B. Regulatory cytokines reduce APC ligand synthesis without ligand transfer (Why this does not fit)
Reduced production could limit replenishment of the APC surface pool. Pre-existing labeled CD86 appears inside regulatory cells, demonstrating transfer rather than merely lower production.
Reasoning steps for option B
How could reduced ligand synthesis eventually lower surface CD86?
Reduced production could limit replenishment of the APC surface pool.
Which observation requires more than reduced synthesis?
Pre-existing labeled CD86 appears inside regulatory cells, demonstrating transfer rather than merely lower production.
C. CTLA-4 internalizes APC ligands, reducing later CD28 costimulation (Best answer)
Its appearance inside regulatory-cell vesicles supports physical acquisition and internalization of CD86. Less CD86 remains available to stimulate their CD28; preventing CTLA-4 internalization preserves that resource and prevents the measured suppression.
Reasoning steps for option C
Where does the labeled APC ligand go?
Its appearance inside regulatory-cell vesicles supports physical acquisition and internalization of CD86.
Why are fresh responders then less active?
Less CD86 remains available to stimulate their CD28; preventing CTLA-4 internalization preserves that resource and prevents the measured suppression.
D. CTLA-4 signals inside fresh responders, reducing their peptide recognition (Why this does not fit)
An inhibitory receptor on a responder can lower signaling within that cell. The responders arrive later, while labeled APC CD86 has already entered regulatory cells; that transfer and its interruption are central to the result.
Reasoning steps for option D
How could cell-intrinsic inhibitory signaling reduce a response?
An inhibitory receptor on a responder can lower signaling within that cell.
Why does it not explain the tracked sequence here?
The responders arrive later, while labeled APC CD86 has already entered regulatory cells; that transfer and its interruption are central to the result.
Takeaway: CTLA-4 can restrain other cells by reducing the costimulatory ligands available to them.
A. Reduced cytokine production after calcineurin-dependent NFAT activation (Why this does not fit)
It would reduce transcription supporting T-cell activation, including IL-2 production. The supplied pattern involves inappropriate lymphocyte persistence with autoimmunity, rather than evidence of a primary inability to initiate activation.
Reasoning steps for option A
What would deficient NFAT-dependent activation tend to reduce?
It would reduce transcription supporting T-cell activation, including IL-2 production.
Why is that less direct than a survival defect?
The supplied pattern involves inappropriate lymphocyte persistence with autoimmunity, rather than evidence of a primary inability to initiate activation.
B. Reduced class switching after CD40 stimulation of mature B cells (Why this does not fit)
It would reduce switched antibody isotypes and favor recurrent infections. It does not explain the characteristic double-negative T-cell accumulation with chronic lymphoproliferation and autoimmune cytopenias.
Reasoning steps for option B
What would a class-switching defect most directly produce?
It would reduce switched antibody isotypes and favor recurrent infections.
Why is it not the best link between these findings?
It does not explain the characteristic double-negative T-cell accumulation with chronic lymphoproliferation and autoimmune cytopenias.
C. Reduced death after Fas stimulation of activated lymphocytes (Best answer)
Chronic lymphoid enlargement with autoimmune cytopenias and alpha-beta double-negative T cells strongly supports ALPS. Impaired Fas-dependent apoptosis permits inappropriate persistence of activated lymphocytes; functional results and genetic testing must still be interpreted together.
Reasoning steps for option C
How do the organ and blood findings fit together?
Chronic lymphoid enlargement with autoimmune cytopenias and alpha-beta double-negative T cells strongly supports ALPS.
Which function links persistence to immune dysregulation?
Impaired Fas-dependent apoptosis permits inappropriate persistence of activated lymphocytes; functional results and genetic testing must still be interpreted together.
D. Reduced self-antigen expression in medullary thymic epithelial cells (Why this does not fit)
AIRE-associated APECED commonly combines candidiasis with primary endocrine autoimmunity. His dominant pattern is persistent lymphoproliferation with autoimmune blood-cell destruction and alpha-beta double-negative T cells.
Reasoning steps for option D
Which syndrome commonly reflects impaired thymic self-antigen display?
AIRE-associated APECED commonly combines candidiasis with primary endocrine autoimmunity.
What evidence points elsewhere in this boy?
His dominant pattern is persistent lymphoproliferation with autoimmune blood-cell destruction and alpha-beta double-negative T cells.
Takeaway: Immune cytopenias plus persistent lymphoproliferation require a unifying immune-regulatory explanation.
The combination supports an ALPS evaluation, in which alpha-beta double-negative T cells are characteristic. Requiring alpha-beta TCR expression excludes gamma-delta cells while retaining CD3-positive cells lacking both CD4 and CD8.
Reasoning steps for option A
Which disorder is supported by the clinical and functional findings?
The combination supports an ALPS evaluation, in which alpha-beta double-negative T cells are characteristic.
Which markers exclude the stated confounder?
Requiring alpha-beta TCR expression excludes gamma-delta cells while retaining CD3-positive cells lacking both CD4 and CD8.
B. CD3 positive, gamma-delta TCR positive, CD4 negative, CD8 negative (Why this does not fit)
It identifies T cells that lack both CD4 and CD8. It specifically selects the gamma-delta population that the question asks to exclude rather than the characteristic alpha-beta ALPS population.
Reasoning steps for option B
Why might this gate initially look suitable?
It identifies T cells that lack both CD4 and CD8.
Why is it the wrong population for this request?
It specifically selects the gamma-delta population that the question asks to exclude rather than the characteristic alpha-beta ALPS population.
C. CD3 positive, alpha-beta TCR positive, CD4 negative, CD8 positive (Why this does not fit)
It includes conventional alpha-beta CD8 T cells. The characteristic population being quantified is negative for CD8 as well as CD4.
Reasoning steps for option C
Which major population does this gate include?
It includes conventional alpha-beta CD8 T cells.
Which criterion does it fail?
The characteristic population being quantified is negative for CD8 as well as CD4.
D. CD3 positive, alpha-beta TCR positive, CD4 positive, CD8 negative (Why this does not fit)
It includes conventional alpha-beta CD4 T cells rather than a double-negative subset. The requested abnormal population lacks both CD4 and CD8, not just CD8.
Reasoning steps for option D
Which major population does this gate include?
It includes conventional alpha-beta CD4 T cells rather than a double-negative subset.
Why does that not target the characteristic expansion?
The requested abnormal population lacks both CD4 and CD8, not just CD8.
Takeaway: Double-negative is incomplete without identifying the TCR lineage.
A. A germline heterozygous variant is equally represented in every tested tissue (Why this does not fit)
It would generally be detectable in independent constitutional tissues as well as blood, subject to assay performance. The variant is concentrated in a selected lymphocyte population and is not detected in the tested fibroblasts.
Reasoning steps for option A
What pattern would a broadly present germline heterozygous variant usually produce?
It would generally be detectable in independent constitutional tissues as well as blood, subject to assay performance.
What makes that interpretation less consistent here?
The variant is concentrated in a selected lymphocyte population and is not detected in the tested fibroblasts.
B. The negative routine blood test excludes a pathogenic FAS contribution (Why this does not fit)
It establishes that the variant was not detected in that sample with that method and sensitivity. The pathogenic variant is demonstrated in the clinically relevant population, showing that bulk testing missed rather than excluded it.
Reasoning steps for option B
What does a negative test actually establish?
It establishes that the variant was not detected in that sample with that method and sensitivity.
Why is exclusion unjustified after the sorted-cell result?
The pathogenic variant is demonstrated in the clinically relevant population, showing that bulk testing missed rather than excluded it.
C. The variant demonstrates lymphoma as the source of the lymphoid enlargement (Why this does not fit)
Yes, somatic mutations can occur in malignant populations. Somatic FAS variants can cause nonmalignant ALPS; malignancy still requires its own clinical and tissue assessment.
Reasoning steps for option C
Can somatic variants occur in malignant cells?
Yes, somatic mutations can occur in malignant populations.
Why does somatic FAS detection not itself diagnose lymphoma?
Somatic FAS variants can cause nonmalignant ALPS; malignancy still requires its own clinical and tissue assessment.
D. A postzygotic variant is enriched in the affected lymphocyte population (Best answer)
A pathogenic variant present in a restricted population can be diluted below the detection limit when all blood cells are tested together. Enrichment in double-negative cells with no detection in fibroblasts supports somatic mosaicism, although it does not map every tissue in the body.
Reasoning steps for option D
Why can sorted cells reveal a variant missed in bulk blood?
A pathogenic variant present in a restricted population can be diluted below the detection limit when all blood cells are tested together.
How does the tissue comparison affect the interpretation?
Enrichment in double-negative cells with no detection in fibroblasts supports somatic mosaicism, although it does not map every tissue in the body.
Takeaway: An unrevealing bulk test can miss a pathogenic variant concentrated in a selected cell population.
A. Attribute the symptoms to hemolysis and repeat only blood counts (Why this does not fit)
Autoimmune hemolytic anemia is a recognized complication and can contribute to fatigue or systemic symptoms. A rapidly enlarging focal node with night sweats and weight loss requires nodal evaluation even if a cytopenia is also found.
Reasoning steps for option A
Why might hemolysis be considered in ALPS?
Autoimmune hemolytic anemia is a recognized complication and can contribute to fatigue or systemic symptoms.
Which finding remains unexplained by that limited approach?
A rapidly enlarging focal node with night sweats and weight loss requires nodal evaluation even if a cytopenia is also found.
B. Begin empiric corticosteroids and assess nodal size at routine follow-up (Why this does not fit)
ALPS can cause symptomatic immune dysregulation and nonmalignant lymphoid enlargement. The new focal growth and systemic symptoms require evaluation for lymphoma; empiric treatment should not replace or obscure that diagnostic assessment.
ALPS can cause symptomatic immune dysregulation and nonmalignant lymphoid enlargement.
Why is it not the preferred first response to this change?
The new focal growth and systemic symptoms require evaluation for lymphoma; empiric treatment should not replace or obscure that diagnostic assessment.
C. Continue serial ultrasonography using the established surveillance interval (Why this does not fit)
It can fit a stable baseline pattern without new concerning features. Rapid change, night sweats, and weight loss create a new diagnostic problem rather than unchanged chronic adenopathy.
Reasoning steps for option C
When might routine surveillance fit?
It can fit a stable baseline pattern without new concerning features.
What makes the old interval insufficient here?
Rapid change, night sweats, and weight loss create a new diagnostic problem rather than unchanged chronic adenopathy.
D. Arrange prompt hematology evaluation and diagnostic tissue sampling (Best answer)
Rapid focal enlargement with systemic symptoms differs from the previously stable symmetric pattern. ALPS carries increased lymphoma risk, so this change warrants prompt evaluation rather than presuming all lymphoid enlargement is nonmalignant.
Reasoning steps for option D
Why should the new node not simply be labeled baseline ALPS?
Rapid focal enlargement with systemic symptoms differs from the previously stable symmetric pattern.
What additional risk makes tissue assessment important?
ALPS carries increased lymphoma risk, so this change warrants prompt evaluation rather than presuming all lymphoid enlargement is nonmalignant.
Takeaway: A known explanation for chronic nodes must not obscure a newly concerning pattern.
A. Defective production of Fas ligand by the patient lymphocytes (Why this does not fit)
Yes, too little endogenous ligand could reduce receptor engagement. Fas ligand is supplied externally and binds normally, yet downstream caspase activation still fails.
Reasoning steps for option A
Could inadequate ligand production reduce death in some settings?
Yes, too little endogenous ligand could reduce receptor engagement.
Why does ligand production not explain this experiment?
Fas ligand is supplied externally and binds normally, yet downstream caspase activation still fails.
B. Defective release of mitochondrial apoptotic factors after cellular stress (Why this does not fit)
It would interfere with the separate mitochondrial apoptosis stimulus. The mitochondrial stimulus still activates executioner caspases and causes death, arguing against that being the demonstrated lesion.
Reasoning steps for option B
Which experimental pathway would this defect disrupt?
It would interfere with the separate mitochondrial apoptosis stimulus.
What does the intact control response show?
The mitochondrial stimulus still activates executioner caspases and causes death, arguing against that being the demonstrated lesion.
C. Defective executioner caspases shared by both apoptotic pathways (Why this does not fit)
It would impair the downstream cell-death response regardless of whether the initiating stimulus was Fas or mitochondrial. Executioner activation and death remain normal after the mitochondrial stimulus, localizing failure upstream in the Fas route.
Reasoning steps for option C
How would a shared executioner defect affect both stimuli?
It would impair the downstream cell-death response regardless of whether the initiating stimulus was Fas or mitochondrial.
Which result opposes a shared downstream defect?
Executioner activation and death remain normal after the mitochondrial stimulus, localizing failure upstream in the Fas route.
D. Defective recruitment of death-signaling proteins downstream of Fas (Best answer)
Ligand binds the surface receptor, but the signal does not progress to caspase-8 activation. Normal executioner activation and death through an alternative route argue against a general inability to execute apoptosis, favoring proximal Fas-associated signaling.
Reasoning steps for option D
Which interval contains the demonstrated failure?
Ligand binds the surface receptor, but the signal does not progress to caspase-8 activation.
How does the mitochondrial control narrow that interval?
Normal executioner activation and death through an alternative route argue against a general inability to execute apoptosis, favoring proximal Fas-associated signaling.
Takeaway: A normal surface receptor does not establish an intact intracellular death signal.
A. A releases inhibitory restraint; B decreases costimulation (Why this does not fit)
It would treat the CTLA-4 fusion protein as though it blocked the CTLA-4 receptor and treat the antibody as though it occupied B7. A occupies B7, whereas B binds CTLA-4; their actual targets predict the opposite directional effects.
Reasoning steps for option A
Which assumption would produce this reversed prediction?
It would treat the CTLA-4 fusion protein as though it blocked the CTLA-4 receptor and treat the antibody as though it occupied B7.
Why does the binding information reject that assumption?
A occupies B7, whereas B binds CTLA-4; their actual targets predict the opposite directional effects.
B. A releases inhibitory restraint; B also releases inhibitory restraint (Why this does not fit)
Blocking CTLA-4 with B reduces an inhibitory influence. A is a ligand-binding fusion protein that prevents CD28 access, not an antibody that disables the CTLA-4 receptor.
Reasoning steps for option B
Why is the second half reasonable?
Blocking CTLA-4 with B reduces an inhibitory influence.
Why is the first half unsupported?
A is a ligand-binding fusion protein that prevents CD28 access, not an antibody that disables the CTLA-4 receptor.
C. A decreases costimulation; B releases inhibitory restraint (Best answer)
It limits access of CD28 to its costimulatory ligands, reducing the activating input. It reduces CTLA-4 restraint while leaving ligands available to CD28, favoring activation in the stated assay.
Reasoning steps for option C
What does occupation of CD80/CD86 by drug A prevent?
It limits access of CD28 to its costimulatory ligands, reducing the activating input.
What does drug B leave available after blocking CTLA-4?
It reduces CTLA-4 restraint while leaving ligands available to CD28, favoring activation in the stated assay.
D. A decreases costimulation; B also decreases costimulation (Why this does not fit)
A occupies the B7 ligands needed for CD28 costimulation. B does not occupy B7 or block CD28; it prevents the inhibitory CTLA-4 interaction instead.
Reasoning steps for option D
Why is the first half reasonable?
A occupies the B7 ligands needed for CD28 costimulation.
Why does the same conclusion not follow for B?
B does not occupy B7 or block CD28; it prevents the inhibitory CTLA-4 interaction instead.
Takeaway: A CTLA-4 fusion protein and an antibody against CTLA-4 do not have the same immune direction.
A. Less inhibition by both the PD-L1 and PD-L2 lines (Best answer)
PD-1 on the T cell can interact with PD-L1 or PD-L2. It blocks PD-1 rather than just one ligand, reducing the stated inhibitory interaction in both conditions; clinical antitumor benefit is not guaranteed.
Reasoning steps for option A
Which shared receptor can receive both inhibitory contacts?
PD-1 on the T cell can interact with PD-L1 or PD-L2.
Why should pembrolizumab affect both lines?
It blocks PD-1 rather than just one ligand, reducing the stated inhibitory interaction in both conditions; clinical antitumor benefit is not guaranteed.
B. Preserved PD-L1 inhibition, with less inhibition by PD-L2 (Why this does not fit)
It would require selective interference with the PD-L2 contact while preserving PD-L1 engagement. No. The drug targets the receptor shared by both ligands, not a PD-L2-specific structure.
Reasoning steps for option B
Which selectivity would this pattern require?
It would require selective interference with the PD-L2 contact while preserving PD-L1 engagement.
Does receptor-level PD-1 blockade have that stated selectivity?
No. The drug targets the receptor shared by both ligands, not a PD-L2-specific structure.
C. Less inhibition by PD-L1, with PD-L2 inhibition preserved (Why this does not fit)
A blocker directed specifically at PD-L1 could spare the PD-L2-to-PD-1 contact. Pembrolizumab binds the shared PD-1 receptor, so its target is not limited to PD-L1-bearing cells.
Reasoning steps for option C
Which targeting strategy could produce this pattern?
A blocker directed specifically at PD-L1 could spare the PD-L2-to-PD-1 contact.
Why is it not the predicted pattern for this drug?
Pembrolizumab binds the shared PD-1 receptor, so its target is not limited to PD-L1-bearing cells.
D. Preserved inhibition by both the PD-L1 and PD-L2 lines (Why this does not fit)
They could remain intact if the intervention acted elsewhere and did not interfere with PD-1 engagement. Adequate pembrolizumab exposure directly targets the receptor mediating the two inhibitory contacts in the experiment.
Reasoning steps for option D
When could both inhibitory interactions remain intact?
They could remain intact if the intervention acted elsewhere and did not interfere with PD-1 engagement.
Why does that not match this exposure?
Adequate pembrolizumab exposure directly targets the receptor mediating the two inhibitory contacts in the experiment.
Takeaway: Blocking a shared receptor can interrupt contacts with more than one ligand.
It targets CTLA-4, which interacts with CD80/CD86 rather than PD-L1. The treatment effect tracks PD-L1 expression and direct binding to the target cells, not a CTLA-4 interaction on T cells.
Reasoning steps for option A
Which checkpoint does ipilimumab block?
It targets CTLA-4, which interacts with CD80/CD86 rather than PD-L1.
Why does the assay identify a different interaction?
The treatment effect tracks PD-L1 expression and direct binding to the target cells, not a CTLA-4 interaction on T cells.
B. Atezolizumab (Best answer)
A PD-L1-specific blocker would reduce PD-L1 inhibition while preserving PD-L2 engagement of PD-1. Atezolizumab targets PD-L1 on the ligand-bearing cells, matching the observed localization and functional selectivity.
Reasoning steps for option B
Which binding target fits the two functional conditions?
A PD-L1-specific blocker would reduce PD-L1 inhibition while preserving PD-L2 engagement of PD-1.
Which named antibody also fits the binding localization?
Atezolizumab targets PD-L1 on the ligand-bearing cells, matching the observed localization and functional selectivity.
C. Nivolumab (Why this does not fit)
It is another antibody directed against PD-1. The antibody binds the PD-L1-bearing target cells and preserves PD-L2-mediated inhibition, both supporting a ligand-specific rather than shared-receptor target.
Reasoning steps for option C
Why is nivolumab a plausible checkpoint alternative?
It is another antibody directed against PD-1.
Which two results argue against that target?
The antibody binds the PD-L1-bearing target cells and preserves PD-L2-mediated inhibition, both supporting a ligand-specific rather than shared-receptor target.
D. Pembrolizumab (Why this does not fit)
It targets PD-1 on T cells rather than PD-L1 on the target cells. Shared receptor blockade would interfere with both ligand contacts, not selectively leave PD-L2 inhibition intact.
Reasoning steps for option D
Which molecule does pembrolizumab target?
It targets PD-1 on T cells rather than PD-L1 on the target cells.
How would that differ from the observed assay?
Shared receptor blockade would interfere with both ligand contacts, not selectively leave PD-L2 inhibition intact.
Takeaway: An antibody to one ligand can leave another ligand of the same receptor functional.
A. Reduced peptide-MHC display prevents cognate TCR engagement (Why this does not fit)
It could reduce the antigen-specific recognition input. Peptide recognition is equal while CD28 binding falls, separating costimulatory access from antigen display.
Reasoning steps for option A
How could poorer antigen display reduce IL-2?
It could reduce the antigen-specific recognition input.
Which control instead localizes the difference to costimulation?
Peptide recognition is equal while CD28 binding falls, separating costimulatory access from antigen display.
B. PD-1 engagement suppresses signaling independently of B7 binding (Why this does not fit)
It could reduce T-cell activation through an inhibitory pathway distinct from CTLA-4 competition. PD-1 is blocked in both conditions, whereas the measured change tracks CD28 access to the shared CTLA-4 ligands.
Reasoning steps for option B
What could PD-1 engagement do in another assay?
It could reduce T-cell activation through an inhibitory pathway distinct from CTLA-4 competition.
Why does that not account for this comparison?
PD-1 is blocked in both conditions, whereas the measured change tracks CD28 access to the shared CTLA-4 ligands.
C. CTLA-4 occupancy limits CD28 access to their shared ligands (Best answer)
Less CD28 binds when ligand-binding CTLA-4 is present. Competition for CD80/CD86 can limit CD28 access even when the total surface ligand pool remains unchanged.
Reasoning steps for option C
What changes despite unchanged total APC ligand abundance?
Less CD28 binds when ligand-binding CTLA-4 is present.
Which process explains that without internalization?
Competition for CD80/CD86 can limit CD28 access even when the total surface ligand pool remains unchanged.
D. CTLA-4 internalization depletes CD80/CD86 from the APC surface (Why this does not fit)
Normal CTLA-4 can acquire ligands from antigen-presenting cells and reduce their availability. The variant cannot internalize, and surface CD80/CD86 abundance remains constant.
Reasoning steps for option D
Why is ligand internalization a plausible competing mechanism?
Normal CTLA-4 can acquire ligands from antigen-presenting cells and reduce their availability.
Which two observations oppose that explanation in this assay?
The variant cannot internalize, and surface CD80/CD86 abundance remains constant.
Takeaway: Ligand competition and ligand internalization are related but distinguishable regulatory effects.
A. Conventional memory differentiation occurred with durable functional protection (Why this does not fit)
Stable memory-associated molecular features and sustained function after withdrawal would support it. The chromatin pattern remains distinct from conventional memory, and function falls again under persistent antigen.
Reasoning steps for option A
What evidence would support a durable memory interpretation?
Stable memory-associated molecular features and sustained function after withdrawal would support it.
Why do the supplied measurements not show that?
The chromatin pattern remains distinct from conventional memory, and function falls again under persistent antigen.
B. Functional recovery occurred without a durable memory-state reset (Best answer)
The cells regained some measured effector function during checkpoint blockade. They indicate that this improvement did not establish a durable conventional memory state in the continued-antigen setting.
Reasoning steps for option B
What does the rise in cytokine-producing cells establish?
The cells regained some measured effector function during checkpoint blockade.
What do persistent chromatin features and later decline add?
They indicate that this improvement did not establish a durable conventional memory state in the continued-antigen setting.
C. Antigen elimination caused the molecular pattern to become quiescent (Why this does not fit)
Antigen clearance could reduce ongoing stimulation and change the conditions governing cell function. Antigen remains abundant, and the measured molecular pattern remains distinct from conventional memory rather than establishing antigen clearance.
Reasoning steps for option C
How could removing antigen alter later stimulation?
Antigen clearance could reduce ongoing stimulation and change the conditions governing cell function.
Which condition contradicts that explanation?
Antigen remains abundant, and the measured molecular pattern remains distinct from conventional memory rather than establishing antigen clearance.
D. Blockade had no functional effect because chromatin remained unchanged (Why this does not fit)
They show that one aspect of the cell state did not reset. Interferon-gamma production rises during treatment; an unchanged molecular feature does not negate that measured functional improvement.
Reasoning steps for option D
Why might persistent chromatin features be mistaken for no effect?
They show that one aspect of the cell state did not reset.
Which independent measurement establishes a real functional effect?
Interferon-gamma production rises during treatment; an unchanged molecular feature does not negate that measured functional improvement.
Takeaway: Improved function during blockade is not the same measurement as a durable change in cell state.
A. Withhold the infusion and diagnose immune colitis without infectious testing (Why this does not fit)
Checkpoint therapy can produce inflammatory diarrhea and colitis. The recent antibiotic exposure and lack of stool evaluation leave infection unresolved; treatment exposure alone cannot establish the cause.
Reasoning steps for option A
Why is immune-mediated colitis an important concern?
Checkpoint therapy can produce inflammatory diarrhea and colitis.
Why is that concern not a complete diagnosis here?
The recent antibiotic exposure and lack of stool evaluation leave infection unresolved; treatment exposure alone cannot establish the cause.
B. Withhold the infusion and assess immune toxicity and infection promptly (Best answer)
A persistent increase of six stools above baseline is clinically significant during checkpoint therapy and warrants prompt assessment with temporary treatment withholding. Recent antibiotic exposure creates a competing infectious explanation; immune-related colitis and infection must be assessed rather than assigning cause from treatment history alone.
Reasoning steps for option B
Why is proceeding with the infusion inappropriate before evaluation?
A persistent increase of six stools above baseline is clinically significant during checkpoint therapy and warrants prompt assessment with temporary treatment withholding.
Why must the assessment include infection?
Recent antibiotic exposure creates a competing infectious explanation; immune-related colitis and infection must be assessed rather than assigning cause from treatment history alone.
C. Continue the infusion and wait for more than seven additional stools daily (Why this does not fit)
Stool increase over baseline helps grade diarrhea and guide management. Persistent symptoms at this level already merit withholding and assessment; escalation to a more severe grade is not a prerequisite for evaluating toxicity.
Reasoning steps for option C
Why might a severity threshold seem useful?
Stool increase over baseline helps grade diarrhea and guide management.
Why is waiting for a higher threshold unsafe reasoning?
Persistent symptoms at this level already merit withholding and assessment; escalation to a more severe grade is not a prerequisite for evaluating toxicity.
D. Continue the infusion and treat presumptive antibiotic-associated diarrhea symptomatically (Why this does not fit)
The recent antibiotic course is a plausible contributor to diarrhea. It does not exclude clinically important immune-related colitis or justify proceeding with the scheduled infusion before assessing persistent symptoms.
Reasoning steps for option D
Why might antibiotic-associated diarrhea be considered?
The recent antibiotic course is a plausible contributor to diarrhea.
What does that possibility fail to address?
It does not exclude clinically important immune-related colitis or justify proceeding with the scheduled infusion before assessing persistent symptoms.
Takeaway: Checkpoint exposure raises concern for immune toxicity but does not exclude infectious diarrhea.
A. Diagnose progression and change cancer therapy without evaluating inflammation (Why this does not fit)
Cancer progression can cause respiratory symptoms in a patient with metastatic disease. Measured tumors are smaller while new diffuse opacities and hypoxemia suggest a competing pulmonary process that must be assessed before attributing symptoms to progression.
Reasoning steps for option A
Why might progression enter a differential for worsening dyspnea?
Cancer progression can cause respiratory symptoms in a patient with metastatic disease.
What makes this proposed response incomplete?
Measured tumors are smaller while new diffuse opacities and hypoxemia suggest a competing pulmonary process that must be assessed before attributing symptoms to progression.
B. Start outpatient antibiotics and defer toxicity assessment until cultures return (Why this does not fit)
Cough and diffuse opacities can result from infection, and current testing is incomplete. Oxygen saturation of 87% with progressive dyspnea requires urgent support and parallel assessment for serious immune toxicity rather than postponing that evaluation.
Reasoning steps for option B
Why should infection remain under consideration?
Cough and diffuse opacities can result from infection, and current testing is incomplete.
Why is outpatient waiting not adequate here?
Oxygen saturation of 87% with progressive dyspnea requires urgent support and parallel assessment for serious immune toxicity rather than postponing that evaluation.
C. Continue treatment and repeat imaging after the next infusion cycle (Why this does not fit)
They suggest an antitumor response in the measured lesions. The new hypoxemia and opacities are a separate organ problem that can coexist with tumor response and requires urgent assessment.
Reasoning steps for option C
Why could the smaller tumor lesions appear reassuring?
They suggest an antitumor response in the measured lesions.
Why does that not justify delayed pulmonary evaluation?
The new hypoxemia and opacities are a separate organ problem that can coexist with tumor response and requires urgent assessment.
D. Withhold treatment and arrange urgent hospital assessment with oxygen support (Best answer)
New marked hypoxemia with progressive respiratory symptoms and diffuse opacities represents significant pulmonary disease, not a minor isolated cough. Checkpoint pneumonitis is a serious possibility, but infection and other causes must also be evaluated; tumor shrinkage does not establish pulmonary safety.
Reasoning steps for option D
Why does this presentation require urgent assessment?
New marked hypoxemia with progressive respiratory symptoms and diffuse opacities represents significant pulmonary disease, not a minor isolated cough.
What must the assessment distinguish?
Checkpoint pneumonitis is a serious possibility, but infection and other causes must also be evaluated; tumor shrinkage does not establish pulmonary safety.
Takeaway: Tumor shrinkage does not make new hypoxemia benign.
A. Vitiligo establishes response, so the imaging must represent transient inflammation (Why this does not fit)
Immune responses can create assessment challenges, and a single unexpected image may require clinical context and follow-up. The cohort includes nonresponders with vitiligo, and progression has been confirmed serially rather than inferred from one unexplained scan.
Reasoning steps for option A
Why can inflammation complicate interpretation during immunotherapy?
Immune responses can create assessment challenges, and a single unexpected image may require clinical context and follow-up.
Why does the skin finding not settle this case?
The cohort includes nonresponders with vitiligo, and progression has been confirmed serially rather than inferred from one unexplained scan.
B. Progression in one patient invalidates the cohort association with response (Why this does not fit)
It would require the proposed predictor to classify every relevant individual correctly. The cohort never showed perfect prediction; a difference in response frequencies can coexist with individual nonresponse.
Reasoning steps for option B
What would a perfect individual predictor require?
It would require the proposed predictor to classify every relevant individual correctly.
Why does a counterexample not erase the reported association?
The cohort never showed perfect prediction; a difference in response frequencies can coexist with individual nonresponse.
C. The two response frequencies show no association after accounting for group size (Why this does not fit)
Different denominators require comparison of proportions rather than response counts alone. Twelve of 17 is substantially higher than 14 of 50; unequal group size does not make those observed proportions equivalent.
Reasoning steps for option C
Why should group size be considered?
Different denominators require comparison of proportions rather than response counts alone.
What happens when those denominators are used?
Twelve of 17 is substantially higher than 14 of 50; unequal group size does not make those observed proportions equivalent.
D. Vitiligo is associated with response but does not establish it individually (Best answer)
Response occurred in about 71% with vitiligo versus 28% without it, showing an association in that cohort. Five of the 17 patients with vitiligo did not respond; depigmentation therefore cannot establish tumor response or override a confirmed assessment of progression.
Reasoning steps for option D
What do the two fractions show?
Response occurred in about 71% with vitiligo versus 28% without it, showing an association in that cohort.
Why is the separate patient compatible with those observations?
Five of the 17 patients with vitiligo did not respond; depigmentation therefore cannot establish tumor response or override a confirmed assessment of progression.
Takeaway: A cohort association can be real without predicting every individual outcome.
A. IL-2 receptor-associated cytokine signaling (Why this does not fit)
It would impair cellular responses to IL-2 after the cytokine is produced. It measures failure of IL-2 transcription with abnormal NFAT localization, which is upstream of signaling through the IL-2 receptor.
Reasoning steps for option A
What would an IL-2 receptor signaling defect primarily alter?
It would impair cellular responses to IL-2 after the cytokine is produced.
Why does this experiment identify an earlier event?
It measures failure of IL-2 transcription with abnormal NFAT localization, which is upstream of signaling through the IL-2 receptor.
B. mTOR-dependent growth signaling (Why this does not fit)
Sirolimus also binds FKBP12 but acts through a different downstream target, mTOR. Retention of phosphorylated NFAT and rescue by nuclear NFAT specifically localize the demonstrated block to its dephosphorylation and nuclear entry.
Reasoning steps for option B
Why is mTOR a credible alternative with an FKBP-binding drug?
Sirolimus also binds FKBP12 but acts through a different downstream target, mTOR.
Which functional result favors calcineurin rather than mTOR?
Retention of phosphorylated NFAT and rescue by nuclear NFAT specifically localize the demonstrated block to its dephosphorylation and nuclear entry.
C. CD28 binding to APC costimulatory ligands (Why this does not fit)
Loss of surface costimulation can reduce activation despite antigen recognition. Direct CD28 stimulation fails to rescue, while nuclear NFAT does, indicating an intracellular interruption beyond the surface contact.
Reasoning steps for option C
How could interrupted CD28 costimulation reduce IL-2?
Loss of surface costimulation can reduce activation despite antigen recognition.
Which intervention argues against that being the direct drug target?
Direct CD28 stimulation fails to rescue, while nuclear NFAT does, indicating an intracellular interruption beyond the surface contact.
D. Calcineurin phosphatase activity (Best answer)
The interruption lies after early calcium release but before normal NFAT nuclear entry; constitutively nuclear NFAT bypasses it. The tacrolimus-FKBP12 complex inhibits calcineurin, preventing NFAT dephosphorylation and reducing cytokine transcription.
Reasoning steps for option D
Where does the rescue experiment place the defect?
The interruption lies after early calcium release but before normal NFAT nuclear entry; constitutively nuclear NFAT bypasses it.
Why does calcineurin fit the drug interaction?
The tacrolimus-FKBP12 complex inhibits calcineurin, preventing NFAT dephosphorylation and reducing cytokine transcription.
Takeaway: FKBP12 binding alone is less informative than the downstream functional pattern.
A. Defective CD40 signaling within otherwise mature B cells (Why this does not fit)
Failure to receive helper signaling through CD40 can impair class switching and immune responses. Direct CD40 stimulation restores switching, demonstrating that the tested B-cell receptor pathway can function.
Reasoning steps for option A
Why could a B-cell CD40 defect cause a similar infection pattern?
Failure to receive helper signaling through CD40 can impair class switching and immune responses.
Which result argues against that location in this patient?
Direct CD40 stimulation restores switching, demonstrating that the tested B-cell receptor pathway can function.
B. Defective maturation that prevents production of circulating B cells (Why this does not fit)
It would leave very few circulating B cells and broadly reduced antibody production. B-cell numbers are preserved and the cells switch when directly stimulated; the problem is their helper interaction, not their absence.
Reasoning steps for option B
What would absent B-cell development usually produce?
It would leave very few circulating B cells and broadly reduced antibody production.
Which findings contradict that explanation?
B-cell numbers are preserved and the cells switch when directly stimulated; the problem is their helper interaction, not their absence.
C. Defective CD40 ligand expression on activated helper T cells (Best answer)
The B cells are present and can execute class switching when they receive the required receptor stimulation and cytokine support. It supports deficient delivery of CD40 ligand by the helper cells, fitting the CD40 ligand deficiency pattern.
Reasoning steps for option C
What does successful direct CD40 stimulation show?
The B cells are present and can execute class switching when they receive the required receptor stimulation and cytokine support.
Where does failure with patient helper cells localize the defect?
It supports deficient delivery of CD40 ligand by the helper cells, fitting the CD40 ligand deficiency pattern.
D. Defective immunoglobulin-switch recombination within mature B cells (Why this does not fit)
Providing an upstream helper signal would not restore the disabled downstream recombination process. The B cells switch after direct CD40 stimulation with cytokines, favoring a missing helper signal rather than an intrinsic inability to switch.
Reasoning steps for option D
What would a fixed switching-machinery defect predict?
Providing an upstream helper signal would not restore the disabled downstream recombination process.
How does the rescue distinguish this case?
The B cells switch after direct CD40 stimulation with cytokines, favoring a missing helper signal rather than an intrinsic inability to switch.
Takeaway: Rescue by direct receptor stimulation can distinguish a missing helper signal from an intrinsic B-cell defect.
A. V-beta-directed recruitment with an important costimulatory contribution (Best answer)
The toxin recruits cells through a superantigen-type interaction involving particular TCR V-beta regions and MHC class II rather than ordinary peptide-specific recognition. Costimulation contributes to the inflammatory response; bypassing ordinary specificity does not mean costimulation is irrelevant.
Reasoning steps for option A
What explains activation of clones with different ordinary peptide specificities?
The toxin recruits cells through a superantigen-type interaction involving particular TCR V-beta regions and MHC class II rather than ordinary peptide-specific recognition.
What does reduced cytokine production after B7-2/CD28 blockade establish?
Costimulation contributes to the inflammatory response; bypassing ordinary specificity does not mean costimulation is irrelevant.
B. Conventional peptide-specific recruitment independent of costimulatory receptor engagement (Why this does not fit)
Conventional peptide specificity would not explain broad recruitment tied to a shared V-beta family. It also fails to explain why blocking that costimulatory interaction markedly reduces cytokine production.
Reasoning steps for option B
How does this description account for the selection of responding clones?
Conventional peptide specificity would not explain broad recruitment tied to a shared V-beta family.
How does it account for the B7-2/CD28 intervention?
It also fails to explain why blocking that costimulatory interaction markedly reduces cytokine production.
C. Conventional peptide-specific recruitment with an important costimulatory contribution (Why this does not fit)
Reduced cytokine production after B7-2/CD28 blockade supports a costimulatory contribution. Recruitment across different ordinary peptide specificities according to V-beta family does not fit conventional peptide-specific recognition.
Reasoning steps for option C
Which part of this description fits the blocking experiment?
Reduced cytokine production after B7-2/CD28 blockade supports a costimulatory contribution.
Which part fails to explain the recruited clones?
Recruitment across different ordinary peptide specificities according to V-beta family does not fit conventional peptide-specific recognition.
D. V-beta-directed recruitment independent of costimulatory receptor engagement (Why this does not fit)
The shared V-beta family despite different ordinary peptide specificities fits superantigen-type recruitment. Marked cytokine reduction after B7-2/CD28 blockade shows that the response is not independent of that costimulatory interaction.
Reasoning steps for option D
Which part fits the pattern of responding T-cell clones?
The shared V-beta family despite different ordinary peptide specificities fits superantigen-type recruitment.
Which part contradicts the intervention result?
Marked cytokine reduction after B7-2/CD28 blockade shows that the response is not independent of that costimulatory interaction.
Takeaway: Broad TCR recruitment and costimulatory dependence are compatible, not contradictory.
A. Occupy CD80/CD86 using a soluble CTLA-4 fusion protein (Best answer)
More APC costimulatory ligand remains available, accompanying excessive responder proliferation. A soluble CTLA-4 fusion protein can restrict CD28 access to CD80/CD86, directly reducing the excess costimulatory opportunity; this is a mechanistic prediction, not a patient-specific prescription.
Reasoning steps for option A
What functional consequence of the variant is demonstrated?
More APC costimulatory ligand remains available, accompanying excessive responder proliferation.
How would ligand occupation compensate in this experiment?
A soluble CTLA-4 fusion protein can restrict CD28 access to CD80/CD86, directly reducing the excess costimulatory opportunity; this is a mechanistic prediction, not a patient-specific prescription.
B. Increase CD28 stimulation using an agonistic receptor antibody (Why this does not fit)
It would increase the activating costimulatory input to responder T cells. The assay already shows excessive proliferation with excess ligand access; adding activating input would reinforce rather than offset that pattern.
Reasoning steps for option B
What signal would direct CD28 stimulation increase?
It would increase the activating costimulatory input to responder T cells.
Why does that oppose the desired correction?
The assay already shows excessive proliferation with excess ligand access; adding activating input would reinforce rather than offset that pattern.
C. Prevent remaining CTLA-4 receptors from binding APC ligands (Why this does not fit)
It would reduce the residual inhibitory control provided by CTLA-4. The demonstrated defect is already insufficient restriction of ligand availability, so further checkpoint blockade would not compensate for it.
Reasoning steps for option C
What would further CTLA-4 blockade do to restraint?
It would reduce the residual inhibitory control provided by CTLA-4.
Why is that the wrong direction for this assay?
The demonstrated defect is already insufficient restriction of ligand availability, so further checkpoint blockade would not compensate for it.
D. Increase CD86 abundance on the antigen-presenting cell surface (Why this does not fit)
It would add ligand available for CD28-mediated costimulation. Excess accessible CD86 is the measured intermediate connecting reduced regulatory restraint to responder hyperproliferation.
Reasoning steps for option D
What resource would this intervention add?
It would add ligand available for CD28-mediated costimulation.
Why does increasing that resource not address the observed problem?
Excess accessible CD86 is the measured intermediate connecting reduced regulatory restraint to responder hyperproliferation.
Takeaway: Insufficient inhibitory checkpoint function calls for less activating access in this assay, not further checkpoint blockade.