
Choose an answer, then open any option to work its reasoning.
MSK · Autoimmune & Rheumatology
The Big 5 Autoimmune Diseases: Antibodies That Never Lie
SLE, RA, scleroderma, dermatomyositis, and Sjogren's all bring fatigue, joint pain, and a positive ANA. One skin finding and one antibody separate them every time.
What this page makes you able to do
- Match each Big 5 disease to its signature antibody fingerprint
- Separate SLE from drug-induced lupus by complement and anti-histone
- Recognize lupus nephritis and start the biopsy-to-induction pathway
- Choose first-line therapy for RA, scleroderma renal crisis, and Raynaud's
- Dr. Fatima Ali, DOPsychiatry residentPrimary reviewer
Last reviewed
The pearl
Pattern first: butterfly rash + low complements = SLE, erosions + anti-CCP = RA, tight skin + Raynaud's = scleroderma, heliotrope + proximal weakness = dermatomyositis, dry eyes + dry mouth = Sjogren's. The antibody is the tiebreaker.
Prove it
Opening question
Answer before you read anything, then keep the mechanism in mind through every section.
A 32-year-old woman presents with fatigue, joint pain, and a facial rash that spares the nasolabial folds. Labs show ANA positive and low C3 and C4. She also reports fingertip pain when her hands get cold.What is the most likely diagnosis?
- Why this failsRA gives symmetric small-joint polyarthritis with morning stiffness >1 hour and erosions on imaging, but it has no malar rash and does not consume complement. Rule: RA destroys joints; it does not consume complement.
- Why this is rightThe malar rash sparing the nasolabial folds plus low C3/C4 is immune-complex consumption, and the cold-induced fingertip pain is Raynaud's. The low complements are the clincher: SLE eats its own complement. Rule: malar rash sparing the nasolabial folds with low C3/C4 is SLE until proven otherwise.
- Why this failsScleroderma gives skin tightening and sclerodactyly with Raynaud's often first, but no butterfly rash and no complement consumption. Rule: scleroderma tightens the skin; it does not spare the nasolabial folds.
- Why this failsDermatomyositis rashes live on the eyelids (heliotrope) and knuckles (Gottron's papules), not the cheeks, and the dominant feature is proximal weakness. Rule: eyelids = dermatomyositis; cheeks = SLE.
- Why this failsSjogren's hallmark is sicca: dry eyes and dry mouth with parotid enlargement; it does not produce a malar rash or low complements. Rule: sicca symptoms, not butterfly rash, define Sjogren's.
Work the reasoning
It spares the nasolabial folds, a pattern no other Big 5 rash shares; the butterfly is SLE's logo.
SLE deposits immune complexes that consume complement; RA, scleroderma, dermatomyositis, and Sjogren's do not lower complement.
That is Raynaud's, common in SLE and scleroderma; with the malar rash and low complements it reinforces SLE.
The answer is Systemic lupus erythematosus: butterfly rash plus complement consumption, with Raynaud's as the second clue.
KNOW YOUR ENEMIES
The Big 5 Fingerprints
Tap each disease. Notice the one finding and the one antibody that make it different from the others.
Five diseases, five fingerprints. Each one can present with fatigue, joint pain, and a positive ANA, so the stem separates them with skin, joints, and serology. Learn the pair that belongs to each disease, and the antibody stops being a list and becomes a signature.
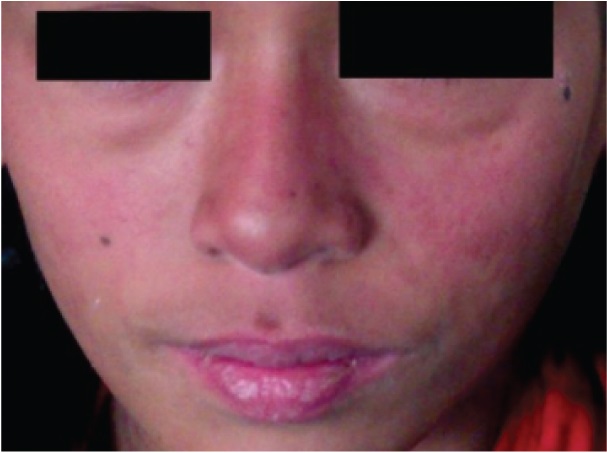
Young women 15-45 (9:1 F:M), more severe in Black and Hispanic patients. Malar (butterfly) rash spares the nasolabial folds and is photosensitive. It attacks everything: joints (non-erosive, Jaccoud's arthropathy), kidneys (lupus nephritis), serosa, blood, and brain (seizures or psychosis).
Antibodies: anti-dsDNA (specific, tracks disease activity) and anti-Smith (most specific of all). ANA positive in ~95%. Unique labs: low C3/C4, false-positive VDRL/RPR, pancytopenia.
Trap: drug-induced lupus (hydralazine, procainamide, isoniazid, quinidine, etanercept) is anti-histone positive but spares the kidneys and CNS.
Rule: butterfly rash + low complements = SLE; anti-Smith is the most specific antibody.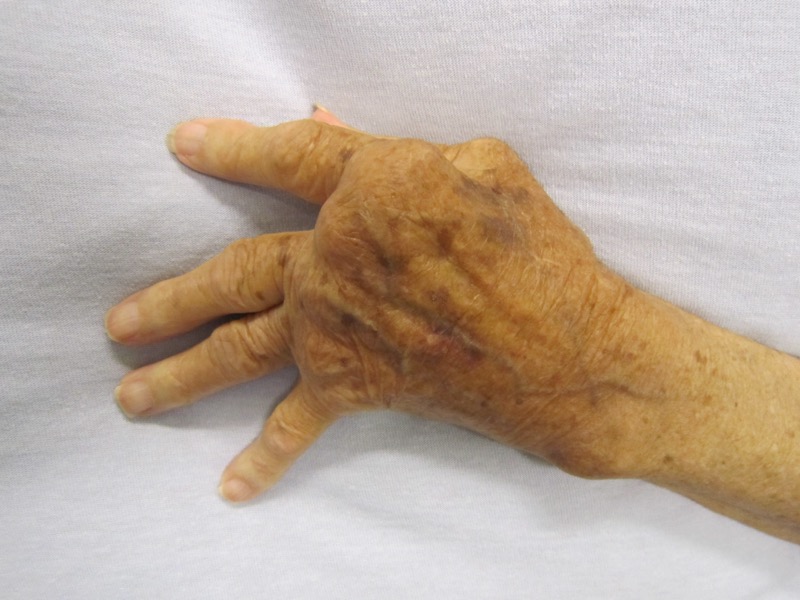
Women 30-50 (3:1 F:M); smoking is a major risk factor. Symmetric erosive polyarthritis of MCP, PIP, and wrists with morning stiffness >1 hour; spares the DIPs. Bony erosions on X-ray are the #1 differentiator from SLE.
Antibodies: anti-CCP (~97% specific, the confirmatory test); RF is sensitive but non-specific (positive in Sjogren's, HCV, endocarditis). No complement consumption.
Extra-articular: rheumatoid nodules (elbows), interstitial lung disease, Felty syndrome (splenomegaly + neutropenia), atlanto-axial subluxation (C1-C2). Swan neck, boutonniere, and ulnar deviation are the deformities. Caplan syndrome = RA + coal worker's pneumoconiosis. First-line: methotrexate.
Rule: erosive arthritis + anti-CCP = RA; SLE is non-erosive.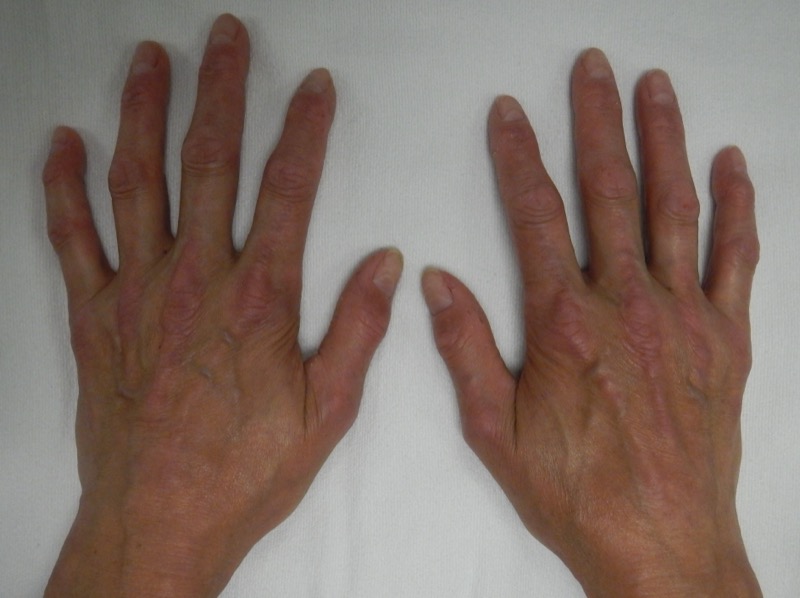
Women 30-50 (4:1 F:M). Skin tightening, sclerodactyly, and mask-like facies; Raynaud's is often the first symptom. Two subtypes matter: limited (CREST) vs diffuse.
Antibodies: anti-centromere = limited/CREST; anti-Scl-70 = diffuse. CREST = Calcinosis, Raynaud's, Esophageal dysmotility, Sclerodactyly, Telangiectasias.
Worst complications: diffuse → renal crisis (malignant hypertension, treat with ACE inhibitor, NOT steroids); limited → pulmonary arterial hypertension. Esophageal dysmotility causes severe GERD and dysphagia.
Rule: anti-centromere = contained CREST; anti-Scl-70 = diffuse; renal crisis gets an ACEi, not steroids.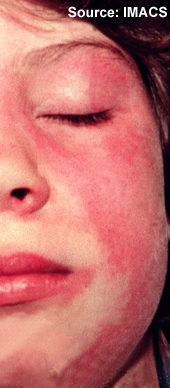
Women 40-60 (2:1 F:M). Heliotrope rash (purple eyelids) plus Gottron's papules (raised violaceous papules over the knuckles) plus proximal muscle weakness. Elevated CK is the most important lab.
Antibodies: anti-Jo-1 = antisynthetase syndrome (myositis + ILD + mechanic's hands); anti-Mi-2 = classic dermatomyositis.
#1 board association: adult dermatomyositis = screen for occult malignancy (ovarian, lung, GI). Polymyositis = same proximal weakness, no rash, no cancer link; juvenile dermatomyositis has no cancer link either.
Rule: eyelid rash + proximal weakness + high CK = dermatomyositis; in adults, hunt the tumor.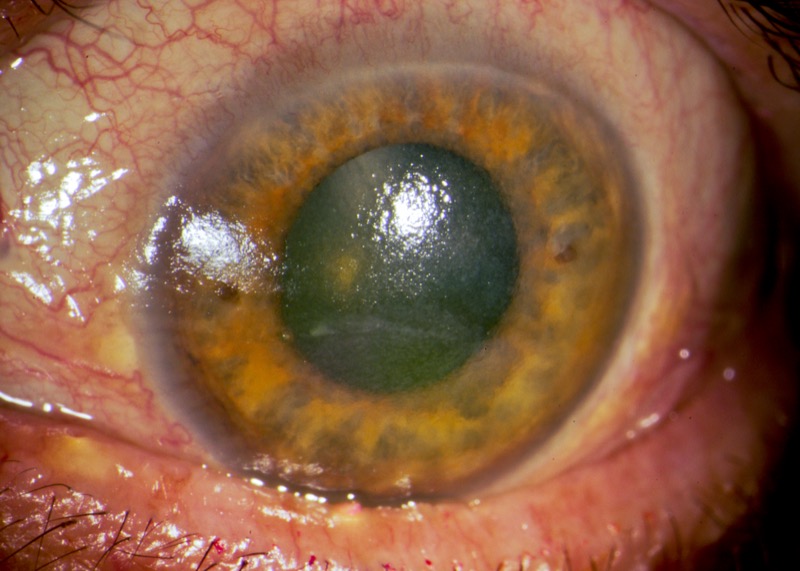
Women 40-60 (9:1 F:M); often coexists with RA or SLE (secondary Sjogren's). Sicca: dry eyes (keratoconjunctivitis sicca) plus dry mouth (xerostomia) with bilateral parotid gland enlargement.
Antibodies: anti-SSA (Ro) and anti-SSB (La); RF is also elevated. Schirmer test <5 mm wetting in 5 minutes is abnormal; lip biopsy shows lymphocytic infiltration.
Extraglandular: Type 1 renal tubular acidosis, peripheral neuropathy, interstitial nephritis. 44x increased risk of MALT lymphoma: a hard, fixed parotid is biopsy, not parotitis.
Rule: anti-SSA (Ro) crosses the placenta. Neonatal lupus and congenital heart block in pregnancy.The rashes deserve a second look, because SLE carries two different skin lesions and boards test the difference. The acute malar rash is photosensitive, spares the nasolabial folds, and heals without scarring. Discoid lesions are chronic, plugged, and scar: on the scalp they cause permanent alopecia. Both count toward classification, but only the malar rash signals acute systemic activity.
Which rash pattern belongs to which SLE lesion?
Joints finish the job. SLE arthritis is non-erosive, even after years, and any deformity (Jaccoud's) stays reducible. RA is erosive and spares the DIPs. When the radiograph shows bony erosions, the diagnosis is RA, not SLE.
ANTIBODY FINGERPRINT
The Drug-Lupus Trap
Same positive ANA, different rules: one antibody pair and one spared organ system decide the answer.
The ANA is a screening test: exquisitely sensitive for SLE, but not specific. It is positive in drug-induced lupus, in the other connective tissue diseases, and at low titer in healthy people. A positive ANA never names the disease; the specific antibody and the organ pattern do.
Drug-induced lupus follows a handful of culprits: hydralazine, procainamide, isoniazid, minocycline, and the TNF inhibitors. It brings arthralgias and serositis with an anti-histone positive, anti-dsDNA negative, complement-normal profile, and it characteristically spares the kidneys and CNS. Stop the drug and the syndrome resolves.
Which organ system is spared?
A 46-year-old woman started hydralazine for hypertension 4 months ago and now reports arthralgias, pleuritic chest pain, and low-grade fever. Exam shows a pleural friction rub and tender wrists without deformity, and no rash. ANA is 1:640 with anti-histone antibodies positive, anti-dsDNA negative, and C3/C4 normal. Which organ system is characteristically spared in this condition?
C. Kidneys and CNS. Hydralazine is a classic culprit, anti-histone positivity with negative anti-dsDNA and normal complements seals the diagnosis, and drug-induced lupus characteristically spares the kidneys and CNS. Serositis and arthralgias are common, which is why joints and lungs are tempting wrong answers. Rule: anti-histone + spared kidneys/CNS = drug-induced lupus, and it resolves when the drug stops.
ANTIBODY FINGERPRINT
The Antibody Decoder
One antibody names the disease. Learn the pair, not the list.
After the ANA, the specific antibody is the confirmatory step. Anti-dsDNA is SLE-specific and tracks disease activity; anti-Smith is SLE-specific and does not move with activity, which makes it the most specific of all. Anti-histone points to drug-induced lupus. Anti-centromere marks limited scleroderma (CREST); anti-Scl-70 (topoisomerase I) marks the diffuse subtype with its ILD risk. Anti-Ro/SSA and anti-La/SSB belong to Sjogren's, and anti-Ro drives neonatal lupus and congenital heart block. Anti-Jo-1 defines antisynthetase syndrome. RF is sensitive but promiscuous; anti-CCP is the RA confirmatory test. Anti-U1-RNP lives in mixed connective tissue disease.
Match each antibody to its disease.
Run the deck until the antibody names the disease on sight.
MEMORY HOOKS
The Sticky Set
Prompt on the left, answer on the right. Say the answer aloud before you tap to reveal.
Three hooks carry the whole page. dsDNA = double-stranded = double trouble: it rises with nephritis and falls with treatment. Smith = SLE-specific, and it never blinks with activity. Jo-1 joins the lung and the muscle in antisynthetase syndrome. And one emergency line: scleroderma renal crisis is an ACE-inhibitor emergency, even when the creatinine is climbing.
Tap each letter of the SLE criteria mnemonic.
SOAP BRAIN MD
SSerositis (pleuritis or pericarditis)
OOral ulcers (painless, palate or nasal)
AArthritis (non-erosive, two or more joints)
PPhotosensitivity (rash after sun exposure)
BBlood disorders (hemolytic anemia, leukopenia, lymphopenia, thrombocytopenia)
RRenal (proteinuria or cellular casts)
AANA (positive in nearly all)
IImmunologic (anti-dsDNA, anti-Smith, antiphospholipid)
NNeurologic (seizures or psychosis)
MMalar rash (spares the nasolabial folds)
DDiscoid rash (scarring plaques)
Four of the eleven criteria classify SLE, but boards test the fingerprint, not the count: malar rash plus low complement plus anti-dsDNA is the disease regardless of tally.
Name the disease from three clues, one at a time.
THE DIAGNOSTIC ALGORITHM
Skin First, Then Serology
Start with the pattern, then let titer, complement, and antibodies finish the diagnosis.
Step one is pattern recognition: malar rash, erosive small joints, tight skin, heliotrope, or sicca. Step two is the ANA titer and its immunofluorescence pattern, which points to the next antibody: homogeneous suggests dsDNA or histones, speckled suggests Smith or RNP, nucleolar suggests Scl-70, and centromere names limited scleroderma. Step three is the confirmatory specific antibody. Step four is the organ workup: complement (low C3/C4 in active SLE, especially with nephritis), urine (proteinuria or casts demand attention), and biopsy when the organ matters: renal, skin, or muscle. ESR and CRP support inflammation but never diagnose a connective tissue disease.
ANA positive. Which antibody comes next?
A 30-year-old has fatigue, arthralgias, and a positive ANA. Which presentation fits each antibody next step?
Put the workup in order.
ORGAN TRACK
Lupus Nephritis: The Nephritis You Cannot Miss
Up to half of SLE patients get it, and it is silent until the urine is checked.
Lupus nephritis presents with hematuria, proteinuria, hypertension, and edema, classically with nephrotic-range proteinuria and an active sediment of dysmorphic red cells and casts. The ISN/RPS classes matter in one sentence each: I is minimal, II is mesangial, III is focal proliferative, IV is diffuse proliferative (the most common and most severe), V is membranous (nephrotic), and VI is sclerotic. Class III and IV get induction with corticosteroids plus cyclophosphamide or mycophenolate mofetil; class V gets steroids plus mycophenolate or a calcineurin inhibitor.
The laboratory tells you when to look: rising anti-dsDNA with falling C3/C4 is the classic activity signal, and a urine dipstick at every visit is the surveillance. Proteinuria of more than 500 mg per day with an active sediment moves straight to biopsy, because the class, not the antibody titer, chooses the induction regimen.
Lupus nephritis risk screen: tick every finding present.
Checked 0
Which induction regimen fits diffuse proliferative disease?
A renal biopsy in a patient with active lupus nephritis shows diffuse proliferative glomerulonephritis (class IV). Which induction regimen is most appropriate?
A. Mycophenolate or cyclophosphamide plus corticosteroids. Class III and IV lupus nephritis are induced with either mycophenolate mofetil or cyclophosphamide combined with corticosteroids. Hydroxychloroquine is for every SLE patient but does not treat proliferative nephritis. NSAIDs are contraindicated when renal function is at risk, and azathioprine is a maintenance option, not induction monotherapy. Rule: proliferative nephritis = induction with MMF or cyclophosphamide plus steroids, after biopsy.
ORGAN TRACK
The Systemic Track: Lungs, Heart, Blood
Each disease has a signature organ. Match the organ to the disease and the stem writes itself.
Lungs. RA brings interstitial lung disease, pleural effusions, and rheumatoid nodules, plus Caplan syndrome when pneumoconiosis is present. SLE brings pleuritis and effusions, and shrinking lung syndrome when diaphragmatic weakness dominates. Scleroderma brings ILD (often NSIP) and pulmonary arterial hypertension, so screening starts with PFTs and an echocardiogram. Myositis adds ILD through the antisynthetase pathway, and Sjogren's can bring ILD or lymphocytic interstitial pneumonitis.
Heart. SLE's most common cardiac lesion is pericarditis, and Libman-Sacks endocarditis is its sterile verrucous signature on the mitral valve. RA adds pericarditis and premature coronary disease. Scleroderma adds PAH, myocardial fibrosis, and the hypertension of renal crisis.
Blood. SLE produces Coombs-positive autoimmune hemolytic anemia, immune thrombocytopenia, leukopenia, and the antiphospholipid syndrome: thrombosis, recurrent pregnancy loss, livedo reticularis, and anticardiolipin or lupus anticoagulant antibodies. RA brings anemia of chronic disease and, with Felty syndrome, splenomegaly with neutropenia.
Match the organ manifestation to its disease.
Which disease owns this cardiac finding?
A 28-year-old woman with fatigue, arthralgias, and a malar rash has a new systolic murmur. Echocardiography shows a sterile verrucous vegetation on the mitral valve with negative blood cultures. Which disease best explains the finding?
A. Systemic lupus erythematosus. Sterile verrucous vegetations with negative cultures are Libman-Sacks endocarditis, the classic SLE cardiac lesion, usually on the mitral valve. RA gives pericarditis and accelerated atherosclerosis rather than sterile vegetations; scleroderma gives PAH and myocardial fibrosis; rheumatic fever vegetations follow streptococcal infection and are culture-negative but valvular and rheumatic, not immune-complex. Rule: sterile verrucous mitral vegetations = Libman-Sacks = SLE.
MANAGEMENT
Treatment by System
Know the first drug for each disease, and the one drug that is an emergency.
SLE. Hydroxychloroquine for every patient: it cuts flares and improves survival. Steroids handle flares, and nephritis graduates to mycophenolate or cyclophosphamide. Belimumab is the refractory non-renal option, and sun avoidance is a prescription, not advice.
RA. Methotrexate is first-line, started early with a short course of steroids for bridge therapy. TNF inhibitors and other biologics or JAK inhibitors follow for inadequate response; NSAIDs are symptomatic only.
Scleroderma. Raynaud's responds to calcium channel blockers and warming. ILD is treated with mycophenolate or nintedanib; PAH with endothelin receptor antagonists or PDE5 inhibitors. Renal crisis is the emergency: an ACE inhibitor now, even when the creatinine is rising, and never stop it for the creatinine.
Sjogren's. Care is symptomatic: artificial tears, saliva substitutes, sialogogues, with hydroxychloroquine for arthralgia and fatigue. Unexplained parotid swelling demands lymphoma surveillance.
Myositis. Corticosteroids with a steroid-sparing agent (methotrexate, azathioprine, or mycophenolate), IVIG for refractory disease, and mandatory malignancy screening in adult dermatomyositis.
Which treatment fits which patient?
Match each clinical situation to its first-line treatment.
Prove it
Walkthrough: name the mechanism
Original practice scenarios, one at a time. Choose an answer, then open any option to work its reasoning.
Clinical walkthrough
