Trace portal blood through systemic escape routes, distinguish rectal varices from hemorrhoids, and explain the benefits and tradeoffs of TIPS.
Follow the blood, not just the vein name: a route that lowers portal pressure can expose a fragile surface vein or let blood bypass hepatic processing.
Why can a useful alternate route become dangerous?
A patient has a scarred liver, an enlarged spleen, and dilated lower esophageal veins. Before naming the vessels, ask what these findings share: blood arriving from abdominal organs encounters resistance before it can leave through the usual hepatic outlet.
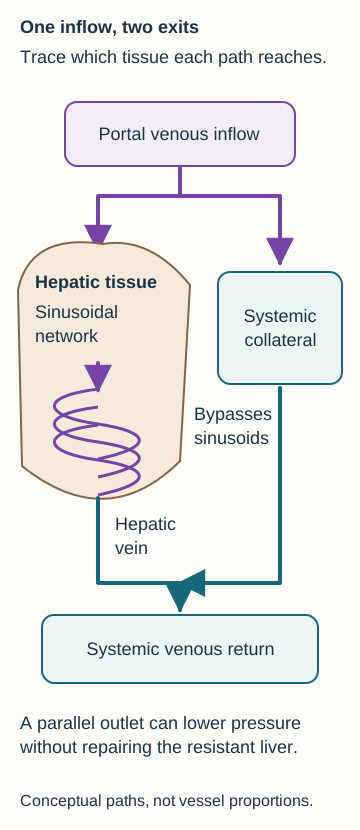
Normally, much of the venous blood from the gut and spleen reaches the portal vein, crosses hepatic sinusoids, and leaves through hepatic veins into the inferior vena cava (IVC). The sinusoids provide contact with liver cells for metabolic processing. The portal vein is an inlet to that tissue; a hepatic vein is an outlet from it. These are not interchangeable names for one vessel. [1][3]
In cirrhosis, structural distortion and increased intrahepatic vascular resistance make that route harder to traverse. Higher portal pressure favors flow through alternate portal-to-systemic venous connections. Existing small vessels can enlarge, and vascular remodeling contributes. Do not picture every collateral as a previously closed fetal tube that suddenly reopens. [1][3]
A portosystemic anastomosis joins a portal tributary to a systemic vein. It provides a route around the sinusoidal circulation, not a second passage through it.
Try tracing the two paths: use the normal-versus-bypass diagram to follow a parcel of gut venous blood to the IVC. Point to the tissue the alternate path avoids. Then predict whether a larger alternate pathway must mean the liver's resistance has disappeared.
Trace the branch that encounters hepatic tissue and the branch that avoids it. The liver outline marks the processing compartment; vessel widths are not measured flows. [1][3]Compare your prediction about the alternate pathway
The systemic outlet can carry more blood while the resistant liver remains unchanged. The parallel pathway reduces the resistance of the overall network, but does not repair the diseased sinusoidal pathway. [1][3]
The visible consequence is partial decompression: some blood has another exit, yet portal hypertension can persist. In a thin-walled submucosal vessel, increased pressure and dilation can create a varix vulnerable to rupture. In an abdominal wall vein, the same redistribution may become visible through the skin. A collateral is therefore evidence of altered circulation, not proof that the underlying disease is cured. [1][2]
Apply it elsewhere: a mesenteric vein connecting to a retroperitoneal systemic vein follows the same principle. The three classic surface sites below are useful landmarks, not an exhaustive inventory of collateral anatomy. [1]
Trace each surface finding to a portal inlet and systemic outlet
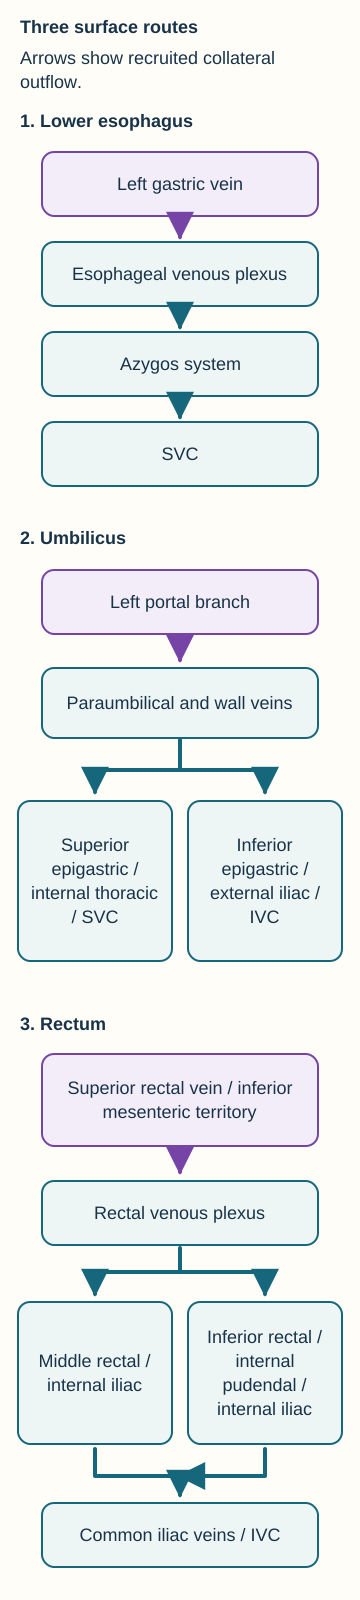
Why do hematemesis, radiating abdominal veins, and rectal varices point to different vessels? Start at the affected surface, identify its portal connection, then trace the systemic return. The route diagrams show venous connections rather than exact vessel size or position.
Lower esophagus: a route toward the superior vena cava
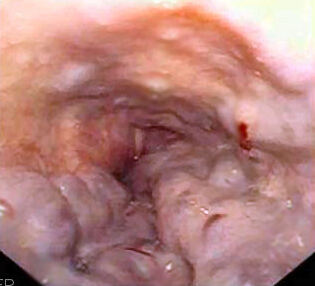
The classic path is left gastric vein → lower esophageal venous plexus → azygos and hemiazygos system → superior vena cava (SVC). The hemiazygos system reaches the azygos before the SVC. Portal hypertension can distend submucosal veins at the gastroesophageal junction. Rupture can cause life-threatening hematemesis. Paraesophageal vessels outside the wall are anatomically related but are not themselves the intraluminal columns seen at endoscopy. [1][2]
Observe the clinical image: look for raised venous columns and red surface markings. The supplied endoscopic photograph illustrates varices with red wale markings; it does not measure portal pressure or establish the cause of portal hypertension. Its full available image is preserved, without new labels or diagnostic overlays. [8]
Look for raised esophageal venous columns and red wale markings. Assess portal hypertension and bleeding risk with clinical findings rather than measuring pressure from the endoscopic image. Image: Samir; source; public domain (author dedication).
Umbilicus: one portal connection, more than one systemic destination
Paraumbilical veins communicate with the left portal venous system and travel with the falciform and round-ligament region toward the umbilicus. Connections to superficial abdominal wall veins produce the radiating pattern called caput medusae. Superior epigastric and internal thoracic pathways reach the SVC; inferior epigastric pathways reach external iliac veins and then the IVC. Superficial epigastric and thoracoepigastric connections can also carry flow toward femoral or axillary drainage. Do not assign every abdominal wall collateral to only one vena cava. [1]
Rectum: separate the two systemic exits
The superior rectal vein belongs to the portal side through the inferior mesenteric vein, which commonly joins the splenic vein. The rectal plexus connects to middle rectal veins → internal iliac veins and to inferior rectal veins → internal pudendal veins → internal iliac veins. Internal iliac blood then passes through common iliac veins into the IVC. The inferior mesenteric vein and internal iliac vein are in different venous systems despite their similar initials. [1]
Trace, cover, reconstruct: cover the systemic labels on the route diagrams. Starting at a bleeding lower esophageal varix, an umbilical collateral, and a rectal collateral, name the first systemic pathway and its eventual cava. The full text above remains available for comparison.
Cover the systemic labels and reconstruct each route. Both rectal branches eventually reach the IVC; the abdominal wall network has superior and inferior exits. The hemiazygos joins azygos return. This is a connection map, not an exhaustive venogram. [1]Check the three reconstructed routes
Lower esophageal return uses the azygos system toward the SVC. Umbilical connections may drain toward either cava. Rectal systemic return reaches the IVC through iliac veins, with an internal pudendal segment specifically on the inferior rectal route. [1]
Apply it to a different scan: a direct splenic-to-left-renal venous connection also bypasses the liver. It is a splenorenal shunt, not the classic left gastric-to-azygos route of lower esophageal varices. Identify both ends before assigning a name. [1]
Separate pressure, flow direction, and liver function
Can portal blood still travel toward the liver when a collateral carries blood away from it? Yes. Hepatopetal means toward the liver; hepatofugal means away from it. These words describe flow in the specific vessel being examined, not an obligatory direction for the entire portal network. [1]
Consider a Doppler report: the main portal vein carries blood toward the liver while a paraumbilical collateral carries blood toward the abdominal wall. Trace both arrows. The streams can coexist because the network has parallel outlets. Neither the visible collateral nor its direction proves that all main portal flow has reversed. Velocity alone is also not a direct portal pressure measurement. [1]
Predict the result: a patient still has ascites and splenomegaly after a large spontaneous collateral develops. Does that observation contradict its pressure-relieving role? Compare the portal inflow, resistant liver, and alternate outlet rather than treating any one finding as a complete pressure test.
Explain persistent ascites despite a collateral
No contradiction is required. Decompression can be incomplete, and the liver disease remains. Increased portal hydrostatic pressure, circulatory dysfunction, and renal sodium and water retention contribute to ascites. Collateral enlargement is not itself the cause of ascites or splenic congestion. [2][3]
Cirrhosis is an important cause, not the definition, of portal hypertension. Obstruction can be before the liver, within it, or at its outflow. Imaging helps localize the affected vascular segment. Small veins around an obstructed portal vein can reconnect portal blood to intrahepatic portal branches: such portoportal channels differ from a connection to a renal vein that bypasses the hepatic sinusoids. [1][2]
Apply the distinction: improving bleeding or fluid accumulation after decompression does not establish normal synthetic function or reversal of cirrhosis. Assess the symptom, hemodynamic change, and underlying liver function as separate outcomes. [2][3]
Rectal varices are not simply another name for hemorrhoids
A patient with cirrhosis reports bright red rectal bleeding. Is the bleeding automatically from a portosystemic collateral? No. Cirrhosis changes the possibilities, but examination must identify the lesion and actual bleeding source. Hemorrhoids, varices, fissures, inflammation, and tumors can occur in the same clinical setting. [4][5]
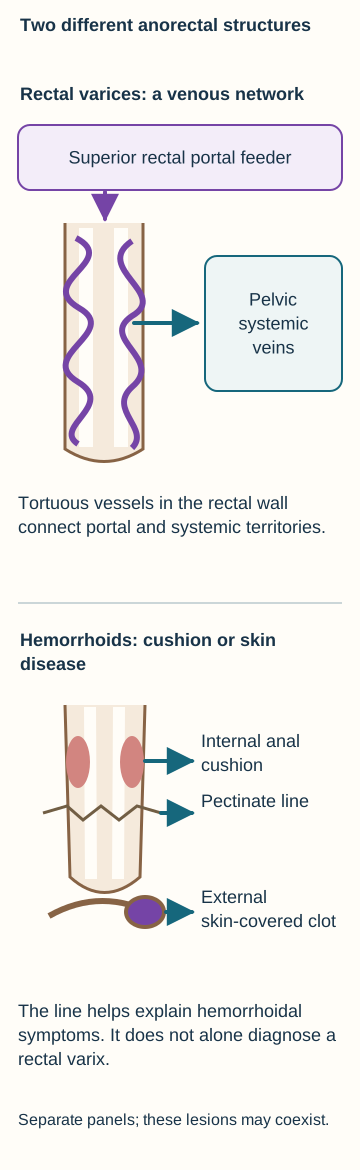
The rectal comparison diagram separates submucosal collateral veins from anal vascular cushions. Rectal varices are enlarged venous routes joining the superior rectal portal territory to systemic drainage. Hemorrhoidal tissue normally contains vessels, connective tissue, and smooth muscle. Symptomatic hemorrhoids involve enlargement, displacement, prolapse, or thrombosis of that tissue. Straining, constipation, pregnancy, and altered support may contribute without any portal hypertension. [1][4][5]
Compare the structures rather than using the pectinate line as a varix test. The upper panel isolates a rectal collateral network; the lower panel distinguishes anal cushion tissue from a painful external skin-covered clot. [1][4][5]
Compare two examinations: one shows tortuous rectal submucosal channels continuing into perirectal veins on Doppler. The other shows prolapsing anal cushions that return after defecation. Assign a vascular explanation to each before reading the comparison.
Compare the two anatomical explanations
A demonstrated portal-to-systemic rectal network supports rectal varices. Prolapsing anal cushions support hemorrhoidal disease. They are distinct structures and may coexist; finding one does not exclude the other. [1][4][5]
The pectinate line helps explain internal versus external hemorrhoidal symptoms; it does not, by itself, classify every enlarged vessel as a hemorrhoid or varix. Internal hemorrhoids are above the line and often cause painless bleeding or prolapse. A thrombosed external hemorrhoid under sensitive perianal skin can be acutely painful because the lower anal region has somatic sensation. Strangulated internal hemorrhoids can also hurt, so pain is not an absolute classifier. [5]
Rectal varices usually appear as longitudinal submucosal venous elevations in the rectum, separate from typical anal cushions. Avoid the old shortcut that their identity is determined by whether they cross the pectinate line. The decisive issue is the demonstrated collateral anatomy, interpreted with examination and appropriate imaging. A fissure is a tear, not a venous bypass. [1][4][5]
Apply it safely: both hemorrhoids and varices may bleed. Persistent bleeding, iron deficiency, or an unexplained change in bowel habits warrants evaluation for other causes even when hemorrhoids are visible. Suspected bleeding rectal varices require specialist assessment; routine hemorrhoid treatment should not be applied merely because a patient reports an anal lump. [2][4][5]
How can a shunt inside the liver bypass the liver?
A stent sits within the liver on CT. Does that guarantee blood passing through it is processed by hepatic tissue? The answer depends on the channel's endpoints, not its physical address.
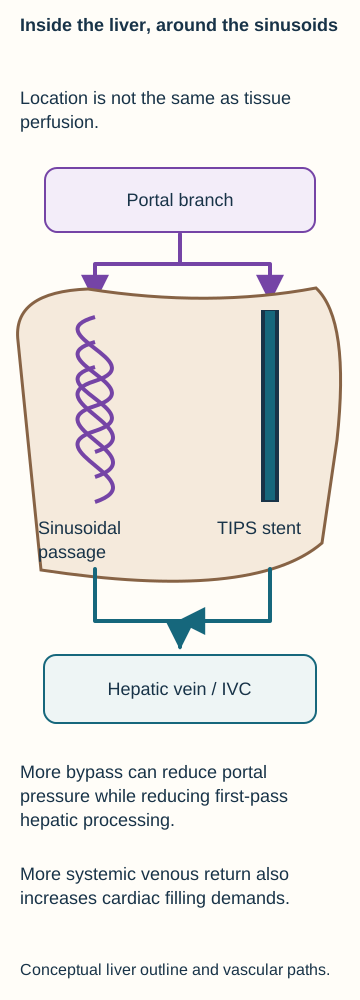
A transjugular intrahepatic portosystemic shunt (TIPS) creates a supported channel between a portal venous branch and a hepatic vein. Blood entering that channel reaches the systemic venous outlet without first traversing the intervening hepatic sinusoids. The TIPS diagram therefore distinguishes location within the liver from perfusion of its processing tissue. Native sinusoidal flow can persist alongside shunt flow. [3]
Trace the straight stent path and compare it with the branching sinusoidal path. A TIPS is physically intrahepatic but provides a portal-to-systemic bypass. The same connection can relieve pressure while increasing bypass exposure and cardiac filling demands. [3]
Try the pressure comparison: with paired pressure measurements, portal pressure is 24 mmHg and systemic outflow pressure is 6 mmHg before TIPS. Afterward they are 15 and 7 mmHg. Subtract the paired pressures, then predict the tendency for blood to enter a competing collateral. These are hypothetical measurements, not universal treatment targets.
Compare the pressure differences
The measured differences are 18 mmHg before and 8 mmHg after. A lower portal-to-systemic difference reduces the pressure driving flow through other collateral routes. It does not directly establish restored hepatocyte function. Actual procedural measurements, targets, and candidacy require specialist interpretation. [3]
By providing a lower-resistance outlet, TIPS can reduce recurrent variceal bleeding and help selected patients with recurrent or refractory ascites. Improvement in ascites involves portal decompression and circulatory and renal responses, including less sodium retention; it is not evidence that albumin synthesis instantly normalized. Benefits must be balanced against hepatic, cardiac, and neurologic risks. [2][3]
Apply it to a natural route: a splenorenal shunt has different endpoints from TIPS, but both permit portal blood to reach a systemic vein without traversing the usual sinusoidal route. Closing one collateral and creating a new low-resistance outlet are different interventions and can have opposite effects on portal pressure. [1][3]
Predict the tradeoff rather than memorizing a complication list
Why might bleeding improve while cognition worsens after a technically functioning TIPS? The same extra bypass that lowers portal pressure reduces hepatic exposure to some gut-derived substances. Ammonia handling is part of this physiology, but hepatic encephalopathy is a clinical syndrome rather than the result of one laboratory number. [3][6]
Consider new disorientation, sleep-wake reversal, and asterixis after shunting. First recognize a compatible syndrome; then assess triggers and alternatives, including infection, bleeding, medication effects, electrolyte disorders, and neurologic disease. A high ammonia result alone neither establishes encephalopathy nor grades its severity. A normal result should prompt reconsideration of the diagnosis. A patent shunt does not exclude shunt-associated encephalopathy. [3][6]
Predict two different consequences: in the TIPS diagram, follow more blood to the hepatic venous outlet. What changes for hepatic processing? What changes for the heart receiving that venous return? State one potential harm in each organ system.
Compare the neurologic and circulatory predictions
Greater sinusoidal bypass can contribute to encephalopathy. Increased venous return can raise cardiac filling demands and precipitate decompensation in a susceptible heart. These are different consequences of the same new vascular connection. [3]
New dyspnea with jugular venous distension and pulmonary congestion after TIPS should therefore raise concern for cardiac decompensation, not simply be labeled worsening liver fluid retention. Elective candidate assessment includes cardiac evaluation as well as liver function, prior encephalopathy, and procedural anatomy. Severe heart failure, important pulmonary hypertension, and other major contraindications require specialist assessment; a desirable pressure reduction does not make every patient a suitable candidate. [3]
Suspected variceal hemorrhage is an emergency. Resuscitation, appropriate vasoactive therapy and antibiotic prophylaxis, and urgent endoscopic assessment are coordinated in hospital. TIPS is used for selected high-risk patients, uncontrolled bleeding, or appropriate recurrence, not as a replacement for initial stabilization. Anatomy helps identify the source; it must not delay emergency care. [2]
Final transfer: if a shunt later narrows and variceal bleeding returns, predict increased resistance through that outlet and renewed pressure toward collateral pathways. Do not infer that new fibrosis necessarily appeared at the same moment. Connect the intervention, the altered pathway, and the clinical consequence. [3]
Apply the anatomy to new patients
For each case, identify the observation that localizes the pathway, then predict what that anatomy changes. The explanations remain available after every question.
Case 1
Show answer and explanations for case 1
A. Increased caval resistance with reversal through hepatic venous channels (Why this does not fit)
Systemic venous congestion can redirect venous return. Patent outflow veins and nodular fibrosis localize the demonstrated lesion within the liver. Trace portal inflow against intrahepatic resistance before invoking a separate caval lesion.
Reasoning steps for option A
What can caval obstruction produce?
Systemic venous congestion can redirect venous return.
Where is the supplied structural abnormality?
Patent outflow veins and nodular fibrosis localize the demonstrated lesion within the liver.
Which pressure should be traced first?
Trace portal inflow against intrahepatic resistance before invoking a separate caval lesion.
B. Reduced hepatic venous resistance with dilation of portal inflow channels (Why this does not fit)
An easier hepatic outlet would favor forward flow through the liver. It does not account for the resistant fibrotic tissue and associated splenic congestion. Inflow, tissue resistance, and outflow are separate parts of the circuit.
Reasoning steps for option B
What would lower outflow resistance favor?
An easier hepatic outlet would favor forward flow through the liver.
Does that explain the observed upstream congestion?
It does not account for the resistant fibrotic tissue and associated splenic congestion.
What distinction matters?
Inflow, tissue resistance, and outflow are separate parts of the circuit.
C. Increased hepatic sinusoidal resistance with recruitment of alternate systemic venous channels (Best answer)
Fibrosis and nodular distortion increase intrahepatic vascular resistance. Higher portal pressure favors alternate venous outflow through the lower esophageal plexus. Dilation of submucosal collateral veins produces esophageal varices.
Reasoning steps for option C
What does the biopsy imply about flow?
Fibrosis and nodular distortion increase intrahepatic vascular resistance.
What is the upstream consequence?
Higher portal pressure favors alternate venous outflow through the lower esophageal plexus.
How does that produce the observed lesion?
Dilation of submucosal collateral veins produces esophageal varices.
D. Reduced portal inflow with recruitment of hepatic arterial channels (Why this does not fit)
Less portal inflow tends to reduce, rather than generate, portal pressure. Fibrous distortion supplies a resistant intrahepatic pathway, not evidence of reduced inflow. The relevant collateral connection is venous on both sides.
Reasoning steps for option D
What can reduced inflow do to pressure?
Less portal inflow tends to reduce, rather than generate, portal pressure.
Which lesion is demonstrated?
Fibrous distortion supplies a resistant intrahepatic pathway, not evidence of reduced inflow.
Are these esophageal channels arterial?
The relevant collateral connection is venous on both sides.
Takeaway: Localize the resistance before tracing the collateral it recruits.
A. A still supplies hepatic sinusoids; B reaches systemic veins first (Best answer)
It reconnects to portal branches inside the liver, upstream of hepatic sinusoids. The left renal vein drains to the systemic IVC rather than to hepatic sinusoids. A is a portoportal bypass of an obstruction; B is a portosystemic bypass of the usual hepatic tissue route.
Reasoning steps for option A
Where does network A reconnect?
It reconnects to portal branches inside the liver, upstream of hepatic sinusoids.
Where does network B end?
The left renal vein drains to the systemic IVC rather than to hepatic sinusoids.
What does this comparison distinguish?
A is a portoportal bypass of an obstruction; B is a portosystemic bypass of the usual hepatic tissue route.
B. Both reach systemic veins before perfusing hepatic sinusoids (Why this does not fit)
A portal tributary must connect to systemic venous return. A reconnects to intrahepatic portal branches rather than to a systemic vein. Portal blood can still enter hepatic sinusoids despite extrahepatic portal obstruction.
Reasoning steps for option B
What makes a channel portosystemic?
A portal tributary must connect to systemic venous return.
Which network lacks that destination?
A reconnects to intrahepatic portal branches rather than to a systemic vein.
What remains possible in A?
Portal blood can still enter hepatic sinusoids despite extrahepatic portal obstruction.
C. Both supply hepatic sinusoids before reaching systemic veins (Why this does not fit)
Portal blood ordinarily perfuses sinusoids before leaving through hepatic veins. B carries splenic venous blood into the left renal vein. A systemic endpoint can bypass hepatic processing even when liver tissue remains viable.
Reasoning steps for option C
What is the usual portal sequence?
Portal blood ordinarily perfuses sinusoids before leaving through hepatic veins.
Which observed connection bypasses that sequence?
B carries splenic venous blood into the left renal vein.
What is the functional distinction?
A systemic endpoint can bypass hepatic processing even when liver tissue remains viable.
D. A reaches systemic veins first; B still supplies hepatic sinusoids (Why this does not fit)
Both provide alternate venous channels around the usual route. A ends in portal branches while B ends in a renal systemic vein. Use its destination, not simply the presence of tortuous vessels.
Reasoning steps for option D
Why consider a bypass in either network?
Both provide alternate venous channels around the usual route.
Which endpoints contradict this assignment?
A ends in portal branches while B ends in a renal systemic vein.
How should a bypass be classified?
Use its destination, not simply the presence of tortuous vessels.
Takeaway: Not every collateral is portosystemic: identify where the alternate channel rejoins circulation.
A. The shunt has failed because ascites remains despite its enlargement (Why this does not fit)
It can provide partial decompression without eliminating all pressure-related disease. The measured pressure difference falls by 5 mmHg while remaining abnormal. Persistent symptoms require assessment of residual disease, not an automatic claim of zero shunt function.
Reasoning steps for option A
What benefit can a collateral provide?
It can provide partial decompression without eliminating all pressure-related disease.
What evidence shows some decompression here?
The measured pressure difference falls by 5 mmHg while remaining abnormal.
What should persistent ascites imply?
Persistent symptoms require assessment of residual disease, not an automatic claim of zero shunt function.
B. The liver has recovered because the portal pressure difference has fallen (Why this does not fit)
It can document a hemodynamic improvement. Synthetic function is unchanged and a larger alternate outlet explains the lower gradient. Pressure relief does not establish restored hepatocyte function.
Reasoning steps for option B
What can a falling gradient document?
It can document a hemodynamic improvement.
What contradicts an inference of liver recovery?
Synthetic function is unchanged and a larger alternate outlet explains the lower gradient.
What must be assessed separately?
Pressure relief does not establish restored hepatocyte function.
C. The shunt causes ascites by increasing the liver sinusoidal resistance (Why this does not fit)
Fibrotic distortion and intrahepatic vascular dysfunction increase that resistance. The portal-to-systemic pressure difference falls rather than rises. An enlarged collateral responds to portal hypertension and need not cause the underlying resistance.
Reasoning steps for option C
What process produces sinusoidal resistance in cirrhosis?
Fibrotic distortion and intrahepatic vascular dysfunction increase that resistance.
What effect is actually measured after shunt enlargement?
The portal-to-systemic pressure difference falls rather than rises.
What avoids reversing cause and effect?
An enlarged collateral responds to portal hypertension and need not cause the underlying resistance.
D. The shunt partly decompresses a hypertensive portal system with persistent liver disease (Best answer)
The alternate outlet accompanies lower but still abnormal portal-to-systemic pressure. Residual portal hypertension and circulatory and renal abnormalities can remain. Yes. A functioning alternate pathway does not itself repair the diseased liver.
Reasoning steps for option D
What does the pressure comparison demonstrate?
The alternate outlet accompanies lower but still abnormal portal-to-systemic pressure.
Why can ascites persist?
Residual portal hypertension and circulatory and renal abnormalities can remain.
Does unchanged synthetic function fit?
Yes. A functioning alternate pathway does not itself repair the diseased liver.
Takeaway: A collateral may function while pressure-related symptoms and liver dysfunction persist.
A. Right-sided cardiac congestion with transmission of pressure through hepatic veins (Why this does not fit)
Right-sided congestion can raise hepatic venous pressure and contribute to ascites. Echocardiography shows no evidence of right-sided congestion, while cirrhosis supplies an intrahepatic source of resistance. Integrate the venous territory and demonstrated organ disease rather than assigning all ascites to cardiac congestion.
Reasoning steps for option A
Why is this a plausible general alternative?
Right-sided congestion can raise hepatic venous pressure and contribute to ascites.
Which patient-specific finding weakens it?
Echocardiography shows no evidence of right-sided congestion, while cirrhosis supplies an intrahepatic source of resistance.
How should the cause be localized?
Integrate the venous territory and demonstrated organ disease rather than assigning all ascites to cardiac congestion.
B. Portal venous congestion with secondary renal sodium and water retention (Best answer)
Splenic venous blood drains into the portal system, so increased resistance can produce upstream splenic congestion. It supports renal sodium retention despite the excess total body fluid, contributing to ascites. Collateral enlargement is a response to the portal pressure disorder rather than a prerequisite for its other manifestations.
Reasoning steps for option B
What links the spleen to the scarred liver?
Splenic venous blood drains into the portal system, so increased resistance can produce upstream splenic congestion.
What does low urinary sodium add?
It supports renal sodium retention despite the excess total body fluid, contributing to ascites.
Why can the wall veins appear later?
Collateral enlargement is a response to the portal pressure disorder rather than a prerequisite for its other manifestations.
C. Reduced plasma oncotic pressure with redistribution of extracellular fluid (Why this does not fit)
Reduced albumin can contribute to fluid distribution and edema. Reduced oncotic pressure alone does not explain splenic venous congestion and subsequent portal collateral development. The portal circulation supplies the shared pressure abnormality, while renal retention contributes to ascites.
Reasoning steps for option C
Why is this explanation initially plausible?
Reduced albumin can contribute to fluid distribution and edema.
Which finding does it not adequately explain?
Reduced oncotic pressure alone does not explain splenic venous congestion and subsequent portal collateral development.
What additional process must be considered?
The portal circulation supplies the shared pressure abnormality, while renal retention contributes to ascites.
D. Primary renal sodium retention with expansion of the systemic venous volume (Why this does not fit)
The low urinary sodium indicates retention, which can expand total body fluid. It does not account for the portal distribution of splenic congestion and collaterals as directly as the demonstrated cirrhotic liver. Renal retention can be secondary to the circulatory disorder rather than a separate primary cause.
Reasoning steps for option D
Why consider a renal contribution?
The low urinary sodium indicates retention, which can expand total body fluid.
Why is it insufficient as the primary unifying explanation?
It does not account for the portal distribution of splenic congestion and collaterals as directly as the demonstrated cirrhotic liver.
How do the mechanisms fit together?
Renal retention can be secondary to the circulatory disorder rather than a separate primary cause.
Takeaway: Portal congestion explains the splenic findings; renal sodium retention contributes to the ascites.
A. Superior rectal vein to internal iliac vein (Why this does not fit)
The superior rectal and internal iliac territories communicate through rectal venous pathways. The observed bleeding source is in the distal esophagus rather than the rectum. Trace the endoscopically demonstrated upper gastrointestinal source.
Reasoning steps for option A
Where is this portal-to-systemic connection relevant?
The superior rectal and internal iliac territories communicate through rectal venous pathways.
Why does it not localize this hemorrhage?
The observed bleeding source is in the distal esophagus rather than the rectum.
What does hematemesis require here?
Trace the endoscopically demonstrated upper gastrointestinal source.
B. Left gastric vein to azygos venous system (Best answer)
A distal esophageal venous column identifies the classic gastroesophageal collateral bed. The left gastric vein is the principal classic portal connection. Esophageal venous connections drain through the azygos system toward the SVC.
Reasoning steps for option B
What does the endoscopic location identify?
A distal esophageal venous column identifies the classic gastroesophageal collateral bed.
What supplies its portal side?
The left gastric vein is the principal classic portal connection.
How does it reach systemic circulation?
Esophageal venous connections drain through the azygos system toward the SVC.
C. Paraumbilical vein to inferior epigastric vein (Why this does not fit)
It connects portal blood to abdominal wall venous drainage and may contribute to caput medusae. The lesion is within the distal esophageal wall, not the periumbilical abdominal wall. Match the portal and systemic pair to the documented surface lesion.
Reasoning steps for option C
What surface finding fits this connection?
It connects portal blood to abdominal wall venous drainage and may contribute to caput medusae.
Why is it not the demonstrated bleeding route?
The lesion is within the distal esophageal wall, not the periumbilical abdominal wall.
What prevents the localization error?
Match the portal and systemic pair to the documented surface lesion.
D. Splenic vein to left renal vein (Why this does not fit)
They can form a direct splenorenal shunt. The bleeding is localized to a distal esophageal submucosal column, not a direct splenorenal connection. Identify the vascular bed at the bleeding surface rather than naming any shunt found in cirrhosis.
Reasoning steps for option D
What route can these vessels form?
They can form a direct splenorenal shunt.
Which finding favors another route?
The bleeding is localized to a distal esophageal submucosal column, not a direct splenorenal connection.
How should the collateral be named?
Identify the vascular bed at the bleeding surface rather than naming any shunt found in cirrhosis.
Takeaway: Distal esophageal varices connect the left gastric portal territory with azygos systemic return.
A. Left renal vein, then inferior vena cava (Why this does not fit)
Splenorenal and many gastrorenal pathways can reach the IVC through the left renal vein. Contrast is in the hemiazygos, which ordinarily joins the azygos system. Use the observed channel, not a different possible portosystemic connection.
Reasoning steps for option A
Which portosystemic routes use a left renal outlet?
Splenorenal and many gastrorenal pathways can reach the IVC through the left renal vein.
What has already been observed here?
Contrast is in the hemiazygos, which ordinarily joins the azygos system.
How should competing real routes be handled?
Use the observed channel, not a different possible portosystemic connection.
B. Internal iliac vein, then common iliac vein (Why this does not fit)
Pelvic systemic return reaches a common iliac vein through an internal iliac vein. Hemiazygos return is thoracic and ordinarily joins the azygos system. The systemic destination depends on the selected collateral bed.
Reasoning steps for option B
What region commonly uses this sequence?
Pelvic systemic return reaches a common iliac vein through an internal iliac vein.
Why does that not follow the demonstrated channel?
Hemiazygos return is thoracic and ordinarily joins the azygos system.
Which anatomical distinction matters?
The systemic destination depends on the selected collateral bed.
C. Internal thoracic vein, then brachiocephalic vein (Why this does not fit)
Superior epigastric abdominal wall return can reach an internal thoracic vein. The visible systemic channel is hemiazygos rather than internal thoracic. Different venous channels can eventually reach the SVC without being the same route.
Reasoning steps for option C
What abdominal route can use this outlet?
Superior epigastric abdominal wall return can reach an internal thoracic vein.
What excludes that route in this venogram?
The visible systemic channel is hemiazygos rather than internal thoracic.
What common endpoint should not obscure the difference?
Different venous channels can eventually reach the SVC without being the same route.
D. Azygos vein, then superior vena cava (Best answer)
The hemiazygos system communicates with the azygos vein. It reaches the superior vena cava. The collateral reaches the right-sided systemic circulation without requiring a new passage through hepatic sinusoids.
Reasoning steps for option D
What receives the usual hemiazygos return?
The hemiazygos system communicates with the azygos vein.
Where does the azygos then empty?
It reaches the superior vena cava.
What was bypassed on this venous route?
The collateral reaches the right-sided systemic circulation without requiring a new passage through hepatic sinusoids.
Takeaway: The hemiazygos ordinarily joins the azygos before reaching the SVC.
A. A paraumbilical collateral draining a portal venous branch (Best answer)
It identifies a paraumbilical venous pathway from the portal system. Dilated superficial connections produce radiating periumbilical veins. The imaged pathway is a portal-to-systemic collateral and both cavae are patent.
Reasoning steps for option A
What does the falciform course identify?
It identifies a paraumbilical venous pathway from the portal system.
What does its abdominal wall connection explain?
Dilated superficial connections produce radiating periumbilical veins.
Why is caval obstruction not required?
The imaged pathway is a portal-to-systemic collateral and both cavae are patent.
B. A thoracic collateral draining the left gastric portal territory (Why this does not fit)
It commonly supplies the gastroesophageal collateral bed. A falciform channel to periumbilical veins identifies the paraumbilical pathway. Radiating periumbilical veins localize the visible consequence to the abdominal wall.
Reasoning steps for option B
What would a left gastric route usually suggest?
It commonly supplies the gastroesophageal collateral bed.
Which findings identify a different route?
A falciform channel to periumbilical veins identifies the paraumbilical pathway.
What does the skin pattern add?
Radiating periumbilical veins localize the visible consequence to the abdominal wall.
C. A pelvic collateral draining the superior rectal portal territory (Why this does not fit)
A connection through the rectal plexus to pelvic systemic veins would support that source. The described feeder arises from the left portal branch in the falciform region. Follow the imaged origin rather than treating all surface veins as pelvic return.
Reasoning steps for option C
What would support a rectal source?
A connection through the rectal plexus to pelvic systemic veins would support that source.
Which observed anatomy argues against it?
The described feeder arises from the left portal branch in the falciform region.
What should guide localization?
Follow the imaged origin rather than treating all surface veins as pelvic return.
D. A systemic bypass carrying blood around an obstructed vena cava (Why this does not fit)
Caval obstruction can create systemic-to-systemic abdominal wall collaterals. Both cavae are patent and the imaged feeder connects to a portal branch. A portal endpoint makes this a portal-to-systemic connection rather than a caval bypass.
Reasoning steps for option D
What else can enlarge abdominal wall veins?
Caval obstruction can create systemic-to-systemic abdominal wall collaterals.
What distinguishes this patient?
Both cavae are patent and the imaged feeder connects to a portal branch.
What defines the route here?
A portal endpoint makes this a portal-to-systemic connection rather than a caval bypass.
Takeaway: Caput medusae is localized by the paraumbilical portal connection, not by superficial veins alone.
A. Upper through hepatic veins to IVC; lower through left renal vein to IVC (Why this does not fit)
Hepatic and renal veins both drain into the IVC. It shows superior and inferior epigastric exits from the abdominal wall collateral. A shared final cava does not justify inserting an unrelated organ vein into a traced pathway.
Reasoning steps for option A
What do these pathways have in common?
Hepatic and renal veins both drain into the IVC.
What does the actual scan document instead?
It shows superior and inferior epigastric exits from the abdominal wall collateral.
What endpoint should not be substituted?
A shared final cava does not justify inserting an unrelated organ vein into a traced pathway.
B. Upper through internal thoracic to IVC; lower through external iliac to SVC (Why this does not fit)
Internal thoracic and external iliac are appropriate regional pathways. Internal thoracic return reaches the SVC, while external iliac return reaches the IVC. Trace each path all the way to the cava rather than stopping at the first systemic vein.
Reasoning steps for option B
Which intermediate veins are correctly named?
Internal thoracic and external iliac are appropriate regional pathways.
Which part of the proposal is reversed?
Internal thoracic return reaches the SVC, while external iliac return reaches the IVC.
How can the error be avoided?
Trace each path all the way to the cava rather than stopping at the first systemic vein.
C. Upper through internal thoracic to SVC; lower through external iliac to IVC (Best answer)
It continues through the internal thoracic and brachiocephalic pathways toward the SVC. It reaches the external iliac and common iliac pathways toward the IVC. A paraumbilical connection can have both superior and inferior systemic exits.
Reasoning steps for option C
Where does superior epigastric return continue?
It continues through the internal thoracic and brachiocephalic pathways toward the SVC.
Where does inferior epigastric return continue?
It reaches the external iliac and common iliac pathways toward the IVC.
What does this show about the collateral?
A paraumbilical connection can have both superior and inferior systemic exits.
D. Upper through azygos to SVC; lower through internal iliac to IVC (Why this does not fit)
Azygos and internal iliac pathways are familiar systemic outlets of esophageal and rectal collaterals. The named vessels are epigastric abdominal wall veins, not esophageal or rectal veins. Superior epigastric return reaches internal thoracic veins; inferior epigastric return reaches external iliac veins.
Reasoning steps for option D
Why are these destinations tempting?
Azygos and internal iliac pathways are familiar systemic outlets of esophageal and rectal collaterals.
What is different in this scan?
The named vessels are epigastric abdominal wall veins, not esophageal or rectal veins.
The inferior rectal vein reaches the internal pudendal venous system. It is not the portal tributary descending from that territory. Inferior mesenteric and inferior rectal veins belong to different parts of the drainage map.
Reasoning steps for option A
What is its usual systemic route?
The inferior rectal vein reaches the internal pudendal venous system.
Does it arise from the inferior mesenteric territory?
It is not the portal tributary descending from that territory.
What similar names should not obscure?
Inferior mesenteric and inferior rectal veins belong to different parts of the drainage map.
B. Internal pudendal vein (Why this does not fit)
It receives inferior rectal systemic venous drainage. The feeder is continuous with the inferior mesenteric portal territory. It must match the demonstrated upstream venous system.
Reasoning steps for option B
Where does this vessel participate?
It receives inferior rectal systemic venous drainage.
What contradicts it as the described feeder?
The feeder is continuous with the inferior mesenteric portal territory.
What must a feeder label preserve?
It must match the demonstrated upstream venous system.
C. Middle rectal vein (Why this does not fit)
It is a systemic tributary draining toward an internal iliac vein. The study follows the inferior mesenteric portal territory into the plexus. Separate the superior rectal portal limb from middle rectal systemic drainage.
Reasoning steps for option C
Which side commonly includes the middle rectal vein?
It is a systemic tributary draining toward an internal iliac vein.
Which side is being traced in this case?
The study follows the inferior mesenteric portal territory into the plexus.
Which distinction resolves the choice?
Separate the superior rectal portal limb from middle rectal systemic drainage.
D. Superior rectal vein (Best answer)
The superior rectal vein joins the inferior mesenteric venous system. It connects the portal side to the rectal venous plexus. Middle and inferior rectal pathways communicate with iliac systemic return.
Reasoning steps for option D
What normally drains the upper rectal portal territory?
The superior rectal vein joins the inferior mesenteric venous system.
How is it used in the documented collateral?
It connects the portal side to the rectal venous plexus.
Where can blood leave the plexus systemically?
Middle and inferior rectal pathways communicate with iliac systemic return.
Takeaway: Superior rectal drainage belongs to the portal system through the inferior mesenteric vein.
The inferior epigastric vein reaches the external iliac system. The observed branch leaves the middle rectum rather than the anterior abdominal wall. Middle rectal drainage belongs to the internal iliac territory in this route.
Reasoning steps for option A
What related abdominal wall vessel drains there?
The inferior epigastric vein reaches the external iliac system.
What region is actually being traced?
The observed branch leaves the middle rectum rather than the anterior abdominal wall.
Which iliac subdivision matters?
Middle rectal drainage belongs to the internal iliac territory in this route.
B. Internal pudendal vein (Why this does not fit)
Inferior rectal venous return usually includes an internal pudendal segment. The imaged branch joins a pelvic vein directly without passing through the internal pudendal vein. Use the observed continuity rather than forcing every rectal outflow into one template.
Reasoning steps for option B
Which route usually includes this vessel?
Inferior rectal venous return usually includes an internal pudendal segment.
Which supplied observation excludes that segment here?
The imaged branch joins a pelvic vein directly without passing through the internal pudendal vein.
How should anatomy variants be handled?
Use the observed continuity rather than forcing every rectal outflow into one template.
C. Internal iliac vein (Best answer)
A middle rectal systemic branch can drain directly to an internal iliac vein. It separates this described route from the usual inferior rectal-to-internal-pudendal pathway. The internal iliac reaches the common iliac vein and then the IVC.
Reasoning steps for option C
Which rectal outflow is described?
A middle rectal systemic branch can drain directly to an internal iliac vein.
What does the absent pudendal segment distinguish?
It separates this described route from the usual inferior rectal-to-internal-pudendal pathway.
Where does the recipient ultimately drain?
The internal iliac reaches the common iliac vein and then the IVC.
D. Inferior mesenteric vein (Why this does not fit)
The superior rectal vein belongs to the inferior mesenteric territory. The case explicitly traces a lateral systemic branch from the middle rectum. A portal feeder and a pelvic systemic recipient are not interchangeable.
Reasoning steps for option D
What rectal vein communicates with this portal vessel?
The superior rectal vein belongs to the inferior mesenteric territory.
Why is it not the described recipient?
The case explicitly traces a lateral systemic branch from the middle rectum.
What separates the competing paths?
A portal feeder and a pelvic systemic recipient are not interchangeable.
Takeaway: The middle rectal systemic route can reach the internal iliac vein without a pudendal intermediate.
A. Superior rectal to inferior mesenteric vein (Why this does not fit)
It describes the rectal portal territory. The mapped branch is in the lower anal systemic territory and reaches an internal iliac vein. It must explain both the local course and the documented systemic endpoint.
Reasoning steps for option A
What would this sequence describe?
It describes the rectal portal territory.
Which findings argue against that sequence?
The mapped branch is in the lower anal systemic territory and reaches an internal iliac vein.
What must the proposed route explain?
It must explain both the local course and the documented systemic endpoint.
B. Inferior rectal to internal pudendal vein (Best answer)
Its lower anal origin and ischioanal course fit the inferior rectal venous route. The inferior rectal vein reaches the internal pudendal vein. Internal pudendal return reaches the internal iliac vein and then systemic caval circulation.
Reasoning steps for option B
What identifies the lower anal branch?
Its lower anal origin and ischioanal course fit the inferior rectal venous route.
What is the usual next named recipient?
The inferior rectal vein reaches the internal pudendal vein.
How does that connect to the supplied endpoint?
Internal pudendal return reaches the internal iliac vein and then systemic caval circulation.
C. Inferior epigastric to external iliac vein (Why this does not fit)
It is an anterior abdominal wall route toward the IVC. A lower anal branch crossing the ischioanal fossa is not an inferior epigastric vessel. The intervening anatomy must also match the imaged branch.
Reasoning steps for option C
Where is this a valid venous route?
It is an anterior abdominal wall route toward the IVC.
Which local course does it fail to explain?
A lower anal branch crossing the ischioanal fossa is not an inferior epigastric vessel.
How is a shared eventual IVC endpoint insufficient?
The intervening anatomy must also match the imaged branch.
D. Middle rectal to external iliac vein (Why this does not fit)
The middle rectal vein is a pelvic systemic route. Middle rectal return reaches internal rather than external iliac venous drainage. Inferior rectal return passes through an internal pudendal vein.
Reasoning steps for option D
Which regional vessel makes this tempting?
The middle rectal vein is a pelvic systemic route.
Which recipient is incorrect for the classic middle rectal route?
Middle rectal return reaches internal rather than external iliac venous drainage.
What route fits the lower anal branch?
Inferior rectal return passes through an internal pudendal vein.
Takeaway: Inferior rectal venous return includes the internal pudendal segment.
A. A diverts portal blood; B redistributes blood already in systemic veins (Best answer)
A directs portal blood into systemic wall veins before the usual hepatic sinusoidal passage. B redirects systemic venous return around caval obstruction without demonstrating a portal connection. Visible wall veins alone do not determine the source of pressure or prove portal hypertension.
Reasoning steps for option A
What does the left portal feeder establish in A?
A directs portal blood into systemic wall veins before the usual hepatic sinusoidal passage.
What does the leg-vein origin establish in B?
B redirects systemic venous return around caval obstruction without demonstrating a portal connection.
What finding should be interpreted cautiously?
Visible wall veins alone do not determine the source of pressure or prove portal hypertension.
B. Neither pathway is a bypass because both eventually reach a vena cava (Why this does not fit)
They return toward the heart through systemic venous pathways. No. A bypass is defined by the intervening route it avoids. A avoids the usual hepatic tissue route and B avoids the obstructed caval segment.
Reasoning steps for option B
What do systemic venous routes ultimately do?
They return toward the heart through systemic venous pathways.
Does a shared eventual endpoint exclude a bypass?
No. A bypass is defined by the intervening route it avoids.
Which two routes are avoided here?
A avoids the usual hepatic tissue route and B avoids the obstructed caval segment.
C. Both pathways bypass hepatic sinusoids because both involve wall veins (Why this does not fit)
Yes. They can participate in portal-to-systemic or systemic-to-systemic pathways. A has a demonstrated portal feeder, while B redirects blood already in systemic veins. A portal origin, not the visible wall location alone, establishes the relevant bypass.
Reasoning steps for option C
Can wall veins carry either type of alternate flow?
Yes. They can participate in portal-to-systemic or systemic-to-systemic pathways.
What differs between the patients?
A has a demonstrated portal feeder, while B redirects blood already in systemic veins.
What identifies sinusoidal bypass?
A portal origin, not the visible wall location alone, establishes the relevant bypass.
D. A redistributes systemic blood; B diverts blood from portal branches (Why this does not fit)
Similar wall veins can arise from different upstream circuits. A begins in the left portal branch, whereas B begins in leg systemic veins. Follow contrast from its origin to the alternate outlet.
Reasoning steps for option D
Why could the same skin finding be misleading?
Similar wall veins can arise from different upstream circuits.
How do the documented origins contradict this assignment?
A begins in the left portal branch, whereas B begins in leg systemic veins.
What corrects the reversed interpretation?
Follow contrast from its origin to the alternate outlet.
Takeaway: An abdominal wall collateral must be classified by its origin and destination.
A. Downward displacement of normal anal vascular cushions (Why this does not fit)
It suggests prolapsing internal hemorrhoidal tissue. The documented rectal channels connect an inferior mesenteric tributary to pelvic systemic veins. A demonstrated portosystemic network is not simply displaced anal cushion tissue.
Reasoning steps for option A
What lesion does cushion displacement suggest?
It suggests prolapsing internal hemorrhoidal tissue.
Which observation requires a different explanation?
The documented rectal channels connect an inferior mesenteric tributary to pelvic systemic veins.
What separates the lesions?
A demonstrated portosystemic network is not simply displaced anal cushion tissue.
B. A mucosal tear caused by passage of hard stool (Why this does not fit)
An anal fissure can cause defecation-associated pain and bleeding. Tortuous submucosal venous channels with portal and systemic continuity are shown, not a tear. Use the lesion anatomy rather than bleeding alone.
Reasoning steps for option B
What could a mucosal tear explain?
An anal fissure can cause defecation-associated pain and bleeding.
What morphology is actually demonstrated?
Tortuous submucosal venous channels with portal and systemic continuity are shown, not a tear.
What should determine the classification?
Use the lesion anatomy rather than bleeding alone.
C. Dilation of a superior rectal portosystemic network (Best answer)
An inferior mesenteric tributary identifies the superior rectal portal side. It establishes a portosystemic rectal collateral pathway. The resulting submucosal venous elevations are rectal varices.
Reasoning steps for option C
Which upstream vessel identifies the portal territory?
An inferior mesenteric tributary identifies the superior rectal portal side.
What does pelvic systemic continuity establish?
It establishes a portosystemic rectal collateral pathway.
What lesion results when these channels dilate?
The resulting submucosal venous elevations are rectal varices.
D. Thrombosis within superficial external anal tissue (Why this does not fit)
A localized tender bluish perianal nodule fits a thrombosed external hemorrhoid. The described channels are proximal rectal submucosal veins with demonstrated venous continuity. The broad label of an anal lump cannot replace the documented vascular network.
Reasoning steps for option D
What finding commonly fits external thrombosis?
A localized tender bluish perianal nodule fits a thrombosed external hemorrhoid.
Why does that not explain this examination?
The described channels are proximal rectal submucosal veins with demonstrated venous continuity.
What should not substitute for imaging?
The broad label of an anal lump cannot replace the documented vascular network.
Takeaway: A portal feeder plus systemic rectal drainage establishes a variceal network, not ordinary hemorrhoidal prolapse.
A. Enlargement of the spleen on abdominal imaging (Why this does not fit)
It supports the broader possibility of portal congestion. No. A patient with portal hypertension may also have ordinary hemorrhoids. Demonstrated continuity of the rectal portal and systemic venous territories is more specific.
Reasoning steps for option A
What does splenomegaly support in this context?
It supports the broader possibility of portal congestion.
Does it identify which anal lesion is variceal?
No. A patient with portal hypertension may also have ordinary hemorrhoids.
What local evidence is stronger?
Demonstrated continuity of the rectal portal and systemic venous territories is more specific.
B. Bleeding that appears bright red rather than dark or tarry (Why this does not fit)
It can arise from several lower gastrointestinal lesions, including hemorrhoids and rectal varices. No. Color does not demonstrate a superior rectal-to-systemic channel. The source must be established from lesion anatomy and appropriate assessment.
Reasoning steps for option B
What can bright red bleeding indicate?
It can arise from several lower gastrointestinal lesions, including hemorrhoids and rectal varices.
Does its color identify the venous connection?
No. Color does not demonstrate a superior rectal-to-systemic channel.
What information is still needed?
The source must be established from lesion anatomy and appropriate assessment.
C. Absence of pain when the mucosal elevation is examined (Why this does not fit)
Internal hemorrhoidal tissue often bleeds or prolapses without somatic-type pain. It does not identify a specific portosystemic connection. It helps characterize symptoms but cannot replace vascular mapping.
Reasoning steps for option C
Why may an internal anal lesion be painless?
Internal hemorrhoidal tissue often bleeds or prolapses without somatic-type pain.
Does painless examination distinguish the two lesions?
It does not identify a specific portosystemic connection.
What role does sensation play?
It helps characterize symptoms but cannot replace vascular mapping.
D. Continuity between the superior rectal portal territory and pelvic systemic veins (Best answer)
Both internal hemorrhoidal tissue and rectal venous lesions can lie above the pectinate line. It connects the superior rectal portal territory to pelvic systemic return. It demonstrates the defining vascular pathway of a rectal collateral.
Reasoning steps for option D
Why does location above the line not settle the diagnosis?
Both internal hemorrhoidal tissue and rectal venous lesions can lie above the pectinate line.
What does this continuity establish?
It connects the superior rectal portal territory to pelvic systemic return.
Why is that more specific than appearance?
It demonstrates the defining vascular pathway of a rectal collateral.
Takeaway: The pectinate line is not a stand-alone test for rectal varices.
A. External hemorrhoidal thrombosis with somatic perianal sensation (Best answer)
It suggests thrombosis in external hemorrhoidal tissue. The distended perianal tissues are supplied by somatic sensory nerves. An isolated external thrombosis does not establish portal hypertension or rectal varices.
Reasoning steps for option A
What does a tense blue skin-covered nodule suggest?
It suggests thrombosis in external hemorrhoidal tissue.
Why can it be acutely painful?
The distended perianal tissues are supplied by somatic sensory nerves.
What does this not establish?
An isolated external thrombosis does not establish portal hypertension or rectal varices.
B. Anal fissure with somatic sensation from the lower canal (Why this does not fit)
A tear in the sensitive lower anal region can be very painful. No tear is present; the lesion is a tense bluish nodule. Thrombosis in external hemorrhoidal tissue can produce marked pain.
Reasoning steps for option B
Why is fissure a plausible pain diagnosis?
A tear in the sensitive lower anal region can be very painful.
Which physical finding discriminates here?
No tear is present; the lesion is a tense bluish nodule.
What else can distend this sensitive tissue?
Thrombosis in external hemorrhoidal tissue can produce marked pain.
C. Internal hemorrhoidal prolapse with visceral mucosal sensation (Why this does not fit)
They can cause prolapse and bleeding, and severe strangulation can be painful. This acute tense nodule is skin-covered outside the anal opening, not prolapsing mucosal tissue. The perianal skin has somatic sensation.
Reasoning steps for option C
What can internal hemorrhoids cause?
They can cause prolapse and bleeding, and severe strangulation can be painful.
What localization favors another lesion?
This acute tense nodule is skin-covered outside the anal opening, not prolapsing mucosal tissue.
What sensory distinction matters?
The perianal skin has somatic sensation.
D. Rectal collateral dilation with portal venous pressure sensation (Why this does not fit)
It can dilate a rectal portosystemic network. The examination instead shows an isolated skin-covered acute nodule without proximal venous channels. Somatic innervation of the external anal region, not a special portal pressure sensory pathway, explains it.
Reasoning steps for option D
What can portal hypertension dilate?
It can dilate a rectal portosystemic network.
What evidence for that network is absent?
The examination instead shows an isolated skin-covered acute nodule without proximal venous channels.
What actually accounts for the severe local pain?
Somatic innervation of the external anal region, not a special portal pressure sensory pathway, explains it.
Takeaway: External hemorrhoidal thrombosis combines a localized clot with somatically sensitive tissue.
A. Reassess bleeding after a trial directed at hemorrhoidal symptoms (Why this does not fit)
Conservative treatment is reasonable for uncomplicated symptomatic hemorrhoids. Anemia, weight loss, and a bowel habit change suggest disease beyond the incidental nonbleeding cushions. Assessment for another gastrointestinal bleeding source is needed.
Reasoning steps for option A
Why might a hemorrhoid-directed trial be considered?
Conservative treatment is reasonable for uncomplicated symptomatic hemorrhoids.
What makes it an insufficient diagnostic priority here?
Anemia, weight loss, and a bowel habit change suggest disease beyond the incidental nonbleeding cushions.
What should not be postponed by the incidental finding?
Assessment for another gastrointestinal bleeding source is needed.
B. Evaluate for a colonic source beyond the observed anal cushions (Best answer)
It establishes the presence of hemorrhoids without proving the reported bleeding comes from them. Iron deficiency, weight loss, and altered bowel habits warrant investigation for other gastrointestinal disease, including a colonic lesion. They may coexist and need symptom care, but cannot account for the whole presentation without further assessment.
Reasoning steps for option B
What does the anoscopy establish?
It establishes the presence of hemorrhoids without proving the reported bleeding comes from them.
Which observations change the priority?
Iron deficiency, weight loss, and altered bowel habits warrant investigation for other gastrointestinal disease, including a colonic lesion.
What role do the hemorrhoids retain?
They may coexist and need symptom care, but cannot account for the whole presentation without further assessment.
C. Prioritize portal venous mapping to attribute bleeding to rectal varices (Why this does not fit)
Portal hypertension can produce rectal varices that bleed. No bleeding varix or rectal collateral has been demonstrated, and the additional symptoms require broader evaluation. Cirrhosis increases the possibilities but does not establish the local bleeding source.
Reasoning steps for option C
Why consider a rectal collateral?
Portal hypertension can produce rectal varices that bleed.
Why is attribution to varices premature?
No bleeding varix or rectal collateral has been demonstrated, and the additional symptoms require broader evaluation.
What separates risk from diagnosis?
Cirrhosis increases the possibilities but does not establish the local bleeding source.
D. Repeat the blood count before investigating the bowel habit change (Why this does not fit)
It can document the trend and help monitor blood loss. It does not identify the cause of current iron deficiency, weight loss, and changed bowel habits. Laboratory follow-up can accompany, rather than replace, assessment of the concerning gastrointestinal presentation.
Reasoning steps for option D
What useful information can a repeat count provide?
It can document the trend and help monitor blood loss.
What problem does monitoring alone leave unresolved?
It does not identify the cause of current iron deficiency, weight loss, and changed bowel habits.
How should monitoring relate to investigation?
Laboratory follow-up can accompany, rather than replace, assessment of the concerning gastrointestinal presentation.
Takeaway: Concerning bowel symptoms and iron deficiency need investigation even when hemorrhoids are present.
A. Two rectal varices differing only in whether they prolapse (Why this does not fit)
Portal hypertension and the mapped rectal venous network support their presence. It does not convert prolapsing anal cushion tissue into another rectal varix. Classify each structure from its own anatomy rather than from the patient risk factor alone.
Reasoning steps for option A
Why are rectal varices plausible here?
Portal hypertension and the mapped rectal venous network support their presence.
What does that not prove about the other lesion?
It does not convert prolapsing anal cushion tissue into another rectal varix.
What does coexistence require?
Classify each structure from its own anatomy rather than from the patient risk factor alone.
B. Two forms of hemorrhoids caused by the same portal collateral (Why this does not fit)
Both can be described imprecisely as enlarged anorectal vessels. The separate rectal network has demonstrated portal-to-systemic continuity. Distinguish anal cushion disease from a rectal variceal network.
Reasoning steps for option B
Why might both lesions be called hemorrhoids?
Both can be described imprecisely as enlarged anorectal vessels.
Which finding makes one a distinct lesion?
The separate rectal network has demonstrated portal-to-systemic continuity.
What classification should replace the shared label?
Distinguish anal cushion disease from a rectal variceal network.
C. A rectal varix that has transformed into an external hemorrhoid (Why this does not fit)
Both lesions can produce bleeding and be near the anal outlet. Two separate structures are present, with different anatomical relationships. Rectal varices and hemorrhoidal tissue are not sequential stages of one lesion.
Reasoning steps for option C
What makes the transformation idea tempting?
Both lesions can produce bleeding and be near the anal outlet.
What has actually been demonstrated?
Two separate structures are present, with different anatomical relationships.
What is the useful distinction?
Rectal varices and hemorrhoidal tissue are not sequential stages of one lesion.
D. Prolapsing hemorrhoidal cushion tissue coexisting with a separate rectal variceal network (Best answer)
It identifies hemorrhoidal tissue with prolapse. Superior rectal-to-pelvic systemic continuity identifies rectal varices. Yes. They are distinct entities and one does not exclude the other; the bleeding source still requires localization.
Reasoning steps for option D
What does the prolapsing cushion identify?
It identifies hemorrhoidal tissue with prolapse.
What does the separate mapped network identify?
Superior rectal-to-pelvic systemic continuity identifies rectal varices.
Can both be present in the same patient?
Yes. They are distinct entities and one does not exclude the other; the bleeding source still requires localization.
Takeaway: Cirrhosis does not prevent ordinary hemorrhoids from coexisting with rectal varices.
A. More blood crosses hepatic sinusoids before reaching a renal vein (Why this does not fit)
The liver ordinarily processes portal blood while it traverses sinusoids. They connect a portal branch directly to a hepatic vein, not to a renal vein. A lower-resistance bypass of intervening sinusoids creates the intended alternate outlet.
The liver ordinarily processes portal blood while it traverses sinusoids.
What do the actual stent endpoints show?
They connect a portal branch directly to a hepatic vein, not to a renal vein.
What creates decompression?
A lower-resistance bypass of intervening sinusoids creates the intended alternate outlet.
B. More blood reaches hepatic venous outflow without traversing sinusoids (Best answer)
It provides access to portal venous inflow upstream of the sinusoids. It provides a systemic outflow route downstream of that tissue bed. The low-resistance channel connects the two without requiring passage through the resistant intervening sinusoids.
Reasoning steps for option B
What does the portal endpoint provide?
It provides access to portal venous inflow upstream of the sinusoids.
What does the hepatic venous endpoint provide?
It provides a systemic outflow route downstream of that tissue bed.
Why can pressure fall?
The low-resistance channel connects the two without requiring passage through the resistant intervening sinusoids.
C. More blood enters the hepatic artery before reaching hepatic sinusoids (Why this does not fit)
The hepatic artery supplies oxygenated arterial blood to hepatic tissue. No. Both stent endpoints are in venous structures. Location inside the liver does not turn a venous shunt into an arterial supply route.
Reasoning steps for option C
Which normal vessel also supplies the liver?
The hepatic artery supplies oxygenated arterial blood to hepatic tissue.
Is it connected by the documented stent?
No. Both stent endpoints are in venous structures.
What should not be inferred from an intrahepatic location?
Location inside the liver does not turn a venous shunt into an arterial supply route.
D. More blood returns through the splenic vein before crossing sinusoids (Why this does not fit)
Portal tributaries such as the splenic vein can participate in alternate pathways. The stent directly connects a portal branch to hepatic venous outflow. Use the endpoints of the constructed channel rather than substituting a different portal tributary.
Reasoning steps for option D
What can collateral redistribution include?
Portal tributaries such as the splenic vein can participate in alternate pathways.
What pathway is documented here?
The stent directly connects a portal branch to hepatic venous outflow.
What determines its function?
Use the endpoints of the constructed channel rather than substituting a different portal tributary.
Takeaway: An intrahepatic channel can bypass hepatic tissue when it links portal inflow directly to hepatic venous outflow.
A. Increased portal bypass has reduced hepatic exposure to gut-derived substances (Best answer)
Disorientation, sleep-wake change, and asterixis after TIPS are compatible with hepatic encephalopathy. Increased portosystemic bypass reduces hepatic processing of some gut-derived substances. Other precipitants and alternative causes still require evaluation; the mechanism is not established by an ammonia value alone.
Reasoning steps for option A
What syndrome fits the new findings?
Disorientation, sleep-wake change, and asterixis after TIPS are compatible with hepatic encephalopathy.
How does the procedure contribute?
Increased portosystemic bypass reduces hepatic processing of some gut-derived substances.
What assessment remains necessary?
Other precipitants and alternative causes still require evaluation; the mechanism is not established by an ammonia value alone.
B. Shunt obstruction has redirected more blood back through hepatic sinusoids (Why this does not fit)
It can impair decompression and permit recurrence of pressure-related complications. The shunt remains patent and the measured pressure difference remains reduced. Encephalopathy can develop despite successful decompression.
Reasoning steps for option B
What can shunt obstruction cause?
It can impair decompression and permit recurrence of pressure-related complications.
What observations argue against that mechanism?
The shunt remains patent and the measured pressure difference remains reduced.
What should a working shunt not exclude?
Encephalopathy can develop despite successful decompression.
C. Reduced venous return has caused isolated cerebral hypoperfusion (Why this does not fit)
It can cause altered mental status in an appropriate hemodynamic setting. TIPS increases rather than reduces venous return, and no hypotensive state is supplied. Portosystemic bypass is the relevant link while alternative causes are assessed.
Reasoning steps for option C
What can cerebral hypoperfusion produce?
It can cause altered mental status in an appropriate hemodynamic setting.
What is the usual immediate circulatory direction after TIPS?
TIPS increases rather than reduces venous return, and no hypotensive state is supplied.
Which procedure-related mechanism better matches this syndrome?
Portosystemic bypass is the relevant link while alternative causes are assessed.
D. Increased sinusoidal perfusion has accelerated removal of gut-derived substances (Why this does not fit)
Greater effective hepatic processing would reduce exposure to some potentially harmful substances. The shunt increases a route around, rather than through, the sinusoidal bed. The proposed increase in processing has the opposite direction from the relevant bypass effect.
Reasoning steps for option D
Why might this sound like successful liver treatment?
Greater effective hepatic processing would reduce exposure to some potentially harmful substances.
Which anatomical change actually occurs with TIPS?
The shunt increases a route around, rather than through, the sinusoidal bed.
How does that affect the explanation?
The proposed increase in processing has the opposite direction from the relevant bypass effect.
Takeaway: A functioning TIPS can contribute to encephalopathy through increased hepatic bypass.
A. Restored hepatic albumin synthesis and increased plasma oncotic pressure (Why this does not fit)
Albumin and plasma oncotic pressure can influence edema formation. Serum albumin remains similar while natriuresis and ascites improve. Portal decompression and altered renal circulatory responses can reduce sodium retention.
Reasoning steps for option A
Why could this pair affect fluid distribution?
Albumin and plasma oncotic pressure can influence edema formation.
Which measured result does not support it here?
Serum albumin remains similar while natriuresis and ascites improve.
What mechanism can improve fluid status without that change?
Portal decompression and altered renal circulatory responses can reduce sodium retention.
B. Lower portal pressure and increased renal sodium retention (Why this does not fit)
A lower portal pressure difference is consistent with a new decompressive outlet. Increased sodium retention would not explain the observed increase in urinary sodium excretion. The hemodynamic improvement must be combined with less, not more, maladaptive retention.
Reasoning steps for option B
Which vascular change matches a functioning TIPS?
A lower portal pressure difference is consistent with a new decompressive outlet.
Which renal change conflicts with the response?
Increased sodium retention would not explain the observed increase in urinary sodium excretion.
What paired direction is needed?
The hemodynamic improvement must be combined with less, not more, maladaptive retention.
C. Lower portal venous pressure and secondary reduction in renal sodium retention (Best answer)
It adds a lower-resistance portal outlet and can decompress the portal system. Improved effective circulation can reduce maladaptive sodium retention and permit greater sodium excretion. No. Ascites can improve through these mechanisms without a rise in serum albumin.
Reasoning steps for option C
What direct vascular effect does TIPS provide?
It adds a lower-resistance portal outlet and can decompress the portal system.
How can the renal response contribute?
Improved effective circulation can reduce maladaptive sodium retention and permit greater sodium excretion.
Does the response require immediate synthetic recovery?
No. Ascites can improve through these mechanisms without a rise in serum albumin.
D. Higher portal outflow resistance and reduced renal sodium retention (Why this does not fit)
Reduced renal sodium retention could help reduce fluid accumulation. TIPS adds a lower-resistance outlet rather than increasing portal outflow resistance. Both its vascular and renal components must agree with the intervention.
Reasoning steps for option D
Which part could improve ascites?
Reduced renal sodium retention could help reduce fluid accumulation.
Which vascular change has the wrong direction?
TIPS adds a lower-resistance outlet rather than increasing portal outflow resistance.
What should a paired explanation accomplish?
Both its vascular and renal components must agree with the intervention.
Takeaway: Ascites can improve through decompression and natriuresis without normalization of albumin synthesis.
A. Increased preload from augmented systemic venous return (Best answer)
It increases an outflow route from the portal circulation to hepatic venous return. A less compliant ventricle may not accommodate the extra filling without a rise in pressure. Cardiac decompensation can produce jugular venous distension and pulmonary congestion.
Reasoning steps for option A
What does the new shunt deliver to systemic veins?
It increases an outflow route from the portal circulation to hepatic venous return.
How does diastolic dysfunction change tolerance?
A less compliant ventricle may not accommodate the extra filling without a rise in pressure.
What clinical consequence follows?
Cardiac decompensation can produce jugular venous distension and pulmonary congestion.
B. Decreased circulating volume from ongoing procedural hemorrhage (Why this does not fit)
It could reduce circulating volume and contribute to hypotension or anemia. Hemoglobin is unchanged, and elevated jugular venous pressure with crackles favors congestion. Increased venous return stressing preexisting cardiac dysfunction fits better than volume loss.
Reasoning steps for option B
What could procedural bleeding produce?
It could reduce circulating volume and contribute to hypotension or anemia.
Which findings favor another explanation?
Hemoglobin is unchanged, and elevated jugular venous pressure with crackles favors congestion.
C. Decreased preload from sequestration of blood in the portal bed (Why this does not fit)
It would reduce cardiac filling rather than directly explain new congestive filling signs. Jugular venous distension and crackles suggest venous and pulmonary congestion. The new outlet generally increases systemic venous return from the portal circulation.
Reasoning steps for option C
What would reduced preload tend to cause?
It would reduce cardiac filling rather than directly explain new congestive filling signs.
Which supplied signs suggest increased filling pressure?
Jugular venous distension and crackles suggest venous and pulmonary congestion.
What is the relevant TIPS effect?
The new outlet generally increases systemic venous return from the portal circulation.
D. Increased hepatic resistance from acute closure of the venous stent (Why this does not fit)
It could reverse portal decompression and cause recurrent portal pressure complications. The shunt is patent and the acute findings are congestive cardiac signs. Diastolic dysfunction reduces tolerance of increased cardiac filling.
Reasoning steps for option D
What could stent closure produce?
It could reverse portal decompression and cause recurrent portal pressure complications.
What observation contradicts that mechanism here?
The shunt is patent and the acute findings are congestive cardiac signs.
What preexisting vulnerability matters?
Diastolic dysfunction reduces tolerance of increased cardiac filling.
Takeaway: TIPS can stress a susceptible heart by increasing venous return and filling pressures.
A. 20 units instead of 20 units (Why this does not fit)
It is the no-shunt output when all 100 units encounter 80% hepatic extraction. Half the input never encounters that extraction step. Do not apply hepatic extraction to blood that bypasses the hepatic compartment.
Reasoning steps for option A
When would 20 units be the systemic output?
It is the no-shunt output when all 100 units encounter 80% hepatic extraction.
What changes with the new channel?
Half the input never encounters that extraction step.
What assumption should not be retained?
Do not apply hepatic extraction to blood that bypasses the hepatic compartment.
B. 40 units instead of 80 units (Why this does not fit)
It is the amount removed from the 50 units that enter sinusoids. It asks for units reaching systemic veins, not units removed. Subtract extraction from each relevant input, then include the bypass contribution.
Reasoning steps for option B
What does 40 units represent after shunting?
It is the amount removed from the 50 units that enter sinusoids.
What does the question ask for instead?
It asks for units reaching systemic veins, not units removed.
What avoids reversing extraction and escape?
Subtract extraction from each relevant input, then include the bypass contribution.
C. 60 units instead of 20 units (Best answer)
All 50 bypassed units reach systemic veins because the model specifies no removal on that path. Twenty percent of 50 remain, which is 10 units. The total is 50 plus 10, or 60 units; without a shunt, 20% of 100, or 20 units, would remain.
Reasoning steps for option C
How many bypassed units reach systemic veins?
All 50 bypassed units reach systemic veins because the model specifies no removal on that path.
How many of the other 50 units survive hepatic passage?
Twenty percent of 50 remain, which is 10 units.
What is the total and comparison?
The total is 50 plus 10, or 60 units; without a shunt, 20% of 100, or 20 units, would remain.
D. 50 units instead of 20 units (Why this does not fit)
It represents the portion bypassing hepatic sinusoids. Ten units also survive passage through the liver because extraction is 80%, not 100%. Add unprocessed bypass flow to the residual substance leaving the perfused liver.
Reasoning steps for option D
What does the 50-unit number correctly represent?
It represents the portion bypassing hepatic sinusoids.
Which systemic contribution is omitted?
Ten units also survive passage through the liver because extraction is 80%, not 100%.
How should parallel pathways be combined?
Add unprocessed bypass flow to the residual substance leaving the perfused liver.
Takeaway: Add the unprocessed bypass contribution to the residual substance leaving the liver; this model is not a drug-dosing rule.
A. The wall-vessel flow excludes portal origin because the main portal vein is forward-flowing (Why this does not fit)
The two vessels are connected to the same broader portal network. It demonstrates flow through a paraumbilical alternate outlet despite continued main portal inflow. A collateral need not require reversal of all main portal flow.
Reasoning steps for option A
Why might opposite directions seem contradictory?
The two vessels are connected to the same broader portal network.
What does the measured wall connection demonstrate?
It demonstrates flow through a paraumbilical alternate outlet despite continued main portal inflow.
What assumption should be discarded?
A collateral need not require reversal of all main portal flow.
B. Hepatopetal main portal venous flow coexists with hepatofugal paraumbilical collateral outflow (Best answer)
Flow toward the liver is hepatopetal. Flow away from the liver is hepatofugal. Some blood continues toward hepatic tissue while some exits through a parallel collateral route.
Reasoning steps for option B
Which term describes the main portal measurement?
Flow toward the liver is hepatopetal.
Which term describes the paraumbilical measurement?
Flow away from the liver is hepatofugal.
How can both occur?
Some blood continues toward hepatic tissue while some exits through a parallel collateral route.
C. The two channels must have been mislabeled because connected veins cannot diverge (Why this does not fit)
Its flow would be constrained by the same serial route. The portal network has parallel pathways, including a collateral outlet. Different connected vessels can carry flow toward different destinations.
Reasoning steps for option C
What would a single unbranched tube require?
Its flow would be constrained by the same serial route.
What structure is present here instead?
The portal network has parallel pathways, including a collateral outlet.
What can branching permit?
Different connected vessels can carry flow toward different destinations.
D. The two directions prove that the portal pressure has returned to normal (Why this does not fit)
It establishes the direction of blood flow in the measured vessel. No direct portal-to-systemic pressure difference is provided. The direction of flow alone does not prove normalization of portal pressure.
Reasoning steps for option D
What does Doppler direction establish?
It establishes the direction of blood flow in the measured vessel.
What measurement is not supplied?
No direct portal-to-systemic pressure difference is provided.
What inference would exceed the data?
The direction of flow alone does not prove normalization of portal pressure.
Takeaway: Flow direction belongs to the measured vessel; collateral flow and forward main portal flow can coexist.
A. The communication raises the fraction of splenic blood entering hepatic sinusoids (Why this does not fit)
It could increase hepatic exposure to portal blood for processing. It takes splenic venous blood directly into a systemic renal vein. It provides a route around rather than toward the usual hepatic tissue passage.
Reasoning steps for option A
What could increased sinusoidal passage favor?
It could increase hepatic exposure to portal blood for processing.
What path does this communication actually create?
It takes splenic venous blood directly into a systemic renal vein.
What is the directional consequence?
It provides a route around rather than toward the usual hepatic tissue passage.
B. The communication establishes renal failure despite the normal creatinine (Why this does not fit)
Severe renal dysfunction can produce metabolic complications. Neither impaired renal function nor an obstructing renal lesion is demonstrated. It establishes a natural portosystemic shunt, not a renal failure diagnosis.
Reasoning steps for option B
Why might kidney dysfunction be considered in altered mental status?
Severe renal dysfunction can produce metabolic complications.
What evidence for renal failure is supplied?
Neither impaired renal function nor an obstructing renal lesion is demonstrated.
What does the CT establish instead?
It establishes a natural portosystemic shunt, not a renal failure diagnosis.
C. Blood must cross renal filtering capillaries before entering the vena cava (Why this does not fit)
Its name identifies venous drainage associated with the kidney. No. The collateral joins venous outflow rather than renal arterial inflow. The usual hepatic sinusoidal route is bypassed.
Reasoning steps for option C
Why might the renal vein suggest kidney processing?
Its name identifies venous drainage associated with the kidney.
Does entering the renal vein require filtration through glomeruli?
No. The collateral joins venous outflow rather than renal arterial inflow.
Which tissue is bypassed before systemic return?
The usual hepatic sinusoidal route is bypassed.
D. Portal blood reaches systemic venous return before the usual passage through hepatic sinusoids (Best answer)
The splenic vein is part of the portal venous system. The left renal vein is systemic venous return toward the IVC. It permits hepatic bypass that can contribute to encephalopathy, while other causes of altered mental status still require assessment.
Reasoning steps for option D
What is the upstream venous system?
The splenic vein is part of the portal venous system.
What is the downstream endpoint?
The left renal vein is systemic venous return toward the IVC.
How can the connection contribute clinically?
It permits hepatic bypass that can contribute to encephalopathy, while other causes of altered mental status still require assessment.
Takeaway: Natural splenorenal shunts can bypass hepatic processing even without a TIPS or renal dysfunction.
A. Increased resistance in the left gastric collateral with reduced upstream portal pressure (Why this does not fit)
It would make that collateral a more resistant outlet. Venography shows narrowing of the TIPS, and the measured upstream pressure difference has increased. It must match both the stent abnormality and the loss of decompression.
Reasoning steps for option A
What would narrowing a collateral do to its own route?
It would make that collateral a more resistant outlet.
Which route is actually narrowed?
Venography shows narrowing of the TIPS, and the measured upstream pressure difference has increased.
What must the explanation match?
It must match both the stent abnormality and the loss of decompression.
B. Decreased resistance in the stent with increased clearance through hepatic sinusoids (Why this does not fit)
It favors portal decompression through the shunt. It shows focal narrowing, not reduced resistance or enhanced sinusoidal clearance. It supports impaired shunt outflow rather than improved decompression.
Reasoning steps for option B
What does a widely patent low-resistance TIPS favor?
It favors portal decompression through the shunt.
How does the later venogram differ?
It shows focal narrowing, not reduced resistance or enhanced sinusoidal clearance.
What does the pressure trend support?
It supports impaired shunt outflow rather than improved decompression.
C. Increased resistance in the stent with renewed pressure toward collateral outflow (Best answer)
It increases resistance through the constructed alternate outlet. The rise from 8 to 18 mmHg shows loss of much of the earlier decompression. Renewed pressure toward variceal pathways can contribute to rebleeding; this is an emergency requiring clinical reassessment.
Reasoning steps for option C
What does focal stent narrowing do?
It increases resistance through the constructed alternate outlet.
What does the pressure change establish?
The rise from 8 to 18 mmHg shows loss of much of the earlier decompression.
Why can bleeding recur?
Renewed pressure toward variceal pathways can contribute to rebleeding; this is an emergency requiring clinical reassessment.
D. Decreased resistance in hepatic sinusoids with diversion into systemic esophageal veins (Why this does not fit)
It would make the usual hepatic route easier to traverse. The new lesion is in the stent and the portal-to-systemic difference has risen. Do not infer that a change in liver fibrosis is required when shunt dysfunction explains the new hemodynamics.
Reasoning steps for option D
What would lower sinusoidal resistance generally favor?
It would make the usual hepatic route easier to traverse.
What findings instead identify the changed resistance?
The new lesion is in the stent and the portal-to-systemic difference has risen.
What causal shortcut should be avoided?
Do not infer that a change in liver fibrosis is required when shunt dysfunction explains the new hemodynamics.
Takeaway: Stent narrowing can reverse decompression and restore pressure toward collateral pathways.