PPI-associated hypergastrinemia: read the hormone beside the acid
Explain PPI feedback, interpret gastrin with gastric acidity, distinguish gland loss from autonomous secretion, and plan safe testing or deprescribing.
A patient taking omeprazole has high fasting gastrin. Should the drug be stopped, or is the rise a predictable response to effective acid suppression? The answer depends on the acid state and the reason treatment began, not the hormone value alone.
By the end, you should be able to explain the feedback response, separate medication effect from gland loss and autonomous secretion, and choose a safe next step when treatment or testing changes.
Interpret gastrin without creating danger
Does a high gastrin result mean too much acid? Not necessarily. Gastrin is a signal to produce acid, not a measurement of acid production. A stomach unable to respond can have a stronger signal than a stomach secreting excessive acid. Read the result beside gastric acidity, medication exposure, and the clinical history. [4]
For example, fasting gastrin of 600 pg/mL, with a laboratory upper limit of 100 pg/mL, means six times that laboratory's upper limit. It does not identify the cause. On omeprazole, a gastric pH of 6 may reflect effective treatment. In an untreated patient with recurrent distal duodenal ulcers, pH 1.4 gives the same hormone concentration a very different meaning.
Verify the measurement: confirm fasting conditions, units, reference range, and the assay if results conflict with the clinical picture.
Verify exposure: include prescribed and over-the-counter proton pump inhibitors (PPIs), H2-receptor antagonists, and when they were last taken. Review renal function and prior gastric surgery.
Establish the acid context: interpret gastric pH with the treatment state. Gastric aspirate may be measured during clinically indicated endoscopy; a pH result is not a direct measurement of acid output per hour.
Protect the patient: recurrent or unusual ulcers, severe reflux, or diarrhea that responds to acid suppression raise concern for a hypersecretory disorder. Specialist-directed evaluation preserves acid control while resolving the diagnosis. [4]
Do not stop a PPI at home to obtain a more interpretable gastrin value when gastrinoma is possible. Acid-related bleeding or other complications can develop quickly if suppression is lost. A high pH measured during treatment cannot exclude a successfully treated gastrinoma. [4]
Pause and compare: two patients have the same fasting gastrin. One has no ulcer history on once-daily therapy; the other previously had multiple postbulbar ulcers and becomes ill when doses are missed. Which history makes a medication interruption more hazardous?
Compare the histories
The second history suggests substantial underlying acid secretion. The shared laboratory value does not imply a shared withdrawal risk.
In a new situation, such as an incidental result from a nonfasting sample, correct the sampling problem before building a tumor diagnosis. In a patient with an active ulcer and suspected gastrinoma, treating acid injury takes priority over an unsupervised medication washout. [4]
Use anatomy to explain a failed acid response
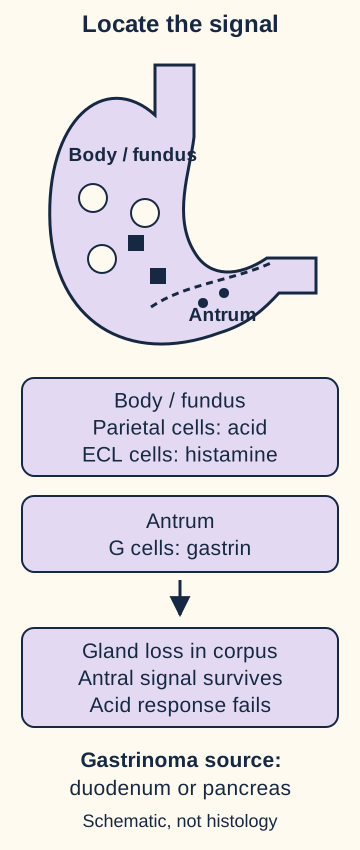
How can gastrin remain high when acid-producing tissue disappears? The hormone source and the acid-producing cells occupy different regions. Antral G cells supply gastrin; the body and fundus contain the oxyntic glands with parietal cells and enterochromaffin-like (ECL) cells. The anatomy figure separates the signal source from its targets. [1][3]
Parietal cells secrete acid and intrinsic factor. ECL cells release histamine, which stimulates parietal cells. Autoimmune gastritis characteristically injures the body and fundus while relatively sparing the antrum. The surviving G cells respond to diminished acid feedback, but additional gastrin cannot replace lost parietal cells. Advanced disease can produce achlorhydria, meaning essentially absent acid secretion. A single high pH sample supports low acidity but does not establish permanent achlorhydria. [3][4]
Trace the two locations: on the anatomy figure, identify where gastrin is made, then where acid is made. Predict what happens to gastrin if oxyntic glands are lost while the antrum remains intact.
Circles represent parietal cells, squares ECL cells, and small dots G cells. The antral hormone source can survive body/fundus gland loss. [1][3][4]Check the regional prediction
Gastrin rises because acid feedback is weak. The intact antral signal does not imply that the body and fundus can still produce an adequate acid response.
The clinical consequence is not limited to a hormone result. Low acid impairs iron handling; loss of intrinsic factor impairs vitamin B12 absorption. Iron deficiency may precede B12 deficiency, so a normal B12 level or a microcytic rather than macrocytic blood count does not exclude corpus-predominant atrophy. Pernicious anemia is a late manifestation of autoimmune gastritis, not a synonym for every stage of the disease. [3]
Histology confirms atrophic gastritis. During endoscopy, samples from the body and the antrum/incisura should be separately labeled so regional information survives. Parietal-cell and intrinsic-factor antibodies can support an autoimmune cause, but neither replaces biopsy: parietal-cell antibodies can be nonspecific and intrinsic-factor antibodies have limited sensitivity. Evaluate iron and B12 status, test for Helicobacter pylori, and consider associated autoimmune thyroid disease. [3]
Apply this to a patient with unexplained iron deficiency, high gastrin, and no PPI exposure. The next explanation to investigate is not necessarily a gastrin-secreting tumor; corpus gland loss could account for both findings. H. pylori-associated atrophy can also reduce acid production. Not all atrophic gastritis is autoimmune, and not every H. pylori infection produces the same acid state. [3][4]
Follow the feedback, not just the drug target
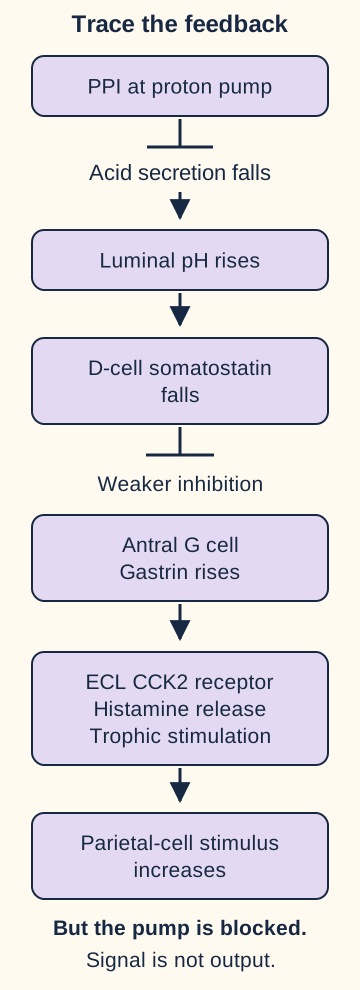
Why does a drug that suppresses acid increase an acid-stimulating hormone? PPIs inhibit the parietal-cell H+/K+-ATPase, the final acid-secretory pump. They do not block gastrin receptors. The higher luminal pH weakens acid-induced somatostatin release from antral D cells, reducing inhibition of G cells. Gastrin consequently rises. [1]
Gastrin reaches CCK2 receptors on ECL cells and promotes histamine release. Histamine acts at parietal-cell H2 receptors. The feedback figure shows why a strong upstream stimulus can coexist with low downstream output: the final pump remains inhibited during effective PPI therapy. A rise in gastrin therefore does not by itself mean that suppression has failed. [1]
Arrowheads show a downstream consequence; flat bars denote an inhibitory relationship. PPI inhibits acid secretion, and less D-cell somatostatin means less inhibition of G cells. High upstream stimulation can coexist with a blocked final pump. [1]
Trace one perturbation at a time
Use the figure as a direction-tracing exercise. Start at the PPI bar across the pump, follow the reduced acid path to the D cell, and then follow the inhibition bar to the G cell. Before opening each answer, predict just the next response.
If acid secretion falls, which way does luminal pH change?
pH rises. Higher pH means lower hydrogen ion concentration, not more acid.
With less acid stimulation of D cells, what happens to G-cell restraint?
Somatostatin restraint decreases, so the G cell can release more gastrin.
With more gastrin, must acid output rise during effective PPI treatment?
No. ECL stimulation can increase while inhibition of the final pump keeps acid output low.
The complete prediction is visible here: pump inhibition lowers acid secretion, higher pH reduces the acid-dependent somatostatin brake, and gastrin rises. Neural, meal-related and inflammatory inputs also affect secretion. Closing the optional answers lets you retrace the same circuit without changing the lesson.
With sustained stimulation, gastrin also has a trophic effect on ECL cells. Linear or micronodular ECL hyperplasia is increased cell growth, not automatically a neuroendocrine tumor. Interpret the actual pathology together with the cause and duration of hypergastrinemia. Chromogranin A may also rise during PPI therapy and is not a specific tumor confirmation. [1][3][4]
Transfer the model to severe autoimmune atrophy: the same hormone can stimulate residual ECL cells even when parietal-cell loss prevents acid secretion. Autoimmune atrophic gastritis carries a recognized risk of type 1 gastric neuroendocrine tumors and gastric adenocarcinoma; it warrants appropriate endoscopic assessment rather than reassurance based solely on the word compensation. That risk context should not be indiscriminately assigned to every PPI user. [3]
Three causes, two acid states
Can the largest gastrin number identify the most dangerous cause? No concentration alone reliably separates medication-related compensation, corpus atrophy, and gastrinoma. Start by asking whether the hormone is appropriate for the measured acid state. Then ask why that state exists. [4]
Interpretation under the stated conditions
Situation
Acid and gastrin
What separates it?
SituationEffective PPI therapy
Acid and gastrinLower acid, higher pH, increased gastrin
What separates it?A pharmacologic block; high pH does not exclude a treated underlying disorder.
SituationAdvanced corpus atrophy
Acid and gastrinLower acid, higher pH, increased gastrin
What separates it?Histologic gland loss, sometimes iron or B12 deficiency.
SituationUntreated gastrinoma
Acid and gastrinAcidic stomach despite increased gastrin
What separates it?Inappropriate secretion; evaluate acid disease and confirm biochemically.
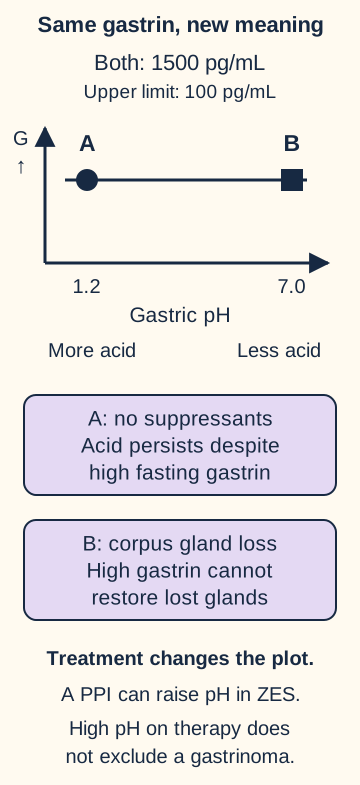
The paired-data figure places high gastrin on two sides of an acidity comparison. For this exercise, sort three descriptions: a patient taking a PPI with pH 6; an untreated patient with corpus atrophy and pH 7; and an untreated patient with recurrent distal ulcers and pH 1.3. All have increased fasting gastrin.
G represents fasting gastrin. A is an untreated acid-secretory pattern; B is corpus gland loss. The values are worked examples, not a diagnostic calculator. PPI treatment can raise the pH of patient A without eliminating a tumor. [3][4]Check the sort
The first two belong to the low-acidity group for different reasons. The third has high gastrin despite an acidic stomach and needs evaluation for inappropriate gastrin secretion.
Now change only the treatment state of the third patient: after a PPI, pH becomes 5.5 and diarrhea improves. The visible consequence is a new acid state, not proof that the tumor has disappeared. This is why the diagram labels untreated gastrinoma explicitly. The same patient can occupy a different position during successful treatment. [4]
Gastrinomas commonly arise in the duodenum or pancreas. Their hormone secretion drives an acid-capable stomach and can cause recurrent, refractory, or postbulbar ulcers, severe reflux, and diarrhea. These findings prompt investigation but are not individually diagnostic. Multiple endocrine neoplasia type 1 (MEN1) can combine gastrinoma with primary hyperparathyroidism and pituitary disease. A history of recurrent kidney stones with hypercalcemia or a relevant family history broadens the evaluation. [4]
Other causes matter when the pattern is incomplete. Renal disease can affect gastrin interpretation. H. pylori may accompany different secretory states depending on the distribution of gastritis. Retained antral tissue after gastric surgery is a rare cause of inappropriate gastrin secretion. A low gastric pH alone is also not abnormal: a healthy fasting stomach can be strongly acidic. The abnormal pairing is persistent fasting hypergastrinemia with acid secretion that should suppress it. [4]
Read paired measurements before ordering localization
When does a high gastrin result become compelling evidence for Zollinger-Ellison syndrome (ZES)? The classical biochemical pattern is fasting gastrin more than ten times the assay upper limit with gastric pH at or below 2, assessed under appropriate conditions and after excluding rare alternatives such as retained antrum. ZES is the acid-hypersecretory syndrome caused by a gastrinoma. [4]
Compare these worked examples using a laboratory upper limit of 100 pg/mL. A value of 1,500 pg/mL is fifteen times that limit. With pH 1.2 in an untreated patient without gastric surgery, the combination meets the classical biochemical criteria. The identical value with pH 7 and corpus gland loss instead supports compensatory hypergastrinemia. Very high values occur in atrophic gastritis and can occur during PPI therapy. [4]
Calculate before classifying: fasting gastrin is 680 pg/mL, the upper limit is 100 pg/mL, and gastric pH is 1.6 in a specialist-supervised evaluation. Is the more-than-tenfold criterion met?
Check the calculation and consequence
680 divided by 100 is 6.8. The value does not meet that criterion. Because gastrin is still inappropriate for the acidity, the result requires further evaluation rather than dismissal.
A lesser gastrin increase with pH at or below 2 may require a secretin stimulation test or acid-output assessment. Secretin can provoke a paradoxical gastrin rise in gastrinoma. A rise of at least 120 pg/mL is the validated positive threshold described in the cited review. Follow the specialist laboratory protocol for boundary values; acid state and treatment conditions matter. Hypochlorhydria or achlorhydria can produce false-positive results. Do not interpret a positive test obtained during profound PPI suppression as unconditional proof of ZES. [4]
Testing strategy belongs with an experienced service. Some patients need assessment of active peptic disease and a carefully supervised adjustment of suppression; this lesson does not provide an outpatient withdrawal schedule. If a result conflicts with the phenotype, recheck conditions and laboratory reliability. A fasting hormone level, a secretin result, and an imaging abnormality each answer different questions.
Apply this distinction to a small pancreatic lesion discovered while a patient takes a PPI. Localization can identify a lesion, but cannot by itself establish that the lesion is the source of gastrin or that the patient has acid hypersecretion. Conversely, negative imaging cannot reliably exclude a small duodenal gastrinoma when the biochemical and clinical pattern is convincing. Establish the functional syndrome and use imaging to localize and stage it with specialist input. [4]
Rebound does not automatically mean relapse
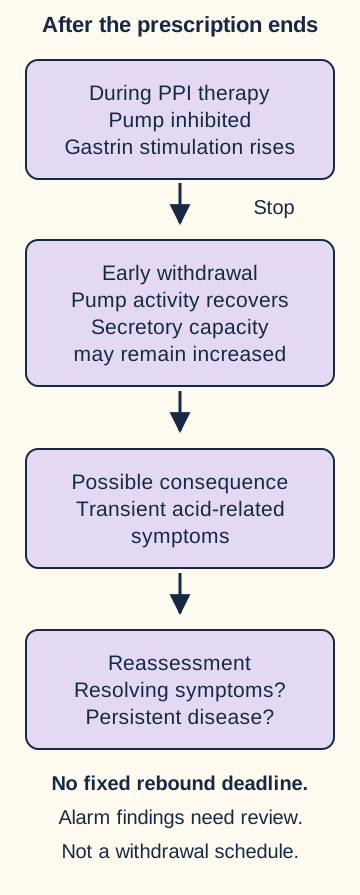
Does heartburn after stopping a PPI prove that indefinite treatment was necessary? No. During prolonged suppression, increased gastrin and ECL stimulation can increase acid-secretory capacity. When pump activity recovers after withdrawal, that capacity can temporarily produce more acid than before treatment. Rebound is a treatment-related possibility; recurrent underlying disease is another. Symptoms alone do not reliably distinguish them. [1]
The withdrawal figure separates the on-treatment state from early withdrawal and later reassessment. Predict which state can combine recovering pump activity with persisting secretory stimulation. The answer is early withdrawal, but the figure is a conceptual time course, not a clock that predicts an individual's symptom duration.
The state sequence has no numeric time scale. Increased secretory capacity can outlast suppression, but symptoms alone do not prove rebound. Indication review and alarm findings govern the clinical response. [1][2][5]Check the prediction
Restored pump activity can expose increased secretory capacity after suppression ends. This explains why new symptoms can appear without proving chronic reflux disease.
In a randomized trial of healthy volunteers, acid-related symptoms during the four weeks after an eight-week esomeprazole course occurred in 44% of the PPI group and 15% of the placebo group. These were reported symptoms, not direct acid-output measurements. The trial supports a withdrawal effect but does not tell us whether a particular patient with established reflux has rebound, relapse, or both. Avoid giving every patient a fixed two-week rebound deadline. [5][1]
Review the indication before the taper
Regularly document why treatment continues. A patient whose temporary indication has ended may be suitable for a trial of deprescribing. In contrast, patients with prior severe erosive esophagitis, esophageal ulcer or peptic stricture, or high upper gastrointestinal bleeding risk generally should not undergo PPI discontinuation. Barrett esophagus and eosinophilic esophagitis are additional reasons not to use a routine deprescribing pathway. Suspected or established gastrinoma requires its own acid-control plan. [2][4]
For an appropriate candidate, either tapering or abrupt discontinuation can be considered; neither is guaranteed to prevent rebound. Many patients taking twice-daily treatment who retain a chronic PPI indication can be considered for once-daily dosing, depending on the indication and response. Agree on symptom rescue, such as an appropriate antacid, alginate, or short-term H2-receptor antagonist, and a reassessment plan. Deprescribing is an indication-based decision, not an attempt to normalize an incidental gastrin result. [2][1]
Apply the boundary to two patients with similar post-withdrawal burning. One has mild symptoms, no alarm findings, and no continuing indication: time-limited rescue and reassessment may be reasonable. The other develops dysphagia, weight loss, bleeding, refractory diarrhea, or recurrent unusual ulcers: evaluate rather than assigning every symptom to rebound. Hematemesis, melena with illness, syncope, or severe acute abdominal pain requires urgent assessment. [4][6]
Keep three questions together: Is the hormone appropriate for the acid state? What explains that state? Does this patient still need acid suppression? These questions connect physiology to a safer decision without treating the laboratory number in isolation.
Apply the lesson
Case 1
Show answer and explanations for case 1
A. Reduced D-cell restraint; inhibition of the parietal pump (Best answer)
Reduced acid stimulation weakens D-cell somatostatin restraint and allows gastrin to rise. Pantoprazole blocks the final pump, so the increased hormone drive coexists with low acidity.
Reasoning steps for option A
With gastric pH 5.8 during pantoprazole therapy, how does reduced acid signaling affect D-cell restraint of gastrin release?
Reduced acid stimulation weakens D-cell somatostatin restraint and allows gastrin to rise.
Why can gastrin be 480 pg/mL even though pantoprazole keeps gastric acidity low?
Pantoprazole blocks the final pump, so the increased hormone drive coexists with low acidity.
B. Increased D-cell restraint; inhibition of the parietal pump (Why this does not fit)
The pump target correctly explains low acidity. Increased somatostatin restraint would oppose, rather than explain, the increased gastrin.
Reasoning steps for option B
Which part of increased D-cell restraint plus pump inhibition could explain pH 5.8 during pantoprazole use?
Inhibition of the parietal proton pump reduces acid secretion and explains pH 5.8; it does not validate the proposed increase in D-cell restraint.
Why does increased D-cell restraint conflict with the fasting gastrin of 480 pg/mL?
Increased somatostatin restraint would oppose, rather than explain, the increased gastrin.
C. Reduced D-cell restraint; blockade of ECL CCK2 receptors (Why this does not fit)
Reduced D-cell restraint correctly predicts a gastrin rise. Pantoprazole inhibits the parietal pump rather than the gastrin receptor on ECL cells.
Reasoning steps for option C
How would reduced D-cell restraint affect gastrin in this patient?
Reduced D-cell restraint correctly predicts a gastrin rise.
Why is ECL CCK2 receptor blockade the wrong drug mechanism for pantoprazole?
Pantoprazole inhibits the parietal pump rather than the gastrin receptor on ECL cells.
D. Increased D-cell restraint; blockade of parietal H2 receptors (Why this does not fit)
Histamine H2 blockade can reduce acid secretion. The drug is a PPI rather than an H2 blocker, and increased D-cell restraint would not explain the gastrin rise.
Reasoning steps for option D
How could parietal H2 receptor blockade affect gastric acidity if it were present?
Histamine H2 blockade can reduce acid secretion.
What two findings make increased D-cell restraint plus H2 blockade a poor explanation here?
The drug is a PPI rather than an H2 blocker, and increased D-cell restraint would not explain the gastrin rise.
Takeaway: Identify pump inhibition as the reason increased hormone drive need not restore acidity
A. Gastrin-driven histamine decreases; acidity returns to pretreatment levels (Why this does not fit)
Blocking the ECL receptor should reduce gastrin-driven histamine release. It cannot restore pretreatment acidity while the downstream proton pump remains inhibited.
Reasoning steps for option A
What happens to gastrin-driven ECL histamine release when CCK2 signaling is selectively blocked?
Blocking the ECL receptor should reduce gastrin-driven histamine release.
Why would reduced ECL histamine fail to restore pretreatment acidity during continued omeprazole therapy?
It cannot restore pretreatment acidity while the downstream proton pump remains inhibited.
B. Gastrin-driven histamine decreases; acidity remains suppressed (Best answer)
The receptor intervention reduces the ECL response to gastrin. Maintained PPI pump inhibition continues to suppress acidity, so a reduced histamine signal does not reverse the drug effect.
Reasoning steps for option B
What ECL response follows selective blockade of gastrin signaling at CCK2 receptors?
The receptor intervention reduces the ECL response to gastrin.
With the proton pump still inhibited, what happens to acidity despite the change in histamine release?
Maintained PPI pump inhibition continues to suppress acidity, so a reduced histamine signal does not reverse the drug effect.
C. Gastrin-driven histamine persists; acidity remains suppressed (Why this does not fit)
Continued pump inhibition correctly predicts continued suppression. The selective CCK2 intervention interrupts the gastrin-driven component of ECL histamine release.
Reasoning steps for option C
Why does continued omeprazole use support the predicted persistence of low acidity?
Continued pump inhibition correctly predicts continued suppression.
Why is persistent gastrin-driven histamine release inconsistent with the specified CCK2 intervention?
The selective CCK2 intervention interrupts the gastrin-driven component of ECL histamine release.
D. Gastrin-driven histamine persists; acidity returns to pretreatment levels (Why this does not fit)
Persisting upstream stimulation could increase acid if an intact final pathway were available. Here both the specified gastrin receptor input and final pump activity are inhibited.
Reasoning steps for option D
Under what pathway condition could persistent upstream stimulation increase acid secretion?
Persisting upstream stimulation could increase acid if an intact final pathway were available.
Which two blocks prevent the proposed return to pretreatment acidity in this experiment?
Here both the specified gastrin receptor input and final pump activity are inhibited.
Takeaway: Follow the maintained pump block to predict continued low acidity
A. Reduced acid feedback with preserved intrinsic factor (Why this does not fit)
Reduced acid feedback explains the compensatory gastrin rise. Preserved intrinsic factor fails to connect progressive parietal-cell loss to the later B12 deficiency.
Reasoning steps for option A
How does loss of acid production account for gastrin of 1400 pg/mL in this untreated patient?
Reduced acid feedback explains the compensatory gastrin rise.
Why would preserved intrinsic factor leave the later B12 deficiency unexplained?
Preserved intrinsic factor fails to connect progressive parietal-cell loss to the later B12 deficiency.
B. Autonomous gastrin release and increased parietal mass (Why this does not fit)
A gastrinoma can cause high gastrin and trophic acid-secretory changes. The untreated high pH and gland loss instead show failed oxyntic function.
Reasoning steps for option B
What gastric changes can accompany autonomous gastrin release from a gastrinoma?
A gastrinoma can cause high gastrin and trophic acid-secretory changes.
Why do pH 7.0 and corpus-predominant gland loss argue against autonomous gastrin release with increased parietal mass?
The untreated high pH and gland loss instead show failed oxyntic function.
C. Loss of antral G cells and reduced duodenal bicarbonate (Why this does not fit)
Antral injury can impair gastrin production. Preserved antrum and high gastrin argue against G-cell loss, and bicarbonate loss does not explain intrinsic-factor-dependent B12 absorption.
Reasoning steps for option C
If antral G cells had been lost, what would happen to gastrin production?
Antral injury can impair gastrin production.
Why do the preserved antrum and later B12 deficiency undermine a G-cell-loss and bicarbonate-loss explanation?
Preserved antrum and high gastrin argue against G-cell loss, and bicarbonate loss does not explain intrinsic-factor-dependent B12 absorption.
D. Reduced acid feedback and reduced intrinsic factor (Best answer)
Parietal-cell loss weakens acid feedback while reducing intrinsic factor. Surviving antral G cells produce more gastrin, and progressive loss of intrinsic factor explains B12 deficiency.
Reasoning steps for option D
How does corpus parietal-cell loss link reduced acid feedback to intrinsic-factor production?
Parietal-cell loss weakens acid feedback while reducing intrinsic factor.
Why can gastrin rise while B12 deficiency develops when the antrum is preserved but oxyntic glands are lost?
Surviving antral G cells produce more gastrin, and progressive loss of intrinsic factor explains B12 deficiency.
Takeaway: Infer preserved G-cell compensation and impaired intrinsic factor
A. Inappropriate but unconfirmed secretion; pursue specialist testing (Best answer)
Acidic hypergastrinemia below the tenfold threshold raises concern without completing the classical diagnostic criterion. Specialist secretin or acid-output assessment addresses the remaining functional uncertainty before localization.
Reasoning steps for option A
What does fasting gastrin of 640 pg/mL alongside gastric pH 1.4 suggest without yet meeting the classical tenfold criterion?
Acidic hypergastrinemia below the tenfold threshold raises concern without completing the classical diagnostic criterion.
Which specialist assessments can resolve the remaining functional uncertainty before tumor localization?
Specialist secretin or acid-output assessment addresses the remaining functional uncertainty before localization.
B. Compensatory secretion; evaluate for corpus atrophy (Why this does not fit)
Corpus atrophy can cause compensatory hypergastrinemia. The pH of 1.4 shows an acidic stomach, not the acid deficiency expected from advanced corpus atrophy.
Reasoning steps for option B
Why might corpus atrophy initially seem relevant to an elevated gastrin result?
Corpus atrophy can cause compensatory hypergastrinemia.
Which gastric pH finding argues against advanced corpus atrophy as the explanation?
The pH of 1.4 shows an acidic stomach, not the acid deficiency expected from advanced corpus atrophy.
C. Biochemically established ZES; begin tumor localization (Why this does not fit)
More than tenfold fasting gastrin with an acidic stomach can establish the classical pattern. The supplied 6.4-fold increase calls for further confirmation before using that criterion.
Reasoning steps for option C
What combination of fasting gastrin and gastric acidity can satisfy the classical biochemical pattern of ZES?
More than tenfold fasting gastrin with an acidic stomach can establish the classical pattern.
Why does this patient's 640 pg/mL gastrin result call for confirmation before localization?
The supplied 6.4-fold increase calls for further confirmation before using that criterion.
D. Low probability of ZES; treat as ordinary recurrent ulcer disease (Why this does not fit)
Many recurrent ulcers have causes other than gastrinoma. Persistent fasting hypergastrinemia with strong acidity and diarrhea merits further evaluation even below the tenfold threshold.
Reasoning steps for option D
Why should recurrent ulcers not automatically be attributed to gastrinoma?
Many recurrent ulcers have causes other than gastrinoma.
Which combination of findings makes further ZES evaluation warranted despite gastrin remaining below tenfold the upper limit?
Persistent fasting hypergastrinemia with strong acidity and diarrhea merits further evaluation even below the tenfold threshold.
Takeaway: Select further specialist biochemical assessment
A. Proceed to tumor-directed treatment using the gastrin result (Why this does not fit)
Tumor treatment is relevant once a gastrinoma is established. This PPI-exposed result is confounded and does not itself establish a tumor.
Reasoning steps for option A
When would tumor-directed treatment become appropriate for suspected gastrinoma?
Tumor treatment is relevant once a gastrinoma is established.
Why does gastrin of 720 pg/mL measured at pH 6.1 on esomeprazole not establish a tumor?
This PPI-exposed result is confounded and does not itself establish a tumor.
B. Continue acid control while arranging specialist testing (Best answer)
An underlying hypersecretory disorder can be masked by effective PPI treatment. The pretreatment phenotype makes an unmonitored interruption hazardous despite the current high pH.
Reasoning steps for option B
Why does symptom control on high-dose esomeprazole not exclude the disorder suggested by earlier distal duodenal ulcers and diarrhea?
An underlying hypersecretory disorder can be masked by effective PPI treatment.
How does the severe pretreatment ulcer-diarrhea history affect the safety of interrupting acid suppression?
The pretreatment phenotype makes an unmonitored interruption hazardous despite the current high pH.
C. Hold therapy for one week and repeat outpatient sampling (Why this does not fit)
Drug-free sampling can reduce biochemical confounding. The severe pretreatment ulcer-diarrhea pattern makes an unmonitored interruption hazardous.
Reasoning steps for option C
What diagnostic advantage could sampling without esomeprazole provide?
Drug-free sampling can reduce biochemical confounding.
Why is an unmonitored one-week treatment interruption risky in this patient?
The severe pretreatment ulcer-diarrhea pattern makes an unmonitored interruption hazardous.
D. Continue therapy and close the investigation because pH is high (Why this does not fit)
A high pH shows low gastric acidity at the time sampled. It does not establish the cause or exclude a treated gastrinoma in a patient with this prior phenotype.
Reasoning steps for option D
What does gastric pH 6.1 establish about acidity at the time of sampling?
A high pH shows low gastric acidity at the time sampled.
Why does that high pH neither identify the cause of hypergastrinemia nor rule out a treated gastrinoma?
Esomeprazole inhibits the final acid-secretory pump even if a gastrinoma continues secreting gastrin. The resulting low acidity can also raise gastrin through feedback, so these treated measurements cannot distinguish drug-related compensation from a masked gastrinoma.
Takeaway: Keep acid control while resolving biochemical uncertainty
A. MEN1 concern with drug-confounded gastric testing (Best answer)
The endocrine constellation raises suspicion for MEN1-associated disease. PPI-associated suppression still prevents attribution of this gastrin result to a tumor without further assessment.
Reasoning steps for option A
In this patient with primary hyperparathyroidism and a sister treated for a pituitary adenoma, what inherited disorder should be considered?
The endocrine constellation raises suspicion for MEN1-associated disease.
Why can his gastrin of 420 pg/mL at pH 5.2 not be attributed to a tumor while he takes omeprazole?
PPI-associated suppression still prevents attribution of this gastrin result to a tumor without further assessment.
B. Sporadic reflux favored, with an interpretable negative acid test (Why this does not fit)
High pH can be reassuring when evaluating an untreated stomach. Here it is measured during therapy and cannot override the endocrine and ulcer history.
Reasoning steps for option B
If this patient's gastric pH of 5.2 had been measured without acid-suppressing treatment, how could it inform an evaluation for acid hypersecretion?
High pH can be reassuring when evaluating an untreated stomach.
Why does the pH of 5.2 measured during omeprazole therapy not outweigh his recurrent ulcers and endocrine history?
Here it is measured during therapy and cannot override the endocrine and ulcer history.
C. MEN1 concern with gastrin attributed to parathyroid disease (Why this does not fit)
The endocrine constellation warrants inherited-syndrome assessment. Attributing the gastric result to parathyroid disease would leave the ulcer history and PPI confounding unresolved.
Reasoning steps for option C
What does the combination of primary hyperparathyroidism and a first-degree relative with a pituitary adenoma warrant in this patient?
The endocrine constellation warrants inherited-syndrome assessment.
Why would attributing his elevated gastrin solely to parathyroid disease be incomplete?
Attributing the gastric result to parathyroid disease would leave the ulcer history and PPI confounding unresolved.
D. MEN1 concern with gastric tumor function already established (Why this does not fit)
The parathyroid and family pituitary pattern raises concern for MEN1. It does not establish a gastrin-secreting source from drug-confounded gastric measurements.
Reasoning steps for option D
What concern is raised by this patient's parathyroid disease and his sister's pituitary adenoma?
The parathyroid and family pituitary pattern raises concern for MEN1.
Do his gastrin of 420 pg/mL and pH of 5.2 during omeprazole therapy establish a gastrin-secreting tumor?
No. Omeprazole-associated acid suppression confounds the gastrin measurement, so these results do not establish a gastrin-secreting source despite the MEN1 concern.
Takeaway: Separate syndrome suspicion from functional tumor confirmation
A. End gastric follow-up because compensation is physiologic (Why this does not fit)
The gastrin response is appropriate for reduced acid secretion. An appropriate response does not erase the neoplastic risk associated with autoimmune atrophy.
Reasoning steps for option A
How does loss of acid secretion from autoimmune corpus atrophy explain this patient's gastrin of 1600 pg/mL?
At pH 6.8, reduced acid feedback permits a compensatory rise in gastrin; the high concentration is appropriate for the loss of acid secretion.
Why does a compensatory gastrin rise not end the need to consider gastric follow-up in autoimmune atrophy?
An appropriate response does not erase the neoplastic risk associated with autoimmune atrophy.
B. Classify the linear proliferation as a type 1 gastric NET (Why this does not fit)
Autoimmune atrophy can predispose to type 1 gastric NETs. Linear ECL hyperplasia is not itself a discrete NET; the biopsy has not described one.
Reasoning steps for option B
Which gastric neuroendocrine tumor subtype can arise in the setting of this patient's autoimmune atrophy?
Autoimmune atrophy can predispose to type 1 gastric NETs.
Does linear ECL hyperplasia without a discrete lesion on this patient's biopsy constitute a gastric NET?
Linear ECL hyperplasia is not itself a discrete NET; the biopsy has not described one.
C. Assess atrophy-related risk; hyperplasia is not a tumor (Best answer)
Autoimmune atrophy is associated with type 1 gastric neuroendocrine tumors and adenocarcinoma. The current biopsy describes hyperplasia; endoscopic risk assessment is justified by the underlying atrophy, not an invented tumor diagnosis.
Reasoning steps for option C
Which two neoplastic risks are associated with this patient's autoimmune corpus atrophy?
Autoimmune atrophy is associated with type 1 gastric neuroendocrine tumors and adenocarcinoma.
Why is endoscopic risk assessment justified despite a biopsy showing only linear ECL hyperplasia?
The current biopsy describes hyperplasia; endoscopic risk assessment is justified by the underlying atrophy, not an invented tumor diagnosis.
D. Treat acid hypersecretion to suppress the trophic response (Why this does not fit)
Acid control is needed in hypersecretory disease. The sampled stomach is already poorly acidic because oxyntic glands have been lost.
Reasoning steps for option D
What acid-secretory state would justify treating hypersecretion, rather than the low-acid state documented in this patient?
Excess acid secretion would justify acid control. This patient's pH 6.8 and autoimmune corpus atrophy instead indicate low acidity.
Why would treatment for acid hypersecretion not fit this patient's pH of 6.8 and autoimmune loss of oxyntic glands?
The sampled stomach is already poorly acidic because oxyntic glands have been lost.
Takeaway: Retain risk assessment for autoimmune atrophy
A. Restart daily PPI and defer any further withdrawal trial (Why this does not fit)
A daily PPI may relieve the symptoms. Deferring another appropriate withdrawal attempt solely because of mild early symptoms risks unnecessary prolonged suppression before determining whether symptoms persist.
Reasoning steps for option A
What symptom benefit might restarting a daily PPI provide for this patient's mild heartburn nine days after discontinuation?
A daily PPI may relieve the symptoms.
Why should mild early heartburn alone not defer another withdrawal attempt when the ulcer-treatment indication has ended?
Deferring another appropriate withdrawal attempt solely because of mild early symptoms risks unnecessary prolonged suppression before determining whether symptoms persist.
B. Offer time-limited rescue with planned reassessment (Best answer)
Withdrawal can cause transient acid-related symptoms. The ended indication and absence of alarm findings support rescue and reassessment rather than an automatic chronic prescription.
Reasoning steps for option B
What withdrawal-related mechanism could explain heartburn nine days after this patient's planned PPI discontinuation?
As pump activity recovers after withdrawal, increased secretory capacity from gastrin-driven ECL stimulation can transiently increase acid secretion. This makes rebound-related heartburn plausible, but symptoms alone do not prove rebound rather than recurrent reflux.
What do the ended indication and absence of alarm symptoms support instead of an automatic chronic PPI prescription?
The ended indication and absence of alarm findings support rescue and reassessment rather than an automatic chronic prescription.
C. Use an H2 antagonist continuously without a return plan (Why this does not fit)
An H2 antagonist can be a symptom-relief option. Substitution without reassessment recreates indefinite suppression before establishing a continuing indication.
Reasoning steps for option C
What role could an H2 antagonist have for this patient's post-withdrawal heartburn?
An H2 antagonist can be a symptom-relief option.
Why would continuous H2-antagonist use without reassessment be a poor substitute for evaluating whether suppression remains necessary?
Substitution without reassessment recreates indefinite suppression before establishing a continuing indication.
D. Repeat endoscopy now to distinguish rebound from relapse (Why this does not fit)
Endoscopy can identify erosive or ulcerative disease when indicated. Mild early symptoms without alarm findings do not require immediate endoscopy, which cannot itself measure rebound physiology.
Reasoning steps for option D
What could endoscopy detect if this patient's symptoms or risk factors later warranted it?
Endoscopy can identify erosive or ulcerative disease when indicated.
Why is immediate endoscopy unnecessary for mild early heartburn without alarm symptoms, and what withdrawal mechanism can it not measure?
Mild early symptoms without alarm findings do not require immediate endoscopy, which cannot itself measure rebound physiology.
Takeaway: Recognize rebound as plausible and arrange reassessment
A. Discontinue PPI because dilation corrected the structural lesion (Why this does not fit)
Dilation can relieve a fixed esophageal narrowing. It does not eliminate the acid injury that produced a peptic stricture, so recurrence prevention can remain indicated.
Reasoning steps for option A
What did dilation accomplish for this patient's short fibrotic esophageal narrowing?
Dilation can relieve a fixed esophageal narrowing.
Why might acid suppression still be indicated after dilation of a stricture preceded by severe erosive esophagitis?
It does not eliminate the acid injury that produced a peptic stricture, so recurrence prevention can remain indicated.
B. Preserve maintenance suppression; review the effective dose (Best answer)
Severe erosions followed by a benign fibrotic narrowing support a peptic stricture. That complication supports maintenance acid protection; low acidity at sampling during PPI use is compatible with feedback hypergastrinemia.
Reasoning steps for option B
What diagnosis is supported by severe distal erosions followed by a benign fibrotic esophageal narrowing?
Severe erosions followed by a benign fibrotic narrowing support a peptic stricture.
How do that prior complication and a pH of 5.6 during pantoprazole use inform maintenance treatment and interpretation of gastrin 380 pg/mL?
That complication supports maintenance acid protection; low acidity at sampling during PPI use is compatible with feedback hypergastrinemia.
C. Use antacid rescue alone because current symptoms have resolved (Why this does not fit)
Antacids can relieve intermittent acid symptoms. Absence of symptoms during treatment does not remove the preventive indication after a peptic stricture.
Reasoning steps for option C
What could antacids do for this patient if intermittent acid symptoms occur?
Antacids can relieve intermittent acid symptoms.
Why does being asymptomatic after dilation and pantoprazole not eliminate the preventive indication for acid suppression?
Absence of symptoms during treatment does not remove the preventive indication after a peptic stricture.
D. Escalate suppression because gastrin suggests inadequate control (Why this does not fit)
Acid-control failure could require treatment adjustment. High pH and symptom control argue against judging failure from compensatory gastrin alone.
Reasoning steps for option D
Under what circumstance might this patient's acid-suppressive treatment need adjustment?
Acid-control failure could require treatment adjustment.
Why do his pH of 5.6 and symptom control argue against escalating pantoprazole solely because gastrin is 380 pg/mL?
High pH and symptom control argue against judging failure from compensatory gastrin alone.
Takeaway: Retain indication-based protection rather than pursue hormone normalization
A. A: additional specialist secretory testing; B: address sampling and drug effects first (Best answer)
A has inappropriate acidic hypergastrinemia below the classical tenfold threshold and needs further biochemical confirmation. B has a nonfasting, drug-exposed result in a suppressed stomach; conditions must be clarified safely before treating that value as diagnostic.
Reasoning steps for option A
What further step fits Patient A's repeated fasting gastrin of 640 pg/mL with pH 1.4 under controlled, drug-free conditions?
A has inappropriate acidic hypergastrinemia below the classical tenfold threshold and needs further biochemical confirmation.
Why must Patient B's breakfast-time gastrin of 1180 pg/mL on a PPI be reassessed before it is considered diagnostic?
B has a nonfasting, drug-exposed result in a suppressed stomach; conditions must be clarified safely before treating that value as diagnostic.
B. A: proceed to localization as confirmed ZES; B: address sampling and drug effects first (Why this does not fit)
B needs a valid physiologic assessment before a diagnostic conclusion. A does not meet the greater-than-tenfold classical criterion; the acidic result still requires further confirmation.
Reasoning steps for option B
What must be established for Patient B before proceeding from a nonfasting, PPI-exposed result to a ZES diagnosis?
B needs a valid physiologic assessment before a diagnostic conclusion.
Why is localization premature for Patient A despite acidic hypergastrinemia at pH 1.4?
A does not meet the greater-than-tenfold classical criterion; the acidic result still requires further confirmation.
C. A: additional specialist secretory testing; B: proceed to localization as confirmed ZES (Why this does not fit)
A is an appropriate candidate for further biochemical assessment. B's apparent greater-than-tenfold result cannot bypass nonfasting sampling and PPI-associated low acidity.
Reasoning steps for option C
Why is Patient A, whose gastrin is elevated but below ten times the upper limit with pH 1.4, a candidate for further biochemical testing?
A's 6.4-fold gastrin elevation is inappropriate at pH 1.4, but remains below the classical greater-than-tenfold criterion, so further biochemical confirmation is needed.
Why does Patient B's gastrin above ten times the upper limit not justify immediate localization?
B's apparent greater-than-tenfold result cannot bypass nonfasting sampling and PPI-associated low acidity.
D. A: proceed to localization as confirmed ZES; B: proceed to localization as confirmed ZES (Why this does not fit)
Localization becomes relevant once the functional evidence adequately establishes the disorder. Neither A's subthreshold acidic pattern nor B's confounded sample alone establishes it by the classical criterion.
Reasoning steps for option D
When does tumor localization become appropriate in a patient being evaluated for ZES?
Localization becomes relevant once the functional evidence adequately establishes the disorder.
Why do neither Patient A's subthreshold acidic result nor Patient B's nonfasting, PPI-confounded result alone meet the classical diagnostic criterion?
Neither A's subthreshold acidic pattern nor B's confounded sample alone establishes it by the classical criterion.
Takeaway: Choose additional secretory confirmation for A but establish valid sampling context for B
A. A: compensation; B: autonomous secretion (Why this does not fit)
High gastrin can reflect either appropriate feedback or autonomous secretion. This assigns the acidic and nonacidic phenotypes in reverse.
Reasoning steps for option A
Why can a fasting gastrin of 1250 pg/mL, by itself, represent either feedback or autonomous secretion in these two patients?
The concentration does not show whether acid feedback is intact. A's pH 1.2 makes the elevation inappropriate, whereas B's pH 7.0 and corpus atrophy support compensation for lost acid production.
What is wrong with calling Patient A’s pH 1.2 compensation and Patient B’s pH 7.0 autonomous secretion?
The assignments are reversed: A has high gastrin despite strong acidity, whereas B has a compensatory rise with corpus atrophy and deficient acid production.
B. A: classical ZES pattern; B: medication-related compensation (Why this does not fit)
The first pattern meets the classical biochemical combination. Patient B is off therapy with documented corpus atrophy, which supports gland loss rather than a medication effect.
Reasoning steps for option B
How does Patient A’s gastrin above ten times the upper limit with gastric pH 1.2 fit the classical ZES biochemical pattern?
A's gastrin is 12.5 times the upper limit with pH 1.2 off therapy and no prior gastric surgery, fitting the classical combination of greater-than-tenfold gastrin and pH at or below 2.
Why does Patient B’s corpus atrophy and pH 7.0 off therapy argue against medication-related compensation?
Patient B is off therapy with documented corpus atrophy, which supports gland loss rather than a medication effect.
C. A: autonomous secretion; B: autonomous secretion (Why this does not fit)
Both values exceed ten times the laboratory upper limit. The numerical criterion alone cannot distinguish gland-loss compensation from ZES.
Reasoning steps for option C
What numerical gastrin criterion do both patients meet despite their different gastric pH values?
Both values exceed ten times the laboratory upper limit.
Why does gastrin of 1250 pg/mL alone fail to establish autonomous secretion in Patient B?
The numerical criterion alone cannot distinguish gland-loss compensation from ZES.
D. A: classical ZES pattern; B: gland-loss compensation (Best answer)
More than tenfold gastrin with pH at or below 2 meets the classical pattern after relevant exclusions. The same concentration with corpus atrophy and high pH instead fits an appropriate response to lost acid production.
Reasoning steps for option D
Why does Patient A’s gastrin above ten times the upper limit with pH 1.2 fit the classical ZES pattern after relevant exclusions?
More than tenfold gastrin with pH at or below 2 meets the classical pattern after relevant exclusions.
How do Patient B’s corpus atrophy and pH 7.0 explain the same gastrin concentration?
The same concentration with corpus atrophy and high pH instead fits an appropriate response to lost acid production.
Takeaway: Separate classical ZES from appropriate atrophy-associated compensation
A. Antral samples alone; assess despite normal B12 (Why this does not fit)
Normal B12 does not exclude early corpus-predominant atrophy. Antral samples alone miss the suspected oxyntic loss that explains the acid and iron findings.
Reasoning steps for option A
Does normal B12 exclude early corpus-predominant atrophy in this patient with iron deficiency and pH 6.9?
Normal B12 does not exclude early corpus-predominant atrophy.
Why are antral biopsies alone inadequate when endoscopy suggests corpus atrophy?
Antral samples alone miss the suspected oxyntic loss that explains the acid and iron findings.
B. Separate regional samples; defer assessment until B12 becomes low (Why this does not fit)
Separately labeled body and antrum/incisura samples preserve distribution. Waiting for B12 deficiency ignores that iron deficiency may appear earlier.
Reasoning steps for option B
What does separately labeling body and antrum/incisura biopsies preserve when evaluating suspected gastric atrophy?
Separately labeled body and antrum/incisura samples preserve distribution.
Why should this patient’s iron deficiency be assessed before B12 becomes low?
Waiting for B12 deficiency ignores that iron deficiency may appear earlier.
C. Separate regional samples; normal B12 need not postpone assessment (Best answer)
Iron deficiency may precede B12 deficiency in corpus-predominant atrophy. Separately labeled body and antrum/incisura biopsies can establish the regional disease now.
Reasoning steps for option C
Why does normal B12 not justify postponing assessment of suspected corpus atrophy in this iron-deficient patient?
Iron deficiency may precede B12 deficiency in corpus-predominant atrophy.
How can separately labeled body and antrum/incisura biopsies establish the suspected disease?
Separate labels preserve the regional distribution, allowing body gland loss to be assessed against the antrum/incisura rather than missing corpus disease with antral-only sampling.
D. Antral samples alone; defer assessment until B12 becomes low (Why this does not fit)
Antral sampling examines the source of gastrin. It does not adequately assess corpus loss, and normal B12 is not a reason to wait for a later deficiency.
Reasoning steps for option D
What relevant gastric feature would antral biopsies examine in a patient with high fasting gastrin?
Antral sampling examines the source of gastrin.
Why is antral-only sampling followed by a wait for B12 deficiency inadequate for this patient with pH 6.9 and suspected corpus atrophy?
It does not adequately assess corpus loss, and normal B12 is not a reason to wait for a later deficiency.
Takeaway: Choose separately labeled regional biopsies to map the suspected process
A. Use positive parietal-cell antibodies to replace gastric mapping (Why this does not fit)
Parietal-cell antibodies support autoimmune disease. They can be nonspecific and cannot establish the distribution or severity of tissue loss.
Reasoning steps for option A
What does a positive parietal-cell antibody result contribute to evaluating autoimmune gastric disease?
Parietal-cell antibodies support autoimmune disease.
Why can positive parietal-cell antibodies not replace biopsies that map gastric tissue loss?
They can be nonspecific and cannot establish the distribution or severity of tissue loss.
B. Repeat serology before investigating the gastric mucosa (Why this does not fit)
Repeating an uncertain result can sometimes clarify laboratory discordance. The clinical low-acid and deficiency pattern already warrants histologic assessment rather than waiting for antibody agreement.
Reasoning steps for option B
What might repeating discordant parietal-cell and intrinsic-factor antibody tests clarify?
Repeating an uncertain result can sometimes clarify laboratory discordance.
Why should this patient’s pH 6.5 and B12 deficiency prompt mucosal assessment without waiting for antibody agreement?
The clinical low-acid and deficiency pattern already warrants histologic assessment rather than waiting for antibody agreement.
C. Autoimmune atrophy remains possible and needs histologic assessment (Best answer)
Intrinsic-factor antibodies have limited sensitivity and parietal-cell antibodies are not completely specific. The clinical pattern remains suggestive; biopsy can confirm and map atrophy despite discordant serology.
Reasoning steps for option C
Why does a negative intrinsic-factor antibody result not exclude autoimmune atrophy in this patient?
Intrinsic-factor antibodies have limited sensitivity and parietal-cell antibodies are not completely specific.
How can biopsy address the suspected atrophy despite discordant antibody results?
The clinical pattern remains suggestive; biopsy can confirm and map atrophy despite discordant serology.
D. Use negative intrinsic-factor antibodies to redirect toward tumor testing (Why this does not fit)
A negative antibody result may prompt consideration of alternatives. Its low sensitivity does not rule out autoimmune atrophy in this low-acid, B12-deficient patient.
Reasoning steps for option D
What consideration might a negative intrinsic-factor antibody test raise during evaluation of high gastrin?
A negative antibody result may prompt consideration of alternatives.
Why should that negative result not redirect this low-acid, B12-deficient patient away from assessing autoimmune atrophy?
Its low sensitivity does not rule out autoimmune atrophy in this low-acid, B12-deficient patient.
Takeaway: Use histology to confirm and localize suspected atrophy
A. Corpus atrophy is the best explanation for the hormone result (Why this does not fit)
Corpus atrophy can raise gastrin through acid deficiency. No gastric histology establishes it, and potent PPI treatment already explains the sampled high pH.
Reasoning steps for option A
How could corpus atrophy cause elevated gastrin in a patient with low acid production?
Corpus atrophy can raise gastrin through acid deficiency.
Why is corpus atrophy not established as the cause of this patient’s gastrin of 560 pg/mL while taking a high-dose PPI?
No gastric histology establishes it, and potent PPI treatment already explains the sampled high pH.
B. Negative CT makes abrupt PPI withdrawal a low-risk diagnostic trial (Why this does not fit)
A negative study may reduce the probability of a visible mass. It does not establish that acid secretion will remain safe when treatment is stopped.
Reasoning steps for option B
What does a negative pancreatic CT indicate about a visible mass in this patient?
A negative study may reduce the probability of a visible mass.
Why does a negative CT not make abrupt PPI withdrawal a safe diagnostic trial in a patient with recurrent ulcers?
It does not establish that acid secretion will remain safe when treatment is stopped.
C. Functional diagnosis unresolved despite negative CT (Best answer)
Imaging evaluates visible lesions, whereas the functional diagnosis requires biochemical and acid context. The concerning phenotype and PPI-confounded result still require specialist assessment.
Reasoning steps for option C
Why does a negative CT not resolve the functional diagnosis in this PPI-treated patient?
Imaging evaluates visible lesions, whereas the functional diagnosis requires biochemical and acid context.
What further assessment is warranted by recurrent ulcers, watery diarrhea, and a PPI-confounded gastrin result?
The concerning phenotype and PPI-confounded result still require specialist assessment.
D. A small gastrinoma is unlikely enough to end investigation (Why this does not fit)
Negative CT lowers the chance of a visible mass. It does not reliably exclude a small duodenal or pancreatic lesion in this clinical setting.
Reasoning steps for option D
How does a negative CT affect the likelihood of a visible pancreatic mass?
Negative CT lowers the chance of a visible mass.
Why does negative CT not justify ending investigation for a small gastrinoma in this patient?
It does not reliably exclude a small duodenal or pancreatic lesion in this clinical setting.
Takeaway: Preserve supervised functional evaluation and acid control
A. A: threshold not met; B: a positive result that establishes ZES (Why this does not fit)
B's numerical increment exceeds 120 pg/mL. A also has a 190 pg/mL increment that meets the threshold, while B's low-acid state prevents an unqualified diagnostic conclusion.
Reasoning steps for option A
How does Patient B’s rise from 720 to 900 pg/mL compare with the specified secretin-test threshold?
B's numerical increment exceeds 120 pg/mL.
Why is it incorrect to say Patient A’s rise from 460 to 650 pg/mL misses the threshold while Patient B’s response establishes ZES?
A also has a 190 pg/mL increment that meets the threshold, while B's low-acid state prevents an unqualified diagnostic conclusion.
B. A: threshold not met; B: confounded response despite exceeding the threshold (Why this does not fit)
B's 180 pg/mL increase must be interpreted in its hypochlorhydric setting. A's 190 pg/mL increase does meet the supplied rule under the stated controlled acidic conditions.
Reasoning steps for option B
Why must Patient B’s 180 pg/mL secretin response be interpreted in light of pH 6.4 on a PPI?
The 180 pg/mL increment exceeds the 120 pg/mL threshold, but pH 6.4 indicates hypochlorhydria, which can cause false-positive secretin responses.
Does Patient A’s 190 pg/mL rise meet the supplied threshold under controlled acidic conditions?
A's 190 pg/mL increase does meet the supplied rule under the stated controlled acidic conditions.
C. A: supports ZES; B: a positive result that establishes ZES (Why this does not fit)
A's 190 pg/mL increment in an acidic controlled setting supports ZES. B also passes the numerical rule, but the low-acid context can generate a false positive.
Reasoning steps for option C
What does Patient A’s 190 pg/mL rise with pH 1.2 support?
A's 190 pg/mL increment in an acidic controlled setting supports ZES.
Why does Patient B’s numerically positive rise at pH 6.4 not establish ZES?
B also passes the numerical rule, but the low-acid context can generate a false positive.
D. A: supports ZES; B: confounded response despite exceeding the threshold (Best answer)
A's increment is 190 pg/mL, above the specified threshold in an acidic controlled setting. B's 180 pg/mL increment also passes numerically, but its PPI-associated hypochlorhydria limits diagnostic validity.
Reasoning steps for option D
Why does Patient A’s secretin response support ZES under the stated controlled conditions?
A's increment is 190 pg/mL, above the specified threshold in an acidic controlled setting.
How should Patient B’s 180 pg/mL rise be interpreted while taking a PPI with gastric pH 6.4?
B's 180 pg/mL increment also passes numerically, but its PPI-associated hypochlorhydria limits diagnostic validity.
Takeaway: Support ZES in A while retaining low-acid test confounding in B
A. Low-acid test confounding with uncertain lesion function (Best answer)
Hypochlorhydria can produce false-positive secretin responses. A lesion does not by itself prove gastrin secretion, so these findings need specialist reconciliation rather than automatic confirmation.
Reasoning steps for option A
How can gastric pH 6.4 during PPI therapy affect the interpretation of this patient's 180 pg/mL secretin-stimulated gastrin rise?
Hypochlorhydria can produce false-positive secretin responses.
Why does the pancreatic lesion not confirm ZES in this patient with low gastric acidity?
A lesion does not by itself prove gastrin secretion, so these findings need specialist reconciliation rather than automatic confirmation.
B. The stimulated increment is interpretable independently of pH (Why this does not fit)
A secretin increment is useful under validated conditions. Hypochlorhydria can produce false positives, so the stated pH cannot be ignored.
Reasoning steps for option B
What testing context would make a secretin increment informative rather than vulnerable to this patient's low-acid confounder?
The increment is informative under validated conditions with gastric acidity and medication effects accounted for; pH 6.4 during PPI use does not provide that unconfounded context.
Why must gastric pH 6.4 be considered before interpreting this patient's secretin result?
Hypochlorhydria can produce false positives, so the stated pH cannot be ignored.
C. The pancreatic lesion supplies the missing proof of hormone function (Why this does not fit)
A lesion can provide a target for localization and further investigation. Its presence does not establish gastrin secretion or repair a low-acid secretin-test limitation.
Reasoning steps for option C
What diagnostic role can the small pancreatic lesion play in this patient's ZES workup?
A lesion can provide a target for localization and further investigation.
Does the pancreatic lesion establish gastrin secretion or resolve the low-acid limitation of the secretin test?
Its presence does not establish gastrin secretion or repair a low-acid secretin-test limitation.
D. The gastrin rise is too small because it is less than 200 pg/mL (Why this does not fit)
Some historical secretin criteria used a 200 pg/mL increase. A lower commonly used criterion exists; the major supplied limitation is the markedly suppressed acid state.
Reasoning steps for option D
What historical secretin-test threshold might lead someone to discount a 180 pg/mL rise?
Some historical secretin criteria used a 200 pg/mL increase.
Why is the rise being below 200 pg/mL not the main limitation of this patient's ZES evaluation?
A lower commonly used criterion exists; the major supplied limitation is the markedly suppressed acid state.
Takeaway: Avoid treating localization as proof of hormone function
A. Feedback ECL stimulation is compatible; retain indicated gastroprotection (Best answer)
PPI-associated acid suppression can increase gastrin-driven ECL stimulation and chromogranin A without establishing a NET. Prior ulcer bleeding during ongoing antiplatelet exposure independently supports continued risk-based protection rather than withdrawal to normalize markers.
Reasoning steps for option A
How can PPI-related acid suppression explain gastrin 520 pg/mL, elevated chromogranin A, and linear ECL hyperplasia without a discrete tumor?
PPI-associated acid suppression can increase gastrin-driven ECL stimulation and chromogranin A without establishing a NET.
Why might gastroprotection remain indicated despite these marker findings in a patient with prior ulcer bleeding who still takes antiplatelet therapy?
Prior ulcer bleeding during ongoing antiplatelet exposure independently supports continued risk-based protection rather than withdrawal to normalize markers.
B. Feedback ECL stimulation fits; stop PPI to normalize markers (Why this does not fit)
The biochemical and linear-cell response fits non-neoplastic feedback stimulation. That interpretation does not erase the ongoing bleeding-prevention indication.
Reasoning steps for option B
What non-neoplastic mechanism fits this patient's elevated gastrin, chromogranin A, and linear ECL hyperplasia?
PPI-related low acidity permits feedback hypergastrinemia, which can stimulate ECL cells and raise chromogranin A without a discrete NET.
Why does that feedback mechanism not, by itself, justify stopping her PPI?
That interpretation does not erase the ongoing bleeding-prevention indication.
C. A gastric NET is established; retain gastroprotection (Why this does not fit)
Prior bleeding and ongoing antiplatelet therapy support protection. Elevated chromogranin A and linear ECL hyperplasia do not establish a discrete neuroendocrine tumor.
Reasoning steps for option C
Which features of this patient's history support continued protection against ulcer bleeding?
Prior bleeding and ongoing antiplatelet therapy support protection.
Why do elevated chromogranin A and linear ECL hyperplasia not establish a gastric NET?
Chromogranin A can rise with PPI-associated ECL stimulation, and linear hyperplasia describes a cellular proliferation rather than the discrete tumor absent from this biopsy.
D. A gastric NET is established; stop PPI to normalize markers (Why this does not fit)
Atrophic or neuroendocrine disease can require further assessment when evidence supports it. The described findings do not establish a NET, and marker normalization is not a sound reason to abandon needed bleeding prevention.
Reasoning steps for option D
What limits attributing these marker findings to a gastric NET or atrophic disease rather than PPI-associated feedback?
The biopsy describes linear ECL hyperplasia without a discrete tumor, not established atrophy or a NET. The markers are compatible with PPI-associated stimulation and do not establish either disease.
Why is stopping needed gastroprotection solely to normalize this patient's markers unsound?
The described findings do not establish a NET, and marker normalization is not a sound reason to abandon needed bleeding prevention.
Takeaway: Retain needed protection while interpreting the marker pattern in drug context
A. Normal acid output is likely because symptoms resolved (Why this does not fit)
Resolution suggests the symptom burden is no longer persistent. Symptoms cannot establish normal gastric output, which was never measured.
Reasoning steps for option A
What does resolution of burning over three weeks indicate about this patient's ongoing symptom burden?
Resolution suggests the symptom burden is no longer persistent.
Can symptom resolution after PPI withdrawal establish that gastric acid output is normal?
Symptoms cannot establish normal gastric output, which was never measured.
B. Recurrent erosive reflux is the preferred explanation (Why this does not fit)
Reflux may recur after stopping treatment. No endoscopic erosions are supplied, and a transient resolving course does not preferentially establish erosive disease.
Reasoning steps for option B
Can reflux symptoms recur after a long-term PPI is stopped?
Reflux may recur after stopping treatment.
Why does this patient's transient burning, without documented erosions, not preferentially establish recurrent erosive reflux?
No endoscopic erosions are supplied, and a transient resolving course does not preferentially establish erosive disease.
C. Transient withdrawal symptoms are plausible, not proven (Best answer)
The timing and resolution are compatible with rebound-related symptoms. The course supports reassessment without proving acid output or requiring an indefinite prescription.
Reasoning steps for option C
How does burning that begins in the second week after PPI withdrawal and then resolves fit with rebound-related symptoms?
The timing and resolution are compatible with rebound-related symptoms.
What does this resolving course support without proving a change in acid output or a need for indefinite PPI therapy?
The course supports reassessment without proving acid output or requiring an indefinite prescription.
D. Antacid response favors persistent reflux over withdrawal (Why this does not fit)
Both reflux and withdrawal-related acid symptoms may respond to antacids. The response does not distinguish these possibilities, while the transient course is compatible with withdrawal.
Reasoning steps for option D
Would relief with an occasional antacid distinguish recurrent reflux from withdrawal-related acid symptoms?
Both reflux and withdrawal-related acid symptoms may respond to antacids.
Which feature of this patient's course remains compatible with withdrawal despite relief from rescue medication?
The response does not distinguish these possibilities, while the transient course is compatible with withdrawal.
Takeaway: Avoid claiming direct acid measurement or confirmed chronic disease
A. Extend observation because rebound symptoms can last several weeks (Why this does not fit)
Withdrawal physiology can persist beyond a brief fixed interval. New ulceration, weight loss and ongoing diarrhea should not be dismissed as uncomplicated rebound.
Reasoning steps for option A
Can withdrawal-related acid physiology persist several weeks after stopping a PPI?
Withdrawal physiology can persist beyond a brief fixed interval.
Why should a new distal duodenal ulcer, weight loss, and persistent diarrhea not be attributed to uncomplicated rebound?
New distal ulceration is active acid injury, and weight loss with ongoing diarrhea is a concerning disease pattern. Together with gastrin 690 pg/mL at pH 1.6, these findings warrant investigation rather than observation as uncomplicated rebound.
B. Repeat gastrin after another untreated month before addressing the ulcer (Why this does not fit)
Repeat testing may help confirm a biochemical finding. Deferring treatment of active acid injury solely for another untreated sample is unsafe.
Reasoning steps for option B
What role could a repeat fasting gastrin measurement play after this patient's result of 690 pg/mL off therapy?
Repeat testing may help confirm a biochemical finding.
Why should treatment of the active distal duodenal ulcer not wait for another untreated month of testing?
Deferring treatment of active acid injury solely for another untreated sample is unsafe.
C. Control acid while investigating hypersecretion (Best answer)
The combination suggests persistent inappropriate gastrin secretion with acid complications. It needs assessment despite the prior withdrawal history, while protecting against further acid injury.
Reasoning steps for option C
What does gastrin 690 pg/mL with gastric pH 1.6, a distal duodenal ulcer, and diarrhea suggest?
The combination suggests persistent inappropriate gastrin secretion with acid complications.
Why should investigation of hypersecretion proceed alongside protection from further acid injury?
It needs assessment despite the prior withdrawal history, while protecting against further acid injury.
D. Treat the ulcer routinely and reserve further testing for recurrence (Why this does not fit)
Routine acid treatment is appropriate for many ulcers. The current unusual ulcer site, diarrhea, weight loss and inappropriate gastrin already justify investigation rather than waiting for another recurrence.
Reasoning steps for option D
Why does acid treatment make sense for the new distal duodenal ulcer even though routine treatment alone is insufficient?
Acid treatment protects against further injury from the active ulcer, but the unusual site, diarrhea, weight loss and acidic hypergastrinemia also require investigation.
Why do this patient's ulcer location, diarrhea, weight loss, and gastrin result warrant investigation now rather than after another recurrence?
The current unusual ulcer site, diarrhea, weight loss and inappropriate gastrin already justify investigation rather than waiting for another recurrence.
Takeaway: Protect acid control during further evaluation
A. A: retain gastroprotection; B: consider a deprescribing trial (Best answer)
Prior bleeding with continued antiplatelet exposure sustains a preventive indication in A. B has an ended indication and low stated risk; equal gastrin results do not require equal prescription decisions.
Reasoning steps for option A
Why does Patient A's prior ulcer bleed during continued antiplatelet exposure support retaining gastroprotection?
Prior bleeding with continued antiplatelet exposure sustains a preventive indication in A.
Why can Patient B, whose H. pylori-associated ulcer has healed after eradication, be considered for deprescribing despite a gastrin level similar to A's?
B has an ended indication and low stated risk; equal gastrin results do not require equal prescription decisions.
B. A: consider discontinuation; B: retain maintenance treatment (Why this does not fit)
Being asymptomatic might seem to favor withdrawal in A, while an ulcer history may encourage continued treatment in B. This reverses the ongoing-risk distinction: A retains bleeding risk and B has a resolved cause.
Reasoning steps for option B
Why might A's lack of symptoms and B's ulcer history superficially suggest stopping A's PPI but maintaining B's?
Being asymptomatic might seem to favor withdrawal in A, while an ulcer history may encourage continued treatment in B.
What ongoing-risk difference makes that proposed allocation inappropriate?
This reverses the ongoing-risk distinction: A retains bleeding risk and B has a resolved cause.
C. A: retain gastroprotection; B: retain treatment for hypergastrinemia (Why this does not fit)
A has a strong preventive indication. The incidental hormone result does not itself supply a maintenance indication for B.
Reasoning steps for option C
What history supplies Patient A with a continuing preventive indication for a PPI?
A's prior ulcer bleed and continuing need for antiplatelet therapy create an ongoing bleeding-prevention indication, even while A is asymptomatic.
Does Patient B's gastrin near 400 pg/mL during PPI therapy itself justify maintenance treatment after ulcer healing and H. pylori eradication?
The incidental hormone result does not itself supply a maintenance indication for B.
D. A: consider discontinuation; B: consider a deprescribing trial (Why this does not fit)
B is a reasonable candidate for a monitored trial. Applying the same decision to A overlooks prior bleeding during continued antiplatelet exposure.
Reasoning steps for option D
Why is a monitored PPI deprescribing trial reasonable for Patient B?
B's H. pylori has been eradicated and the ulcer has healed, with no NSAID, antithrombotic exposure or other maintenance indication, making a monitored trial reasonable.
What bleeding-risk factor does a proposal to discontinue both patients' PPIs overlook in Patient A?
Applying the same decision to A overlooks prior bleeding during continued antiplatelet exposure.
Takeaway: Let indications rather than identical laboratory values determine the paired decisions
A. Eradicate H. pylori; confirm with nonserologic testing (Best answer)
Documented H. pylori in atrophic gastritis warrants treatment. A nonserologic confirmation assesses eradication even when autoimmune disease may coexist.
Reasoning steps for option A
In this patient with corpus-predominant atrophy and H. pylori on histology, what warrants eradication despite possible autoimmune gastritis?
Documented H. pylori in atrophic gastritis warrants treatment.
After treating the biopsy-proven H. pylori, what does nonserologic testing assess?
A nonserologic confirmation assesses eradication even when autoimmune disease may coexist.
B. Eradicate H. pylori; confirm with repeat antibody testing (Why this does not fit)
Treating the identified infection is appropriate. Antibodies can persist and are not the appropriate eradication-confirmation method.
Reasoning steps for option B
Is treatment appropriate when H. pylori is identified alongside possible autoimmune gastritis?
Treating the identified infection is appropriate.
Why is repeat antibody testing unsuitable for confirming eradication in this patient?
Antibodies can persist and are not the appropriate eradication-confirmation method.
C. Observe the infection; repeat biopsy after B12 replacement (Why this does not fit)
B12 replacement is important if deficiency is present. It does not treat the documented infection or justify deferring its eradication.
Reasoning steps for option C
If this patient also has B12 deficiency, what role does replacement have?
B12 replacement is important if deficiency is present.
Why would B12 replacement not justify postponing treatment of the H. pylori found on histology?
It does not treat the documented infection or justify deferring its eradication.
D. Observe the infection; follow gastrin for spontaneous normalization (Why this does not fit)
Gastrin can reflect the acid state. It is not a reliable endpoint for untreated infection, and established atrophy may persist despite changes in infection status.
Reasoning steps for option D
What can the elevated fasting gastrin indicate when this patient's gastric pH is 6.7?
At pH 6.7 with corpus atrophy, elevated gastrin can reflect compensation for low acid production rather than serve as a measure of whether H. pylori has cleared.
Why is following gastrin for spontaneous normalization inadequate management of the documented H. pylori infection?
It is not a reliable endpoint for untreated infection, and established atrophy may persist despite changes in infection status.
Takeaway: Apply infection treatment and nonserologic confirmation in atrophic gastritis
A. The ulcer pattern resolves confounding and confirms a tumor (Why this does not fit)
Recurrent ulcers and diarrhea strengthen concern for ZES. They do not make a drug- and renal-confounded hormone value definitive tumor evidence.
Reasoning steps for option A
How do recurrent ulcers and diarrhea affect concern for ZES in this patient?
Recurrent ulcers and diarrhea strengthen concern for ZES.
Why does the ulcer-diarrhea pattern not make a gastrin of 590 pg/mL definitive tumor evidence while the patient takes high-dose PPI and has renal dysfunction?
They do not make a drug- and renal-confounded hormone value definitive tumor evidence.
B. The treated pH lowers concern enough to stop evaluation (Why this does not fit)
A high pH shows low gastric acidity at sampling, compatible with PPI effect. It does not establish sustained acid control, reconstruct untreated secretion, or explain away persistent concerning symptoms.
Reasoning steps for option B
What does gastric pH 6.0 indicate about acidity at the time of sampling on high-dose PPI?
A high pH shows low gastric acidity at sampling, compatible with PPI effect.
Why does that single treated pH measurement not justify ending evaluation of the recurrent ulcers and diarrhea?
It does not establish sustained acid control, reconstruct untreated secretion, or explain away persistent concerning symptoms.
C. Both confounders matter; investigate the ulcer phenotype (Best answer)
PPI suppression and renal dysfunction both affect interpretation of gastrin. Neither explains away the recurrent ulcer-diarrhea history, so specialist evaluation remains appropriate.
Reasoning steps for option C
Which two factors complicate interpretation of gastrin 590 pg/mL in this patient?
PPI suppression and renal dysfunction both affect interpretation of gastrin.
Why should the recurrent ulcer-diarrhea history still prompt specialist evaluation despite those confounders?
Neither explains away the recurrent ulcer-diarrhea history, so specialist evaluation remains appropriate.
D. Renal disease accounts for gastrin; defer gastric evaluation (Why this does not fit)
Renal dysfunction can contribute to hypergastrinemia. It does not resolve the recurrent ulcer-diarrhea phenotype or exclude a coexisting secretory disorder.
Reasoning steps for option D
How can a creatinine of 2.4 mg/dL affect interpretation of this patient's gastrin?
Renal dysfunction can contribute to hypergastrinemia.
Why does renal dysfunction alone not justify deferring evaluation of the recurrent ulcer-diarrhea phenotype?
It does not resolve the recurrent ulcer-diarrhea phenotype or exclude a coexisting secretory disorder.
Takeaway: Retain clinical suspicion and supervised evaluation
A. Retained antral tissue sustaining inappropriate gastrin secretion (Best answer)
Retained-antrum syndrome is a rare postoperative cause of inappropriate hypergastrinemia. The prior gastric operation makes it an alternative to investigate, not a diagnosis established by the history alone.
Reasoning steps for option A
What rare cause of inappropriate hypergastrinemia should be considered when records do not establish whether all antral tissue was removed?
Retained-antrum syndrome is a rare postoperative cause of inappropriate hypergastrinemia.
How strongly does the prior partial gastrectomy establish retained-antrum syndrome in this patient?
The prior gastric operation makes it an alternative to investigate, not a diagnosis established by the history alone.
B. PPI-related hypochlorhydria persisting during the test (Why this does not fit)
Antisecretory exposure can confound gastrin measurements. Testing is described off suppressants and the pH does not show hypochlorhydria.
Reasoning steps for option B
How could PPI exposure produce hypergastrinemia if it were responsible for this postoperative patient's result?
PPI-associated acid suppression can reduce acid feedback and raise gastrin, but that mechanism would require a compatible medication and acid context.
Why do testing off suppressants and a gastric pH of 1.5 argue against PPI-related hypochlorhydria here?
Testing is described off suppressants and the pH does not show hypochlorhydria.
C. Recurrent ordinary marginal ulcer disease after surgery (Why this does not fit)
Marginal ulcers can recur after gastric surgery for several reasons. That description alone does not account for the persistent fasting hypergastrinemia with acidity; retained-antrum physiology is a targeted alternative to investigate.
Reasoning steps for option C
Can marginal ulcers recur after a partial gastrectomy and gastrojejunostomy?
Marginal ulcers can recur after gastric surgery for several reasons.
Why does labeling these lesions ordinary marginal ulcers leave the fasting gastrin of 530 pg/mL with gastric acidity unexplained?
That description alone does not account for the persistent fasting hypergastrinemia with acidity; retained-antrum physiology is a targeted alternative to investigate.
D. Complete loss of oxyntic tissue with compensatory gastrin (Why this does not fit)
Extensive parietal-cell loss can increase gastrin through acid deficiency. The sampled stomach remains strongly acidic, making this a poor explanation for the paired result.
Reasoning steps for option D
How could extensive loss of oxyntic parietal cells raise gastrin?
Extensive parietal-cell loss can increase gastrin through acid deficiency.
Why does gastric pH 1.5 make extensive acid-producing gland loss a poor explanation for this patient's paired results?
The sampled stomach remains strongly acidic, making this a poor explanation for the paired result.
Takeaway: Use surgical anatomy to identify a rare competing source
A. Select abrupt discontinuation for its established superiority in preventing symptoms (Why this does not fit)
Abrupt discontinuation is an acceptable option in selected patients. Evidence does not establish a superior ability to prevent rebound symptoms.
Reasoning steps for option A
Is abrupt discontinuation a possible method for this patient who has no continuing PPI indication?
Abrupt discontinuation is an acceptable option in selected patients.
Does evidence establish that abrupt discontinuation prevents rebound symptoms better than tapering?
Evidence does not establish a superior ability to prevent rebound symptoms.
B. Select tapering to establish whether recurrent symptoms represent GERD (Why this does not fit)
Tapering can be chosen for symptom management or preference. Symptoms during tapering still cannot reliably distinguish rebound from recurrent reflux.
Reasoning steps for option B
Why might this patient choose a taper while concerned about symptom recurrence?
Tapering can be chosen for symptom management or preference.
Can symptoms arising during a taper reliably distinguish rebound acid symptoms from recurrent GERD?
Symptoms during tapering still cannot reliably distinguish rebound from recurrent reflux.
C. Select either approach with rescue and reassessment (Best answer)
AGA advice allows either approach for a suitable candidate. Patient preference can inform the method; neither guarantees symptom prevention.
Reasoning steps for option C
Which discontinuation methods are allowed for a suitable patient after PPI indication and bleeding risk have been reviewed?
AGA advice permits either tapering or abrupt discontinuation in a suitable candidate after review of the ongoing indication and bleeding risk.
How should this patient's preference for fewer tablets factor into the choice, given that neither method guarantees symptom prevention?
Patient preference can inform the method; neither guarantees symptom prevention.
D. Continue the current PPI until gastrin reaches the reference range (Why this does not fit)
A normal hormone result might appear reassuring before withdrawal. Continued acid suppression can sustain feedback hypergastrinemia, and a normal gastrin target is not a deprescribing requirement.
Reasoning steps for option D
Would a reference-range gastrin establish that this patient's PPI should be continued or discontinued?
No. A reference-range result describes the hormone concentration, but the prescribing decision rests on the reviewed indication and bleeding risk, not a gastrin-normalization target.
Why is waiting for gastrin to normalize while continuing the PPI not a deprescribing requirement?
Continued acid suppression can sustain feedback hypergastrinemia, and a normal gastrin target is not a deprescribing requirement.
Takeaway: Choose a supported discontinuation approach without promising prevention of symptoms
A. A: acid production can recover; B: gland loss continues to limit acid (Best answer)
Drug inhibition can end while A retains the cells needed to produce acid. B12 replacement treats a deficiency but does not restore lost parietal glands, so the same initial laboratory pairing predicts different responses.
Reasoning steps for option A
Why could Patient A's acid production recover after supervised PPI withdrawal when biopsies show preserved oxyntic glands?
Drug inhibition can end while A retains the cells needed to produce acid.
Why is Patient B's acid production likely to remain limited after B12 replacement despite a similar initial gastrin and pH?
B12 replacement treats a deficiency but does not restore lost parietal glands, so the same initial laboratory pairing predicts different responses.
B. A: persistent gland failure; B: acid recovery with B12 replacement (Why this does not fit)
Severe gland loss can produce persistent acid failure. A has preserved glands, while B rather than A has the anatomical loss that B12 replacement does not reverse.
Reasoning steps for option B
Which patient's biopsy findings could support persistent gland-related acid failure rather than reversible drug inhibition?
B's advanced autoimmune corpus atrophy supports persistent acid failure from gland loss; A's preserved oxyntic glands do not support that proposed failure.
Why do the preserved glands in A and advanced corpus atrophy in B argue against assigning persistent gland failure to A and B12-driven acid recovery to B?
A has preserved glands, while B rather than A has the anatomical loss that B12 replacement does not reverse.
C. A: acid recovery; B: acid recovery once the vitamin is replaced (Why this does not fit)
A can recover secretion as drug effect wanes. Correcting B12 deficiency does not reconstruct B's oxyntic mucosa.
Reasoning steps for option C
What acid response is plausible for Patient A as the PPI effect wanes?
A can recover secretion as drug effect wanes.
Why is acid recovery not similarly expected in Patient B after B12 replacement?
Correcting B12 deficiency does not reconstruct B's oxyntic mucosa.
D. A: acid output remains blocked by high gastrin; B: persistent gland failure (Why this does not fit)
B's established tissue loss limits the response. High gastrin is a stimulatory signal, not the blocker that prevents A's pumps from recovering.
Reasoning steps for option D
Which patient's established tissue loss limits acid production after the proposed interventions?
B's established tissue loss limits the response.
Does Patient A's high gastrin itself block recovery of acid secretion after PPI withdrawal?
High gastrin is a stimulatory signal, not the blocker that prevents A's pumps from recovering.
Takeaway: Predict recovery after withdrawal but not restoration of glands from B12 replacement