Distinguish intracranial bleeding by compartment, connect CT patterns to pressure and CSF flow, and choose urgent investigations and treatment.
A head CT shows blood. Before naming the bleed, ask where the blood sits, what vessel could put it there, and what danger follows. A lens at the skull, a crescent along the brain, blood in the fluid-filled fissures, and blood within brain tissue call for different next decisions. The patterns are useful, but a changing examination is never less important than a memorable silhouette.
1. Which space is filling?
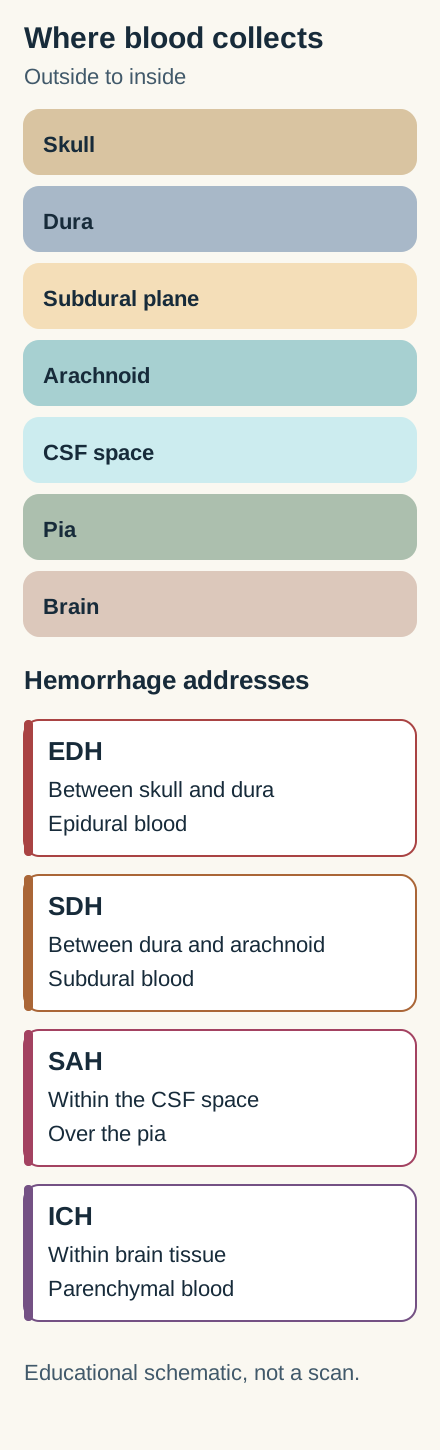
It is tempting to call every collection outside the brain “subdural.” Trace the layers instead: skull, dura, arachnoid, cerebrospinal fluid (CSF) space, pia, then brain. An epidural hematoma separates skull from dura; a subdural hematoma collects between dura and arachnoid; subarachnoid blood enters the CSF-filled space beneath arachnoid. Intracerebral hemorrhage lies within parenchyma. These are locations, not interchangeable descriptions of severity. [6]
Original compartment model: follow the labeled layers from bone inward; the address boxes distinguish four possible sites of blood.
Try the boundary test: point to the dura in the diagram, then decide whether blood above or below it would be restrained by its attachments to cranial sutures. Above the dura, separation from bone commonly stops at sutures and produces a biconvex lens. Beneath it, blood can spread across sutures around the convexity, creating a crescent, although the falx and tentorium limit its extent. Blood in the subarachnoid space instead outlines sulci, fissures and basal cisterns. These shapes are consequences of anatomy, not proofs of a particular vessel or timing. [6]
Transfer: if bright material follows the Sylvian fissure rather than pressing in from the inner table, look for a source of subarachnoid hemorrhage even if the patient also fell. Trauma and aneurysm are both possible contexts; the history and vascular evaluation decide what comes next.
2. Why can a patient talk and then suddenly deteriorate?
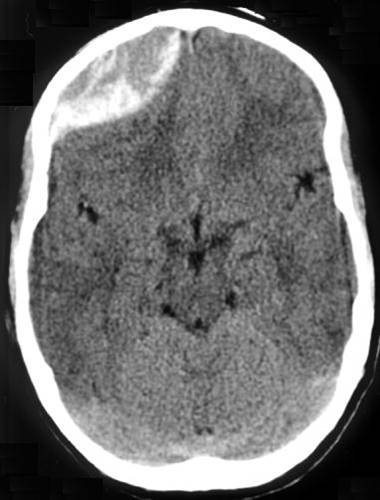
A lucid interval is a warning pattern, not a required diagnostic criterion. Imagine a boxer struck over the temple who briefly loses consciousness, speaks coherently, then becomes drowsy with a dilating pupil. At the thin pterion junction, the frontal, parietal, temporal and sphenoid bones meet over a groove carrying the middle meningeal artery (MMA). The MMA arises from the maxillary artery, a branch of the external carotid artery. A fracture can tear it; arterial bleeding may quickly strip dura from bone. [13][3]
Real acute epidural CT: the lens-shaped collection favors the skull-facing side of the dura. Image: Jpogi, CC BY-SA 3.0; Source and license information.
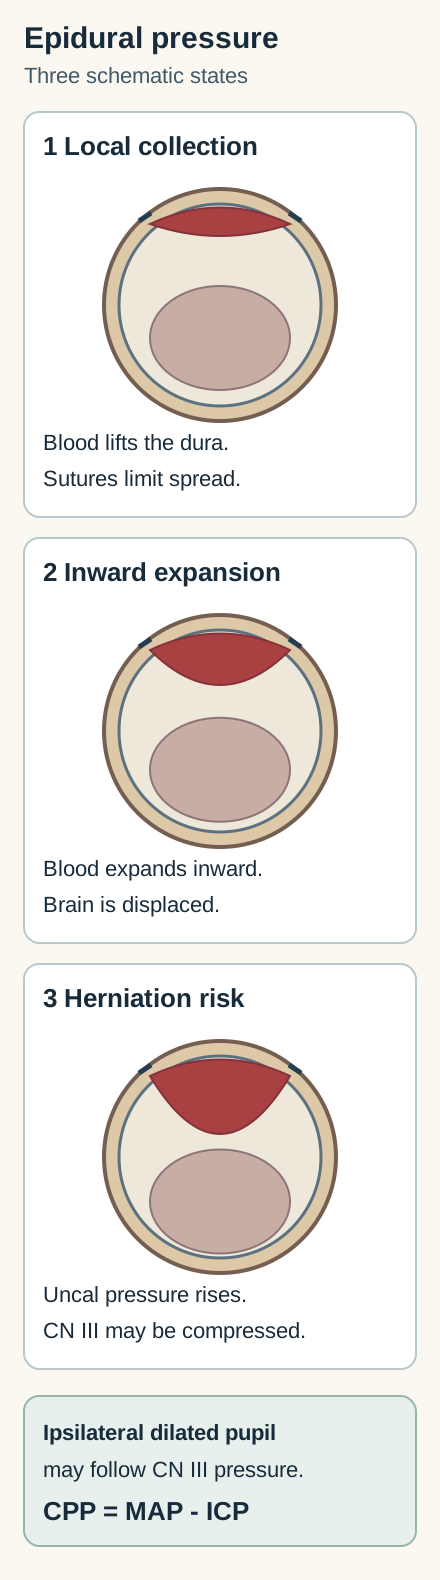
Predict before revealing: which of three expansion states has lower cerebral perfusion pressure (CPP) and greater risk of a newly enlarged, poorly reactive pupil? Open the comparison to see the labeled states, then close it and try predicting again. Compare the pressure states to predict perfusion and pupil changes.
Compare expansion states and reveal the predicted effectsCompare the three labeled states: reserve is exhausted before pressure rises steeply.
As blood expands, compensatory reserve is consumed. Intracranial pressure (ICP) then rises and CPP falls because CPP is approximately mean arterial pressure minus ICP. Uncal displacement can compress ipsilateral CN III; its superficial parasympathetic pupillary fibers are vulnerable to external pressure. A poorly reactive dilated pupil may accompany ptosis and a down-and-out eye, but pupil findings vary and a normal pupil does not rule out danger. [3][6]
The answer remains visible: expansion initially consumes reserve, then raises ICP, lowers CPP at the same arterial pressure (CPP is approximately MAP minus ICP), and may produce ipsilateral pupillary dilation from uncal herniation. A lucid period can reflect temporary clinical improvement before deterioration; it neither proves ongoing expansion nor excludes subsequent expansion. A rapidly worsening patient needs immediate resuscitation and neurosurgical consultation.
An epidural hematoma over 30 cm³ warrants evacuation regardless of Glasgow Coma Scale; observation requires volume below 30 cm³, thickness below 15 mm, shift below 5 mm, GCS above 8 and no focal deficit, with serial CT and close neurological observation in a neurosurgical center. Do not delay escalation to prove the classic story. [3][6]
Transfer: an obtunded patient with a lens-shaped CT collection but no witnessed lucid interval still has a potential epidural emergency. Conversely, a lucid interval alone does not identify a vessel. Put the trajectory, CT and examination together.
Try it here · Checkpoint 1 of 3
Make your prediction before reading the choices. A first attempt is just a starting point.
Case 1
Show answer and explanations for case 1
A. Close observation because volume is below 30 mL (Why this does not fit)
The observation criteria must all be met; volume alone is insufficient when thickness, shift and the examination are unfavorable.
Reasoning steps for option A
Does 24 mL alone permit observation?
No. EDH observation also requires favorable thickness, shift and examination.
What do the 17-mm thickness, 6-mm shift and worsening pupil imply?
The patient fails observation criteria and has evolving mass effect requiring urgent evacuation.
Does this option account for the supplied conditions?
The observation criteria must all be met; volume alone is insufficient when thickness, shift and the examination are unfavorable.
B. Ventricular drainage as the initial definitive treatment (Why this does not fit)
An EVD may treat hydrocephalus, but the immediate lesion is an expanding extra-axial mass, not isolated ventricular obstruction.
Reasoning steps for option B
Does 24 mL alone permit observation?
No. EDH observation also requires favorable thickness, shift and examination.
What do the 17-mm thickness, 6-mm shift and worsening pupil imply?
The patient fails observation criteria and has evolving mass effect requiring urgent evacuation.
Does this option account for the supplied conditions?
An EVD may treat hydrocephalus, but the immediate lesion is an expanding extra-axial mass, not isolated ventricular obstruction.
C. Delayed burr-hole drainage after liquefaction (Why this does not fit)
Delayed drainage can be appropriate for selected chronic subdural collections, not a deteriorating patient with acute EDH.
Reasoning steps for option C
Does 24 mL alone permit observation?
No. EDH observation also requires favorable thickness, shift and examination.
What do the 17-mm thickness, 6-mm shift and worsening pupil imply?
The patient fails observation criteria and has evolving mass effect requiring urgent evacuation.
Does this option account for the supplied conditions?
Delayed drainage can be appropriate for selected chronic subdural collections, not a deteriorating patient with acute EDH.
D. Urgent neurosurgical evacuation (Best answer)
The scan identifies EDH, but volume below 30 mL does not make observation safe. Thickness, shift and deterioration fail nonoperative criteria and herniation signs demand urgent evacuation.
Reasoning steps for option D
Does 24 mL alone permit observation?
No. EDH observation also requires favorable thickness, shift and examination.
What do the 17-mm thickness, 6-mm shift and worsening pupil imply?
The patient fails observation criteria and has evolving mass effect requiring urgent evacuation.
Does this option account for the supplied conditions?
The scan identifies EDH, but volume below 30 mL does not make observation safe. Thickness, shift and deterioration fail nonoperative criteria and herniation signs demand urgent evacuation.
Takeaway: Apply the entire observation rule and the clinical trajectory, not one favorable volume measurement.
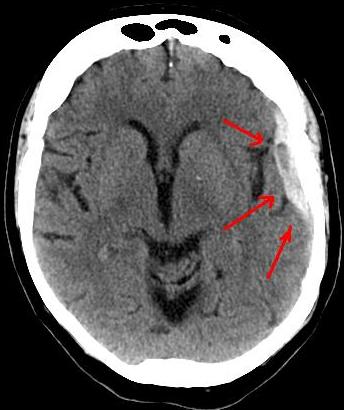
A daughter reports that her older father has become slower, unsteady and confused after a fall he hardly remembers. Bridging veins run from the cortical surface to dural venous sinuses, especially the superior sagittal sinus. Brain atrophy lengthens and tensions their course, so relatively modest acceleration or deceleration can tear them. Older adults, people with alcohol-related atrophy or repeated falls, and patients taking antithrombotic drugs merit particular attention; a subdural can also be acute and rapidly dangerous. [5][6]
Real subdural CT: follow the collection around the convexity rather than across the brain tissue. This image alone cannot date the bleed. Image: Lucien Monfils; Commons crop by Doc James; CC BY-SA 3.0, no local edits. Source and license information.
Pause and trace: does the broad collection follow the inner skull across a suture, or form a compact lens bounded at it? A crescent can cross sutures because it sits deep to the dura's skull attachments. The visible consequence can be compression, sulcal effacement and midline shift even when the history sounds trivial. Order urgent noncontrast head CT for concerning new neurological symptoms and involve neurosurgery.
In acute subdural hematoma, thickness over 10 mm or midline shift over 5 mm generally warrants evacuation regardless of Glasgow Coma Scale; deterioration or pupil abnormality can demand surgery even below these measurements. [3][5]
What does CT brightness tell you?
Fresh clotted blood is often hyperdense; as a subdural evolves it can appear closer to brain density and later become hypodense. An isodense collection may be detected by asymmetrical sulci, displaced cortex or mass effect. Mixed densities can reflect blood products of different ages or rebleeding; anemia can make acute blood less conspicuous. Do not use a single attenuation value to assign an exact day, or dismiss a symptomatic person because the crescent is dark. Clinical history, serial imaging when indicated and specialist judgment matter. [5][6]
Transfer and safeguard: an infant with a subdural hematoma, especially with retinal hemorrhages or other injuries, requires a careful, multidisciplinary evaluation for possible abusive head trauma and other causes. Neither a CT pattern nor a retinal finding alone proves a mechanism; protect the child while following local safeguarding procedures. [9]
4. What if the worst headache arrives in seconds?
“Thunderclap” describes an abrupt peak in pain, not a diagnosis. A person abruptly develops a maximal headache with vomiting, photophobia and a stiff neck. Saccular aneurysms often arise at arterial branch points. Blood released by rupture may fill basal cisterns and fissures instead of forming a lens or crescent. Syncope, seizure or a preceding sudden warning headache can occur. Smoking, hypertension, cocaine exposure, vascular Ehlers-Danlos syndrome and family history affect suspicion. Aneurysmal subarachnoid hemorrhage (SAH) remains urgent even when the neurological examination initially seems reassuring. [1]
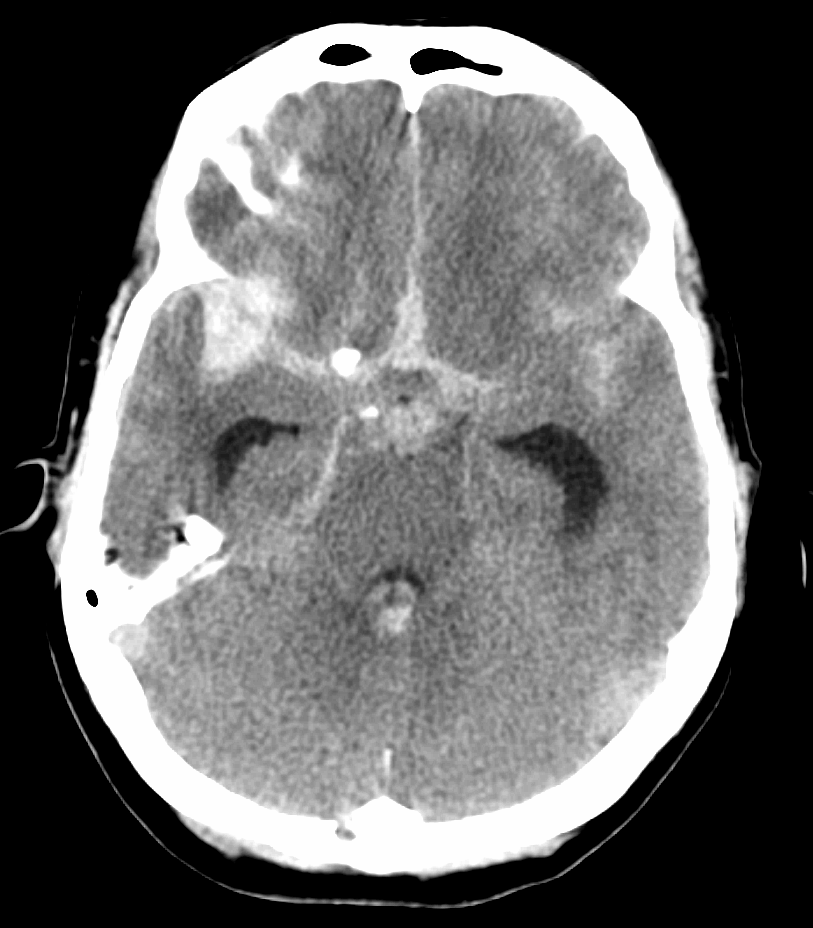
Real SAH CT: blood tracks through fluid spaces rather than making a smooth extra-axial crescent. Image: James Heilman, MD, CC BY-SA 3.0; Source and license information.
Choose the first investigation: a sudden maximal headache calls for emergent noncontrast head CT. Compare the scan above with the subdural image: following blood into cisterns redirects the search toward an aneurysm and vascular imaging. If CT is negative, interpret its timing and quality. A high-quality CT obtained within six hours of onset in a neurologically intact patient, interpreted by a board-certified neuroradiologist, has particularly high sensitivity in the appropriate setting; do not turn this into universal early-CT exclusion.
If suspicion remains, particularly after six hours or with a neurological deficit, assess LP safety and perform it for CSF evaluation when safe. CTA helps identify a culprit aneurysm after hemorrhage is established but an incidental aneurysm does not prove a CT-negative headache was SAH. [1][4]
Why sample CSF?
RBC breakdown generates bilirubin, giving CSF a yellow appearance called xanthochromia. After checking for contraindications such as mass effect or significant coagulopathy, LP in a CT-negative patient with continuing concern assesses RBCs and bilirubin; NICE advises waiting at least 12 hours from symptom onset before collecting CSF for bilirubin analysis. Interpretation depends on timing and laboratory method: a traumatic tap may add RBCs, and ex-vivo hemolysis can produce oxyhemoglobin after collection, whereas bilirubin suggests blood breakdown in vivo when assessed correctly. Clearing between tubes alone cannot reliably rule out SAH. A positive result prompts vascular evaluation. [4][8][10]
Apply anatomy: a posterior communicating artery (PCOM) aneurysm can externally compress adjacent CN III; superficial parasympathetic fibers make a dilated pupil concerning alongside ptosis and a down-and-out eye, but the pupil rule is not absolute. The anterior communicating artery (ACOM) is a common aneurysm site. Rarely, a large lesion impinges on crossing fibers at the optic chiasm and causes bitemporal field loss, not the usual presenting pattern.
Autosomal dominant polycystic kidney disease (ADPKD) raises intracranial aneurysm risk; screen patients with personal SAH or family aneurysm, SAH or unexplained sudden death when they have reasonable life expectancy and are eligible for treatment. Discuss other screening situations through shared decision-making. Noncontrast time-of-flight MRA is preferred for screening; an acute thunderclap needs urgent assessment instead. [7][11][15]
Transfer: sudden severe headache with a negative scan obtained late is not “migraine by subtraction.” Revisit onset, scan quality, examination and alternative diagnoses; complete an appropriate SAH evaluation before discharge.
Try it here · Checkpoint 2 of 3
Make your prediction before reading the choices. A first attempt is just a starting point.
Case 7
Show answer and explanations for case 7
A. End SAH evaluation because the red-cell count decreased (Why this does not fit)
Traumatic sampling and SAH can coexist; clearing alone cannot override the bilirubin and onset pattern.
Reasoning steps for option A
Does a falling red-cell count exclude prior SAH?
No. Procedural blood and SAH may coexist.
Why does the bilirubin result matter here?
The timing permits in vivo breakdown and normal serum bilirubin and CSF protein reduce alternative explanations.
Does this option account for the supplied conditions?
Traumatic sampling and SAH can coexist; clearing alone cannot override the bilirubin and onset pattern.
B. Urgent vascular imaging for a possible bleeding source (Best answer)
Bilirubin in this clinical context supports prior CSF bleeding despite partial clearing; vascular evaluation is needed for a possible aneurysmal source.
Reasoning steps for option B
Does a falling red-cell count exclude prior SAH?
No. Procedural blood and SAH may coexist.
Why does the bilirubin result matter here?
The timing permits in vivo breakdown and normal serum bilirubin and CSF protein reduce alternative explanations.
Does this option account for the supplied conditions?
Bilirubin in this clinical context supports prior CSF bleeding despite partial clearing; vascular evaluation is needed for a possible aneurysmal source.
C. Repeat noncontrast CT alone to exclude an aneurysm (Why this does not fit)
Noncontrast CT can show blood but is not a sufficient test for aneurysm anatomy.
Reasoning steps for option C
Does a falling red-cell count exclude prior SAH?
No. Procedural blood and SAH may coexist.
Why does the bilirubin result matter here?
The timing permits in vivo breakdown and normal serum bilirubin and CSF protein reduce alternative explanations.
Does this option account for the supplied conditions?
Noncontrast CT can show blood but is not a sufficient test for aneurysm anatomy.
D. Repeat LP solely to demonstrate further tube clearing (Why this does not fit)
Further clearing would still not reliably distinguish the possibilities and delays source investigation.
Reasoning steps for option D
Does a falling red-cell count exclude prior SAH?
No. Procedural blood and SAH may coexist.
Why does the bilirubin result matter here?
The timing permits in vivo breakdown and normal serum bilirubin and CSF protein reduce alternative explanations.
Does this option account for the supplied conditions?
Further clearing would still not reliably distinguish the possibilities and delays source investigation.
Takeaway: Interpret the laboratory method, alternative bilirubin sources and symptom timing together.
5. After an aneurysm ruptures, what must happen next?
Finding blood is not the end of treatment. Picture an aneurysm leaking into the cisterns, with blood extending into the ventricles. Ventricular CSF communicates with subarachnoid CSF, so intraventricular hemorrhage (IVH) can place RBCs in circulating CSF. Blood may obstruct outflow acutely or impair arachnoid-granulation resorption, sometimes causing communicating hydrocephalus over ensuing weeks. Worsening consciousness can signal acute hydrocephalus; reassess urgently for imaging and possible external ventricular drainage. [1]
Original CSF-flow model: follow the arrows from ventricles through subarachnoid spaces to granulations; imagine obstructed flow or resorption.
Trace and predict: follow CSF from the ventricles into subarachnoid spaces and onward to absorption at arachnoid granulations. If blood blocks outflow or later impairs absorption, ventricular spaces enlarge: hydrocephalus is a mechanical explanation for decline, not simply “more headache.” If consciousness changes, seek urgent reassessment rather than waiting for a scheduled scan. [1]
A second priority is preventing rebleeding. An aneurysm is secured by endovascular coiling or surgical clipping, with modality chosen by the treating cerebrovascular team and anatomy. Arrange treatment as early as feasible, preferably within 24 hours of onset when appropriate. Give enteral nimodipine in aneurysmal SAH to improve functional outcomes and reduce delayed cerebral ischemia (DCI); it does not secure the aneurysm or cure angiographic vasospasm. Monitor for hypotension and follow the treating team's protocol. [1]
Transfer: between days 4 and 14 after successful coiling, a patient develops new aphasia. Securing the aneurysm lowers rebleeding risk but does not eliminate DCI. Prompt examination, evaluation for other causes and specialist-directed perfusion management are necessary; angiographic narrowing and clinical ischemia are related but not identical. [1]
Yellow fluid does not always mean a ruptured aneurysm
SAH and IVH can both yield CSF RBCs and, after hemoglobin breakdown, bilirubin-associated xanthochromia. HSV encephalitis can cause hemorrhagic temporal-lobe injury and CSF RBCs, but RBCs alone do not identify HSV or establish xanthochromia; fever, encephalopathy, seizures, temporal imaging and viral testing help distinguish it. Very high CSF protein and systemic bilirubin, particularly in newborns, may also color CSF. Think about traumatic sampling and specimen handling before attributing every yellow sample to intracranial hemorrhage. [8][14]
6. What changes when blood is inside the brain?
A patient with long-standing hypertension abruptly develops weakness, and CT shows a hematoma centered in the putamen. This is intracerebral hemorrhage (ICH), not a fourth extra-axial shape. Chronic hypertension damages penetrating arteries, producing lipohyalinotic change and sometimes tiny Charcot-Bouchard aneurysms. Lenticulostriate vessels supply the putamen and nearby internal capsule, so a deep bleed can abruptly impair contralateral movement.
Thalamic hemorrhage, involving posterior cerebral artery perforator territory, often causes contralateral sensory loss; vertical gaze or pupil findings vary with extension. Pontine hemorrhage can cause coma, pinpoint but reactive pupils, quadriparesis and abnormal respiration. Cerebellar bleeding may begin with vertigo and ataxia before brainstem compression. These are localization patterns, not substitutes for CT. [2][16]
In an older patient with recurrent lobar hemorrhages, consider cerebral amyloid angiopathy (CAA), with amyloid in cortical and leptomeningeal vessel walls; lobar microbleeds and cortical superficial siderosis on susceptibility-sensitive MRI support the pattern. In a younger patient with lobar bleeding, investigate possibilities such as arteriovenous malformation, cavernous malformation or cerebral venous thrombosis. Neither location alone proves etiology, and anticoagulant exposure or another vascular lesion may coexist. [2][5]
Compare the two scans mentally: a deep putaminal focus displaces brain from within, whereas the epidural lens presses inward from under the skull. That location changes investigation and reversals. Obtain urgent CT, monitor airway and neurological status, and review anticoagulant use immediately. For warfarin-associated ICH, rapidly give four-factor prothrombin complex concentrate (4F-PCC) plus intravenous vitamin K when indicated; vitamin K alone acts too slowly to provide immediate factor replacement. Other anticoagulants need drug-specific reversal strategies. [2]
Predict the harm: a patient taking aspirin has spontaneous ICH but no emergency surgery planned. Routine platelet transfusion to reverse aspirin is potentially harmful and should not be given reflexively; emergency neurosurgery is a distinct setting in which platelet transfusion may be considered. Escalate to an ICH team instead of treating all antithrombotic exposure as the same problem. [2]
Pressure, posterior fossa and blood pressure
The cerebellum has little room to swell. Deterioration, brainstem compression, obstructive hydrocephalus or a cerebellar hematoma volume of at least 15 mL is an indication for immediate surgical evacuation, with or without ventricular drainage; drainage alone may not solve direct compression. For selected mild-to-moderate spontaneous ICH presenting with systolic pressure 150 to 220 mm Hg, smooth acute lowering toward 140 mm Hg and maintaining roughly 130 to 150 mm Hg may be reasonable.
Avoid abruptly pushing systolic pressure below 130 mm Hg in that setting. Large or severe bleeds demand individualized decisions. This acute range is not the long-term target: after stabilization, sustained blood-pressure control around 130/80 mm Hg may help prevent recurrence, individualized to tolerance and other disease. The same small-vessel disease also causes ischemic injury and cognitive decline.
Recurrence risk varies with etiology, location, BP and MRI findings, not one annual percentage. Choose an individualized antihypertensive regimen rather than a mandatory drug class. [2]
Transfer: a selected lobar hematoma and a deep putaminal hematoma do not have identical surgical evidence. Selected patients with lobar ICH may benefit from minimally invasive evacuation, but trial findings do not establish benefit for every deep hemorrhage. A stable deep hemorrhage still needs neurocritical observation, serial neurological examinations and repeat imaging when indicated. Deterioration, substantial mass effect or refractory ICP warrants renewed neurosurgical assessment. Consider location, volume, course and expertise rather than offering one operation to all patients. [12][2]
Try it here · Checkpoint 3 of 3
Make your prediction before reading the choices. A first attempt is just a starting point.
Case 22
Show answer and explanations for case 22
A. Hyperosmolar treatment as definitive care without surgical evaluation (Why this does not fit)
Hyperosmolar measures may temporize during emergency care but do not replace indicated evacuation.
Reasoning steps for option A
Which two problems are present in the posterior fossa?
Direct brainstem compression and obstructed CSF circulation.
Why is drainage alone incomplete?
It does not evacuate the compressive cerebellar clot.
Does this option account for the supplied conditions?
Hyperosmolar measures may temporize during emergency care but do not replace indicated evacuation.
B. Urgent hematoma evacuation with ventricular drainage when indicated (Best answer)
The clot directly compresses brainstem and obstructs CSF; immediate evacuation is indicated, with drainage as needed.
Reasoning steps for option B
Which two problems are present in the posterior fossa?
Direct brainstem compression and obstructed CSF circulation.
Why is drainage alone incomplete?
It does not evacuate the compressive cerebellar clot.
Does this option account for the supplied conditions?
The clot directly compresses brainstem and obstructs CSF; immediate evacuation is indicated, with drainage as needed.
C. Medical observation until the clot reaches 30 mL (Why this does not fit)
A 30-mL threshold from other settings is not appropriate; this patient already has deterioration, compression and volume above 15 mL.
Reasoning steps for option C
Which two problems are present in the posterior fossa?
Direct brainstem compression and obstructed CSF circulation.
Why is drainage alone incomplete?
It does not evacuate the compressive cerebellar clot.
Does this option account for the supplied conditions?
A 30-mL threshold from other settings is not appropriate; this patient already has deterioration, compression and volume above 15 mL.
D. Ventricular drainage alone followed by observation of the cerebellar clot (Why this does not fit)
Drainage may treat hydrocephalus but leaves direct posterior-fossa compression untreated.
Reasoning steps for option D
Which two problems are present in the posterior fossa?
Direct brainstem compression and obstructed CSF circulation.
Why is drainage alone incomplete?
It does not evacuate the compressive cerebellar clot.
Does this option account for the supplied conditions?
Drainage may treat hydrocephalus but leaves direct posterior-fossa compression untreated.
Takeaway: Identify both obstruction and direct compression before deciding whether drainage alone is enough.
For each case, identify the compartment first, then use tempo and examination to choose an immediate action. A lens predicts a possible rapidly expanding extra-axial mass; a crescent can present late; cisternal blood changes the aneurysm workup; a parenchymal focus changes reversal and pressure decisions. Before viewing an answer, state which finding would overturn your first impression. Return to the corresponding image if the shape and history disagree.
Case 2
Show answer and explanations for case 2
A. Urgent evacuation with continued reversal (Best answer)
This is acute SDH exceeding thickness and shift surgical criteria; preserved consciousness does not cancel the indication.
Reasoning steps for option A
Which compartment allows the crescent to cross sutures?
The subdural compartment beneath the dura.
Does being awake override 12-mm thickness and 6-mm shift?
No. Either measurement exceeds the acute-SDH surgical threshold regardless of GCS.
Does this option account for the supplied conditions?
This is acute SDH exceeding thickness and shift surgical criteria; preserved consciousness does not cancel the indication.
B. Reversal followed by delayed elective drainage (Why this does not fit)
Reversal is necessary but does not relieve existing mass effect or remove the acute surgical indication.
Reasoning steps for option B
Which compartment allows the crescent to cross sutures?
The subdural compartment beneath the dura.
Does being awake override 12-mm thickness and 6-mm shift?
No. Either measurement exceeds the acute-SDH surgical threshold regardless of GCS.
Does this option account for the supplied conditions?
Reversal is necessary but does not relieve existing mass effect or remove the acute surgical indication.
C. Observation until consciousness worsens (Why this does not fit)
Waiting for decline overlooks CT-based criteria that apply regardless of GCS.
Reasoning steps for option C
Which compartment allows the crescent to cross sutures?
The subdural compartment beneath the dura.
Does being awake override 12-mm thickness and 6-mm shift?
No. Either measurement exceeds the acute-SDH surgical threshold regardless of GCS.
Does this option account for the supplied conditions?
Waiting for decline overlooks CT-based criteria that apply regardless of GCS.
D. EVD placement instead of clot evacuation (Why this does not fit)
The shift is from an extra-axial clot, not documented hydrocephalus; ventricular drainage is not a substitute.
Reasoning steps for option D
Which compartment allows the crescent to cross sutures?
The subdural compartment beneath the dura.
Does being awake override 12-mm thickness and 6-mm shift?
No. Either measurement exceeds the acute-SDH surgical threshold regardless of GCS.
Does this option account for the supplied conditions?
The shift is from an extra-axial clot, not documented hydrocephalus; ventricular drainage is not a substitute.
Takeaway: In acute SDH, combine compartment and measurements before interpreting a reassuring examination.
A. Proceed with multidisciplinary safeguarding and medical evaluation in parallel (Best answer)
The findings require prompt comprehensive assessment, including history, other injuries and medical alternatives; pending coagulation studies do not justify delaying safeguarding.
Reasoning steps for option A
Do these findings establish one injury mechanism?
No. They are concerning but require assessment of history, other injuries and medical alternatives.
Should protective assessment wait for coagulation results?
No. Safeguarding and medical evaluation should proceed in parallel.
Does this option account for the supplied conditions?
The findings require prompt comprehensive assessment, including history, other injuries and medical alternatives; pending coagulation studies do not justify delaying safeguarding.
B. Base the mechanism on CT density, then limit other testing to that mechanism (Why this does not fit)
Attenuation cannot reliably date or attribute the injury, so it cannot select a unique mechanism.
Reasoning steps for option B
Do these findings establish one injury mechanism?
No. They are concerning but require assessment of history, other injuries and medical alternatives.
Should protective assessment wait for coagulation results?
No. Safeguarding and medical evaluation should proceed in parallel.
Does this option account for the supplied conditions?
Attenuation cannot reliably date or attribute the injury, so it cannot select a unique mechanism.
C. Finish the bleeding-disorder evaluation before requesting a child-protection assessment (Why this does not fit)
Medical mimics deserve investigation, but possible coexisting disease should not postpone protective assessment.
Reasoning steps for option C
Do these findings establish one injury mechanism?
No. They are concerning but require assessment of history, other injuries and medical alternatives.
Should protective assessment wait for coagulation results?
No. Safeguarding and medical evaluation should proceed in parallel.
Does this option account for the supplied conditions?
Medical mimics deserve investigation, but possible coexisting disease should not postpone protective assessment.
D. Use short-interval head CT as a substitute for broader injury assessment (Why this does not fit)
Repeat CT may follow intracranial evolution but cannot replace ophthalmologic, skeletal and multidisciplinary assessment when indicated.
Reasoning steps for option D
Do these findings establish one injury mechanism?
No. They are concerning but require assessment of history, other injuries and medical alternatives.
Should protective assessment wait for coagulation results?
No. Safeguarding and medical evaluation should proceed in parallel.
Does this option account for the supplied conditions?
Repeat CT may follow intracranial evolution but cannot replace ophthalmologic, skeletal and multidisciplinary assessment when indicated.
Takeaway: Investigate medical alternatives and protect the infant without claiming that one imaging pattern proves causation.
A. Brain MRI with diffusion-weighted sequences only (Why this does not fit)
Diffusion MRI can identify ischemia but cannot replace CSF testing for suspected occult SAH here.
Reasoning steps for option A
Why does the negative CT not finish this investigation?
It was obtained fourteen hours after a sudden maximal headache, beyond the selected early-CT pathway.
What makes CSF analysis an appropriate next test?
Concern remains and the supplied examination, CT and coagulation findings reveal no LP contraindication.
Does this option account for the supplied conditions?
Diffusion MRI can identify ischemia but cannot replace CSF testing for suspected occult SAH here.
B. CT angiography alone to establish whether prior bleeding occurred (Why this does not fit)
CTA identifies vascular lesions but an incidental aneurysm does not itself prove that a CT-negative headache involved bleeding; CSF directly tests the unresolved hemorrhage question.
Reasoning steps for option B
Why does the negative CT not finish this investigation?
It was obtained fourteen hours after a sudden maximal headache, beyond the selected early-CT pathway.
What makes CSF analysis an appropriate next test?
Concern remains and the supplied examination, CT and coagulation findings reveal no LP contraindication.
Does this option account for the supplied conditions?
CTA identifies vascular lesions but an incidental aneurysm does not itself prove that a CT-negative headache involved bleeding; CSF directly tests the unresolved hemorrhage question.
C. Repeat the same noncontrast CT immediately without interval change (Why this does not fit)
An immediate identical CT is unlikely to resolve the time-dependent sensitivity limitation.
Reasoning steps for option C
Why does the negative CT not finish this investigation?
It was obtained fourteen hours after a sudden maximal headache, beyond the selected early-CT pathway.
What makes CSF analysis an appropriate next test?
Concern remains and the supplied examination, CT and coagulation findings reveal no LP contraindication.
Does this option account for the supplied conditions?
An immediate identical CT is unlikely to resolve the time-dependent sensitivity limitation.
D. Lumbar puncture with CSF analysis (Best answer)
Beyond six hours, LP with CSF red cells and bilirubin can assess hemorrhage missed by CT in this suitable patient.
Reasoning steps for option D
Why does the negative CT not finish this investigation?
It was obtained fourteen hours after a sudden maximal headache, beyond the selected early-CT pathway.
What makes CSF analysis an appropriate next test?
Concern remains and the supplied examination, CT and coagulation findings reveal no LP contraindication.
Does this option account for the supplied conditions?
Beyond six hours, LP with CSF red cells and bilirubin can assess hemorrhage missed by CT in this suitable patient.
Takeaway: Beyond six hours, LP with CSF red cells and bilirubin can assess hemorrhage missed by CT in this suitable patient.
A. Continue urgent cerebrovascular evaluation rather than applying the intact-examination pathway (Best answer)
A new focal deficit requires urgent reassessment for SAH and other vascular causes; the selected neurologically intact pathway is no longer an adequate disposition basis.
Reasoning steps for option A
What changed after the reassuring early scan?
A new focal language and motor deficit appeared.
Can the neurologically intact pathway still justify discharge?
No. The changed examination requires urgent evaluation of vascular causes.
Does this option account for the supplied conditions?
A new focal deficit requires urgent reassessment for SAH and other vascular causes; the selected neurologically intact pathway is no longer an adequate disposition basis.
B. Treat as confirmed aneurysmal SAH on the neurological findings alone (Why this does not fit)
The deficit increases urgency but does not establish aneurysmal bleeding without further diagnostic evidence.
Reasoning steps for option B
What changed after the reassuring early scan?
A new focal language and motor deficit appeared.
Can the neurologically intact pathway still justify discharge?
No. The changed examination requires urgent evaluation of vascular causes.
Does this option account for the supplied conditions?
The deficit increases urgency but does not establish aneurysmal bleeding without further diagnostic evidence.
C. Arrange outpatient vascular imaging because the scan has excluded an acute vascular cause (Why this does not fit)
A negative noncontrast CT does not exclude ischemia, aneurysm or every cause of thunderclap headache.
Reasoning steps for option C
What changed after the reassuring early scan?
A new focal language and motor deficit appeared.
Can the neurologically intact pathway still justify discharge?
No. The changed examination requires urgent evaluation of vascular causes.
Does this option account for the supplied conditions?
A negative noncontrast CT does not exclude ischemia, aneurysm or every cause of thunderclap headache.
D. Discharge after symptomatic treatment because scan timing determines the pathway (Why this does not fit)
Timing is only one qualifier; evolving focal deficits require a new evaluation.
Reasoning steps for option D
What changed after the reassuring early scan?
A new focal language and motor deficit appeared.
Can the neurologically intact pathway still justify discharge?
No. The changed examination requires urgent evaluation of vascular causes.
Does this option account for the supplied conditions?
Timing is only one qualifier; evolving focal deficits require a new evaluation.
Takeaway: A diagnostic pathway applies to the complete patient state, not only elapsed time.
A. Uncal displacement from a temporal mass rather than either aneurysm (Why this does not fit)
A temporal mass can compress CN III, but the supplied scan describes cisternal SAH and aneurysms, not a temporal mass. The ipsilateral PCOM lesion directly matches the nerve course.
Reasoning steps for option A
Where do ptosis, poor adduction and pupil dilation localize?
The right oculomotor nerve.
Which detected aneurysm lies beside that nerve?
The right posterior communicating origin aneurysm; this supports symptoms without proving the rupture source.
Does this option account for the supplied conditions?
A temporal mass can compress CN III, but the supplied scan describes cisternal SAH and aneurysms, not a temporal mass. The ipsilateral PCOM lesion directly matches the nerve course.
B. Diabetic microvascular third-nerve injury rather than either aneurysm (Why this does not fit)
Microvascular palsy is a competing cause of CN III dysfunction, but an acute pupil-involving syndrome with SAH and an adjacent PCOM aneurysm favors compression.
Reasoning steps for option B
Where do ptosis, poor adduction and pupil dilation localize?
The right oculomotor nerve.
Which detected aneurysm lies beside that nerve?
The right posterior communicating origin aneurysm; this supports symptoms without proving the rupture source.
Does this option account for the supplied conditions?
Microvascular palsy is a competing cause of CN III dysfunction, but an acute pupil-involving syndrome with SAH and an adjacent PCOM aneurysm favors compression.
C. Right posterior communicating artery origin aneurysm (Best answer)
The right PCom origin abuts right CN III; compressive pupil-involving palsy points to this lesion even when another aneurysm coexists.
Reasoning steps for option C
Where do ptosis, poor adduction and pupil dilation localize?
The right oculomotor nerve.
Which detected aneurysm lies beside that nerve?
The right posterior communicating origin aneurysm; this supports symptoms without proving the rupture source.
Does this option account for the supplied conditions?
The right PCom origin abuts right CN III; compressive pupil-involving palsy points to this lesion even when another aneurysm coexists.
D. Anterior communicating artery aneurysm (Why this does not fit)
Anterior communicating lesions may affect optic pathways but are not the closest explanation for right CN III dysfunction.
Reasoning steps for option D
Where do ptosis, poor adduction and pupil dilation localize?
The right oculomotor nerve.
Which detected aneurysm lies beside that nerve?
The right posterior communicating origin aneurysm; this supports symptoms without proving the rupture source.
Does this option account for the supplied conditions?
Anterior communicating lesions may affect optic pathways but are not the closest explanation for right CN III dysfunction.
Takeaway: The right PCom origin abuts right CN III; compressive pupil-involving palsy points to this lesion even when another aneurysm coexists.
A. Left optic nerve: retinal axons carrying the entire left-eye field (Why this does not fit)
A left optic-nerve lesion primarily impairs the left eye rather than temporal fields from both eyes.
Reasoning steps for option A
Which retinal half receives a temporal visual field?
The nasal half of each retina.
Where do those axons cross?
At the optic chiasm, where this aneurysm projects.
Does this option account for the supplied conditions?
A left optic-nerve lesion primarily impairs the left eye rather than temporal fields from both eyes.
B. Optic chiasm: uncrossed axons from both temporal hemiretinas (Why this does not fit)
Temporal retinal fibers carry nasal visual fields and remain uncrossed; this combination does not explain the supplied losses.
Reasoning steps for option B
Which retinal half receives a temporal visual field?
The nasal half of each retina.
Where do those axons cross?
At the optic chiasm, where this aneurysm projects.
Does this option account for the supplied conditions?
Temporal retinal fibers carry nasal visual fields and remain uncrossed; this combination does not explain the supplied losses.
C. Right optic tract: axons carrying the left visual hemifield from both eyes (Why this does not fit)
Right optic-tract injury causes a left homonymous deficit, affecting the same side of space in both eyes, not their temporal halves.
Reasoning steps for option C
Which retinal half receives a temporal visual field?
The nasal half of each retina.
Where do those axons cross?
At the optic chiasm, where this aneurysm projects.
Does this option account for the supplied conditions?
Right optic-tract injury causes a left homonymous deficit, affecting the same side of space in both eyes, not their temporal halves.
D. Optic chiasm: crossing axons from both nasal hemiretinas (Best answer)
Temporal fields project to nasal retina. Bilateral temporal loss localizes to crossing nasal-retinal axons in the chiasm. Directional ACOM compression is possible but rare.
Reasoning steps for option D
Which retinal half receives a temporal visual field?
The nasal half of each retina.
Where do those axons cross?
At the optic chiasm, where this aneurysm projects.
Does this option account for the supplied conditions?
Temporal fields project to nasal retina. Bilateral temporal loss localizes to crossing nasal-retinal axons in the chiasm. Directional ACOM compression is possible but rare.
Takeaway: Map fields to retinal halves, then localize crossing fibers; rare ACOM mass effect is one possible cause, not a stereotyped presentation.
A. Continue nimodipine and urgently assess/treat delayed cerebral ischemia (Best answer)
Nimodipine improves functional outcome without reliably resolving angiographic spasm; new deficit still needs immediate DCI evaluation and treatment.
Reasoning steps for option A
What does persistent angiographic narrowing establish about nimodipine benefit?
It does not negate the clinical outcome benefit.
What does new day-seven weakness require despite preventive treatment?
Urgent assessment for delayed ischemia and alternative causes while tolerated nimodipine continues.
Does this option account for the supplied conditions?
Nimodipine improves functional outcome without reliably resolving angiographic spasm; new deficit still needs immediate DCI evaluation and treatment.
B. Increase nimodipine above standard dosing until narrowing disappears (Why this does not fit)
Escalating dose to chase vessel caliber risks hypotension and is not the recommended endpoint.
Reasoning steps for option B
What does persistent angiographic narrowing establish about nimodipine benefit?
It does not negate the clinical outcome benefit.
What does new day-seven weakness require despite preventive treatment?
Urgent assessment for delayed ischemia and alternative causes while tolerated nimodipine continues.
Does this option account for the supplied conditions?
Escalating dose to chase vessel caliber risks hypotension and is not the recommended endpoint.
C. Replace nimodipine with prophylactic hypervolemia solely to normalize arterial caliber (Why this does not fit)
Prophylactic hypervolemia can cause harm and is not a substitute for nimodipine or symptom-directed DCI care.
Reasoning steps for option C
What does persistent angiographic narrowing establish about nimodipine benefit?
It does not negate the clinical outcome benefit.
What does new day-seven weakness require despite preventive treatment?
Urgent assessment for delayed ischemia and alternative causes while tolerated nimodipine continues.
Does this option account for the supplied conditions?
Prophylactic hypervolemia can cause harm and is not a substitute for nimodipine or symptom-directed DCI care.
D. Stop nimodipine because angiographic narrowing demonstrates lack of benefit (Why this does not fit)
Narrowing alone does not show that nimodipine is ineffective for clinical outcome.
Reasoning steps for option D
What does persistent angiographic narrowing establish about nimodipine benefit?
It does not negate the clinical outcome benefit.
What does new day-seven weakness require despite preventive treatment?
Urgent assessment for delayed ischemia and alternative causes while tolerated nimodipine continues.
Does this option account for the supplied conditions?
Narrowing alone does not show that nimodipine is ineffective for clinical outcome.
Takeaway: Nimodipine improves functional outcome without reliably resolving angiographic spasm; new deficit still needs immediate DCI evaluation and treatment.
A. Delayed cerebral ischemia in the right MCA territory (Best answer)
Delayed focal deficit in the risk window plus corresponding right MCA narrowing and no alternative supports DCI.
Reasoning steps for option A
Which territory matches the left arm deficit?
The right hemisphere, consistent with the supplied right MCA narrowing.
Why is delayed ischemia favored over the listed alternatives?
The timing fits, CT shows no new bleeding or ventricular enlargement, and current ictal activity is absent.
Does this option account for the supplied conditions?
Delayed focal deficit in the risk window plus corresponding right MCA narrowing and no alternative supports DCI.
B. Acute obstructive hydrocephalus from residual ventricular blood (Why this does not fit)
Stable ventricular caliber argues against acute symptomatic hydrocephalus.
Reasoning steps for option B
Which territory matches the left arm deficit?
The right hemisphere, consistent with the supplied right MCA narrowing.
Why is delayed ischemia favored over the listed alternatives?
The timing fits, CT shows no new bleeding or ventricular enlargement, and current ictal activity is absent.
Does this option account for the supplied conditions?
Stable ventricular caliber argues against acute symptomatic hydrocephalus.
C. Rebleeding from the secured aneurysm (Why this does not fit)
No new blood argues against rerupture as the immediate cause.
Reasoning steps for option C
Which territory matches the left arm deficit?
The right hemisphere, consistent with the supplied right MCA narrowing.
Why is delayed ischemia favored over the listed alternatives?
The timing fits, CT shows no new bleeding or ventricular enlargement, and current ictal activity is absent.
Does this option account for the supplied conditions?
No new blood argues against rerupture as the immediate cause.
D. Postictal weakness from a focal seizure (Why this does not fit)
Postictal weakness remains a differential possibility; the sustained new deficit during the DCI window with corresponding arterial narrowing favors ischemia. A negative EEG alone would not exclude a prior seizure.
Reasoning steps for option D
Which territory matches the left arm deficit?
The right hemisphere, consistent with the supplied right MCA narrowing.
Why is delayed ischemia favored over the listed alternatives?
The timing fits, CT shows no new bleeding or ventricular enlargement, and current ictal activity is absent.
Does this option account for the supplied conditions?
Postictal weakness remains a differential possibility; the sustained new deficit during the DCI window with corresponding arterial narrowing favors ischemia. A negative EEG alone would not exclude a prior seizure.
Takeaway: Delayed focal deficit in the risk window plus corresponding right MCA narrowing and no alternative supports DCI.
A. Worsening right arm and leg weakness from posterior-limb compression (Best answer)
The initial focus is putaminal. Medial expansion threatens corticospinal fibers in the left posterior limb, worsening contralateral limb weakness.
Reasoning steps for option A
Which deep structure lies lateral to the internal capsule?
The putaminal region.
What does medial progression threaten first?
Adjacent capsular motor pathways, worsening contralateral weakness.
Does this option account for the supplied conditions?
The initial focus is putaminal. Medial expansion threatens corticospinal fibers in the left posterior limb, worsening contralateral limb weakness.
B. New abulia from direct injury to the caudate head (Why this does not fit)
The caudate head is an anterior deep structure; the described medial progression toward the posterior limb instead threatens motor pathways.
Reasoning steps for option B
Which deep structure lies lateral to the internal capsule?
The putaminal region.
What does medial progression threaten first?
Adjacent capsular motor pathways, worsening contralateral weakness.
Does this option account for the supplied conditions?
The caudate head is an anterior deep structure; the described medial progression toward the posterior limb instead threatens motor pathways.
C. New aphasia from direct injury to lateral frontal cortex (Why this does not fit)
A dominant cortical extension could cause aphasia, but the proposed progression is medial from a deep lateral focus, not outward into cortex.
Reasoning steps for option C
Which deep structure lies lateral to the internal capsule?
The putaminal region.
What does medial progression threaten first?
Adjacent capsular motor pathways, worsening contralateral weakness.
Does this option account for the supplied conditions?
A dominant cortical extension could cause aphasia, but the proposed progression is medial from a deep lateral focus, not outward into cortex.
D. New right hemisensory loss from thalamic rather than capsular involvement (Why this does not fit)
The thalamus is medial to the capsule, but immediate medial progression from the putamen first threatens the capsule; no thalamic extension is described.
Reasoning steps for option D
Which deep structure lies lateral to the internal capsule?
The putaminal region.
What does medial progression threaten first?
Adjacent capsular motor pathways, worsening contralateral weakness.
Does this option account for the supplied conditions?
The thalamus is medial to the capsule, but immediate medial progression from the putamen first threatens the capsule; no thalamic extension is described.
Takeaway: Medial expansion from the putamen can threaten posterior-limb corticospinal fibers and worsen contralateral arm and leg weakness.
A. New cortical language dysfunction from direct lateral frontal extension (Why this does not fit)
The imaging direction is toward the midline ventricle, not outward into lateral frontal cortex.
Reasoning steps for option A
Which deep focus fits sensory loss and vertical gaze impairment?
Thalamic hemorrhage with adjacent rostral involvement.
What can ventricular extension cause?
Blood can obstruct CSF circulation and produce hydrocephalus.
Does this option account for the supplied conditions?
The imaging direction is toward the midline ventricle, not outward into lateral frontal cortex.
B. Acute hydrocephalus if blood enters and obstructs ventricular CSF flow (Best answer)
A thalamic-region bleed abutting the third ventricle can extend intraventricularly and obstruct CSF flow.
Reasoning steps for option B
Which deep focus fits sensory loss and vertical gaze impairment?
Thalamic hemorrhage with adjacent rostral involvement.
What can ventricular extension cause?
Blood can obstruct CSF circulation and produce hydrocephalus.
Does this option account for the supplied conditions?
A thalamic-region bleed abutting the third ventricle can extend intraventricularly and obstruct CSF flow.
C. New contralateral homonymous field loss from isolated optic-tract compression (Why this does not fit)
Visual pathway involvement can occur with some deep lesions, but the specified extension toward the ventricular lumen particularly threatens CSF circulation.
Reasoning steps for option C
Which deep focus fits sensory loss and vertical gaze impairment?
Thalamic hemorrhage with adjacent rostral involvement.
What can ventricular extension cause?
Blood can obstruct CSF circulation and produce hydrocephalus.
Does this option account for the supplied conditions?
Visual pathway involvement can occur with some deep lesions, but the specified extension toward the ventricular lumen particularly threatens CSF circulation.
D. New obstructive hydrocephalus from fourth-ventricle compression by a cerebellar mass (Why this does not fit)
Hydrocephalus is possible, but this supratentorial thalamic focus approaches the third ventricle rather than directly compressing the fourth from the cerebellum.
Reasoning steps for option D
Which deep focus fits sensory loss and vertical gaze impairment?
Thalamic hemorrhage with adjacent rostral involvement.
What can ventricular extension cause?
Blood can obstruct CSF circulation and produce hydrocephalus.
Does this option account for the supplied conditions?
Hydrocephalus is possible, but this supratentorial thalamic focus approaches the third ventricle rather than directly compressing the fourth from the cerebellum.
Takeaway: A thalamic-region bleed abutting the third ventricle can extend intraventricularly and obstruct CSF flow.
A. Unilateral ptosis with a fixed dilated pupil and otherwise intact horizontal gaze (Why this does not fit)
This favors peripheral CN III compression; the bilateral long-tract and respiratory findings require broader brainstem injury.
Reasoning steps for option A
Where is the hematoma relative to the fourth ventricle?
Anterior to it, consistent with the pons.
Which additional gaze function can pontine injury impair?
Conjugate horizontal gaze.
Does this option account for the supplied conditions?
This favors peripheral CN III compression; the bilateral long-tract and respiratory findings require broader brainstem injury.
B. Bitemporal visual-field loss with preserved eye movements (Why this does not fit)
Bitemporal loss localizes to the chiasm, not the central posterior-fossa lesion.
Reasoning steps for option B
Where is the hematoma relative to the fourth ventricle?
Anterior to it, consistent with the pons.
Which additional gaze function can pontine injury impair?
Conjugate horizontal gaze.
Does this option account for the supplied conditions?
Bitemporal loss localizes to the chiasm, not the central posterior-fossa lesion.
C. Contralateral hemisensory loss with preserved horizontal gaze (Why this does not fit)
A thalamic focus can cause hemisensory loss, but it does not fit blood anterior to the fourth ventricle and this pontine syndrome.
Reasoning steps for option C
Where is the hematoma relative to the fourth ventricle?
Anterior to it, consistent with the pons.
Which additional gaze function can pontine injury impair?
Conjugate horizontal gaze.
Does this option account for the supplied conditions?
A thalamic focus can cause hemisensory loss, but it does not fit blood anterior to the fourth ventricle and this pontine syndrome.
D. Bilateral horizontal gaze impairment (Best answer)
The examination and CT localize to the pons. Injury involving pontine horizontal gaze networks can impair conjugate horizontal gaze as well as consciousness and respiration.
Reasoning steps for option D
Where is the hematoma relative to the fourth ventricle?
Anterior to it, consistent with the pons.
Which additional gaze function can pontine injury impair?
Conjugate horizontal gaze.
Does this option account for the supplied conditions?
The examination and CT localize to the pons. Injury involving pontine horizontal gaze networks can impair conjugate horizontal gaze as well as consciousness and respiration.
Takeaway: Localize the hemorrhage, then predict another function of the involved brainstem region.
A. The lobar pattern generally carries greater recurrence concern because it supports amyloid-related vessel disease (Best answer)
The first pattern supports CAA; this etiology generally confers greater recurrent hemorrhage concern than deep arteriolosclerosis. This is not a fixed prediction for an individual.
Reasoning steps for option A
Which vessel disease fits the strictly lobar hemorrhagic markers?
Cerebral amyloid angiopathy.
With comparable BP control, how do the etiologies affect future risk?
CAA-related hemorrhage generally carries greater recurrence concern than deep arteriolosclerosis; equal BP control does not erase vessel pathology.
Does this option account for the supplied conditions?
The first pattern supports CAA; this etiology generally confers greater recurrent hemorrhage concern than deep arteriolosclerosis. This is not a fixed prediction for an individual.
B. The lobar pattern supports amyloid-related disease, but comparable BP control generally makes its recurrence risk lower than deep arteriolosclerosis (Why this does not fit)
Identifying CAA is only the first inference. BP control is important but does not reverse its generally higher recurrence concern compared with deep arteriolosclerosis.
Reasoning steps for option B
Which vessel disease fits the strictly lobar hemorrhagic markers?
Cerebral amyloid angiopathy.
With comparable BP control, how do the etiologies affect future risk?
CAA-related hemorrhage generally carries greater recurrence concern than deep arteriolosclerosis; equal BP control does not erase vessel pathology.
Does this option account for the supplied conditions?
Identifying CAA is only the first inference. BP control is important but does not reverse its generally higher recurrence concern compared with deep arteriolosclerosis.
C. The deep pattern generally carries greater recurrence concern because it preferentially indicates amyloid-related disease (Why this does not fit)
Deep perforator hemorrhage and microbleeds favor arteriolosclerosis, not the cortical and leptomeningeal distribution of CAA.
Reasoning steps for option C
Which vessel disease fits the strictly lobar hemorrhagic markers?
Cerebral amyloid angiopathy.
With comparable BP control, how do the etiologies affect future risk?
CAA-related hemorrhage generally carries greater recurrence concern than deep arteriolosclerosis; equal BP control does not erase vessel pathology.
Does this option account for the supplied conditions?
Deep perforator hemorrhage and microbleeds favor arteriolosclerosis, not the cortical and leptomeningeal distribution of CAA.
D. Recurrence concern is similar because controlled BP makes the vessel distributions prognostically interchangeable (Why this does not fit)
BP control reduces risk but does not erase the prognostic effect of different vessel pathology and MRI markers.
Reasoning steps for option D
Which vessel disease fits the strictly lobar hemorrhagic markers?
Cerebral amyloid angiopathy.
With comparable BP control, how do the etiologies affect future risk?
CAA-related hemorrhage generally carries greater recurrence concern than deep arteriolosclerosis; equal BP control does not erase vessel pathology.
Does this option account for the supplied conditions?
BP control reduces risk but does not erase the prognostic effect of different vessel pathology and MRI markers.
Takeaway: Infer the vessel pathology from distribution, then discuss future risk without applying a uniform annual percentage.
Venous and capillary congestion can produce hemorrhagic venous infarction.
Does this option account for the supplied conditions?
The distribution and sinus occlusion identify venous thrombosis; impaired outflow causes congestion and hemorrhagic venous infarction.
D. Direct high-flow arterial shunting into a focal vascular nidus (Why this does not fit)
An AVM could bleed, but a focal nidus or early draining vein is not described; sinus obstruction and bilateral nonterritorial lesions favor venous congestion.
Reasoning steps for option D
Why does the distribution argue against a single arterial infarct?
Venous and capillary congestion can produce hemorrhagic venous infarction.
Does this option account for the supplied conditions?
An AVM could bleed, but a focal nidus or early draining vein is not described; sinus obstruction and bilateral nonterritorial lesions favor venous congestion.
Takeaway: Nonarterial hemorrhage distribution plus sinus occlusion identifies an outflow problem rather than a ruptured perforator.
A. Give desmopressin as an established outcome-improving replacement for platelet transfusion (Why this does not fit)
Desmopressin is considered in some protocols, but its effectiveness for preventing hematoma expansion in antiplatelet-associated ICH is uncertain; it is not an established outcome-improving substitute.
Reasoning steps for option A
Is aspirin primarily a coagulation-factor problem?
No. It inhibits platelet function.
Does replacing platelets therefore improve this nonsurgical ICH?
Not necessarily; routine transfusion in this setting is potentially harmful.
Does this option account for the supplied conditions?
Desmopressin is considered in some protocols, but its effectiveness for preventing hematoma expansion in antiplatelet-associated ICH is uncertain; it is not an established outcome-improving substitute.
B. Give platelets now to replace inhibited circulating platelets (Why this does not fit)
This appears mechanistically attractive, but outcome evidence argues against routine transfusion in the supplied nonsurgical setting.
Reasoning steps for option B
Is aspirin primarily a coagulation-factor problem?
No. It inhibits platelet function.
Does replacing platelets therefore improve this nonsurgical ICH?
Not necessarily; routine transfusion in this setting is potentially harmful.
Does this option account for the supplied conditions?
This appears mechanistically attractive, but outcome evidence argues against routine transfusion in the supplied nonsurgical setting.
C. Use four-factor PCC instead to reverse aspirin inhibition (Why this does not fit)
PCC replaces coagulation factors and treats selected anticoagulant effects, not aspirin-mediated platelet inhibition.
Reasoning steps for option C
Is aspirin primarily a coagulation-factor problem?
No. It inhibits platelet function.
Does replacing platelets therefore improve this nonsurgical ICH?
Not necessarily; routine transfusion in this setting is potentially harmful.
Does this option account for the supplied conditions?
PCC replaces coagulation factors and treats selected anticoagulant effects, not aspirin-mediated platelet inhibition.
D. Cancel routine platelet transfusion while continuing standard ICH care (Best answer)
The pharmacologic rationale does not establish clinical benefit. Routine platelet transfusion in nonsurgical aspirin-associated spontaneous ICH is potentially harmful.
Reasoning steps for option D
Is aspirin primarily a coagulation-factor problem?
No. It inhibits platelet function.
Does replacing platelets therefore improve this nonsurgical ICH?
Not necessarily; routine transfusion in this setting is potentially harmful.
Does this option account for the supplied conditions?
The pharmacologic rationale does not establish clinical benefit. Routine platelet transfusion in nonsurgical aspirin-associated spontaneous ICH is potentially harmful.
Takeaway: Antithrombotic mechanism and the surgical context determine whether a proposed reversal is supported.
A. Perform immediate decompressive surgery based on volume alone (Why this does not fit)
Decompression may be considered for severe mass effect or refractory pressure, neither of which is supplied.
Reasoning steps for option A
Does the cited surgical trial concern an identical anatomical population?
No. Selected lobar benefit cannot simply be assigned to a stable putaminal hemorrhage.
Which supplied findings support monitored medical care?
Stable consciousness and examination without hydrocephalus or progressing mass effect.
Does this option account for the supplied conditions?
Decompression may be considered for severe mass effect or refractory pressure, neither of which is supplied.
B. Insert an EVD now as the primary treatment for the deep clot (Why this does not fit)
There is no hydrocephalus or ventricular blood; an EVD would not directly evacuate the parenchymal clot.
Reasoning steps for option B
Does the cited surgical trial concern an identical anatomical population?
No. Selected lobar benefit cannot simply be assigned to a stable putaminal hemorrhage.
Which supplied findings support monitored medical care?
Stable consciousness and examination without hydrocephalus or progressing mass effect.
Does this option account for the supplied conditions?
There is no hydrocephalus or ventricular blood; an EVD would not directly evacuate the parenchymal clot.
C. Schedule early minimally invasive evacuation within the next day (Why this does not fit)
Location and eligibility matter. Lobar benefit does not establish routine benefit for a stable putaminal hematoma.
Reasoning steps for option C
Does the cited surgical trial concern an identical anatomical population?
No. Selected lobar benefit cannot simply be assigned to a stable putaminal hemorrhage.
Which supplied findings support monitored medical care?
Stable consciousness and examination without hydrocephalus or progressing mass effect.
Does this option account for the supplied conditions?
Location and eligibility matter. Lobar benefit does not establish routine benefit for a stable putaminal hematoma.
D. Continue neurocritical medical care and serial reassessment with neurosurgical input (Best answer)
Stable deep ICH without ventricular obstruction does not automatically warrant evacuation; selected lobar trial findings cannot simply be transferred to this patient.
Reasoning steps for option D
Does the cited surgical trial concern an identical anatomical population?
No. Selected lobar benefit cannot simply be assigned to a stable putaminal hemorrhage.
Which supplied findings support monitored medical care?
Stable consciousness and examination without hydrocephalus or progressing mass effect.
Does this option account for the supplied conditions?
Stable deep ICH without ventricular obstruction does not automatically warrant evacuation; selected lobar trial findings cannot simply be transferred to this patient.
Takeaway: Surgery evidence must fit location, severity and clinical trajectory, not just the word hemorrhage.
A. Replace daily treatment with doses only for readings above 180 (Why this does not fit)
Intermittent treatment leaves sustained hypertension unaddressed and increases variability.
Reasoning steps for option A
Is this an acute expansion or long-term prevention decision?
Long-term prevention, six months after ICH.
Which findings support adjusting daily treatment?
Persistent hypertension despite adherence, without orthostatic symptoms or renal instability.
Does this option account for the supplied conditions?
Intermittent treatment leaves sustained hypertension unaddressed and increases variability.
B. Target systolic BP below 110 to prevent recurrent rupture (Why this does not fit)
The recommended long-term approach is not maximal lowering; excessive reduction risks adverse effects without established added benefit here.
Reasoning steps for option B
Is this an acute expansion or long-term prevention decision?
Long-term prevention, six months after ICH.
Which findings support adjusting daily treatment?
Persistent hypertension despite adherence, without orthostatic symptoms or renal instability.
Does this option account for the supplied conditions?
The recommended long-term approach is not maximal lowering; excessive reduction risks adverse effects without established added benefit here.
C. Accept the current BP because acute hematoma expansion is no longer possible (Why this does not fit)
Resolving the initial clot does not eliminate the risk from chronic hypertension.
Reasoning steps for option C
Is this an acute expansion or long-term prevention decision?
Long-term prevention, six months after ICH.
Which findings support adjusting daily treatment?
Persistent hypertension despite adherence, without orthostatic symptoms or renal instability.
Does this option account for the supplied conditions?
Resolving the initial clot does not eliminate the risk from chronic hypertension.
D. Adjust a tolerable daily regimen toward approximately 130/80 with follow-up (Best answer)
Persistent hypertension remains modifiable; the absence of orthostatic symptoms supports cautious intensification with monitoring toward the long-term target.
Reasoning steps for option D
Is this an acute expansion or long-term prevention decision?
Long-term prevention, six months after ICH.
Which findings support adjusting daily treatment?
Persistent hypertension despite adherence, without orthostatic symptoms or renal instability.
Does this option account for the supplied conditions?
Persistent hypertension remains modifiable; the absence of orthostatic symptoms supports cautious intensification with monitoring toward the long-term target.
Takeaway: Use recovery-stage BP, tolerance and adherence to plan sustained prevention rather than importing acute-care thresholds.
A. Small-vessel arteriolosclerosis causing both hemorrhagic and ischemic tissue injury (Best answer)
Deep hemorrhagic markers, lacunar cavities and white-matter injury support a shared small-vessel process contributing to vascular cognitive impairment.
Reasoning steps for option A
Do the MRI findings show only hemorrhagic injury?
No. White-matter changes and small deep cavities also support ischemic small-vessel injury.
How can one vessel process explain the cognitive course?
Deep arteriolosclerosis can cause both hemorrhages and accumulating ischemic damage affecting executive function.
Does this option account for the supplied conditions?
Deep hemorrhagic markers, lacunar cavities and white-matter injury support a shared small-vessel process contributing to vascular cognitive impairment.
B. Obstructive hydrocephalus caused by a persistent ventricular clot (Why this does not fit)
No ventricular obstruction or enlargement is described; the structural pattern is diffuse small-vessel injury.
Reasoning steps for option B
Do the MRI findings show only hemorrhagic injury?
No. White-matter changes and small deep cavities also support ischemic small-vessel injury.
How can one vessel process explain the cognitive course?
Deep arteriolosclerosis can cause both hemorrhages and accumulating ischemic damage affecting executive function.
Does this option account for the supplied conditions?
No ventricular obstruction or enlargement is described; the structural pattern is diffuse small-vessel injury.
C. A new focal hemorrhagic tumor causing the remote deep lesions (Why this does not fit)
A focal tumor would not readily explain distributed microbleeds, deep cavities and confluent small-vessel white-matter injury.
Reasoning steps for option C
Do the MRI findings show only hemorrhagic injury?
No. White-matter changes and small deep cavities also support ischemic small-vessel injury.
How can one vessel process explain the cognitive course?
Deep arteriolosclerosis can cause both hemorrhages and accumulating ischemic damage affecting executive function.
Does this option account for the supplied conditions?
A focal tumor would not readily explain distributed microbleeds, deep cavities and confluent small-vessel white-matter injury.
D. Amyloid angiopathy confined to cortical vessels as the sole explanation (Why this does not fit)
Strictly cortical amyloid disease fits lobar markers better than this combined deep hemorrhagic and ischemic pattern.
Reasoning steps for option D
Do the MRI findings show only hemorrhagic injury?
No. White-matter changes and small deep cavities also support ischemic small-vessel injury.
How can one vessel process explain the cognitive course?
Deep arteriolosclerosis can cause both hemorrhages and accumulating ischemic damage affecting executive function.
Does this option account for the supplied conditions?
Strictly cortical amyloid disease fits lobar markers better than this combined deep hemorrhagic and ischemic pattern.
Takeaway: Prior hemorrhage does not mean all later impairment is another bleed; the same vessels can also produce ischemic injury.
A. Use the average recurrence risk of deep hypertensive ICH to select a restart date (Why this does not fit)
Deep and lobar etiologies carry different risks; MRI findings cannot be ignored when applying recurrence estimates.
Reasoning steps for option A
What do strictly lobar markers and siderosis suggest?
CAA-related hemorrhagic vulnerability.
Why is stopping or restarting anticoagulation not automatic?
AF with prior embolic TIA supplies an important competing risk while BP remains modifiable.
Does this option account for the supplied conditions?
Deep and lobar etiologies carry different risks; MRI findings cannot be ignored when applying recurrence estimates.
B. Improve BP and jointly reassess hemorrhagic and embolic risks before choosing stroke prevention (Best answer)
The MRI suggests CAA-related recurrence risk, hypertension is modifiable, and AF with prior TIA carries competing embolic risk. A shared individualized decision is needed.
Reasoning steps for option B
What do strictly lobar markers and siderosis suggest?
CAA-related hemorrhagic vulnerability.
Why is stopping or restarting anticoagulation not automatic?
AF with prior embolic TIA supplies an important competing risk while BP remains modifiable.
Does this option account for the supplied conditions?
The MRI suggests CAA-related recurrence risk, hypertension is modifiable, and AF with prior TIA carries competing embolic risk. A shared individualized decision is needed.
C. Restart anticoagulation on the assumption that correcting BP normalizes lobar recurrence risk (Why this does not fit)
BP treatment is important but does not eliminate amyloid-related vessel fragility.
Reasoning steps for option C
What do strictly lobar markers and siderosis suggest?
CAA-related hemorrhagic vulnerability.
Why is stopping or restarting anticoagulation not automatic?
AF with prior embolic TIA supplies an important competing risk while BP remains modifiable.
Does this option account for the supplied conditions?
BP treatment is important but does not eliminate amyloid-related vessel fragility.
D. Select a fixed anticoagulation restart interval from the embolic-risk score without incorporating MRI markers (Why this does not fit)
The embolic indication is important, but the hemorrhagic MRI phenotype and BP must also enter individualized timing and treatment decisions.
Reasoning steps for option D
What do strictly lobar markers and siderosis suggest?
CAA-related hemorrhagic vulnerability.
Why is stopping or restarting anticoagulation not automatic?
AF with prior embolic TIA supplies an important competing risk while BP remains modifiable.
Does this option account for the supplied conditions?
The embolic indication is important, but the hemorrhagic MRI phenotype and BP must also enter individualized timing and treatment decisions.
Takeaway: A high-risk hemorrhagic pattern and an important embolic indication require individualized assessment, not one universal restart rule.