Connect placental position, separation, maternal-fetal physiology, safe workup, delivery route, hemorrhage care, and accreta-spectrum planning.
The central decision is to separate placental position from placental separation, then follow maternal and fetal physiology before choosing a test or a birth route. A small visible stain can hide major maternal hemorrhage, while dramatic fetal deterioration after membrane rupture may represent blood loss from the fetal circulation.
Step and Level 1 explains uteroplacental blood flow, the maternal and fetal compartments, vasoconstriction, separation, and coagulation. Step and Level 2 uses presentation, examination safety, imaging limits, and immediate management. Step and Level 3 adds surveillance, route, recurrence, postpartum risk, and placenta accreta spectrum planning. Beyond the examinations, the lesson names guideline windows, referral thresholds, counseling, and medication details that must be verified against current labeling and the treating institution's protocol.
Position is different from attachment
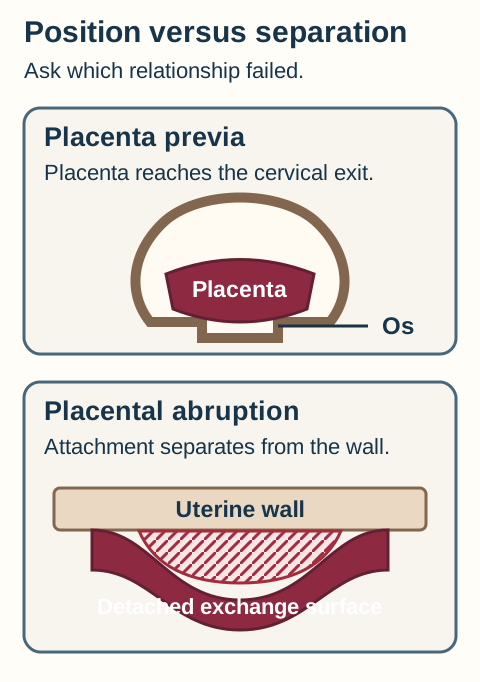
Placenta previa describes position: placental tissue reaches or covers the internal cervical os, the opening between the uterine cavity and cervical canal. A noncovering edge within 20 mm is commonly described as low-lying. Position can change as the lower uterine segment develops, so an early label does not permanently determine the route of birth. [1][14]
Previa changes the relationship to the birth route. Abruption changes the attachment and exchange surface. Original Bone Wizardry schematic; not a clinical image. View the full-size diagram.
Placental abruption describes attachment: a normally implanted placenta separates before birth. Maternal blood can collect in the decidual interface, reduce the attached exchange surface, and stimulate thrombin-related uterine irritability. Pain, tenderness, frequent contractions, or sustained high tone support the pattern, but a small or chronic separation can be subtler. [2][7]
The circulations remain distinct. Maternal blood enters the intervillous space through uterine spiral arteries and bathes the outside of chorionic villi. Fetal blood remains inside villous capillaries. Ordinary bleeding from previa or abruption is therefore primarily maternal, although impaired maternal perfusion or loss of exchange surface can rapidly compromise the fetus.
Think low resistance and high flow. The placenta depends on sustained maternal perfusion across a broad exchange surface. A fall in maternal pressure, arterial constriction, or physical separation can reduce oxygen delivery even when no fetal vessel has ruptured. The fetal heart tracing reflects the consequence of impaired delivery, not a disease-specific label.
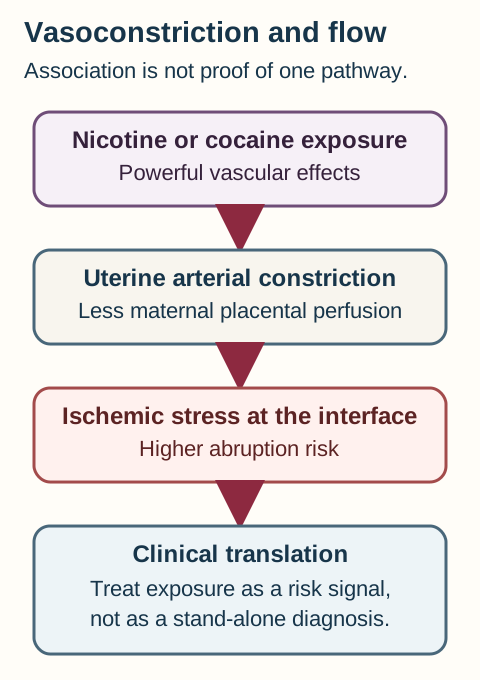
Vasoconstrictive exposure raises suspicion through impaired maternal perfusion, but current physiology still determines diagnosis and urgency. Original Bone Wizardry schematic; not a clinical image. View the full-size diagram.
Nicotine and cocaine have clinically important vascular effects. Smoking is associated with both placenta previa and abruption, while cocaine exposure has a strong association with abruption. Vasoconstriction offers a coherent path from exposure to impaired maternal placental perfusion, but exposure alone does not diagnose separation and does not prove one universal placental-growth adaptation. [11][12][17]
Risk adjusts suspicion, not certainty. Prior previa, uterine surgery, increasing parity, multiple gestation, and smoking increase concern for low implantation. Chronic hypertension, preeclampsia, prior abruption, trauma, smoking, cocaine exposure, and rapid uterine decompression increase concern for separation. The current maternal and fetal trajectory still determines urgency. [7][12]
Retrieval check: coverage can obstruct a vaginal birth route even when exchange is intact, whereas separation can impair exchange while leaving the cervical route anatomically open. Name the failed relationship before naming the management consequence.
Try it here · Checkpoint 1 of 3
Make your prediction before reading the choices. A first attempt is just a starting point.
Case 3
Show answer and explanations for case 3
A. Rupture of maternal cervical ectropion vessels (Why this does not fit)
Cervical ectropion can produce maternal bleeding and is a credible lower-tract source. Direct visual examination found no cervical or vaginal lesion, while known placental coverage and bleeding during cervical change point to the placental attachment instead.
Reasoning steps for option A
For ppa-03 option A, which two findings must be reconciled before accepting this choice?
For ppa-03, option A may initially fit no lower-tract lesion, but it also must explain normal neonatal hemoglobin.
For ppa-03 option A, what comparison determines whether this choice outranks the alternatives?
Option A falls behind in ppa-03 because the combined pattern is better resolved by localize ordinary previa bleeding to the maternal uteroplacental compartment..
B. Disruption of the maternal uteroplacental vascular bed (Best answer)
Maternal blood normally fills the intervillous space around fetal villi. Bleeding with cervical change in previa can disrupt that maternal bed, explaining the maternal hemoglobin fall while the newborn avoids primary blood-loss anemia.
Reasoning steps for option B
For ppa-03 option B, which two findings must be reconciled before accepting this choice?
In ppa-03, option B must account for no lower-tract lesion while remaining consistent with maternal hemoglobin fall.
For ppa-03 option B, what comparison determines whether this choice outranks the alternatives?
Option B remains preferred in ppa-03 because use the absent lower-tract lesion and known coverage to localize the maternal source
C. Rupture of fetal capillaries inside chorionic villi (Why this does not fit)
Villous capillaries contain fetal blood. Their rupture would threaten the newborn's circulating volume, which is inconsistent with the normal neonatal hemoglobin and the documented maternal blood loss.
Reasoning steps for option C
For ppa-03 option C, which two findings must be reconciled before accepting this choice?
For ppa-03, option C may initially fit no lower-tract lesion, but it also must explain normal neonatal hemoglobin.
For ppa-03 option C, what comparison determines whether this choice outranks the alternatives?
Option C falls behind in ppa-03 because the combined pattern is better resolved by localize ordinary previa bleeding to the maternal uteroplacental compartment..
D. Tearing of unprotected fetal vessels over the cervix (Why this does not fit)
Vasa previa can cause rapid fetal hemorrhage after membrane rupture. The stem instead supplies maternal blood loss, no primary neonatal anemia, and no membrane-rupture event.
Reasoning steps for option D
For ppa-03 option D, which two findings must be reconciled before accepting this choice?
For ppa-03, option D may initially fit no lower-tract lesion, but it also must explain normal neonatal hemoglobin.
For ppa-03 option D, what comparison determines whether this choice outranks the alternatives?
Option D falls behind in ppa-03 because the combined pattern is better resolved by localize ordinary previa bleeding to the maternal uteroplacental compartment..
Takeaway: Maternal blood surrounds the villi; fetal blood is inside their capillaries.
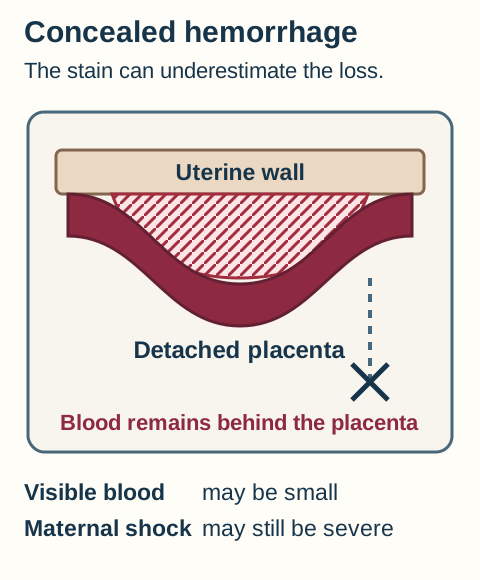
Visible blood is not total blood. A retroplacental hematoma may remain behind the placenta rather than draining through the cervix. Tachycardia, narrowing pulse pressure, hypotension, altered mentation, uterine findings, and fetal deterioration can be more informative than the amount on a pad. Early hemoglobin may also remain near baseline before equilibration or fluid administration changes the concentration. [2][7]
A closed drainage path changes what is visible, not the amount of placental separation. Original Bone Wizardry schematic; not a clinical image. View the full-size diagram.
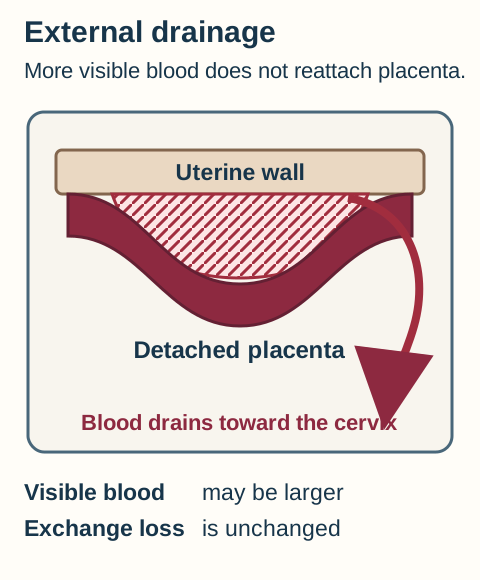
Hold the injury constant. In the concealed model, maternal blood has no open exit. If a path toward the cervix opens, more blood becomes visible, but the same placental area remains detached and the lost exchange surface is not restored.
Compare an open drainage path
Opening the outlet changes visibility without repairing placental attachment. Original Bone Wizardry schematic; not a clinical image. View the full-size diagram.
The counterfactual result is more external bleeding with unchanged attachment. This is a teaching model, not a procedure and not a quantitative estimate of blood loss.
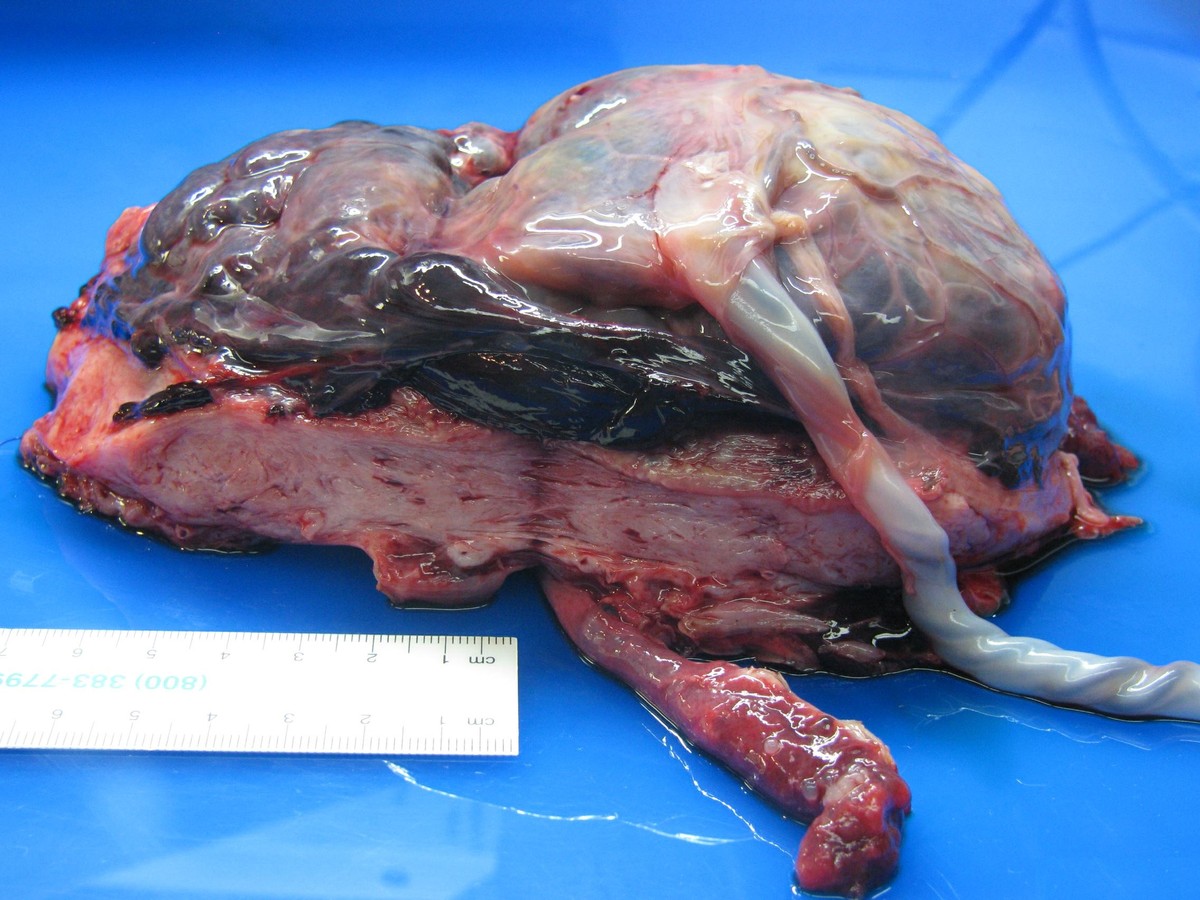
Gross specimen showing a retroplacental hematoma at a separated placental interface. This is a pathology photograph, not a living-patient examination image. Mikael Häggström, CC0 1.0; metadata removed and image resized for publication.
The pathology image shows what the diagrams abstract: a dark hematoma occupies the interface between placenta and uterine wall. A living patient can have a clinically important separation without a collection that is visible on ultrasound, and the gross specimen does not establish how much blood was externally visible.
Fetal monitoring reports physiology. Recurrent late decelerations suggest reduced oxygen delivery during contractions. Persistent bradycardia can indicate severe compromise. A reassuring tracing does not exclude a small abruption, and major maternal hemorrhage from previa can also produce late decelerations through maternal hypotension. [2][7]
Vasa previa changes whose blood is lost. Unprotected fetal vessels traverse membranes near or across the cervix. Membrane rupture can tear them, causing bleeding followed by abrupt fetal bradycardia while maternal blood pressure and pulse initially remain stable. A modest visible volume can be catastrophic for a fetus because the fetal circulating volume is small. [6]
Use the differential effect. Maternal shock with scant visible blood and a tender uterus favors concealed maternal hemorrhage. Bleeding immediately after membrane rupture with severe fetal collapse and preserved maternal circulation raises concern for fetal-vessel hemorrhage. Both patterns demand action before the visible volume looks dramatic.
Stabilize first, then ask what each test can answer
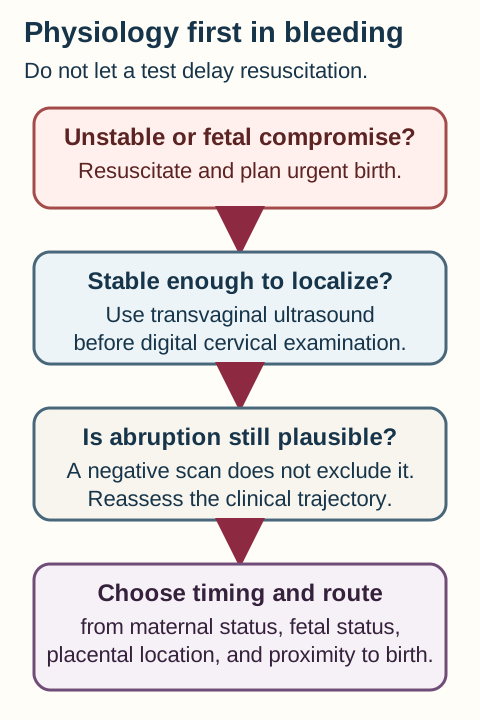
Resuscitation comes before optional confirmation. In significant hemorrhage, assess airway, breathing, circulation, mental status, and ongoing loss; obtain large-bore intravenous access; activate obstetric, anesthesia, neonatal, and blood-bank support as appropriate; and provide indicated blood products. Fetal assessment and delivery planning proceed in parallel when they can guide care. Imaging must not postpone treatment of shock. [2][3]
Resuscitation precedes optional confirmation. Transvaginal localization answers a different question from clinical assessment of abruption. Original Bone Wizardry schematic; not a clinical image. View the full-size diagram.
Transvaginal ultrasound localizes the edge in a sufficiently stable patient. It is more accurate than transabdominal imaging for the relation between placenta and internal os and is considered safe when performed appropriately. The probe need not enter the cervical canal. [1]
Digital cervical examination waits while previa remains possible because palpation can disrupt vascular placental tissue over the os. A careful speculum examination is not the same procedure: when the patient and setting permit, visual inspection can identify a cervical or vaginal source. Do not convert a prohibition on digital palpation into a blanket prohibition on all visual examination. [2]
Ultrasound does not rule out abruption. Fresh blood may resemble placental tissue, a collection may be small or concealed in a difficult plane, and the image changes with time. A negative scan cannot cancel evolving tenderness, high tone, maternal perfusion failure, or fetal compromise. [7]
Laboratory work answers parallel questions. A complete blood count and crossmatch help prepare for hemorrhage; prothrombin time, activated partial thromboplastin time, fibrinogen, and platelets assess hemostatic depletion; renal and metabolic testing may reflect shock severity. A fetal-cell assay addresses fetomaternal hemorrhage and anti-D prophylaxis, not the size of a maternal retroplacental hematoma.
The time budget changes the sequence. A stable patient with painless bleeding and unknown placental location can undergo focused localization before digital examination. A patient with worsening perfusion and persistent fetal bradycardia needs emergency treatment even when the scan shows no clot.
Try it here · Checkpoint 2 of 3
Make your prediction before reading the choices. A first attempt is just a starting point.
Case 6
Show answer and explanations for case 6
A. Begin a brief tocolytic trial while repeating fetal corrective measures (Why this does not fit)
Contraction suppression does not treat the separated interface, and this term fetus has persistent bradycardia. A time-limited trial would delay indicated birth.
Reasoning steps for option A
For ppa-06 option A, which two findings must be reconciled before accepting this choice?
For ppa-06, option A may initially fit tender high-tone uterus, but it also must explain cervix remote from birth with negative ultrasound.
For ppa-06 option A, what comparison determines whether this choice outranks the alternatives?
Option A falls behind in ppa-06 because the combined pattern is better resolved by act on clinical abruption with persistent fetal compromise despite negative ultrasound..
B. Prepare operative delivery but wait for laboratory confirmation of coagulopathy (Why this does not fit)
Coagulation tests guide component support, not whether persistent fetal compromise with a cervix remote from birth requires delivery. Preparation and resuscitation can proceed without waiting.
Reasoning steps for option B
For ppa-06 option B, which two findings must be reconciled before accepting this choice?
For ppa-06, option B may initially fit tender high-tone uterus, but it also must explain cervix remote from birth with negative ultrasound.
For ppa-06 option B, what comparison determines whether this choice outranks the alternatives?
Option B falls behind in ppa-06 because the combined pattern is better resolved by act on clinical abruption with persistent fetal compromise despite negative ultrasound..
C. Proceed with urgent cesarean while continuing hemorrhage management (Best answer)
The clinical pattern supports severe abruption despite negative ultrasound. Persistent bradycardia and a cervix remote from vaginal birth make urgent cesarean the feasible rescue route.
Reasoning steps for option C
For ppa-06 option C, which two findings must be reconciled before accepting this choice?
In ppa-06, option C must account for tender high-tone uterus while remaining consistent with persistent fetal bradycardia.
For ppa-06 option C, what comparison determines whether this choice outranks the alternatives?
Option C remains preferred in ppa-06 because choose the response that addresses that problem within the stated time budget for ppa-06.
D. Attempt rapid induction because prior imaging excluded placental coverage (Why this does not fit)
A clear os makes vaginal birth anatomically possible but does not make it imminent. With the cervix at 2 cm and persistent fetal bradycardia, induction is too slow.
Reasoning steps for option D
For ppa-06 option D, which two findings must be reconciled before accepting this choice?
For ppa-06, option D may initially fit tender high-tone uterus, but it also must explain cervix remote from birth with negative ultrasound.
For ppa-06 option D, what comparison determines whether this choice outranks the alternatives?
Option D falls behind in ppa-06 because the combined pattern is better resolved by act on clinical abruption with persistent fetal compromise despite negative ultrasound..
Takeaway: A negative ultrasound cannot overrule persistent fetal compromise with a convincing abruption presentation.
A changing laboratory pattern can expose concealed harm
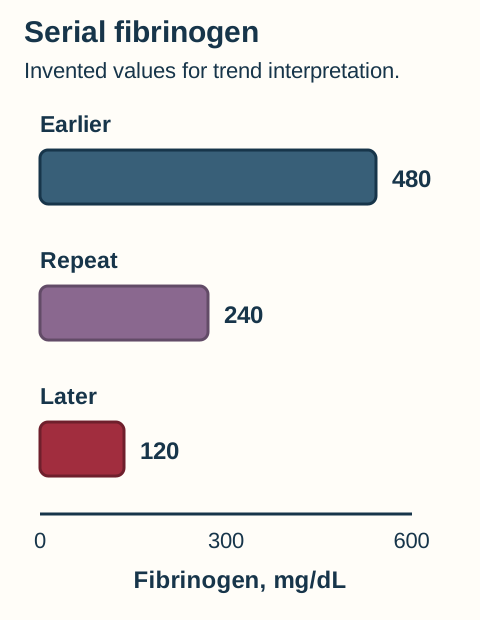
Pregnancy raises fibrinogen, so a value inside an adult reference interval can represent a major decline. Read the direction of change beside platelets, clotting times, bleeding, and the maternal trajectory. No isolated fibrinogen value establishes the entire diagnosis of disseminated intravascular coagulation. [8]
The middle value is half the earlier concentration. Pregnancy context and the direction of change matter before a value becomes severely low. Original Bone Wizardry schematic; not a clinical image. View the full-size diagram.
The invented series falls from 480 to 240 to 120 mg/dL. The middle value is already half the earlier concentration even though some adult laboratories would still print it near their reference interval. The final value is severely low, but the lesson is the trend rather than a universal trigger.
Placental injury can activate coagulation. Tissue factor exposure and widespread thrombin generation may consume fibrinogen, platelets, and other factors while hemorrhage continues. Falling fibrinogen and platelets with prolonged clotting times and bleeding from puncture sites increase concern for consumptive coagulopathy. [2][8]
Replace the affected components. Red cells restore oxygen-carrying capacity but not every consumed hemostatic element. Plasma provides multiple clotting factors, cryoprecipitate or a locally available fibrinogen product addresses fibrinogen depletion, and platelets address clinically important thrombocytopenia. Use the institution's obstetric hemorrhage protocol while controlling the source and planning indicated birth.
Do not normalize before acting. Component replacement, uterine source control, and delivery planning often occur together. The goal is not to delay necessary birth until every laboratory value is normal; it is to restore perfusion and hemostasis while ending the process that is sustaining hemorrhage.
Rhesus D prophylaxis is a separate branch. For an unsensitized rhesus D-negative patient, a new bleeding event may require anti-D prophylaxis even after routine antenatal prophylaxis. A Kleihauer-Betke test or the locally used quantitative method estimates fetal blood in maternal circulation to guide any additional dose. Verify dosing against current labeling and local policy; the assay does not diagnose abruption or measure concealed maternal blood. [2]
Beyond the examination, early coordination with transfusion medicine, anesthesia, critical care, and the operative team becomes appropriate when bleeding is ongoing, shock is developing, fibrinogen is falling, or placenta accreta spectrum is possible. A local massive-transfusion pathway is safer than an improvised universal product ratio.
Urgency and route are separate decisions
The diagnosis does not select both answers. First decide whether birth is needed now from maternal stability, continuing bleeding, fetal condition, gestational age, and the trajectory. Then choose the fastest safe route from placental position, cervical progress, fetal viability, presentation, prior uterine surgery, and operative risk.
Physiology and anatomy determine different parts of the plan
Situation
Reasoned direction
SituationPlacenta still covers the os
Reasoned directionCesarean route; timing depends on bleeding, labor, and maternal-fetal status.
SituationAbruption with a live compromised fetus and vaginal birth not imminent
Reasoned directionUrgent cesarean while resuscitation continues.
SituationAbruption with fetal death and a stable mother
Reasoned directionVaginal birth is often favored if no obstetric contraindication exists, with close hemorrhage and coagulation surveillance.
SituationMild suspected preterm abruption with stable assessments
Reasoned directionMonitored expectant care may be reasonable; any deterioration changes the plan.
Stable previa can be planned. For uncomplicated persistent previa without bleeding or another obstetric complication, ACOG-endorsed guidance recommends delivery from 36 0/7 through 37 6/7 weeks. Recurrent or active bleeding can justify earlier birth, and major hemorrhage is an emergency rather than a scheduling problem. [3]
Low-lying is not identical to covering. Accessible patient guidance treats an edge under 20 mm at 36 weeks as favoring cesarean, while systematic review and prospective evidence show that selected patients with a noncovering edge, especially 11 to 20 mm, can achieve vaginal birth after detailed counseling in a setting ready for emergency cesarean and transfusion. This is an individualized discussion, not a guarantee or a universal invitation to labor. [13][14][18]
Stable preterm bleeding may allow time. When bleeding stops, maternal observations and serial laboratories remain stable, fetal assessment is reassuring, and labor is absent, monitored expectant care can balance placental risk against prematurity. The plan must specify return precautions, transport, recurrent-bleeding response, fetal surveillance, anemia treatment, and access to urgent birth.
Corticosteroids support maturation, not acute rescue. A standard late-preterm course for an eligible singleton at 34 0/7 through 36 6/7 weeks who is likely to deliver within seven days and has not received a prior course is betamethasone 12 mg intramuscularly every 24 hours for two doses. Verify against current labeling and the treating protocol. Do not give it when delivery is unlikely, do not routinely use it in pregestational diabetes under the cited guidance, and do not delay indicated delivery to finish the course. [3][5]
Abruption route follows feasibility. Continuing major hemorrhage, maternal deterioration, or persistent fetal compromise requires expeditious birth. A live compromised fetus with a cervix remote from delivery usually requires cesarean. If vaginal birth is imminent, it may be fastest. After confirmed fetal death, vaginal delivery often avoids additional operative bleeding when maternal and obstetric conditions permit. [2]
Strict bed rest is not a treatment. Individualize advice about activity, vaginal penetration, travel, work, and when to return. Routine activity restriction has weak benefit evidence and can produce physical, thrombotic, financial, and psychosocial harm. Hospital observation for a real hemorrhage risk is different from prescribing immobilization as therapy. [10]
A scar changes the placental interface
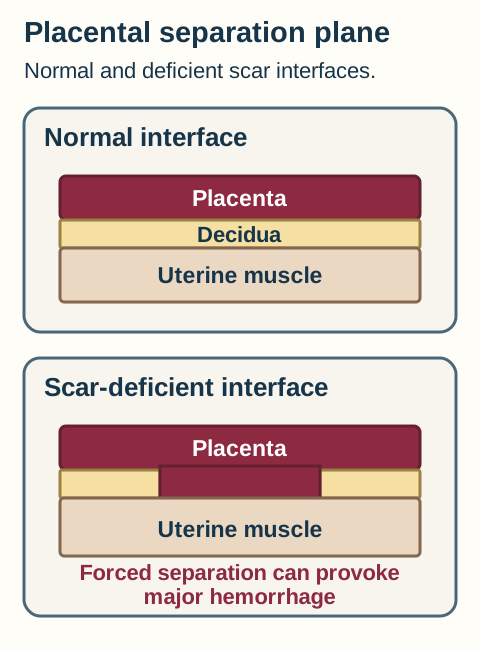
Placenta accreta spectrum becomes more likely when a low anterior placenta overlies a prior cesarean scar. The normal decidual separation plane may be deficient, and scar dehiscence or remodeling can bring placental tissue into direct contact with myometrium. This is abnormal attachment, not merely another name for previa or abruption. [4]
A deficient separation plane explains why attempted placental removal can trigger major hemorrhage in placenta accreta spectrum. Original Bone Wizardry schematic; not a clinical image. View the full-size diagram.
Imaging refines risk. Expert ultrasound, including Doppler and transvaginal assessment when appropriate, can identify placental lacunae, abnormal vascular patterns, and a disrupted interface. A negative or incomplete nonexpert scan does not erase a high-risk history. Magnetic resonance imaging can answer selected anatomic questions but should not automatically replace available expert ultrasound. [1][4]
Traditional pathology terms describe depth. Accreta denotes abnormal attachment at superficial myometrium, increta denotes villi extending into myometrium, and percreta denotes extension through the uterine wall toward or beyond serosa. Imaging suspicion and operative nonseparation are clinically important even before a final microscopic label is available.
Do not test the plane by force. During a planned cesarean hysterectomy for suspected placenta accreta spectrum, the fetus is delivered through an incision that avoids the placenta, and the placenta is generally left in situ. Attempted removal can tear the vascular interface and provoke catastrophic hemorrhage. [4]
Plan at an experienced center. A multidisciplinary team, immediately available blood products, appropriate anesthesia and critical-care capability, neonatal support, and a documented operative strategy improve readiness. Stable suspected placenta accreta spectrum is commonly planned for 34 0/7 through 35 6/7 weeks under ACOG and SMFM guidance, individualized for bleeding, labor, membrane rupture, fetal concerns, and local expertise. [4][15]
After any substantial hemorrhage, continue surveillance for recurrent bleeding, anemia, transfusion complications, postpartum hemorrhage, renal or ischemic injury, and emotional consequences. Abruption can also affect fetal growth during an ongoing pregnancy, so follow-up does not end when the visible bleeding stops.
Prevention means risk reduction, not a promise. Control chronic hypertension, support tobacco and nicotine cessation, counsel against cocaine and other vasoactive substances, review prior placental history early in the next pregnancy, and arrange timely placental localization. A prior abruption increases recurrence risk and warrants preconception and early obstetric counseling. [7][11]
Referral becomes urgent with recurrent bleeding, maternal instability, fetal compromise, falling fibrinogen, suspected placenta accreta spectrum, uncertain placental location before examination, or a birth route that may require resources unavailable locally. Beyond-level judgment is often the recognition that the safest next action is coordinated transfer before a predictable crisis.
Try it here · Checkpoint 3 of 3
Make your prediction before reading the choices. A first attempt is just a starting point.
Case 22
Show answer and explanations for case 22
A. Continue stronger cord traction until the placenta releases (Why this does not fit)
Unexpected nonseparation at a scar interface is a warning for abnormal attachment. Increasing force can enlarge the vascular injury and worsen hemorrhage.
Reasoning steps for option A
For ppa-22 option A, which two findings must be reconciled before accepting this choice?
For ppa-22, option A may initially fit indeterminate preoperative interface, but it also must explain brisk scar-interface bleeding.
For ppa-22 option A, what comparison determines whether this choice outranks the alternatives?
Option A falls behind in ppa-22 because the combined pattern is better resolved by respond to unexpected nonseparation and bleeding as operative accreta spectrum..
B. Close the uterus and observe without activating hemorrhage support (Why this does not fit)
Brisk bleeding is already present, so observation without a coordinated hemorrhage response is unsafe. The uncertain interface now has an operative consequence.
Reasoning steps for option B
For ppa-22 option B, which two findings must be reconciled before accepting this choice?
For ppa-22, option B may initially fit indeterminate preoperative interface, but it also must explain brisk scar-interface bleeding.
For ppa-22 option B, what comparison determines whether this choice outranks the alternatives?
Option B falls behind in ppa-22 because the combined pattern is better resolved by respond to unexpected nonseparation and bleeding as operative accreta spectrum..
C. Stop separation attempts and activate the placenta accreta hemorrhage plan (Best answer)
Failure to separate at the scar plus brisk bleeding should be treated as suspected placenta accreta spectrum. Avoid further disruption while escalating to the prepared multidisciplinary strategy.
Reasoning steps for option C
For ppa-22 option C, which two findings must be reconciled before accepting this choice?
In ppa-22, option C must account for indeterminate preoperative interface while remaining consistent with placenta does not separate.
For ppa-22 option C, what comparison determines whether this choice outranks the alternatives?
Option C remains preferred in ppa-22 because stop disruption and escalate hemorrhage control before pursuing a microscopic label
D. Curette the interface to obtain tissue before changing the operative plan (Why this does not fit)
Additional instrumentation can disrupt the vascular attachment and does not need to precede hemorrhage control. Histologic classification is secondary to maternal safety.
Reasoning steps for option D
For ppa-22 option D, which two findings must be reconciled before accepting this choice?
For ppa-22, option D may initially fit indeterminate preoperative interface, but it also must explain brisk scar-interface bleeding.
For ppa-22 option D, what comparison determines whether this choice outranks the alternatives?
Option D falls behind in ppa-22 because the combined pattern is better resolved by respond to unexpected nonseparation and bleeding as operative accreta spectrum..
Takeaway: Placental position, separation, and depth of attachment describe different relationships.
Independent practice now removes the guided prompts. Each case requires a single best answer from the supplied findings, and every option includes its own explanation after commitment.
Case 1
Show answer and explanations for case 1
A. Transvaginal ultrasound localization (Best answer)
Transvaginal imaging can define the placental edge without passing through the cervical canal. Placental coverage remains unresolved, and maternal and fetal stability permit targeted imaging. An inconclusive abdominal scan does not clear the os for digital examination.
Reasoning steps for option A
For ppa-01 option A, which two findings must be reconciled before accepting this choice?
In ppa-01, option A must account for stable maternal and fetal assessment while remaining consistent with placental edge unresolved on transabdominal imaging.
For ppa-01 option A, what comparison determines whether this choice outranks the alternatives?
Option A remains preferred in ppa-01 because choose the response that addresses that problem within the stated time budget for ppa-01.
B. Pelvic magnetic resonance imaging localization as the initial definitive test (Why this does not fit)
magnetic resonance imaging can clarify selected complex placental anatomy. The unresolved issue is edge localization, for which transvaginal ultrasound is the appropriate next assessment. Reserve additional imaging for a question not adequately answered by suitable ultrasound.
Reasoning steps for option B
For ppa-01 option B, which two findings must be reconciled before accepting this choice?
For ppa-01, option B may initially fit stable maternal and fetal assessment, but it also must explain digital examination not yet safe.
For ppa-01 option B, what comparison determines whether this choice outranks the alternatives?
Option B falls behind in ppa-01 because the combined pattern is better resolved by select safe placental localization before digital examination in a stable bleeding patient..
C. Digital assessment of dilation under ultrasound guidance (Why this does not fit)
Cervical dilation can influence delivery planning. Guidance does not eliminate the risk of touching a placenta whose relationship to the os remains undefined. Localize the placental edge before digital palpation when previa is possible.
Reasoning steps for option C
For ppa-01 option C, which two findings must be reconciled before accepting this choice?
For ppa-01, option C may initially fit stable maternal and fetal assessment, but it also must explain digital examination not yet safe.
For ppa-01 option C, what comparison determines whether this choice outranks the alternatives?
Option C falls behind in ppa-01 because the combined pattern is better resolved by select safe placental localization before digital examination in a stable bleeding patient..
D. Kleihauer-Betke testing to establish the source (Why this does not fit)
A fetal-cell assay can help estimate fetomaternal hemorrhage. It does not show whether placental tissue covers the cervix in this stable patient. Choose a test that answers the anatomic safety question.
Reasoning steps for option D
For ppa-01 option D, which two findings must be reconciled before accepting this choice?
For ppa-01, option D may initially fit stable maternal and fetal assessment, but it also must explain digital examination not yet safe.
For ppa-01 option D, what comparison determines whether this choice outranks the alternatives?
Option D falls behind in ppa-01 because the combined pattern is better resolved by select safe placental localization before digital examination in a stable bleeding patient..
Takeaway: Define placental location before digital examination, without delaying resuscitation when needed.
A. Activate hemorrhage resuscitation while arranging urgent cesarean delivery (Best answer)
Persistent placental coverage obstructs the vaginal route, and continuing bleeding with shock makes waiting unsafe. Maternal resuscitation and urgent delivery planning should occur together.
Reasoning steps for option A
For ppa-02 option A, which two findings must be reconciled before accepting this choice?
In ppa-02, option A must account for known placental coverage while remaining consistent with continuous hemorrhage.
For ppa-02 option A, what comparison determines whether this choice outranks the alternatives?
Option A remains preferred in ppa-02 because choose the response that addresses that problem within the stated time budget for ppa-02.
B. Begin massive-transfusion support but defer delivery until blood pressure normalizes (Why this does not fit)
Transfusion is essential, but the ongoing placental source will not be controlled by reaching a normal pressure first. Source control and resuscitation must proceed in parallel.
Reasoning steps for option B
For ppa-02 option B, which two findings must be reconciled before accepting this choice?
For ppa-02, option B may initially fit known placental coverage, but it also must explain maternal shock.
For ppa-02 option B, what comparison determines whether this choice outranks the alternatives?
Option B falls behind in ppa-02 because the combined pattern is better resolved by prioritize simultaneous hemorrhage resuscitation and urgent birth in unstable placenta previa..
C. Perform bedside transvaginal ultrasound before activating the hemorrhage team (Why this does not fit)
Placental coverage is already documented, and the patient is in shock. Repeat localization cannot improve immediate care enough to justify delaying resuscitation.
Reasoning steps for option C
For ppa-02 option C, which two findings must be reconciled before accepting this choice?
For ppa-02, option C may initially fit known placental coverage, but it also must explain maternal shock.
For ppa-02 option C, what comparison determines whether this choice outranks the alternatives?
Option C falls behind in ppa-02 because the combined pattern is better resolved by prioritize simultaneous hemorrhage resuscitation and urgent birth in unstable placenta previa..
D. Obtain a complete fetal tracing before requesting blood products (Why this does not fit)
Fetal assessment informs delivery, but maternal confusion and profound hypotension already establish a life-threatening emergency. Blood support is not contingent on first recording a complete tracing.
Reasoning steps for option D
For ppa-02 option D, which two findings must be reconciled before accepting this choice?
For ppa-02, option D may initially fit known placental coverage, but it also must explain maternal shock.
For ppa-02 option D, what comparison determines whether this choice outranks the alternatives?
Option D falls behind in ppa-02 because the combined pattern is better resolved by prioritize simultaneous hemorrhage resuscitation and urgent birth in unstable placenta previa..
Takeaway: Maternal shock establishes an immediate treatment priority even before a full fetal assessment is available.
A. Recommend cesarean because any edge within 20 mm constitutes coverage (Why this does not fit)
Proximity to the cervix warrants attention to hemorrhage and route. The measured 18 mm gap explicitly excludes coverage in this study. Preserve the difference between a low-lying edge and placenta previa.
Reasoning steps for option A
For ppa-04 option A, which two findings must be reconciled before accepting this choice?
For ppa-04, option A may initially fit noncovering 18 mm edge, but it also must explain immediate operative and transfusion support.
For ppa-04 option A, what comparison determines whether this choice outranks the alternatives?
Option A falls behind in ppa-04 because the combined pattern is better resolved by counsel about a selected trial of labor for a noncovering low-lying placenta..
B. Use magnetic resonance imaging evidence of placental maturity to determine eligibility for labor (Why this does not fit)
Additional imaging can address selected complex placental questions. Neither placental maturity on magnetic resonance imaging nor another scan substitutes for the relevant edge distance, history, and resources. Choose route using clinical and anatomic factors rather than an unrelated imaging target.
Reasoning steps for option B
For ppa-04 option B, which two findings must be reconciled before accepting this choice?
For ppa-04, option B may initially fit noncovering 18 mm edge, but it also must explain immediate operative and transfusion support.
For ppa-04 option B, what comparison determines whether this choice outranks the alternatives?
Option B falls behind in ppa-04 because the combined pattern is better resolved by counsel about a selected trial of labor for a noncovering low-lying placenta..
C. Offer labor with the same hemorrhage counseling as a normally located placenta (Why this does not fit)
Avoiding coverage makes labor a potential option. The edge is still low-lying, so increased bleeding risk and the possibility of operative delivery remain relevant. Eligibility for discussion does not make the location risk-free.
Reasoning steps for option C
For ppa-04 option C, which two findings must be reconciled before accepting this choice?
For ppa-04, option C may initially fit noncovering 18 mm edge, but it also must explain immediate operative and transfusion support.
For ppa-04 option C, what comparison determines whether this choice outranks the alternatives?
Option C falls behind in ppa-04 because the combined pattern is better resolved by counsel about a selected trial of labor for a noncovering low-lying placenta..
D. Discuss a monitored trial of labor as an individualized option (Best answer)
Selected asymptomatic patients with an edge 11 to 20 mm from the os may be considered for labor. The placenta does not cover the os, and the supplied history and resources support individualized counseling. Low-lying placental tissue is not equivalent to coverage.
Reasoning steps for option D
For ppa-04 option D, which two findings must be reconciled before accepting this choice?
In ppa-04, option D must account for noncovering 18 mm edge while remaining consistent with no bleeding or scar.
For ppa-04 option D, what comparison determines whether this choice outranks the alternatives?
Option D remains preferred in ppa-04 because choose the response that addresses that problem within the stated time budget for ppa-04.
Takeaway: A measurable gap changes the route discussion, but does not abolish hemorrhage precautions.
A. Use current placental anatomy and counsel separately about birth after prior cesarean (Best answer)
The placenta is now more than 20 mm from the os and expert imaging shows no abnormal scar interface. Resolved previa no longer supplies its own cesarean indication, while the prior cesarean still deserves an independent route discussion.
Reasoning steps for option A
For ppa-05 option A, which two findings must be reconciled before accepting this choice?
In ppa-05, option A must account for resolved 32 mm edge distance while remaining consistent with prior cesarean considered separately.
For ppa-05 option A, what comparison determines whether this choice outranks the alternatives?
Option A remains preferred in ppa-05 because separate previa-based route from prior-cesarean counseling and accreta risk
B. Retain a mandatory cesarean because the placenta was once over the os (Why this does not fit)
Persistent coverage would obstruct the route, but the current expert study shows resolution. A historical position should not be carried forward as a permanent mechanical contraindication.
Reasoning steps for option B
For ppa-05 option B, which two findings must be reconciled before accepting this choice?
For ppa-05, option B may initially fit resolved 32 mm edge distance, but it also must explain expert interface assessment is reassuring.
For ppa-05 option B, what comparison determines whether this choice outranks the alternatives?
Option B falls behind in ppa-05 because the combined pattern is better resolved by separate resolved previa from prior-cesarean route counseling and accreta assessment..
C. Schedule cesarean hysterectomy because any anterior placenta over a scar proves abnormal attachment (Why this does not fit)
A scar and anterior placenta raise pretest concern, but the current placental edge is clear and expert imaging lacks suspicious interface findings. Risk warrants assessment, not an irreversible operation without supporting evidence.
Reasoning steps for option C
For ppa-05 option C, which two findings must be reconciled before accepting this choice?
For ppa-05, option C may initially fit resolved 32 mm edge distance, but it also must explain expert interface assessment is reassuring.
For ppa-05 option C, what comparison determines whether this choice outranks the alternatives?
Option C falls behind in ppa-05 because the combined pattern is better resolved by separate resolved previa from prior-cesarean route counseling and accreta assessment..
D. Diagnose clinically silent abruption because the placental edge is now farther from the os (Why this does not fit)
Abruption is premature loss of attachment, not increased edge-to-os distance as the lower uterine segment develops. The stem supplies no bleeding, pain, tenderness, or imaging evidence of separation.
Reasoning steps for option D
For ppa-05 option D, which two findings must be reconciled before accepting this choice?
For ppa-05, option D may initially fit resolved 32 mm edge distance, but it also must explain expert interface assessment is reassuring.
For ppa-05 option D, what comparison determines whether this choice outranks the alternatives?
Option D falls behind in ppa-05 because the combined pattern is better resolved by separate resolved previa from prior-cesarean route counseling and accreta assessment..
Takeaway: Serial localization can change the diagnosis without implying placental detachment.
A. The stable hemoglobin indicates adequate circulating volume despite the vital-sign change (Why this does not fit)
A stable hemoglobin can be reassuring when the broader clinical course is stable. New hypotension and tachycardia after trauma demonstrate a deteriorating course before equilibration can be assumed. An early concentration is not a direct measure of remaining blood volume.
Reasoning steps for option A
For ppa-07 option A, which two findings must be reconciled before accepting this choice?
For ppa-07, option A may initially fit trauma and uterine tenderness, but it also must explain scant external blood and early hemoglobin.
For ppa-07 option A, what comparison determines whether this choice outranks the alternatives?
Option A falls behind in ppa-07 because the combined pattern is better resolved by recognize concealed acute maternal blood loss despite scant visible blood and early hemoglobin..
B. The declining pressure is best attributed to normal late-pregnancy vascular adaptation (Why this does not fit)
Pregnancy alters baseline vascular resistance and blood volume. An acute fall after trauma with uterine tenderness and fetal deterioration is not a normal adaptation pattern. Time course separates baseline physiology from acute perfusion failure.
Reasoning steps for option B
For ppa-07 option B, which two findings must be reconciled before accepting this choice?
For ppa-07, option B may initially fit trauma and uterine tenderness, but it also must explain scant external blood and early hemoglobin.
For ppa-07 option B, what comparison determines whether this choice outranks the alternatives?
Option B falls behind in ppa-07 because the combined pattern is better resolved by recognize concealed acute maternal blood loss despite scant visible blood and early hemoglobin..
C. The scant visible blood makes fetal hemorrhage more likely than maternal blood loss (Why this does not fit)
A torn fetal vessel can produce fetal compromise with limited visible blood. Substantial maternal hemodynamic deterioration and uterine tenderness favor a maternal hemorrhagic process. Use whose circulation is failing to interpret the apparent volume.
Reasoning steps for option C
For ppa-07 option C, which two findings must be reconciled before accepting this choice?
For ppa-07, option C may initially fit trauma and uterine tenderness, but it also must explain scant external blood and early hemoglobin.
For ppa-07 option C, what comparison determines whether this choice outranks the alternatives?
Option C falls behind in ppa-07 because the combined pattern is better resolved by recognize concealed acute maternal blood loss despite scant visible blood and early hemoglobin..
D. Acute maternal hemorrhage can be concealed while the early hemoglobin remains misleading (Best answer)
Hemoglobin concentration may not immediately reflect the magnitude of acute blood loss. The hemodynamic decline and uterine findings support significant bleeding despite a small external stain. Assess total hemorrhage from physiology and serial data, not a single initial concentration.
Reasoning steps for option D
For ppa-07 option D, which two findings must be reconciled before accepting this choice?
In ppa-07, option D must account for trauma and uterine tenderness while remaining consistent with maternal perfusion deterioration.
For ppa-07 option D, what comparison determines whether this choice outranks the alternatives?
Option D remains preferred in ppa-07 because choose the response that addresses that problem within the stated time budget for ppa-07.
Takeaway: Scant external bleeding and an early near-baseline hemoglobin can coexist with hemorrhagic shock.
A. Stop coagulation testing because prothrombin time remains normal (Why this does not fit)
Different components of hemostasis can become abnormal at different times. A normal prothrombin time cannot cancel a rapid fibrinogen decline and falling platelets during obstetric bleeding.
Reasoning steps for option A
For ppa-08 option A, which two findings must be reconciled before accepting this choice?
For ppa-08, option A may initially fit fibrinogen halves, but it also must explain normal prothrombin time does not erase the trend.
For ppa-08 option A, what comparison determines whether this choice outranks the alternatives?
Option A falls behind in ppa-08 because the combined pattern is better resolved by interpret serial fibrinogen and platelet decline in pregnancy before a single severe threshold..
B. Repeat hemostatic assessment and prepare targeted component support (Best answer)
Fibrinogen has halved from a pregnancy-level baseline while platelets are falling. Serial testing and hemorrhage readiness are appropriate before the value becomes severely low or clinical bleeding worsens.
Reasoning steps for option B
For ppa-08 option B, which two findings must be reconciled before accepting this choice?
In ppa-08, option B must account for fibrinogen halves while remaining consistent with platelets fall.
For ppa-08 option B, what comparison determines whether this choice outranks the alternatives?
Option B remains preferred in ppa-08 because select serial reassessment before a later severe result
C. Document physiologic normalization from pregnancy to a nonpregnant state (Why this does not fit)
A rapid fall during painful bleeding is not a benign return to a nonpregnant reference range. The trajectory is concerning because pregnancy ordinarily has higher fibrinogen.
Reasoning steps for option C
For ppa-08 option C, which two findings must be reconciled before accepting this choice?
For ppa-08, option C may initially fit fibrinogen halves, but it also must explain normal prothrombin time does not erase the trend.
For ppa-08 option C, what comparison determines whether this choice outranks the alternatives?
Option C falls behind in ppa-08 because the combined pattern is better resolved by interpret serial fibrinogen and platelet decline in pregnancy before a single severe threshold..
D. Diagnose severe disseminated intravascular coagulation from these two values alone (Why this does not fit)
The trend raises concern for consumption, but the complete diagnosis and severity require clinical context and additional hemostatic data. Concern should prompt reassessment rather than a one-number shortcut.
Reasoning steps for option D
For ppa-08 option D, which two findings must be reconciled before accepting this choice?
For ppa-08, option D may initially fit fibrinogen halves, but it also must explain normal prothrombin time does not erase the trend.
For ppa-08 option D, what comparison determines whether this choice outranks the alternatives?
Option D falls behind in ppa-08 because the combined pattern is better resolved by interpret serial fibrinogen and platelet decline in pregnancy before a single severe threshold..
Takeaway: A result inside an adult reference interval can still be an important obstetric warning.
A. Give fibrinogen replacement alone and defer other components (Why this does not fit)
Fibrinogen is severely depleted, but active oozing also occurs with marked thrombocytopenia and prolonged prothrombin time. Treating only one component leaves two documented deficits unaddressed.
Reasoning steps for option A
For ppa-09 option A, which two findings must be reconciled before accepting this choice?
For ppa-09, option A may initially fit active oozing, but it also must explain thrombocytopenia and prolonged prothrombin time.
For ppa-09 option A, what comparison determines whether this choice outranks the alternatives?
Option A falls behind in ppa-09 because the combined pattern is better resolved by select multicomponent hemostatic support from an active bleeding laboratory pattern..
B. Give platelets alone because the count is the lowest printed value (Why this does not fit)
Platelet replacement may be needed, but it does not restore fibrinogen or the broader factor deficit reflected by the prolonged prothrombin time. Printed magnitude does not determine which component matters.
Reasoning steps for option B
For ppa-09 option B, which two findings must be reconciled before accepting this choice?
For ppa-09, option B may initially fit active oozing, but it also must explain thrombocytopenia and prolonged prothrombin time.
For ppa-09 option B, what comparison determines whether this choice outranks the alternatives?
Option B falls behind in ppa-09 because the combined pattern is better resolved by select multicomponent hemostatic support from an active bleeding laboratory pattern..
C. Replace fibrinogen, platelets, and deficient factors while controlling the source (Best answer)
The patient has active bleeding with severe fibrinogen depletion, thrombocytopenia, and prolonged prothrombin time. Multicomponent support should proceed with resuscitation and indicated delivery.
Reasoning steps for option C
For ppa-09 option C, which two findings must be reconciled before accepting this choice?
In ppa-09, option C must account for active oozing while remaining consistent with severe hypofibrinogenemia.
For ppa-09 option C, what comparison determines whether this choice outranks the alternatives?
Option C remains preferred in ppa-09 because choose the response that addresses that problem within the stated time budget for ppa-09.
D. Continue red cells alone until hemoglobin returns to the prenatal value (Why this does not fit)
Red cells restore oxygen-carrying capacity but do not correct platelet, fibrinogen, or clotting-factor deficits. A prenatal hemoglobin target is not a substitute for treating active coagulopathy.
Reasoning steps for option D
For ppa-09 option D, which two findings must be reconciled before accepting this choice?
For ppa-09, option D may initially fit active oozing, but it also must explain thrombocytopenia and prolonged prothrombin time.
For ppa-09 option D, what comparison determines whether this choice outranks the alternatives?
Option D falls behind in ppa-09 because the combined pattern is better resolved by select multicomponent hemostatic support from an active bleeding laboratory pattern..
Takeaway: Treat hemostatic depletion and the cause of hemorrhage in parallel.
A. Wait for spontaneous labor because the limited bleeding proves the placental problem has resolved (Why this does not fit)
Spontaneous labor may provide a vaginal delivery route. Limited visible bleeding does not establish resolution of the placental disorder after confirmed fetal death. Do not use a small stain as the sole justification for deferring delivery planning.
Reasoning steps for option A
For ppa-10 option A, which two findings must be reconciled before accepting this choice?
For ppa-10, option A may initially fit confirmed fetal death, but it also must explain no contraindication to labor.
For ppa-10 option A, what comparison determines whether this choice outranks the alternatives?
Option A falls behind in ppa-10 because the combined pattern is better resolved by choose maternal-safety-focused route after abruption-associated fetal death..
B. Give prophylactic plasma before initiating delivery despite the current laboratory results (Why this does not fit)
Plasma can replace deficient coagulation factors during active hemostatic failure. The supplied clotting times, platelet count, and fibrinogen do not establish a current indication for empiric factor replacement as a prerequisite. Prepare for deterioration and monitor hemostasis without requiring unnecessary prophylactic products.
Reasoning steps for option B
For ppa-10 option B, which two findings must be reconciled before accepting this choice?
For ppa-10, option B may initially fit confirmed fetal death, but it also must explain no contraindication to labor.
For ppa-10 option B, what comparison determines whether this choice outranks the alternatives?
Option B falls behind in ppa-10 because the combined pattern is better resolved by choose maternal-safety-focused route after abruption-associated fetal death..
C. Plan vaginal delivery with continued hemorrhage and coagulation surveillance (Best answer)
Vaginal birth is often favored after abruption with fetal death when maternal condition permits. The mother is now stable and no obstetric contraindication to labor is supplied. Abruption and fetal death do not by themselves mandate cesarean delivery.
Reasoning steps for option C
For ppa-10 option C, which two findings must be reconciled before accepting this choice?
In ppa-10, option C must account for confirmed fetal death while remaining consistent with maternal stability after resuscitation.
For ppa-10 option C, what comparison determines whether this choice outranks the alternatives?
Option C remains preferred in ppa-10 because choose the response that addresses that problem within the stated time budget for ppa-10.
D. Proceed to cesarean because fetal death itself establishes maternal instability (Why this does not fit)
Cesarean can be necessary when maternal condition or obstetric circumstances require it. Here the mother is stable after resuscitation and fetal death does not itself define her current hemodynamic state. Assess maternal physiology separately from fetal viability when choosing the route.
Reasoning steps for option D
For ppa-10 option D, which two findings must be reconciled before accepting this choice?
For ppa-10, option D may initially fit confirmed fetal death, but it also must explain no contraindication to labor.
For ppa-10 option D, what comparison determines whether this choice outranks the alternatives?
Option D falls behind in ppa-10 because the combined pattern is better resolved by choose maternal-safety-focused route after abruption-associated fetal death..
Takeaway: After fetal death, maternal condition and obstetric feasibility determine the safest delivery route.
A. Perform cesarean because any abruption makes the cervical route unsafe (Why this does not fit)
Cesarean may be needed for maternal or fetal compromise, but abruption does not place placental tissue across a documented clear os. The route depends on current physiology and labor progress.
Reasoning steps for option A
For ppa-11 option A, which distinction must be made before treating cesarean as mandatory?
Abruption concerns placental attachment and physiology; it does not by itself place tissue across a cervix that imaging has shown to be clear.
For ppa-11 option A, what current findings argue against immediate operative delivery?
Maternal observations and laboratories are stable, the tracing is reassuring, and labor is progressing, so close monitored vaginal delivery remains reasonable unless the trajectory worsens.
B. Use tocolysis to stop term labor and preserve the remaining attachment (Why this does not fit)
The patient is at term in progressive labor, and contraction suppression does not restore placental attachment. Tocolysis would not improve the supplied stable route decision.
Reasoning steps for option B
For ppa-11 option B, why does contraction suppression not address the dominant problem?
The patient is at term and in progressive labor; tocolysis cannot restore placental attachment or improve a route decision already supported by present stability.
For ppa-11 option B, what comparison places monitored delivery ahead of tocolysis?
Continued surveillance preserves the ability to detect deterioration, whereas stopping term labor adds delay without treating the suspected placental process.
C. Pause delivery planning until repeat ultrasound excludes a retroplacental collection (Why this does not fit)
Ultrasound may help with anatomy, but it cannot exclude abruption and should not become the condition for continued monitored labor. Current maternal-fetal stability and progress support the plan; deterioration, not a negative scan, should trigger route reassessment.
Reasoning steps for option C
For ppa-11 option C, what can repeat ultrasound contribute and what can it not establish?
It may describe anatomy or a visible collection, but a negative study cannot exclude clinical abruption.
For ppa-11 option C, why should imaging not become the condition for continued delivery planning?
The plan is justified by current maternal-fetal stability and labor progress; a worsening trajectory, not failure to visualize a clot, should change the route.
D. Continue monitored vaginal delivery with immediate readiness to escalate (Best answer)
Maternal findings and laboratories are stable, the fetus remains reassuring, the os is clear, and labor is progressing. Continuous surveillance and operative readiness preserve the ability to respond if the trajectory changes.
Reasoning steps for option D
For ppa-11 option D, which three findings make monitored vaginal delivery defensible?
The cervical route is clear, labor is progressing, and both maternal and fetal assessments remain stable.
For ppa-11 option D, what safeguard keeps this from becoming low-risk routine labor?
Continuous surveillance and immediate readiness to escalate preserve a rapid response if bleeding, perfusion, laboratory results, or fetal status deteriorate.
Takeaway: Abruption can permit vaginal delivery when anatomy, labor, and maternal-fetal condition support it.
A. Proceed to cesarean because a possible abruption alone requires immediate birth (Why this does not fit)
Urgent birth is needed when abruption causes compromise or significant ongoing bleeding. Those indications are not present in the current stabilized preterm assessment. Balance the risks of prematurity against the actual severity and trajectory.
Reasoning steps for option A
For ppa-12 option A, which two findings must be reconciled before accepting this choice?
For ppa-12, option A may initially fit preterm episode resolves, but it also must explain reassuring fetus without labor.
For ppa-12 option A, what comparison determines whether this choice outranks the alternatives?
Option A falls behind in ppa-12 because the combined pattern is better resolved by balance prematurity against a stabilized suspected preterm abruption..
B. Begin induction now because a clear os proves birth is safer than continued pregnancy (Why this does not fit)
A clear os can make vaginal delivery anatomically feasible. Feasibility does not establish a current indication for preterm delivery in a stable pregnancy. Decide whether to deliver before deciding that a feasible route must be used.
Reasoning steps for option B
For ppa-12 option B, which two findings must be reconciled before accepting this choice?
For ppa-12, option B may initially fit preterm episode resolves, but it also must explain reassuring fetus without labor.
For ppa-12 option B, what comparison determines whether this choice outranks the alternatives?
Option B falls behind in ppa-12 because the combined pattern is better resolved by balance prematurity against a stabilized suspected preterm abruption..
C. Continue close expectant obstetric care with reassessment for any deterioration (Best answer)
Selected stable preterm patients with suspected mild abruption can be managed expectantly. Both maternal and fetal assessments are reassuring after the episode and there is no active labor. Observation is a conditional strategy, not a declaration that abruption is excluded.
Reasoning steps for option C
For ppa-12 option C, which two findings must be reconciled before accepting this choice?
In ppa-12, option C must account for preterm episode resolves while remaining consistent with stable serial assessment.
For ppa-12 option C, what comparison determines whether this choice outranks the alternatives?
Option C remains preferred in ppa-12 because choose the response that addresses that problem within the stated time budget for ppa-12.
D. Discontinue obstetric surveillance because the bleeding has stopped (Why this does not fit)
Resolution of visible bleeding is a favorable development. The episode still warrants follow-up because recurrent bleeding or fetal effects can occur. A temporary improvement does not erase a clinically suspected placental disorder.
Reasoning steps for option D
For ppa-12 option D, which two findings must be reconciled before accepting this choice?
For ppa-12, option D may initially fit preterm episode resolves, but it also must explain reassuring fetus without labor.
For ppa-12 option D, what comparison determines whether this choice outranks the alternatives?
Option D falls behind in ppa-12 because the combined pattern is better resolved by balance prematurity against a stabilized suspected preterm abruption..
Takeaway: Stable preterm abruption can justify careful observation, but not the end of surveillance.
A. Antenatal corticosteroids while continuing observation and reassessment (Best answer)
Eligible preterm patients at substantial risk of birth soon may benefit from antenatal corticosteroids. The patient is at 30 weeks with recurrent bleeding and a documented near-term delivery risk. Use the anticipated delivery interval, not the diagnosis alone, to time fetal maturation treatment.
Reasoning steps for option A
For ppa-13 option A, which two findings must be reconciled before accepting this choice?
In ppa-13, option A must account for 30 week gestation while remaining consistent with birth likely within seven days.
For ppa-13 option A, what comparison determines whether this choice outranks the alternatives?
Option A remains preferred in ppa-13 because choose the response that addresses that problem within the stated time budget for ppa-13.
B. Routine repeated corticosteroid courses every week until birth (Why this does not fit)
Corticosteroids may be considered again only under specific circumstances and guidance. The supplied indication is for an initial course, not an automatic recurring schedule. An indicated initial treatment does not justify indefinite repetition.
Reasoning steps for option B
For ppa-13 option B, which two findings must be reconciled before accepting this choice?
For ppa-13, option B may initially fit 30 week gestation, but it also must explain no previous steroid course.
For ppa-13 option B, what comparison determines whether this choice outranks the alternatives?
Option B falls behind in ppa-13 because the combined pattern is better resolved by select antenatal corticosteroids from gestational age and near-term birth probability..
C. Postpone all corticosteroids until a planned operation several weeks later (Why this does not fit)
Timing treatment near an anticipated birth helps target benefit. The team now judges birth within seven days likely rather than reliably several weeks away. Update treatment timing when the near-term delivery risk changes.
Reasoning steps for option C
For ppa-13 option C, which two findings must be reconciled before accepting this choice?
For ppa-13, option C may initially fit 30 week gestation, but it also must explain no previous steroid course.
For ppa-13 option C, what comparison determines whether this choice outranks the alternatives?
Option C falls behind in ppa-13 because the combined pattern is better resolved by select antenatal corticosteroids from gestational age and near-term birth probability..
D. Delay any necessary emergency birth until two days after the first dose (Why this does not fit)
A longer interval may allow more benefit when waiting is safe. Corticosteroid administration does not override a later indication for urgent delivery. Fetal maturation treatment must not create a compulsory delay during hemorrhage.
Reasoning steps for option D
For ppa-13 option D, which two findings must be reconciled before accepting this choice?
For ppa-13, option D may initially fit 30 week gestation, but it also must explain no previous steroid course.
For ppa-13 option D, what comparison determines whether this choice outranks the alternatives?
Option D falls behind in ppa-13 because the combined pattern is better resolved by select antenatal corticosteroids from gestational age and near-term birth probability..
Takeaway: Time corticosteroids to a meaningful preterm birth risk without allowing them to delay emergency care.
A. Proceed with urgent cesarean while continuing resuscitation (Best answer)
The patient now has ongoing hemorrhage and persistent fetal compromise with vaginal birth remote. The emergency indication overrides the unfinished maturation course.
Reasoning steps for option A
For ppa-14 option A, which two findings must be reconciled before accepting this choice?
In ppa-14, option A must account for incomplete steroid course while remaining consistent with new hemorrhage and persistent bradycardia.
For ppa-14 option A, what comparison determines whether this choice outranks the alternatives?
Option A remains preferred in ppa-14 because choose the response that addresses that problem within the stated time budget for ppa-14.
B. Continue observation for one hour to determine whether bradycardia resolves (Why this does not fit)
Persistent bradycardia despite initial response measures is not compatible with an additional observation interval during continuing bleeding. The current physiology has replaced the earlier stable state.
Reasoning steps for option B
For ppa-14 option B, which two findings must be reconciled before accepting this choice?
For ppa-14, option B may initially fit incomplete steroid course, but it also must explain vaginal birth remote.
For ppa-14 option B, what comparison determines whether this choice outranks the alternatives?
Option B falls behind in ppa-14 because the combined pattern is better resolved by abandon steroid-related waiting when hemorrhage and fetal compromise develop..
C. Use tocolysis until the scheduled second steroid dose (Why this does not fit)
Tocolysis cannot repair the placental process and should not postpone a birth that has become necessary. Completing steroids is not the priority in active compromise.
Reasoning steps for option C
For ppa-14 option C, which two findings must be reconciled before accepting this choice?
For ppa-14, option C may initially fit incomplete steroid course, but it also must explain vaginal birth remote.
For ppa-14 option C, what comparison determines whether this choice outranks the alternatives?
Option C falls behind in ppa-14 because the combined pattern is better resolved by abandon steroid-related waiting when hemorrhage and fetal compromise develop..
D. Give the second betamethasone dose early before deciding on delivery (Why this does not fit)
Betamethasone supports maturation over time and does not restore acute placental oxygen delivery. An accelerated dose is not fetal resuscitation.
Reasoning steps for option D
For ppa-14 option D, which two findings must be reconciled before accepting this choice?
For ppa-14, option D may initially fit incomplete steroid course, but it also must explain vaginal birth remote.
For ppa-14 option D, what comparison determines whether this choice outranks the alternatives?
Option D falls behind in ppa-14 because the combined pattern is better resolved by abandon steroid-related waiting when hemorrhage and fetal compromise develop..
Takeaway: A plan to gain maturity remains valid only while maternal and fetal conditions allow waiting.
A. Proceed directly to a routine cesarean today without expert interface assessment (Why this does not fit)
Persistent coverage establishes the cesarean route, but a prior scar plus incomplete interface imaging can change the delivery location, team, blood preparation, and operative strategy. In a stable patient with expert assessment immediately available, bypassing that evaluation discards actionable planning information.
Reasoning steps for option A
For ppa-15 option A, what useful question remains unanswered before a routine cesarean?
The prior scar interface was incompletely visualized, so placenta accreta spectrum risk and the resources needed for delivery remain incompletely assessed.
For ppa-15 option A, why is prompt expert assessment compatible with timely delivery?
She is currently stable and expert imaging is available immediately, allowing actionable planning without sending her home or delaying the indicated admission.
B. Obtain prompt expert placental assessment while coordinating cesarean delivery during this admission (Best answer)
She is already within the 36 0/7 to 37 6/7 stable-previa window, and the new bleed favors delivery rather than prolonged observation. Immediate expert interface assessment can refine placenta accreta spectrum resources without delaying necessary care or assuming the diagnosis.
Reasoning steps for option B
For ppa-15 option B, how do timing and the new bleed affect the decision?
She is already within the stable-previa delivery window, and a new bleed makes prolonged routine-term waiting less appropriate.
For ppa-15 option B, why pair expert assessment with cesarean coordination rather than choose only one?
Coverage establishes the cesarean route, while the incompletely assessed scar interface can change location, team, blood preparation, and operative strategy.
C. Treat incomplete interface visualization as diagnostic placenta accreta spectrum and schedule cesarean hysterectomy (Why this does not fit)
A scar and anterior previa raise pretest risk, but incomplete visualization is not proof of abnormal attachment. Expert assessment and multidisciplinary readiness are appropriate before committing to an irreversible operation.
Reasoning steps for option C
For ppa-15 option C, why does high pretest risk not equal a confirmed accreta-spectrum diagnosis?
Anterior previa over a prior scar raises concern, but incomplete visualization is not proof of abnormal attachment.
For ppa-15 option C, what action preserves safety without committing prematurely to hysterectomy?
Prompt expert imaging and multidisciplinary readiness refine the operative plan before an irreversible procedure is selected.
D. Discharge and defer repeat imaging and delivery until 39 weeks unless bleeding recurs (Why this does not fit)
Persistent coverage and a new bleed do not fit routine low-risk term timing. Waiting also leaves the incompletely assessed scar interface unresolved before labor or another hemorrhage.
Reasoning steps for option D
For ppa-15 option D, which two facts make routine 39-week waiting inappropriate?
Persistent placental coverage remains present, and a new bleeding episode has occurred within the recommended planned-delivery window.
For ppa-15 option D, what additional risk remains unresolved by discharge?
The scar interface has not been adequately characterized, leaving a potentially important delivery-resource question unanswered before labor or recurrent hemorrhage.
Takeaway: At 36 weeks with persistent previa, a new bleed and incompletely assessed scar interface call for prompt expert planning and cesarean delivery, not prolonged routine-term waiting or an assumed accreta diagnosis.
A. Loss of maternal blood from a placental bed covering the os (Why this does not fit)
Previa can cause maternal bleeding and secondary fetal compromise. Coverage was not identified, and the sudden fetal collapse immediately after rupture occurs without maternal circulatory deterioration. Timing and the circulation affected help distinguish a fetal vessel injury from maternal bed bleeding.
Reasoning steps for option A
For ppa-16 option A, which two findings must be reconciled before accepting this choice?
For ppa-16, option A may initially fit bleeding immediately after membrane rupture, but it also must explain stable maternal circulation.
For ppa-16 option A, what comparison determines whether this choice outranks the alternatives?
Option A falls behind in ppa-16 because the combined pattern is better resolved by infer fetal-vessel hemorrhage from membrane rupture and disproportionate fetal collapse..
B. Loss of fetal blood through a ruptured unprotected membranous vessel (Best answer)
Fetal vessels crossing the cervical membranes can tear when the membranes rupture. The immediate association with rupture and marked fetal compromise despite stable maternal circulation fit fetal hemorrhage. Vasa previa can threaten the fetus before maternal observations show hemorrhagic shock.
Reasoning steps for option B
For ppa-16 option B, which two findings must be reconciled before accepting this choice?
In ppa-16, option B must account for bleeding immediately after membrane rupture while remaining consistent with profound fetal bradycardia.
For ppa-16 option B, what comparison determines whether this choice outranks the alternatives?
Option B remains preferred in ppa-16 because choose the response that addresses that problem within the stated time budget for ppa-16.
C. Maternal cervical capillary disruption associated with rapid dilation (Why this does not fit)
Cervical change can cause maternal bleeding during labor. Minor cervical bleeding does not explain profound fetal bradycardia immediately after membrane rupture with maternal circulation preserved. Account for the severe fetal effect rather than explaining only the visible blood.
Reasoning steps for option C
For ppa-16 option C, which two findings must be reconciled before accepting this choice?
For ppa-16, option C may initially fit bleeding immediately after membrane rupture, but it also must explain stable maternal circulation.
For ppa-16 option C, what comparison determines whether this choice outranks the alternatives?
Option C falls behind in ppa-16 because the combined pattern is better resolved by infer fetal-vessel hemorrhage from membrane rupture and disproportionate fetal collapse..
D. Diffuse maternal coagulation-factor consumption preceding membrane rupture (Why this does not fit)
disseminated intravascular coagulation can complicate severe placental hemorrhage. No maternal hemostatic failure is supplied, and the deterioration is tightly linked to membrane rupture. Prefer the mechanism supported by the immediate event and physiologic pattern.
Reasoning steps for option D
For ppa-16 option D, which two findings must be reconciled before accepting this choice?
For ppa-16, option D may initially fit bleeding immediately after membrane rupture, but it also must explain stable maternal circulation.
For ppa-16 option D, what comparison determines whether this choice outranks the alternatives?
Option D falls behind in ppa-16 because the combined pattern is better resolved by infer fetal-vessel hemorrhage from membrane rupture and disproportionate fetal collapse..
Takeaway: Bleeding with membrane rupture and abrupt fetal collapse can represent fetal, not maternal, hemorrhage.
A. Use the result to determine whether placental tissue covers the os (Why this does not fit)
Fetal-cell quantification contains no anatomic information about the placental edge. Ultrasound, not a blood assay, answers the location question.
Reasoning steps for option A
For ppa-17 option A, which two findings must be reconciled before accepting this choice?
For ppa-17, option A may initially fit unsensitized rhesus d-negative status, but it also must explain quantified fetal whole-blood estimate.
For ppa-17 option A, what comparison determines whether this choice outranks the alternatives?
Option A falls behind in ppa-17 because the combined pattern is better resolved by use quantified fetomaternal hemorrhage to individualize supplemental anti-D prophylaxis..
B. Use the result to diagnose maternal consumptive coagulopathy (Why this does not fit)
The assay estimates fetal cells in maternal blood rather than fibrinogen, platelets, or clotting-factor function. Hemostatic studies answer the coagulopathy question.
Reasoning steps for option B
For ppa-17 option B, which two findings must be reconciled before accepting this choice?
For ppa-17, option B may initially fit unsensitized rhesus d-negative status, but it also must explain quantified fetal whole-blood estimate.
For ppa-17 option B, what comparison determines whether this choice outranks the alternatives?
Option B falls behind in ppa-17 because the combined pattern is better resolved by use quantified fetomaternal hemorrhage to individualize supplemental anti-D prophylaxis..
C. Use the quantified volume with the local protocol to determine supplemental anti-D (Best answer)
The new bleeding episode is a sensitizing event despite prior routine prophylaxis. The measured fetomaternal volume informs whether additional anti-D is needed without imposing a universal dose.
Reasoning steps for option C
For ppa-17 option C, which two findings must be reconciled before accepting this choice?
In ppa-17, option C must account for unsensitized rhesus d-negative status while remaining consistent with new sensitizing bleed despite prior prophylaxis.
For ppa-17 option C, what comparison determines whether this choice outranks the alternatives?
Option C remains preferred in ppa-17 because use quantified fetal volume only for protocol-based supplemental prophylaxis
D. Use the result to calculate the maternal blood concealed behind the placenta (Why this does not fit)
A retroplacental hematoma is primarily maternal blood outside the maternal circulation. A fetal-cell assay cannot measure that hidden maternal volume or exclude abruption.
Reasoning steps for option D
For ppa-17 option D, which two findings must be reconciled before accepting this choice?
For ppa-17, option D may initially fit unsensitized rhesus d-negative status, but it also must explain quantified fetal whole-blood estimate.
For ppa-17 option D, what comparison determines whether this choice outranks the alternatives?
Option D falls behind in ppa-17 because the combined pattern is better resolved by use quantified fetomaternal hemorrhage to individualize supplemental anti-D prophylaxis..
Takeaway: Fetal-cell quantification guides immunoprophylaxis; it is not a placental localization or disseminated intravascular coagulation test.
A. Discharge because the negative fetal-cell test excludes traumatic separation (Why this does not fit)
A maternal retroplacental bleed may occur without detectable fetal cells. The worsening tenderness and new late decelerations provide clinical evidence that the limited assay cannot negate.
Reasoning steps for option A
For ppa-18 option A, which two findings must be reconciled before accepting this choice?
For ppa-18, option A may initially fit trauma, but it also must explain worsening tenderness and late decelerations.
For ppa-18 option A, what comparison determines whether this choice outranks the alternatives?
Option A falls behind in ppa-18 because the combined pattern is better resolved by integrate limited negative tests with an evolving trauma-associated abruption pattern..
B. Treat the tracing as diagnostic of vasa previa (Why this does not fit)
Fetal compromise can accompany fetal-vessel hemorrhage, but no bleeding with membrane rupture is supplied. Trauma and progressive uterine tenderness more strongly support a maternal placental process.
Reasoning steps for option B
For ppa-18 option B, which two findings must be reconciled before accepting this choice?
For ppa-18, option B may initially fit trauma, but it also must explain worsening tenderness and late decelerations.
For ppa-18 option B, what comparison determines whether this choice outranks the alternatives?
Option B falls behind in ppa-18 because the combined pattern is better resolved by integrate limited negative tests with an evolving trauma-associated abruption pattern..
C. Continue observation because two negative tests create a reliable rule-out (Why this does not fit)
Neither ultrasound nor fetal-cell testing reliably excludes abruption. Combining two tests aimed at limited targets does not overrule a worsening clinical trajectory.
Reasoning steps for option C
For ppa-18 option C, which two findings must be reconciled before accepting this choice?
For ppa-18, option C may initially fit trauma, but it also must explain worsening tenderness and late decelerations.
For ppa-18 option C, what comparison determines whether this choice outranks the alternatives?
Option C falls behind in ppa-18 because the combined pattern is better resolved by integrate limited negative tests with an evolving trauma-associated abruption pattern..
D. Escalate for suspected abruption and prepare for indicated delivery (Best answer)
Progressive tenderness and recurrent late decelerations after trauma indicate evolving placental dysfunction. Prompt reassessment, resuscitation readiness, and delivery planning are appropriate despite the negative tests.
Reasoning steps for option D
For ppa-18 option D, which two findings must be reconciled before accepting this choice?
In ppa-18, option D must account for trauma while remaining consistent with negative ultrasound and fetal-cell assay.
For ppa-18 option D, what comparison determines whether this choice outranks the alternatives?
Option D remains preferred in ppa-18 because choose the response that addresses that problem within the stated time budget for ppa-18.
A. Arrange immediate birth at 29 weeks solely because abnormal attachment is suspected (Why this does not fit)
Suspected placenta accreta spectrum requires deliberate planning because an unscheduled hemorrhage can be dangerous. No present bleeding, labor, or fetal compromise is supplied to justify immediate very preterm birth solely on suspicion. Distinguish urgent specialist preparation from a current emergency delivery indication.
Reasoning steps for option A
For ppa-19 option A, which two findings must be reconciled before accepting this choice?
For ppa-19, option A may initially fit three prior cesareans, but it also must explain lacunae and abnormal interface.
For ppa-19 option A, what comparison determines whether this choice outranks the alternatives?
Option A falls behind in ppa-19 because the combined pattern is better resolved by refer a high-risk scar, previa, and abnormal interface combination for specialist planning..
B. Refer for specialist placenta accreta spectrum assessment and multidisciplinary delivery planning (Best answer)
Prior cesareans with an anterior low placenta raise the risk of placenta accreta spectrum. The abnormal interface findings reinforce the need for specialist planning despite current stability. Use the risk history and imaging together before the delivery becomes an emergency.
Reasoning steps for option B
For ppa-19 option B, which two findings must be reconciled before accepting this choice?
In ppa-19, option B must account for three prior cesareans while remaining consistent with anterior previa.
For ppa-19 option B, what comparison determines whether this choice outranks the alternatives?
Option B remains preferred in ppa-19 because choose the response that addresses that problem within the stated time budget for ppa-19.
C. Continue routine delivery planning because the absence of bleeding excludes abnormal attachment (Why this does not fit)
Current absence of bleeding supports maternal stability. It does not exclude an abnormal interface that becomes dangerous during placental separation at birth. An asymptomatic present course can coexist with a major delivery-planning problem.
Reasoning steps for option C
For ppa-19 option C, which two findings must be reconciled before accepting this choice?
For ppa-19, option C may initially fit three prior cesareans, but it also must explain lacunae and abnormal interface.
For ppa-19 option C, what comparison determines whether this choice outranks the alternatives?
Option C falls behind in ppa-19 because the combined pattern is better resolved by refer a high-risk scar, previa, and abnormal interface combination for specialist planning..
D. Schedule a routine placental extraction at a facility without major hemorrhage resources (Why this does not fit)
Many cesarean deliveries allow straightforward placental separation. The scar history, anterior previa, and abnormal interface make routine extraction planning unsafe. Match delivery resources to suspected placental attachment rather than current symptoms alone.
Reasoning steps for option D
For ppa-19 option D, which two findings must be reconciled before accepting this choice?
For ppa-19, option D may initially fit three prior cesareans, but it also must explain lacunae and abnormal interface.
For ppa-19 option D, what comparison determines whether this choice outranks the alternatives?
Option D falls behind in ppa-19 because the combined pattern is better resolved by refer a high-risk scar, previa, and abnormal interface combination for specialist planning..
Takeaway: Previa over a cesarean scar can require substantial preparation before any bleeding begins.
A. Replace expert ultrasound with routine magnetic resonance imaging (Why this does not fit)
Magnetic resonance imaging can clarify selected anatomy, but it should not automatically substitute for available expert placental ultrasound. The first problem is incomplete visualization by a routine study.
Reasoning steps for option A
For ppa-20 option A, which two findings must be reconciled before accepting this choice?
For ppa-20, option A may initially fit four prior cesareans, but it also must explain incomplete routine interface visualization.
For ppa-20 option A, what comparison determines whether this choice outranks the alternatives?
Option A falls behind in ppa-20 because the combined pattern is better resolved by reject an incomplete negative scan in a patient with high pretest accreta risk..
B. Accept the report as definitive because no accreta was named (Why this does not fit)
The interface was not completely seen, and the patient has strong pretest risk from multiple scars and anterior previa. A limited negative report cannot exclude an unexamined abnormality.
Reasoning steps for option B
For ppa-20 option B, which two findings must be reconciled before accepting this choice?
For ppa-20, option B may initially fit four prior cesareans, but it also must explain incomplete routine interface visualization.
For ppa-20 option B, what comparison determines whether this choice outranks the alternatives?
Option B falls behind in ppa-20 because the combined pattern is better resolved by reject an incomplete negative scan in a patient with high pretest accreta risk..
C. Wait for bleeding before arranging any further assessment (Why this does not fit)
Placenta accreta spectrum may remain asymptomatic until attempted separation at delivery. Planning should begin from risk and anatomy rather than waiting for hemorrhage.
Reasoning steps for option C
For ppa-20 option C, which two findings must be reconciled before accepting this choice?
For ppa-20, option C may initially fit four prior cesareans, but it also must explain incomplete routine interface visualization.
For ppa-20 option C, what comparison determines whether this choice outranks the alternatives?
Option C falls behind in ppa-20 because the combined pattern is better resolved by reject an incomplete negative scan in a patient with high pretest accreta risk..
D. Arrange expert placental ultrasound and multidisciplinary planning (Best answer)
Multiple scars, anterior previa, and incomplete routine imaging justify specialist assessment. Expert evaluation can refine anatomy and delivery resources without presuming an irreversible diagnosis.
Reasoning steps for option D
For ppa-20 option D, which two findings must be reconciled before accepting this choice?
In ppa-20, option D must account for four prior cesareans while remaining consistent with anterior previa.
For ppa-20 option D, what comparison determines whether this choice outranks the alternatives?
Option D remains preferred in ppa-20 because choose the response that addresses that problem within the stated time budget for ppa-20.
Takeaway: A limited scan is not a definitive negative result in a high-risk placental setting.
A. Leave the placenta in situ and proceed with planned hysterectomy (Best answer)
The planned approach anticipates an absent or unsafe separation plane. Keeping the attachment intact reduces the chance of provoking uncontrolled hemorrhage before definitive surgery.
Reasoning steps for option A
For ppa-21 option A, which two findings must be reconciled before accepting this choice?
In ppa-21, option A must account for planned cesarean hysterectomy while remaining consistent with placenta-avoiding uterine incision.
For ppa-21 option A, what comparison determines whether this choice outranks the alternatives?
Option A remains preferred in ppa-21 because choose the response that addresses that problem within the stated time budget for ppa-21.
B. Use forceful cord traction to test whether a plane exists (Why this does not fit)
Traction is routine only when a normal separation plane is expected. Testing suspected placenta accreta spectrum by force can trigger the hemorrhage the operation is designed to prevent.
Reasoning steps for option B
For ppa-21 option B, which two findings must be reconciled before accepting this choice?
For ppa-21, option B may initially fit planned cesarean hysterectomy, but it also must explain strong accreta-spectrum suspicion.
For ppa-21 option B, what comparison determines whether this choice outranks the alternatives?
Option B falls behind in ppa-21 because the combined pattern is better resolved by avoid placental separation in planned cesarean hysterectomy for suspected accreta spectrum..
C. Incise through the placenta to map its depth before hysterectomy (Why this does not fit)
The team already has a placenta-avoiding incision. Transecting highly vascular placental tissue adds bleeding without providing a necessary bedside grading method.
Reasoning steps for option C
For ppa-21 option C, which two findings must be reconciled before accepting this choice?
For ppa-21, option C may initially fit planned cesarean hysterectomy, but it also must explain strong accreta-spectrum suspicion.
For ppa-21 option C, what comparison determines whether this choice outranks the alternatives?
Option C falls behind in ppa-21 because the combined pattern is better resolved by avoid placental separation in planned cesarean hysterectomy for suspected accreta spectrum..
D. Manually detach the placenta to reduce the hysterectomy specimen (Why this does not fit)
Specimen size is not the immediate priority. Manual separation can tear the abnormal vascular interface and convert a controlled procedure into massive hemorrhage.
Reasoning steps for option D
For ppa-21 option D, which two findings must be reconciled before accepting this choice?
For ppa-21, option D may initially fit planned cesarean hysterectomy, but it also must explain strong accreta-spectrum suspicion.
For ppa-21 option D, what comparison determines whether this choice outranks the alternatives?
Option D falls behind in ppa-21 because the combined pattern is better resolved by avoid placental separation in planned cesarean hysterectomy for suspected accreta spectrum..
Takeaway: Avoid forced placental separation during a planned cesarean hysterectomy for suspected placenta accreta spectrum.
A. Reduced uteroplacental perfusion during maternal hemorrhagic shock (Best answer)
The fetus depends on maternal perfusion of the placental exchange surface. Major maternal blood loss and hypotension can impair oxygen delivery even without a tender hypertonic uterus. An abnormal fetal tracing is not exclusive to abruption.
Reasoning steps for option A
For ppa-23 option A, which two findings must be reconciled before accepting this choice?
In ppa-23, option A must account for known previa and soft uterus while remaining consistent with maternal hemorrhagic shock.
For ppa-23 option A, what comparison determines whether this choice outranks the alternatives?
Option A remains preferred in ppa-23 because choose the response that addresses that problem within the stated time budget for ppa-23.
B. Direct drainage of fetal blood from every bleeding maternal placental vessel (Why this does not fit)
Fetal hemorrhage can cause severe fetal compromise. Maternal placental-bed bleeding does not automatically open the fetal capillary circulation. Distinguish loss of maternal perfusion from direct fetal blood loss.
Reasoning steps for option B
For ppa-23 option B, which two findings must be reconciled before accepting this choice?
For ppa-23, option B may initially fit known previa and soft uterus, but it also must explain new late decelerations.
For ppa-23 option B, what comparison determines whether this choice outranks the alternatives?
Option B falls behind in ppa-23 because the combined pattern is better resolved by explain fetal late decelerations from maternal shock during previa hemorrhage..
C. Normal fetal adaptation to a larger intervillous oxygen reserve (Why this does not fit)
A functioning placental circulation normally supports fetal oxygen supply. Maternal hypotension reduces effective perfusion rather than increasing the oxygen reserve. Predict the direction of oxygen delivery from the actual circulatory change.
Reasoning steps for option C
For ppa-23 option C, which two findings must be reconciled before accepting this choice?
For ppa-23, option C may initially fit known previa and soft uterus, but it also must explain new late decelerations.
For ppa-23 option C, what comparison determines whether this choice outranks the alternatives?
Option C falls behind in ppa-23 because the combined pattern is better resolved by explain fetal late decelerations from maternal shock during previa hemorrhage..
D. Mechanical cord compression caused by placental tissue covering the maternal cervix (Why this does not fit)
Cord compression can alter the fetal heart tracing in other settings. The supplied temporal change is maternal hemorrhagic shock, not a demonstrated cord event. Prefer the mechanism supported by the hemodynamic change rather than inventing a separate obstruction.
Reasoning steps for option D
For ppa-23 option D, which two findings must be reconciled before accepting this choice?
For ppa-23, option D may initially fit known previa and soft uterus, but it also must explain new late decelerations.
For ppa-23 option D, what comparison determines whether this choice outranks the alternatives?
Option D falls behind in ppa-23 because the combined pattern is better resolved by explain fetal late decelerations from maternal shock during previa hemorrhage..
Takeaway: Previa hemorrhage can compromise the fetus through maternal hypoperfusion.
A. A careful speculum examination of the vagina and cervix (Best answer)
Speculum examination can directly display a cervical or vaginal bleeding source. The patient is stable and the principal placental-location concern has been assessed. Do not equate appropriate visual inspection with digital manipulation of an unlocalized placenta.
Reasoning steps for option A
For ppa-24 option A, which two findings must be reconciled before accepting this choice?
In ppa-24, option A must account for stable light spotting while remaining consistent with placenta and fetal vessels clear of cervix.
For ppa-24 option A, what comparison determines whether this choice outranks the alternatives?
Option A remains preferred in ppa-24 because choose the response that addresses that problem within the stated time budget for ppa-24.
B. Repeated digital cervical palpation as the best method to locate a surface lesion (Why this does not fit)
Digital examination can assess cervical dilation when appropriate. It does not provide the direct visual inspection needed to identify a cervical or vaginal surface source. Select the examination according to the structure and abnormality being assessed.
Reasoning steps for option B
For ppa-24 option B, which two findings must be reconciled before accepting this choice?
For ppa-24, option B may initially fit stable light spotting, but it also must explain suspected lower-tract source.
For ppa-24 option B, what comparison determines whether this choice outranks the alternatives?
Option B falls behind in ppa-24 because the combined pattern is better resolved by choose careful visual speculum examination after placental and fetal-vessel localization..
C. A fetal-cell assay to distinguish cervical from vaginal maternal bleeding (Why this does not fit)
Fetal-cell testing can quantify fetomaternal hemorrhage. Both proposed local sources are maternal and their locations cannot be distinguished by that assay. A blood-cell count is not a localizing examination of the lower genital tract.
Reasoning steps for option C
For ppa-24 option C, which two findings must be reconciled before accepting this choice?
For ppa-24, option C may initially fit stable light spotting, but it also must explain suspected lower-tract source.
For ppa-24 option C, what comparison determines whether this choice outranks the alternatives?
Option C falls behind in ppa-24 because the combined pattern is better resolved by choose careful visual speculum examination after placental and fetal-vessel localization..
D. Pelvic magnetic resonance imaging before any visual examination of the cervix (Why this does not fit)
magnetic resonance imaging can answer selected complex anatomic questions. A stable suspected surface bleeding source can be evaluated directly without making magnetic resonance imaging a prerequisite. Do not replace a suitable direct assessment with unnecessary advanced imaging.
Reasoning steps for option D
For ppa-24 option D, which two findings must be reconciled before accepting this choice?
For ppa-24, option D may initially fit stable light spotting, but it also must explain suspected lower-tract source.
For ppa-24 option D, what comparison determines whether this choice outranks the alternatives?
Option D falls behind in ppa-24 because the combined pattern is better resolved by choose careful visual speculum examination after placental and fetal-vessel localization..
Takeaway: Digital cervical examination and careful speculum inspection are not interchangeable procedures.
A. Placental separation after rapid uterine decompression (Best answer)
Rapid loss of uterine volume can stress the placental attachment. The subsequent bleeding, constant pain, high tone, and late decelerations fit acute separation with impaired exchange.
Reasoning steps for option A
For ppa-25 option A, which two findings must be reconciled before accepting this choice?
In ppa-25, option A must account for rapid fluid loss from polyhydramnios while remaining consistent with bleeding with constant pain and high tone.
For ppa-25 option A, what comparison determines whether this choice outranks the alternatives?
Option A remains preferred in ppa-25 because choose the response that addresses that problem within the stated time budget for ppa-25.
B. Uterine rupture through the prior cesarean scar (Why this does not fit)
Uterine rupture can cause pain and fetal compromise, but no prior uterine scar or loss of uterine contour is supplied. Sustained hypertonic tenderness after decompression better supports abruption.
Reasoning steps for option B
For ppa-25 option B, which two findings must be reconciled before accepting this choice?
For ppa-25, option B may initially fit rapid fluid loss from polyhydramnios, but it also must explain late decelerations.
For ppa-25 option B, what comparison determines whether this choice outranks the alternatives?
Option B falls behind in ppa-25 because the combined pattern is better resolved by connect rapid uterine decompression to placental separation and impaired exchange..
C. Umbilical cord prolapse after membrane rupture (Why this does not fit)
Cord prolapse can produce sudden fetal bradycardia, but it does not explain maternal bleeding with a persistently painful, high-tone uterus. A satisfactory mechanism must account for both maternal and fetal findings.
Reasoning steps for option C
For ppa-25 option C, which two findings must be reconciled before accepting this choice?
For ppa-25, option C may initially fit rapid fluid loss from polyhydramnios, but it also must explain late decelerations.
For ppa-25 option C, what comparison determines whether this choice outranks the alternatives?
Option C falls behind in ppa-25 because the combined pattern is better resolved by connect rapid uterine decompression to placental separation and impaired exchange..
D. Rupture of an unprotected fetal vessel over the cervix (Why this does not fit)
Vasa previa can cause bleeding and fetal collapse after membrane rupture, but the marked uterine pain and sustained high tone favor placental separation rather than isolated fetal-vessel injury.
Reasoning steps for option D
For ppa-25 option D, which two findings must be reconciled before accepting this choice?
For ppa-25, option D may initially fit rapid fluid loss from polyhydramnios, but it also must explain late decelerations.
For ppa-25 option D, what comparison determines whether this choice outranks the alternatives?
Option D falls behind in ppa-25 because the combined pattern is better resolved by connect rapid uterine decompression to placental separation and impaired exchange..
Takeaway: A rapid change in uterine distension can precede placental separation and impaired exchange.
A. It means imaging must have confirmed the diagnosis before delivery could be justified (Why this does not fit)
Imaging can contribute to assessment when time and clinical condition permit. Urgent management can be justified by severe clinical and fetal findings without a visible hematoma. The need for timely treatment is not conditional on later tissue confirmation.
Reasoning steps for option A
For ppa-26 option A, which two findings must be reconciled before accepting this choice?
For ppa-26, option A may initially fit convincing acute uterine and fetal pattern, but it also must explain nondiagnostic later histology.
For ppa-26 option A, what comparison determines whether this choice outranks the alternatives?
Option A falls behind in ppa-26 because the combined pattern is better resolved by preserve a convincing clinical abruption diagnosis despite nondiagnostic histology..
B. It does not by itself invalidate a clinically convincing abruption diagnosis (Best answer)
Clinical and histopathologic abruption diagnoses have imperfect concordance. The documented acute uterine and fetal findings remain relevant despite nondiagnostic tissue sampling. Integrate pathology with the event rather than treating it as an infallible retrospective exclusion test.
Reasoning steps for option B
For ppa-26 option B, which two findings must be reconciled before accepting this choice?
In ppa-26, option B must account for convincing acute uterine and fetal pattern while remaining consistent with clinical abruption diagnosis.
For ppa-26 option B, what comparison determines whether this choice outranks the alternatives?
Option B remains preferred in ppa-26 because choose the response that addresses that problem within the stated time budget for ppa-26.
C. It establishes placenta accreta spectrum as the explanation for the bleeding (Why this does not fit)
placenta accreta spectrum is a disorder of abnormal placental attachment with specific clinical and anatomic evidence. A nondiagnostic abruption specimen does not supply evidence of abnormal attachment. Failure to confirm one diagnosis does not automatically establish another.
Reasoning steps for option C
For ppa-26 option C, which two findings must be reconciled before accepting this choice?
For ppa-26, option C may initially fit convincing acute uterine and fetal pattern, but it also must explain nondiagnostic later histology.
For ppa-26 option C, what comparison determines whether this choice outranks the alternatives?
Option C falls behind in ppa-26 because the combined pattern is better resolved by preserve a convincing clinical abruption diagnosis despite nondiagnostic histology..
D. It proves the acute maternal and fetal findings were unrelated to the placenta (Why this does not fit)
A convincing tissue finding can support a placental diagnosis. Absence of definitive histology does not establish an alternative explanation for the documented clinical event. A negative confirmatory study is not proof of an unrelated cause.
Reasoning steps for option D
For ppa-26 option D, which two findings must be reconciled before accepting this choice?
For ppa-26, option D may initially fit convincing acute uterine and fetal pattern, but it also must explain nondiagnostic later histology.
For ppa-26 option D, what comparison determines whether this choice outranks the alternatives?
Option D falls behind in ppa-26 because the combined pattern is better resolved by preserve a convincing clinical abruption diagnosis despite nondiagnostic histology..
Takeaway: Abruption remains a clinical diagnosis when later pathology is nondiagnostic.