Locate a retained duct stone, distinguish obstruction from infected obstruction, and choose confirmatory imaging, therapeutic ERCP, or urgent drainage.
A blocked duct and an infected blocked duct are not the same emergency. Establish the anatomy, look for systemic illness, and decide whether the next step should confirm a stone or drain the system.
Locate the blockage and identify what lies upstream
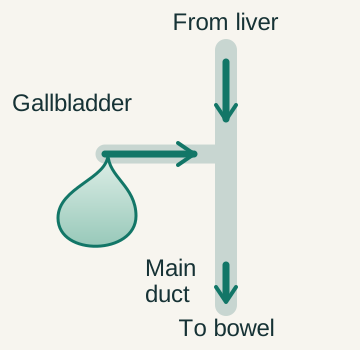
The liver makes bile, which passes through hepatic ducts toward the common bile duct and intestine. The gallbladder joins this pathway through the cystic duct. A transient cystic-duct obstruction mainly affects the gallbladder reservoir. A stone in the common duct can instead obstruct bile draining from the liver. Choledocholithiasis is the term for stones in that common duct. [1][4][5]
Obstructed bile delivery can increase conjugated bilirubin in blood. Some enters urine, while less pigment reaches the intestine. Jaundice, dark urine, and pale stools therefore make sense as consequences of altered pigment flow. Alkaline phosphatase and GGT often support a cholestatic pattern, although early or changing obstruction can produce a mixed biochemical picture. [1][5]
A stone near the shared biliary and pancreatic outlet can also be associated with pancreatitis. Pain and elevated pancreatic enzymes answer a different question from whether a stone remains in the duct. Some stones pass; others remain and continue to obstruct. Do not use the diagnosis of gallstone pancreatitis as automatic proof that therapeutic duct access is still needed. [1]
Stones are not the only causes of obstructed infected bile. Benign or malignant strictures and obstructed stents can create a similar problem. The immediate question is whether drainage is impaired and infection is present. The longer-term question is why the obstruction occurred and how to prevent another episode. [2][3]
Can impair hepatic bile drainage and raise conjugated bilirubin. [1][5]
Distal outlet
May involve pancreatic drainage as well as bile flow. [1]
Look for inflammation plus evidence of a biliary source
Acute cholangitis is infection associated with impaired biliary drainage. Stagnant bile and increased pressure facilitate bacterial proliferation and spread into the circulation. The intestine can supply organisms, but it does not manufacture the bile being trapped. This distinction matters when explaining why antibiotics may need to be paired with an anatomic drainage procedure. [2][3]
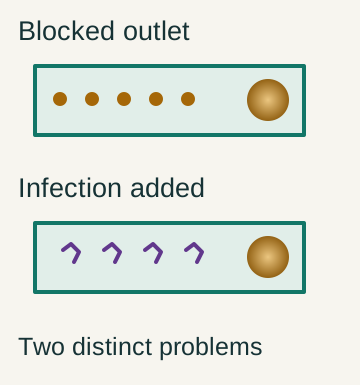
The lower example adds infection to a blocked route. A duct stone or dilation alone does not establish the inflammatory evidence needed for cholangitis.
The classic Charcot triad is fever, right upper abdominal pain, and jaundice. It is a useful recognition pattern but has limited sensitivity. An older adult may have confusion, malaise, or hypotension without reporting a textbook pain history. Absence of the complete triad does not safely exclude cholangitis. Shock or altered consciousness should accelerate care rather than become a required diagnostic checklist. [2][3]
TG18 groups diagnostic evidence into systemic inflammation, cholestasis, and imaging. Inflammation includes fever, chills, or inflammatory laboratory abnormalities. Cholestasis includes jaundice or abnormal liver tests. Imaging can show duct dilation or an obstructing cause such as a stone, stricture, or stent problem. A scan supports the source but cannot alone prove infection. [3]
Under TG18, systemic inflammation plus either cholestasis or imaging supports a suspected diagnosis. Evidence from all three categories supports a definite diagnosis. This structured approach helps recognize an incomplete classic presentation. Treatment should not wait for an academic label to become perfect when the clinical picture already indicates a dangerous infected obstruction. [3]
Inflammation Find clinical or laboratory evidence of a systemic response. [3]
Cholestasis Identify jaundice or liver-test abnormalities. [3]
Imaging Look for impaired drainage or its cause. [3]
Integrate Inflammation plus one other category is suspected; all three is definite under TG18. [3]
Use the revised adult criteria before choosing diagnostic ERCP
In a stable adult without an immediate drainage emergency, estimate the likelihood of a retained common-duct stone. The 2019 ASGE guideline identifies three high-risk routes. These are a duct stone seen on ultrasound or cross-sectional imaging, ascending cholangitis, or the combination of total bilirubin greater than 4 mg/dL and a dilated common duct. Any one route can justify proceeding toward therapeutic duct intervention. [1]
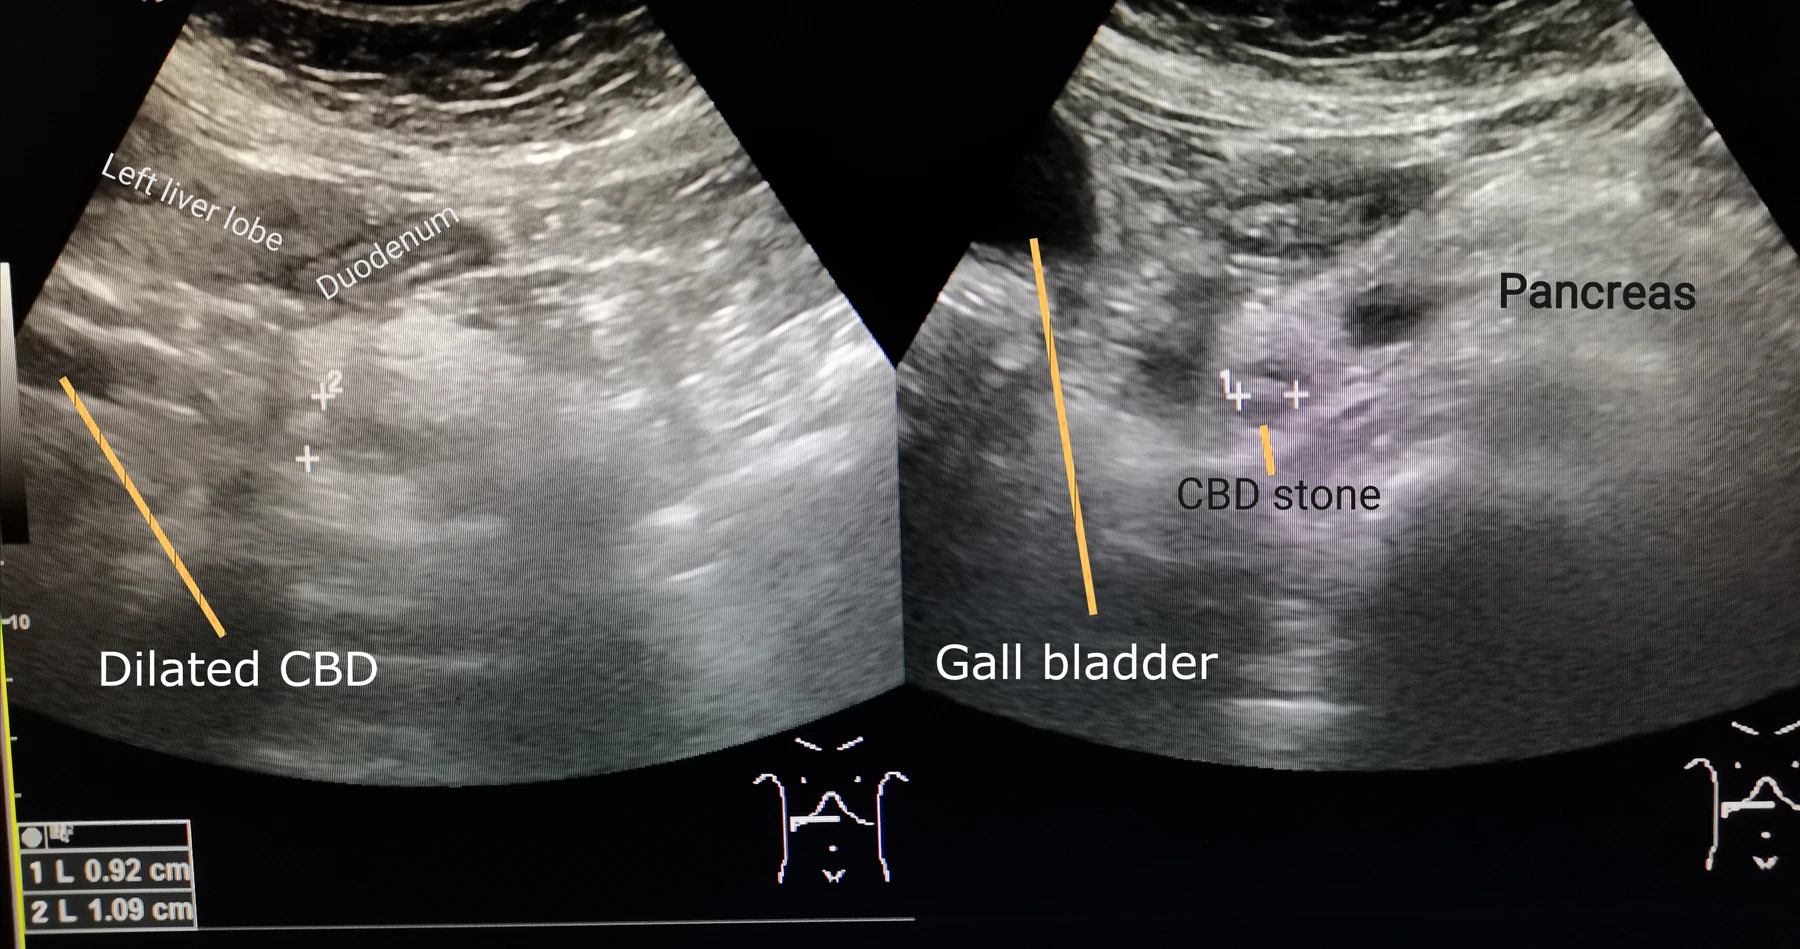
Published ultrasound shows a distal common-duct stone and upstream dilation. The two panels belong to one source image. They demonstrate anatomy, not infection by themselves. Whole image retained.
The word and is essential in the laboratory-plus-dilation route. Bilirubin greater than 4 mg/dL alone is not the revised high-risk combination. Nor does dilation alone establish it. The guideline defines dilation for this rule as greater than 6 mm with the gallbladder present and uses 8 mm after cholecystectomy. Interpret diameter in the actual anatomic setting rather than applying one cutoff universally. [1]
Intermediate-risk features include abnormal liver blood tests, age older than 55 years, or duct dilation without a high-risk route. These patients usually need confirmation by EUS, MRCP, or an appropriate operative duct-imaging strategy. This adult prediction scheme is not a validated universal pediatric rule and should not replace clinical judgment in unusual anatomy or a changing acute illness. [1]
A worked comparison shows why the conjunction matters. A stable adult with bilirubin 5 mg/dL but no duct dilation or visible stone does not meet that combined high-risk route. A similar adult with bilirubin 5 mg/dL and an 8-mm duct while the gallbladder remains does. A demonstrated duct stone is independently high risk even when bilirubin is lower. [1]
High risk
Stone on imaging, cholangitis, or bilirubin greater than 4 plus duct dilation. [1]
Intermediate risk
Abnormal liver tests, age above 55, or dilation without a high-risk route. [1]
Next question
Confirm uncertain stones; treat established high-probability obstruction appropriately. [1]
Distinguish finding the stone from treating it
Ultrasound is a practical first study, but may miss a small distal duct stone. Persistent suspicion after a negative study should be assessed using the clinical probability and laboratory trajectory. A reassuring-looking scan does not erase a clear cholangitis presentation, and repeat elective imaging must not delay source control in an unstable patient. [1][2][4]
MRCP maps the biliary tree using magnetic resonance imaging. EUS uses an ultrasound probe on an endoscope and can provide detailed views of the distal duct. It is minimally invasive, not entirely noninvasive. Both are useful confirmation options in intermediate-risk adults; choice depends on contraindications, expertise, availability, and whether a linked therapeutic procedure is appropriate. [1]
ERCP provides access to the duct for drainage, stone removal, and other therapy. It also carries risks, including pancreatitis, bleeding, infection, and perforation. Avoiding unnecessary diagnostic ERCP is therefore a clinical objective rather than an inconvenience. Once a therapeutic indication is established, the procedural plan can be chosen with the endoscopic and surgical teams. [1][2]
Gallstone pancreatitis without cholangitis, continuing biliary obstruction, or choledocholithiasis is not an indication for routine urgent ERCP. If a retained obstructing stone or cholangitis is present, that exception no longer applies. The pancreatic diagnosis and the drainage question should be assessed separately, then combined into one coherent plan. [1]
MRCP
Answers a duct-anatomy question without entering the duct. [1]
EUS
Provides detailed imaging through an endoscope. [1]
ERCP
Treats or drains the duct when the indication justifies its risks. [1][2]

 Enlarge the whole image
 Enlarge the whole image
 Enlarge the whole image
