Trace gastric acid, intrinsic factor, pepsinogen, and protective secretions to their source cells, then predict how drugs, cell loss, and feedback alter function.
Two patients have high serum gastrin. One has recurrent ulcers and very acidic gastric fluid; the other has an almost acid-free stomach and vitamin B12 deficiency. The hormone concentration alone cannot explain either patient. Ask which cell is functioning, where its product goes, and whether the signal is causing the abnormality or responding to it.
By the end, you should be able to trace acid across a parietal cell, distinguish acid suppression from intrinsic-factor failure, and predict what happens when gastric protection or duodenal neutralization fails. The route through the lesson is source cell, transport, feedback, vitamin handling, digestion, then protection.
Which cell supplies the missing product?
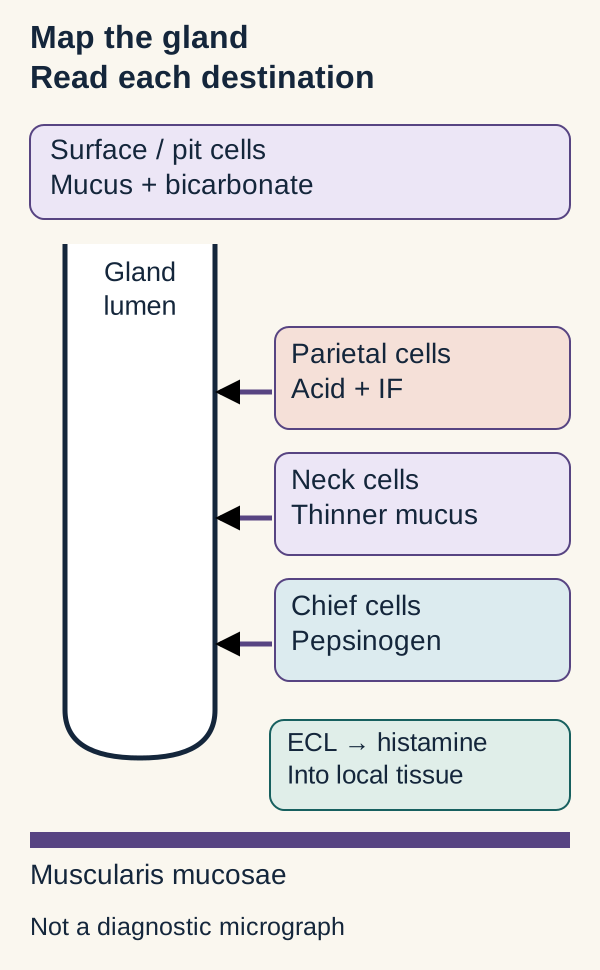
Location predicts function, but a secretion's origin is not necessarily its destination. Fundic and body glands contain acid-secreting parietal cells and pepsinogen-secreting chief cells. Gastrin is released mainly from antral G cells into blood, not into gastric juice. ECL means enterochromaffin-like: these nearby signaling cells release histamine, which acts locally on parietal cells. [1][2]
Cell populations overlap; the drawing shows their predominant distribution, not rigid floors. Read each arrow by its destination. [1][2]
Surface and pit mucous cells establish the mucus-bicarbonate barrier facing the lumen. Mucous neck cells contribute a different, thinner mucus within the gland; they should not be treated as identical to surface barrier cells. Large eosinophilic parietal cells are prominent in upper and middle oxyntic glands. Their abundant mitochondria supply energy for transport, and canaliculi provide secretory membrane area. Deeper chief cells are basophilic because their abundant rough endoplasmic reticulum supports protein synthesis. The muscularis mucosae is a thin muscle layer below the glands, not another secretory compartment. [1][5]
Trace the drawn path from a deep chief cell into the lumen. Now predict the destination of histamine from the separate ECL box: a neighboring parietal cell through local tissue, not food in the lumen. This distinction separates an exocrine digestive product from a local regulator.
Check your prediction: would injury limited to deep chief cells directly abolish intrinsic factor?
No. The injured population supplies pepsinogen. Intrinsic factor comes from parietal cells. Extensive gland atrophy can affect both populations, but a selective-cell question requires selective consequences.
Transfer that distinction to a biopsy report: a basophilic basal population suggests protein secretion, whereas pink cells with canaliculi suggest acid transport. Do not diagnose a disorder from schematic color alone; actual pathology requires a properly sampled and interpreted specimen.
Acid enters the lumen while bicarbonate enters blood
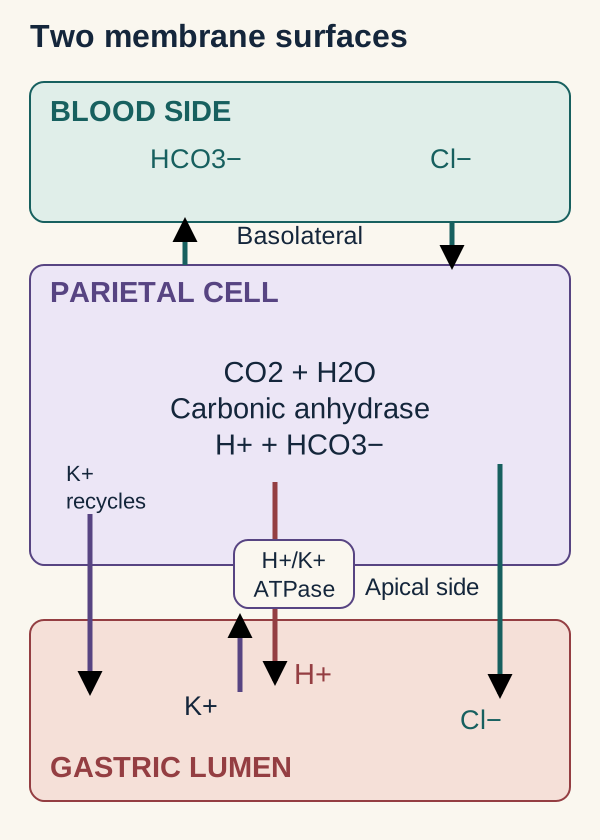
Does the parietal cell pour preformed acid out of storage? No. It generates ions and transports them across different membrane surfaces. Apical means toward the gland lumen; basolateral means toward interstitium and blood. Carbonic anhydrase facilitates the reaction CO2 + H2O ⇌ H+ + HCO3−. The products have different destinations. [7]
Follow the labeled directions rather than color. Acid secretion and the gastric venous alkaline tide are opposite-sided consequences of the same cellular process. Original transport model. [2][7]
The apical H+/K+-ATPase uses ATP to export H+ in exchange for luminal K+. Potassium recycles through apical channels so that exchange can continue. Chloride enters from the blood side through basolateral chloride-bicarbonate exchange and exits through apical channels. Hydrogen and chloride accumulate together in luminal fluid as hydrochloric acid. These coupled fluxes occur together; the diagram is not a claim that every transporter waits for the preceding one.
Bicarbonate exits basolaterally, producing a temporary postprandial alkaline tide in blood draining the stomach. This is not gastric-lumen bicarbonate secretion and is not automatically a systemic metabolic alkalosis. Secretion into the intestine and whole-body acid-base regulation also matter. Pancreatic bicarbonate secretion has an opposing acid-base effect on venous blood. [3][7]
Three signals, one final pump
Secretagogues act at tissue-facing basolateral receptors, whereas the acid pump operates at the apical canalicular surface. Acetylcholine activates M3 receptors and calcium signaling. Gastrin acts at CCK2 receptors, also called CCK-B receptors. Its important acid-stimulating effect in humans is through ECL-cell histamine release, with additional direct and potentiating actions on parietal cells. Histamine activates H2 receptors, raising cAMP. Calcium and cAMP pathways reinforce each other rather than behaving as independent on/off switches. Stimulation also brings pump-containing membranes to the canalicular surface. [2]
Predict the difference between blocking a receptor and blocking the pump. An H2 antagonist reduces histamine-dependent stimulation, including much of gastrin's indirect effect. A proton-pump inhibitor such as omeprazole acts on the final H+/K+-ATPase step, suppressing acid output across different initiating signals. It does not neutralize acid already in the lumen in the way an antacid does. [8]
Check the transport prediction: which blood-side flux falls when acid secretion is strongly suppressed?
The acid-linked bicarbonate efflux decreases, so the gastric contribution to the alkaline tide decreases. The pump is apical, but changing its activity changes the demand on the coupled basolateral exchanger.
Now apply that reasoning to stronger histamine stimulation: with functioning cells, pumps, and substrates, luminal H+ secretion and blood-side bicarbonate delivery increase together. A more acidic lumen does not imply that the blood leaving the stomach has become more acidic.
High gastrin can report opposite acid states
When acid lowers antral pH, D-cell somatostatin restrains G-cell gastrin. Somatostatin also inhibits ECL histamine release and parietal-cell acid secretion. When acid output falls, the acid-dependent restraint on gastrin weakens. High gastrin plus high gastric pH can be a feedback response, not proof of a gastrinoma.[2][6]
Change the cause, then trace the consequences
Use the comparison below as a qualitative model. Start with a functioning parietal cell, then apply either perturbation. Each optional response answers one prediction: acid output, feedback, or the separate carrier route. Earlier responses remain available; no response is required to read onward. Close the responses to reset the comparison. These immediate state diagrams are not numerical patient simulations.
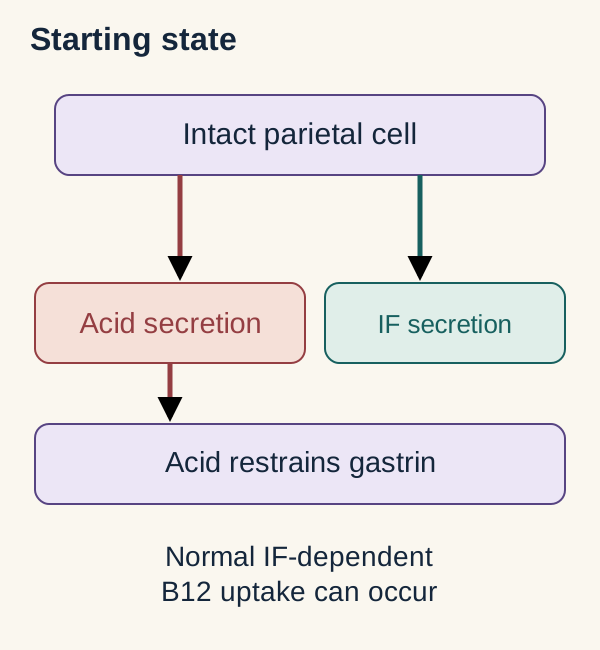
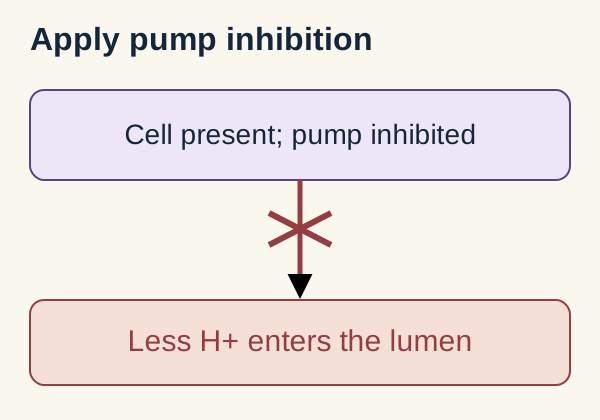
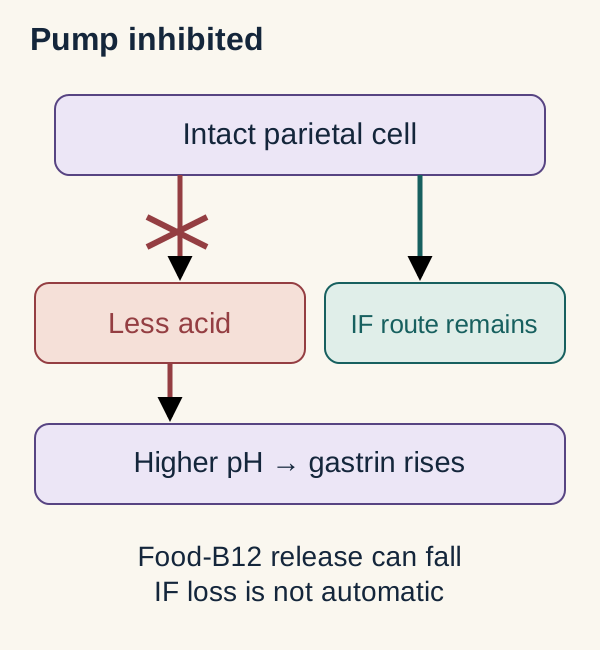
Starting state: an intact secretory cell supplies two distinct products. The feedback path monitors acidity, not vitamin absorption. Original qualitative model. [2][4]Apply pump inhibition: which way does acid output change?
With less acid, which way does feedback-driven gastrin change?
Gastrin can rise because the acid-dependent restraint is weaker. [2]
Does inhibiting the pump necessarily eliminate intrinsic factor?
No. The separate carrier route need not be lost when the cell survives. [4][8]
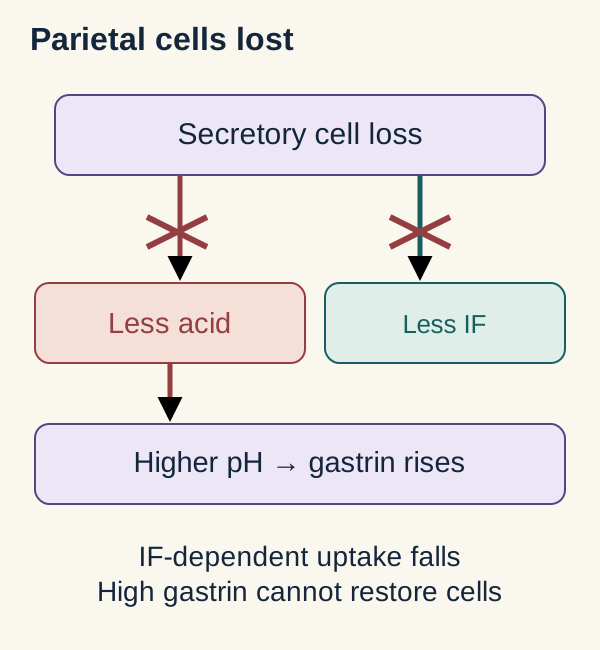
The final comparison retains the earlier acid and feedback results while displaying the carrier distinction.Apply parietal-cell loss: which way does acid output change?
One changed output: less acid reaches the lumen.
Acid output falls because the secretory-cell population is lost. [5]
With a responding antrum, which way does gastrin change after cell loss?
Gastrin rises in response to the loss of acid-dependent feedback. [5]
Which separate parietal-cell product is also lost?
Intrinsic factor falls because its source cells have been destroyed. [5]
The carrier route now differs from isolated pump inhibition, even though the acid and gastrin directions resemble it.
The complete comparison is also readable without opening either response: effective pump inhibition means less acid, higher pH, and often higher gastrin, without obligatory intrinsic-factor loss. Autoimmune parietal-cell destruction means less acid and less intrinsic factor, usually with higher gastrin. These are idealized patterns; disease extent and treatment alter measured values.
Now consider recurrent distal duodenal ulcers with diarrhea and high gastrin despite strongly acidic gastric fluid. Autonomous gastrin secretion becomes a concern because gastrin is high when normal feedback should suppress it. A gastrinoma can produce this pattern, but clinical confirmation requires more than a hormone result. Acid hypersecretion can overwhelm duodenal neutralization and contribute to diarrhea and maldigestion. [6]
In the classical diagnostic approach, fasting gastrin greater than ten times the assay upper limit together with gastric pH at or below 2 strongly establishes the biochemical pattern of Zollinger-Ellison syndrome after relevant alternatives are excluded. Smaller increases require further evaluation. Acid suppression confounds interpretation, and secretin testing can be misleading in hypochlorhydria. Do not abruptly stop a PPI to test a patient with suspected severe acid hypersecretion. Specialist-supervised assessment protects against rapid acid-related complications. [6]
Intrinsic factor is made in the stomach but used in the ileum
Can normal acid secretion guarantee normal B12 absorption? No. Acid helps prepare food-bound vitamin; intrinsic factor enables a later receptor-mediated uptake step. Separating those jobs explains why an acid problem, a carrier problem, and an ileal problem can produce different laboratory patterns. [4]
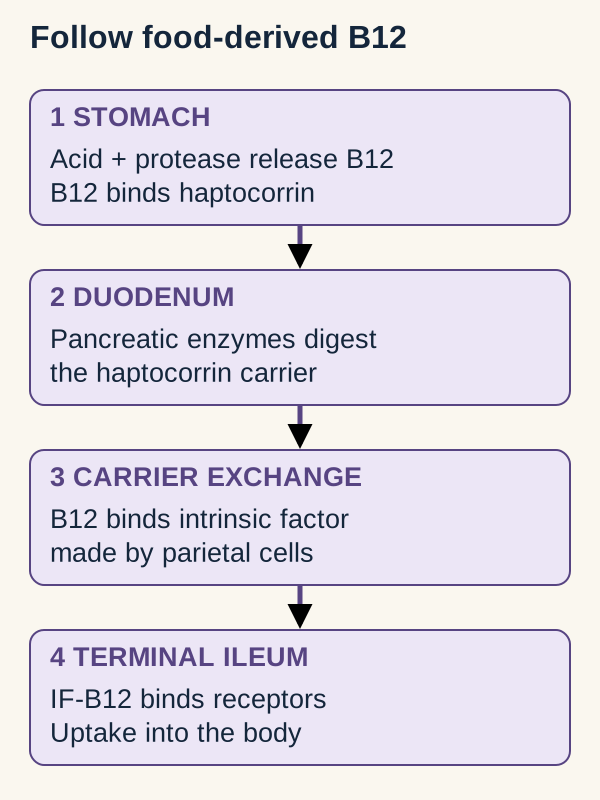
Original route map. Trace the vitamin forward, then identify where a proposed defect first interrupts it. This depicts the normal food-derived, receptor-mediated pathway. [4]
Gastric acid and protease help release B12 from food proteins. Freed B12 binds haptocorrin, also called R protein. In the duodenum, pancreatic digestive enzymes break down that carrier, allowing B12 to bind intrinsic factor. The complex reaches receptors in the terminal ileum. The stomach supplies the carrier; the ileum supplies the uptake site.
Place an imaginary interruption at each location. Poor food release impairs absorption of food-bound B12, but free vitamin in fortified foods or supplements does not need that initial separation step. Intrinsic-factor failure impairs normal receptor-mediated absorption even when the vitamin is already free. Ileal resection can impair uptake despite normal intrinsic-factor secretion. Severe pancreatic dysfunction can interfere earlier with carrier processing as well as digestion. [4]
Check your localization: would adding more acid correct B12 malabsorption after terminal ileal resection?
No. Better food release does not recreate the uptake surface. The absent step lies downstream from acid and intrinsic-factor secretion.
Autoimmune gastritis primarily injures corpus and fundus oxyntic glands. Loss of acid and intrinsic factor can eventually produce pernicious anemia, a late manifestation characterized by B12 deficiency and macrocytic anemia. Body stores can delay symptoms for years. Neurologic injury can occur without anemia, so a normal mean corpuscular volume does not exclude clinically important B12 deficiency. Iron deficiency can also accompany corpus-predominant atrophy and may appear earlier. [4][5]
In a new patient with pernicious anemia, explaining absorption is only part of the task. The AGA expert review advises endoscopy with topographical biopsies if no recent examination has been performed, both to document corpus-predominant atrophy and assess gastric neoplasia. Check iron and B12 status rather than assuming one deficiency excludes the other. Physiological dependence on intrinsic factor is not a claim that every therapeutic oral dose is ineffective: small fractional absorption at high doses can occur, while parenteral replacement bypasses gastrointestinal absorption. Treatment selection requires clinical assessment. [4][5]
Acid starts gastric proteolysis; bicarbonate changes the environment
Why does a chief cell release a precursor rather than active pepsin? A protease should attack food in the lumen, not the cell that stores it. Chief cells store the inactive zymogen pepsinogen in secretory granules and release it into the gland lumen. Low luminal pH initiates its conversion to pepsin, and active pepsin can activate additional pepsinogen. Acid also denatures proteins and limits many ingested microbes; it is not itself a protein-digesting enzyme. [1][2]
Compare two samples containing equal pepsinogen. One enters an acidic gastric environment; the other encounters strongly suppressed acid secretion. Predict activity rather than assuming equal precursor means equal digestion. The acidic sample supports activation and pepsin activity. The higher-pH sample has less effective gastric proteolysis even if chief cells continue supplying precursor. [8]
After chyme reaches the duodenum, neutralization becomes helpful rather than harmful. Acid stimulates intestinal S cells to release secretin; secretin stimulates bicarbonate-rich pancreatic duct fluid. Acinar cells supply digestive enzymes, with CCK and cholinergic signals important for their secretion. Thus ductal bicarbonate and acinar enzymes are distinct outputs, even though both travel in pancreatic juice. [3] Duodenal glands also supply bicarbonate-rich mucus, and bile ducts contribute bicarbonate-containing fluid. These are additional sources of alkaline secretion, not substitutes for the full pancreatic response. [10][11]
Rising duodenal pH reduces pepsin activity and supports pancreatic enzyme function. Pancreatic protease activation uses a different trigger: brush-border enteropeptidase initiates trypsinogen conversion to trypsin, and trypsin activates additional protease precursors. Do not substitute gastric acid for enteropeptidase in that sequence. [3]
Check the prediction: if ductal bicarbonate delivery falls but enzyme output is preserved, is digestion necessarily normal?
No. Enzymes can arrive in an environment that remains too acidic for normal function. Secretion of an enzyme and effective activity at its destination are different requirements.
Transfer this to the patient with acid hypersecretion: excessive acid delivery can exceed available neutralizing capacity even when the pancreas is responding. Conversely, weak pancreatic bicarbonate delivery can leave the duodenum acidic without excessive gastric acid production. Identify which side of the acid-neutralization balance is abnormal before assigning the organ at fault.
Normal acid output can injure an unprotected surface
Does a gastric erosion prove excess acid secretion? No. Injury reflects both the luminal challenge and the tissue's ability to resist it. Mucus holds a bicarbonate-rich layer near the epithelium, maintaining a much less acidic cell-surface environment than the bulk gastric lumen. Tight junctions, rapid epithelial repair, and adequate blood flow provide additional protection. [1][9]
Imagine normal gastric acid bathing two surfaces: one has intact bicarbonate-rich mucus and perfusion; the other has diminished local protection after NSAID exposure. Point to the changed variable before predicting injury. The second surface can develop erosions even if measured acid output has not increased. Cyclooxygenase inhibition reduces prostaglandin-dependent protection. Prostaglandins support mucus, bicarbonate, and perfusion and can inhibit parietal-cell acid secretion. Blood flow also supplies oxygen and nutrients and helps clear acid that reaches tissue. [2][9]
Keep three restraints distinct. Somatostatin reduces secretory drive within the gastric signaling network. Prostaglandins support the mucosal surface as well as restraining acid secretion. Intestinal feedback reduces additional gastric delivery while the duodenum processes incoming acid and nutrients. Secretin promotes neutralization; other intestinal hormonal and neural signals contribute to reduced gastric secretion and slower emptying. This is coordinated feedback, not one universal hormone receptor. [1][2][3]
Check the distinction: does lowering gastric acid replace the mucus barrier or restore intrinsic factor?
No. It reduces the luminal acid challenge. It does not directly replace protective mucus, restore mucosal perfusion, or supply intrinsic factor. A treatment can help one part of the problem without correcting every affected function.
For a new case, name the failed task first: acid generation, vitamin carriage, zymogen activation, acid neutralization, or surface protection. Then locate the cell or tissue and predict the remaining outputs. A secretion list becomes useful when one change lets you predict what stays intact as well as what fails.
Independent practice
Case 1
Show answer and explanations for case 1
A. Pepsinogen (Why this does not fit)
Gastric proteolysis helps release B12 from food. The question concerns the carrier-dependent uptake step, not only food-protein digestion.
Reasoning steps for option A
How does pepsinogen-related gastric proteolysis help make food-bound B12 available?
It helps release B12 from food proteins.
Why does food-protein digestion not explain impaired receptor-mediated B12 absorption here?
The defect is in carrier-dependent uptake, not simply release of B12 from food.
What distinction helps separate B12 release from B12 uptake?
Digestion releases food-bound B12; intrinsic factor supports its uptake.
B. Intrinsic factor (Best answer)
Intrinsic factor enables receptor-mediated uptake of B12. Corpus parietal-cell loss removes the carrier required by the terminal ileum.
Reasoning steps for option B
What does intrinsic factor enable in B12 absorption?
It enables receptor-mediated uptake of B12 in the terminal ileum.
Why does autoimmune corpus atrophy point to loss of the product needed for B12 uptake?
Corpus parietal-cell loss reduces intrinsic factor, which is required for receptor-mediated uptake.
What is the reusable role of intrinsic factor in B12 absorption?
The stomach supplies intrinsic factor, and the terminal ileum absorbs its B12 complex.
C. Gastrin (Why this does not fit)
Gastrin changes when acid output falls. It regulates acid secretion but does not carry B12 to ileal receptors.
Reasoning steps for option C
How can low gastric acid output affect gastrin levels?
Reduced acid-dependent restraint can allow gastrin to rise.
Why is gastrin not the gastric product that carries B12 to ileal receptors?
A. Increased intrinsic-factor secretion (Why this does not fit)
Parietal cells remain available to produce intrinsic factor. Preserved cells do not imply increased carrier output, and carrier secretion does not explain the demonstrated defense defect.
Reasoning steps for option A
Which gastric cell type secretes intrinsic factor?
Parietal cells.
Does preserved parietal-cell number establish increased intrinsic-factor secretion?
No; cell preservation does not establish increased secretion.
What does preserved parietal-cell function imply about intrinsic-factor availability?
It can remain available; cell preservation alone does not imply increased output.
B. Increased chief-cell pepsinogen synthesis (Why this does not fit)
Pepsin can contribute to injury at an exposed surface. The evidence identifies loss of prostaglandin-supported protection, not increased precursor production.
Reasoning steps for option B
What do chief cells secrete that can be converted to pepsin?
Pepsinogen.
Does reduced bicarbonate identify increased pepsinogen synthesis?
No; it identifies impaired mucosal protection, not increased precursor production.
What is the reusable distinction between pepsinogen secretion and bicarbonate loss?
Pepsinogen is a digestive precursor; bicarbonate supports mucosal defense.
C. Reduced circulating gastrin (Why this does not fit)
Lower gastrin could reduce acid stimulation. Unchanged acid output and reduced epithelial bicarbonate favor a protective deficit rather than suppressed G-cell drive.
Reasoning steps for option C
What hormone stimulates gastric acid secretion?
Gastrin.
Does unchanged acid output support reduced gastrin as the direct explanation for injury?
No; the observed bicarbonate loss supports impaired protection.
What does reduced epithelial bicarbonate indicate about gastric injury?
A weakened mucosal defense, not necessarily altered gastrin.
D. Reduced mucosal blood flow (Best answer)
Prostaglandins support gastric mucosal perfusion. Cyclooxygenase inhibition can reduce both bicarbonate protection and perfusion without acid hypersecretion.
Reasoning steps for option D
How do prostaglandins affect gastric mucosal blood flow?
They support mucosal perfusion; cyclooxygenase inhibition can reduce it.
Why can naproxen reduce both bicarbonate secretion and mucosal perfusion?
Cyclooxygenase inhibition lowers prostaglandin synthesis, weakening both protective effects.
How can NSAIDs cause gastric injury when acid output is unchanged?
They reduce prostaglandin-dependent defenses; NSAID injury can reflect impaired protection without acid hypersecretion.
Takeaway: NSAID injury can reflect reduced protection despite normal acid output.
Chief cells synthesize the gastric protease precursor. Deep gland location and abundant rough endoplasmic reticulum identify that population.
Reasoning steps for option A
Why are chief cells basophilic?
Their abundant rough endoplasmic reticulum supports protein synthesis.
What precursor do chief cells secrete?
Pepsinogen, the precursor of pepsin.
Which cells supply pepsinogen in fundic glands?
Deep chief cells; fundic chief cells secrete pepsinogen.
B. Parietal cells and intrinsic factor (Why this does not fit)
Parietal cells are another major fundic secretory population. The preserved eosinophilic upper cells, not the depleted basal cells, supply intrinsic factor.
Reasoning steps for option B
What important product do parietal cells secrete?
Intrinsic factor, which supports vitamin B12 absorption.
Which finding argues against parietal cell depletion here?
The upper eosinophilic cells are intact.
Which gastric cells secrete hydrochloric acid?
Parietal cells secrete hydrochloric acid.
C. ECL cells and histamine (Why this does not fit)
ECL cells regulate fundic acid secretion. The described large basal protein-synthesizing population is chief cells, not the local histamine regulator.
Reasoning steps for option C
What signal do ECL cells release?
Histamine, which stimulates acid secretion.
Why does the described depleted population not fit ECL cells?
It consists of deep basophilic cells rich in rough endoplasmic reticulum.
How does histamine from ECL cells affect parietal cells?
It stimulates acid secretion through H2 receptors.
D. Surface cells and mucus (Why this does not fit)
Surface mucous cells secrete a protective glycoprotein product. The surface is preserved and the depleted cells are deep in the gland.
Reasoning steps for option D
What do surface mucous cells secrete?
Mucus that helps protect the gastric lining.
Which observation rules out surface cells as the depleted population?
The surface epithelium remains intact.
Where are gastric surface mucous cells located?
They line the gastric lumen and pits.
Takeaway: Deep basophilic chief cells supply pepsinogen, not intrinsic factor.
A. Nutrient-stimulated intestinal I-cell secretion (Why this does not fit)
CCK contributes to pancreatic enzyme secretion. Preserved enzyme delivery and a secretin-rescuable fluid defect favor S-cell signaling rather than I-cell enzyme stimulation.
Reasoning steps for option A
What pancreatic secretion does CCK chiefly stimulate?
CCK chiefly stimulates enzyme secretion.
Why does normal enzyme delivery argue against deficient I-cell signaling?
I-cell CCK promotes enzyme secretion, which is preserved here.
What is the reusable distinction between CCK and secretin?
B. Meal-stimulated antral G-cell secretion (Why this does not fit)
Gastrin stimulates gastric acid secretion, but acid is perfused directly into the duodenum here. It does not account for deficient pancreatic bicarbonate with preserved response to secretin.
Reasoning steps for option B
What gastric secretion does gastrin stimulate?
Gastrin stimulates gastric acid secretion.
Why does direct duodenal acid perfusion weaken gastrin deficiency as the explanation?
The acid stimulus is supplied directly to the duodenum, bypassing gastric acid secretion.
C. Acid-stimulated intestinal S-cell secretion (Best answer)
Duodenal acid normally stimulates intestinal S-cell secretin release. Responsiveness to injected secretin supports preserved ductal capacity and favors deficient endogenous signaling among these choices; rescue does not prove every ductal function normal.
Reasoning steps for option C
What intestinal hormone do S cells release in response to acid?
S cells release secretin in response to duodenal acid.
Why does intravenous secretin rescue favor impaired endogenous signaling?
It shows that supplied secretin can restore bicarbonate output.
How does secretin produce the bicarbonate response?
A. Exposed-surface pH rises; intrinsic-factor output preserved (Why this does not fit)
Surviving oxyntic cells can preserve intrinsic-factor secretion. Loss of adherent mucus removes local bicarbonate retention, so exposed-surface pH falls rather than rises.
Reasoning steps for option A
Why could intrinsic-factor output remain intact after surface and pit epithelial denudation?
The deeper oxyntic parietal cells remain intact.
What happens to exposed-surface pH when denudation removes adherent mucus and bicarbonate retention?
It falls.
Which gastric cells produce intrinsic factor?
Parietal cells; intact parietal cells can preserve intrinsic-factor output.
B. Exposed-surface pH falls; intrinsic-factor output preserved (Best answer)
Denudation removes the adherent mucus-bicarbonate barrier, lowering exposed-surface pH. Intact oxyntic parietal cells can continue to produce intrinsic factor despite injury to surface and pit cells.
Reasoning steps for option B
Why does the exposed surface become more acidic after chemical injury?
Loss of adherent mucus reduces local bicarbonate retention.
Why can intrinsic-factor output persist despite surface denudation?
The deeper oxyntic parietal cells remain intact.
What determines whether intrinsic-factor secretion is preserved in this injury?
Preservation of parietal cells; surface injury alone need not reduce their secretion.
C. Exposed-surface pH falls; intrinsic-factor output reduced (Why this does not fit)
The lost surface barrier predicts lower exposed-surface pH. Intrinsic factor comes from the preserved deeper oxyntic parietal cells, so surface denudation alone does not reduce their output.
Reasoning steps for option C
Which predicted change follows loss of the adherent mucus-bicarbonate barrier?
Exposed-surface pH falls.
Why is reduced intrinsic-factor output not expected from the described denudation alone?
The deeper oxyntic parietal cells are intact.
What source of intrinsic factor is spared when injury is limited to surface and pit epithelium?
Oxyntic parietal cells; their preservation supports continued intrinsic-factor output.
D. Exposed-surface pH rises; intrinsic-factor output reduced (Why this does not fit)
Loss of adherent mucus lowers rather than raises exposed-surface pH. Preserved oxyntic parietal cells also oppose reduced intrinsic-factor output.
Reasoning steps for option D
What surface change does loss of adherent mucus predict?
Lower exposed-surface pH.
Which intact cell population argues against reduced intrinsic-factor output?
Deeper oxyntic parietal cells.
How should intrinsic-factor output be predicted when parietal cells are spared?
It can be preserved despite injury to the surface epithelium.
Takeaway: Surface mucus-bicarbonate loss lowers exposed gastric pH while intact deeper parietal cells preserve intrinsic-factor secretion.
The apical H+/K+-ATPase exports hydrogen and imports potassium. Inhibiting this direct acid transport also reduces the coupled basolateral bicarbonate contribution to gastric venous blood.
Reasoning steps for option A
Which apical exchange does the inhibited transporter normally perform?
It exports H+ into the lumen while importing K+.
Why does the stated lumen-facing location support this target over the basolateral sodium-potassium pump?
The H+/K+-ATPase is on the apical membrane; the Na+/K+-ATPase is basolateral.
What happens to the postprandial venous bicarbonate rise when parietal acid secretion falls?
It becomes smaller; less acid secretion produces a smaller associated alkaline tide.
B. Reduced apical H+ export/K+ entry; larger bicarbonate rise (Why this does not fit)
Apical hydrogen-potassium exchange is the relevant direct acid transport. Less hydrogen secretion yields a smaller, not larger, associated venous alkaline tide.
Reasoning steps for option B
Which apical exchange is a direct target of the drug?
The H+/K+-ATPase exports H+ and imports K+.
Does inhibiting that exchange make the postprandial venous bicarbonate rise larger or smaller?
Smaller, because reduced acid secretion reduces the associated alkaline tide.
How does the alkaline tide relate to parietal acid secretion?
It rises with acid secretion and falls when acid secretion is inhibited.
C. Reduced basolateral Na+ export/K+ entry; smaller bicarbonate rise (Why this does not fit)
Basolateral Na+/K+-ATPase exports sodium and imports potassium to sustain ionic gradients. It is not the direct lumen-facing acid secretory transport specified by the question, even though disrupting it could indirectly reduce acid.
Reasoning steps for option C
What is the normal direction of Na+ and K+ transport through the basolateral Na+/K+-ATPase?
It exports Na+ and imports K+.
Why is that pump not the direct target specified by the membrane location?
It is basolateral, whereas the drug binds the lumen-facing apical membrane.
Which transporter directly exports gastric H+ into the lumen?
The apical H+/K+-ATPase.
D. Reduced basolateral Na+ export/K+ entry; larger bicarbonate rise (Why this does not fit)
The basolateral sodium-potassium pump maintains gradients, not direct luminal hydrogen export. A fall in acid-linked flux would also reduce, not enlarge, the venous bicarbonate rise.
Reasoning steps for option D
What does the basolateral Na+/K+-ATPase transport?
It exports Na+ and imports K+ to maintain ionic gradients.
What direction should the venous bicarbonate response take when acid-linked flux falls?
It should decrease, not increase.
How should the venous alkaline tide change when parietal acid secretion is inhibited?
It should become smaller.
Takeaway: Identify the directly inhibited apical proton transport and separately predict the coupled venous bicarbonate response.
A. Inappropriate gastrin elevation despite acidity; reduced duodenal lipase activity (Why this does not fit)
Very high gastrin despite pH 1.2 indicates inappropriate secretion. Acid suppression reduces the excess acid load and should improve, not impair, delivered lipase activity.
Reasoning steps for option A
Why might markedly high gastrin suggest inappropriate secretion here?
Gastric pH 1.2 shows acidity, which should restrain gastrin release.
What does the measured gastric pH indicate about the acid state?
The stomach is strongly acidic, not low in acid.
How does suppressing excess acid affect intestinal lipase function?
It reduces acid-mediated impairment of lipase activity in the duodenum.
B. Compensatory gastrin elevation from low acid; improved duodenal lipase activity (Why this does not fit)
Low-acid feedback can raise gastrin. Gastric pH 1.2 instead documents acidity despite high gastrin, although neutralizing excess acid should improve intestinal lipase function.
Reasoning steps for option B
Why can low gastric acidity raise gastrin?
Reduced acid feedback can increase gastrin secretion.
Which measurement contradicts low-acid feedback in this patient?
The gastric pH of 1.2 indicates strong acidity.
Why can acid suppression improve fat digestion when enzyme delivery is normal?
Less acid reaches the duodenum to impair lipase activity.
C. Compensatory gastrin elevation from low acid; reduced duodenal lipase activity (Why this does not fit)
Compensatory gastrin elevation occurs with low acid. This patient has strongly acidic gastric contents, and effective acid suppression favors improved rather than reduced duodenal lipase activity.
Reasoning steps for option C
What feedback response can occur when gastric acid is low?
Gastrin secretion can rise as acid-mediated inhibition falls.
What finding rules out low gastric acid as the explanation here?
The measured gastric pH is 1.2.
What is the effect of excess gastric acid on duodenal lipase activity?
It impairs lipase activity; reducing acid can relieve that impairment.
Marked hypergastrinemia despite gastric acidity is inappropriate under the stated conditions. Effective acid suppression limits the acid load that compromises intestinal lipase despite normal enzyme delivery.
Reasoning steps for option D
Why is high gastrin inappropriate when gastric pH is 1.2?
Strong acidity should suppress gastrin release.
How can excess gastric acid contribute to fatty stools despite normal enzyme delivery?
It impairs lipase activity in the duodenum.
What change in intestinal lipase function is expected after effective acid suppression?
Lipase activity improves as the duodenal acid load falls.
Takeaway: High gastrin despite low gastric pH differs from compensatory hypergastrinemia; suppressing excess acid can improve intestinal lipase function.
A. Stronger acid-dependent gastrin restraint; preserved intrinsic-factor secretion (Why this does not fit)
Higher gastric pH weakens acid-dependent gastrin restraint, not strengthens it. Intact corpus cells can retain intrinsic-factor secretion during pump inhibition.
Reasoning steps for option A
Can intact corpus parietal cells continue intrinsic-factor secretion during proton-pump inhibition?
Yes. Pump inhibition does not by itself prevent intrinsic-factor secretion.
Does the higher gastric pH strengthen acid-dependent restraint of gastrin?
No. Less acidity weakens that restraint.
What does high gastric pH imply for gastrin feedback?
It weakens acid-dependent restraint and can raise gastrin.
B. Weaker acid-dependent gastrin restraint; reduced intrinsic-factor secretion (Why this does not fit)
Reduced acid feedback explains rising gastrin. Inhibiting the acid pump does not imply reduced carrier secretion from intact parietal cells.
Reasoning steps for option B
Does the higher gastric pH explain the rise in fasting gastrin?
A. A: food-protein release; B: intrinsic-factor availability (Best answer)
Free B12 bypasses release from food, but normal receptor-mediated uptake still requires intrinsic factor. The different responses localize A before carrier binding and B to the gastric carrier-dependent pathway.
Reasoning steps for option A
Why can Patient A absorb free B12 despite acid suppression?
Free B12 bypasses release from food proteins.
Why does Patient A's normal free-B12 absorption argue against intrinsic-factor deficiency?
At a physiological dose, free B12 still needs intrinsic factor for ileal uptake.
What gastric defect best explains Patient A's poor absorption of food-bound B12?
Impaired acid-dependent release from food; free B12 bypasses this release step.
B. A: intrinsic-factor availability; B: food-protein release (Why this does not fit)
Either gastric acid loss or carrier loss can reduce food-B12 absorption. Normal absorption of a small free dose argues against major intrinsic-factor failure in A, while B fails even after food release is bypassed.
Reasoning steps for option B
Why might intrinsic-factor deficiency seem plausible for Patient A?
It can impair absorption of food-derived B12.
What finding argues against intrinsic-factor deficiency in Patient A?
Normal absorption of a physiological free-B12 dose indicates that intrinsic-factor-dependent uptake is intact.
What does normal absorption of free B12 establish in this setting?
It supports a defect in food release rather than a defect in intrinsic-factor-dependent uptake.
C. A: haptocorrin digestion; B: ileal receptor uptake (Why this does not fit)
Pancreatic processing and ileal uptake are additional B12 requirements. Normal pancreatic function and the specified autoimmune gastric lesion favor gastric release and carrier defects rather than these paired alternatives.
Reasoning steps for option C
Why might impaired haptocorrin digestion seem plausible in Patient A?
Pancreatic enzymes normally digest haptocorrin so B12 can bind intrinsic factor.
What stated finding makes impaired haptocorrin digestion a poor explanation for Patient B?
Patient B has autoimmune corpus atrophy, which points to a gastric carrier defect, and pancreatic function is normal.
What role does pancreatic digestion play in B12 absorption?
It releases B12 from haptocorrin, allowing B12 to bind intrinsic factor.
D. A: ileal receptor uptake; B: haptocorrin digestion (Why this does not fit)
Downstream failure can affect free and food-derived vitamin. Normal free-dose uptake in A contradicts a major ileal defect, and pancreatic function is preserved in B.
Reasoning steps for option D
Why might ileal receptor failure seem plausible as a cause of poor B12 absorption?
Ileal receptors take up the intrinsic-factor-B12 complex.
What finding argues against ileal receptor failure in Patient A?
Normal absorption of free B12 shows that downstream uptake is functioning.
What does failure to absorb both food-bound and free B12 suggest when gastric atrophy is present?
A defect in intrinsic-factor availability can impair uptake of both preparations.
Takeaway: Free vitamin bypasses food release; it does not automatically bypass intrinsic-factor dependence at physiological doses.
A. Reduced duodenal IF-B12 formation; preserved receptor-mediated uptake (Why this does not fit)
Carrier formation and uptake are distinct functions. The preserved secretions support formation, while ileal resection impairs uptake, the reverse of this option.
Reasoning steps for option A
Can impaired intrinsic-factor production reduce formation of IF-B12?
Yes. Inadequate intrinsic factor can impair formation of the complex.
What do the normal gastric secretions and protease processing indicate here?
They support normal duodenal IF-B12 formation; the resection instead reduces ileal uptake.
What general distinction helps localize a B12 absorption defect?
Assess complex formation separately from uptake.
B. Preserved duodenal IF-B12 formation; reduced receptor-mediated uptake (Best answer)
Gastric carrier and pancreatic processing permit complex formation. Resection removes the downstream uptake surface, not the intact preparation steps.
Reasoning steps for option B
How do normal intrinsic factor and gastric acid affect B12 preparation?
They support formation of the IF-B12 complex.
What does terminal ileal resection remove from the absorption process?
It removes the site for receptor-mediated uptake.
Why can normal B12 preparation coexist with poor absorption?
Upstream complex formation cannot replace a missing downstream uptake site.
C. Reduced duodenal IF-B12 formation; reduced receptor-mediated uptake (Why this does not fit)
Both gastric and ileal disorders can cause B12 deficiency. This patient lacks the uptake surface but has no demonstrated failure of carrier formation.
Reasoning steps for option C
Can gastric failure and ileal loss each cause B12 deficiency?
Yes. They impair different stages of B12 absorption.
Why is reduced duodenal IF-B12 formation not expected in this patient?
Gastric acid and intrinsic factor are normal, and haptocorrin is processed normally.
How should a suspected multistage absorption defect be evaluated?
Identify which individual stage is impaired rather than assuming all stages fail.
D. Preserved duodenal IF-B12 formation; preserved receptor-mediated uptake (Why this does not fit)
Normal acid and intrinsic factor support vitamin preparation. They do not replace the missing terminal ileal receptors.
Reasoning steps for option D
Do normal gastric acid and intrinsic factor support B12 complex formation?
Yes. They permit normal upstream preparation.
Why is receptor-mediated uptake not preserved after terminal ileal resection?
The resection removes the intestinal site needed for that uptake.
Can intact upstream preparation compensate for loss of an absorption site?
No. Normal preparation does not restore a missing uptake surface.
Takeaway: Normal upstream B12 preparation does not ensure absorption when the terminal ileal uptake surface is lost.
A. Higher pancreatic protease activity; greater persistence of pepsin activity (Why this does not fit)
Acidity supports pepsin activity. It does not provide the environment normally needed for effective pancreatic proteolysis.
Reasoning steps for option A
Why might pH 2.5 seem to support greater pepsin activity?
Pepsin is adapted to acidic conditions.
Why does that acidic advantage not imply higher pancreatic protease activity?
Pancreatic proteases function poorly at such a low pH.
What general principle distinguishes pepsin from pancreatic proteases here?
Enzyme activity depends on the pH suited to each enzyme.
B. Lower pancreatic protease activity; less persistence of pepsin activity (Why this does not fit)
Poor neutralization can impair pancreatic digestion. The same low pH favors rather than suppresses the persistence of acid-dependent pepsin activity.
Reasoning steps for option B
Why is lower pancreatic protease activity plausible at pH 2.5?
The acidic lumen impairs pancreatic protease function.
Why is less pepsin activity not expected in the acidic lumen?
Acidity supports pepsin activity rather than suppressing it.
What does low duodenal pH imply for acid-dependent pepsin?
It favors pepsin persistence relative to neutral pH.
C. Unchanged pancreatic protease activity; less persistence of pepsin activity (Why this does not fit)
The delivered pancreatic precursor amount is unchanged. Amount alone does not assure normal activity, and failure to neutralize does not preferentially suppress pepsin.
Why does unchanged precursor amount not ensure unchanged protease activity?
Low pH impairs enzyme function despite precursor availability.
What general principle separates enzyme amount from enzyme activity?
Substrate and enzyme availability do not override unsuitable pH.
D. Lower pancreatic protease activity; greater persistence of pepsin activity (Best answer)
At pH 2.5, delivered pancreatic proteases function poorly despite available precursors and enteropeptidase. Acid-dependent pepsin remains more active than in otherwise equivalent fluid neutralized to pH 7.
Reasoning steps for option D
Why is pancreatic protease activity lower at pH 2.5 than at pH 7?
The acidic lumen is unfavorable for pancreatic protease function.
Why does pepsin persist more at pH 2.5 than at pH 7?
Its acid-dependent activity is favored by the low pH.
What paired activity pattern follows from these pH effects?
Pancreatic protease activity falls as pepsin persistence rises; enzyme activity depends on pH.
Takeaway: At pH 2.5 pancreatic protease function declines while acid-dependent pepsin persists relative to pH 7.
A. More B12 remains haptocorrin-bound, leaving less available for intrinsic factor (Best answer)
Pancreatic proteases digest haptocorrin in the duodenum. Loss of those enzymes impairs the handoff despite available intrinsic factor and ductal alkalinization.
Reasoning steps for option A
Which pancreatic activity normally releases B12 from haptocorrin in the duodenum?
Proteolysis by pancreatic enzymes.
Why does reduced pancreatic protease delivery leave more B12 haptocorrin-bound?
Less haptocorrin is digested, so less B12 is released.
When can B12 bind intrinsic factor after leaving haptocorrin?
After haptocorrin is digested; carrier transfer requires proteolysis.
B. More B12 binds intrinsic factor because haptocorrin processing accelerates (Why this does not fit)
Intrinsic factor becomes useful after vitamin is released from haptocorrin. Reduced pancreatic protease delivery delays rather than accelerates that release.
Reasoning steps for option B
What role does intrinsic factor have in intestinal B12 absorption?
It binds released B12 for subsequent absorption.
Which stated finding argues against lack of intrinsic factor as the cause?
Intrinsic factor is measurable in gastric juice.
What must occur before intrinsic factor can bind B12?
B12 must be released from haptocorrin first.
C. Less B12 binds intrinsic factor because parietal-cell synthesis must stop (Why this does not fit)
The intrinsic-factor pathway depends on a gastric product. Intrinsic factor is measured as present; the documented defect is pancreatic carrier processing.
Reasoning steps for option C
Which gastric cell type produces intrinsic factor?
Parietal cells.
What finding shows intrinsic factor is present in this patient?
It is measurable in gastric juice.
Which organ supplies the proteases needed to digest haptocorrin?
The pancreas; carrier digestion depends on pancreatic proteases.
D. Normal carrier transfer occurs because bicarbonate alone digests haptocorrin (Why this does not fit)
Bicarbonate improves the environment for intestinal digestion. It does not replace the proteases required to digest the protein carrier.
Reasoning steps for option D
What does pancreatic bicarbonate secretion do to duodenal pH?
It raises the pH.
Why does normal duodenal alkalinization not ensure normal haptocorrin digestion?
A suitable pH does not replace the missing proteases.
What is required to digest haptocorrin?
Proteolytic enzymes; bicarbonate alone cannot digest a protein.
Takeaway: A normal secretin-driven duct response does not establish normal pancreatic protease delivery.
A. Preserved histamine-driven cAMP; reduced acetylcholine-driven calcium (Why this does not fit)
M3 blockade could reduce acetylcholine calcium, but only H2 receptors are antagonized here. Histamine-driven cAMP should decline while muscarinic calcium remains available.
M3 blockade would reduce acetylcholine-driven calcium.
Which receptor is actually antagonized in the stem?
The H2 receptor, not the M3 receptor.
What does selective H2 antagonism directly spare?
M3-mediated calcium signaling.
B. Reduced histamine-driven cAMP; reduced acetylcholine-driven calcium (Why this does not fit)
H2 antagonism reduces histamine cAMP. It does not also block acetylcholine-M3 calcium signaling in these otherwise intact cells.
Reasoning steps for option B
Which response is correctly predicted by H2 antagonism alone?
Reduced histamine-driven cAMP.
Why is reduced acetylcholine-driven calcium not expected here?
Acetylcholine-M3 signaling remains intact.
What happens to a parallel pathway under selective receptor blockade?
It remains available if its receptor is not blocked.
C. Reduced histamine-driven cAMP; preserved acetylcholine-driven calcium (Best answer)
H2 receptors signal through cAMP, so selective antagonism reduces histamine-driven cAMP. Acetylcholine uses M3 calcium signaling, which remains available.
Reasoning steps for option C
Which second messenger does the H2 receptor engage in parietal cells?
cAMP.
Which second messenger does acetylcholine-M3 signaling engage?
Calcium.
What signaling pattern follows selective H2 blockade?
Histamine cAMP falls while M3 calcium remains intact.
D. Preserved histamine-driven cAMP; preserved acetylcholine-driven calcium (Why this does not fit)
Preserved M3 calcium is expected, but histamine cAMP cannot remain unchanged under effective selective H2 blockade.
A. X blocks M3 signaling; Y abolishes histamine-induced cAMP (Why this does not fit)
Selective loss of acetylcholine calcium identifies M3 pathway inhibition by X. Pump inhibition by Y is downstream and does not abolish histamine-induced cAMP.
Reasoning steps for option A
What does the loss of acetylcholine-induced calcium signaling identify about X?
X inhibits M3 signaling.
Why would pump inhibition by Y not abolish histamine-induced cAMP?
The proton pump acts downstream of H2 receptor signaling and cAMP production.
Where does the proton pump act relative to receptor-generated second messengers?
It acts downstream, so blocking it can reduce acid secretion without removing upstream signaling.
B. X blocks M3 signaling; Y preserves histamine-induced cAMP while reducing acid output (Best answer)
X disrupts M3 calcium signaling while histamine H2-cAMP remains intact. Y blocks the final proton transporter, reducing acid without eliminating upstream histamine cAMP.
Reasoning steps for option B
Which receptor pathway does X disrupt when acetylcholine-induced calcium signaling disappears?
The M3 pathway.
What happens to histamine-induced cAMP when Y blocks the apical proton pump?
It remains intact because pump inhibition is downstream of cAMP production.
How can Y reduce acid output while histamine-induced cAMP persists?
It blocks the final proton transporter downstream of H2-cAMP signaling.
C. X blocks H2 signaling; Y abolishes histamine-induced cAMP (Why this does not fit)
H2 blockade would reduce histamine-induced cAMP, which X preserves. Y acts at the proton pump rather than erasing receptor-generated cAMP.
Reasoning steps for option C
Which acid-secretion step does Y inhibit?
The apical H+/K+-ATPase, the final proton transporter.
Why is X not an H2 inhibitor in these cells?
Histamine-induced cAMP is preserved, while acetylcholine-induced calcium signaling is lost.
What does preserved histamine-induced cAMP indicate about H2 signaling?
H2 receptor signaling remains functional when its cAMP response is preserved.
D. X blocks H2 signaling; Y preserves histamine-induced cAMP while reducing acid output (Why this does not fit)
Y may reduce acid while preserving cAMP, but X cannot be H2 blockade when histamine cAMP survives and acetylcholine calcium disappears.
Reasoning steps for option D
What effect can blocking the apical H+/K+-ATPase have on acid output?
It can reduce acid output.
Why can X not be an H2 inhibitor in this experiment?
Histamine-induced cAMP persists, while acetylcholine-induced calcium signaling is abolished.
Which signaling response distinguishes M3 inhibition from H2 inhibition here?
Loss of acetylcholine-induced calcium with preserved histamine-induced cAMP indicates M3 inhibition.
Takeaway: M3 signaling and histamine cAMP are distinct from the final proton pump that carries acid output.
A. Inhibition of G cells, ECL cells and parietal-cell secretion (Best answer)
Somatostatin restrains the gastric secretory network at multiple levels. Its known actions encompass the measured declines in gastrin, local histamine and acid.
Reasoning steps for option A
How can somatostatin lower gastrin after a meal?
It inhibits gastric G cells.
Which measured change supports G-cell inhibition?
Gastrin declines after infusion.
What general effect does somatostatin have on G cells?
It suppresses G-cell secretion.
B. Stimulation of G cells with inhibition of ECL and parietal cells (Why this does not fit)
Reduced ECL and parietal activity could decrease acid. G-cell stimulation conflicts with both the measured gastrin decline and the known inhibitory action of somatostatin.
Reasoning steps for option B
How could ECL and parietal-cell inhibition reduce acid output?
It reduces histamine signaling and acid secretion.
Which measured change conflicts with G-cell stimulation?
Gastrin declines rather than rises.
What does somatostatin generally do to gastric secretory cells?
It inhibits their secretion.
C. Inhibition of G cells with stimulation of ECL and parietal cells (Why this does not fit)
G-cell inhibition could reduce endogenous gastrin. Direct ECL and parietal stimulation is not the known effect of the infused inhibitor.
Reasoning steps for option C
How could G-cell inhibition reduce gastrin?
It suppresses gastrin release.
Which measured declines conflict with ECL and parietal-cell stimulation?
Histamine signaling and acid output both decline.
What is a general effect of somatostatin on ECL and parietal cells?
It inhibits their secretory activity.
D. Stimulation of G cells, ECL cells and parietal-cell secretion (Why this does not fit)
Coordinated stimulation explains the original meal response. It predicts the opposite direction from the postinfusion measurements.
Reasoning steps for option D
How can somatostatin lower gastrin?
It inhibits G cells.
Which measured response conflicts with stimulation of all three cell types?
Gastrin, histamine signaling, and acid output all decline.
What is the general gastric action of somatostatin?
It restrains secretion at multiple levels.
Takeaway: Somatostatin can restrain gastrin, ECL histamine, and parietal secretion.
C. Less somatostatin; less gastrin-driven histamine release (Why this does not fit)
Reduced ECL drive would help restrain acid. The proposed fall in somatostatin would release G-cell restraint rather than explain the expected feedback.
Reasoning steps for option C
How does reduced gastrin affect ECL-cell histamine release?
It reduces gastrin-driven histamine release.
When lower pH activates intact D cells, should somatostatin rise or fall?
It should rise.
What is the reusable consequence of less gastrin reaching ECL cells?
ECL histamine stimulation falls.
D. More somatostatin; less gastrin-driven histamine release (Best answer)
Low antral pH increases D-cell restraint of G cells. Reduced gastrin then reduces ECL stimulation, providing the downstream histamine prediction.
Reasoning steps for option D
How does low antral pH affect D-cell somatostatin release?
It increases release.
How does increased somatostatin affect G-cell gastrin release?
It inhibits gastrin release.
How does reduced gastrin affect ECL-cell histamine release?
It reduces histamine release; acid feedback proceeds from D-cell somatostatin to G-cell inhibition to reduced ECL stimulation.
Takeaway: Trace acid feedback through D cells to G cells before predicting the ECL response.
A. Repeat fasting gastrin after vitamin replacement (Why this does not fit)
Hypergastrinemia can accompany loss of acid secretion. A hormone value alone cannot document the distribution of atrophy or exclude gastric neoplasia.
Reasoning steps for option A
Why can fasting gastrin rise in autoimmune atrophic gastritis?
Loss of acid secretion can cause hypergastrinemia.
Why does a gastrin level not assess gastric neoplasia risk directly?
It does not show the distribution of gastric atrophy or identify a lesion.
What assessment is needed to map suspected gastric atrophy?
Upper endoscopy with topographical gastric biopsies.
B. Terminal ileal biopsies for tissue assessment (Why this does not fit)
The terminal ileum is the uptake site for intrinsic-factor-bound B12. The antibody-supported carrier disorder points to gastric pathology; ileal sampling alone misses that tissue and its neoplastic risk.
Reasoning steps for option B
Where is intrinsic-factor-bound B12 absorbed?
In the terminal ileum.
Why would terminal ileal biopsies miss the main concern here?
The antibody-supported disorder points to gastric pathology and associated neoplastic risk.
Which tissue should be sampled to assess suspected autoimmune gastric atrophy?
The gastric mucosa, using topographical biopsies.
C. Upper endoscopy with topographical gastric biopsies (Best answer)
Pernicious anemia can be a late manifestation of autoimmune corpus-predominant atrophy. The AGA review advises assessing the gastric distribution and excluding prevalent neoplasia when no recent examination exists.
Reasoning steps for option C
How can autoimmune corpus atrophy lead to pernicious anemia?
Loss of intrinsic-factor-producing parietal cells impairs B12 absorption.
Why is endoscopy appropriate when pernicious anemia is newly diagnosed without a recent examination?
It assesses gastric atrophy and can identify prevalent neoplasia.
What endoscopic sampling best assesses the distribution of gastric atrophy?
Topographical biopsies from the stomach.
D. Secretin-stimulated pancreatic function testing (Why this does not fit)
Secretin testing assesses pancreatic duct function, not the distribution of autoimmune gastric atrophy or associated gastric neoplasia. It does not substitute for gastric biopsies.
Reasoning steps for option D
What function does secretin-stimulated testing assess?
Pancreatic duct function.
Why does pancreatic function testing not assess this patient's gastric risk?
It does not show gastric atrophy or detect gastric neoplasia.
Which evaluation assesses autoimmune gastric atrophy and associated neoplasia?
Upper endoscopy with topographical gastric biopsies.
Takeaway: New pernicious anemia without recent endoscopy warrants gastric mucosal mapping and neoplasia assessment.
Parietal carbonic anhydrase supplies bicarbonate generated alongside hydrogen for acid secretion, so its inhibition reduces the gastric venous bicarbonate rise. Separate duct bicarbonate loss impairs duodenal neutralization and lowers activity of delivered pancreatic proteases.
Reasoning steps for option A
How does parietal-cell carbonic anhydrase inhibition affect bicarbonate export into gastric venous blood?
It reduces bicarbonate generated alongside secreted hydrogen ions.
Why does inhibiting pancreatic duct bicarbonate export lower the activity of delivered proteases?
Poorer neutralization leaves the duodenal environment less suitable for protease activity.
What does the gastric alkaline tide reflect?
Venous bicarbonate export associated with parietal acid secretion.
B. A: smaller venous bicarbonate rise; B: higher protease activity (Why this does not fit)
Parietal carbonic anhydrase inhibition can diminish the venous alkaline tide. In B, normal precursor delivery does not overcome poor neutralization, so protease activity falls rather than rises.
Reasoning steps for option B
Why is a smaller gastric venous bicarbonate rise expected when parietal carbonic anhydrase is inhibited?
The enzyme supports bicarbonate generation during acid secretion.
Why does normal acinar precursor delivery not preserve protease activity when duct bicarbonate export is inhibited?
The delivered enzymes face inadequate neutralization.
What condition supports pancreatic protease activity in the duodenum?
C. A: larger venous bicarbonate rise; B: lower protease activity (Why this does not fit)
Reduced pancreatic duct bicarbonate leaves incoming gastric acid less neutralized and lowers pancreatic protease function. In A, inhibition of parietal carbonic anhydrase decreases, not increases, acid-linked bicarbonate production and venous export.
Reasoning steps for option C
Why does inhibiting pancreatic duct bicarbonate export reduce protease activity?
Less bicarbonate means less neutralization of gastric acid.
Why does parietal carbonic anhydrase inhibition not enlarge the gastric venous bicarbonate rise?
It reduces, rather than increases, acid-linked bicarbonate generation.
Which source supports bicarbonate delivery for duodenal neutralization?
Pancreatic ducts export bicarbonate into the duodenum.
D. A: larger venous bicarbonate rise; B: higher protease activity (Why this does not fit)
Normal acinar precursor delivery makes enzyme availability plausible. Nevertheless, ductal neutralization is impaired in B, and parietal bicarbonate generation is reduced in A; neither proposed increase follows.
Reasoning steps for option D
Why can normal acinar precursor delivery support the availability of pancreatic proteases?
A. Add additional pepsinogen without changing pH (Why this does not fit)
More precursor can help when secretion is deficient. The measured precursor amount is normal and the acid-dependent activation condition remains absent.
Reasoning steps for option A
When could adding pepsinogen increase gastric proteolysis?
It can help if pepsinogen secretion is deficient.
Why would more pepsinogen not address this sample's defect?
Its pepsinogen amount is already normal, while the acidic activation condition is missing.
What should be checked before supplementing a digestive precursor?
Determine whether the precursor is deficient or its activation condition is impaired.
B. Acidify the aliquot to pH 2 (Best answer)
Low pH initiates pepsinogen conversion and supports pepsin activity. The precursor is already present; restoring its luminal environment addresses the demonstrated activation defect.
Reasoning steps for option B
What does low pH initiate for pepsinogen?
It initiates conversion of pepsinogen into active pepsin.
Why does acidification address the measured defect?
The precursor is present, but the acidic environment required for activation is absent.
What condition supports gastric pepsin activity?
An acidic gastric environment supports pepsinogen activation and pepsin activity.
C. Add bicarbonate to increase the pH (Why this does not fit)
Bicarbonate supports pancreatic digestion downstream. Further alkalinization does not restore the acidic environment required for gastric pepsin activation.
Reasoning steps for option C
Where can bicarbonate support digestive enzyme activity?
It supports pancreatic digestion downstream in the intestine.
Why would added bicarbonate not restore pepsin activation?
Raising pH does not provide the acidic condition required for pepsinogen activation.
How does pH affect gastric and pancreatic digestion differently?
Gastric pepsin requires an acidic environment, while bicarbonate supports downstream pancreatic digestion.
D. Add intrinsic factor without changing pH (Why this does not fit)
Intrinsic factor is another gastric product relevant to nutrient absorption. It binds B12 rather than converting the existing protease precursor to active pepsin.
Reasoning steps for option D
What nutrient does intrinsic factor help the body absorb?
Intrinsic factor binds vitamin B12 and supports its absorption.
Why would intrinsic factor not activate pepsinogen?
It binds vitamin B12 and does not supply the acidic condition needed for pepsinogen conversion.
What is intrinsic factor's role in gastric physiology?
It binds vitamin B12 for absorption rather than activating a protease precursor.
Takeaway: Acidification to pH 2 restores the missing pepsinogen activation environment when precursor is present.
A. Pancreatic trypsinogen synthesis; active pepsin (Why this does not fit)
A missing pancreatic precursor could limit active trypsin, but normal trypsinogen delivery excludes deficient synthesis as the demonstrated bottleneck. Pepsin does not initiate the intestinal trypsinogen activation cascade.
Reasoning steps for option A
Why might deficient trypsinogen synthesis seem plausible as a cause of low active trypsin?
Too little precursor could limit production of active trypsin.
What finding argues against deficient trypsinogen synthesis in this sample?
Normal amounts of trypsinogen were delivered.
What does normal precursor delivery establish when active enzyme remains scarce?
It directs attention to precursor activation rather than synthesis.
B. Pancreatic trypsinogen synthesis; active trypsin (Why this does not fit)
Active trypsin could bypass the initiating conversion. Normal precursor delivery and rescue by healthy brush border instead localize the original failure to the membrane activation step, not pancreatic synthesis.
Reasoning steps for option B
Why could adding active trypsin seem to reproduce the brush-border rescue?
Active trypsin can activate pancreatic protease precursors.
Which observation localizes the original failure to the brush-border activation step?
How can an active enzyme bypass a missing precursor-activation step?
Supplying the active enzyme bypasses its required initiating conversion.
C. Brush-border enteropeptidase-mediated trypsinogen activation; active pepsin (Why this does not fit)
Healthy brush-border rescue localizes the defect to enteropeptidase-dependent activation. Gastric pepsin does not replace active trypsin for downstream pancreatic protease precursor activation at intestinal pH.
Reasoning steps for option C
Why does brush-border rescue support a defect in enteropeptidase-dependent activation?
Enteropeptidase on the brush border initiates trypsinogen activation.
Why would active pepsin fail to reproduce this intestinal rescue?
Pepsin does not substitute for trypsin in activating pancreatic protease precursors at intestinal pH.
Which enzyme normally initiates pancreatic protease precursor activation in the intestine?
D. Brush-border enteropeptidase-mediated trypsinogen activation; active trypsin (Best answer)
Normal trypsinogen delivery with rescue by healthy brush border localizes the defect to enteropeptidase-dependent activation. Soluble active trypsin bypasses that initiating step and activates downstream pancreatic protease precursors.
Reasoning steps for option D
How does normal trypsinogen delivery narrow the source of low active trypsin?
It indicates that precursor supply is intact.
What does rescue by healthy brush border identify as the defective process?
Enteropeptidase-mediated trypsinogen activation.
How does soluble active trypsin reproduce the rescue without brush border?
It bypasses enteropeptidase and activates downstream pancreatic protease precursors.
Takeaway: Brush-border rescue localizes failed trypsinogen activation; soluble active trypsin bypasses the membrane initiating step.
A. Pepsin activity increases; gastric emptying slows (Why this does not fit)
Early duodenal acid feedback slows gastric emptying. Separately, neutralization to pH 7 reduces rather than increases pepsin activity in the sampled aliquot.
Reasoning steps for option A
What does early duodenal acid feedback do to gastric emptying?
It slows gastric emptying.
What happens to pepsin activity when the aliquot is raised to pH 7?
It decreases.
How does duodenal acid affect gastric delivery to the intestine?
It initially slows gastric emptying.
B. Pepsin activity decreases; gastric emptying accelerates (Why this does not fit)
Neutralization reduces acid-dependent pepsin activity. The separately specified early feedback response to duodenal acid slows emptying relative to before exposure.
Reasoning steps for option B
How does neutralization affect pepsin activity?
It reduces pepsin activity.
Does early feedback to duodenal acid accelerate or slow gastric emptying?
It slows gastric emptying.
What is the early gastric response to acid entering the duodenum?
Gastric emptying slows.
C. Pepsin activity decreases; gastric emptying slows (Best answer)
Raising the aliquot from pH 2.5 to 7 reduces pepsin activity. Separately, initial duodenal acid exposure triggers feedback that slows gastric emptying relative to baseline; this need not persist after neutralization.
Reasoning steps for option C
Why does pepsin activity fall when the aliquot reaches pH 7?
Neutral pH reduces pepsin activity.
How does early duodenal acid exposure change gastric emptying from baseline?
It slows gastric emptying.
What happens to pepsin activity as acidic chyme is neutralized?
It decreases.
D. Pepsin activity increases; gastric emptying accelerates (Why this does not fit)
Pepsin is supported by acidic fluid, not neutral pH. Initial acid exposure also restrains, rather than accelerates, gastric emptying.
Reasoning steps for option D
What pH conditions support pepsin activity?
Acidic conditions support pepsin activity.
What happens to pepsin when the aliquot is neutralized to pH 7?
Its activity decreases.
How does early duodenal acid feedback affect gastric emptying?
It slows gastric emptying.
Takeaway: Neutralization reduces pepsin activity; early duodenal acid feedback slows emptying relative to before exposure.
A. A: reduced acid drive; B: preserved secretory capacity (Why this does not fit)
Antral D-cell loss reduces inhibition of G cells, so A tends toward greater acid drive. Corpus atrophy in B removes acid-secreting capacity despite high gastrin.
Reasoning steps for option A
Why might high gastrin increase acid secretion in stomach regions with intact parietal cells?
Gastrin stimulates parietal cells when they remain functional.
What does preserved fundic gland tissue imply about Patient A's acid-secretory capacity?
The capacity is preserved, not reduced.
How does loss of antral D-cell inhibition generally affect acid drive?
Reduced antral somatostatin permits increased G-cell stimulation of preserved fundic glands in A. Corpus cell loss in B limits acid-secretory capacity despite high gastrin.
Reasoning steps for option B
How does reduced antral somatostatin affect G-cell stimulation in Patient A?
It removes inhibition of G cells, increasing gastrin stimulation.
Why can Patient A respond to increased gastrin with greater acid secretion?
Its fundic glands remain preserved and able to secrete acid.
How should antral D-cell loss and corpus atrophy be distinguished physiologically?
Antral D-cell loss increases acid drive, while corpus atrophy reduces acid capacity.
C. A: greater acid drive; B: preserved secretory capacity (Why this does not fit)
A can have increased drive after antral D-cell failure. B lacks intact parietal capacity despite antral gastrin signaling.
Reasoning steps for option C
Why does reduced antral somatostatin support increased acid drive in Patient A?
Less somatostatin inhibition permits greater G-cell stimulation.
Why does Patient B's intact antrum not preserve its acid-secretory capacity?
Its corpus-predominant atrophy removes acid-secreting cells.
What determines whether high gastrin can produce acid secretion?
Functional parietal cells are required for gastrin-driven acid secretion.
D. A: reduced acid drive; B: reduced secretory capacity (Why this does not fit)
Corpus atrophy explains B's limited acid capacity. A has preserved fundic glands and less D-cell restraint, favoring greater rather than reduced acid drive.
Reasoning steps for option D
Why is reduced acid capacity plausible in Patient B?
Corpus atrophy reduces the population of acid-secreting cells.
What does Patient A's preserved fundic tissue imply despite antral inflammation?
Its acid-secretory capacity remains available.
How does antral D-cell loss affect acid drive when fundic glands are intact?
It reduces somatostatin restraint and tends to increase acid drive.
Takeaway: Antral D-cell loss increases acid drive with preserved fundic cells, whereas corpus atrophy limits acid capacity.
How does reduced gastric acidity affect gastrin when antral G cells are spared?
It weakens acid feedback, increasing gastrin secretion.
C. Preserved intrinsic factor; increased gastrin (Why this does not fit)
High pH with antral sparing supports increased gastrin. Corpus atrophy does not preserve the parietal-cell carrier output.
Reasoning steps for option C
Why is increased gastrin plausible with high gastric pH?
Reduced acidity weakens feedback restraint on gastrin.
Does corpus atrophy preserve parietal-cell intrinsic factor output?
No. Corpus atrophy reduces intrinsic factor.
What happens to intrinsic factor when corpus parietal cells are lost?
Intrinsic factor falls, impairing B12 absorption.
D. Reduced intrinsic factor; increased gastrin (Best answer)
Corpus parietal-cell loss reduces intrinsic factor, consistent with low B12 even without macrocytosis. Higher pH weakens restraint of the spared antral G cells, increasing gastrin.
Reasoning steps for option D
How does corpus atrophy account for low vitamin B12?
Parietal-cell loss reduces intrinsic factor and B12 absorption.
Why does high gastric pH favor increased gastrin?
It weakens acid-mediated feedback restraint.
What paired secretory pattern follows corpus atrophy with antral sparing?
Intrinsic factor decreases while gastrin increases.
Takeaway: Corpus atrophy lowers intrinsic factor and high pH raises gastrin despite a normal mean corpuscular volume.
A. A: intrinsic factor reduced; B: intrinsic factor preserved (Why this does not fit)
A retains strong acidity without a separate carrier disorder, favoring preserved intrinsic factor. B has corpus cell loss and low B12, favoring reduced carrier secretion.
Reasoning steps for option A
Why might corpus atrophy reduce intrinsic-factor secretion in Patient B?
Loss of corpus parietal cells reduces intrinsic-factor-producing capacity.
What finding in Patient A argues against reduced intrinsic factor?
Gastric pH 1.2 supports functioning acid-secreting parietal tissue, and no separate intrinsic-factor disorder is identified.
What does low B12 alongside corpus atrophy suggest about intrinsic-factor output?
It supports reduced output from lost parietal cells.
B. A: intrinsic factor reduced; B: intrinsic factor reduced (Why this does not fit)
Corpus atrophy supports reduced carrier output in B. High gastrin with preserved acidity in A does not establish loss of intrinsic-factor production.
Reasoning steps for option B
Why is reduced intrinsic factor plausible in Patient B?
Corpus atrophy can reduce parietal-cell secretion.
Does high gastrin establish intrinsic-factor loss in Patient A?
No; Patient A has strongly acidic gastric contents, and high gastrin alone does not establish carrier loss.
What determines intrinsic-factor capacity more directly than gastrin concentration?
A retains acidic parietal secretion without a separate carrier disorder, supporting preserved intrinsic factor rather than proving it. Corpus atrophy in B reduces parietal carrier capacity despite high gastrin.
Reasoning steps for option C
Why is preserved intrinsic factor consistent with Patient A?
Strong acidity supports functioning parietal cells, and no separate intrinsic-factor disorder is identified.
What finding argues against preserved intrinsic factor in Patient B?
Corpus atrophy with low B12 supports reduced parietal-cell carrier output.
How should intrinsic-factor output be assessed when gastrin is high?
Assess the state of parietal tissue, since gastrin alone does not establish carrier output.
D. A: intrinsic factor preserved; B: intrinsic factor preserved (Why this does not fit)
A can retain carrier output with functioning parietal cells. B cannot restore lost intrinsic-factor-producing cells simply by raising gastrin.
Reasoning steps for option D
Why can functioning parietal tissue in Patient A support intrinsic-factor secretion?
Parietal cells secrete intrinsic factor as well as acid.
Why does high gastrin not restore intrinsic-factor output in Patient B?
Gastrin cannot replace parietal cells lost through corpus atrophy.
What effect can corpus atrophy have on intrinsic-factor secretion?
It can reduce secretion by depleting parietal cells.
Takeaway: High gastrin alone does not determine carrier output; compare preserved acid-producing tissue with corpus cell loss.