GERD, Erosive Esophagitis, and Peptic Ulcer Disease
Separate reflux from ulcer disease, interpret acid and mucosal defense, and choose safe testing, eradication, bleeding care and perforation management.
Burning after dinner is not a diagnosis, and a stronger acid suppressant is not always the safest next treatment. First distinguish reflux into the esophagus from an ulcer in the stomach or duodenum. Then ask whether the patient needs routine treatment, investigation for an important underlying disease, or immediate resuscitation.
Does the symptom identify the injured tissue?
A patient describes sour fluid reaching the mouth when lying down. Another reports epigastric pain while taking naproxen. Both may improve with acid suppression, but that response does not establish the same disease. Gastroesophageal reflux disease (GERD) means reflux causing troublesome symptoms or complications. Erosive esophagitis is visible esophageal mucosal injury; it is neither required for GERD nor predicted reliably by symptom intensity. Peptic ulcer disease (PUD) is a deeper mucosal defect, extending through the muscularis mucosae, usually in the stomach or proximal duodenum. Helicobacter pylori infection is a potential cause of ulcer disease, not another name for an ulcer. Infection can exist without an ulcer, and an NSAID ulcer can occur without infection. [1][10]
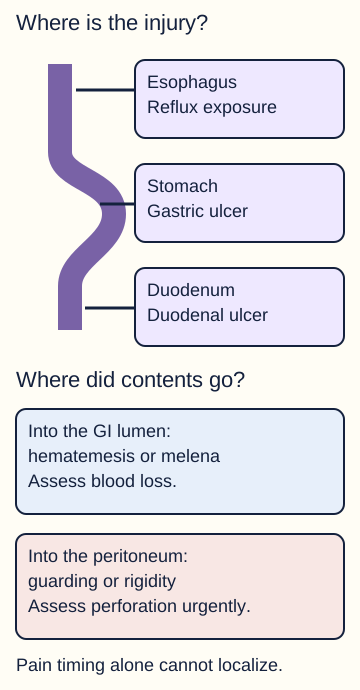
Locate before labeling. On the compartment diagram, assign regurgitation to the esophagus, a gastric crater to the stomach and a duodenal crater to the proximal small bowel. Next assign melena to loss of blood into the gastrointestinal lumen and involuntary guarding to irritation of the peritoneum. The last two observations identify complications, not simply a different pain location. Hematemesis and coffee-ground emesis also suggest upper gastrointestinal bleeding; a patient can lose considerable blood without severe abdominal pain. [5][6]
Assign the symptom to a site, then identify whether blood or luminal contents have entered another compartment. [1][5][6][10]
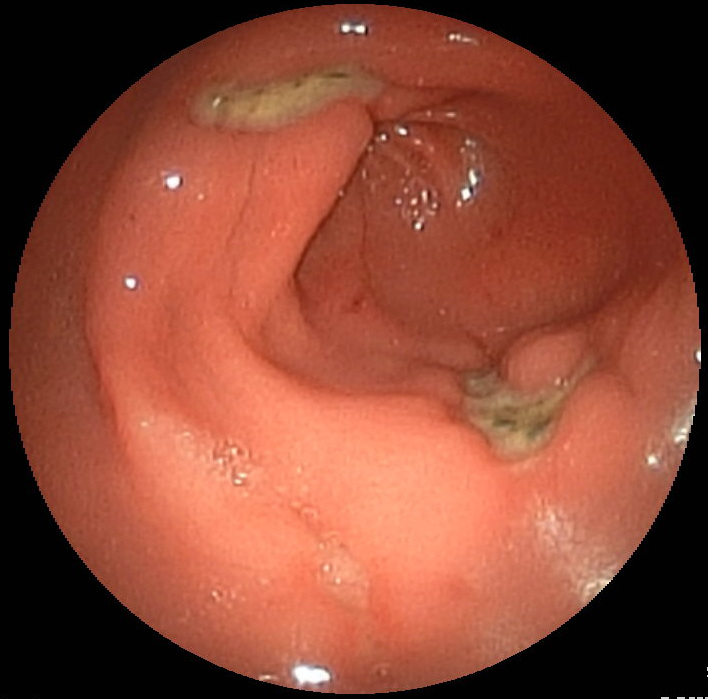
Predict whether a photograph of a gastric ulcer proves NSAID injury, H. pylori infection or cancer. It proves none of those causes. The antral endoscopy image shows a mucosal crater; medication history, testing and tissue assessment answer different questions. Gastric ulcers need assessment for malignancy, generally including biopsy and follow-up appropriate to their appearance, histology and healing. Duodenal ulcers are very rarely malignant and do not carry the same routine malignancy-biopsy requirement. [10]
Identify the crater, then separate recognition from etiology. Appearance alone does not establish NSAID exposure, H. pylori infection or benign histology. Tissue and infection assessment answer those questions. Image: Med_Chaos; original source; Public domain, released by the author. [10].
For a new patient whose pain improves with food, do not use that pattern alone to declare a duodenal ulcer. Traditional gastric-versus-duodenal meal patterns overlap. Likewise, severe heartburn does not prove severe erosions, and a normal endoscopy does not exclude reflux. Carry forward the site, the evidence of injury and the suspected cause as three separate judgments. [1][10]
Who can start outpatient treatment, and who needs investigation?
A 34-year-old has heartburn and regurgitation after large evening meals, without dysphagia, bleeding, weight loss or persistent vomiting. Compare this with a 64-year-old whose solid-food swallowing is progressively worse and who has lost weight. Choose a first action for each before reading on: an empiric treatment trial, noninvasive infection testing or upper endoscopy.
For typical uncomplicated reflux, an eight-week trial of a once-daily proton pump inhibitor (PPI), taken 30 to 60 minutes before a meal, is reasonable. The second patient needs endoscopy rather than another empiric course. Dysphagia, odynophagia, gastrointestinal bleeding, iron-deficiency anemia, unexplained weight loss and persistent vomiting demand assessment for structural or otherwise important disease. A patient with possible ischemic chest pain needs an appropriate cardiac evaluation before symptoms are assigned to reflux. [1]
The route for dyspepsia is not identical to the route for classic reflux. In the ACG/CAG approach, patients aged 60 years or older with dyspepsia generally undergo endoscopy. Younger patients without concerning risk features usually receive a noninvasive H. pylori test and treatment if positive, followed by a PPI trial if negative or still symptomatic. A strong gastric cancer family history or childhood in a high-incidence region may justify earlier endoscopy. Alarm features in a patient under 60 with dyspepsia are assessed individually; the age threshold is not permission to ignore progressive dysphagia or overt bleeding. [2]
Now change only the first patient's history: correctly taken therapy fails and endoscopy is normal. Predict whether a normal examination rules out GERD. It does not. If GERD has never been objectively established, ambulatory reflux monitoring off PPI can establish or refute abnormal acid exposure. If GERD is already established and symptoms persist despite optimized twice-daily PPI, impedance-pH monitoring on treatment can assess persistent acid or nonacid reflux and symptom association. These are different diagnostic questions. Check adherence and administration first. If diagnostic endoscopy with esophageal biopsies has not been performed off PPI, it is ideally done after a two- to four-week hold when safe; acid suppression can heal erosions and obscure other diagnoses. Manometry alone does not diagnose GERD. [1]
Is the problem excess acid or insufficient protection?
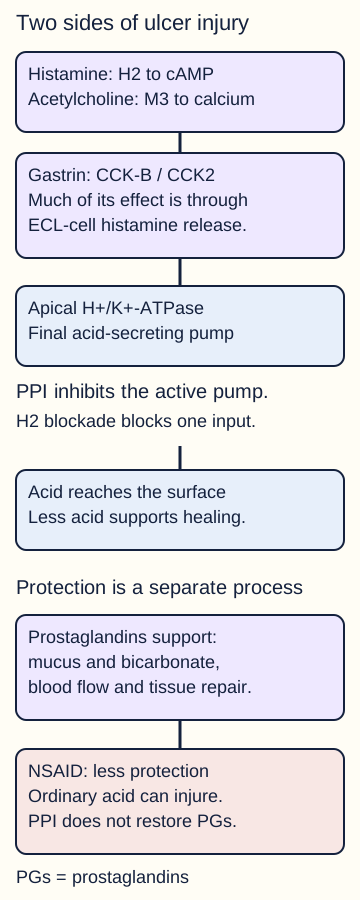
A patient develops an ulcer while taking an NSAID even though acid production is not unusually high. Predict which intervention addresses acid secretion and which addresses the loss of protection. The parietal-cell diagram separates those processes so that a normal acid output cannot falsely reassure you about ulcer risk.
Histamine acts at H2 receptors through cAMP. Acetylcholine acts at M3 receptors through intracellular calcium signaling. Gastrin acts through CCK-B, also called CCK2, receptors with calcium signaling; much of its acid-stimulating effect in humans is mediated through histamine release from enterochromaffin-like cells. These inputs converge on the apical H+/K+-ATPase. An H2 receptor antagonist blocks one stimulatory input. A PPI acts at the final proton pump after activation in an acidic environment, forming covalent bonds with the pump. Its effect therefore outlasts its brief plasma exposure. Taking most PPIs before a meal aligns drug availability with pump activation. [7][8]
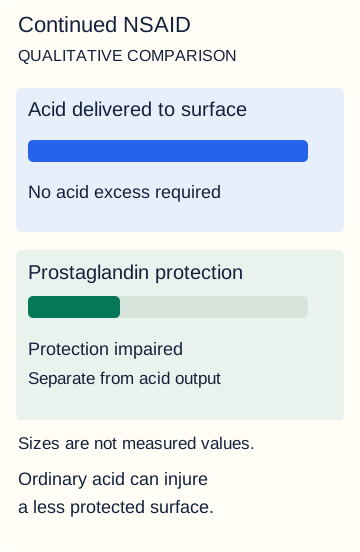
Protection is an active process: mucus and bicarbonate limit acid contact, mucosal blood flow supports tissue, and epithelial restitution repairs small defects. Prostaglandins support these defenses. NSAID inhibition of cyclooxygenase reduces prostaglandin-dependent protection, so ordinary acid exposure can injure a less protected surface. Lowering acid helps healing, but does not mean the NSAID's effect on protection has disappeared. [8][9]
Predict the effect of a PPI on acid and the effect of an NSAID on protection. Lowering acid supports healing without directly restoring prostaglandin synthesis. [7][8][9]
Compare acid delivery with mucosal protection
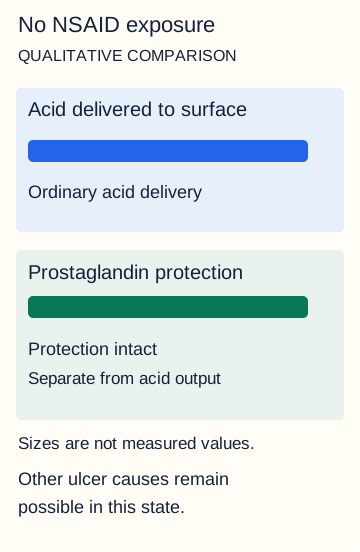
Predict acid delivery and mucosal protection separately for each scenario. These are qualitative comparisons, not measured percentages or estimates of ulcer probability. The complete comparison and each result remain visible without opening an explanation.
Visible comparison for all four scenarios
Scenario
Acid
Protection and consequence
ScenarioNo NSAID
AcidOrdinary delivery
Protection and consequenceIntact in this simplified model; other ulcer causes remain possible.
ScenarioContinued NSAID
AcidNo excess required
Protection and consequenceReduced protection permits injury from ordinary acid.
ScenarioNSAID plus PPI
AcidSuppressed
Protection and consequenceNSAID-related loss of protection persists; risk is reduced, not abolished.
ScenarioNSAID stopped plus PPI
AcidSuppressed
Protection and consequenceProtection can recover over time while acid suppression supports healing.
1. No NSAID exposure
With ordinary acid delivery and no NSAID effect, which side of this comparison is preserved?
Check the mechanism: No NSAID exposure
Prostaglandin-dependent protection is intact in this simplified model. Ordinary acid delivery is not the same as acid hypersecretion, and absence of NSAIDs does not exclude other ulcer causes. [8][9]
No NSAID-related defense loss; other causes of ulcer disease remain possible. Sizes are categorical illustrations, not measured percentages or ulcer probabilities. [8][9]
Visible result. No NSAID-related defense loss; other causes of ulcer disease remain possible.
2. Continued NSAID
Acid output remains ordinary while naproxen continues. Predict what changes at the mucosal surface.
Check the mechanism: Continued NSAID
Cyclooxygenase inhibition reduces prostaglandin-dependent protection. Mucus, bicarbonate, blood flow and repair are less effective, so ulceration does not require excess acid production. [8][9]
Ordinary acid can injure the surface when NSAID exposure weakens mucosal defenses. Sizes are categorical illustrations, not measured percentages or ulcer probabilities. [8][9]
Visible result. Ordinary acid can injure the surface when NSAID exposure weakens mucosal defenses.
3. NSAID plus PPI
Keep the NSAID and add a PPI. Predict the independent effects on acid delivery and protection.
Check the mechanism: NSAID plus PPI
The PPI inhibits the final acid pump, lowering acid delivery. Continued NSAID exposure can still impair prostaglandin-dependent defenses. Lower ulcer risk is not zero risk and does not mean prostaglandins have been restored. [8][9]
PPI reduces acid-related injury while the NSAID-related defense deficit can persist. Sizes are categorical illustrations, not measured percentages or ulcer probabilities. [8][9]
Visible result. PPI reduces acid-related injury while the NSAID-related defense deficit can persist.
4. NSAID stopped plus PPI
Now stop the NSAID and continue the PPI. Which benefit is not an immediate restoration of normal protection?
Check the mechanism: NSAID stopped plus PPI
Acid suppression supports healing while withdrawal removes the NSAID driver. Mucosal protection can recover over time; stopping the drug does not instantly normalize an injured surface. Actual healing depends on exposure, injury and other causes. [8][9]
Stopping the NSAID removes that driver; mucosal recovery takes time while the PPI supports healing. Sizes are categorical illustrations, not measured percentages or ulcer probabilities. [8][9]
Visible result. Stopping the NSAID removes that driver; mucosal recovery takes time while the PPI supports healing.
Transfer the comparison: for a patient who must continue an NSAID, explain why adding a PPI reduces but does not abolish risk. For a patient who can stop the NSAID, distinguish removal of the cause from the time needed for mucosal recovery. [8][9]
H. pylori provides a second test of this reasoning. Urease helps the organism survive its acidic environment. [13] Antral-predominant infection can reduce somatostatin inhibition, increase gastrin and increase acid delivery to the duodenum. Gastric-type metaplasia in the duodenum can harbor the organism in peptic duodenitis when gastric infection is also present. This is not the same process as gastric intestinal metaplasia. [14] With corpus-predominant atrophic gastritis, loss of acid-producing glands can instead lower acid output while gastric ulcer and cancer risk remain important. Thus infection does not always mean excess acid, and low acid does not establish a healthy stomach. [7]
Which cause must treatment address?
Compare two patients with similar-sized gastric ulcers: one takes daily naproxen, and the other has a positive urea breath test. A PPI can help both ulcers heal. Decide what must be added to the plan for each patient, then check whether the plan addresses the cause as well as the acid.
For NSAID-associated injury, stop the NSAID when feasible and provide ulcer-healing acid suppression. If anti-inflammatory treatment remains necessary, reassess the indication, dose, alternatives and combined gastrointestinal and cardiovascular risks; gastroprotection is often needed. Current or previous peptic ulcer disease is an indication to evaluate H. pylori status; treat documented infection. [12] Neither a negative infection test nor PPI use makes continued NSAID exposure harmless. Failure to heal calls for reassessment of adherence, ongoing exposures, infection and malignancy, not simply indefinite repetition of the same prescription. [9][10]
For H. pylori infection with unknown antibiotic susceptibility, the 2024 ACG guideline favors 14 days of optimized bismuth quadruple therapy: a PPI, bismuth, tetracycline and metronidazole. The PPI is twice daily; the other agents require multiple daily doses, so explain the schedule and likely adverse effects before treatment starts. Do not casually substitute doxycycline for tetracycline. Empiric clarithromycin or levofloxacin regimens are not reliable defaults because resistance matters. Clarithromycin- or levofloxacin-containing salvage treatment should be susceptibility-directed. Rifabutin triple therapy or vonoprazan-amoxicillin dual therapy are alternatives in appropriate patients without penicillin allergy; prior regimens and availability affect selection. [3][4]
For reflux, address exposure as well as secretion: weight reduction when appropriate, avoiding meals within two to three hours of bedtime, raising the head of the bed for nocturnal symptoms, stopping tobacco and avoiding personally reproducible triggers. After a successful uncomplicated trial, seek the lowest effective treatment and consider discontinuation or intermittent use when appropriate. Los Angeles grade C means mucosal breaks join the tops of at least two folds but involve less than 75% of the circumference; grade D involves at least 75%. Grade B has breaks longer than 5 mm that do not bridge fold tops. [15] Severe Los Angeles grade C or D esophagitis is different: long-term maintenance PPI or antireflux surgery is generally needed. Repeat endoscopy after healing severe esophagitis can assess underlying Barrett esophagus that inflammation previously obscured. [1]
Transfer the distinction to a patient who feels well after antibiotics: symptom improvement is encouraging but does not prove eradication. Plan the confirmation test before the treatment encounter ends.
When does a negative test become trustworthy?
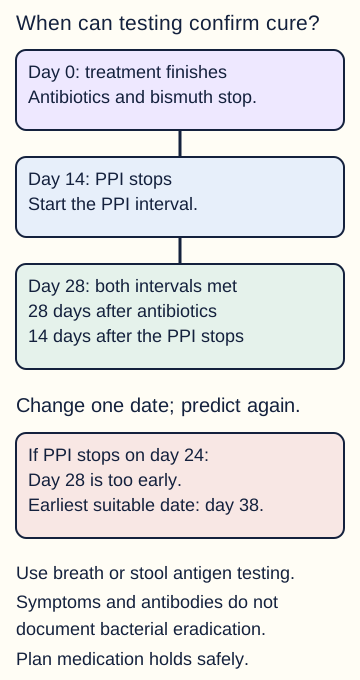
A patient completes H. pylori antibiotics and submits a stool antigen sample one week later while still taking a PPI. Predict whether a negative result proves cure. It does not: both timing and acid suppression can reduce the usefulness of the result. The testing calendar distinguishes the date antibiotics end from the date the PPI is stopped.
Calculate both intervals independently. Use at least four weeks after antibiotics and at least two weeks off PPI or potassium-competitive acid blocker therapy, with a safe symptom-management plan. This example assumes bismuth stops with antibiotics on day0; separate continued bismuth use requires its own four-week hold. [3][4][11][12]
Confirm eradication in every treated patient with a urea breath test, stool antigen test or appropriate biopsy-based test. Wait at least four weeks after antibiotics end and withhold PPI or potassium-competitive acid blocker therapy for at least two weeks before testing. Also withhold bismuth for at least four weeks before active testing, including bismuth taken separately after the antibiotic course. [12] When clinically suitable, H2 antagonists or antacids can bridge symptoms; follow the laboratory's instructions because H2 antagonists may also require a shorter hold before a breath test. If a needed drug cannot safely be withheld, arrange a testing strategy rather than accepting a potentially false negative. [3][4][11]
Set the antibiotic and bismuth completion date to day 0. If the PPI stops on day 14, the earliest test satisfying both minimum intervals is day 28. If it stops on day 24, day 28 is too early: the PPI interval does not finish until day 38. These are minimum scheduling intervals, not a reason to interrupt essential treatment without a plan.
A positive antibody test does not reliably distinguish current infection from past infection because antibodies may persist. It should not document cure. Urea breath and stool antigen testing evaluate active infection. A negative biopsy obtained during an acute bleed or while taking a PPI can also miss infection; arrange repeat testing under suitable conditions when suspicion remains. A negative result is an observation made under particular conditions, not an unconditional exclusion. [11]
Apply the same attention to the other clocks: an initial uncomplicated reflux trial is usually eight weeks, optimized bismuth quadruple therapy is 14 days, and an admitted patient with upper gastrointestinal bleeding generally needs endoscopy within 24 hours after presentation, with resuscitation first. The interval answers a different clinical question in each setting. [1][4][5]
Has the ulcer bled, obstructed or perforated?
One patient has melena, syncope and tachycardia. Another has abrupt severe abdominal pain with involuntary guarding. A third vomits food eaten many hours earlier and is volume depleted. Assign each to blood loss, peritoneal contamination or impaired gastric emptying before choosing the next action. These complications can coexist, but their immediate priorities differ.
Tachycardia, orthostasis and syncope can reflect depletion of circulating volume. For suspected significant bleeding, assess airway, circulation and ongoing loss; obtain intravenous access, laboratory studies and blood availability while resuscitating. A restrictive red-cell transfusion threshold around hemoglobin 7 g/dL applies to many hospitalized patients, not as a reason to delay blood in exsanguinating shock. Cardiovascular disease and the overall clinical context may alter decisions. The hemoglobin concentration may remain deceptively normal early in acute blood loss. Only carefully assessed very-low-risk patients, such as those with a Glasgow-Blatchford score of 0 or 1 and suitable follow-up, may avoid admission. Do not apply this shortcut to a patient with syncope and instability. [5]
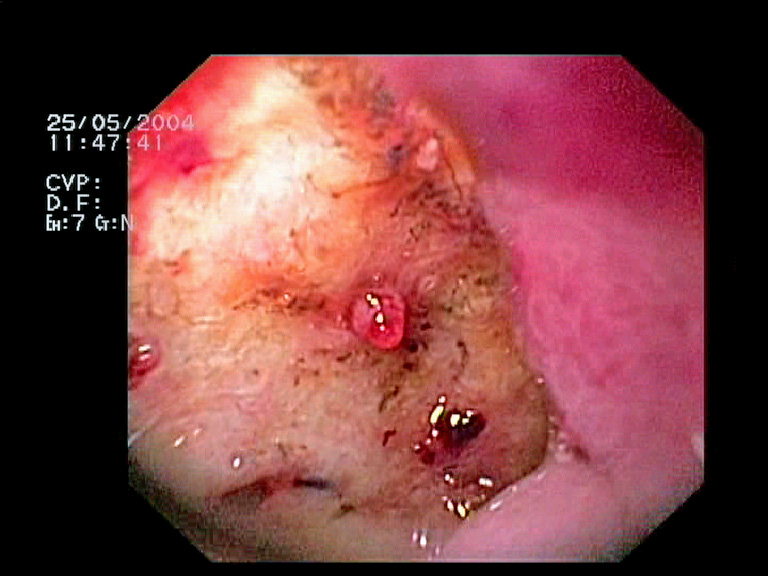
The visible-vessel endoscopy photograph tests a second decision: must an ulcer be actively spurting before it needs therapy? No. Active bleeding and a nonbleeding visible vessel are high-risk endoscopic findings that warrant hemostatic treatment. After successful treatment, high-dose PPI is recommended for three days, followed by twice-daily oral PPI for the first two weeks after endoscopy. Recurrent bleeding generally prompts repeat endoscopic treatment; failure of endoscopic control can require transcatheter embolization. [5]
Find the nonbleeding visible vessel at the ulcer base. A still image cannot determine current bleeding; a nonbleeding visible vessel warrants endoscopic hemostasis. Image: Jeremias; source; CC BY-SA 3.0. [5]
Sudden severe pain, rigidity and free intraperitoneal air suggest perforation. Begin resuscitation, broad-spectrum intravenous antibiotics and urgent surgical assessment together. CT is preferred when promptly available and the patient can safely undergo it; a negative upright radiograph does not exclude perforation. Do not delay necessary source control in an unstable patient to obtain a perfect image. Routine outpatient acid suppression or elective endoscopy cannot treat contamination of the peritoneal cavity. Nonoperative care is reserved for highly selected patients with a sealed perforation and no peritonitis or sepsis, under close specialist observation. [6]
Persistent vomiting, retained food and hypochloremic metabolic alkalosis suggest gastric outlet obstruction. Correct volume and electrolyte deficits and decompress the stomach as needed while investigating the obstruction and excluding malignancy. Persistent pain radiating to the back may reflect penetration into an adjacent organ such as the pancreas; it is not the same as free perforation. For either presentation, reassess anatomy rather than assuming more acid suppression is the entire solution. [10]
Apply the distinctions to new patients
For each case, name the affected compartment, decide whether the patient is stable, and identify the finding that changes testing or treatment. Commit to an answer before opening optional reasoning. Then explain why the nearest alternative would be appropriate in a different patient. The explanations remain available without JavaScript; answering never controls access to the lesson.
Case 1
Show answer and explanations for case 1
A. Premeal PPI trial; premeal PPI trial (Why this does not fit)
A PPI trial fits the first patient. The second has low-risk uninvestigated dyspepsia, for which active H. pylori testing precedes empiric PPI treatment in the ACG/CAG pathway.
Reasoning steps for option A
For the choice "Premeal PPI trial; premeal PPI trial", which findings in this case must the choice account for?
Retrosternal burning and sour regurgitation in the first patient; Epigastric discomfort and fullness without reflux symptoms in the second; Both younger and without alarms or gastric cancer risk.
What specific finding, threshold, mechanism, or management rule makes "Premeal PPI trial; premeal PPI trial" fit or fail in this case?
A PPI trial fits the first patient. The second has low-risk uninvestigated dyspepsia, for which active H. pylori testing precedes empiric PPI treatment in the ACG/CAG pathway.
Which case-specific discriminator separates "Premeal PPI trial; premeal PPI trial" from the competing choices?
Differentiate typical reflux from uninvestigated dyspepsia rather than assigning both burning syndromes to GERD. Then, Apply the distinct low-risk pathways: premeal PPI for the first and active infection test-and-treat for the second.
B. Active H. pylori testing; premeal PPI trial (Why this does not fit)
This reverses the initial approaches. Typical uncomplicated reflux supports a premeal PPI trial, while the second patient should first be tested for active H. pylori.
Reasoning steps for option B
For the choice "Active H. pylori testing; premeal PPI trial", which findings in this case must the choice account for?
Retrosternal burning and sour regurgitation in the first patient; Epigastric discomfort and fullness without reflux symptoms in the second; Both younger and without alarms or gastric cancer risk.
What specific finding, threshold, mechanism, or management rule makes "Active H. pylori testing; premeal PPI trial" fit or fail in this case?
This reverses the initial approaches. Typical uncomplicated reflux supports a premeal PPI trial, while the second patient should first be tested for active H. pylori.
Which case-specific discriminator separates "Active H. pylori testing; premeal PPI trial" from the competing choices?
Differentiate typical reflux from uninvestigated dyspepsia rather than assigning both burning syndromes to GERD. Then, Apply the distinct low-risk pathways: premeal PPI for the first and active infection test-and-treat for the second.
C. Premeal PPI trial; active H. pylori testing (Best answer)
The first presentation supports an eight-week once-daily premeal PPI trial. The second is low-risk dyspepsia: test for active H. pylori, eradicate if positive, and use a PPI if testing is negative or symptoms persist after eradication.
Reasoning steps for option C
For the choice "Premeal PPI trial; active H. pylori testing", which findings in this case must the choice account for?
Retrosternal burning and sour regurgitation in the first patient; Epigastric discomfort and fullness without reflux symptoms in the second; Both younger and without alarms or gastric cancer risk.
What specific finding, threshold, mechanism, or management rule makes "Premeal PPI trial; active H. pylori testing" fit or fail in this case?
The first presentation supports an eight-week once-daily premeal PPI trial. The second is low-risk dyspepsia: test for active H. pylori, eradicate if positive, and use a PPI if testing is negative or symptoms persist after eradication.
Which case-specific discriminator separates "Premeal PPI trial; active H. pylori testing" from the competing choices?
Differentiate typical reflux from uninvestigated dyspepsia rather than assigning both burning syndromes to GERD. Then, Apply the distinct low-risk pathways: premeal PPI for the first and active infection test-and-treat for the second.
D. Active H. pylori testing; active H. pylori testing (Why this does not fit)
Active infection testing fits the second patient. Routine H. pylori testing is not the initial GERD-specific investigation for the first patient without another indication.
Reasoning steps for option D
For the choice "Active H. pylori testing; active H. pylori testing", which findings in this case must the choice account for?
Retrosternal burning and sour regurgitation in the first patient; Epigastric discomfort and fullness without reflux symptoms in the second; Both younger and without alarms or gastric cancer risk.
What specific finding, threshold, mechanism, or management rule makes "Active H. pylori testing; active H. pylori testing" fit or fail in this case?
Active infection testing fits the second patient. Routine H. pylori testing is not the initial GERD-specific investigation for the first patient without another indication.
Which case-specific discriminator separates "Active H. pylori testing; active H. pylori testing" from the competing choices?
Differentiate typical reflux from uninvestigated dyspepsia rather than assigning both burning syndromes to GERD. Then, Apply the distinct low-risk pathways: premeal PPI for the first and active infection test-and-treat for the second.
Takeaway: Compare the symptom patterns before choosing the pathway: typical reflux supports a timed PPI trial, while low-risk uninvestigated dyspepsia starts with active H. pylori testing. [1][2]
A. GERD remains unproven; obtain endoscopy with sampling (Best answer)
Normal acid exposure during suppression does not establish the untreated reflux state. Independently, progressive dysphagia, weight loss and anemia require prompt endoscopic inspection and sampling of suspicious lesions.
Reasoning steps for option A
For the choice "GERD remains unproven; obtain endoscopy with sampling", which findings in this case must the choice account for?
Normal acid exposure measured while taking PPI; GERD has not been established off therapy; Progressive solid dysphagia with weight loss and iron deficiency despite relief of burning.
What specific finding, threshold, mechanism, or management rule makes "GERD remains unproven; obtain endoscopy with sampling" fit or fail in this case?
Normal acid exposure during suppression does not establish the untreated reflux state. Independently, progressive dysphagia, weight loss and anemia require prompt endoscopic inspection and sampling of suspicious lesions.
Which case-specific discriminator separates "GERD remains unproven; obtain endoscopy with sampling" from the competing choices?
Recognize that normal on-treatment acid exposure cannot establish or exclude the untreated reflux diagnosis. Then, Prioritize structural inspection and lesion sampling for the independent alarm presentation rather than choosing motility testing first.
B. GERD is excluded; obtain endoscopy with sampling (Why this does not fit)
Endoscopy is needed, but normal on-treatment acid exposure cannot exclude baseline GERD. Symptom response and the treated pH result also do not explain away the alarm findings.
Reasoning steps for option B
For the choice "GERD is excluded; obtain endoscopy with sampling", which findings in this case must the choice account for?
Normal acid exposure measured while taking PPI; GERD has not been established off therapy; Progressive solid dysphagia with weight loss and iron deficiency despite relief of burning.
What specific finding, threshold, mechanism, or management rule makes "GERD is excluded; obtain endoscopy with sampling" fit or fail in this case?
Endoscopy is needed, but normal on-treatment acid exposure cannot exclude baseline GERD. Symptom response and the treated pH result also do not explain away the alarm findings.
Which case-specific discriminator separates "GERD is excluded; obtain endoscopy with sampling" from the competing choices?
Recognize that normal on-treatment acid exposure cannot establish or exclude the untreated reflux diagnosis. Then, Prioritize structural inspection and lesion sampling for the independent alarm presentation rather than choosing motility testing first.
C. GERD remains unproven; obtain esophageal manometry (Why this does not fit)
The reflux interpretation is sound. Manometry, however, should not replace initial structural evaluation when progressive dysphagia, weight loss and anemia raise concern for narrowing or malignancy.
Reasoning steps for option C
For the choice "GERD remains unproven; obtain esophageal manometry", which findings in this case must the choice account for?
Normal acid exposure measured while taking PPI; GERD has not been established off therapy; Progressive solid dysphagia with weight loss and iron deficiency despite relief of burning.
What specific finding, threshold, mechanism, or management rule makes "GERD remains unproven; obtain esophageal manometry" fit or fail in this case?
The reflux interpretation is sound. Manometry, however, should not replace initial structural evaluation when progressive dysphagia, weight loss and anemia raise concern for narrowing or malignancy.
Which case-specific discriminator separates "GERD remains unproven; obtain esophageal manometry" from the competing choices?
Recognize that normal on-treatment acid exposure cannot establish or exclude the untreated reflux diagnosis. Then, Prioritize structural inspection and lesion sampling for the independent alarm presentation rather than choosing motility testing first.
D. GERD is excluded; obtain esophageal manometry (Why this does not fit)
This both overinterprets the on-PPI study and bypasses structural assessment. A treated acid measurement does not exclude GERD, and manometry cannot provide lesion histology.
Reasoning steps for option D
For the choice "GERD is excluded; obtain esophageal manometry", which findings in this case must the choice account for?
Normal acid exposure measured while taking PPI; GERD has not been established off therapy; Progressive solid dysphagia with weight loss and iron deficiency despite relief of burning.
What specific finding, threshold, mechanism, or management rule makes "GERD is excluded; obtain esophageal manometry" fit or fail in this case?
This both overinterprets the on-PPI study and bypasses structural assessment. A treated acid measurement does not exclude GERD, and manometry cannot provide lesion histology.
Which case-specific discriminator separates "GERD is excluded; obtain esophageal manometry" from the competing choices?
Recognize that normal on-treatment acid exposure cannot establish or exclude the untreated reflux diagnosis. Then, Prioritize structural inspection and lesion sampling for the independent alarm presentation rather than choosing motility testing first.
Takeaway: Interpret testing in its medication state, then act on the alarm presentation. A normal on-PPI pH result is not permission to defer endoscopy for progressive dysphagia. [1]
A. Before breakfast; prolonged reversible blockade of H2 receptors (Why this does not fit)
Premeal timing is appropriate, but omeprazole does not work by reversible H2-receptor antagonism.
Reasoning steps for option A
For the choice "Before breakfast; prolonged reversible blockade of H2 receptors", which findings in this case must the choice account for?
Adherent omeprazole taken hours after dinner; Persistent daytime symptoms without alarms; Short plasma half-life despite prolonged effect.
What specific finding, threshold, mechanism, or management rule makes "Before breakfast; prolonged reversible blockade of H2 receptors" fit or fail in this case?
Premeal timing is appropriate, but omeprazole does not work by reversible H2-receptor antagonism.
Which case-specific discriminator separates "Before breakfast; prolonged reversible blockade of H2 receptors" from the competing choices?
Identify a dose-meal mismatch rather than missed medication. Then, Explain persistent pharmacodynamic action through covalent pump inhibition rather than plasma persistence.
B. At bedtime; covalent inhibition of active proton pumps (Why this does not fit)
Covalent pump inhibition explains persistent action, but routine bedtime administration hours after food is poorly aligned with active pumps.
Reasoning steps for option B
For the choice "At bedtime; covalent inhibition of active proton pumps", which findings in this case must the choice account for?
Adherent omeprazole taken hours after dinner; Persistent daytime symptoms without alarms; Short plasma half-life despite prolonged effect.
What specific finding, threshold, mechanism, or management rule makes "At bedtime; covalent inhibition of active proton pumps" fit or fail in this case?
Covalent pump inhibition explains persistent action, but routine bedtime administration hours after food is poorly aligned with active pumps.
Which case-specific discriminator separates "At bedtime; covalent inhibition of active proton pumps" from the competing choices?
Identify a dose-meal mismatch rather than missed medication. Then, Explain persistent pharmacodynamic action through covalent pump inhibition rather than plasma persistence.
C. At bedtime; prolonged neutralization of acid in the lumen (Why this does not fit)
This treats a PPI like an antacid and does not correct the mismatch between drug availability and meal-stimulated pump activity.
Reasoning steps for option C
For the choice "At bedtime; prolonged neutralization of acid in the lumen", which findings in this case must the choice account for?
Adherent omeprazole taken hours after dinner; Persistent daytime symptoms without alarms; Short plasma half-life despite prolonged effect.
What specific finding, threshold, mechanism, or management rule makes "At bedtime; prolonged neutralization of acid in the lumen" fit or fail in this case?
This treats a PPI like an antacid and does not correct the mismatch between drug availability and meal-stimulated pump activity.
Which case-specific discriminator separates "At bedtime; prolonged neutralization of acid in the lumen" from the competing choices?
Identify a dose-meal mismatch rather than missed medication. Then, Explain persistent pharmacodynamic action through covalent pump inhibition rather than plasma persistence.
D. Before breakfast; covalent inhibition of active proton pumps (Best answer)
Premeal dosing aligns drug availability with active pumps; covalent binding explains why pump inhibition can outlast brief plasma exposure.
Reasoning steps for option D
For the choice "Before breakfast; covalent inhibition of active proton pumps", which findings in this case must the choice account for?
Adherent omeprazole taken hours after dinner; Persistent daytime symptoms without alarms; Short plasma half-life despite prolonged effect.
What specific finding, threshold, mechanism, or management rule makes "Before breakfast; covalent inhibition of active proton pumps" fit or fail in this case?
Premeal dosing aligns drug availability with active pumps; covalent binding explains why pump inhibition can outlast brief plasma exposure.
Which case-specific discriminator separates "Before breakfast; covalent inhibition of active proton pumps" from the competing choices?
Identify a dose-meal mismatch rather than missed medication. Then, Explain persistent pharmacodynamic action through covalent pump inhibition rather than plasma persistence.
Takeaway: Premeal dosing aligns drug availability with active pumps; covalent binding explains why pump inhibition can outlast brief plasma exposure. [1][8]
A. LA grade B; use PPI only during symptom flares (Why this does not fit)
Breaks continuous between fold tops are more extensive than grade B. The original severe injury, not just current symptoms, determines the need for ongoing maintenance.
Reasoning steps for option A
For the choice "LA grade B; use PPI only during symptom flares", which findings in this case must the choice account for?
Mucosal breaks bridge the tops of multiple folds; Approximately half the circumference is affected; Severe injury healed on PPI; medication is the selected long-term approach.
What specific finding, threshold, mechanism, or management rule makes "LA grade B; use PPI only during symptom flares" fit or fail in this case?
Breaks continuous between fold tops are more extensive than grade B. The original severe injury, not just current symptoms, determines the need for ongoing maintenance.
Which case-specific discriminator separates "LA grade B; use PPI only during symptom flares" from the competing choices?
Classify bridging mucosal breaks involving less than 75% of the circumference as LA grade C rather than B or D. Then, Use the original severe grade to retain maintenance therapy despite current healing and symptom resolution.
B. LA grade C; continue effective maintenance PPI (Best answer)
Bridging fold tops with involvement below 75% of the circumference is LA grade C. After healing severe esophagitis, ongoing effective maintenance PPI is indicated when medical management is selected.
Reasoning steps for option B
For the choice "LA grade C; continue effective maintenance PPI", which findings in this case must the choice account for?
Mucosal breaks bridge the tops of multiple folds; Approximately half the circumference is affected; Severe injury healed on PPI; medication is the selected long-term approach.
What specific finding, threshold, mechanism, or management rule makes "LA grade C; continue effective maintenance PPI" fit or fail in this case?
Bridging fold tops with involvement below 75% of the circumference is LA grade C. After healing severe esophagitis, ongoing effective maintenance PPI is indicated when medical management is selected.
Which case-specific discriminator separates "LA grade C; continue effective maintenance PPI" from the competing choices?
Classify bridging mucosal breaks involving less than 75% of the circumference as LA grade C rather than B or D. Then, Use the original severe grade to retain maintenance therapy despite current healing and symptom resolution.
C. LA grade D; continue effective maintenance PPI (Why this does not fit)
Maintenance is appropriate, but grade D requires involvement of at least 75% of the circumference. About half the circumference with bridging breaks fits grade C.
Reasoning steps for option C
For the choice "LA grade D; continue effective maintenance PPI", which findings in this case must the choice account for?
Mucosal breaks bridge the tops of multiple folds; Approximately half the circumference is affected; Severe injury healed on PPI; medication is the selected long-term approach.
What specific finding, threshold, mechanism, or management rule makes "LA grade D; continue effective maintenance PPI" fit or fail in this case?
Maintenance is appropriate, but grade D requires involvement of at least 75% of the circumference. About half the circumference with bridging breaks fits grade C.
Which case-specific discriminator separates "LA grade D; continue effective maintenance PPI" from the competing choices?
Classify bridging mucosal breaks involving less than 75% of the circumference as LA grade C rather than B or D. Then, Use the original severe grade to retain maintenance therapy despite current healing and symptom resolution.
D. LA grade C; use PPI only during symptom flares (Why this does not fit)
The grade is correct, but symptom-triggered short courses are not the preferred strategy for maintaining healed grade C disease. Absence of symptoms does not erase the recurrence risk.
Reasoning steps for option D
For the choice "LA grade C; use PPI only during symptom flares", which findings in this case must the choice account for?
Mucosal breaks bridge the tops of multiple folds; Approximately half the circumference is affected; Severe injury healed on PPI; medication is the selected long-term approach.
What specific finding, threshold, mechanism, or management rule makes "LA grade C; use PPI only during symptom flares" fit or fail in this case?
The grade is correct, but symptom-triggered short courses are not the preferred strategy for maintaining healed grade C disease. Absence of symptoms does not erase the recurrence risk.
Which case-specific discriminator separates "LA grade C; use PPI only during symptom flares" from the competing choices?
Classify bridging mucosal breaks involving less than 75% of the circumference as LA grade C rather than B or D. Then, Use the original severe grade to retain maintenance therapy despite current healing and symptom resolution.
Takeaway: Interpret the original endoscopic extent, then choose maintenance from that severity. Healed LA grade C disease still needs ongoing effective acid suppression or an appropriate procedural alternative. [1][15]
A. Impedance-pH monitoring after restarting twice-daily PPI (Why this does not fit)
This studies breakthrough reflux on therapy but is not the best way to establish an unproven baseline diagnosis.
Reasoning steps for option A
For the choice "Impedance-pH monitoring after restarting twice-daily PPI", which findings in this case must the choice account for?
Adequate empiric trial; Normal off-treatment endoscopy; No prior objective GERD evidence.
What specific finding, threshold, mechanism, or management rule makes "Impedance-pH monitoring after restarting twice-daily PPI" fit or fail in this case?
This studies breakthrough reflux on therapy but is not the best way to establish an unproven baseline diagnosis.
Which case-specific discriminator separates "Impedance-pH monitoring after restarting twice-daily PPI" from the competing choices?
Recognize that normal mucosa does not exclude reflux. Then, Select off-treatment testing because the baseline diagnosis is unproven.
B. Ambulatory reflux monitoring while remaining off PPI (Best answer)
Normal endoscopy does not exclude nonerosive GERD. Off-treatment monitoring evaluates baseline reflux exposure before assigning a functional or reflux diagnosis.
Reasoning steps for option B
For the choice "Ambulatory reflux monitoring while remaining off PPI", which findings in this case must the choice account for?
Adequate empiric trial; Normal off-treatment endoscopy; No prior objective GERD evidence.
What specific finding, threshold, mechanism, or management rule makes "Ambulatory reflux monitoring while remaining off PPI" fit or fail in this case?
Normal endoscopy does not exclude nonerosive GERD. Off-treatment monitoring evaluates baseline reflux exposure before assigning a functional or reflux diagnosis.
Which case-specific discriminator separates "Ambulatory reflux monitoring while remaining off PPI" from the competing choices?
Recognize that normal mucosa does not exclude reflux. Then, Select off-treatment testing because the baseline diagnosis is unproven.
C. Repeat upper endoscopy after another full PPI course (Why this does not fit)
A second treated examination will not quantify baseline acid exposure and may conceal erosions rather than resolve the question.
Reasoning steps for option C
For the choice "Repeat upper endoscopy after another full PPI course", which findings in this case must the choice account for?
Adequate empiric trial; Normal off-treatment endoscopy; No prior objective GERD evidence.
What specific finding, threshold, mechanism, or management rule makes "Repeat upper endoscopy after another full PPI course" fit or fail in this case?
A second treated examination will not quantify baseline acid exposure and may conceal erosions rather than resolve the question.
Which case-specific discriminator separates "Repeat upper endoscopy after another full PPI course" from the competing choices?
Recognize that normal mucosa does not exclude reflux. Then, Select off-treatment testing because the baseline diagnosis is unproven.
D. High-resolution manometry while remaining off PPI (Why this does not fit)
Manometry can identify motility disorders and is important before antireflux procedures, but it does not establish abnormal reflux exposure.
Reasoning steps for option D
For the choice "High-resolution manometry while remaining off PPI", which findings in this case must the choice account for?
Adequate empiric trial; Normal off-treatment endoscopy; No prior objective GERD evidence.
What specific finding, threshold, mechanism, or management rule makes "High-resolution manometry while remaining off PPI" fit or fail in this case?
Manometry can identify motility disorders and is important before antireflux procedures, but it does not establish abnormal reflux exposure.
Which case-specific discriminator separates "High-resolution manometry while remaining off PPI" from the competing choices?
Recognize that normal mucosa does not exclude reflux. Then, Select off-treatment testing because the baseline diagnosis is unproven.
Takeaway: Normal endoscopy does not exclude nonerosive GERD. Off-treatment monitoring evaluates baseline reflux exposure before assigning a functional or reflux diagnosis. [1]
A. Wireless acid monitoring after discontinuing all PPI therapy (Why this does not fit)
Off-treatment testing can establish GERD, but severe prior esophagitis has already established it; the current question concerns symptoms during treatment.
Reasoning steps for option A
For the choice "Wireless acid monitoring after discontinuing all PPI therapy", which findings in this case must the choice account for?
Prior LA grade C; Adherent optimized twice-daily dosing; Persistent regurgitation with healed mucosa.
What specific finding, threshold, mechanism, or management rule makes "Wireless acid monitoring after discontinuing all PPI therapy" fit or fail in this case?
Off-treatment testing can establish GERD, but severe prior esophagitis has already established it; the current question concerns symptoms during treatment.
Which case-specific discriminator separates "Wireless acid monitoring after discontinuing all PPI therapy" from the competing choices?
Recognize that GERD is established despite current healing. Then, Choose a study detecting acid and nonacid reflux during the symptomatic treatment state.
B. Gastric emptying scintigraphy while continuing the PPI (Why this does not fit)
This could evaluate suspected delayed gastric emptying, but it does not measure esophageal reflux-symptom association and no retained-food syndrome is given.
Reasoning steps for option B
For the choice "Gastric emptying scintigraphy while continuing the PPI", which findings in this case must the choice account for?
Prior LA grade C; Adherent optimized twice-daily dosing; Persistent regurgitation with healed mucosa.
What specific finding, threshold, mechanism, or management rule makes "Gastric emptying scintigraphy while continuing the PPI" fit or fail in this case?
This could evaluate suspected delayed gastric emptying, but it does not measure esophageal reflux-symptom association and no retained-food syndrome is given.
Which case-specific discriminator separates "Gastric emptying scintigraphy while continuing the PPI" from the competing choices?
Recognize that GERD is established despite current healing. Then, Choose a study detecting acid and nonacid reflux during the symptomatic treatment state.
C. Esophageal manometry after withholding the morning PPI (Why this does not fit)
Manometry is needed in preprocedural assessment to exclude important motility disorders, but does not directly answer the reflux-symptom association question.
Reasoning steps for option C
For the choice "Esophageal manometry after withholding the morning PPI", which findings in this case must the choice account for?
Prior LA grade C; Adherent optimized twice-daily dosing; Persistent regurgitation with healed mucosa.
What specific finding, threshold, mechanism, or management rule makes "Esophageal manometry after withholding the morning PPI" fit or fail in this case?
Manometry is needed in preprocedural assessment to exclude important motility disorders, but does not directly answer the reflux-symptom association question.
Which case-specific discriminator separates "Esophageal manometry after withholding the morning PPI" from the competing choices?
Recognize that GERD is established despite current healing. Then, Choose a study detecting acid and nonacid reflux during the symptomatic treatment state.
D. Impedance-pH monitoring while continuing the PPI (Best answer)
Established GERD and optimized treatment support on-therapy impedance-pH monitoring, which can detect acid and nonacid reflux and relate episodes to symptoms.
Reasoning steps for option D
For the choice "Impedance-pH monitoring while continuing the PPI", which findings in this case must the choice account for?
Prior LA grade C; Adherent optimized twice-daily dosing; Persistent regurgitation with healed mucosa.
What specific finding, threshold, mechanism, or management rule makes "Impedance-pH monitoring while continuing the PPI" fit or fail in this case?
Established GERD and optimized treatment support on-therapy impedance-pH monitoring, which can detect acid and nonacid reflux and relate episodes to symptoms.
Which case-specific discriminator separates "Impedance-pH monitoring while continuing the PPI" from the competing choices?
Recognize that GERD is established despite current healing. Then, Choose a study detecting acid and nonacid reflux during the symptomatic treatment state.
Takeaway: Established GERD and optimized treatment support on-therapy impedance-pH monitoring, which can detect acid and nonacid reflux and relate episodes to symptoms. [1]
A. Stop naproxen; repeat active infection testing after suitable holds (Best answer)
The NSAID is avoidable and likely contributes, but suppression makes the negative active test unreliable. Address the exposure and reassess potentially coexisting infection.
Reasoning steps for option A
For the choice "Stop naproxen; repeat active infection testing after suitable holds", which findings in this case must the choice account for?
Avoidable naproxen exposure; Gastric ulcer with benign margin biopsies; Negative active test during PPI and recent antibiotics.
What specific finding, threshold, mechanism, or management rule makes "Stop naproxen; repeat active infection testing after suitable holds" fit or fail in this case?
The NSAID is avoidable and likely contributes, but suppression makes the negative active test unreliable. Address the exposure and reassess potentially coexisting infection.
Which case-specific discriminator separates "Stop naproxen; repeat active infection testing after suitable holds" from the competing choices?
Choose withdrawal of an avoidable ulcerogenic exposure. Then, Recognize that concurrent infection has not been adequately excluded and arrange valid active testing.
B. Continue naproxen; repeat active infection testing after suitable holds (Why this does not fit)
Repeating the test is appropriate, but continuing an avoidable NSAID preserves another important ulcer cause.
Reasoning steps for option B
For the choice "Continue naproxen; repeat active infection testing after suitable holds", which findings in this case must the choice account for?
Avoidable naproxen exposure; Gastric ulcer with benign margin biopsies; Negative active test during PPI and recent antibiotics.
What specific finding, threshold, mechanism, or management rule makes "Continue naproxen; repeat active infection testing after suitable holds" fit or fail in this case?
Repeating the test is appropriate, but continuing an avoidable NSAID preserves another important ulcer cause.
Which case-specific discriminator separates "Continue naproxen; repeat active infection testing after suitable holds" from the competing choices?
Choose withdrawal of an avoidable ulcerogenic exposure. Then, Recognize that concurrent infection has not been adequately excluded and arrange valid active testing.
C. Stop naproxen; accept the existing negative infection result (Why this does not fit)
Withdrawal is appropriate, but the negative result under two suppressive exposures does not adequately exclude infection.
Reasoning steps for option C
For the choice "Stop naproxen; accept the existing negative infection result", which findings in this case must the choice account for?
Avoidable naproxen exposure; Gastric ulcer with benign margin biopsies; Negative active test during PPI and recent antibiotics.
What specific finding, threshold, mechanism, or management rule makes "Stop naproxen; accept the existing negative infection result" fit or fail in this case?
Withdrawal is appropriate, but the negative result under two suppressive exposures does not adequately exclude infection.
Which case-specific discriminator separates "Stop naproxen; accept the existing negative infection result" from the competing choices?
Choose withdrawal of an avoidable ulcerogenic exposure. Then, Recognize that concurrent infection has not been adequately excluded and arrange valid active testing.
D. Continue naproxen; accept the existing negative infection result (Why this does not fit)
This leaves an avoidable exposure in place and treats an inadequately prepared test as definitive.
Reasoning steps for option D
For the choice "Continue naproxen; accept the existing negative infection result", which findings in this case must the choice account for?
Avoidable naproxen exposure; Gastric ulcer with benign margin biopsies; Negative active test during PPI and recent antibiotics.
What specific finding, threshold, mechanism, or management rule makes "Continue naproxen; accept the existing negative infection result" fit or fail in this case?
This leaves an avoidable exposure in place and treats an inadequately prepared test as definitive.
Which case-specific discriminator separates "Continue naproxen; accept the existing negative infection result" from the competing choices?
Choose withdrawal of an avoidable ulcerogenic exposure. Then, Recognize that concurrent infection has not been adequately excluded and arrange valid active testing.
Takeaway: The NSAID is avoidable and likely contributes, but suppression makes the negative active test unreliable. Address the exposure and reassess potentially coexisting infection. [9][11][12]
A. Prostaglandin restoration; accept the negative test as cure (Why this does not fit)
Acid suppression does not directly reverse NSAID prostaglandin loss, and continued PPI can reduce active-test sensitivity.
Reasoning steps for option A
For the choice "Prostaglandin restoration; accept the negative test as cure", which findings in this case must the choice account for?
Necessary NSAID exposure with concurrent daily PPI; Adequate antibiotic and bismuth interval; Negative stool antigen without a PPI hold.
What specific finding, threshold, mechanism, or management rule makes "Prostaglandin restoration; accept the negative test as cure" fit or fail in this case?
Acid suppression does not directly reverse NSAID prostaglandin loss, and continued PPI can reduce active-test sensitivity.
Which case-specific discriminator separates "Prostaglandin restoration; accept the negative test as cure" from the competing choices?
Identify acid suppression without assuming restoration of mucosal prostaglandins. Then, Evaluate both medication-preparation intervals rather than accepting the antibiotic interval alone.
B. Prostaglandin restoration; repeat testing after a safe PPI hold (Why this does not fit)
The test limitation is recognized, but protection comes through acid reduction, not restoration of prostaglandin synthesis.
Reasoning steps for option B
For the choice "Prostaglandin restoration; repeat testing after a safe PPI hold", which findings in this case must the choice account for?
Necessary NSAID exposure with concurrent daily PPI; Adequate antibiotic and bismuth interval; Negative stool antigen without a PPI hold.
What specific finding, threshold, mechanism, or management rule makes "Prostaglandin restoration; repeat testing after a safe PPI hold" fit or fail in this case?
The test limitation is recognized, but protection comes through acid reduction, not restoration of prostaglandin synthesis.
Which case-specific discriminator separates "Prostaglandin restoration; repeat testing after a safe PPI hold" from the competing choices?
Identify acid suppression without assuming restoration of mucosal prostaglandins. Then, Evaluate both medication-preparation intervals rather than accepting the antibiotic interval alone.
C. Acid suppression; repeat testing after a safe PPI hold (Best answer)
PPI reduces acid burden despite ongoing impaired defense. Six weeks after antibiotics is adequate, but the missing PPI hold leaves a negative test unreliable.
Reasoning steps for option C
For the choice "Acid suppression; repeat testing after a safe PPI hold", which findings in this case must the choice account for?
Necessary NSAID exposure with concurrent daily PPI; Adequate antibiotic and bismuth interval; Negative stool antigen without a PPI hold.
What specific finding, threshold, mechanism, or management rule makes "Acid suppression; repeat testing after a safe PPI hold" fit or fail in this case?
PPI reduces acid burden despite ongoing impaired defense. Six weeks after antibiotics is adequate, but the missing PPI hold leaves a negative test unreliable.
Which case-specific discriminator separates "Acid suppression; repeat testing after a safe PPI hold" from the competing choices?
Identify acid suppression without assuming restoration of mucosal prostaglandins. Then, Evaluate both medication-preparation intervals rather than accepting the antibiotic interval alone.
D. Acid suppression; accept the negative test as cure (Why this does not fit)
The protective mechanism is correctly identified, but the antibiotic interval alone does not make an on-PPI negative active test conclusive.
Reasoning steps for option D
For the choice "Acid suppression; accept the negative test as cure", which findings in this case must the choice account for?
Necessary NSAID exposure with concurrent daily PPI; Adequate antibiotic and bismuth interval; Negative stool antigen without a PPI hold.
What specific finding, threshold, mechanism, or management rule makes "Acid suppression; accept the negative test as cure" fit or fail in this case?
The protective mechanism is correctly identified, but the antibiotic interval alone does not make an on-PPI negative active test conclusive.
Which case-specific discriminator separates "Acid suppression; accept the negative test as cure" from the competing choices?
Identify acid suppression without assuming restoration of mucosal prostaglandins. Then, Evaluate both medication-preparation intervals rather than accepting the antibiotic interval alone.
Takeaway: PPI reduces acid burden despite ongoing impaired defense. Six weeks after antibiotics is adequate, but the missing PPI hold leaves a negative test unreliable. [8][9][11][12]
A. Defer ulcer biopsy; give optimized bismuth quadruple therapy (Why this does not fit)
The empiric regimen is appropriate, but a plausible infectious cause and symptom relief do not replace tissue assessment of an irregular gastric ulcer.
Reasoning steps for option A
For the choice "Defer ulcer biopsy; give optimized bismuth quadruple therapy", which findings in this case must the choice account for?
Irregular gastric ulcer not sampled; H. pylori in adjacent mucosa; No prior eradication and unknown susceptibility.
What specific finding, threshold, mechanism, or management rule makes "Defer ulcer biopsy; give optimized bismuth quadruple therapy" fit or fail in this case?
The empiric regimen is appropriate, but a plausible infectious cause and symptom relief do not replace tissue assessment of an irregular gastric ulcer.
Which case-specific discriminator separates "Defer ulcer biopsy; give optimized bismuth quadruple therapy" from the competing choices?
Keep the lesion-histology question separate from infection causation. Then, Choose a suitable empiric eradication regimen given absent susceptibility data.
B. Obtain ulcer biopsies; give empiric clarithromycin triple therapy (Why this does not fit)
Lesion sampling is appropriate, but clarithromycin should not be selected empirically without evidence of susceptibility.
Reasoning steps for option B
For the choice "Obtain ulcer biopsies; give empiric clarithromycin triple therapy", which findings in this case must the choice account for?
Irregular gastric ulcer not sampled; H. pylori in adjacent mucosa; No prior eradication and unknown susceptibility.
What specific finding, threshold, mechanism, or management rule makes "Obtain ulcer biopsies; give empiric clarithromycin triple therapy" fit or fail in this case?
Lesion sampling is appropriate, but clarithromycin should not be selected empirically without evidence of susceptibility.
Which case-specific discriminator separates "Obtain ulcer biopsies; give empiric clarithromycin triple therapy" from the competing choices?
Keep the lesion-histology question separate from infection causation. Then, Choose a suitable empiric eradication regimen given absent susceptibility data.
C. Defer ulcer biopsy; give empiric clarithromycin triple therapy (Why this does not fit)
This assumes benign histology from infection and uses an unsupported empiric antibiotic regimen.
Reasoning steps for option C
For the choice "Defer ulcer biopsy; give empiric clarithromycin triple therapy", which findings in this case must the choice account for?
Irregular gastric ulcer not sampled; H. pylori in adjacent mucosa; No prior eradication and unknown susceptibility.
What specific finding, threshold, mechanism, or management rule makes "Defer ulcer biopsy; give empiric clarithromycin triple therapy" fit or fail in this case?
This assumes benign histology from infection and uses an unsupported empiric antibiotic regimen.
Which case-specific discriminator separates "Defer ulcer biopsy; give empiric clarithromycin triple therapy" from the competing choices?
Keep the lesion-histology question separate from infection causation. Then, Choose a suitable empiric eradication regimen given absent susceptibility data.
D. Obtain ulcer biopsies; give optimized bismuth quadruple therapy (Best answer)
Gastric lesion histology remains unresolved despite adjacent-mucosa infection. Treat proven infection using an appropriate unknown-susceptibility regimen while obtaining lesion assessment.
Reasoning steps for option D
For the choice "Obtain ulcer biopsies; give optimized bismuth quadruple therapy", which findings in this case must the choice account for?
Irregular gastric ulcer not sampled; H. pylori in adjacent mucosa; No prior eradication and unknown susceptibility.
What specific finding, threshold, mechanism, or management rule makes "Obtain ulcer biopsies; give optimized bismuth quadruple therapy" fit or fail in this case?
Gastric lesion histology remains unresolved despite adjacent-mucosa infection. Treat proven infection using an appropriate unknown-susceptibility regimen while obtaining lesion assessment.
Which case-specific discriminator separates "Obtain ulcer biopsies; give optimized bismuth quadruple therapy" from the competing choices?
Keep the lesion-histology question separate from infection causation. Then, Choose a suitable empiric eradication regimen given absent susceptibility data.
Takeaway: Gastric lesion histology remains unresolved despite adjacent-mucosa infection. Treat proven infection using an appropriate unknown-susceptibility regimen while obtaining lesion assessment. [3][4][10]
A. Repeat endoscopy now to obtain routine ulcer-margin cancer biopsies (Why this does not fit)
That concern is substantially different for gastric ulcers; an uncomplicated healed clinical course in the duodenal bulb does not require routine cancer sampling.
Reasoning steps for option A
For the choice "Repeat endoscopy now to obtain routine ulcer-margin cancer biopsies", which findings in this case must the choice account for?
Uncomplicated duodenal ulcer with symptom resolution; Negative active test six weeks after all antibiotics and bismuth and three weeks off PPI, with no resumption; No persistent alarm findings.
What specific finding, threshold, mechanism, or management rule makes "Repeat endoscopy now to obtain routine ulcer-margin cancer biopsies" fit or fail in this case?
That concern is substantially different for gastric ulcers; an uncomplicated healed clinical course in the duodenal bulb does not require routine cancer sampling.
Which case-specific discriminator separates "Repeat endoscopy now to obtain routine ulcer-margin cancer biopsies" from the competing choices?
Determine that active testing meets both timing requirements. Then, Distinguish duodenal from gastric malignancy follow-up.
B. Accept eradication without routine repeat endoscopy for cancer biopsy (Best answer)
The negative test was appropriately timed, and uncomplicated duodenal ulcers have very low malignant potential. New or persistent symptoms would change follow-up.
Reasoning steps for option B
For the choice "Accept eradication without routine repeat endoscopy for cancer biopsy", which findings in this case must the choice account for?
Uncomplicated duodenal ulcer with symptom resolution; Negative active test six weeks after all antibiotics and bismuth and three weeks off PPI, with no resumption; No persistent alarm findings.
What specific finding, threshold, mechanism, or management rule makes "Accept eradication without routine repeat endoscopy for cancer biopsy" fit or fail in this case?
The negative test was appropriately timed, and uncomplicated duodenal ulcers have very low malignant potential. New or persistent symptoms would change follow-up.
Which case-specific discriminator separates "Accept eradication without routine repeat endoscopy for cancer biopsy" from the competing choices?
Determine that active testing meets both timing requirements. Then, Distinguish duodenal from gastric malignancy follow-up.
C. Repeat the eradication regimen before arranging any further follow-up (Why this does not fit)
Appropriately timed negative active testing and clinical resolution provide no evidence requiring another antibiotic course.
Reasoning steps for option C
For the choice "Repeat the eradication regimen before arranging any further follow-up", which findings in this case must the choice account for?
Uncomplicated duodenal ulcer with symptom resolution; Negative active test six weeks after all antibiotics and bismuth and three weeks off PPI, with no resumption; No persistent alarm findings.
What specific finding, threshold, mechanism, or management rule makes "Repeat the eradication regimen before arranging any further follow-up" fit or fail in this case?
Appropriately timed negative active testing and clinical resolution provide no evidence requiring another antibiotic course.
Which case-specific discriminator separates "Repeat the eradication regimen before arranging any further follow-up" from the competing choices?
Determine that active testing meets both timing requirements. Then, Distinguish duodenal from gastric malignancy follow-up.
D. Order H. pylori IgG before accepting the stool antigen result (Why this does not fit)
Persistent antibodies cannot overturn an appropriately timed negative active test or establish treatment failure.
Reasoning steps for option D
For the choice "Order H. pylori IgG before accepting the stool antigen result", which findings in this case must the choice account for?
Uncomplicated duodenal ulcer with symptom resolution; Negative active test six weeks after all antibiotics and bismuth and three weeks off PPI, with no resumption; No persistent alarm findings.
What specific finding, threshold, mechanism, or management rule makes "Order H. pylori IgG before accepting the stool antigen result" fit or fail in this case?
Persistent antibodies cannot overturn an appropriately timed negative active test or establish treatment failure.
Which case-specific discriminator separates "Order H. pylori IgG before accepting the stool antigen result" from the competing choices?
Determine that active testing meets both timing requirements. Then, Distinguish duodenal from gastric malignancy follow-up.
Takeaway: The negative test was appropriately timed, and uncomplicated duodenal ulcers have very low malignant potential. New or persistent symptoms would change follow-up. [3][4][10][11]
A. Persistent infection; optimized bismuth quadruple therapy (Best answer)
The positive active test was suitably timed. After clarithromycin-based treatment and without previous optimized quadruple therapy, the latter is an appropriate empiric regimen.
Reasoning steps for option A
For the choice "Persistent infection; optimized bismuth quadruple therapy", which findings in this case must the choice account for?
Positive breath test six weeks after antibiotics and three weeks off PPI; Previous clarithromycin regimen; No previous optimized bismuth quadruple therapy.
What specific finding, threshold, mechanism, or management rule makes "Persistent infection; optimized bismuth quadruple therapy" fit or fail in this case?
The positive active test was suitably timed. After clarithromycin-based treatment and without previous optimized quadruple therapy, the latter is an appropriate empiric regimen.
Which case-specific discriminator separates "Persistent infection; optimized bismuth quadruple therapy" from the competing choices?
Confirm that active-test timing supports true persistence despite symptom relief. Then, Use prior failed therapy and absence of previous optimized BQT to choose the next regimen.
B. Persistent infection; another clarithromycin triple course (Why this does not fit)
Test interpretation is correct, but repeating a failed clarithromycin regimen without susceptibility support is inappropriate.
Reasoning steps for option B
For the choice "Persistent infection; another clarithromycin triple course", which findings in this case must the choice account for?
Positive breath test six weeks after antibiotics and three weeks off PPI; Previous clarithromycin regimen; No previous optimized bismuth quadruple therapy.
What specific finding, threshold, mechanism, or management rule makes "Persistent infection; another clarithromycin triple course" fit or fail in this case?
Test interpretation is correct, but repeating a failed clarithromycin regimen without susceptibility support is inappropriate.
Which case-specific discriminator separates "Persistent infection; another clarithromycin triple course" from the competing choices?
Confirm that active-test timing supports true persistence despite symptom relief. Then, Use prior failed therapy and absence of previous optimized BQT to choose the next regimen.
C. Residual test positivity after cure; defer further therapy (Why this does not fit)
Breath testing detects active urease activity, unlike persistent antibodies, and this appropriately timed positive test should not be dismissed as a cured state.
Reasoning steps for option C
For the choice "Residual test positivity after cure; defer further therapy", which findings in this case must the choice account for?
Positive breath test six weeks after antibiotics and three weeks off PPI; Previous clarithromycin regimen; No previous optimized bismuth quadruple therapy.
What specific finding, threshold, mechanism, or management rule makes "Residual test positivity after cure; defer further therapy" fit or fail in this case?
Breath testing detects active urease activity, unlike persistent antibodies, and this appropriately timed positive test should not be dismissed as a cured state.
Which case-specific discriminator separates "Residual test positivity after cure; defer further therapy" from the competing choices?
Confirm that active-test timing supports true persistence despite symptom relief. Then, Use prior failed therapy and absence of previous optimized BQT to choose the next regimen.
D. Uninterpretable test timing; repeat breath testing in six weeks (Why this does not fit)
The antibiotic and PPI intervals already satisfy minimum requirements; an automatic six-week delay does not address documented persistent infection.
Reasoning steps for option D
For the choice "Uninterpretable test timing; repeat breath testing in six weeks", which findings in this case must the choice account for?
Positive breath test six weeks after antibiotics and three weeks off PPI; Previous clarithromycin regimen; No previous optimized bismuth quadruple therapy.
What specific finding, threshold, mechanism, or management rule makes "Uninterpretable test timing; repeat breath testing in six weeks" fit or fail in this case?
The antibiotic and PPI intervals already satisfy minimum requirements; an automatic six-week delay does not address documented persistent infection.
Which case-specific discriminator separates "Uninterpretable test timing; repeat breath testing in six weeks" from the competing choices?
Confirm that active-test timing supports true persistence despite symptom relief. Then, Use prior failed therapy and absence of previous optimized BQT to choose the next regimen.
Takeaway: The positive active test was suitably timed. After clarithromycin-based treatment and without previous optimized quadruple therapy, the latter is an appropriate empiric regimen. [3][4][11]
Only 25 days have elapsed after antibiotics and four days after PPI cessation; neither minimum interval is satisfied.
Reasoning steps for option A
For the choice "September 27", which findings in this case must the choice account for?
Antibiotics and bismuth end September2; PPI ends September23; No resumed suppressive medication or bismuth.
What specific finding, threshold, mechanism, or management rule makes "September 27" fit or fail in this case?
Only 25 days have elapsed after antibiotics and four days after PPI cessation; neither minimum interval is satisfied.
Which case-specific discriminator separates "September 27" from the competing choices?
Calculate antibiotic minimum as September30. Then, Calculate PPI minimum as October7 and choose the later date.
B. September 30 (Why this does not fit)
Four weeks have elapsed after antibiotics, but only one week after PPI cessation; the PPI interval still fails.
Reasoning steps for option B
For the choice "September 30", which findings in this case must the choice account for?
Antibiotics and bismuth end September2; PPI ends September23; No resumed suppressive medication or bismuth.
What specific finding, threshold, mechanism, or management rule makes "September 30" fit or fail in this case?
Four weeks have elapsed after antibiotics, but only one week after PPI cessation; the PPI interval still fails.
Which case-specific discriminator separates "September 30" from the competing choices?
Calculate antibiotic minimum as September30. Then, Calculate PPI minimum as October7 and choose the later date.
C. October 7 (Best answer)
This date is at least four weeks after antibiotics and two weeks after stopping PPI; the later-finishing interval determines the earliest suitable date.
Reasoning steps for option C
For the choice "October 7", which findings in this case must the choice account for?
Antibiotics and bismuth end September2; PPI ends September23; No resumed suppressive medication or bismuth.
What specific finding, threshold, mechanism, or management rule makes "October 7" fit or fail in this case?
This date is at least four weeks after antibiotics and two weeks after stopping PPI; the later-finishing interval determines the earliest suitable date.
Which case-specific discriminator separates "October 7" from the competing choices?
Calculate antibiotic minimum as September30. Then, Calculate PPI minimum as October7 and choose the later date.
D. October 21 (Why this does not fit)
Both intervals are satisfied, but this is not the earliest offered date; the guideline does not require four weeks off the PPI.
Reasoning steps for option D
For the choice "October 21", which findings in this case must the choice account for?
Antibiotics and bismuth end September2; PPI ends September23; No resumed suppressive medication or bismuth.
What specific finding, threshold, mechanism, or management rule makes "October 21" fit or fail in this case?
Both intervals are satisfied, but this is not the earliest offered date; the guideline does not require four weeks off the PPI.
Which case-specific discriminator separates "October 21" from the competing choices?
Calculate antibiotic minimum as September30. Then, Calculate PPI minimum as October7 and choose the later date.
Takeaway: This date is at least four weeks after antibiotics and two weeks after stopping PPI; the later-finishing interval determines the earliest suitable date. [3][4]
A. Start eradication therapy based on positive serum IgG (Why this does not fit)
A positive antibody test can reflect remote infection. It does not establish active infection or justify treating this discordant result as confirmed infection without addressing the unreliable active test.
Reasoning steps for option A
For the choice "Start eradication therapy based on positive serum IgG", which findings in this case must the choice account for?
Negative active test during PPI/recent antibiotics; Positive antibody; No documented eradication course.
What specific finding, threshold, mechanism, or management rule makes "Start eradication therapy based on positive serum IgG" fit or fail in this case?
A positive antibody test can reflect remote infection. It does not establish active infection or justify treating this discordant result as confirmed infection without addressing the unreliable active test.
Which case-specific discriminator separates "Start eradication therapy based on positive serum IgG" from the competing choices?
Identify suppressed sensitivity of the negative active test. Then, Recognize that antibody positivity cannot settle current infection status.
B. Exclude H. pylori based on negative stool antigen (Why this does not fit)
PPI and recent antibiotics can suppress active-test sensitivity; the negative result was obtained under unreliable conditions.
Reasoning steps for option B
For the choice "Exclude H. pylori based on negative stool antigen", which findings in this case must the choice account for?
Negative active test during PPI/recent antibiotics; Positive antibody; No documented eradication course.
What specific finding, threshold, mechanism, or management rule makes "Exclude H. pylori based on negative stool antigen" fit or fail in this case?
PPI and recent antibiotics can suppress active-test sensitivity; the negative result was obtained under unreliable conditions.
Which case-specific discriminator separates "Exclude H. pylori based on negative stool antigen" from the competing choices?
Identify suppressed sensitivity of the negative active test. Then, Recognize that antibody positivity cannot settle current infection status.
C. Repeat stool antigen after safe medication washout (Best answer)
The tests answer different questions and both have limitations here. Repeat stool antigen or breath testing under suitable medication conditions before assigning infection status.
Reasoning steps for option C
For the choice "Repeat stool antigen after safe medication washout", which findings in this case must the choice account for?
Negative active test during PPI/recent antibiotics; Positive antibody; No documented eradication course.
What specific finding, threshold, mechanism, or management rule makes "Repeat stool antigen after safe medication washout" fit or fail in this case?
The tests answer different questions and both have limitations here. Repeat stool antigen or breath testing under suitable medication conditions before assigning infection status.
Which case-specific discriminator separates "Repeat stool antigen after safe medication washout" from the competing choices?
Identify suppressed sensitivity of the negative active test. Then, Recognize that antibody positivity cannot settle current infection status.
D. Repeat serum IgG after safe medication washout (Why this does not fit)
Waiting through a medication washout does not make serum IgG an active-infection test. Antibodies can persist; use a properly prepared breath or stool antigen test to settle the current infection question.
Reasoning steps for option D
For the choice "Repeat serum IgG after safe medication washout", which findings in this case must the choice account for?
Negative active test during PPI/recent antibiotics; Positive antibody; No documented eradication course.
What specific finding, threshold, mechanism, or management rule makes "Repeat serum IgG after safe medication washout" fit or fail in this case?
Waiting through a medication washout does not make serum IgG an active-infection test. Antibodies can persist; use a properly prepared breath or stool antigen test to settle the current infection question.
Which case-specific discriminator separates "Repeat serum IgG after safe medication washout" from the competing choices?
Identify suppressed sensitivity of the negative active test. Then, Recognize that antibody positivity cannot settle current infection status.
Takeaway: The tests answer different questions and both have limitations here. Repeat stool antigen or breath testing under suitable medication conditions before assigning infection status. [4][11]
A. Continue resuscitation while arranging endoscopic hemostasis (Best answer)
Persistent shock requires treatment based on physiology and ongoing loss, not rigid reliance on a 7-g/dL threshold. Resuscitation and arranging bleeding control proceed together.
Reasoning steps for option A
For the choice "Continue resuscitation while arranging endoscopic hemostasis", which findings in this case must the choice account for?
Persistent hypotension after initial fluid; Overt upper GI blood loss; Hemoglobin above7; Endoscopy immediately available.
What specific finding, threshold, mechanism, or management rule makes "Continue resuscitation while arranging endoscopic hemostasis" fit or fail in this case?
Persistent shock requires treatment based on physiology and ongoing loss, not rigid reliance on a 7-g/dL threshold. Resuscitation and arranging bleeding control proceed together.
Which case-specific discriminator separates "Continue resuscitation while arranging endoscopic hemostasis" from the competing choices?
Recognize continued shock despite an initial resuscitation attempt. Then, Apply transfusion guidance in context rather than letting the measured hemoglobin delay blood or safe source control.
B. Proceed to sedated endoscopy before further circulatory resuscitation (Why this does not fit)
Endoscopic control is important, but sedation before addressing persistent shock increases risk; available endoscopy does not replace resuscitation.
Reasoning steps for option B
For the choice "Proceed to sedated endoscopy before further circulatory resuscitation", which findings in this case must the choice account for?
Persistent hypotension after initial fluid; Overt upper GI blood loss; Hemoglobin above7; Endoscopy immediately available.
What specific finding, threshold, mechanism, or management rule makes "Proceed to sedated endoscopy before further circulatory resuscitation" fit or fail in this case?
Endoscopic control is important, but sedation before addressing persistent shock increases risk; available endoscopy does not replace resuscitation.
Which case-specific discriminator separates "Proceed to sedated endoscopy before further circulatory resuscitation" from the competing choices?
Recognize continued shock despite an initial resuscitation attempt. Then, Apply transfusion guidance in context rather than letting the measured hemoglobin delay blood or safe source control.
C. Withhold transfusion until hemoglobin falls below 7 g/dL (Why this does not fit)
The restrictive threshold guides many stabilized patients; it is not a reason to defer needed blood in ongoing hemodynamic compromise.
Reasoning steps for option C
For the choice "Withhold transfusion until hemoglobin falls below 7 g/dL", which findings in this case must the choice account for?
Persistent hypotension after initial fluid; Overt upper GI blood loss; Hemoglobin above7; Endoscopy immediately available.
What specific finding, threshold, mechanism, or management rule makes "Withhold transfusion until hemoglobin falls below 7 g/dL" fit or fail in this case?
The restrictive threshold guides many stabilized patients; it is not a reason to defer needed blood in ongoing hemodynamic compromise.
Which case-specific discriminator separates "Withhold transfusion until hemoglobin falls below 7 g/dL" from the competing choices?
Recognize continued shock despite an initial resuscitation attempt. Then, Apply transfusion guidance in context rather than letting the measured hemoglobin delay blood or safe source control.
D. Give high-dose IV PPI and reassess hemodynamics after six hours (Why this does not fit)
PPI may be part of ulcer care but cannot replace timely resuscitation and bleeding control in a patient with ongoing shock.
Reasoning steps for option D
For the choice "Give high-dose IV PPI and reassess hemodynamics after six hours", which findings in this case must the choice account for?
Persistent hypotension after initial fluid; Overt upper GI blood loss; Hemoglobin above7; Endoscopy immediately available.
What specific finding, threshold, mechanism, or management rule makes "Give high-dose IV PPI and reassess hemodynamics after six hours" fit or fail in this case?
PPI may be part of ulcer care but cannot replace timely resuscitation and bleeding control in a patient with ongoing shock.
Which case-specific discriminator separates "Give high-dose IV PPI and reassess hemodynamics after six hours" from the competing choices?
Recognize continued shock despite an initial resuscitation attempt. Then, Apply transfusion guidance in context rather than letting the measured hemoglobin delay blood or safe source control.
Takeaway: Persistent shock requires treatment based on physiology and ongoing loss, not rigid reliance on a 7-g/dL threshold. Resuscitation and arranging bleeding control proceed together. [5]
A. Repeat endoscopic treatment; retain standard once-daily oral PPI (Why this does not fit)
Repeat endoscopy is generally the first intervention for recurrent bleeding, but high-dose PPI is recommended during the first three days after successful hemostasis.
Reasoning steps for option A
For the choice "Repeat endoscopic treatment; retain standard once-daily oral PPI", which findings in this case must the choice account for?
Initially successful endoscopic hemostasis; Recurrent hematemesis and hemoglobin decline after twelve hours; Restabilized patient; Only standard once-daily PPI prescribed.
What specific finding, threshold, mechanism, or management rule makes "Repeat endoscopic treatment; retain standard once-daily oral PPI" fit or fail in this case?
Repeat endoscopy is generally the first intervention for recurrent bleeding, but high-dose PPI is recommended during the first three days after successful hemostasis.
Which case-specific discriminator separates "Repeat endoscopic treatment; retain standard once-daily oral PPI" from the competing choices?
Distinguish recurrent bleeding after initial success from failure of all endoscopic control. Then, Select repeat endoscopic treatment and correct early post-hemostasis PPI intensity.
B. Proceed directly to embolization; use high-dose PPI therapy (Why this does not fit)
The acid-suppression intensity is appropriate, but recurrent bleeding after initial success generally warrants repeat endoscopic treatment before embolization for endoscopic failure.
Reasoning steps for option B
For the choice "Proceed directly to embolization; use high-dose PPI therapy", which findings in this case must the choice account for?
Initially successful endoscopic hemostasis; Recurrent hematemesis and hemoglobin decline after twelve hours; Restabilized patient; Only standard once-daily PPI prescribed.
What specific finding, threshold, mechanism, or management rule makes "Proceed directly to embolization; use high-dose PPI therapy" fit or fail in this case?
The acid-suppression intensity is appropriate, but recurrent bleeding after initial success generally warrants repeat endoscopic treatment before embolization for endoscopic failure.
Which case-specific discriminator separates "Proceed directly to embolization; use high-dose PPI therapy" from the competing choices?
Distinguish recurrent bleeding after initial success from failure of all endoscopic control. Then, Select repeat endoscopic treatment and correct early post-hemostasis PPI intensity.
C. Proceed directly to embolization; retain standard once-daily oral PPI (Why this does not fit)
This bypasses a recommended repeat endoscopic attempt and retains insufficient post-hemostasis acid-suppression intensity.
Reasoning steps for option C
For the choice "Proceed directly to embolization; retain standard once-daily oral PPI", which findings in this case must the choice account for?
Initially successful endoscopic hemostasis; Recurrent hematemesis and hemoglobin decline after twelve hours; Restabilized patient; Only standard once-daily PPI prescribed.
What specific finding, threshold, mechanism, or management rule makes "Proceed directly to embolization; retain standard once-daily oral PPI" fit or fail in this case?
This bypasses a recommended repeat endoscopic attempt and retains insufficient post-hemostasis acid-suppression intensity.
Which case-specific discriminator separates "Proceed directly to embolization; retain standard once-daily oral PPI" from the competing choices?
Distinguish recurrent bleeding after initial success from failure of all endoscopic control. Then, Select repeat endoscopic treatment and correct early post-hemostasis PPI intensity.
D. Repeat endoscopic treatment; use high-dose PPI therapy (Best answer)
Recurrent bleeding after initial endoscopic success generally prompts repeat endoscopy. The early post-hemostasis period also warrants high-dose rather than standard once-daily PPI.
Reasoning steps for option D
For the choice "Repeat endoscopic treatment; use high-dose PPI therapy", which findings in this case must the choice account for?
Initially successful endoscopic hemostasis; Recurrent hematemesis and hemoglobin decline after twelve hours; Restabilized patient; Only standard once-daily PPI prescribed.
What specific finding, threshold, mechanism, or management rule makes "Repeat endoscopic treatment; use high-dose PPI therapy" fit or fail in this case?
Recurrent bleeding after initial endoscopic success generally prompts repeat endoscopy. The early post-hemostasis period also warrants high-dose rather than standard once-daily PPI.
Which case-specific discriminator separates "Repeat endoscopic treatment; use high-dose PPI therapy" from the competing choices?
Distinguish recurrent bleeding after initial success from failure of all endoscopic control. Then, Select repeat endoscopic treatment and correct early post-hemostasis PPI intensity.
Takeaway: Recurrent bleeding after initial endoscopic success generally prompts repeat endoscopy. The early post-hemostasis period also warrants high-dose rather than standard once-daily PPI. [5]
A. Inject epinephrine into both ulcers as sole therapy (Why this does not fit)
A clean base does not require hemostasis, and epinephrine alone is not adequate definitive treatment of a high-risk vessel.
Reasoning steps for option A
For the choice "Inject epinephrine into both ulcers as sole therapy", which findings in this case must the choice account for?
One clean-base ulcer; One nonbleeding visible vessel; No current spurting; Hemodynamic stabilization.
What specific finding, threshold, mechanism, or management rule makes "Inject epinephrine into both ulcers as sole therapy" fit or fail in this case?
A clean base does not require hemostasis, and epinephrine alone is not adequate definitive treatment of a high-risk vessel.
Which case-specific discriminator separates "Inject epinephrine into both ulcers as sole therapy" from the competing choices?
Classify the two lesions by rebleeding risk. Then, Treat the high-risk stigma even without active bleeding while avoiding unnecessary therapy of the low-risk lesion.
B. Definitive hemostasis of the visible vessel alone (Best answer)
Risk is determined by the stigma, not simply by bleeding at that instant. A visible vessel merits therapy whereas a clean base does not.
Reasoning steps for option B
For the choice "Definitive hemostasis of the visible vessel alone", which findings in this case must the choice account for?
One clean-base ulcer; One nonbleeding visible vessel; No current spurting; Hemodynamic stabilization.
What specific finding, threshold, mechanism, or management rule makes "Definitive hemostasis of the visible vessel alone" fit or fail in this case?
Risk is determined by the stigma, not simply by bleeding at that instant. A visible vessel merits therapy whereas a clean base does not.
Which case-specific discriminator separates "Definitive hemostasis of the visible vessel alone" from the competing choices?
Classify the two lesions by rebleeding risk. Then, Treat the high-risk stigma even without active bleeding while avoiding unnecessary therapy of the low-risk lesion.
C. Observe both ulcers with PPI and no endoscopic treatment (Why this does not fit)
A nonbleeding visible vessel still carries sufficient rebleeding risk to warrant endoscopic treatment despite current hemodynamic stability.
Reasoning steps for option C
For the choice "Observe both ulcers with PPI and no endoscopic treatment", which findings in this case must the choice account for?
One clean-base ulcer; One nonbleeding visible vessel; No current spurting; Hemodynamic stabilization.
What specific finding, threshold, mechanism, or management rule makes "Observe both ulcers with PPI and no endoscopic treatment" fit or fail in this case?
A nonbleeding visible vessel still carries sufficient rebleeding risk to warrant endoscopic treatment despite current hemodynamic stability.
Which case-specific discriminator separates "Observe both ulcers with PPI and no endoscopic treatment" from the competing choices?
Classify the two lesions by rebleeding risk. Then, Treat the high-risk stigma even without active bleeding while avoiding unnecessary therapy of the low-risk lesion.
D. Definitive hemostasis of both visible ulcer bases (Why this does not fit)
Treating the vessel is appropriate, but prophylactic clipping of an uncomplicated clean base adds no established benefit.
Reasoning steps for option D
For the choice "Definitive hemostasis of both visible ulcer bases", which findings in this case must the choice account for?
One clean-base ulcer; One nonbleeding visible vessel; No current spurting; Hemodynamic stabilization.
What specific finding, threshold, mechanism, or management rule makes "Definitive hemostasis of both visible ulcer bases" fit or fail in this case?
Treating the vessel is appropriate, but prophylactic clipping of an uncomplicated clean base adds no established benefit.
Which case-specific discriminator separates "Definitive hemostasis of both visible ulcer bases" from the competing choices?
Classify the two lesions by rebleeding risk. Then, Treat the high-risk stigma even without active bleeding while avoiding unnecessary therapy of the low-risk lesion.
Takeaway: Risk is determined by the stigma, not simply by bleeding at that instant. A visible vessel merits therapy whereas a clean base does not. [5]
A. Nonoperative observation with continued bowel rest (Why this does not fit)
Absence of contrast leakage alone does not qualify a patient for observation. Persistent circulatory compromise and diffuse peritonitis violate the conditions for selected nonoperative care.
Reasoning steps for option A
For the choice "Nonoperative observation with continued bowel rest", which findings in this case must the choice account for?
Duodenal defect with free air but no contrast extravasation; Diffuse peritonitis; Persistent hypotension and tachycardia despite initial fluid; Antibiotics and resuscitation already started.
What specific finding, threshold, mechanism, or management rule makes "Nonoperative observation with continued bowel rest" fit or fail in this case?
Absence of contrast leakage alone does not qualify a patient for observation. Persistent circulatory compromise and diffuse peritonitis violate the conditions for selected nonoperative care.
Which case-specific discriminator separates "Nonoperative observation with continued bowel rest" from the competing choices?
Distinguish absence of visible contrast leakage from proof that perforation can be managed nonoperatively. Then, Integrate shock and peritonitis to reject observation and arrange urgent surgical source control without waiting for complete stabilization.
B. Urgent surgical source control with resuscitation (Best answer)
The study may show no ongoing contrast escape, but this does not establish safe containment in a patient with shock and diffuse peritonitis. Surgical assessment and source control must proceed alongside resuscitation.
Reasoning steps for option B
For the choice "Urgent surgical source control with resuscitation", which findings in this case must the choice account for?
Duodenal defect with free air but no contrast extravasation; Diffuse peritonitis; Persistent hypotension and tachycardia despite initial fluid; Antibiotics and resuscitation already started.
What specific finding, threshold, mechanism, or management rule makes "Urgent surgical source control with resuscitation" fit or fail in this case?
The study may show no ongoing contrast escape, but this does not establish safe containment in a patient with shock and diffuse peritonitis. Surgical assessment and source control must proceed alongside resuscitation.
Which case-specific discriminator separates "Urgent surgical source control with resuscitation" from the competing choices?
Distinguish absence of visible contrast leakage from proof that perforation can be managed nonoperatively. Then, Integrate shock and peritonitis to reject observation and arrange urgent surgical source control without waiting for complete stabilization.
C. Repeat contrast imaging before deciding about surgery (Why this does not fit)
Repeating imaging to prove an active leak would delay needed source control. The existing free air plus peritonitis and instability already require urgent surgical management.
Reasoning steps for option C
For the choice "Repeat contrast imaging before deciding about surgery", which findings in this case must the choice account for?
Duodenal defect with free air but no contrast extravasation; Diffuse peritonitis; Persistent hypotension and tachycardia despite initial fluid; Antibiotics and resuscitation already started.
What specific finding, threshold, mechanism, or management rule makes "Repeat contrast imaging before deciding about surgery" fit or fail in this case?
Repeating imaging to prove an active leak would delay needed source control. The existing free air plus peritonitis and instability already require urgent surgical management.
Which case-specific discriminator separates "Repeat contrast imaging before deciding about surgery" from the competing choices?
Distinguish absence of visible contrast leakage from proof that perforation can be managed nonoperatively. Then, Integrate shock and peritonitis to reject observation and arrange urgent surgical source control without waiting for complete stabilization.
D. Endoscopic ulcer treatment after blood pressure normalizes (Why this does not fit)
Endoscopic ulcer treatment is not a substitute for surgical source control in this setting. Waiting for full blood-pressure normalization before arranging definitive care adds unsafe delay.
Reasoning steps for option D
For the choice "Endoscopic ulcer treatment after blood pressure normalizes", which findings in this case must the choice account for?
Duodenal defect with free air but no contrast extravasation; Diffuse peritonitis; Persistent hypotension and tachycardia despite initial fluid; Antibiotics and resuscitation already started.
What specific finding, threshold, mechanism, or management rule makes "Endoscopic ulcer treatment after blood pressure normalizes" fit or fail in this case?
Endoscopic ulcer treatment is not a substitute for surgical source control in this setting. Waiting for full blood-pressure normalization before arranging definitive care adds unsafe delay.
Which case-specific discriminator separates "Endoscopic ulcer treatment after blood pressure normalizes" from the competing choices?
Distinguish absence of visible contrast leakage from proof that perforation can be managed nonoperatively. Then, Integrate shock and peritonitis to reject observation and arrange urgent surgical source control without waiting for complete stabilization.
Takeaway: No contrast extravasation is only one consideration. Nonoperative perforation care also requires a stable patient without peritonitis or sepsis; shock and diffuse guarding demand urgent source-control planning. [6]
A. Acid output rises; prostaglandin protection returns to baseline (Why this does not fit)
PPI inhibits the final acid pump, and it does not reverse the NSAID effect on prostaglandin production.
Reasoning steps for option A
For the choice "Acid output rises; prostaglandin protection returns to baseline", which findings in this case must the choice account for?
NSAID ulcer despite ordinary initial acid output; Infection reliably excluded; PPI added while NSAID continues.
What specific finding, threshold, mechanism, or management rule makes "Acid output rises; prostaglandin protection returns to baseline" fit or fail in this case?
PPI inhibits the final acid pump, and it does not reverse the NSAID effect on prostaglandin production.
Which case-specific discriminator separates "Acid output rises; prostaglandin protection returns to baseline" from the competing choices?
Infer defense failure rather than required acid excess. Then, Predict pump suppression without assuming restoration of prostaglandin protection.
B. Acid output falls; prostaglandin protection returns to baseline (Why this does not fit)
The acid prediction fits PPI action, but continuing naproxen can maintain the mucosal-defense deficit.
Reasoning steps for option B
For the choice "Acid output falls; prostaglandin protection returns to baseline", which findings in this case must the choice account for?
NSAID ulcer despite ordinary initial acid output; Infection reliably excluded; PPI added while NSAID continues.
What specific finding, threshold, mechanism, or management rule makes "Acid output falls; prostaglandin protection returns to baseline" fit or fail in this case?
The acid prediction fits PPI action, but continuing naproxen can maintain the mucosal-defense deficit.
Which case-specific discriminator separates "Acid output falls; prostaglandin protection returns to baseline" from the competing choices?
Infer defense failure rather than required acid excess. Then, Predict pump suppression without assuming restoration of prostaglandin protection.
C. Acid output remains unchanged; prostaglandin protection falls further (Why this does not fit)
The ongoing NSAID exposure affects protection, but effective PPI therapy is expected to suppress acid rather than leave it unchanged.
Reasoning steps for option C
For the choice "Acid output remains unchanged; prostaglandin protection falls further", which findings in this case must the choice account for?
NSAID ulcer despite ordinary initial acid output; Infection reliably excluded; PPI added while NSAID continues.
What specific finding, threshold, mechanism, or management rule makes "Acid output remains unchanged; prostaglandin protection falls further" fit or fail in this case?
The ongoing NSAID exposure affects protection, but effective PPI therapy is expected to suppress acid rather than leave it unchanged.
Which case-specific discriminator separates "Acid output remains unchanged; prostaglandin protection falls further" from the competing choices?
Infer defense failure rather than required acid excess. Then, Predict pump suppression without assuming restoration of prostaglandin protection.
D. Acid output falls; prostaglandin protection remains impaired (Best answer)
Normal initial acid output does not exclude NSAID-related injury. PPI suppresses acid while the continued NSAID can sustain impaired protection.
Reasoning steps for option D
For the choice "Acid output falls; prostaglandin protection remains impaired", which findings in this case must the choice account for?
NSAID ulcer despite ordinary initial acid output; Infection reliably excluded; PPI added while NSAID continues.
What specific finding, threshold, mechanism, or management rule makes "Acid output falls; prostaglandin protection remains impaired" fit or fail in this case?
Normal initial acid output does not exclude NSAID-related injury. PPI suppresses acid while the continued NSAID can sustain impaired protection.
Which case-specific discriminator separates "Acid output falls; prostaglandin protection remains impaired" from the competing choices?
Infer defense failure rather than required acid excess. Then, Predict pump suppression without assuming restoration of prostaglandin protection.
Takeaway: Normal initial acid output does not exclude NSAID-related injury. PPI suppresses acid while the continued NSAID can sustain impaired protection. [7][8][9]
A. Acid-activated covalent inhibition of the final proton pump (Best answer)
A final-pump inhibitor suppresses secretion from different upstream inputs; covalent binding explains why inhibition can outlast brief plasma exposure.
Reasoning steps for option A
For the choice "Acid-activated covalent inhibition of the final proton pump", which findings in this case must the choice account for?
H2 blockade leaves cholinergic-stimulated secretion; Second drug suppresses both stimuli; Drug effect outlasts plasma exposure.
What specific finding, threshold, mechanism, or management rule makes "Acid-activated covalent inhibition of the final proton pump" fit or fail in this case?
A final-pump inhibitor suppresses secretion from different upstream inputs; covalent binding explains why inhibition can outlast brief plasma exposure.
Which case-specific discriminator separates "Acid-activated covalent inhibition of the final proton pump" from the competing choices?
Locate the second drug downstream of different receptor inputs. Then, Use persistent effect to distinguish covalent pump inhibition from transient neutralization or reversible receptor blockade.
B. Reversible competitive antagonism of the histamine H2 receptor (Why this does not fit)
This reduces a single stimulatory pathway and does not explain robust suppression of cholinergic stimulation plus the prolonged pump effect.
Reasoning steps for option B
For the choice "Reversible competitive antagonism of the histamine H2 receptor", which findings in this case must the choice account for?
H2 blockade leaves cholinergic-stimulated secretion; Second drug suppresses both stimuli; Drug effect outlasts plasma exposure.
What specific finding, threshold, mechanism, or management rule makes "Reversible competitive antagonism of the histamine H2 receptor" fit or fail in this case?
This reduces a single stimulatory pathway and does not explain robust suppression of cholinergic stimulation plus the prolonged pump effect.
Which case-specific discriminator separates "Reversible competitive antagonism of the histamine H2 receptor" from the competing choices?
Locate the second drug downstream of different receptor inputs. Then, Use persistent effect to distinguish covalent pump inhibition from transient neutralization or reversible receptor blockade.
C. Neutralization of secreted hydrogen ions within the gastric lumen (Why this does not fit)
Antacids reduce luminal acidity transiently rather than inhibiting the secretory apparatus across stimuli for a prolonged period.
Reasoning steps for option C
For the choice "Neutralization of secreted hydrogen ions within the gastric lumen", which findings in this case must the choice account for?
H2 blockade leaves cholinergic-stimulated secretion; Second drug suppresses both stimuli; Drug effect outlasts plasma exposure.
What specific finding, threshold, mechanism, or management rule makes "Neutralization of secreted hydrogen ions within the gastric lumen" fit or fail in this case?
Antacids reduce luminal acidity transiently rather than inhibiting the secretory apparatus across stimuli for a prolonged period.
Which case-specific discriminator separates "Neutralization of secreted hydrogen ions within the gastric lumen" from the competing choices?
Locate the second drug downstream of different receptor inputs. Then, Use persistent effect to distinguish covalent pump inhibition from transient neutralization or reversible receptor blockade.
D. Reversible competitive antagonism of the acetylcholine M3 receptor (Why this does not fit)
This blocks cholinergic signaling but does not account for direct histamine-stimulated secretion also being strongly suppressed.
Reasoning steps for option D
For the choice "Reversible competitive antagonism of the acetylcholine M3 receptor", which findings in this case must the choice account for?
H2 blockade leaves cholinergic-stimulated secretion; Second drug suppresses both stimuli; Drug effect outlasts plasma exposure.
What specific finding, threshold, mechanism, or management rule makes "Reversible competitive antagonism of the acetylcholine M3 receptor" fit or fail in this case?
This blocks cholinergic signaling but does not account for direct histamine-stimulated secretion also being strongly suppressed.
Which case-specific discriminator separates "Reversible competitive antagonism of the acetylcholine M3 receptor" from the competing choices?
Locate the second drug downstream of different receptor inputs. Then, Use persistent effect to distinguish covalent pump inhibition from transient neutralization or reversible receptor blockade.
Takeaway: A final-pump inhibitor suppresses secretion from different upstream inputs; covalent binding explains why inhibition can outlast brief plasma exposure. [7][8]
A. Lower somatostatin, lower gastrin and lower acid delivery (Why this does not fit)
Less somatostatin releases gastrin from inhibition rather than lowering it; preserved corpus glands can respond with more acid.
Reasoning steps for option A
For the choice "Lower somatostatin, lower gastrin and lower acid delivery", which findings in this case must the choice account for?
Antral-predominant infection; Preserved corpus glands; Duodenal ulcer; No NSAID exposure.
What specific finding, threshold, mechanism, or management rule makes "Lower somatostatin, lower gastrin and lower acid delivery" fit or fail in this case?
Less somatostatin releases gastrin from inhibition rather than lowering it; preserved corpus glands can respond with more acid.
Which case-specific discriminator separates "Lower somatostatin, lower gastrin and lower acid delivery" from the competing choices?
Locate the infection in the regulatory rather than atrophic acid-producing compartment. Then, Predict linked changes in inhibition, gastrin and duodenal acid exposure.
B. Higher somatostatin, lower gastrin and lower acid delivery (Why this does not fit)
This inhibitory pattern does not explain the high-acid tendency of antral-predominant infection with preserved acid-producing glands.
Reasoning steps for option B
For the choice "Higher somatostatin, lower gastrin and lower acid delivery", which findings in this case must the choice account for?
Antral-predominant infection; Preserved corpus glands; Duodenal ulcer; No NSAID exposure.
What specific finding, threshold, mechanism, or management rule makes "Higher somatostatin, lower gastrin and lower acid delivery" fit or fail in this case?
This inhibitory pattern does not explain the high-acid tendency of antral-predominant infection with preserved acid-producing glands.
Which case-specific discriminator separates "Higher somatostatin, lower gastrin and lower acid delivery" from the competing choices?
Locate the infection in the regulatory rather than atrophic acid-producing compartment. Then, Predict linked changes in inhibition, gastrin and duodenal acid exposure.
C. Lower somatostatin, higher gastrin and higher acid delivery (Best answer)
Antral inflammation can reduce D-cell restraint; increased gastrin then stimulates preserved acid-producing tissue and increases duodenal acid exposure.
Reasoning steps for option C
For the choice "Lower somatostatin, higher gastrin and higher acid delivery", which findings in this case must the choice account for?
Antral-predominant infection; Preserved corpus glands; Duodenal ulcer; No NSAID exposure.
What specific finding, threshold, mechanism, or management rule makes "Lower somatostatin, higher gastrin and higher acid delivery" fit or fail in this case?
Antral inflammation can reduce D-cell restraint; increased gastrin then stimulates preserved acid-producing tissue and increases duodenal acid exposure.
Which case-specific discriminator separates "Lower somatostatin, higher gastrin and higher acid delivery" from the competing choices?
Locate the infection in the regulatory rather than atrophic acid-producing compartment. Then, Predict linked changes in inhibition, gastrin and duodenal acid exposure.
D. Higher somatostatin, higher gastrin and higher acid delivery (Why this does not fit)
Increased gastrin and acid are plausible, but increased somatostatin is inconsistent with the loss of antral inhibition described by this pattern.
Reasoning steps for option D
For the choice "Higher somatostatin, higher gastrin and higher acid delivery", which findings in this case must the choice account for?
Antral-predominant infection; Preserved corpus glands; Duodenal ulcer; No NSAID exposure.
What specific finding, threshold, mechanism, or management rule makes "Higher somatostatin, higher gastrin and higher acid delivery" fit or fail in this case?
Increased gastrin and acid are plausible, but increased somatostatin is inconsistent with the loss of antral inhibition described by this pattern.
Which case-specific discriminator separates "Higher somatostatin, higher gastrin and higher acid delivery" from the competing choices?
Locate the infection in the regulatory rather than atrophic acid-producing compartment. Then, Predict linked changes in inhibition, gastrin and duodenal acid exposure.
Takeaway: Antral inflammation can reduce D-cell restraint; increased gastrin then stimulates preserved acid-producing tissue and increases duodenal acid exposure. [7]
A. Isolated antral D-cell loss; fasting gastrin is expected to rise (Why this does not fit)
D-cell loss could raise gastrin, but it would tend to stimulate preserved corpus acid production rather than explain extensive corpus gland loss with low acid output.
Reasoning steps for option A
For the choice "Isolated antral D-cell loss; fasting gastrin is expected to rise", which findings in this case must the choice account for?
Extensive corpus gland loss; Preserved antral endocrine cells; Low acid output without PPI confounding; Acid-somatostatin-gastrin feedback supplied.
What specific finding, threshold, mechanism, or management rule makes "Isolated antral D-cell loss; fasting gastrin is expected to rise" fit or fail in this case?
D-cell loss could raise gastrin, but it would tend to stimulate preserved corpus acid production rather than explain extensive corpus gland loss with low acid output.
Which case-specific discriminator separates "Isolated antral D-cell loss; fasting gastrin is expected to rise" from the competing choices?
Localize the primary deficit to acid-producing tissue rather than isolated antral inhibition. Then, Predict increased gastrin from reduced acid-mediated negative feedback.
B. Loss of corpus parietal cells; fasting gastrin is expected to fall (Why this does not fit)
Parietal-cell loss explains low acid, but less acid-mediated antral inhibition tends to raise gastrin when antral endocrine cells remain intact.
Reasoning steps for option B
For the choice "Loss of corpus parietal cells; fasting gastrin is expected to fall", which findings in this case must the choice account for?
Extensive corpus gland loss; Preserved antral endocrine cells; Low acid output without PPI confounding; Acid-somatostatin-gastrin feedback supplied.
What specific finding, threshold, mechanism, or management rule makes "Loss of corpus parietal cells; fasting gastrin is expected to fall" fit or fail in this case?
Parietal-cell loss explains low acid, but less acid-mediated antral inhibition tends to raise gastrin when antral endocrine cells remain intact.
Which case-specific discriminator separates "Loss of corpus parietal cells; fasting gastrin is expected to fall" from the competing choices?
Localize the primary deficit to acid-producing tissue rather than isolated antral inhibition. Then, Predict increased gastrin from reduced acid-mediated negative feedback.
C. Isolated antral D-cell loss; fasting gastrin is expected to fall (Why this does not fit)
Loss of inhibitory D-cell activity would not lower gastrin and does not explain the corpus pathology.
Reasoning steps for option C
For the choice "Isolated antral D-cell loss; fasting gastrin is expected to fall", which findings in this case must the choice account for?
Extensive corpus gland loss; Preserved antral endocrine cells; Low acid output without PPI confounding; Acid-somatostatin-gastrin feedback supplied.
What specific finding, threshold, mechanism, or management rule makes "Isolated antral D-cell loss; fasting gastrin is expected to fall" fit or fail in this case?
Loss of inhibitory D-cell activity would not lower gastrin and does not explain the corpus pathology.
Which case-specific discriminator separates "Isolated antral D-cell loss; fasting gastrin is expected to fall" from the competing choices?
Localize the primary deficit to acid-producing tissue rather than isolated antral inhibition. Then, Predict increased gastrin from reduced acid-mediated negative feedback.
D. Loss of corpus parietal cells; fasting gastrin is expected to rise (Best answer)
Loss of acid-producing tissue explains hyposecretion. Reduced acid-mediated inhibitory feedback allows gastrin to rise despite the stomach being unable to restore normal acid production.
Reasoning steps for option D
For the choice "Loss of corpus parietal cells; fasting gastrin is expected to rise", which findings in this case must the choice account for?
Extensive corpus gland loss; Preserved antral endocrine cells; Low acid output without PPI confounding; Acid-somatostatin-gastrin feedback supplied.
What specific finding, threshold, mechanism, or management rule makes "Loss of corpus parietal cells; fasting gastrin is expected to rise" fit or fail in this case?
Loss of acid-producing tissue explains hyposecretion. Reduced acid-mediated inhibitory feedback allows gastrin to rise despite the stomach being unable to restore normal acid production.
Which case-specific discriminator separates "Loss of corpus parietal cells; fasting gastrin is expected to rise" from the competing choices?
Localize the primary deficit to acid-producing tissue rather than isolated antral inhibition. Then, Predict increased gastrin from reduced acid-mediated negative feedback.
Takeaway: Loss of acid-producing tissue explains hyposecretion. Reduced acid-mediated inhibitory feedback allows gastrin to rise despite the stomach being unable to restore normal acid production. [7]
A. Begin metoclopramide and schedule gastric emptying scintigraphy (Why this does not fit)
Delayed emptying could cause retained food, but a mechanical outlet lesion must be excluded before assuming gastroparesis or choosing a prokinetic-centered plan.
Reasoning steps for option A
For the choice "Begin metoclopramide and schedule gastric emptying scintigraphy", which findings in this case must the choice account for?
What specific finding, threshold, mechanism, or management rule makes "Begin metoclopramide and schedule gastric emptying scintigraphy" fit or fail in this case?
Delayed emptying could cause retained food, but a mechanical outlet lesion must be excluded before assuming gastroparesis or choosing a prokinetic-centered plan.
Which case-specific discriminator separates "Begin metoclopramide and schedule gastric emptying scintigraphy" from the competing choices?
Distinguish outlet obstruction from uncomplicated regurgitation. Then, Link vomiting to volume/electrolyte losses and prioritize stabilization plus structural evaluation.
B. IV fluids/electrolytes, decompression and structural evaluation (Best answer)
Retained food and a pyloric-ulcer history suggest obstruction; vomiting explains chloride and potassium depletion with alkalosis. Stabilization and structural evaluation are priorities.
Reasoning steps for option B
For the choice "IV fluids/electrolytes, decompression and structural evaluation", which findings in this case must the choice account for?
What specific finding, threshold, mechanism, or management rule makes "IV fluids/electrolytes, decompression and structural evaluation" fit or fail in this case?
Retained food and a pyloric-ulcer history suggest obstruction; vomiting explains chloride and potassium depletion with alkalosis. Stabilization and structural evaluation are priorities.
Which case-specific discriminator separates "IV fluids/electrolytes, decompression and structural evaluation" from the competing choices?
Distinguish outlet obstruction from uncomplicated regurgitation. Then, Link vomiting to volume/electrolyte losses and prioritize stabilization plus structural evaluation.
C. Start oral eradication therapy and reassess vomiting after two weeks (Why this does not fit)
Infection treatment may address a contributor but cannot substitute for correcting major deficits and evaluating obstruction; oral medication tolerance is also uncertain.
Reasoning steps for option C
For the choice "Start oral eradication therapy and reassess vomiting after two weeks", which findings in this case must the choice account for?
What specific finding, threshold, mechanism, or management rule makes "Start oral eradication therapy and reassess vomiting after two weeks" fit or fail in this case?
Infection treatment may address a contributor but cannot substitute for correcting major deficits and evaluating obstruction; oral medication tolerance is also uncertain.
Which case-specific discriminator separates "Start oral eradication therapy and reassess vomiting after two weeks" from the competing choices?
Distinguish outlet obstruction from uncomplicated regurgitation. Then, Link vomiting to volume/electrolyte losses and prioritize stabilization plus structural evaluation.
D. Increase oral PPI and monitor electrolytes at outpatient follow-up (Why this does not fit)
Acid suppression may contribute to treatment, but significant dehydration and electrolyte abnormalities make delayed outpatient reassessment unsafe.
Reasoning steps for option D
For the choice "Increase oral PPI and monitor electrolytes at outpatient follow-up", which findings in this case must the choice account for?
What specific finding, threshold, mechanism, or management rule makes "Increase oral PPI and monitor electrolytes at outpatient follow-up" fit or fail in this case?
Acid suppression may contribute to treatment, but significant dehydration and electrolyte abnormalities make delayed outpatient reassessment unsafe.
Which case-specific discriminator separates "Increase oral PPI and monitor electrolytes at outpatient follow-up" from the competing choices?
Distinguish outlet obstruction from uncomplicated regurgitation. Then, Link vomiting to volume/electrolyte losses and prioritize stabilization plus structural evaluation.
Takeaway: Retained food and a pyloric-ulcer history suggest obstruction; vomiting explains chloride and potassium depletion with alkalosis. Stabilization and structural evaluation are priorities. [10]
A. Begin a therapeutic PPI trial for persistent dyspepsia (Best answer)
The active test was prepared and timed appropriately, supporting eradication. Persistent low-risk dyspepsia after eradication warrants a PPI trial rather than assuming infection persists.
Reasoning steps for option A
For the choice "Begin a therapeutic PPI trial for persistent dyspepsia", which findings in this case must the choice account for?
Persistent dyspepsia without alarm or gastric cancer risk features; Negative stool antigen six weeks after antibiotics and bismuth and three weeks off PPI; No adequate PPI trial outside eradication therapy.
What specific finding, threshold, mechanism, or management rule makes "Begin a therapeutic PPI trial for persistent dyspepsia" fit or fail in this case?
The active test was prepared and timed appropriately, supporting eradication. Persistent low-risk dyspepsia after eradication warrants a PPI trial rather than assuming infection persists.
Which case-specific discriminator separates "Begin a therapeutic PPI trial for persistent dyspepsia" from the competing choices?
Accept the appropriately prepared negative active test rather than diagnosing persistence from symptoms. Then, Advance the low-risk dyspepsia pathway to a PPI trial before retreatment, routine endoscopy or later-line prokinetics.
B. Repeat the eradication regimen for persistent infection (Why this does not fit)
Symptoms do not establish treatment failure. The appropriately prepared negative active test gives no basis for an automatic second eradication course.
Reasoning steps for option B
For the choice "Repeat the eradication regimen for persistent infection", which findings in this case must the choice account for?
Persistent dyspepsia without alarm or gastric cancer risk features; Negative stool antigen six weeks after antibiotics and bismuth and three weeks off PPI; No adequate PPI trial outside eradication therapy.
What specific finding, threshold, mechanism, or management rule makes "Repeat the eradication regimen for persistent infection" fit or fail in this case?
Symptoms do not establish treatment failure. The appropriately prepared negative active test gives no basis for an automatic second eradication course.
Which case-specific discriminator separates "Repeat the eradication regimen for persistent infection" from the competing choices?
Accept the appropriately prepared negative active test rather than diagnosing persistence from symptoms. Then, Advance the low-risk dyspepsia pathway to a PPI trial before retreatment, routine endoscopy or later-line prokinetics.
C. Arrange upper endoscopy before trying symptom treatment (Why this does not fit)
Endoscopy becomes important with age-related or individualized risk or other indications. This younger patient has neither alarm features nor elevated gastric cancer risk and has not tried the recommended next medical step.
Reasoning steps for option C
For the choice "Arrange upper endoscopy before trying symptom treatment", which findings in this case must the choice account for?
Persistent dyspepsia without alarm or gastric cancer risk features; Negative stool antigen six weeks after antibiotics and bismuth and three weeks off PPI; No adequate PPI trial outside eradication therapy.
What specific finding, threshold, mechanism, or management rule makes "Arrange upper endoscopy before trying symptom treatment" fit or fail in this case?
Endoscopy becomes important with age-related or individualized risk or other indications. This younger patient has neither alarm features nor elevated gastric cancer risk and has not tried the recommended next medical step.
Which case-specific discriminator separates "Arrange upper endoscopy before trying symptom treatment" from the competing choices?
Accept the appropriately prepared negative active test rather than diagnosing persistence from symptoms. Then, Advance the low-risk dyspepsia pathway to a PPI trial before retreatment, routine endoscopy or later-line prokinetics.
D. Begin a prokinetic before trying further acid suppression (Why this does not fit)
Prokinetic treatment can be considered later in the dyspepsia pathway, but it should not displace the initial PPI trial after infection has been addressed.
Reasoning steps for option D
For the choice "Begin a prokinetic before trying further acid suppression", which findings in this case must the choice account for?
Persistent dyspepsia without alarm or gastric cancer risk features; Negative stool antigen six weeks after antibiotics and bismuth and three weeks off PPI; No adequate PPI trial outside eradication therapy.
What specific finding, threshold, mechanism, or management rule makes "Begin a prokinetic before trying further acid suppression" fit or fail in this case?
Prokinetic treatment can be considered later in the dyspepsia pathway, but it should not displace the initial PPI trial after infection has been addressed.
Which case-specific discriminator separates "Begin a prokinetic before trying further acid suppression" from the competing choices?
Accept the appropriately prepared negative active test rather than diagnosing persistence from symptoms. Then, Advance the low-risk dyspepsia pathway to a PPI trial before retreatment, routine endoscopy or later-line prokinetics.
Takeaway: Validate the eradication test before treating ongoing symptoms as infection. In a younger low-risk patient with persistent dyspepsia after cure, the next medical step is a PPI trial. [2][3][4][12]
A. Excess acid exposure with positive reflux-symptom association (Why this does not fit)
The symptom index is positive, but 1.8% lies within the supplied physiologic exposure range; symptom association does not itself establish excess exposure.
Reasoning steps for option A
For the choice "Excess acid exposure with positive reflux-symptom association", which findings in this case must the choice account for?
Off-PPI acid exposure of1.8% with normal defined below4%; Seven of ten symptom episodes associated with reflux; Positive symptom-index threshold of50%; Normal structural and motility evaluation.
What specific finding, threshold, mechanism, or management rule makes "Excess acid exposure with positive reflux-symptom association" fit or fail in this case?
The symptom index is positive, but 1.8% lies within the supplied physiologic exposure range; symptom association does not itself establish excess exposure.
Which case-specific discriminator separates "Excess acid exposure with positive reflux-symptom association" from the competing choices?
Compare measured acid burden with the reference limit. Then, Calculate symptom association independently and distinguish physiologic exposure with hypersensitivity from excess exposure.
B. Physiologic acid exposure with negative reflux-symptom association (Why this does not fit)
The acid burden is physiologic, but 7/10 yields 70%, above the supplied positive symptom-index threshold.
Reasoning steps for option B
For the choice "Physiologic acid exposure with negative reflux-symptom association", which findings in this case must the choice account for?
Off-PPI acid exposure of1.8% with normal defined below4%; Seven of ten symptom episodes associated with reflux; Positive symptom-index threshold of50%; Normal structural and motility evaluation.
What specific finding, threshold, mechanism, or management rule makes "Physiologic acid exposure with negative reflux-symptom association" fit or fail in this case?
The acid burden is physiologic, but 7/10 yields 70%, above the supplied positive symptom-index threshold.
Which case-specific discriminator separates "Physiologic acid exposure with negative reflux-symptom association" from the competing choices?
Compare measured acid burden with the reference limit. Then, Calculate symptom association independently and distinguish physiologic exposure with hypersensitivity from excess exposure.
C. Physiologic acid exposure with positive reflux-symptom association (Best answer)
Acid exposure is below 4%, while 7/10 symptoms gives a 70% index. This supports a reflux-hypersensitivity pattern rather than excess acid exposure or absent symptom association.
Reasoning steps for option C
For the choice "Physiologic acid exposure with positive reflux-symptom association", which findings in this case must the choice account for?
Off-PPI acid exposure of1.8% with normal defined below4%; Seven of ten symptom episodes associated with reflux; Positive symptom-index threshold of50%; Normal structural and motility evaluation.
What specific finding, threshold, mechanism, or management rule makes "Physiologic acid exposure with positive reflux-symptom association" fit or fail in this case?
Acid exposure is below 4%, while 7/10 symptoms gives a 70% index. This supports a reflux-hypersensitivity pattern rather than excess acid exposure or absent symptom association.
Which case-specific discriminator separates "Physiologic acid exposure with positive reflux-symptom association" from the competing choices?
Compare measured acid burden with the reference limit. Then, Calculate symptom association independently and distinguish physiologic exposure with hypersensitivity from excess exposure.
D. Excess acid exposure with negative reflux-symptom association (Why this does not fit)
Both components misinterpret the results: exposure is physiologic and the symptom index is positive.
Reasoning steps for option D
For the choice "Excess acid exposure with negative reflux-symptom association", which findings in this case must the choice account for?
Off-PPI acid exposure of1.8% with normal defined below4%; Seven of ten symptom episodes associated with reflux; Positive symptom-index threshold of50%; Normal structural and motility evaluation.
What specific finding, threshold, mechanism, or management rule makes "Excess acid exposure with negative reflux-symptom association" fit or fail in this case?
Both components misinterpret the results: exposure is physiologic and the symptom index is positive.
Which case-specific discriminator separates "Excess acid exposure with negative reflux-symptom association" from the competing choices?
Compare measured acid burden with the reference limit. Then, Calculate symptom association independently and distinguish physiologic exposure with hypersensitivity from excess exposure.
Takeaway: Acid exposure is below 4%, while 7/10 symptoms gives a 70% index. This supports a reflux-hypersensitivity pattern rather than excess acid exposure or absent symptom association. [1]
A. GBS 1; continue hospital care for hydration (Best answer)
The supplied components total 1, within the very-low-risk bleeding group. Persistent inability to hydrate is an independent reason not to discharge solely on the bleeding score.
Reasoning steps for option A
For the choice "GBS 1; continue hospital care for hydration", which findings in this case must the choice account for?
Normal urea, hemoglobin, blood pressure and pulse by the supplied rubric; Melena contributes one point; other positive GBS features absent; Persistent vomiting and IV hydration requirement.
What specific finding, threshold, mechanism, or management rule makes "GBS 1; continue hospital care for hydration" fit or fail in this case?
The supplied components total 1, within the very-low-risk bleeding group. Persistent inability to hydrate is an independent reason not to discharge solely on the bleeding score.
Which case-specific discriminator separates "GBS 1; continue hospital care for hydration" from the competing choices?
Calculate GBS1 rather than treat vomiting as a score component. Then, Separate predicted bleeding-intervention risk from overall suitability for discharge.
B. GBS 1; discharge based on bleeding risk (Why this does not fit)
The score is correctly categorized, but outpatient suitability also requires addressing ongoing vomiting and hydration needs.
Reasoning steps for option B
For the choice "GBS 1; discharge based on bleeding risk", which findings in this case must the choice account for?
Normal urea, hemoglobin, blood pressure and pulse by the supplied rubric; Melena contributes one point; other positive GBS features absent; Persistent vomiting and IV hydration requirement.
What specific finding, threshold, mechanism, or management rule makes "GBS 1; discharge based on bleeding risk" fit or fail in this case?
The score is correctly categorized, but outpatient suitability also requires addressing ongoing vomiting and hydration needs.
Which case-specific discriminator separates "GBS 1; discharge based on bleeding risk" from the competing choices?
Calculate GBS1 rather than treat vomiting as a score component. Then, Separate predicted bleeding-intervention risk from overall suitability for discharge.
C. GBS 3; continue hospital care for bleeding (Why this does not fit)
The supplied GBS components total 1. Vomiting is not a 2-point component. Continued hospital care is justified by hydration needs, not a falsely elevated bleeding score.
Reasoning steps for option C
For the choice "GBS 3; continue hospital care for bleeding", which findings in this case must the choice account for?
Normal urea, hemoglobin, blood pressure and pulse by the supplied rubric; Melena contributes one point; other positive GBS features absent; Persistent vomiting and IV hydration requirement.
What specific finding, threshold, mechanism, or management rule makes "GBS 3; continue hospital care for bleeding" fit or fail in this case?
The supplied GBS components total 1. Vomiting is not a 2-point component. Continued hospital care is justified by hydration needs, not a falsely elevated bleeding score.
Which case-specific discriminator separates "GBS 3; continue hospital care for bleeding" from the competing choices?
Calculate GBS1 rather than treat vomiting as a score component. Then, Separate predicted bleeding-intervention risk from overall suitability for discharge.
D. GBS 1; discharge after one fluid bolus (Why this does not fit)
The bleeding score is low, but a single bolus does not establish safe outpatient hydration while oral fluids remain intolerable. Disposition must address the continuing clinical need.
Reasoning steps for option D
For the choice "GBS 1; discharge after one fluid bolus", which findings in this case must the choice account for?
Normal urea, hemoglobin, blood pressure and pulse by the supplied rubric; Melena contributes one point; other positive GBS features absent; Persistent vomiting and IV hydration requirement.
What specific finding, threshold, mechanism, or management rule makes "GBS 1; discharge after one fluid bolus" fit or fail in this case?
The bleeding score is low, but a single bolus does not establish safe outpatient hydration while oral fluids remain intolerable. Disposition must address the continuing clinical need.
Which case-specific discriminator separates "GBS 1; discharge after one fluid bolus" from the competing choices?
Calculate GBS1 rather than treat vomiting as a score component. Then, Separate predicted bleeding-intervention risk from overall suitability for discharge.
Takeaway: The supplied components total 1, within the very-low-risk bleeding group. Persistent inability to hydrate is an independent reason not to discharge solely on the bleeding score. [5]
A. Repeat optimized bismuth quadruple therapy for 14 days (Why this does not fit)
Optimized quadruple therapy is preferred in some treatment-experienced patients who have not previously received it; this patient has a valid failure after that regimen.
Reasoning steps for option A
For the choice "Repeat optimized bismuth quadruple therapy for 14 days", which findings in this case must the choice account for?
Prior optimized BQT with good adherence; Positive active test six weeks after all antibiotics and bismuth and three weeks off PPI, with no resumption; No penicillin allergy and no susceptibility results.
What specific finding, threshold, mechanism, or management rule makes "Repeat optimized bismuth quadruple therapy for 14 days" fit or fail in this case?
Optimized quadruple therapy is preferred in some treatment-experienced patients who have not previously received it; this patient has a valid failure after that regimen.
Which case-specific discriminator separates "Repeat optimized bismuth quadruple therapy for 14 days" from the competing choices?
Validate the test timing and reject symptom response as cure. Then, Use prior optimized treatment and susceptibility constraints to choose an appropriate different regimen.
B. Use PPI-amoxicillin-clarithromycin triple therapy for 14 days (Why this does not fit)
Clarithromycin salvage should require documented susceptibility; past exposure and unknown susceptibility make blind selection inappropriate.
Reasoning steps for option B
For the choice "Use PPI-amoxicillin-clarithromycin triple therapy for 14 days", which findings in this case must the choice account for?
Prior optimized BQT with good adherence; Positive active test six weeks after all antibiotics and bismuth and three weeks off PPI, with no resumption; No penicillin allergy and no susceptibility results.
What specific finding, threshold, mechanism, or management rule makes "Use PPI-amoxicillin-clarithromycin triple therapy for 14 days" fit or fail in this case?
Clarithromycin salvage should require documented susceptibility; past exposure and unknown susceptibility make blind selection inappropriate.
Which case-specific discriminator separates "Use PPI-amoxicillin-clarithromycin triple therapy for 14 days" from the competing choices?
Validate the test timing and reject symptom response as cure. Then, Use prior optimized treatment and susceptibility constraints to choose an appropriate different regimen.
C. Use PPI-amoxicillin-levofloxacin triple therapy for 14 days (Why this does not fit)
Levofloxacin salvage likewise requires susceptibility support and is not the preferred empiric solution here.
Reasoning steps for option C
For the choice "Use PPI-amoxicillin-levofloxacin triple therapy for 14 days", which findings in this case must the choice account for?
Prior optimized BQT with good adherence; Positive active test six weeks after all antibiotics and bismuth and three weeks off PPI, with no resumption; No penicillin allergy and no susceptibility results.
What specific finding, threshold, mechanism, or management rule makes "Use PPI-amoxicillin-levofloxacin triple therapy for 14 days" fit or fail in this case?
Levofloxacin salvage likewise requires susceptibility support and is not the preferred empiric solution here.
Which case-specific discriminator separates "Use PPI-amoxicillin-levofloxacin triple therapy for 14 days" from the competing choices?
Validate the test timing and reject symptom response as cure. Then, Use prior optimized treatment and susceptibility constraints to choose an appropriate different regimen.
D. Use PPI-amoxicillin-rifabutin triple therapy for 14 days (Best answer)
The positive test meets both timing requirements and establishes persistence despite symptom relief. After prior optimized quadruple therapy, rifabutin triple therapy is an empiric alternative in a patient without penicillin allergy.
Reasoning steps for option D
For the choice "Use PPI-amoxicillin-rifabutin triple therapy for 14 days", which findings in this case must the choice account for?
Prior optimized BQT with good adherence; Positive active test six weeks after all antibiotics and bismuth and three weeks off PPI, with no resumption; No penicillin allergy and no susceptibility results.
What specific finding, threshold, mechanism, or management rule makes "Use PPI-amoxicillin-rifabutin triple therapy for 14 days" fit or fail in this case?
The positive test meets both timing requirements and establishes persistence despite symptom relief. After prior optimized quadruple therapy, rifabutin triple therapy is an empiric alternative in a patient without penicillin allergy.
Which case-specific discriminator separates "Use PPI-amoxicillin-rifabutin triple therapy for 14 days" from the competing choices?
Validate the test timing and reject symptom response as cure. Then, Use prior optimized treatment and susceptibility constraints to choose an appropriate different regimen.
Takeaway: The positive test meets both timing requirements and establishes persistence despite symptom relief. After prior optimized quadruple therapy, rifabutin triple therapy is an empiric alternative in a patient without penicillin allergy. [3][4]