Hirschsprung Disease: From Distal Aganglionosis to Clinical Decisions
Trace distal aganglionosis to bowel obstruction, interpret imaging and biopsy, recognize enterocolitis, and plan care before and after repair.
Why can the most visibly enlarged bowel be upstream from the primary defect? In Hirschsprung disease, a distal segment lacks enteric ganglion cells and cannot coordinate relaxation and propulsion normally. Trace that relationship and you can explain neonatal obstruction, choose a diagnostic specimen, recognize enterocolitis, and interpret persistent symptoms after repair.
The central task is to separate three questions: Is the child obstructed or systemically ill? Is distal bowel aganglionic? How far does the abnormal bowel extend? A radiograph, a pressure recording, and a biopsy answer different parts of that problem. The examples below are educational scenarios, not patient records.
Why is the narrow segment the problem?
A term newborn has progressive abdominal distention, bilious vomiting, and no meconium at 40 hours. A large proximal colon might attract your attention, but size does not locate the primary neuronal defect. Hirschsprung disease is a congenital absence of ganglion cells in the distal bowel's submucosal (Meissner) and myenteric (Auerbach) plexuses. Loss of coordinated enteric inhibition and propulsion creates a persistently contracted distal segment and functional obstruction. The bowel is not necessarily closed by a physical membrane. [1]
Enteric neural crest cells normally populate the gut predominantly in a proximal-to-distal direction, with the distal bowel populated last. Disturbed migration, proliferation, survival, or differentiation can leave that distal region without its normal enteric neurons. The familiar description of arrested migration is a useful starting point, not a complete explanation of every genetic form. [6]
Trace pressure, not just diameter
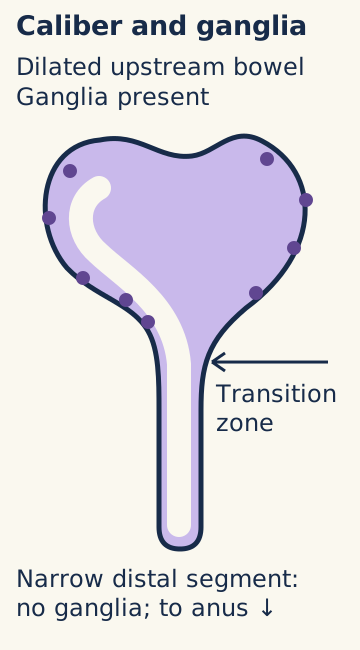
Use the bowel diagram to trace stool toward the anus. Identify where coordinated passage fails, then predict which side accumulates gas and stool. The distal aganglionic bowel remains relatively narrow; the upstream ganglionated bowel dilates and can become muscularly hypertrophied. Thus, megacolon describes a consequence rather than the location of missing ganglia.
Teaching purpose: locate the narrow aganglionic distal segment and the dilated, ganglionated proximal bowel across the transition zone. [1]
Now imagine temporary decompression. Passing gas and stool can reduce the proximal diameter without restoring a single enteric ganglion cell. An explosive discharge after a clinician's rectal examination supports distal obstruction in the right setting, but neither proves the diagnosis nor establishes a cure. The rectal vault may be relatively empty despite substantial upstream stool retention. This differs from the stool-filled rectum often found with functional fecal retention. [1][5]
Prediction: what changes after successful irrigation?
Distention and retained contents may decrease. The aganglionic segment remains abnormal, so recurrent obstruction is still possible without definitive treatment.
Apply the same reasoning to an older child with lifelong difficult stool passage and poor growth: a soft abdomen immediately after evacuation does not explain away a developmental obstruction. The history before decompression still matters.
How far does the abnormal bowel extend?
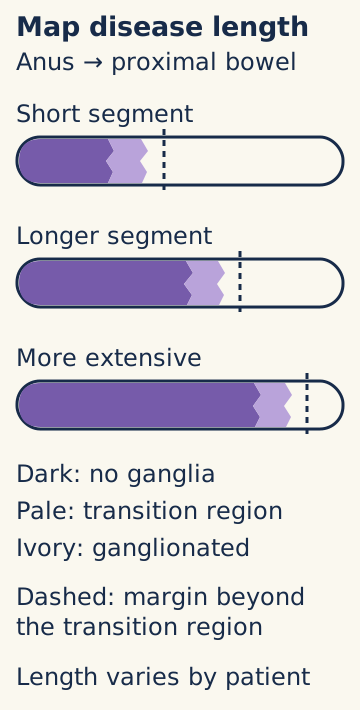
Does a narrow rectum mean that only the rectum is affected? In classical Hirschsprung disease, aganglionosis begins distally and extends proximally in a contiguous segment. Rectosigmoid disease is most common. Long-segment disease extends farther, and total-colonic aganglionosis is less common. The length changes planning and prognosis, not the fundamental requirement to demonstrate ganglion status. [1][5]
Teaching purpose: compare how far aganglionosis extends proximally from the rectum and see that a margin must lie above the transition region rather than at a single visual point. [1]
Consider three mapping samples described from distal to proximal: rectum without ganglia, sigmoid without ganglia, and descending colon containing ganglion cells. Mark the first sampled level with ganglia. Now ask whether that single finding identifies a safe final anastomotic margin. It does not: the intervening transition zone can have abnormal nerve distribution, and its proximal extent can be asymmetric around the circumference.
Map tissue before selecting a margin
The goal of pull-through surgery is to bring normally ganglionated bowel to the distal outlet while protecting the anal canal and continence structures. It is not simply to connect the first spot where one ganglion cell appears. Intraoperative mapping, assessment beyond the transition zone, and circumferential evaluation help prevent a transition-zone pull-through. The current ERNICA guideline describes transection at least 5-10 cm proximal to the first normal biopsy and the value of a circumferential specimen. These are specialist operative decisions, not distances to infer from an enema alone. [1]
Try a counterfactual: if another biopsy farther proximally is still abnormal, does the distal rectal diagnosis become less convincing? No. The disease extent is longer than initially estimated. Conversely, a proximal biopsy containing ganglia cannot substitute for an appropriately located diagnostic rectal biopsy.
A missing or misleading radiographic caliber change should prompt caution about localization, particularly in long-segment disease. A label such as ultrashort disease must not be assigned from constipation and an absent relaxation reflex alone. Histology, specimen location, and specialist interpretation are essential; pressure testing does not measure the length of aganglionosis. [1]
Mapping check: why sample around the circumference?
A single sample can miss asymmetric abnormal innervation. A normal-looking point is not proof that the whole proposed margin has normal plexuses.
Transfer this distinction to postoperative obstruction: an apparently successful operation does not exclude retained abnormal bowel. Reviewing original margin histology can be as important as looking for a mechanical narrowing.
What can the presentation and radiograph establish?
Should evaluation wait until 48 hours without meconium? No. Failure to pass meconium by 48 hours in a term infant is a strong warning, but the current guideline identifies delay beyond 24 hours within the characteristic triad of distention, delayed meconium, and bilious vomiting. An ill or biliously vomiting newborn needs prompt obstruction assessment, including consideration of other surgical emergencies such as malrotation with volvulus. A timing threshold is not permission to wait. [1]
Early meconium passage does not exclude Hirschsprung disease. Some infants present later with constipation, distention, feeding difficulty, or poor weight gain. In older children, constipation beginning very early in life and growth failure deserve more scrutiny than constipation arising during toilet training in an otherwise thriving child. Down syndrome or an affected relative lowers the threshold for biopsy when symptoms are suggestive. [1]
Compare narrow and wide regions
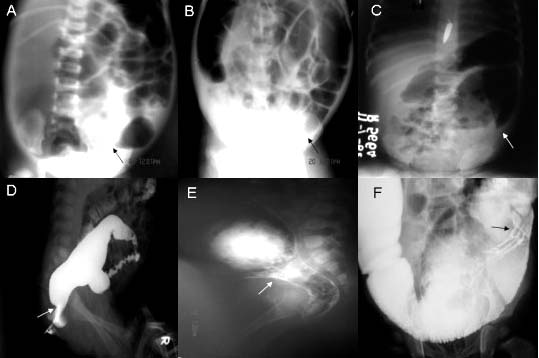
The clinical image contains six published radiographs: the upper row shows plain abdominal films, while the lower row shows contrast enemas. In the lower panels, follow the contrast-filled lumen from the rectum proximally and identify the change from a narrow distal region to a wider region. The original arrows indicate transition levels at the rectosigmoid, midsigmoid, and descending colon in the respective columns. These are real clinical examples, not three stages in one patient's progression. [3]
Teaching purpose: recognize a narrow-to-wide caliber change at three possible levels. A-C are plain radiographs and D-F are contrast enemas; arrows indicate rectosigmoid, midsigmoid, and descending colon, respectively. Imaging suggests a transition zone but does not confirm aganglionosis; rectal biopsy confirms it. Image: Akshay Pratap et al.; original source; CC BY 2.0. [1][3].
For a separate worked example, suppose the rectum measures 1.0 cm and the sigmoid 2.0 cm on an appropriately obtained study. The rectosigmoid ratio is 0.5, an inversion of the usual wider rectum. Combined with the clinical history, this supports distal functional obstruction. It does not directly show ganglion cells.
Predict what happens if the same symptomatic infant's enema has no clear transition zone. Suspicion should not collapse: very young infants may not yet have a marked diameter contrast, and more extensive disease may lack the usual rectosigmoid pattern. Imaging helps estimate anatomy and likely extent; representative rectal histology confirms the diagnosis. The small historical imaging series supplied the illustration, not a universal diagnostic accuracy estimate. [1][3]
Image check: which row can outline the lumen with contrast?
The lower row, panels D-F. The upper row, A-C, consists of plain radiographs. Neither row establishes the presence or absence of ganglion cells.
In a new patient with fever, marked distention, and lethargy, stop treating imaging as an elective localization exercise. Systemic illness changes the immediate priority to stabilization and evaluation for enterocolitis or perforation.
Which evidence can confirm aganglionosis?
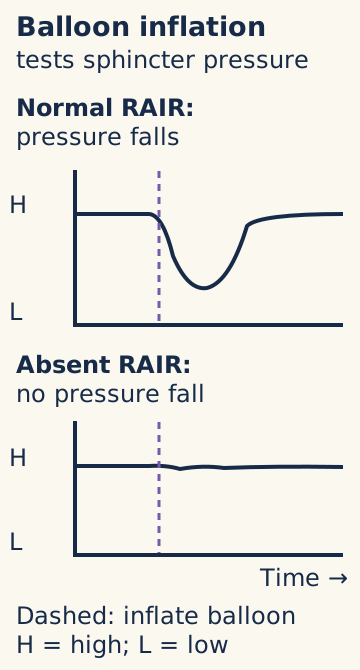
An infant has an absent rectoanal inhibitory reflex (RAIR). Does that finish the diagnostic workup? Rectal distention normally produces a transient reduction in internal anal sphincter pressure. In Hirschsprung disease that relaxation is absent. Trace the pressure diagram at the moment of balloon inflation: the informative feature is the pressure response, not simply a high resting pressure. Manometry supports suspicion but does not replace tissue diagnosis. [1]
Teaching purpose: distinguish a normal pressure fall following rectal inflation from absent reflex relaxation; manometry supports suspicion but biopsy confirms disease. [1]
Contrast enema, manometry, and biopsy are not a compulsory three-test staircase. Their order depends on the clinical situation and local expertise. A suggestive history can justify biopsy even when an enema is nondiagnostic or manometry is unavailable. Histologic confirmation is required before definitive pull-through surgery. [1]
Audit the sample before interpreting the result
Read a report: “No ganglion cells identified; mucosa only.” Decide whether this is positive or inadequate. The correct conclusion is inadequate for the usual diagnostic assessment because the specimen lacks representative submucosa. Rectal suction biopsy is useful because it can obtain mucosa and submucosa without a full-thickness operation; the myenteric plexus lies deeper between muscle layers. Open biopsy is another option when adequate tissue cannot be obtained by suction. [1]
Location matters too. Samples should be from the posterior or lateral rectal wall at least 2 cm above the dentate line, avoiding the physiologically sparse ganglion region immediately above the anus. A specimen that is too distal risks a misleading interpretation. The request and report should document the sampling level and adequacy. Multiple suction samples can improve the chance of obtaining representative tissue. [1]
On an adequate sample, absent ganglion cells together with the appropriate nerve pattern and ancillary stains supports Hirschsprung disease. Hypertrophic extrinsic nerves may be present. Acetylcholinesterase activity is often increased, whereas the normal calretinin-positive mucosal nerve pattern is absent. Small immature ganglion cells can be difficult to recognize, especially in premature infants. The 2026 update recommends H&E plus calretinin to improve diagnostic accuracy, with experienced pathology review rather than a diagnosis from one negative observation. A negative acetylcholinesterase result in a very young infant does not independently exclude disease. [1][5]
Specimen check: what if definite ganglion cells are present?
In a representative, correctly located rectal specimen, identified ganglion cells argue against classical Hirschsprung disease. Reconcile discordant pressure testing with specimen quality and other causes of outlet dysfunction, rather than overriding histology.
Apply this to a child whose pressure study suggests obstruction but whose pathology is uncertain: resolve adequacy and expert interpretation before assigning an irreversible surgical diagnosis.
What does an associated syndrome change?
Two children have severe constipation. One has biopsy-proven aganglionosis and sensorineural deafness with pigmentary differences. The other has oral mucosal neuromas, a tall slender habitus, and intestinal ganglioneuromatosis. Should they receive the same enteric diagnosis because both have neural developmental abnormalities?
Compare the tissue first. Hirschsprung disease is defined by absent ganglion cells. Waardenburg-Shah syndrome combines Hirschsprung disease with pigmentary and hearing findings. Congenital central hypoventilation can also coexist with Hirschsprung disease; unexplained sleep-related hypoventilation needs its own respiratory and genetic assessment, not attribution to abdominal distention. Down syndrome is another important association. These patterns guide broader assessment and syndrome-directed genetic consultation. [5]
RET is central to many familial and sporadic forms of Hirschsprung disease, but “a RET variant” is not a complete risk assessment. Many disease-associated variants impair enteric nervous system development. Penetrance and recurrence vary with the particular variant, family history, sex, and disease extent. Counseling should not assign one Mendelian recurrence percentage to every family or interpret a negative test as excluding histologically proven disease. [1][5]
Separate two different enteric pathologies
MEN2B-associated intestinal ganglioneuromatosis can cause distention, constipation, diarrhea, or megacolon, but it is not the absent-ganglion lesion of Hirschsprung disease. Oral neuromas and marfanoid features should raise that alternative and its urgent endocrine implications. Rare MEN2A-associated RET variants can coexist with Hirschsprung disease and confer medullary thyroid cancer risk. The family and variant require genetics and endocrine assessment; neither all Hirschsprung disease nor all RET findings imply MEN2. [4]
Comparison check: what distinguishes the two children?
The enteric histology. Aganglionosis supports Hirschsprung disease; ganglioneuromatosis supports a different process that can accompany MEN2B.
Now apply the distinction to an infant with confirmed Hirschsprung disease and relatives with medullary thyroid carcinoma. Do not dismiss the cancer history because constipation is already explained. Request variant-specific counseling and appropriate family evaluation. Conversely, an isolated low-risk developmental RET finding is not a reason to invent a universal cancer-surveillance schedule.
When does the problem become an emergency?
A child awaiting repair develops fever, increasing distention, foul explosive diarrhea, and lethargy. Is the diarrhea reassuring evidence that the obstruction has resolved? No. Hirschsprung-associated enterocolitis (HAEC) can present with diarrhea despite impaired emptying; some patients instead have reduced stool passage. It can occur before or after pull-through. Shock, poor perfusion, and progressive abdominal findings require immediate escalation. [2]
Choose the next priority from the child's condition
For a systemically ill child, prioritize inpatient resuscitation, intravenous fluids, broad-spectrum antibiotics including anaerobic coverage, and prompt pediatric surgical involvement. Surgical-team-directed rectal irrigations address retained contents when appropriate. Bowel rest, gastric decompression, and intensive care support depend on severity. Perforation requires urgent operative management. Do not delay treatment for elective manometry or contrast enema; contrast enema during acute HAEC carries a perforation risk. [1][2]
Compare that child with a carefully assessed patient who has only mild symptoms, normal hydration, and no systemic disturbance. Selected mild episodes may be managed outside hospital under a specialist plan with close reassessment, but infancy lowers the admission threshold. This exception must not be applied to fever with lethargy, poor perfusion, dehydration, or worsening distention. Families need clear emergency contact instructions, not a requirement to calculate a score before seeking help. [1]
Repair the obstruction, then continue care
Before elective repair, decompression and nutritional assessment help establish a stable, growing child. Failure of irrigations, refractory enterocolitis, or perforation may require diversion. The operative plan depends on histologic extent and clinical condition. The 2026 guideline also suggests renal and urinary tract ultrasound screening within the first year and emphasizes growth assessment rather than routine special-formula substitution. [1]
After repair, compare two patterns of soiling. A child with a dilated stool-filled colon may have overflow from retention and need an emptying-focused plan. A child with frequent loose stools and no dilation may need a different dietary or medical approach. Calling both “diarrhea” can produce opposite and inappropriate treatments. Persistent obstruction or recurrent HAEC warrants assessment for stricture, twist, an obstructing muscular cuff, or residual abnormal innervation. Review pathology and obtain further studies after acute illness is controlled. [1]
If mechanical causes and abnormal pull-through innervation have been addressed, a nonrelaxing outlet may respond to specialist botulinum toxin treatment. This therapeutic use is different from routine preventive injections, which the updated guideline does not recommend. It also advises against routine preventive serial anal dilatations. Assessment of anastomotic caliber and treatment of a diagnosed stricture are separate decisions. [1]
Priority check: does prior repair exclude HAEC?
No. Fever, distention, and systemic illness after repair still require urgent evaluation. A prior operation changes the possible causes of obstruction, not the need to recognize enterocolitis.
Transfer the lesson to adolescence: stool passage is not the only outcome. Follow-up should address continence, growth, participation in school and social life, individualized nutrition, sexual health and fertility concerns, and a clear plan for adult care. No operation guarantees freedom from bowel dysfunction or future enterocolitis. [1]
Apply the relationships to new cases
Before reading the options, identify the decision required: urgent stabilization, diagnostic confirmation, localization, or follow-up. Then name the finding that separates your preferred answer from its closest alternative.
Case 1
Show answer and explanations for case 1
A. Transient meconium impaction with intact rectal innervation (Why this does not fit)
A plug can respond to washout, but absent ganglia and calretinin at an adequate site argue against an innervated distal outlet.
Reasoning steps for option A
Which detail in this case makes "Transient meconium impaction with intact rectal innervation" a plausible alternative at first?
A meconium plug can respond promptly to washout.
Which case finding makes "Transient meconium impaction with intact rectal innervation" less appropriate than the supported choice?
A plug can respond to washout, but absent ganglia and calretinin at an adequate site argue against an innervated distal outlet.
What discriminator from this case separates "Transient meconium impaction with intact rectal innervation" from the supported choice?
C. Persistent distal tonic contraction from absent enteric innervation despite temporary decompression (Best answer)
Biopsy and distal caliber pattern support a nonrelaxing aganglionic segment; washing out retained contents does not restore innervation.
Reasoning steps for option C
Which supplied findings in this case support "Persistent distal tonic contraction from absent enteric innervation despite temporary decompression"?
Recurrent obstruction after washout and distal narrow segment; Adequate biopsy lacks ganglia and calretinin fibers.
How do the case findings justify "Persistent distal tonic contraction from absent enteric innervation despite temporary decompression" as the supported choice?
Biopsy and distal caliber pattern support a nonrelaxing aganglionic segment; washing out retained contents does not restore innervation.
What decision rule from this case supports "Persistent distal tonic contraction from absent enteric innervation despite temporary decompression" over the nearby alternatives?
D. Anatomic rectal stenosis with preserved myenteric plexuses causing fixed narrowing (Why this does not fit)
Stenosis could cause distal obstruction, but histologic aganglionosis rather than preserved plexuses identifies the functional mechanism.
Reasoning steps for option D
Which detail in this case makes "Anatomic rectal stenosis with preserved myenteric plexuses causing fixed narrowing" a plausible alternative at first?
A fixed rectal narrowing can cause persistent outlet obstruction.
Which case finding makes "Anatomic rectal stenosis with preserved myenteric plexuses causing fixed narrowing" less appropriate than the supported choice?
Stenosis could cause distal obstruction, but histologic aganglionosis rather than preserved plexuses identifies the functional mechanism.
What discriminator from this case separates "Anatomic rectal stenosis with preserved myenteric plexuses causing fixed narrowing" from the supported choice?
A. Sigmoid dilation recurs because its normal ganglia have been lost (Why this does not fit)
The sigmoid is documented to contain ganglion cells. Recurrent dilation need not imply a new neuronal defect.
Reasoning steps for option A
Which detail in this case makes "Sigmoid dilation recurs because its normal ganglia have been lost" a plausible alternative at first?
Proximal dilation can suggest intrinsic proximal disease.
Which case finding makes "Sigmoid dilation recurs because its normal ganglia have been lost" less appropriate than the supported choice?
The sigmoid is documented to contain ganglion cells. Recurrent dilation need not imply a new neuronal defect.
What discriminator from this case separates "Sigmoid dilation recurs because its normal ganglia have been lost" from the supported choice?
Decompression treats accumulated contents, not the congenital distal lesion.
B. Sigmoid dilation recurs because persistent distal aganglionic resistance remains after irrigation (Best answer)
The measurable reduction reflects evacuation of contents, while the distal aganglionic segment remains an outlet resistance.
Reasoning steps for option B
Which supplied findings in this case support "Sigmoid dilation recurs because persistent distal aganglionic resistance remains after irrigation"?
Rectal aganglionosis with ganglionated proximal sigmoid; Sigmoid diameter falls with irrigation while rectum remains narrow.
How do the case findings justify "Sigmoid dilation recurs because persistent distal aganglionic resistance remains after irrigation" as the supported choice?
The measurable reduction reflects evacuation of contents, while the distal aganglionic segment remains an outlet resistance.
What decision rule from this case supports "Sigmoid dilation recurs because persistent distal aganglionic resistance remains after irrigation" over the nearby alternatives?
Decompression treats accumulated contents, not the congenital distal lesion.
C. Rectal dilation predominates because its relaxation reflex returns (Why this does not fit)
The persistently narrow rectum is aganglionic; irrigation does not restore reflex relaxation.
Reasoning steps for option C
Which detail in this case makes "Rectal dilation predominates because its relaxation reflex returns" a plausible alternative at first?
Increased upstream pressure can eventually distend bowel.
Which case finding makes "Rectal dilation predominates because its relaxation reflex returns" less appropriate than the supported choice?
The persistently narrow rectum is aganglionic; irrigation does not restore reflex relaxation.
What discriminator from this case separates "Rectal dilation predominates because its relaxation reflex returns" from the supported choice?
Decompression treats accumulated contents, not the congenital distal lesion.
D. Both segments stay decompressed because the obstruction was luminal (Why this does not fit)
A luminal plug could produce temporary obstruction, but documented aganglionosis establishes a persisting distal abnormality.
Reasoning steps for option D
Which detail in this case makes "Both segments stay decompressed because the obstruction was luminal" a plausible alternative at first?
Evacuation can resolve a transient luminal obstruction.
Which case finding makes "Both segments stay decompressed because the obstruction was luminal" less appropriate than the supported choice?
A luminal plug could produce temporary obstruction, but documented aganglionosis establishes a persisting distal abnormality.
What discriminator from this case separates "Both segments stay decompressed because the obstruction was luminal" from the supported choice?
Decompression treats accumulated contents, not the congenital distal lesion.
Takeaway: Decompression treats accumulated contents, not the congenital distal lesion.
A. Ratio 0.63 supports distal aganglionosis; obtain adequate rectal histology to confirm ganglion status (Best answer)
Rectum divided by sigmoid is 12/19; recurrent obstruction after evacuation warrants biopsy.
Reasoning steps for option A
Which supplied findings in this case support "Ratio 0.63 supports distal aganglionosis; obtain adequate rectal histology to confirm ganglion status"?
Rectum 12 mm and sigmoid 19 mm; Obstruction recurs after contrast evacuation.
How do the case findings justify "Ratio 0.63 supports distal aganglionosis; obtain adequate rectal histology to confirm ganglion status" as the supported choice?
Rectum divided by sigmoid is 12/19; recurrent obstruction after evacuation warrants biopsy.
What decision rule from this case supports "Ratio 0.63 supports distal aganglionosis; obtain adequate rectal histology to confirm ganglion status" over the nearby alternatives?
A rectum narrower than sigmoid supports, but cannot establish, the diagnosis.
B. Ratio 1.58 supports a normal distal outlet; assess proximal motility (Why this does not fit)
Inverting the ratio reverses the measured rectosigmoid relationship.
Reasoning steps for option B
Which detail in this case makes "Ratio 1.58 supports a normal distal outlet; assess proximal motility" a plausible alternative at first?
The inverse ratio 19/12 is easy to calculate mistakenly.
Which case finding makes "Ratio 1.58 supports a normal distal outlet; assess proximal motility" less appropriate than the supported choice?
Inverting the ratio reverses the measured rectosigmoid relationship.
What discriminator from this case separates "Ratio 1.58 supports a normal distal outlet; assess proximal motility" from the supported choice?
A rectum narrower than sigmoid supports, but cannot establish, the diagnosis.
C. Ratio 0.63 establishes the diagnosis; plan resection from imaging alone without biopsy (Why this does not fit)
The ratio supports suspicion but cannot show ganglion status or a safe margin.
Reasoning steps for option C
Which detail in this case makes "Ratio 0.63 establishes the diagnosis; plan resection from imaging alone without biopsy" a plausible alternative at first?
A low ratio is classically associated with disease.
Which case finding makes "Ratio 0.63 establishes the diagnosis; plan resection from imaging alone without biopsy" less appropriate than the supported choice?
The ratio supports suspicion but cannot show ganglion status or a safe margin.
What discriminator from this case separates "Ratio 0.63 establishes the diagnosis; plan resection from imaging alone without biopsy" from the supported choice?
A rectum narrower than sigmoid supports, but cannot establish, the diagnosis.
D. Ratio 1.58 suggests total colonic disease; sample ileum first (Why this does not fit)
Neither the calculation nor localization justifies assuming total-colon aganglionosis.
Reasoning steps for option D
Which detail in this case makes "Ratio 1.58 suggests total colonic disease; sample ileum first" a plausible alternative at first?
Extensive proximal disease could alter caliber broadly.
Which case finding makes "Ratio 1.58 suggests total colonic disease; sample ileum first" less appropriate than the supported choice?
Neither the calculation nor localization justifies assuming total-colon aganglionosis.
What discriminator from this case separates "Ratio 1.58 suggests total colonic disease; sample ileum first" from the supported choice?
A rectum narrower than sigmoid supports, but cannot establish, the diagnosis.
Takeaway: A rectum narrower than sigmoid supports, but cannot establish, the diagnosis.
A. Repeat contrast enema after reaccumulation of stool (Why this does not fit)
Early repeat imaging may remain nondiagnostic; persistent obstruction requires histologic assessment.
Reasoning steps for option A
Which detail in this case makes "Repeat contrast enema after reaccumulation of stool" a plausible alternative at first?
Repeat imaging could reveal a delayed transition.
Which case finding makes "Repeat contrast enema after reaccumulation of stool" less appropriate than the supported choice?
Early repeat imaging may remain nondiagnostic; persistent obstruction requires histologic assessment.
What discriminator from this case separates "Repeat contrast enema after reaccumulation of stool" from the supported choice?
An indistinct neonatal transition zone cannot overrule a persistent obstructive phenotype.
B. Anorectal manometry to establish the final diagnosis (Why this does not fit)
Manometry can raise suspicion, but absent RAIR does not establish aganglionosis.
Reasoning steps for option B
Which detail in this case makes "Anorectal manometry to establish the final diagnosis" a plausible alternative at first?
Manometry can interrogate outlet relaxation.
Which case finding makes "Anorectal manometry to establish the final diagnosis" less appropriate than the supported choice?
Manometry can raise suspicion, but absent RAIR does not establish aganglionosis.
What discriminator from this case separates "Anorectal manometry to establish the final diagnosis" from the supported choice?
An indistinct neonatal transition zone cannot overrule a persistent obstructive phenotype.
C. Appropriately sited rectal suction biopsy with adequate submucosa for ganglion assessment (Best answer)
An early false-negative contrast study plus recurrent distal obstruction merits adequate tissue sampling.
Reasoning steps for option C
Which supplied findings in this case support "Appropriately sited rectal suction biopsy with adequate submucosa for ganglion assessment"?
Early contrast without transition; Transient decompression followed by recurrence.
How do the case findings justify "Appropriately sited rectal suction biopsy with adequate submucosa for ganglion assessment" as the supported choice?
An early false-negative contrast study plus recurrent distal obstruction merits adequate tissue sampling.
What decision rule from this case supports "Appropriately sited rectal suction biopsy with adequate submucosa for ganglion assessment" over the nearby alternatives?
An indistinct neonatal transition zone cannot overrule a persistent obstructive phenotype.
D. Serial plain radiographs to define a caliber transition (Why this does not fit)
Films can monitor distension but cannot determine distal ganglion status.
Reasoning steps for option D
Which detail in this case makes "Serial plain radiographs to define a caliber transition" a plausible alternative at first?
Serial films can document recurrent obstruction.
Which case finding makes "Serial plain radiographs to define a caliber transition" less appropriate than the supported choice?
Films can monitor distension but cannot determine distal ganglion status.
What discriminator from this case separates "Serial plain radiographs to define a caliber transition" from the supported choice?
An indistinct neonatal transition zone cannot overrule a persistent obstructive phenotype.
Takeaway: An indistinct neonatal transition zone cannot overrule a persistent obstructive phenotype.
A. Rectal suction biopsy at an appropriate level to directly assess distal ganglion status (Best answer)
Early meconium does not negate recurrent distal obstruction. Representative histology directly tests whether ganglion cells are present.
Reasoning steps for option A
Which supplied findings in this case support "Rectal suction biopsy at an appropriate level to directly assess distal ganglion status"?
Early meconium despite later recurrent bilious obstruction; Fixed small-bowel causes excluded; empty rectal vault with recurrent proximal retention.
How do the case findings justify "Rectal suction biopsy at an appropriate level to directly assess distal ganglion status" as the supported choice?
Early meconium does not negate recurrent distal obstruction. Representative histology directly tests whether ganglion cells are present.
What decision rule from this case supports "Rectal suction biopsy at an appropriate level to directly assess distal ganglion status" over the nearby alternatives?
Early passage of meconium is not an exclusion test.
B. Repeat plain radiography after the next feeding (Why this does not fit)
Serial gas patterns can show recurrent obstruction but cannot distinguish ganglionated from aganglionic bowel.
Reasoning steps for option B
Which detail in this case makes "Repeat plain radiography after the next feeding" a plausible alternative at first?
Imaging can document recurrent obstruction after feeding.
Which case finding makes "Repeat plain radiography after the next feeding" less appropriate than the supported choice?
Serial gas patterns can show recurrent obstruction but cannot distinguish ganglionated from aganglionic bowel.
What discriminator from this case separates "Repeat plain radiography after the next feeding" from the supported choice?
Early passage of meconium is not an exclusion test.
C. Contrast enema after complete bowel preparation (Why this does not fit)
An enema can support localization, but bowel preparation can alter the caliber pattern and imaging cannot establish neuronal status.
Reasoning steps for option C
Which detail in this case makes "Contrast enema after complete bowel preparation" a plausible alternative at first?
A contrast study can identify luminal filling defects or a transition.
Which case finding makes "Contrast enema after complete bowel preparation" less appropriate than the supported choice?
An enema can support localization, but bowel preparation can alter the caliber pattern and imaging cannot establish neuronal status.
What discriminator from this case separates "Contrast enema after complete bowel preparation" from the supported choice?
Early passage of meconium is not an exclusion test.
D. Anorectal manometry without further tissue sampling (Why this does not fit)
Manometry evaluates the relaxation reflex, but absent relaxation is not sufficient to establish aganglionosis.
Reasoning steps for option D
Which detail in this case makes "Anorectal manometry without further tissue sampling" a plausible alternative at first?
A pressure study can identify impaired outlet relaxation.
Which case finding makes "Anorectal manometry without further tissue sampling" less appropriate than the supported choice?
Manometry evaluates the relaxation reflex, but absent relaxation is not sufficient to establish aganglionosis.
What discriminator from this case separates "Anorectal manometry without further tissue sampling" from the supported choice?
Early passage of meconium is not an exclusion test.
Takeaway: Early passage of meconium is not an exclusion test.
A. Repeat thyroid and celiac testing during distension (Why this does not fit)
These disorders can impair growth and stooling, but prior normal testing and the distal-outlet pattern favor another assessment first.
Reasoning steps for option A
Which detail in this case makes "Repeat thyroid and celiac testing during distension" a plausible alternative at first?
Endocrine or malabsorptive disorders can cause poor growth.
Which case finding makes "Repeat thyroid and celiac testing during distension" less appropriate than the supported choice?
These disorders can impair growth and stooling, but prior normal testing and the distal-outlet pattern favor another assessment first.
What discriminator from this case separates "Repeat thyroid and celiac testing during distension" from the supported choice?
Refractory early-onset constipation with growth concerns warrants organic evaluation.
B. Colonic transit testing before evaluating distal histology (Why this does not fit)
Transit testing may help later, but slow transit can be secondary to distal obstruction; congenital aganglionosis must be assessed.
Reasoning steps for option B
Which detail in this case makes "Colonic transit testing before evaluating distal histology" a plausible alternative at first?
Refractory constipation can reflect slow colonic transit.
Which case finding makes "Colonic transit testing before evaluating distal histology" less appropriate than the supported choice?
Transit testing may help later, but slow transit can be secondary to distal obstruction; congenital aganglionosis must be assessed.
What discriminator from this case separates "Colonic transit testing before evaluating distal histology" from the supported choice?
Refractory early-onset constipation with growth concerns warrants organic evaluation.
C. Rectal biopsy after specialist assessment to evaluate congenital distal aganglionosis (Best answer)
Infant-onset symptoms, poor growth, and an empty distal vault despite proximal retention warrant evaluation of rectal innervation.
Reasoning steps for option C
Which supplied findings in this case support "Rectal biopsy after specialist assessment to evaluate congenital distal aganglionosis"?
Infant-onset constipation with poor growth despite adequate laxatives; Relatively empty distal vault with proximal loading and normal thyroid/celiac tests.
How do the case findings justify "Rectal biopsy after specialist assessment to evaluate congenital distal aganglionosis" as the supported choice?
Infant-onset symptoms, poor growth, and an empty distal vault despite proximal retention warrant evaluation of rectal innervation.
What decision rule from this case supports "Rectal biopsy after specialist assessment to evaluate congenital distal aganglionosis" over the nearby alternatives?
Refractory early-onset constipation with growth concerns warrants organic evaluation.
D. An empiric dietary exclusion trial before further testing (Why this does not fit)
Dietary factors can contribute to symptoms, but an exclusion trial does not resolve the longstanding organic warning signs.
Reasoning steps for option D
Which detail in this case makes "An empiric dietary exclusion trial before further testing" a plausible alternative at first?
Dietary intolerance can contribute to constipation and distension.
Which case finding makes "An empiric dietary exclusion trial before further testing" less appropriate than the supported choice?
Dietary factors can contribute to symptoms, but an exclusion trial does not resolve the longstanding organic warning signs.
What discriminator from this case separates "An empiric dietary exclusion trial before further testing" from the supported choice?
Refractory early-onset constipation with growth concerns warrants organic evaluation.
Takeaway: Refractory early-onset constipation with growth concerns warrants organic evaluation.
A. A establishes disease; obtain proximal mapping before repair (Why this does not fit)
A was obtained at an appropriate level but lacks representative submucosa, so it cannot establish absent ganglia in that plexus.
Reasoning steps for option A
Which detail in this case makes "A establishes disease; obtain proximal mapping before repair" a plausible alternative at first?
An appropriate sampling level can suggest a reliable specimen.
Which case finding makes "A establishes disease; obtain proximal mapping before repair" less appropriate than the supported choice?
A was obtained at an appropriate level but lacks representative submucosa, so it cannot establish absent ganglia in that plexus.
What discriminator from this case separates "A establishes disease; obtain proximal mapping before repair" from the supported choice?
Insufficient submucosa makes an apparently negative biopsy nondiagnostic.
B. B establishes disease; use A to estimate proximal extent (Why this does not fit)
B has suitable depth but is too distal, where physiologic hypoganglionosis may confound diagnosis.
Reasoning steps for option B
Which detail in this case makes "B establishes disease; use A to estimate proximal extent" a plausible alternative at first?
Ample submucosa can suggest a diagnostic specimen.
Which case finding makes "B establishes disease; use A to estimate proximal extent" less appropriate than the supported choice?
B has suitable depth but is too distal, where physiologic hypoganglionosis may confound diagnosis.
What discriminator from this case separates "B establishes disease; use A to estimate proximal extent" from the supported choice?
Insufficient submucosa makes an apparently negative biopsy nondiagnostic.
C. Together they exclude a sampling problem; schedule definitive repair without repeat biopsy (Why this does not fit)
The defects do not compensate for each other: neither specimen has both adequate depth and site.
Reasoning steps for option C
Which detail in this case makes "Together they exclude a sampling problem; schedule definitive repair without repeat biopsy" a plausible alternative at first?
Concordant negative-cell reports can appear to reinforce each other.
Which case finding makes "Together they exclude a sampling problem; schedule definitive repair without repeat biopsy" less appropriate than the supported choice?
The defects do not compensate for each other: neither specimen has both adequate depth and site.
What discriminator from this case separates "Together they exclude a sampling problem; schedule definitive repair without repeat biopsy" from the supported choice?
Insufficient submucosa makes an apparently negative biopsy nondiagnostic.
D. Neither establishes disease; repeat at adequate depth and site (Best answer)
A lacks the required compartment and B risks physiologic distal hypoganglionosis. A new specimen must satisfy both criteria.
Reasoning steps for option D
Which supplied findings in this case support "Neither establishes disease; repeat at adequate depth and site"?
Sample A has appropriate location but no submucosa; Sample B has submucosa but is immediately above the dentate line.
How do the case findings justify "Neither establishes disease; repeat at adequate depth and site" as the supported choice?
A lacks the required compartment and B risks physiologic distal hypoganglionosis. A new specimen must satisfy both criteria.
What decision rule from this case supports "Neither establishes disease; repeat at adequate depth and site" over the nearby alternatives?
Insufficient submucosa makes an apparently negative biopsy nondiagnostic.
Takeaway: Insufficient submucosa makes an apparently negative biopsy nondiagnostic.
A. Urgently involve pediatric surgery to consider diversion while supporting fluids (Best answer)
Escalation to operative decompression may be needed when irrigations fail.
Reasoning steps for option A
Which supplied findings in this case support "Urgently involve pediatric surgery to consider diversion while supporting fluids"?
Confirmed aganglionosis; Worsening emesis and distension despite adequate irrigations.
How do the case findings justify "Urgently involve pediatric surgery to consider diversion while supporting fluids" as the supported choice?
Escalation to operative decompression may be needed when irrigations fail.
What decision rule from this case supports "Urgently involve pediatric surgery to consider diversion while supporting fluids" over the nearby alternatives?
Persistent obstruction despite adequate irrigations can require surgical diversion.
B. Increase irrigation frequency while postponing surgical review (Why this does not fit)
Worsening obstruction despite technically adequate irrigation requires reassessment, not only repetition.
Reasoning steps for option B
Which detail in this case makes "Increase irrigation frequency while postponing surgical review" a plausible alternative at first?
Increasing frequency can sometimes improve washout.
Which case finding makes "Increase irrigation frequency while postponing surgical review" less appropriate than the supported choice?
Worsening obstruction despite technically adequate irrigation requires reassessment, not only repetition.
What discriminator from this case separates "Increase irrigation frequency while postponing surgical review" from the supported choice?
Persistent obstruction despite adequate irrigations can require surgical diversion.
C. Give therapeutic sphincter botulinum injection before excluding obstructive complications (Why this does not fit)
A targeted postoperative outlet therapy does not replace urgent assessment of an obstructed newborn.
Reasoning steps for option C
Which detail in this case makes "Give therapeutic sphincter botulinum injection before excluding obstructive complications" a plausible alternative at first?
Botulinum toxin can address outlet dysfunction in selected postoperative cases.
Which case finding makes "Give therapeutic sphincter botulinum injection before excluding obstructive complications" less appropriate than the supported choice?
A targeted postoperative outlet therapy does not replace urgent assessment of an obstructed newborn.
What discriminator from this case separates "Give therapeutic sphincter botulinum injection before excluding obstructive complications" from the supported choice?
Persistent obstruction despite adequate irrigations can require surgical diversion.
D. Proceed with planned elective pull-through without reevaluating distension (Why this does not fit)
Worsening obstruction requires stabilization and a surgical decompression plan before routine timing.
Reasoning steps for option D
Which detail in this case makes "Proceed with planned elective pull-through without reevaluating distension" a plausible alternative at first?
Definitive surgery ultimately treats aganglionosis.
Which case finding makes "Proceed with planned elective pull-through without reevaluating distension" less appropriate than the supported choice?
Worsening obstruction requires stabilization and a surgical decompression plan before routine timing.
What discriminator from this case separates "Proceed with planned elective pull-through without reevaluating distension" from the supported choice?
Persistent obstruction despite adequate irrigations can require surgical diversion.
Takeaway: Persistent obstruction despite adequate irrigations can require surgical diversion.
A. IV fluids and cultures, then await cultures before antibiotics or decompression (Why this does not fit)
Cultures may be obtained promptly, but shock and suspected HAEC require immediate antimicrobial and bowel-directed care.
Reasoning steps for option A
Which detail in this case makes "IV fluids and cultures, then await cultures before antibiotics or decompression" a plausible alternative at first?
Fluids and cultures are important early shock steps.
Which case finding makes "IV fluids and cultures, then await cultures before antibiotics or decompression" less appropriate than the supported choice?
Cultures may be obtained promptly, but shock and suspected HAEC require immediate antimicrobial and bowel-directed care.
What discriminator from this case separates "IV fluids and cultures, then await cultures before antibiotics or decompression" from the supported choice?
Hirschsprung-associated enterocolitis with shock requires urgent resuscitation and decompression.
B. Antibiotics and urgent contrast enema before perfusion assessment (Why this does not fit)
Antimicrobials matter, but contrast enema in acute toxic HAEC and delayed resuscitation are unsafe.
Reasoning steps for option B
Which detail in this case makes "Antibiotics and urgent contrast enema before perfusion assessment" a plausible alternative at first?
Antibiotics and imaging can appear to localize source.
Which case finding makes "Antibiotics and urgent contrast enema before perfusion assessment" less appropriate than the supported choice?
Antimicrobials matter, but contrast enema in acute toxic HAEC and delayed resuscitation are unsafe.
What discriminator from this case separates "Antibiotics and urgent contrast enema before perfusion assessment" from the supported choice?
Hirschsprung-associated enterocolitis with shock requires urgent resuscitation and decompression.
C. Resuscitation, broad-spectrum antibiotics, and careful rectal decompression (Best answer)
This simultaneously addresses shock, infection, and obstructed colon.
Reasoning steps for option C
Which supplied findings in this case support "Resuscitation, broad-spectrum antibiotics, and careful rectal decompression"?
Toxic diarrhea and tense distension in known HSCR; Hypotension without free air.
How do the case findings justify "Resuscitation, broad-spectrum antibiotics, and careful rectal decompression" as the supported choice?
This simultaneously addresses shock, infection, and obstructed colon.
What decision rule from this case supports "Resuscitation, broad-spectrum antibiotics, and careful rectal decompression" over the nearby alternatives?
Hirschsprung-associated enterocolitis with shock requires urgent resuscitation and decompression.
D. Fluid resuscitation and immediate pull-through before infection control (Why this does not fit)
Resuscitation matters, but acute septic enterocolitis requires antibiotics and decompression rather than elective definitive reconstruction.
Reasoning steps for option D
Which detail in this case makes "Fluid resuscitation and immediate pull-through before infection control" a plausible alternative at first?
Resuscitation and surgery can seem definitive.
Which case finding makes "Fluid resuscitation and immediate pull-through before infection control" less appropriate than the supported choice?
Resuscitation matters, but acute septic enterocolitis requires antibiotics and decompression rather than elective definitive reconstruction.
What discriminator from this case separates "Fluid resuscitation and immediate pull-through before infection control" from the supported choice?
Hirschsprung-associated enterocolitis with shock requires urgent resuscitation and decompression.
Takeaway: Hirschsprung-associated enterocolitis with shock requires urgent resuscitation and decompression.
A. Prior irrigation may reduce the accuracy of caliber measurements (Why this does not fit)
Prior decompression can alter caliber, but the immediate problem is safety during a tender, febrile episode.
Reasoning steps for option A
Which detail in this case makes "Prior irrigation may reduce the accuracy of caliber measurements" a plausible alternative at first?
Irrigation can affect radiographic caliber.
Which case finding makes "Prior irrigation may reduce the accuracy of caliber measurements" less appropriate than the supported choice?
Prior decompression can alter caliber, but the immediate problem is safety during a tender, febrile episode.
What discriminator from this case separates "Prior irrigation may reduce the accuracy of caliber measurements" from the supported choice?
Do not perform an acute contrast enema in toxic suspected HAEC.
B. The radiographic transition may not match the histologic boundary during stable mapping (Why this does not fit)
Imaging can misestimate extent, but that limitation applies even when stable and is not the strongest reason to defer now.
Reasoning steps for option B
Which detail in this case makes "The radiographic transition may not match the histologic boundary during stable mapping" a plausible alternative at first?
Imaging and histologic transition need not agree.
Which case finding makes "The radiographic transition may not match the histologic boundary during stable mapping" less appropriate than the supported choice?
Imaging can misestimate extent, but that limitation applies even when stable and is not the strongest reason to defer now.
What discriminator from this case separates "The radiographic transition may not match the histologic boundary during stable mapping" from the supported choice?
Do not perform an acute contrast enema in toxic suspected HAEC.
C. Perforation risk and stabilization take priority during acute illness (Best answer)
Suspected acute HAEC changes the immediate priority to stabilization, antibiotics, and appropriate decompression; a contrast enema may increase perforation risk.
Reasoning steps for option C
Which supplied findings in this case support "Perforation risk and stabilization take priority during acute illness"?
Febrile tender distended infant with known HSCR; Proposed enema before resuscitation.
How do the case findings justify "Perforation risk and stabilization take priority during acute illness" as the supported choice?
Suspected acute HAEC changes the immediate priority to stabilization, antibiotics, and appropriate decompression; a contrast enema may increase perforation risk.
What decision rule from this case supports "Perforation risk and stabilization take priority during acute illness" over the nearby alternatives?
Do not perform an acute contrast enema in toxic suspected HAEC.
D. Retained contrast may reduce the usefulness of subsequent imaging (Why this does not fit)
Residual contrast can affect later images, but this is secondary to the risk in an inflamed, distended bowel.
Reasoning steps for option D
Which detail in this case makes "Retained contrast may reduce the usefulness of subsequent imaging" a plausible alternative at first?
Procedures may influence timing of sampling.
Which case finding makes "Retained contrast may reduce the usefulness of subsequent imaging" less appropriate than the supported choice?
Residual contrast can affect later images, but this is secondary to the risk in an inflamed, distended bowel.
What discriminator from this case separates "Retained contrast may reduce the usefulness of subsequent imaging" from the supported choice?
Do not perform an acute contrast enema in toxic suspected HAEC.
Takeaway: Do not perform an acute contrast enema in toxic suspected HAEC.
A. Careful examination of the anastomosis, with targeted imaging if needed (Best answer)
Caliber change and painful evacuation suggest a mechanical lesion that should be examined before functional treatment.
Reasoning steps for option A
Which supplied findings in this case support "Careful examination of the anastomosis, with targeted imaging if needed"?
Progressively thin painful stools and distension; No systemic enterocolitis symptoms.
How do the case findings justify "Careful examination of the anastomosis, with targeted imaging if needed" as the supported choice?
Caliber change and painful evacuation suggest a mechanical lesion that should be examined before functional treatment.
What decision rule from this case supports "Careful examination of the anastomosis, with targeted imaging if needed" over the nearby alternatives?
A symptomatic narrowed anastomosis calls for targeted assessment, not routine prophylaxis.
B. Empiric therapeutic botulinum toxin before examining the anastomosis for a stricture (Why this does not fit)
Toxin may help selected nonrelaxation but a mechanical stricture must first be excluded.
Reasoning steps for option B
Which detail in this case makes "Empiric therapeutic botulinum toxin before examining the anastomosis for a stricture" a plausible alternative at first?
Functional outlet hypertonicity can respond to toxin.
Which case finding makes "Empiric therapeutic botulinum toxin before examining the anastomosis for a stricture" less appropriate than the supported choice?
Toxin may help selected nonrelaxation but a mechanical stricture must first be excluded.
What discriminator from this case separates "Empiric therapeutic botulinum toxin before examining the anastomosis for a stricture" from the supported choice?
A symptomatic narrowed anastomosis calls for targeted assessment, not routine prophylaxis.
C. Repeat rectal biopsy as the first test without evaluating anatomy (Why this does not fit)
Residual aganglionosis is possible, but progressive caliber change makes mechanical assessment a priority.
Reasoning steps for option C
Which detail in this case makes "Repeat rectal biopsy as the first test without evaluating anatomy" a plausible alternative at first?
Retained transition zone can produce obstruction.
Which case finding makes "Repeat rectal biopsy as the first test without evaluating anatomy" less appropriate than the supported choice?
Residual aganglionosis is possible, but progressive caliber change makes mechanical assessment a priority.
What discriminator from this case separates "Repeat rectal biopsy as the first test without evaluating anatomy" from the supported choice?
A symptomatic narrowed anastomosis calls for targeted assessment, not routine prophylaxis.
D. Treat presumed HAEC first without assessing outlet anatomy (Why this does not fit)
No systemic illness is reported and the symptom trajectory points to narrowing.
Reasoning steps for option D
Which detail in this case makes "Treat presumed HAEC first without assessing outlet anatomy" a plausible alternative at first?
Enterocolitis can cause distension after repair.
Which case finding makes "Treat presumed HAEC first without assessing outlet anatomy" less appropriate than the supported choice?
No systemic illness is reported and the symptom trajectory points to narrowing.
What discriminator from this case separates "Treat presumed HAEC first without assessing outlet anatomy" from the supported choice?
A symptomatic narrowed anastomosis calls for targeted assessment, not routine prophylaxis.
Takeaway: A symptomatic narrowed anastomosis calls for targeted assessment, not routine prophylaxis.
A. RET MEN2 endocrine surveillance as the sole syndromic assessment (Why this does not fit)
RET-associated endocrine risk is important with relevant genotype but does not explain the pigmentary-auditory pattern.
Reasoning steps for option A
Which detail in this case makes "RET MEN2 endocrine surveillance as the sole syndromic assessment" a plausible alternative at first?
RET disease can accompany HSCR.
Which case finding makes "RET MEN2 endocrine surveillance as the sole syndromic assessment" less appropriate than the supported choice?
RET-associated endocrine risk is important with relevant genotype but does not explain the pigmentary-auditory pattern.
What discriminator from this case separates "RET MEN2 endocrine surveillance as the sole syndromic assessment" from the supported choice?
Pigmentary changes plus deafness can connect Hirschsprung disease to Waardenburg spectrum.
B. Sleep ventilation testing alone without hearing follow-up (Why this does not fit)
CCHS can coexist with HSCR, but the specific auditory and pigmentary phenotype warrants hearing-directed care.
Reasoning steps for option B
Which detail in this case makes "Sleep ventilation testing alone without hearing follow-up" a plausible alternative at first?
CCHS is an associated syndromic diagnosis.
Which case finding makes "Sleep ventilation testing alone without hearing follow-up" less appropriate than the supported choice?
CCHS can coexist with HSCR, but the specific auditory and pigmentary phenotype warrants hearing-directed care.
What discriminator from this case separates "Sleep ventilation testing alone without hearing follow-up" from the supported choice?
Pigmentary changes plus deafness can connect Hirschsprung disease to Waardenburg spectrum.
C. Repeat colon imaging to determine whether pigmentary findings predict segment length (Why this does not fit)
Pigmentary traits do not replace genetic and hearing evaluation or establish bowel extent.
Reasoning steps for option C
Which detail in this case makes "Repeat colon imaging to determine whether pigmentary findings predict segment length" a plausible alternative at first?
Imaging helps characterize bowel extent.
Which case finding makes "Repeat colon imaging to determine whether pigmentary findings predict segment length" less appropriate than the supported choice?
Pigmentary traits do not replace genetic and hearing evaluation or establish bowel extent.
What discriminator from this case separates "Repeat colon imaging to determine whether pigmentary findings predict segment length" from the supported choice?
Pigmentary changes plus deafness can connect Hirschsprung disease to Waardenburg spectrum.
D. Targeted Waardenburg-spectrum genetics and audiologic follow-up (Best answer)
Pigmentary findings plus hearing loss and aganglionosis support syndromic evaluation and hearing care.
Reasoning steps for option D
Which supplied findings in this case support "Targeted Waardenburg-spectrum genetics and audiologic follow-up"?
Biopsy-confirmed aganglionosis; Congenital hearing and pigmentary differences.
How do the case findings justify "Targeted Waardenburg-spectrum genetics and audiologic follow-up" as the supported choice?
Pigmentary findings plus hearing loss and aganglionosis support syndromic evaluation and hearing care.
What decision rule from this case supports "Targeted Waardenburg-spectrum genetics and audiologic follow-up" over the nearby alternatives?
Pigmentary changes plus deafness can connect Hirschsprung disease to Waardenburg spectrum.
Takeaway: Pigmentary changes plus deafness can connect Hirschsprung disease to Waardenburg spectrum.
Which detail in this case makes "Both relatives have aganglionosis from the same RET phenotype despite different bowel histology" a plausible alternative at first?
Both phenotypes involve enteric neural abnormalities.
Which case finding makes "Both relatives have aganglionosis from the same RET phenotype despite different bowel histology" less appropriate than the supported choice?
What discriminator from this case separates "Both relatives have aganglionosis from the same RET phenotype despite different bowel histology" from the supported choice?
MEN2B features should not be conflated with the particular RET-associated HSCR and MEN2A relationship.
B. MEN2B ganglioneuromatosis differs from the cousin's aganglionosis (Best answer)
Neuromas and ganglioneuromatosis identify MEN2B, not the absence of ganglia in HSCR.
Reasoning steps for option B
Which supplied findings in this case support "MEN2B ganglioneuromatosis differs from the cousin's aganglionosis"?
A. Schedule interval dilation, but reserve botulinum toxin for symptomatic nonrelaxation (Why this does not fit)
Routine preventive dilation is not recommended despite appropriate restriction of toxin.
Reasoning steps for option A
Which detail in this case makes "Schedule interval dilation, but reserve botulinum toxin for symptomatic nonrelaxation" a plausible alternative at first?
A procedure might appear to forestall anastomotic narrowing.
Which case finding makes "Schedule interval dilation, but reserve botulinum toxin for symptomatic nonrelaxation" less appropriate than the supported choice?
Routine preventive dilation is not recommended despite appropriate restriction of toxin.
What discriminator from this case separates "Schedule interval dilation, but reserve botulinum toxin for symptomatic nonrelaxation" from the supported choice?
Aftercare monitors growth and bowel function while avoiding routine preventive outlet procedures.
B. Schedule botulinum toxin, but reserve dilation for proven stricture (Why this does not fit)
Botulinum toxin may be therapeutic after evaluation, not routine prevention.
Reasoning steps for option B
Which detail in this case makes "Schedule botulinum toxin, but reserve dilation for proven stricture" a plausible alternative at first?
Botulinum toxin can relieve demonstrated nonrelaxation.
Which case finding makes "Schedule botulinum toxin, but reserve dilation for proven stricture" less appropriate than the supported choice?
Botulinum toxin may be therapeutic after evaluation, not routine prevention.
What discriminator from this case separates "Schedule botulinum toxin, but reserve dilation for proven stricture" from the supported choice?
Aftercare monitors growth and bowel function while avoiding routine preventive outlet procedures.
C. Monitor growth and bowel function; reserve procedures for demonstrated problems (Best answer)
Surveillance and enterocolitis education are appropriate without prophylactic outlet intervention.
Reasoning steps for option C
Which supplied findings in this case support "Monitor growth and bowel function; reserve procedures for demonstrated problems"?
Thriving asymptomatic child after pull-through; Request for preventive dilation and toxin.
How do the case findings justify "Monitor growth and bowel function; reserve procedures for demonstrated problems" as the supported choice?
Surveillance and enterocolitis education are appropriate without prophylactic outlet intervention.
What decision rule from this case supports "Monitor growth and bowel function; reserve procedures for demonstrated problems" over the nearby alternatives?
Aftercare monitors growth and bowel function while avoiding routine preventive outlet procedures.
D. Replace clinical follow-up with yearly contrast imaging in asymptomatic children (Why this does not fit)
Routine imaging is not a substitute for growth and bowel-function assessment.
Reasoning steps for option D
Which detail in this case makes "Replace clinical follow-up with yearly contrast imaging in asymptomatic children" a plausible alternative at first?
Imaging can detect anatomic complications.
Which case finding makes "Replace clinical follow-up with yearly contrast imaging in asymptomatic children" less appropriate than the supported choice?
Routine imaging is not a substitute for growth and bowel-function assessment.
What discriminator from this case separates "Replace clinical follow-up with yearly contrast imaging in asymptomatic children" from the supported choice?
Aftercare monitors growth and bowel function while avoiding routine preventive outlet procedures.
Takeaway: Aftercare monitors growth and bowel function while avoiding routine preventive outlet procedures.