Connect octreotide receptor effects to variceal care, endocrine and secretory syndromes, formulation choices, and predictable glucose, biliary and cardiac harms.
How can one drug help a patient vomiting blood, another with persistent growth hormone excess, and another losing liters of stool? Octreotide suppresses several physiologic outputs. The useful question is which output is causing harm, and what essential function might be suppressed at the same time.
By the end, you should be able to trace receptor signaling to an organ effect, place octreotide within acute variceal care, separate symptom control from treatment of a tumor, and investigate new symptoms during chronic therapy. The examples are original educational scenarios, not patient records.
An inhibitory signal is not a receptor blocker
Does reducing hormone release mean octreotide antagonizes the hormone's receptor? No. Octreotide is a synthetic somatostatin analog: it activates somatostatin receptors, which transmit inhibitory signals. Its activity favors SSTR2, with activity at SSTR5. Receptor expression and downstream responsiveness vary among tumors, so the same prescription does not guarantee the same response. [1][6]
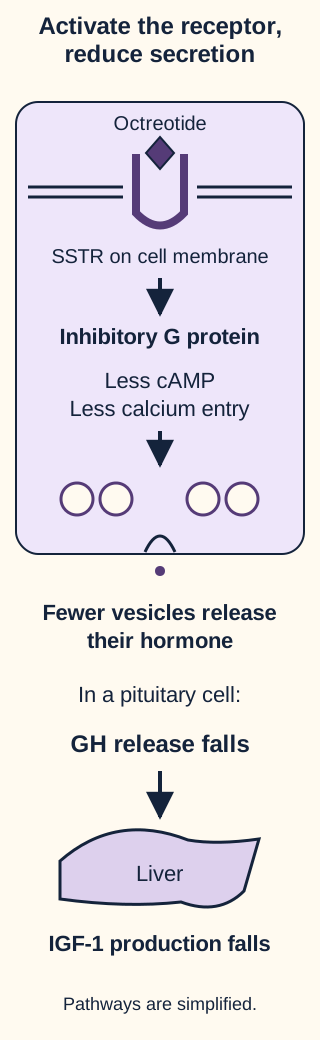
Somatostatin receptors couple to inhibitory G proteins. Reduced adenylyl cyclase activity lowers intracellular cyclic AMP. Effects on ion channels reduce calcium entry, and other signaling pathways reduce exocytosis. A secretory cell consequently releases less stored hormone. These are related pathways, not a claim that every organ effect passes through one identical intracellular sequence. [6]
In the pituitary, less growth hormone (GH) release means less stimulation of hepatic insulin-like growth factor 1 (IGF-1) production. In responsive neuroendocrine cells, suppression of serotonin, vasoactive intestinal peptide (VIP), and other mediators can reduce secretory symptoms. In the gastrointestinal circulation, inhibition of vasodilatory peptides and associated splanchnic effects reduce blood flow toward the portal circulation. [1]
Trace secretion, then change the target
Use the receptor diagram to follow the path from receptor activation to a secretory vesicle. Before reading the comparison below, predict the direction of GH and then IGF-1 when a responsive pituitary cell releases fewer vesicles.
Trace the receptor, intracellular signals and vesicles, then predict GH and IGF-1. The purpose is to distinguish activating an inhibitory receptor from blocking a hormone receptor. This is a qualitative original model. [1][3][6]
Responsive pituitary cell: somatostatin receptor activation → less GH release → less hepatic IGF-1 production.
Peripheral GH receptor blockade: less GH action at the liver → less IGF-1 production, without requiring suppression of pituitary GH release.
The first path describes octreotide; the second describes pegvisomant. Both can lower IGF-1, but the site of action differs. A falling IGF-1 therefore does not, by itself, identify the drug's target. GH is not used to assess biochemical control during pegvisomant treatment. [3]
Predict the effect of poor receptor expression
A tumor with limited functional somatostatin receptor expression may release substantial hormone despite treatment. A weak response calls for assessment of treatment delivery and tumor biology, not an assumption that the disease was cured.
Apply the same reasoning to a VIP-secreting tumor: reducing its hormone output can improve diarrhea even while the mass remains visible. Keep secretion and tumor size as separate measurements.
Reduce portal inflow while treating the bleeding source
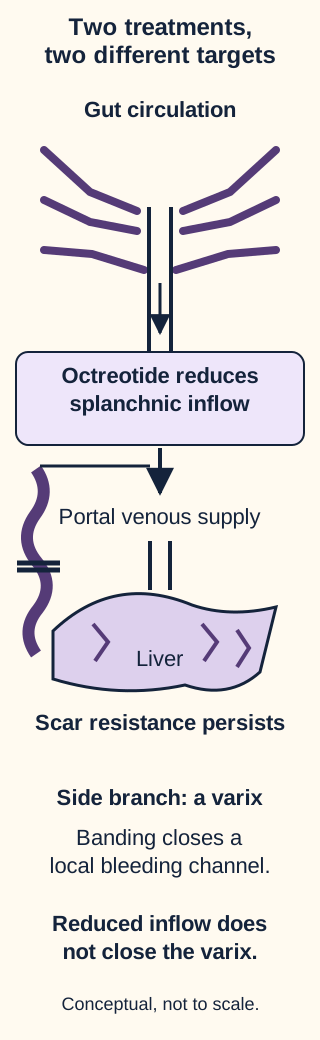
If hematemesis slows after octreotide, can endoscopy wait? Less inflow is not closure of a bleeding varix. In cirrhosis, resistance within the liver contributes to portal hypertension. Reducing splanchnic blood flow reduces the inflow feeding that high-pressure system; it does not reverse cirrhotic architecture or mechanically ligate a varix. The portal-flow diagram keeps these different targets visible. [1][2]
A patient with cirrhosis, hematemesis and shock needs parallel care. Protect the airway when consciousness or active vomiting of blood threatens it; restore perfusion with appropriate access, fluids and blood. Start a vasoactive agent such as octreotide and antibiotic prophylaxis as soon as variceal hemorrhage is suspected, rather than waiting for confirmation. Use a monitored setting. In the United States, variceal hemorrhage is a guideline-supported use outside the listed Sandostatin indications. [1][2]
At presentation: resuscitation, early vasoactive treatment and antibiotics proceed together.
After initial stabilization: upper endoscopy within 12 hours of presentation; if unstable, as soon as safely possible. Ligate bleeding esophageal varices.
After hemostasis: continue short-course therapy, reassess rebleeding risk and plan prevention.
Baveno VII recommends conservative red-cell transfusion targeting hemoglobin approximately 7 to 8 g/dL, individualized for ongoing hemorrhage, hemodynamics, age and cardiovascular disease. A target is not permission to withhold resuscitation from someone in shock. Antibiotic prophylaxis addresses a separate infection risk in cirrhosis with gastrointestinal bleeding. ESGE recommends ceftriaxone 1 g daily for up to 7 days, adapted to allergies, local resistance and clinical policy. [2][7]
For a simplified illustration only, pressure gradient equals flow multiplied by resistance. If flow is 1,000 mL/min and the assumed resistance is 0.020 mmHg per mL/min, the modeled gradient is 20 mmHg. Reducing flow to 750 at the same assumed resistance gives 15 mmHg. Calculate the change, then ask whether a lower number proves that the varix is closed: it does not. Real resistance and flow are dynamic; these values are not a patient-specific pressure or bleeding-risk calculator.
Compare two interventions on the flow diagram
Trace the route from gut vessels toward the liver. Now identify where octreotide acts and where a band acts. Predict which anatomical problem remains after inflow decreases.
Locate the drug effect and the band separately. The purpose is to explain why reduced portal inflow does not replace local hemostasis or treatment of persistent hepatic resistance. [1][2][7]
The damaged varix and hepatic resistance remain. That visible distinction explains why improvement during an infusion does not cancel endoscopy. It also explains why simply increasing the infusion is inadequate when combined drug and endoscopic treatment fails.
When combined drug and endoscopic treatment fails, urgent expert escalation to salvage transjugular intrahepatic portosystemic shunt (TIPS) is appropriate. An esophageal self-expanding metal stent or balloon tamponade can provide temporary control while definitive therapy is arranged; neither is a long-term solution. [2][7]
If a stent stops the bleeding, is definitive treatment finished?
No. The stent supplies temporary local control after combined treatment has failed. Use that interval to arrange definitive therapy rather than treating the initial response as durable prevention.
Risk can justify TIPS before another hemorrhage. Baveno VII recommends preemptive covered TIPS within 72 hours, ideally within 24 hours, for eligible patients with Child-Pugh C scores 10 to 13, Child-Pugh B scores above 7 with active bleeding at initial endoscopy, or hepatic venous pressure gradient above 20 mmHg during hemorrhage. Selection also requires specialist assessment of suitability. This is different from salvage TIPS for uncontrolled bleeding. [2]
Transfer the idea to a fundal gastric varix: the early resuscitation and drug bundle still matters, but definitive local treatment differs. Tissue adhesive or appropriate expert endovascular/endoscopic therapy may be required; do not generalize esophageal band ligation to every gastric varix. [2][7]
Follow the abnormal output, not just the diagnosis name
Does feeling better establish disease control? A useful response has an appropriate endpoint. Compare three patients and predict which measurement should improve if secretion is suppressed.
Output control and the work that remains
Clinical setting
Expected response
Still needed
Clinical settingPersistent acromegaly
Expected responseLower GH and age-adjusted IGF-1
Still neededPituitary assessment and management of associated disease
Clinical settingCarcinoid syndrome
Expected responseLess flushing and diarrhea
Still neededTumor staging and a disease-specific treatment plan
Clinical settingVIPoma
Expected responseLess watery stool and reduced electrolyte losses
Still neededFluid and electrolyte replacement and tumor treatment
For acromegaly, transsphenoidal surgery is preferred when a pituitary adenoma is appropriately resectable. A somatostatin receptor ligand is useful for persistent disease after surgery or when surgery is unsuitable. Judge response with GH, age-adjusted IGF-1, symptoms and appropriate imaging, not headache alone. After surgery, IGF-1 can decline slowly; assess it at least 12 weeks later when judging persistent disease. Use consistent assays when possible. [3]
For example, an IGF-1 of 480 ng/mL with an age-adjusted laboratory range of 80 to 240 ng/mL remains twice the upper limit even if sweating improves. That is partial clinical improvement, not biochemical normalization. Conversely, persistent sleep apnea can need its own treatment even after biochemical control. [3]
Carcinoid syndrome can respond through reduced mediator release. VIPoma produces profuse watery diarrhea, often with hypokalemia and reduced gastric acid secretion. Octreotide can suppress VIP-mediated output, but severe dehydration and potassium loss need simultaneous correction. Receptor responsiveness varies, and a poor response should prompt reassessment rather than reflexive dose escalation. [1]
Which result proves a tumor is gone?
Neither improved stool frequency nor reduced hormone levels proves eradication. They assess output; tumor burden requires its own assessment.
There is an important qualification: octreotide is not merely a symptom drug in every tumor setting. In PROMID, 85 patients with well-differentiated metastatic midgut neuroendocrine tumors were randomized to octreotide LAR or placebo. Median time to progression was 14.3 versus 6 months, with a progression hazard ratio of 0.34 and a 95% confidence interval of 0.20 to 0.59. The overall-survival hazard ratio was 0.81 with a 95% confidence interval of 0.30 to 2.18, which includes 1. This supports an antiproliferative effect in that selected population, not universal tumor shrinkage, cure or a confirmed survival benefit from that report. The US labels describe secretory indications and their own evidence limitations. [5][4]
Apply the output distinction to a patient whose diarrhea improves but liver lesions enlarge: symptom benefit and tumor progression can coexist. Oncology reassessment remains necessary. Selected refractory secretory diarrheal states may receive specialist off-label treatment, but undifferentiated acute diarrhea is not an automatic indication for octreotide.
The therapeutic inhibition can explain a new illness
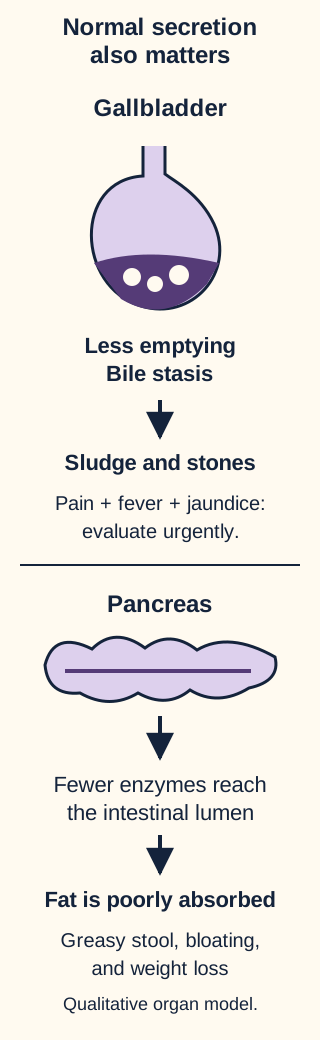
Could a drug prescribed for diarrhea cause a different diarrhea? Yes. Suppressing pathologic secretion can help, while suppressing normal pancreatic enzyme and bile secretion can impair digestion. The digestive-output diagram separates watery secretory loss from greasy, poorly absorbed stool. New steatorrhea, bloating or weight loss warrants assessment for pancreatic exocrine insufficiency rather than automatic treatment as tumor breakthrough. [1][4]
Compare biliary pain with fever or jaundice against greasy stool with weight loss. The purpose is to distinguish obstructive complications from impaired digestion during therapy, rather than interpreting every new stool symptom as tumor recurrence. [1][4]
Reduced gallbladder contractility and bile secretion also favor biliary stasis, sludge and gallstones. Complications include cholecystitis, duct obstruction, cholangitis and pancreatitis. Fever with right upper quadrant pain and jaundice is an urgent obstructive-infectious pattern, not a harmless expected injection effect. If complications of cholelithiasis are suspected, the labels advise discontinuing octreotide and treating appropriately. [1][4]
Predict glucose in two directions
Octreotide can inhibit insulin, glucagon and GH. Insulin suppression tends to raise glucose; reduced glucagon or GH effects can reduce glucose availability or insulin resistance. The net response depends on the disease, remaining pancreatic function and concurrent therapy. Both hypoglycemia and hyperglycemia are possible. A glucose rise does not rule out an octreotide effect. [1]
Compare two concrete observations: a patient needs less injected insulin as GH excess improves; another develops hyperglycemia after treatment begins. Predict the dominant balance in each, then check the explanation: the first may have less insulin resistance, while the second may have insufficient endogenous insulin secretion. These are qualitative explanations, not a calculator for insulin adjustment. Measure the actual glucose and adjust treatment clinically.
Does the same dose guarantee the same glucose response?
No. The balance of insulin secretion, counter-regulatory hormones, food intake and diabetes therapy differs between patients. Recheck glucose when treatment starts or the dose changes.
Bradycardia, atrioventricular conduction abnormalities and arrhythmias have been reported. Beta blockers such as metoprolol can add to the slow-pulse effect. Syncope with a pulse of 38/min after initiation requires prompt ECG assessment and clinical treatment, including review of all rate-slowing drugs; a temporal association is important but does not exclude other causes. Consider cardiac monitoring for intravenous treatment because higher-degree atrioventricular block has been reported. [1]
The injection label reports bradycardia in 25%, conduction abnormalities in 10%, hyperglycemia in 16% and hypoglycemia in 3% of studied patients with acromegaly. These are population-specific observations, not predicted rates for a brief variceal infusion, and underlying cardiac disease can complicate attribution. Transfer that caution to any adverse-event percentage: first ask which patients and exposure produced it. [1]
Match duration and surveillance to the formulation
Does “longer acting than somatostatin” mean every octreotide product lasts a month? Natural somatostatin has a plasma half-life of about 1 to 3 minutes; octreotide injection has a half-life of about 1.7 to 1.9 hours. A depot formulation achieves prolonged delivery by releasing drug over time. Product and route therefore matter as much as the molecule's name. [1]
Short-acting solution: subcutaneous or intravenous use. Acute variceal treatment uses a monitored intravenous regimen, commonly for 2 to 5 days under the treating protocol. It is not a substitute for secondary prevention. [2]
Sandostatin LAR Depot: gluteal intramuscular maintenance injections at 4-week intervals after response and tolerance to short-acting therapy are established. It is not administered intravenously and is not an emergency substitute. This description concerns this named depot product, not every octreotide formulation. [4]
For carcinoid syndrome and VIPoma, the LAR label calls for continuing the prior subcutaneous treatment for at least 2 weeks after the first depot injection; some patients need longer overlap. Without it, symptoms may recur before therapeutically effective levels are reached. Do not automatically apply that overlap rule to every acromegaly transition. [4]
Predict why diarrhea might recur a few days after an abrupt switch despite months of prior benefit. The immediate interpretation should include inadequate coverage during depot initiation, not only drug resistance. Now transfer this to an acute bleed: a monthly intramuscular product cannot replace a titratable emergency regimen.
Surveillance follows the suppressed system:
Glucose: check at initiation, dose changes and during ongoing treatment; reassess insulin and other glucose-lowering therapy.
Hormonal benefit: GH and IGF-1 for acromegaly; symptom pattern and appropriate biochemical markers such as VIP or urinary 5-HIAA for secretory tumors.
Thyroid and nutrition: baseline and periodic TSH with total or free T4 during chronic treatment; monitor vitamin B12 and investigate malabsorption.
Biliary and cardiac safety: periodic gallbladder assessment with prompt evaluation of symptoms; review pulse, ECG and concurrent medication according to risk and route.
TSH suppression can contribute to hypothyroidism, so a TSH result alone may not answer the question when free T4 is low. Routine surveillance and urgent symptom evaluation serve different purposes. [1][4]
Octreotide can reduce cyclosporine blood concentrations through altered absorption. Monitor drug levels and coordinate adjustment with the transplant team. A concentration change is a drug-exposure finding, not evidence that the transplant needs less immunosuppression. [1][4]
Why check exposure when the prescribed dose is unchanged?
The swallowed dose and the absorbed amount are not identical. A new interacting treatment can lower a previously adequate drug concentration without any missed dose.
Other interactions include increased bromocriptine availability and additive bradycardia with rate-slowing drugs. Somatostatin receptor binding can interfere with lutetium Lu 177 dotatate therapy; specialist scheduling uses formulation-specific withholding intervals, at least 24 hours for short-acting injection and 4 weeks for LAR according to these labels. Do not interchange the intervals. [1][4]
Ask what remains untreated
Which patient needs an immediate new plan: one with stable surveillance, one with mild asymptomatic hyperglycemia, one with fever and jaundice, or one with complete heart block? Rank the examples before reading the comparison.
Complete heart block requires immediate monitored assessment and treatment. Fever and jaundice require urgent evaluation for biliary infection and obstruction. Mild hyperglycemia needs timely review and adjustment but is not equivalent to those emergencies; stable findings support continued planned surveillance. Severity and physiology determine urgency, not simply whether an adverse effect appears on a list. [1]
Return to the bleeding patient who has recovered after ligation and short-course octreotide. The infusion has not abolished portal hypertension. Secondary prophylaxis generally combines a nonselective beta blocker and repeat endoscopic ligation when tolerated; TIPS and other decisions depend on the patient's course. Chronic octreotide is not the routine replacement for this plan. [2]
Return to the patient with several days of uncomplicated diarrhea after sick contacts. There is no established hormone-secreting disorder to target. Rehydration and cause-appropriate care take priority; the systemic effects and treatment burden of octreotide are not justified by diarrhea alone. A known secretory syndrome with dehydration, by contrast, needs both output control and replacement of what has already been lost.
State the treatment boundary in one sentence
Use octreotide to suppress a harmful output while separately treating its cause and monitoring the normal functions suppressed with it.
For a new situation, name the abnormal output, predict the benefit, identify one plausible harm, and specify the care that octreotide does not replace. Then attempt the independent cases without relying on section titles.
Independent clinical practice
Case 1
Show answer and explanations for case 1
A. Intravenous octreotide with antibiotics after positive cultures (Why this does not fit)
Octreotide appropriately reduces splanchnic inflow before endoscopy. Waiting for positive cultures mistakes prophylaxis for infection treatment and omits a parallel intervention.
Reasoning steps for option A
What can octreotide accomplish before endoscopy?
Octreotide appropriately reduces splanchnic inflow before endoscopy.
Why is waiting for positive cultures inappropriate here?
Waiting for positive cultures mistakes prophylaxis for infection treatment and omits a parallel intervention.
B. Intravenous proton pump inhibitor plus antibiotic prophylaxis (Why this does not fit)
A proton pump inhibitor may be started for an undifferentiated upper gastrointestinal bleed. This combination lacks a vasoactive agent despite the substantial variceal risk; acid suppression does not replace portal-inflow reduction.
Reasoning steps for option B
Where can acid suppression fit in an undifferentiated bleed?
A proton pump inhibitor may be started for an undifferentiated upper gastrointestinal bleed.
Does this plan address the suspected portal hypertensive source?
This combination lacks a vasoactive agent despite the substantial variceal risk; acid suppression does not replace portal-inflow reduction.
C. Antibiotic prophylaxis with octreotide after visualization (Why this does not fit)
Antibiotic prophylaxis is indicated in cirrhotic gastrointestinal bleeding. The same presentation is sufficient to start vasoactive therapy now rather than waiting four hours for visual proof.
Reasoning steps for option C
Why start antibiotic prophylaxis in this presentation?
Antibiotic prophylaxis is indicated in cirrhotic gastrointestinal bleeding.
Should the vasoactive drug await visual confirmation?
The same presentation is sufficient to start vasoactive therapy now rather than waiting four hours for visual proof.
D. Intravenous octreotide plus antibiotic prophylaxis (Best answer)
Cirrhosis with hematemesis warrants early treatment for suspected variceal hemorrhage. Normal temperature and leukocytes do not eliminate the indication for antibiotic prophylaxis; neither component should await endoscopy.
Reasoning steps for option D
What makes a variceal source sufficiently likely to treat?
Cirrhosis with hematemesis warrants early treatment for suspected variceal hemorrhage.
Do normal temperature and leukocytes remove the prophylaxis indication?
Normal temperature and leukocytes do not eliminate the indication for antibiotic prophylaxis; neither component should await endoscopy.
Takeaway: Suspected variceal hemorrhage needs early vasoactive therapy and infection prophylaxis even without overt infection.
A. Observe and reassess without another unit now (Best answer)
The patient has stable perfusion and hemoglobin within the Baveno VII target of approximately 7 to 8 g/dL. Further red cells are not indicated solely to normalize the count; reassess if bleeding or ischemia develops.
Reasoning steps for option A
How does 7.6 g/dL compare with the recommended target?
The patient has stable perfusion and hemoglobin within the Baveno VII target of approximately 7 to 8 g/dL.
What should happen while perfusion and hemoglobin remain stable?
Further red cells are not indicated solely to normalize the count; reassess if bleeding or ischemia develops.
B. Transfuse to maintain hemoglobin above 9 g/dL (Why this does not fit)
More liberal thresholds may be selected for cardiovascular disease or ongoing instability. Neither condition is supplied, so this higher target is not justified by the current measurements.
Reasoning steps for option B
What could justify a higher transfusion target?
More liberal thresholds may be selected for cardiovascular disease or ongoing instability.
Is that justification present in the supplied findings?
Neither condition is supplied, so this higher target is not justified by the current measurements.
C. Transfuse to a hemoglobin of 10 g/dL (Why this does not fit)
Anemia can impair oxygen delivery when perfusion or cardiac reserve is inadequate. Those modifiers are absent here; a target of 10 g/dL adds unnecessary volume beyond the recommended restrictive range.
Reasoning steps for option C
When might anemia require a more liberal transfusion approach?
Anemia can impair oxygen delivery when perfusion or cardiac reserve is inadequate.
Does this patient have the modifiers needed for that target?
Those modifiers are absent here; a target of 10 g/dL adds unnecessary volume beyond the recommended restrictive range.
D. Transfuse one more unit to prevent early rebleeding (Why this does not fit)
Patients remain at risk of rebleeding after successful ligation. Extra red cells are not secondary prophylaxis and may increase portal pressure; prevention requires an appropriate portal-hypertension plan.
Reasoning steps for option D
Does successful ligation eliminate rebleeding risk?
Patients remain at risk of rebleeding after successful ligation.
Does an extra unit serve as recurrence prevention?
Extra red cells are not secondary prophylaxis and may increase portal pressure; prevention requires an appropriate portal-hypertension plan.
Takeaway: Use clinical stability and an individualized restrictive target rather than transfusing to a normal hemoglobin.
A. Proceed with moderate sedation and nasal oxygen (Why this does not fit)
Prompt endoscopy is needed once the patient is resuscitated. Active vomiting and inability to handle secretions create aspiration risk that oxygen and moderate sedation do not correct.
Reasoning steps for option A
Why is timely endoscopy important?
Prompt endoscopy is needed once the patient is resuscitated.
Does oxygen with sedation protect this particular airway?
Active vomiting and inability to handle secretions create aspiration risk that oxygen and moderate sedation do not correct.
B. Intubate for airway protection, then perform endoscopy (Best answer)
Blood pressure has improved but ongoing hematemesis and impaired consciousness threaten airway protection. Intubation before endoscopy addresses that risk while the vasoactive and definitive bleeding treatments proceed.
Reasoning steps for option B
Which threat persists after blood pressure improves?
Blood pressure has improved but ongoing hematemesis and impaired consciousness threaten airway protection.
How can definitive treatment proceed with that threat addressed?
Intubation before endoscopy addresses that risk while the vasoactive and definitive bleeding treatments proceed.
C. Give erythromycin and proceed without intubation (Why this does not fit)
Erythromycin can improve gastric visualization before urgent endoscopy. It does not restore protective airway reflexes in a drowsy patient vomiting blood.
Reasoning steps for option C
Why might erythromycin be useful before endoscopy?
Erythromycin can improve gastric visualization before urgent endoscopy.
Does better visualization restore protective airway reflexes?
It does not restore protective airway reflexes in a drowsy patient vomiting blood.
D. Delay endoscopy until lactulose restores alertness (Why this does not fit)
Encephalopathy treatment can improve mental status in cirrhosis. Waiting for that response leaves ongoing hemorrhage untreated; airway protection permits urgent definitive care.
Reasoning steps for option D
What can treating encephalopathy accomplish?
Encephalopathy treatment can improve mental status in cirrhosis.
Can treatment of active hemorrhage await that response?
Waiting for that response leaves ongoing hemorrhage untreated; airway protection permits urgent definitive care.
Takeaway: Restored blood pressure does not resolve aspiration risk during ongoing hematemesis and impaired consciousness.
A. Thermal coagulation of the bleeding point (Why this does not fit)
Thermal treatment is used for selected nonvariceal bleeding lesions. A large fundal venous channel without an ulcer requires varix-directed therapy rather than treating it as an ulcer vessel.
Reasoning steps for option A
For what kind of bleeding source is thermal therapy used?
Thermal treatment is used for selected nonvariceal bleeding lesions.
Does the supplied lesion fit that source?
A large fundal venous channel without an ulcer requires varix-directed therapy rather than treating it as an ulcer vessel.
B. Mechanical clips across the bleeding point (Why this does not fit)
Clips can control selected focal nonvariceal bleeding sites. The supplied lesion is a large fundal varix, for which tissue adhesive is the guideline-supported choice among these options.
Reasoning steps for option B
What bleeding pattern can be treated with clips?
Clips can control selected focal nonvariceal bleeding sites.
Which feature instead favors tissue adhesive here?
The supplied lesion is a large fundal varix, for which tissue adhesive is the guideline-supported choice among these options.
C. Cyanoacrylate injection into the fundal varix (Best answer)
The endoscopic anatomy identifies a cardiofundal gastric varix rather than an esophageal varix or ulcer. Cyanoacrylate is recommended for this source when suitable expertise is available, alongside the already-started acute treatment.
Reasoning steps for option C
Where has the bleeding been localized?
The endoscopic anatomy identifies a cardiofundal gastric varix rather than an esophageal varix or ulcer.
Which available treatment fits that location?
Cyanoacrylate is recommended for this source when suitable expertise is available, alongside the already-started acute treatment.
D. Band ligation of the fundal venous column (Why this does not fit)
Band ligation is preferred for acute esophageal variceal hemorrhage. The fundal location changes the treatment choice; an esophageal recommendation should not be transferred unchanged.
Reasoning steps for option D
Which variceal location favors band ligation?
Band ligation is preferred for acute esophageal variceal hemorrhage.
Is that the location described in this patient?
The fundal location changes the treatment choice; an esophageal recommendation should not be transferred unchanged.
Takeaway: Localize the bleeding varix before choosing definitive endoscopic therapy.
A. Repeat banding alone during the next outpatient visit (Why this does not fit)
Serial ligation forms part of secondary prevention for many patients. It does not address the current preemptive-TIPS indication associated with the score of 11.
Reasoning steps for option A
What is the usual role of serial ligation?
Serial ligation forms part of secondary prevention for many patients.
Which present risk is not addressed by an outpatient-only plan?
It does not address the current preemptive-TIPS indication associated with the score of 11.
B. Decompression assessment only after another hemorrhage (Why this does not fit)
Salvage TIPS is used when combined therapy fails to control bleeding. This patient also meets a preemptive indication while stable, so waiting for recurrence misses that opportunity.
Reasoning steps for option B
When is salvage TIPS appropriate?
Salvage TIPS is used when combined therapy fails to control bleeding.
Why is waiting for failure insufficient in this patient?
This patient also meets a preemptive indication while stable, so waiting for recurrence misses that opportunity.
C. Assessment for covered TIPS within 72 hours (Best answer)
Child-Pugh C scores 10 to 13 meet the Baveno VII high-risk criterion after variceal bleeding. Successful banding does not negate that risk; arrange specialist assessment for preemptive TIPS, ideally within 24 hours.
Reasoning steps for option C
What does the Child-Pugh score identify?
Child-Pugh C scores 10 to 13 meet the Baveno VII high-risk criterion after variceal bleeding.
Does initial hemostasis remove the preemptive indication?
Successful banding does not negate that risk; arrange specialist assessment for preemptive TIPS, ideally within 24 hours.
D. Continuation of octreotide until varices are eradicated (Why this does not fit)
Octreotide reduces portal inflow during the acute episode. An extended infusion is not the recommended replacement for high-risk assessment and definitive decompression planning.
Reasoning steps for option D
What benefit does the acute infusion provide?
Octreotide reduces portal inflow during the acute episode.
Can prolonged infusion replace the high-risk assessment?
An extended infusion is not the recommended replacement for high-risk assessment and definitive decompression planning.
A. Continue the infusion, then assess for preemptive TIPS within 72 hours (Why this does not fit)
Preemptive TIPS is considered early for eligible high-risk patients even when initial hemostasis succeeds. This patient has uncontrolled hemorrhage now; a prevention-oriented timetable without immediate control misclassifies active treatment failure.
Reasoning steps for option A
What problem does preemptive TIPS address?
Preemptive TIPS is considered early for eligible high-risk patients even when initial hemostasis succeeds.
Does the current bleeding state fit a prevention-only plan?
This patient has uncontrolled hemorrhage now; a prevention-oriented timetable without immediate control misclassifies active treatment failure.
B. Change the vasoactive infusion, observe for 12 hours, then repeat ligation (Why this does not fit)
A different vasoactive agent and repeat endoscopic therapy can be considered in selected courses. Here combined treatment has already failed with continuing shock and failed repeat access, so another observation period does not address the need for salvage control.
Reasoning steps for option B
When can ongoing pharmacological and endoscopic reassessment be reasonable?
A different vasoactive agent and repeat endoscopic therapy can be considered in selected courses.
What makes another observation interval unsafe in this episode?
Here combined treatment has already failed with continuing shock and failed repeat access, so another observation period does not address the need for salvage control.
C. Obtain temporary esophageal control, then continue banding-based prevention alone (Why this does not fit)
Temporary mechanical control can arrest otherwise uncontrolled esophageal bleeding. After combined-treatment failure it is a bridge, not a reason to abandon urgent definitive decompression once the patient is stabilized.
Reasoning steps for option C
What useful immediate effect can a stent or balloon have?
Temporary mechanical control can arrest otherwise uncontrolled esophageal bleeding.
Does that temporary response replace salvage planning?
After combined-treatment failure it is a bridge, not a reason to abandon urgent definitive decompression once the patient is stabilized.
D. Obtain temporary esophageal control, then proceed to urgent salvage TIPS (Best answer)
Continued hemorrhage and recurrent shock after combined therapy constitute failure to control the bleed. An esophageal covered stent or balloon can provide temporary control while salvage TIPS provides definitive decompression.
Reasoning steps for option D
Which treatment phase follows failure to achieve hemostasis?
Continued hemorrhage and recurrent shock after combined therapy constitute failure to control the bleed.
How should temporary mechanical control connect to definitive treatment?
An esophageal covered stent or balloon can provide temporary control while salvage TIPS provides definitive decompression.
Takeaway: Uncontrolled bleeding after combined therapy needs temporary local control followed by salvage decompression, not a prevention-only plan.
A. Nonselective beta blockade plus scheduled repeat ligation (Best answer)
The patient is stable and has no supplied contraindication to nonselective beta blockade. Combining it with serial ligation addresses recurrence risk after the short vasoactive course ends.
Reasoning steps for option A
Is a nonselective beta blocker feasible from the supplied data?
The patient is stable and has no supplied contraindication to nonselective beta blockade.
How should it be combined with endoscopic treatment?
Combining it with serial ligation addresses recurrence risk after the short vasoactive course ends.
B. Selective beta-1 blockade plus scheduled repeat ligation (Why this does not fit)
Beta-1 blockade can lower cardiac output and may be prescribed for other cardiac indications. Guideline secondary prophylaxis uses nonselective beta blockade, not substitution with a purely beta-1-selective drug.
Reasoning steps for option B
What action does selective beta-1 blockade provide?
Beta-1 blockade can lower cardiac output and may be prescribed for other cardiac indications.
Does that make it the recommended substitute in this setting?
Guideline secondary prophylaxis uses nonselective beta blockade, not substitution with a purely beta-1-selective drug.
C. Repeat ligation without pharmacological portal-pressure reduction (Why this does not fit)
Ligation is an important component of secondary prevention. When a nonselective beta blocker is tolerated, combination therapy is preferred to ligation alone.
Reasoning steps for option C
How does ligation contribute to recurrence prevention?
Ligation is an important component of secondary prevention.
What additional therapy is appropriate when tolerated?
When a nonselective beta blocker is tolerated, combination therapy is preferred to ligation alone.
D. Monthly octreotide depot with endoscopy only for recurrent symptoms (Why this does not fit)
Depot octreotide provides maintenance control for selected endocrine and secretory indications. It is not routine secondary prophylaxis for variceal hemorrhage and does not replace scheduled eradication therapy.
Reasoning steps for option D
For which treatment role is a depot useful?
Depot octreotide provides maintenance control for selected endocrine and secretory indications.
Does that role include routine variceal secondary prevention?
It is not routine secondary prophylaxis for variceal hemorrhage and does not replace scheduled eradication therapy.
Takeaway: After the acute course, secondary prevention is not repeated or indefinite octreotide therapy.
A. 20 mmHg; proceed with definitive local hemostasis (Why this does not fit)
The initial model gradient is 1,000 multiplied by 0.020 = 20 mmHg, and local hemostasis is still needed. Keeping the old gradient ignores the measured reduction in flow while resistance is held constant.
Reasoning steps for option A
Which measurement produces 20 mmHg?
The initial model gradient is 1,000 multiplied by 0.020 = 20 mmHg, and local hemostasis is still needed.
How does the new flow change the prediction?
Keeping the old gradient ignores the measured reduction in flow while resistance is held constant.
B. 15 mmHg; proceed with definitive local hemostasis (Best answer)
The simplified relation gives 750 multiplied by 0.020 = 15 mmHg, compared with 20 mmHg initially. The lower gradient is not proof that the varix is closed, so local treatment remains necessary; this model is not a clinical risk calculator.
Reasoning steps for option B
What gradient follows from the new flow at fixed resistance?
The simplified relation gives 750 multiplied by 0.020 = 15 mmHg, compared with 20 mmHg initially.
Does that number establish closure of the bleeding vessel?
The lower gradient is not proof that the varix is closed, so local treatment remains necessary; this model is not a clinical risk calculator.
C. 15 mmHg; defer local treatment because the gradient has fallen (Why this does not fit)
The numerical prediction is correct under the stated fixed-resistance assumption. The inference about treatment is not: an improved modeled gradient does not establish durable hemostasis of the untreated varix.
Reasoning steps for option C
Is the pressure calculation correct?
The numerical prediction is correct under the stated fixed-resistance assumption.
What separate fact is needed before concluding that the bleeding source is controlled?
The inference about treatment is not: an improved modeled gradient does not establish durable hemostasis of the untreated varix.
D. 20 mmHg; defer local treatment while awaiting a pressure response (Why this does not fit)
A pressure response can be monitored during vasoactive treatment. The model already predicts 15 rather than 20 mmHg, and waiting for a drug response is not a substitute for treating the bleeding source.
Reasoning steps for option D
What response has the model already predicted?
A pressure response can be monitored during vasoactive treatment.
Should definitive treatment wait for a further drug effect?
The model already predicts 15 rather than 20 mmHg, and waiting for a drug response is not a substitute for treating the bleeding source.
Takeaway: A modeled pressure reduction from lower inflow does not establish local hemostasis or eliminate the need for endoscopy.
A. A: pituitary secretion suppression; B: pituitary secretion suppression (Why this does not fit)
Pituitary secretion suppression explains the falls in GH and IGF-1 with A. The normalization of IGF-1 without reduced GH in B is better explained by inhibition of peripheral GH action, not by the same demonstrated secretory response.
Reasoning steps for option A
Does an upstream secretory effect fit A?
Pituitary secretion suppression explains the falls in GH and IGF-1 with A.
Which feature of B requires a different site-of-action explanation?
The normalization of IGF-1 without reduced GH in B is better explained by inhibition of peripheral GH action, not by the same demonstrated secretory response.
B. A: peripheral GH receptor blockade; B: peripheral GH receptor blockade (Why this does not fit)
Peripheral blockade fits B because IGF-1 normalizes while GH remains high. Assigning the same target to A does not best account for its clear fall in upstream GH; pituitary secretion suppression better explains that trajectory.
Reasoning steps for option B
Which patient fits peripheral action blockade?
Peripheral blockade fits B because IGF-1 normalizes while GH remains high.
What additional response in A favors an upstream target?
Assigning the same target to A does not best account for its clear fall in upstream GH; pituitary secretion suppression better explains that trajectory.
C. A: peripheral GH receptor blockade; B: pituitary secretion suppression (Why this does not fit)
Peripheral blockade can lower IGF-1 without requiring reduced GH, whereas pituitary suppression reduces the GH supply. Those expected relationships are assigned to the wrong patients: A has the concordant fall and B the downstream-only normalization.
Reasoning steps for option C
How do the two sites ordinarily differ in their hormone responses?
Peripheral blockade can lower IGF-1 without requiring reduced GH, whereas pituitary suppression reduces the GH supply.
Which patient shows each of those patterns?
Those expected relationships are assigned to the wrong patients: A has the concordant fall and B the downstream-only normalization.
The concordant decrease in GH and IGF-1 with A is consistent with reducing hormone release upstream. In B, normal IGF-1 despite persistent GH fits peripheral action blockade; clinical follow-up on such therapy uses IGF-1 rather than requiring GH suppression.
Reasoning steps for option D
Where does the concordant A response place the inhibitory effect?
The concordant decrease in GH and IGF-1 with A is consistent with reducing hormone release upstream.
Where can inhibition lower IGF-1 without suppressing GH in B?
In B, normal IGF-1 despite persistent GH fits peripheral action blockade; clinical follow-up on such therapy uses IGF-1 rather than requiring GH suppression.
Takeaway: Concordant versus discordant GH and IGF-1 responses help distinguish reduced secretion from reduced peripheral hormone action.
A. Judge hormonal nonresponse by the unchanged MRI despite falling IGF-1 (Why this does not fit)
MRI monitors the anatomical response of the pituitary lesion. Unchanged size does not establish hormonal nonresponse because the measured IGF-1 has fallen substantially.
Reasoning steps for option A
What domain does the MRI assess?
MRI monitors the anatomical response of the pituitary lesion.
Does that anatomical result invalidate the observed hormone response?
Unchanged size does not establish hormonal nonresponse because the measured IGF-1 has fallen substantially.
B. Judge residual activity by elevated IGF-1 despite the symptomatic benefit (Best answer)
The fall from 650 to 320 ng/mL indicates benefit, but 320 remains above the same-assay age-adjusted range. Persistent biochemical activity warrants treatment reassessment independently of symptoms and the unchanged tumor size.
Reasoning steps for option B
How do both the trend and the reference range affect interpretation?
The fall from 650 to 320 ng/mL indicates benefit, but 320 remains above the same-assay age-adjusted range.
Which aspect of disease control still needs reassessment?
Persistent biochemical activity warrants treatment reassessment independently of symptoms and the unchanged tumor size.
C. Judge normalization by the relative IGF-1 decrease rather than its range (Why this does not fit)
A large relative decrease shows a meaningful directional biochemical response. Normalization is determined against the age-adjusted reference interval, not by reaching a chosen percentage reduction from a high baseline.
Reasoning steps for option C
What does a substantial relative decrease establish?
A large relative decrease shows a meaningful directional biochemical response.
How is normalization distinguished from improvement?
Normalization is determined against the age-adjusted reference interval, not by reaching a chosen percentage reduction from a high baseline.
D. Judge control by symptomatic improvement despite residual IGF-1 elevation (Why this does not fit)
Improved symptoms show a clinically useful response. They do not establish biochemical normalization while IGF-1 remains above the age-adjusted upper limit of 240 ng/mL.
Reasoning steps for option D
What does the symptom response demonstrate?
Improved symptoms show a clinically useful response.
Does it establish that the remaining hormone elevation is controlled?
They do not establish biochemical normalization while IGF-1 remains above the age-adjusted upper limit of 240 ng/mL.
Takeaway: A substantial hormone decrease can represent benefit without meeting the age-adjusted biochemical target.
A. Escalate pituitary therapy for biochemical nonresponse while continuing imaging (Why this does not fit)
Pituitary-directed treatment can be needed for persistent secretory disease or tumor concerns. The normal IGF-1 supports biochemical response to peripheral blockade, and the supplied higher GH alone does not establish a need for that escalation.
Reasoning steps for option A
When might additional pituitary-directed treatment be needed?
Pituitary-directed treatment can be needed for persistent secretory disease or tumor concerns.
Does this GH result establish biochemical nonresponse to the current target?
The normal IGF-1 supports biochemical response to peripheral blockade, and the supplied higher GH alone does not establish a need for that escalation.
B. Assess biochemical control with IGF-1 while continuing separate imaging (Best answer)
Pegvisomant reduces peripheral GH action rather than requiring suppression of pituitary GH secretion. The normal age-adjusted IGF-1 supports biochemical control; anatomical surveillance remains a separate treatment responsibility.
Reasoning steps for option B
Which step in the hormone axis is inhibited now?
Pegvisomant reduces peripheral GH action rather than requiring suppression of pituitary GH secretion.
Which endpoint measures its biochemical effect while imaging continues?
The normal age-adjusted IGF-1 supports biochemical control; anatomical surveillance remains a separate treatment responsibility.
C. Assess control primarily with symptoms and glucose while continuing imaging (Why this does not fit)
Symptoms and glycemia are important measures of treatment benefit and associated disease. They do not replace the available age-adjusted IGF-1 for biochemical assessment on pegvisomant.
Reasoning steps for option C
Why continue assessing symptoms and glucose?
Symptoms and glycemia are important measures of treatment benefit and associated disease.
Do those observations replace the specific biochemical endpoint?
They do not replace the available age-adjusted IGF-1 for biochemical assessment on pegvisomant.
D. Escalate GH-action blockade to normalize GH while continuing imaging (Why this does not fit)
A high GH concentration can indicate active disease during some acromegaly treatments. It is not the biochemical target for pegvisomant, so escalation based solely on GH despite normal IGF-1 applies the wrong endpoint.
Reasoning steps for option D
When might GH be useful in acromegaly follow-up?
A high GH concentration can indicate active disease during some acromegaly treatments.
Does that target remain appropriate during pegvisomant treatment?
It is not the biochemical target for pegvisomant, so escalation based solely on GH despite normal IGF-1 applies the wrong endpoint.
Takeaway: During peripheral GH receptor blockade, IGF-1 is the biochemical endpoint rather than a requirement for GH suppression.
A. Begin octreotide and defer surgical review until IGF-1 normalizes (Why this does not fit)
Octreotide can suppress GH and sometimes reduce tumor size. The supplied progressive visual deficit and resectability make deferral of indicated surgical assessment inappropriate.
Reasoning steps for option A
What benefit could octreotide provide?
Octreotide can suppress GH and sometimes reduce tumor size.
What makes waiting for that benefit inappropriate here?
The supplied progressive visual deficit and resectability make deferral of indicated surgical assessment inappropriate.
B. Plan radiation as the first treatment while observing the visual fields (Why this does not fit)
Radiation can be used for selected persistent acromegaly when other options are inadequate. It is not the preferred initial strategy for an operable tumor with progressive compression requiring timely evaluation.
Reasoning steps for option B
When can radiation have a role in acromegaly?
Radiation can be used for selected persistent acromegaly when other options are inadequate.
Why is it not the preferred initial strategy in this presentation?
It is not the preferred initial strategy for an operable tumor with progressive compression requiring timely evaluation.
C. Arrange transsphenoidal surgical management with endocrine care (Best answer)
The patient has an operable pituitary source of GH excess plus progressive mass-related visual loss. Surgical management offers source treatment and decompression; endocrine monitoring and treatment remain necessary afterward.
Reasoning steps for option C
Which two problems arise from this operable tumor?
The patient has an operable pituitary source of GH excess plus progressive mass-related visual loss.
Which strategy can address both while preserving follow-up?
Surgical management offers source treatment and decompression; endocrine monitoring and treatment remain necessary afterward.
D. Begin pegvisomant and use IGF-1 to judge chiasmal decompression (Why this does not fit)
Pegvisomant can lower IGF-1 through peripheral GH receptor blockade. IGF-1 cannot establish decompression of a chiasm threatened by a resectable mass.
Reasoning steps for option D
Where does pegvisomant act?
Pegvisomant can lower IGF-1 through peripheral GH receptor blockade.
Can its biochemical endpoint establish chiasmal decompression?
IGF-1 cannot establish decompression of a chiasm threatened by a resectable mass.
Takeaway: When a resectable pituitary tumor threatens vision, biochemical suppression does not replace surgical assessment.
A. Classify the secretory treatment as ineffective because lesions grew (Why this does not fit)
Tumor progression shows that disease control is insufficient in one domain. It does not invalidate the measured decrease in flushing and diarrhea, which may remain worth preserving during reassessment.
Reasoning steps for option A
Which treatment domain is insufficiently controlled?
Tumor progression shows that disease control is insufficient in one domain.
Does that erase the benefit in the secretory domain?
It does not invalidate the measured decrease in flushing and diarrhea, which may remain worth preserving during reassessment.
B. Classify the imaging change as controlled disease because symptoms improved (Why this does not fit)
Symptom reduction is a meaningful therapeutic outcome in a secretory syndrome. It cannot override documented growth of metastases or serve as a substitute for imaging.
Reasoning steps for option B
Why does the symptom response matter?
Symptom reduction is a meaningful therapeutic outcome in a secretory syndrome.
Can it supersede documented growth of metastases?
It cannot override documented growth of metastases or serve as a substitute for imaging.
C. Retain the evidence of symptom benefit while reassessing tumor-directed care (Best answer)
Reduced flushing and stool frequency support useful suppression of secretory output. Radiographic progression is a separate endpoint and requires tumor-directed reassessment despite that benefit.
Reasoning steps for option C
What does the change in flushing and stool count demonstrate?
Reduced flushing and stool frequency support useful suppression of secretory output.
How should the separate imaging result affect the plan?
Radiographic progression is a separate endpoint and requires tumor-directed reassessment despite that benefit.
D. Use the lower stool count to reduce the frequency of tumor surveillance (Why this does not fit)
Symptoms can improve when octreotide reduces hormone release. Improvement is not a reliable substitute for tumor surveillance, especially when the current images already show progression.
Reasoning steps for option D
How can secretion change without eradication?
Symptoms can improve when octreotide reduces hormone release.
What does that imply for continued imaging?
Improvement is not a reliable substitute for tumor surveillance, especially when the current images already show progression.
Takeaway: Secretory benefit and radiographic tumor progression can coexist during octreotide treatment.
A. Restored pancreatic enzyme delivery; continue fluid and potassium replacement (Why this does not fit)
Restoring digestive enzyme delivery can improve diarrhea caused by pancreatic exocrine insufficiency. The original fasting-persistent watery pattern and response to a secretion inhibitor instead favor reduced secretory signaling, although continued replacement is appropriately recognized.
Reasoning steps for option A
Which type of diarrhea could improve with enzyme replacement?
Restoring digestive enzyme delivery can improve diarrhea caused by pancreatic exocrine insufficiency.
Does that mechanism fit this stool pattern and administered treatment?
The original fasting-persistent watery pattern and response to a secretion inhibitor instead favor reduced secretory signaling, although continued replacement is appropriately recognized.
B. Reduced hormone-driven secretion; transition from replacement to routine surveillance (Why this does not fit)
The fall in stool output is consistent with suppression of the harmful secretory signal. The supplied orthostasis and potassium of 2.8 show that recovery is incomplete, so routine surveillance is not enough yet.
Reasoning steps for option B
What does the stool response demonstrate?
The fall in stool output is consistent with suppression of the harmful secretory signal.
Do the other measurements establish that replacement is finished?
The supplied orthostasis and potassium of 2.8 show that recovery is incomplete, so routine surveillance is not enough yet.
C. Restored pancreatic enzyme delivery; transition from replacement to routine surveillance (Why this does not fit)
Enzyme replacement can help malabsorptive pancreatic disease once deficiencies are addressed. Octreotide suppresses rather than replaces normal digestive secretion, and the persistent orthostasis and hypokalemia also argue against ending replacement.
Reasoning steps for option C
Does octreotide restore digestive enzyme delivery?
Enzyme replacement can help malabsorptive pancreatic disease once deficiencies are addressed.
Are the remaining physiological deficits resolved?
Octreotide suppresses rather than replaces normal digestive secretion, and the persistent orthostasis and hypokalemia also argue against ending replacement.
D. Reduced hormone-driven secretion; continue fluid and potassium replacement (Best answer)
The fasting-persistent high-volume pattern and pancreatic mass support a hormone-mediated secretory syndrome responsive to octreotide. Lower output does not restore prior losses immediately; persistent orthostasis and low potassium require continued monitored replacement.
Reasoning steps for option D
Which diarrheal process fits the fasting pattern and rapid antisecretory response?
The fasting-persistent high-volume pattern and pancreatic mass support a hormone-mediated secretory syndrome responsive to octreotide.
What do the remaining blood pressure and potassium abnormalities require?
Lower output does not restore prior losses immediately; persistent orthostasis and low potassium require continued monitored replacement.
Takeaway: Suppression of a hormone-driven secretory output does not immediately correct accumulated fluid and electrolyte deficits.
A. Evaluate bile-duct obstruction as the primary stool problem (Why this does not fit)
Biliary obstruction can impair bile delivery and cause pale or fatty stools. Normal bilirubin and nondilated ducts make it less consistent with the supplied pattern than treatment-related digestive inhibition.
Reasoning steps for option A
How can obstruction change stool character?
Biliary obstruction can impair bile delivery and cause pale or fatty stools.
What do the biliary findings contribute to this comparison?
Normal bilirubin and nondilated ducts make it less consistent with the supplied pattern than treatment-related digestive inhibition.
B. Evaluate pancreatic exocrine insufficiency as the primary stool problem (Best answer)
Octreotide can inhibit pancreatic enzymes and bile acids and impair fat digestion. New oily stools, bloating and weight loss after dose escalation fit the label recommendation to assess exocrine insufficiency while not assuming the drug is the only possible cause.
Reasoning steps for option B
Which normal secretions can be inhibited along with tumor output?
Octreotide can inhibit pancreatic enzymes and bile acids and impair fat digestion.
How does the new phenotype guide the diagnostic priority?
New oily stools, bloating and weight loss after dose escalation fit the label recommendation to assess exocrine insufficiency while not assuming the drug is the only possible cause.
C. Evaluate recurrent mediator secretion as the primary stool problem (Why this does not fit)
Recurrent carcinoid mediator secretion can cause diarrhea during maintenance treatment. Here flushing remains controlled and the new bulky oily pattern favors malabsorption over recurrence of the prior secretory syndrome.
Reasoning steps for option C
Can the underlying tumor syndrome cause recurrent diarrhea?
Recurrent carcinoid mediator secretion can cause diarrhea during maintenance treatment.
Which features make a different mechanism more likely now?
Here flushing remains controlled and the new bulky oily pattern favors malabsorption over recurrence of the prior secretory syndrome.
D. Evaluate infectious enterocolitis as the primary stool problem (Why this does not fit)
An enteric infection is a common alternative cause of new diarrhea. The prominent oily bulky stools with weight loss and their relation to dose escalation more specifically suggest maldigestion; infection can be assessed if additional findings support it.
Reasoning steps for option D
Why keep an enteric infection in the broader differential?
An enteric infection is a common alternative cause of new diarrhea.
Which supplied features prioritize a digestive evaluation instead?
The prominent oily bulky stools with weight loss and their relation to dose escalation more specifically suggest maldigestion; infection can be assessed if additional findings support it.
Takeaway: New greasy stools during secretory control suggest impaired digestion rather than automatic tumor breakthrough.
A. Enteric infection; investigate pathogens and ongoing fluid losses (Why this does not fit)
An infection can cause recurrent watery stool and should be investigated when the clinical picture supports it. The supplied onset follows an avoidable formulation-coverage gap and reproduces the established secretory syndrome, making that gap the more direct explanation.
Reasoning steps for option A
Can infection produce watery diarrhea during treatment?
An infection can cause recurrent watery stool and should be investigated when the clinical picture supports it.
What temporal relationship makes the transition itself important here?
The supplied onset follows an avoidable formulation-coverage gap and reproduces the established secretory syndrome, making that gap the more direct explanation.
B. Receptor resistance; reassess tumor biology and secretory treatment (Why this does not fit)
Loss of receptor-mediated response can contribute to worsening secretory symptoms. The abrupt recurrence immediately after short-acting doses stop at depot initiation more directly points to an early exposure gap than newly demonstrated resistance.
Reasoning steps for option B
Could reduced receptor responsiveness impair control?
Loss of receptor-mediated response can contribute to worsening secretory symptoms.
Which recent treatment detail provides a more direct explanation here?
The abrupt recurrence immediately after short-acting doses stop at depot initiation more directly points to an early exposure gap than newly demonstrated resistance.
C. Early exposure gap; reinstate overlap during depot initiation (Best answer)
The first Sandostatin LAR injection does not immediately assure effective concentrations. In VIPoma and carcinoid syndrome, the label calls for at least two weeks of the prior subcutaneous regimen, sometimes longer, coordinated with the treating team.
Reasoning steps for option C
Is effective depot coverage immediate after the first injection?
The first Sandostatin LAR injection does not immediately assure effective concentrations.
What product-specific transition requirement addresses the gap?
In VIPoma and carcinoid syndrome, the label calls for at least two weeks of the prior subcutaneous regimen, sometimes longer, coordinated with the treating team.
D. Exocrine insufficiency; assess digestion and enzyme replacement (Why this does not fit)
Somatostatin analogs can suppress digestion, and exocrine insufficiency warrants evaluation and appropriate treatment. The returning high-volume watery pattern without oily stool, immediately after loss of short-acting coverage, favors inadequate early secretion control.
Reasoning steps for option D
What different diarrheal process can octreotide cause?
Somatostatin analogs can suppress digestion, and exocrine insufficiency warrants evaluation and appropriate treatment.
How does this phenotype and timing compare with that process?
The returning high-volume watery pattern without oily stool, immediately after loss of short-acting coverage, favors inadequate early secretion control.
Takeaway: Secretory-syndrome transitions to Sandostatin LAR require initial short-acting overlap.
A. Insulin suppression may outweigh the benefit of reduced GH activity (Best answer)
Octreotide can suppress insulin while reducing GH-related insulin resistance. If insufficient insulin secretion dominates, glucose can rise despite improvement in GH and IGF-1, so measure and reassess glycemic control.
Reasoning steps for option A
Which competing pancreatic and pituitary effects occur during therapy?
Octreotide can suppress insulin while reducing GH-related insulin resistance.
Which balance reconciles lower GH activity with higher glucose?
If insufficient insulin secretion dominates, glucose can rise despite improvement in GH and IGF-1, so measure and reassess glycemic control.
B. Glucagon suppression may increase hepatic glucose output (Why this does not fit)
Octreotide can inhibit glucagon secretion. Less glucagon tends to reduce rather than increase hepatic glucose output, so this proposed direction does not explain the observed rise.
Reasoning steps for option B
What can happen to glucagon secretion on treatment?
Octreotide can inhibit glucagon secretion.
Does that direction predict greater hepatic glucose output?
Less glucagon tends to reduce rather than increase hepatic glucose output, so this proposed direction does not explain the observed rise.
C. GH suppression may increase peripheral insulin resistance (Why this does not fit)
Excess GH contributes to insulin resistance in acromegaly. Reducing that excess tends to lessen its contribution rather than increase it; another drug effect is needed to reconcile the higher glucose.
Reasoning steps for option C
What is the metabolic effect of excess GH?
Excess GH contributes to insulin resistance in acromegaly.
What direction is expected when that contribution decreases?
Reducing that excess tends to lessen its contribution rather than increase it; another drug effect is needed to reconcile the higher glucose.
D. Glucagon stimulation may be a direct pancreatic drug effect (Why this does not fit)
Increased glucagon would provide a physiological route to higher hepatic glucose output. Octreotide is a suppressor rather than a direct stimulator of glucagon release, so this does not describe its recognized pancreatic action.
Reasoning steps for option D
Could increased glucagon raise glucose?
Increased glucagon would provide a physiological route to higher hepatic glucose output.
Is direct stimulation of glucagon the expected octreotide action?
Octreotide is a suppressor rather than a direct stimulator of glucagon release, so this does not describe its recognized pancreatic action.
Takeaway: Improved GH control can coexist with hyperglycemia when inhibition of insulin secretion outweighs other effects.
A. Use the GH concentration alone to set the next insulin dose (Why this does not fit)
GH activity influences insulin resistance. It does not directly quantify current insulin needs during reduced intake; measured glucose patterns guide diabetes adjustments.
Reasoning steps for option A
How can GH influence insulin resistance?
GH activity influences insulin resistance.
Does its concentration replace measured glucose for dose assessment?
It does not directly quantify current insulin needs during reduced intake; measured glucose patterns guide diabetes adjustments.
B. Continue the insulin doses and treat each episode with additional snacks (Why this does not fit)
Immediate carbohydrate treatment is needed for symptomatic hypoglycemia when safe to administer. Repeated fasting lows with changing intake and hormone effects also require regimen reassessment, not only repeated rescue snacks.
Reasoning steps for option B
What is required during a symptomatic low glucose episode?
Immediate carbohydrate treatment is needed for symptomatic hypoglycemia when safe to administer.
Why is repeated rescue alone insufficient for this pattern?
Repeated fasting lows with changing intake and hormone effects also require regimen reassessment, not only repeated rescue snacks.
C. Reassess insulin and intake using repeated glucose measurements (Best answer)
Reduced intake and changing insulin resistance or counter-regulatory hormone secretion can reduce insulin requirements. Serial measurements and prompt clinical adjustment address these combined contributors after the immediate lows are treated.
Reasoning steps for option C
Which changes could reduce current insulin requirements?
Reduced intake and changing insulin resistance or counter-regulatory hormone secretion can reduce insulin requirements.
How should actual requirements be reassessed?
Serial measurements and prompt clinical adjustment address these combined contributors after the immediate lows are treated.
D. Withdraw octreotide and retain the original insulin doses without reassessment (Why this does not fit)
Octreotide can contribute to hypoglycemia and its role should be reviewed. Retaining fixed insulin despite reduced intake and recurrent lows ignores another clear contributor; treatment decisions require the whole regimen.
Reasoning steps for option D
Could octreotide contribute to the low glucose?
Octreotide can contribute to hypoglycemia and its role should be reviewed.
What other supplied contributor still needs review?
Retaining fixed insulin despite reduced intake and recurrent lows ignores another clear contributor; treatment decisions require the whole regimen.
Takeaway: Low glucose during octreotide therapy requires attention to intake, insulin exposure and changing hormonal balance.
A. Isolated acute cholecystitis without duct involvement (Why this does not fit)
Gallbladder inflammation can cause fever and right upper quadrant pain. The common-duct stone, duct dilation and jaundice show that this is not an isolated gallbladder process.
Reasoning steps for option A
What can gallbladder inflammation cause?
Gallbladder inflammation can cause fever and right upper quadrant pain.
Which findings establish additional duct involvement?
The common-duct stone, duct dilation and jaundice show that this is not an isolated gallbladder process.
B. Pancreatic exocrine insufficiency from reduced enzyme release (Why this does not fit)
Octreotide-associated exocrine suppression can produce weight loss and steatorrhea. It does not explain a visible obstructing duct stone with fever and cholestatic jaundice.
Reasoning steps for option B
What symptoms can exocrine suppression cause?
Octreotide-associated exocrine suppression can produce weight loss and steatorrhea.
Does it explain the obstructing stone and cholestatic fever pattern?
It does not explain a visible obstructing duct stone with fever and cholestatic jaundice.
C. Acute pancreatitis as the principal complication (Why this does not fit)
Biliary stones can precipitate pancreatitis during octreotide exposure. The supplied findings instead localize obstruction and infection to the biliary system, with no biochemical pancreatic pattern.
Reasoning steps for option C
Can a biliary stone precipitate pancreatitis?
Biliary stones can precipitate pancreatitis during octreotide exposure.
Where do the current tests localize the main complication?
The supplied findings instead localize obstruction and infection to the biliary system, with no biochemical pancreatic pattern.
D. Ascending cholangitis associated with an obstructing biliary stone (Best answer)
Octreotide promotes gallbladder stasis and stones, and obstruction can become infected. Fever, right upper quadrant pain, jaundice and the demonstrated common-duct stone fit cholangitis and require urgent treatment.
Reasoning steps for option D
What can happen when a stagnant biliary system becomes obstructed?
Octreotide promotes gallbladder stasis and stones, and obstruction can become infected.
How do fever, jaundice and the ultrasound fit together?
Fever, right upper quadrant pain, jaundice and the demonstrated common-duct stone fit cholangitis and require urgent treatment.
Takeaway: Biliary stasis from octreotide can lead to stones with obstruction and cholangitis.
A. Atrioventricular block associated with additive drug effects (Best answer)
Alternate P waves without QRS complexes identify 2:1 atrioventricular conduction, not simply a low sinus rate. The new infusion on top of beta blockade is a plausible additive cause requiring urgent rhythm assessment and review of both drugs; the data do not prove an exclusive cause.
Reasoning steps for option A
What does an atrial rate twice the conducted ventricular rate identify?
Alternate P waves without QRS complexes identify 2:1 atrioventricular conduction, not simply a low sinus rate.
Which recent change creates a plausible additive contributor?
The new infusion on top of beta blockade is a plausible additive cause requiring urgent rhythm assessment and review of both drugs; the data do not prove an exclusive cause.
B. Atrioventricular block associated with acute ischemic injury (Why this does not fit)
Ischemia can cause atrioventricular block and must be considered when clinically indicated. The supplied timing after a new conduction-slowing drug, together with no ischemic symptoms or ECG change, favors an additive medication contribution for first review rather than establishing acute ischemia.
Reasoning steps for option B
Can ischemia cause this type of conduction problem?
Ischemia can cause atrioventricular block and must be considered when clinically indicated.
Which supplied features favor a different immediate contributor?
The supplied timing after a new conduction-slowing drug, together with no ischemic symptoms or ECG change, favors an additive medication contribution for first review rather than establishing acute ischemia.
C. Sinus bradycardia associated with cumulative beta blockade (Why this does not fit)
A beta blocker can reduce sinus rate as well as impair conduction. The atrial rate is not slow: alternate P waves fail to conduct, placing the observed problem in atrioventricular conduction rather than sinus impulse generation.
Reasoning steps for option C
What rate would primarily fall in sinus bradycardia?
A beta blocker can reduce sinus rate as well as impair conduction.
What does the preserved P-wave rate show in this strip?
The atrial rate is not slow: alternate P waves fail to conduct, placing the observed problem in atrioventricular conduction rather than sinus impulse generation.
D. Atrioventricular block associated with hyperkalemic toxicity (Why this does not fit)
Potassium excess can impair cardiac conduction. The potassium is 4.2 mmol/L and QRS is narrow, so hyperkalemia does not fit the provided measurements.
Reasoning steps for option D
How can potassium excess affect conduction?
Potassium excess can impair cardiac conduction.
Do the current potassium and QRS findings support that explanation?
The potassium is 4.2 mmol/L and QRS is narrow, so hyperkalemia does not fit the provided measurements.
Takeaway: Identify failed atrioventricular conduction before attributing a slow ventricular rate to sinus slowing or another adverse effect.
A. The TSH response is inappropriately low for the free T4 result (Best answer)
A low free T4 should ordinarily stimulate increased TSH if pituitary signaling is intact. Octreotide can suppress TSH; assess thyroid dysfunction and other relevant causes rather than using a normal-range TSH as reassurance.
Reasoning steps for option A
What TSH response would low free T4 ordinarily provoke?
A low free T4 should ordinarily stimulate increased TSH if pituitary signaling is intact.
How does the actual TSH fit with treatment-related suppression?
Octreotide can suppress TSH; assess thyroid dysfunction and other relevant causes rather than using a normal-range TSH as reassurance.
B. The paired values show the usual response to isolated primary thyroid failure (Why this does not fit)
Primary thyroid failure commonly lowers T4. An intact pituitary normally responds with increased TSH, so these paired values require consideration of a central or drug-related effect.
Reasoning steps for option B
How does primary thyroid failure affect T4?
Primary thyroid failure commonly lowers T4.
Is the supplied TSH the usual compensatory response?
An intact pituitary normally responds with increased TSH, so these paired values require consideration of a central or drug-related effect.
C. The normal-range TSH establishes an intact thyroid axis (Why this does not fit)
TSH is a useful screening test in many settings of primary thyroid disease. Its interpretation is limited when secretion is suppressed; the low free T4 and symptoms cannot be disregarded.
Reasoning steps for option C
When is TSH a useful screening measurement?
TSH is a useful screening test in many settings of primary thyroid disease.
Why does a normal-range value not settle this case?
Its interpretation is limited when secretion is suppressed; the low free T4 and symptoms cannot be disregarded.
D. A binding-protein change has lowered total T4 without lowering free T4 (Why this does not fit)
Changes in thyroid-binding proteins can alter total T4 while leaving free hormone availability normal. The supplied result is low free T4, not isolated low total T4, so this explanation does not account for the measured abnormality.
Reasoning steps for option D
Which T4 measurement can binding-protein changes alter in isolation?
Changes in thyroid-binding proteins can alter total T4 while leaving free hormone availability normal.
Is that the abnormal measurement supplied here?
The supplied result is low free T4, not isolated low total T4, so this explanation does not account for the measured abnormality.
Takeaway: A TSH value within range does not exclude hypothyroidism when secretion may be suppressed and free T4 is low.
A. Missed doses; confirm adherence before reconsidering the regimen (Why this does not fit)
Missed doses are a common explanation for a lower trough and ordinarily warrant review. The inpatient doses were directly observed, so this does not account for the supplied exposure change.
Reasoning steps for option A
Why might missed doses initially be considered?
Missed doses are a common explanation for a lower trough and ordinarily warrant review.
What observation makes that explanation inadequate here?
The inpatient doses were directly observed, so this does not account for the supplied exposure change.
B. Reduced absorption; coordinate concentration-guided transplant-team review (Best answer)
The observed doses, matched trough timing and lower oral exposure support a real change rather than a sampling or adherence problem. An unchanged elimination half-life weighs against accelerated elimination, and the recognized octreotide interaction favors reduced absorption; the subtarget level needs coordinated concentration-guided reassessment.
Reasoning steps for option B
Do the sampling and administration records support a genuine exposure change?
The observed doses, matched trough timing and lower oral exposure support a real change rather than a sampling or adherence problem.
Which mechanism and response fit the remaining pharmacokinetic evidence?
An unchanged elimination half-life weighs against accelerated elimination, and the recognized octreotide interaction favors reduced absorption; the subtarget level needs coordinated concentration-guided reassessment.
C. Accelerated elimination; adjust the regimen for increased clearance (Why this does not fit)
Increased clearance can lower exposure despite an unchanged administered dose. The unchanged elimination half-life weighs against this alternative but does not independently prove unchanged clearance, while reduced cyclosporine absorption is a recognized octreotide interaction.
Reasoning steps for option C
Could faster clearance cause a lower trough at the same dose?
Increased clearance can lower exposure despite an unchanged administered dose.
Which additional result makes absorption the better fit?
The unchanged elimination half-life weighs against this alternative but does not independently prove unchanged clearance, while reduced cyclosporine absorption is a recognized octreotide interaction.
D. Later trough sampling; repeat the level at the original sampling time (Why this does not fit)
A sample drawn later after a dose can be lower without a change in overall exposure. Both troughs were drawn at 12 hours and the measured oral exposure also fell, so mismatched timing is not the supplied explanation.
Reasoning steps for option D
How could sample timing falsely suggest reduced exposure?
A sample drawn later after a dose can be lower without a change in overall exposure.
Do these sample times and the exposure measurement support that artifact?
Both troughs were drawn at 12 hours and the measured oral exposure also fell, so mismatched timing is not the supplied explanation.
Takeaway: Interpret low oral cyclosporine exposure using dose, sampling and elimination information before coordinating an absorption-interaction response.
Depressed vitamin B12 levels have been observed during octreotide treatment. The combination of macrocytosis and neurological symptoms makes B12 assessment particularly relevant without assuming the drug is the only possible cause.
Reasoning steps for option A
Which nutritional level can fall during octreotide treatment?
Depressed vitamin B12 levels have been observed during octreotide treatment.
Why do the new symptoms make its measurement relevant?
The combination of macrocytosis and neurological symptoms makes B12 assessment particularly relevant without assuming the drug is the only possible cause.
B. Serum folate (Why this does not fit)
Folate deficiency can produce macrocytic anemia. Vitamin B12 deficiency more directly joins the neurological findings to macrocytosis and is specifically a monitoring concern in the octreotide label.
Reasoning steps for option B
Can folate deficiency produce macrocytosis?
Folate deficiency can produce macrocytic anemia.
Which alternative better joins the neurological and label-related findings?
Vitamin B12 deficiency more directly joins the neurological findings to macrocytosis and is specifically a monitoring concern in the octreotide label.
C. Ferritin and transferrin saturation (Why this does not fit)
Iron deficiency is common and can cause fatigue with anemia. It more often produces a microcytic pattern and does not as directly account for macrocytosis with paresthesias during this therapy.
Reasoning steps for option C
Why can iron studies be useful in anemic fatigue?
Iron deficiency is common and can cause fatigue with anemia.
How does this blood count and neurological pattern differ?
It more often produces a microcytic pattern and does not as directly account for macrocytosis with paresthesias during this therapy.
D. Serum copper (Why this does not fit)
Copper deficiency can produce anemia and neurological findings and may enter the broader nutritional differential. The macrocytic pattern and the specific B12 monitoring concern in the octreotide label make B12 the more directly indicated first assessment here, without excluding other causes.
Reasoning steps for option D
Can copper deficiency enter this nutritional differential?
Copper deficiency can produce anemia and neurological findings and may enter the broader nutritional differential.
Which test more directly matches both the blood count and the recognized label concern?
The macrocytic pattern and the specific B12 monitoring concern in the octreotide label make B12 the more directly indicated first assessment here, without excluding other causes.
Takeaway: Chronic octreotide surveillance includes vitamin B12 because altered absorption can accompany long-term treatment.
A. Progression benefit unconfirmed; survival benefit supported (Why this does not fit)
A survival point estimate below 1 points in a favorable direction. Its interval spans 1 while the progression interval does not, so this option reverses which benefit is supported.
Reasoning steps for option A
Does a point estimate below 1 settle the survival question?
A survival point estimate below 1 points in a favorable direction.
Which of the two intervals actually excludes the null value?
Its interval spans 1 while the progression interval does not, so this option reverses which benefit is supported.
B. Progression benefit supported; survival benefit supported (Why this does not fit)
The progression interval lies below 1 and supports delayed progression in this selected population. The survival interval includes 1, so its favorable point estimate does not establish a survival benefit.
Reasoning steps for option B
What does the progression confidence interval show?
The progression interval lies below 1 and supports delayed progression in this selected population.
Does the survival interval support the same level of conclusion?
The survival interval includes 1, so its favorable point estimate does not establish a survival benefit.
C. Progression benefit unconfirmed; survival benefit unconfirmed (Why this does not fit)
The survival result remains inconclusive because its interval spans 1. The progression result is different: its entire interval is below 1, so the uncertainty in survival should not erase the progression evidence.
Reasoning steps for option C
Which endpoint remains uncertain?
The survival result remains inconclusive because its interval spans 1.
Must uncertainty in one endpoint invalidate the other?
The progression result is different: its entire interval is below 1, so the uncertainty in survival should not erase the progression evidence.
D. Progression benefit supported; survival benefit unconfirmed (Best answer)
The progression hazard ratio and interval support a benefit for the selected midgut-tumor population. The survival interval includes 1 and substantial uncertainty, so survival benefit was not confirmed in this report; that is not proof of no survival effect.
Reasoning steps for option D
Which endpoint has a confidence interval entirely below 1?
The progression hazard ratio and interval support a benefit for the selected midgut-tumor population.
What conclusion is justified for the other endpoint?
The survival interval includes 1 and substantial uncertainty, so survival benefit was not confirmed in this report; that is not proof of no survival effect.
Takeaway: Interpret uncertainty separately for progression and survival rather than transferring significance between endpoints.
A. Impaired receptor-mediated regulation; peripheral blockade can lower IGF-1 without requiring lower GH (Best answer)
The active control preparation and preserved response to direct adenylyl cyclase inhibition favor impaired receptor-mediated regulation upstream of the observed cAMP response. Peripheral GH receptor blockade acts at a different target and can lower IGF-1 without requiring suppression of GH release; these data do not identify one specific receptor or signaling defect.
Reasoning steps for option A
What remains functional when the receptor step is bypassed?
The active control preparation and preserved response to direct adenylyl cyclase inhibition favor impaired receptor-mediated regulation upstream of the observed cAMP response.
How does a peripheral receptor antagonist avoid requiring correction of that pituitary secretory response?
Peripheral GH receptor blockade acts at a different target and can lower IGF-1 without requiring suppression of GH release; these data do not identify one specific receptor or signaling defect.
B. Impaired receptor-mediated regulation; peripheral blockade can lower GH without requiring lower IGF-1 (Why this does not fit)
The bypass result does favor impaired receptor-mediated regulation rather than resistance of secretion to reduced cAMP. The predicted endocrine response is reversed: peripheral GH blockade is assessed by lower IGF-1 and need not lower GH.
Reasoning steps for option B
Does the first part fit the bypass experiment?
The bypass result does favor impaired receptor-mediated regulation rather than resistance of secretion to reduced cAMP.
Which hormone is the relevant downstream response to peripheral blockade?
The predicted endocrine response is reversed: peripheral GH blockade is assessed by lower IGF-1 and need not lower GH.
C. Resistance of release to lower cAMP; peripheral blockade can lower IGF-1 without requiring lower GH (Why this does not fit)
Peripheral GH receptor blockade can lower IGF-1 without requiring reduced pituitary GH release. The proposed localization is contradicted by the experiment: GH release does fall when cAMP is lowered by direct adenylyl cyclase inhibition.
Reasoning steps for option C
Is the predicted peripheral endocrine response reasonable?
Peripheral GH receptor blockade can lower IGF-1 without requiring reduced pituitary GH release.
Does the tumor-cell release machinery resist the demonstrated reduction in cAMP?
The proposed localization is contradicted by the experiment: GH release does fall when cAMP is lowered by direct adenylyl cyclase inhibition.
D. Resistance of release to lower cAMP; peripheral blockade can lower GH without requiring lower IGF-1 (Why this does not fit)
A downstream secretory defect and a peripheral receptor intervention concern different physiological levels. The experiment shows preserved suppression of release when cAMP falls, and peripheral blockade primarily reduces GH action reflected in IGF-1 rather than requiring lower GH.
Reasoning steps for option D
Which experimental observation tests downstream secretion?
A downstream secretory defect and a peripheral receptor intervention concern different physiological levels.
Which biochemical endpoint should peripheral action blockade change?
The experiment shows preserved suppression of release when cAMP falls, and peripheral blockade primarily reduces GH action reflected in IGF-1 rather than requiring lower GH.
Takeaway: A preserved downstream response can localize poor receptor-mediated inhibition, while peripheral GH blockade targets a different part of the axis.