Trace obstructed bile flow through laboratory patterns, imaging, infection, urgent drainage, and chronic fibrosis, then compare plans for stones, scars, and tumors.
A patient with jaundice has two different problems to solve: where bile is being held back, and whether the patient can safely wait for a detailed map. A wide duct does not answer the second question. Infection and organ dysfunction can make a modest obstruction an emergency, while prolonged obstruction can damage liver architecture without any dramatic septic episode.
Does finding a wide bile duct mean that the next test must be ERCP? No. Detecting backup, identifying its cause, and restoring drainage are different tasks. In a stable patient with suspected obstruction, transabdominal ultrasound is usually the first study. It evaluates gallstones, the gallbladder, and intrahepatic and extrahepatic duct caliber. A negative examination does not reliably exclude a small distal common bile duct stone. [1][2]
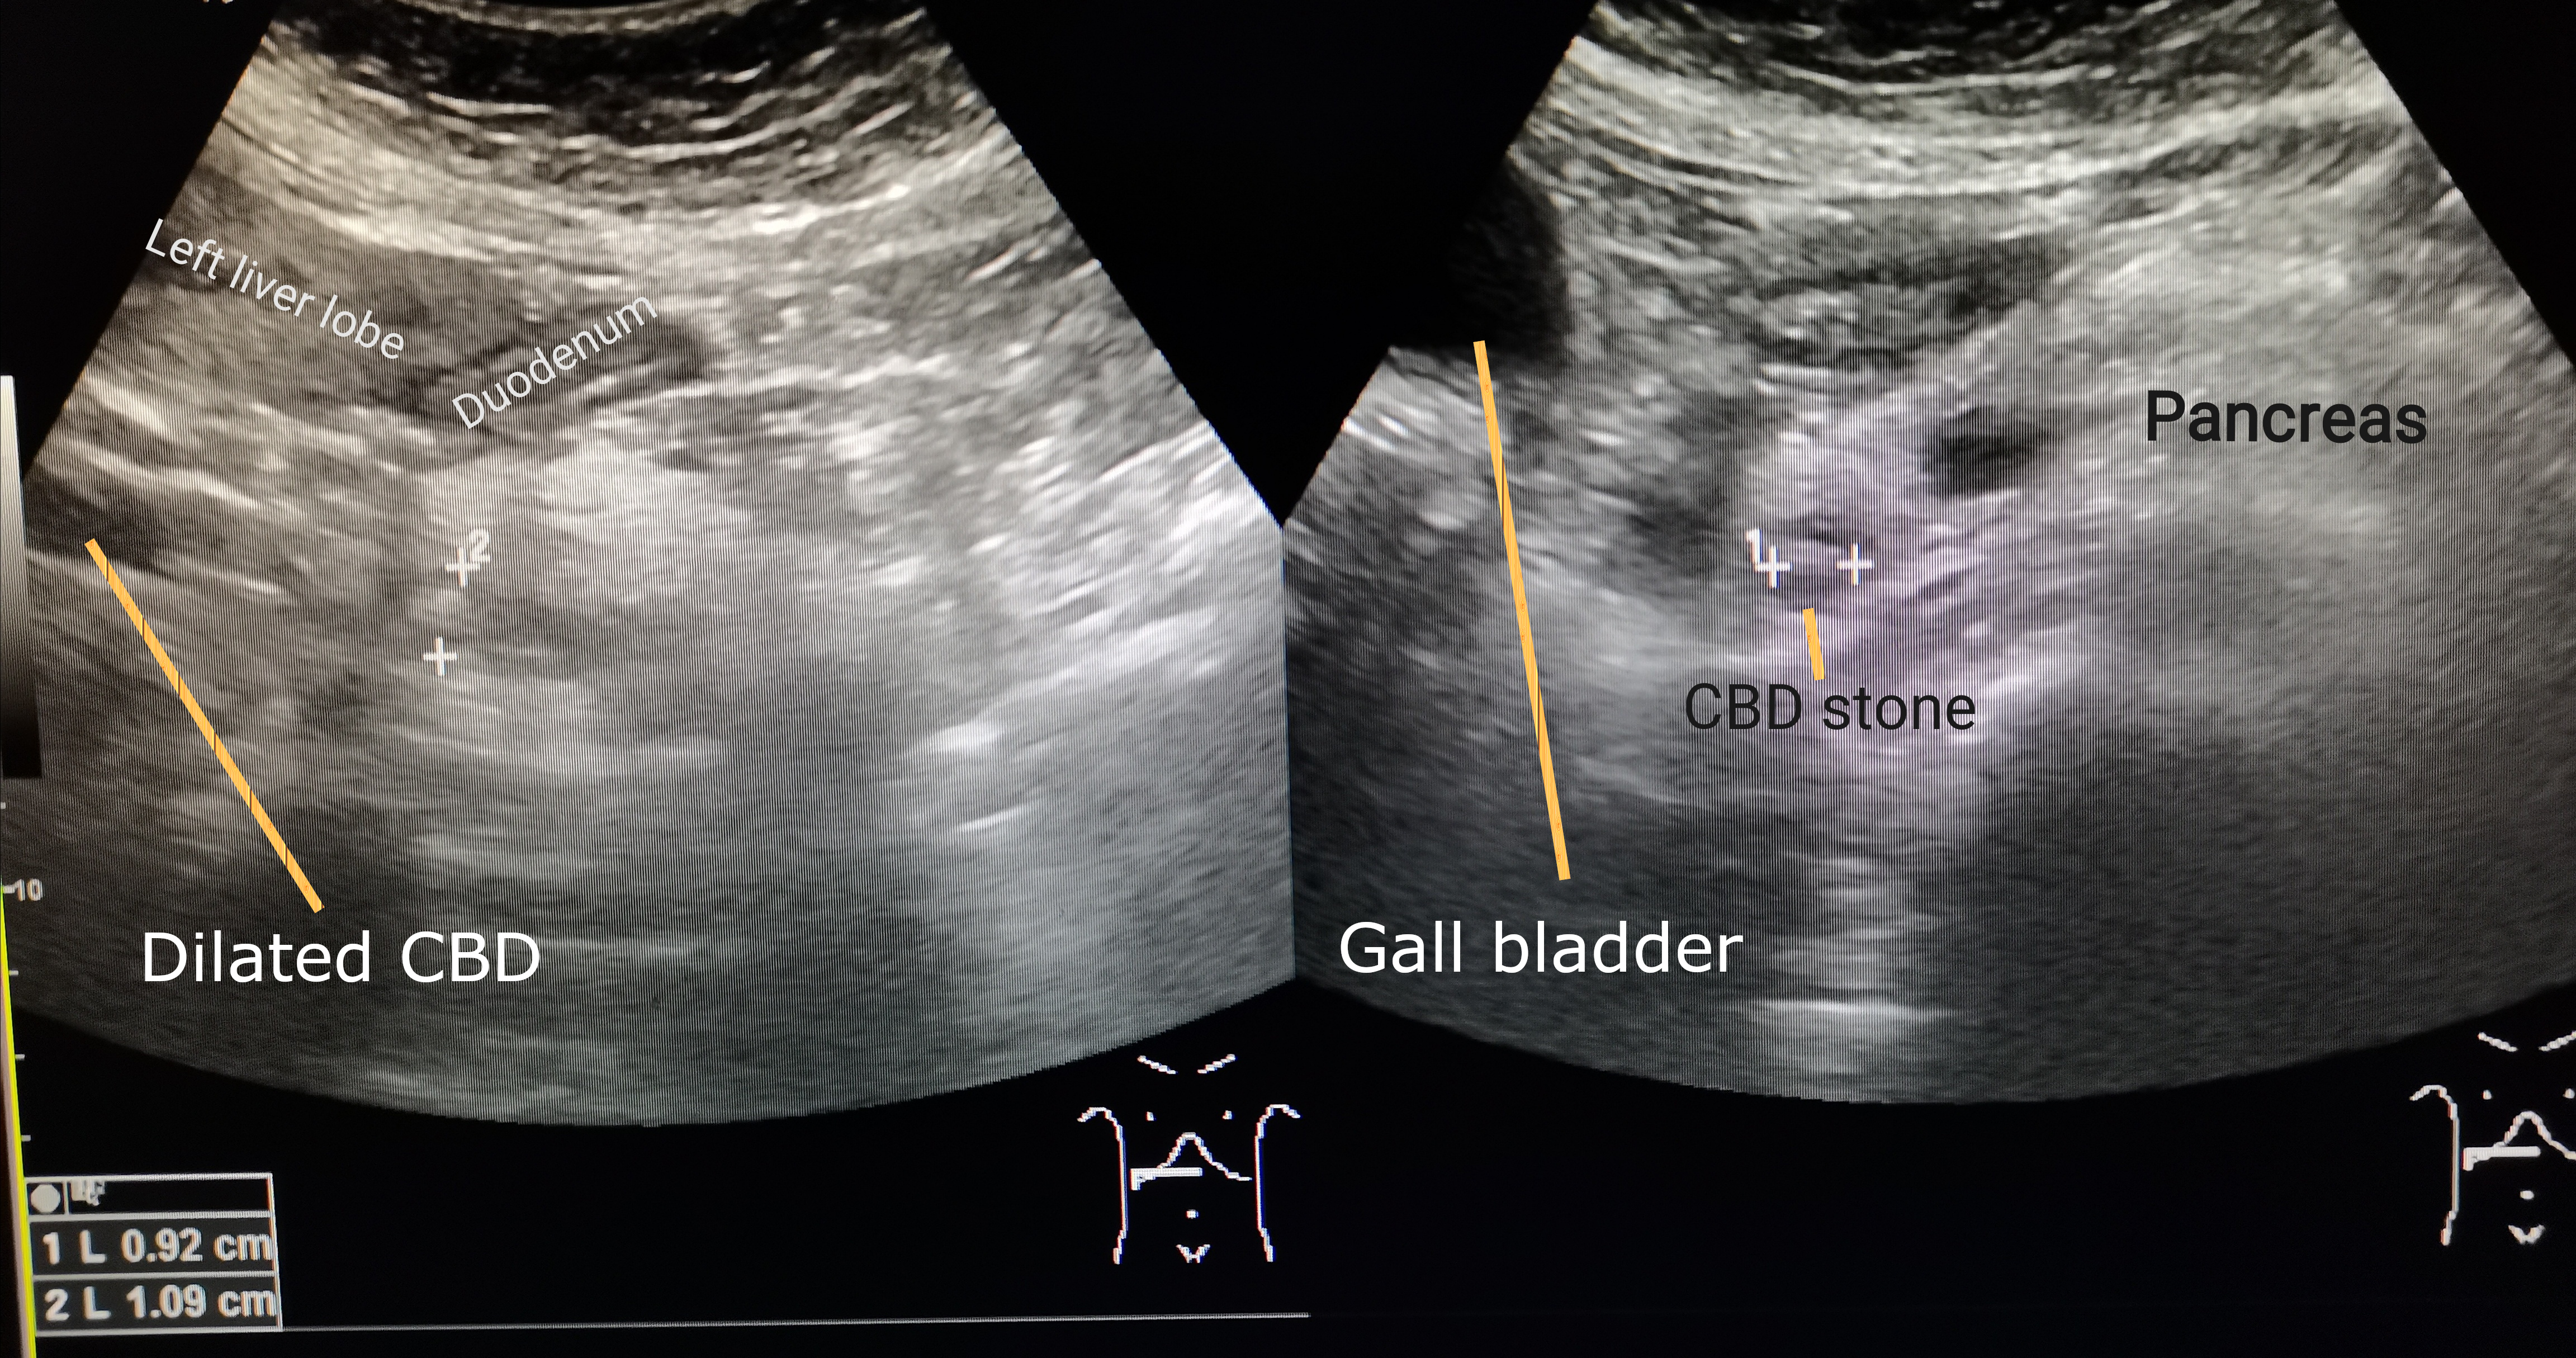
The accompanying clinical ultrasound contains the source author's labels: one view measures a dilated duct and another identifies a distal stone. It demonstrates a positive finding, not how every obstructed duct will look. The complete original image is preserved; neither the image nor its duct measurement determines clinical urgency.
Trace the dilated common bile duct to the distal stone on ultrasound. If the clinical suspicion persists despite a scan without a visible stone, evaluate for a small distal obstruction. Image: Cerevisae; source; CC BY-SA 4.0. [2]
Choose a tool for the unresolved question
Tool
Useful task
Important limit
ToolUltrasound
Useful taskDetect gallstones and upstream dilation.
Important limitThe distal duct may be obscured.
ToolMRCP
Useful taskMap ducts, stones, and the length and level of a narrowing without endoscopic instrumentation.
Important limitIt does not drain the duct.
ToolEUS
Useful taskAssess small distal stones, the pancreas, or a periampullary lesion; obtain selected tissue samples.
Important limitThe tissue strategy depends on lesion location.
ToolContrast-enhanced CT
Useful taskAssess a mass, vascular relationships, complications, and staging.
Important limitA negative CT is not a reliable small-stone exclusion test.
ToolERCP
Useful taskDrain, extract stones, dilate or stent a stricture, and obtain duct-based samples.
Important limitInvasive complications make it inappropriate as a routine diagnostic shortcut.
MRCP and EUS are useful when stone probability is intermediate. ASGE high-risk features that support proceeding to ERCP include a duct stone on imaging, ascending cholangitis, or the combination of total bilirubin above 4 mg/dL and a dilated common duct. Dilation alone does not supply that combined criterion. Availability, anatomy, and procedural suitability still matter. [2][5]
Consider a stable patient with intermittent pain, bilirubin 2.3 mg/dL, and a 9 mm common duct but no visible duct stone. Before reading the answer, choose between confirming a suspected stone and performing an invasive drainage procedure.
Compare the two test strategies
MRCP or EUS can establish whether a stone remains. The combination of moderate biochemical abnormality and dilation raises suspicion without meeting the bilirubin-plus-dilation high-risk criterion. A therapeutic procedure can follow a positive result. [2]
Now change one feature: fever with hypotension develops. The clinical question is no longer simply whether another image can find a stone. Resuscitation and a rapid source-control plan take priority over an elective mapping sequence. [3][4]
Retained bile has an acute branch and a chronic branch
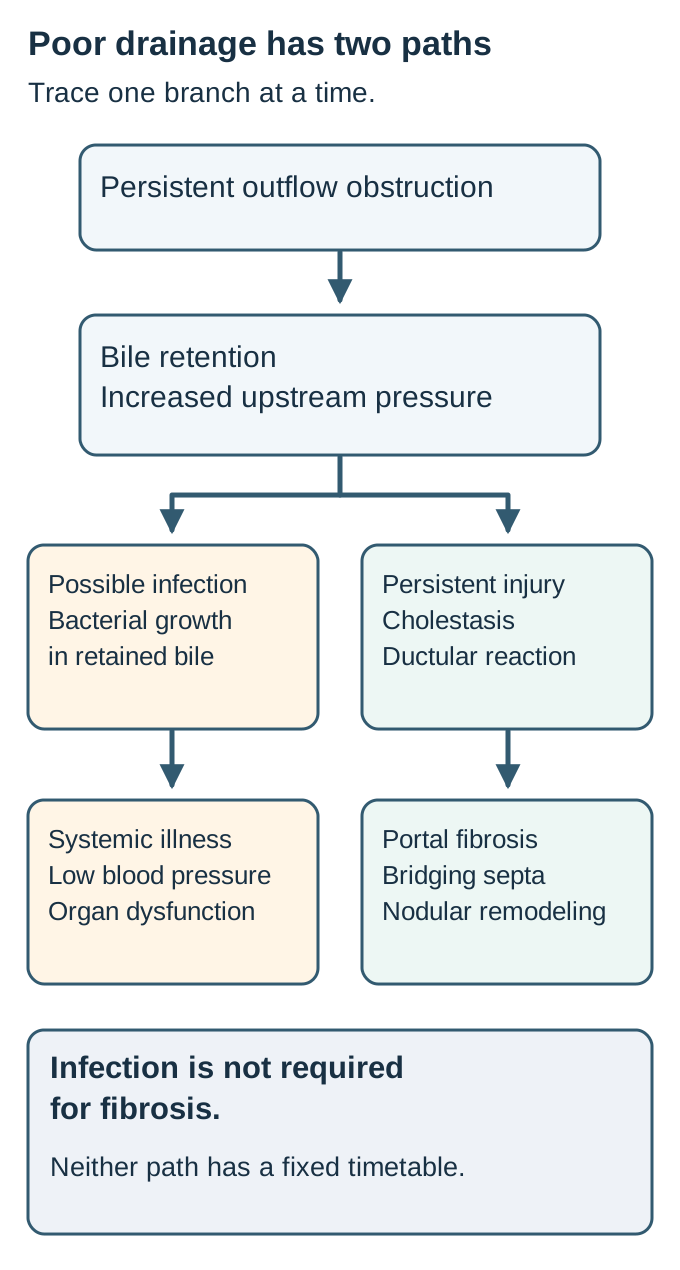
Must obstruction become infected before it can scar the liver? No. Increased outflow resistance retains bile and raises upstream pressure. Conjugated bilirubin and bile constituents accumulate, producing canalicular and ductular cholestasis. Infection and fibrosis are possible consequences of obstruction, not compulsory consecutive stages. The branching diagram separates these two paths. [3][6][7]
In the acute branch, poor drainage permits bacterial proliferation and impairs clearance. Rising intraductal pressure can facilitate passage of bacteria and inflammatory products into the circulation. Cholangitis can therefore progress from a local infection to bacteremia and organ dysfunction. A stone is not required: a scar, tumor, or blocked stent can create the same setting. [3][4]
In the chronic branch, persistent cholestatic injury produces portal edema, inflammation, ductular reaction, and injury near the bile duct interface. Fibrosis begins around portal structures and may bridge between portal regions. Advanced remodeling with regenerative nodules is secondary biliary cirrhosis. The word secondary identifies the obstructive cause; it is not a separate blood-test pattern. Recurrent infection can add injury, but an afebrile patient is not protected from progressive fibrosis. [5][6][7]
Follow the diagram from a persistent benign stricture. Cover the infection branch with your hand or follow only the chronic branch mentally. Predict whether years of poor drainage can still produce portal fibrosis.
Trace the chronic injury branch without the infection branch. The diagram separates a possible acute infection from chronic injury; neither is a fixed timeline. [3][6][7][3][6][7]Check the prediction without the infection branch
Yes. Persistent bile retention and associated tissue injury remain even without a recognized episode of cholangitis. Restoring drainage addresses the cause of injury; treating fever alone would not correct the narrowing. [6][7]
There is no universal interval from obstruction to cirrhosis. Completeness, duration, etiology, recurrent inflammation, and residual drainage affect the course. Neither one bilirubin result nor a single duct diameter measures fibrosis. Biopsy is not the first test for a readily identifiable extrahepatic block. [1][6]
Some fibrosis can regress after durable relief. A small serial-biopsy study in chronic pancreatitis found improvement in selected patients after surgical drainage, but not in everyone. This does not establish immediate or complete reversal of established cirrhosis. A falling bilirubin can coexist with residual portal hypertension or impaired hepatic reserve. [7]
Transfer the distinction to follow-up: improving jaundice supports better bile flow, while persistent ascites, thrombocytopenia, or varices still requires evaluation of chronic liver disease and portal hypertension. Do not use an improving skin color as the entire recovery assessment.
Trace the drainage territory before naming the cause
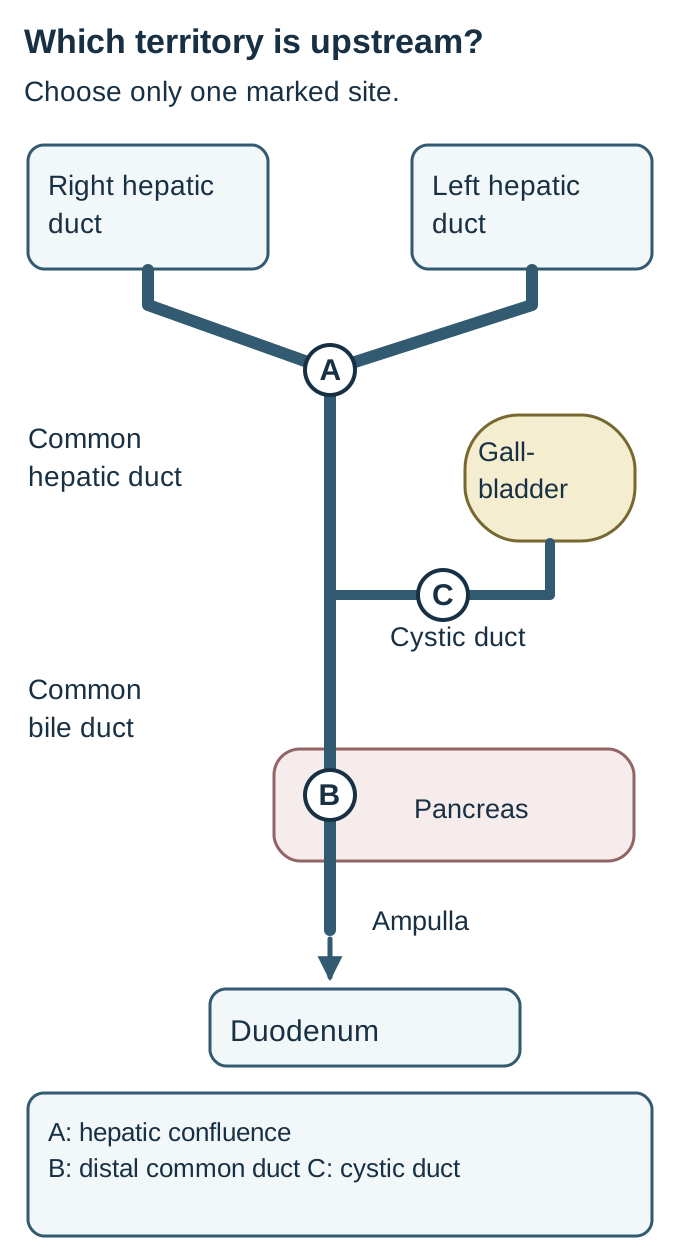
Would the same stone cause the same backup in the cystic duct and the common bile duct? The cystic duct serves the gallbladder. The common hepatic duct drains the liver, then joins the cystic duct to form the common bile duct. The shared outlet passes near the pancreatic head and enters the duodenum. A block below the cystic duct junction can obstruct liver drainage and communicate pressure to the gallbladder; an isolated cystic duct block ordinarily cannot obstruct the whole liver. [2][5]
Use the accompanying original duct map as a tracing exercise. Start at each hepatic branch and follow the continuous route to the intestine. Stop at the selected obstruction site. Ducts upstream of that point are the territory at risk. Upstream dilation varies with the obstruction and clinical context.
Select A, B, or C, then trace each hepatic branch toward the duodenum. These are alternative sites, not simultaneous lesions. The diagram is schematic and does not imply that every upstream segment must dilate. [2][5][2][5]
Choose site A at the hepatic confluence, site B below the cystic junction, or site C in the cystic duct. Which best fits dilation of both intrahepatic systems with a normal-caliber distal common duct?
Check the drainage territory
Site A blocks the outflow from both hepatic systems while leaving the distal duct downstream of the blockage. Site B would place the extrahepatic duct above it under pressure as well. Site C mainly isolates gallbladder drainage. The pattern localizes the lesion but does not establish whether it is a scar or a tumor. [5]
Stones often produce abrupt or intermittent pain and transient jaundice, but a retained stone can cause sustained obstruction, pancreatitis, or cholangitis. Benign strictures can follow surgery, transplantation, pancreatitis, ischemia, inflammation, or instrumentation. A short narrowing near a prior operative site makes scarring plausible, not certain. [2][5][6]
Pancreatic head and ampullary tumors can obstruct the distal duct. Bile duct cancers occur at different levels, and gallbladder cancer or enlarged nodes can obstruct through invasion or external compression. Progressive painless jaundice, weight loss, and a distended gallbladder raise concern for distal malignant obstruction. They neither prove cancer nor identify one cancer type. CT or MRI, location-appropriate endoscopy, and a coordinated tissue strategy resolve the cause. [5][6]
A nondiagnostic brush sample does not establish a benign stricture. For a jaundiced patient with a distal extrahepatic stricture but no pancreatic mass, ESGE recommends complementary EUS-guided and ERCP-based tissue acquisition. Persistent uncertainty may justify cholangioscopy-guided biopsy. Perihilar lesions need a different, multidisciplinary sampling plan; a distal-lesion biopsy strategy should not be copied automatically into a potentially curative hilar pathway. [5]
Try the opposite pattern: a stone confined to the cystic duct, gallbladder inflammation, normal bilirubin, and no common duct compression. That combination supports a gallbladder problem without evidence of whole-liver outflow obstruction. Associated common duct stones or extrinsic hepatic duct compression would change the interpretation. [2]
Read the laboratory pattern and its direction
Can an obstruction look hepatocellular at the beginning? Yes. The usual cholestatic pattern is an alkaline phosphatase (ALP) increase out of proportion to aminotransferases, compared with each test's upper limit of normal. Gamma-glutamyl transferase (GGT) supports a hepatobiliary source of increased ALP, but is nonspecific and does not localize a blockage. Conjugated hyperbilirubinemia can reflect impaired biliary excretion from either obstruction or hepatocellular disease. [1]
For example, ALP 720 U/L with an upper limit of 120 is six times normal, while ALT 80 U/L with an upper limit of 40 is twice normal. The relative pattern favors cholestasis. The next question is whether imaging and history identify a mechanical cause, not whether one enzyme result independently proves a stone. Isolated ALP with normal GGT and bilirubin instead warrants confirmation of the enzyme source, including possible bone disease, before biliary instrumentation. [1]
Conjugated bilirubin is water soluble and can appear in urine, causing dark urine. Reduced delivery of bilirubin to the intestine reduces stool pigment, producing pale stools. Unconjugated bilirubin in isolated hemolysis does not produce bilirubinuria. Pruritus can accompany retained bile constituents, but itching alone neither localizes the lesion nor establishes cirrhosis. [1]
Acute common duct stones can produce striking AST or ALT increases, even without cholangitis. A prospective study documented this presentation in patients with confirmed stones; a relatively narrow duct did not exclude it. Preserve the differential diagnosis for toxic, ischemic, and viral injury, but do not discard obstruction solely because the first panel resembles hepatitis. [9]
Compare two samples: ALT falls from 760 to 180 U/L, while direct bilirubin rises from 1.8 to 4.9 mg/dL and fever begins. Decide whether the falling ALT alone demonstrates recovery.
Interpret the changing results
It does not. Falling aminotransferases do not prove a patent duct. Worsening conjugated bilirubin with new fever requires reassessment for persistent obstruction and infection. The patient's physiology and the complete trend are more important than the direction of one enzyme. [1][3][9]
Finally separate injury markers from reserve and organ dysfunction. Creatinine, oxygenation, mental status, coagulation, and platelet trends help identify deterioration; they do not become reassuring simply because ALT falls. When cholestasis persists without a visible obstruction, consider primary biliary cholangitis, primary sclerosing cholangitis, drug-related injury, and other intrahepatic causes. Primary biliary cholangitis affects small intrahepatic ducts; it does not ordinarily explain a focal extrahepatic cutoff. [1][3]
The patient's physiology sets the urgency
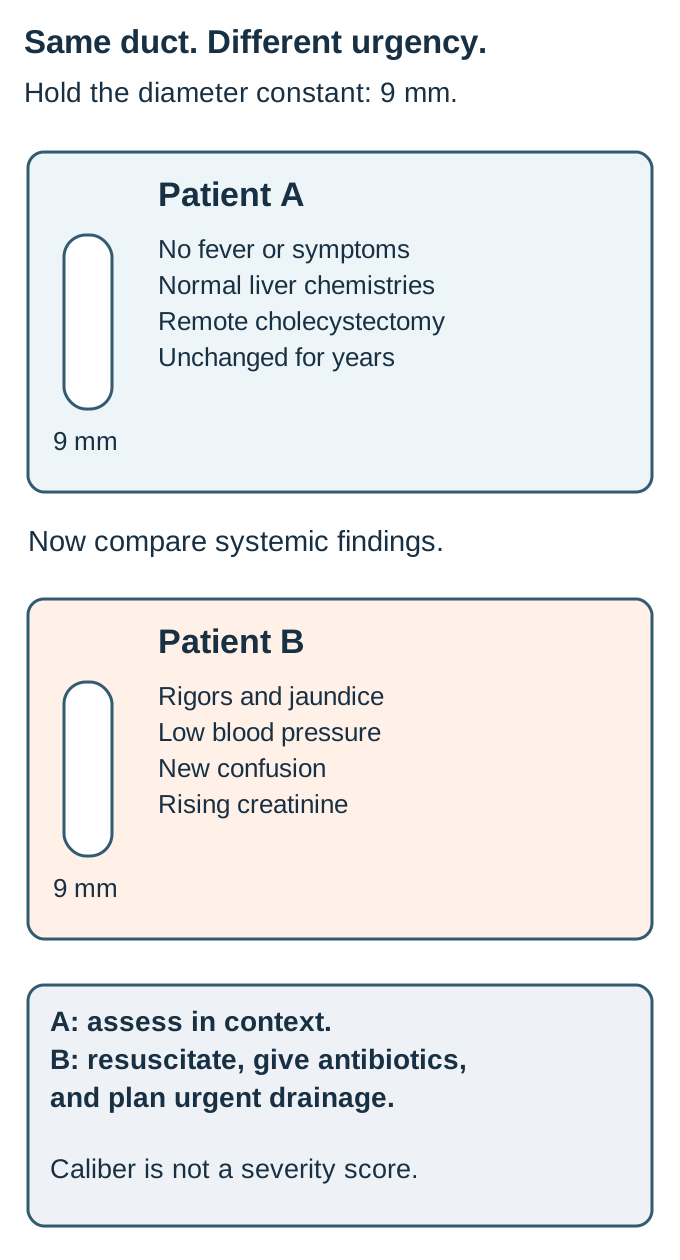
Two common ducts measure 9 mm. Should their patients receive the same plan? No. Dilation supports impaired drainage in context, but caliber also reflects age, prior cholecystectomy, anatomy, and duration. Early or partial obstruction may produce little dilation. Incidental mild dilation with normal laboratory results is a different problem from jaundice with systemic illness. [2][3]
The accompanying comparison holds duct caliber constant. One patient is stable and afebrile; another has rigors, confusion, rising creatinine, and hypotension. Point to the findings that alter the immediate plan. The difference is systemic infection and organ dysfunction, not a larger duct.
The controlled comparison holds diameter constant. Identify the systemic findings that change urgency before reading the section answer. Caliber is not a severity score. [2][3][4][2][3][4]
Tokyo diagnostic criteria combine evidence of systemic inflammation, cholestasis, and imaging showing dilation or an obstructing cause. Fever, right upper quadrant pain, and jaundice are the classic triad, but all three are not required. Older or severely ill patients may not report characteristic pain. Hypotension, altered consciousness, renal dysfunction, respiratory failure, coagulation abnormalities, or thrombocytopenia can indicate severe cholangitis. [3]
Begin prompt assessment and treatment when biliary sepsis is suspected: support circulation and oxygenation, obtain cultures when this does not delay treatment, and give appropriate intravenous antibiotics. Initial coverage and later narrowing depend on likely enteric organisms, severity, community versus healthcare exposure, local resistance, allergies, renal function, and culture results. Organize drainage while resuscitation is underway. Do not wait for every organ abnormality to normalize before pursuing source control. [4][8]
Moderate cholangitis also warrants early drainage, even without shock. Mild disease may initially respond to antibiotics, but persistent obstruction, nonresponse, or deterioration requires reassessment and drainage. ASGE suggests decompression within 48 hours for cholangitis; this is not permission to wait until that limit in a patient with shock. Severe disease requires drainage as soon as feasible after initial stabilization and with continuing support. [3][4][8]
Check the same-caliber comparison
The stable patient can undergo a probability-based diagnostic assessment. The hypotensive, confused patient needs resuscitation, antibiotics, and urgent biliary source control. A similar duct diameter does not make their risks equivalent. [3][4]
Transfer this reasoning to a follow-up call: fever and recurrent jaundice in someone with a biliary stent need urgent reassessment of infection and stent patency. Prior drainage does not guarantee present drainage. [4][6]
Restore drainage and plan what happens afterward
When does successful decompression finish the job? It treats the immediate outflow problem, but not necessarily the source of future obstruction. The durable plan differs for stones, scars, and malignancy. In cholangitis, ERCP is generally preferred when feasible. If the patient tolerates it, drainage and stone clearance can occur together. An unstable patient may need a shorter decompression procedure first, with difficult extraction deferred until safer. [2][8]
After stone clearance, address the gallbladder and recurrence risk with the surgical team. Mild gallstone pancreatitis without cholangitis or persistent obstruction does not justify routine urgent ERCP. An improving patient with no retained stone instead needs pancreatitis care and an appropriate cholecystectomy plan, generally during the same admission for mild disease. [2]
For a benign stricture, establish its cause, level, and length, assess malignancy, and select a treatment with planned reassessment. Balloon dilation and temporary stenting may require repeat procedures. The September 2026 ESGE guideline suggests multiple plastic stents for postcholecystectomy strictures; a fully covered metal stent is an option in selected anatomy. For chronic pancreatitis-associated strictures, it suggests a temporary fully covered metal stent for 6 to 12 months. These are conditional recommendations, not interchangeable rules for every stricture. A lesion close to the hepatic confluence needs special attention to branch drainage. [5][6]
Malignant obstruction requires coordination of staging, tissue needs, resectability, symptoms, and treatment timing. Routine preoperative drainage may be avoided when a stable patient can undergo upfront surgery within 1 to 2 weeks. Cholangitis, severe symptoms such as intense pruritus, a longer surgical delay, or planned neoadjuvant treatment in a jaundiced patient can favor drainage. Avoid an uncovered metal stent when the etiology remains unconfirmed. Do not commit the patient to a stent or sampling route before considering the definitive treatment plan. [5][6]
Compare a stable patient scheduled for surgery next week with a jaundiced patient who will receive neoadjuvant therapy before later surgery. Predict whether their pre-treatment drainage plans must be identical.
Check the treatment-timing comparison
They need not be identical. The first may proceed through the coordinated surgical pathway without routine preoperative drainage. The second has a prolonged treatment interval during which jaundice can interfere with therapy and favor planned drainage. Infection or severe symptoms would change either assessment. [6]
If ERCP fails, the next route depends on anatomy, urgency, and expertise. For malignant obstruction, current ESGE guidance favors expert EUS-guided transmural drainage over percutaneous drainage after failed ERCP when feasible. Percutaneous transhepatic drainage remains important when EUS expertise is absent, the EUS route is unsuitable, or it fails. Surgically altered anatomy can also require specialized endoscopic or percutaneous approaches; surgery is a selected alternative or definitive repair, not the automatic emergency fallback. [6][8]
Every temporary stent needs a documented exchange or extraction plan, a responsible service, and instructions for recurrent fever or jaundice. Antibiotics can treat infection but cannot reliably compensate for a persistently blocked system. In long-standing disease, follow liver function and portal hypertension as well as duct patency. The lasting questions are whether bile can drain, whether the cause has been treated, and what injury remains. [4][6][7]
Apply the reasoning to a new patient
Case 1
Show answer and explanations for case 1
A. Below the cystic duct junction (Best answer)
The common bile duct is the shared route from the liver and communicating gallbladder toward the duodenum. A block below their junction places both the hepatic ducts and the patent gallbladder connection upstream; the exact cause still needs imaging rather than being established by the painless presentation.
Reasoning steps for option A
Which duct carries bile after the cystic and hepatic pathways meet?
The common bile duct is the shared route from the liver and communicating gallbladder toward the duodenum.
Which inferred obstruction would explain all the upstream structures?
A block below their junction places both the hepatic ducts and the patent gallbladder connection upstream; the exact cause still needs imaging rather than being established by the painless presentation.
B. Within small intrahepatic ducts (Why this does not fit)
Small-duct cholangiopathies can produce pruritus and cholestatic jaundice. Dilation of the extrahepatic duct together with the communicating gallbladder is better explained by a downstream mechanical block than by diffuse small-duct disease.
Reasoning steps for option B
What pattern can small-duct disease produce?
Small-duct cholangiopathies can produce pruritus and cholestatic jaundice.
Which imaging findings favor a different level of obstruction?
Dilation of the extrahepatic duct together with the communicating gallbladder is better explained by a downstream mechanical block than by diffuse small-duct disease.
C. At the hepatic duct confluence (Why this does not fit)
A confluence lesion can obstruct both intrahepatic systems. It leaves the extrahepatic duct and gallbladder downstream, whereas both are distended here through a patent cystic connection.
Reasoning steps for option C
Which territory is upstream of a confluence lesion?
A confluence lesion can obstruct both intrahepatic systems.
Why does it not best fit the entire supplied pattern?
It leaves the extrahepatic duct and gallbladder downstream, whereas both are distended here through a patent cystic connection.
D. Within the cystic duct (Why this does not fit)
An isolated cystic duct block primarily obstructs the gallbladder. No. Both hepatic systems and the extrahepatic duct are dilated, and the cystic duct is explicitly patent.
Reasoning steps for option D
What does the cystic duct drain?
An isolated cystic duct block primarily obstructs the gallbladder.
Can that isolated block explain this hepatic duct pattern?
No. Both hepatic systems and the extrahepatic duct are dilated, and the cystic duct is explicitly patent.
Takeaway: Use the distribution of backup to localize a block; painless jaundice does not establish its histology.
A. Magnetic resonance cholangiopancreatography (Best answer)
MRCP can identify a retained stone and map the biliary tree. Dilation and abnormal liver chemistries create intermediate suspicion without a high-risk feature requiring direct ERCP.
Reasoning steps for option A
What task can MRCP perform without endoscopic duct instrumentation?
MRCP can identify a retained stone and map the biliary tree.
Why is confirmation preferable in this profile?
Dilation and abnormal liver chemistries create intermediate suspicion without a high-risk feature requiring direct ERCP.
B. ERCP with empiric sphincterotomy (Why this does not fit)
A visible duct stone, cholangitis, or bilirubin above 4 mg/dL with duct dilation supports a high-risk pathway. No. The patient is stable, no stone is seen, and bilirubin is 2.3 mg/dL; empiric sphincterotomy adds risk before confirmation.
Reasoning steps for option B
When can ERCP directly follow a stone assessment?
A visible duct stone, cholangitis, or bilirubin above 4 mg/dL with duct dilation supports a high-risk pathway.
Does this presentation meet one of those criteria?
No. The patient is stable, no stone is seen, and bilirubin is 2.3 mg/dL; empiric sphincterotomy adds risk before confirmation.
C. Contrast-enhanced abdominal CT (Why this does not fit)
It can assess a pancreatic or biliary mass, vascular involvement, and other abdominal complications. The unresolved question is a retained common duct stone in a stable intermediate-risk presentation, for which MRCP directly evaluates the duct lumen without relying on CT visibility of a small stone.
Reasoning steps for option C
When is contrast-enhanced CT especially useful in obstructive jaundice?
It can assess a pancreatic or biliary mass, vascular involvement, and other abdominal complications.
Why is MRCP the better focused investigation in this patient?
The unresolved question is a retained common duct stone in a stable intermediate-risk presentation, for which MRCP directly evaluates the duct lumen without relying on CT visibility of a small stone.
D. Hepatobiliary scintigraphy (Why this does not fit)
Hepatobiliary scintigraphy can assess cystic duct patency in suspected acute cholecystitis. The unresolved question is a common duct stone, for which MRCP provides a more appropriate anatomic assessment.
Reasoning steps for option D
What obstruction question is scintigraphy often used to address?
Hepatobiliary scintigraphy can assess cystic duct patency in suspected acute cholecystitis.
What is unresolved in this patient instead?
The unresolved question is a common duct stone, for which MRCP provides a more appropriate anatomic assessment.
Takeaway: Choose a test for the remaining uncertainty rather than treating dilation alone as a procedure indication.
A. Confirm a stone with MRCP first (Why this does not fit)
Intermediate-risk patients benefit from confirmatory imaging that can prevent an unnecessary invasive procedure. Bilirubin above 4 mg/dL plus a dilated duct establishes a high-risk profile, for which direct therapeutic ERCP is the recommended pathway rather than required MRCP confirmation.
Reasoning steps for option A
Which stone-risk group generally benefits from MRCP before ERCP?
Intermediate-risk patients benefit from confirmatory imaging that can prevent an unnecessary invasive procedure.
Why does the specified ASGE pathway place this patient elsewhere?
Bilirubin above 4 mg/dL plus a dilated duct establishes a high-risk profile, for which direct therapeutic ERCP is the recommended pathway rather than required MRCP confirmation.
B. Perform cholecystectomy without duct evaluation (Why this does not fit)
That approach can suit patients without meaningful common duct risk factors, with additional assessment chosen as indicated. Persistent jaundice, bilirubin 6.2 mg/dL, and a 10 mm duct require a duct-clearance strategy, not a gallbladder-only plan.
Reasoning steps for option B
When can gallbladder surgery proceed without a separate preoperative duct investigation?
That approach can suit patients without meaningful common duct risk factors, with additional assessment chosen as indicated.
Why is ignoring the duct risk inappropriate here?
Persistent jaundice, bilirubin 6.2 mg/dL, and a 10 mm duct require a duct-clearance strategy, not a gallbladder-only plan.
C. Proceed to therapeutic ERCP (Best answer)
Total bilirubin above 4 mg/dL plus a dilated common duct constitutes a high-risk profile. No. Bilirubin 6.2 mg/dL and a 10 mm duct satisfy the combined criterion despite nondiagnostic stone visualization.
Reasoning steps for option C
Which combined findings support direct ERCP in suspected stones?
Total bilirubin above 4 mg/dL plus a dilated common duct constitutes a high-risk profile.
Does absence of a visible stone negate this criterion?
No. Bilirubin 6.2 mg/dL and a 10 mm duct satisfy the combined criterion despite nondiagnostic stone visualization.
D. Confirm a stone with EUS first (Why this does not fit)
It is useful when stone probability is intermediate or a small distal stone remains uncertain. The combined bilirubin and duct-dilation criterion already places this patient in the direct-ERCP high-risk category; individualized practice may differ, but the specified pathway is unambiguous.
Reasoning steps for option D
When does EUS help avoid an unnecessary ERCP?
It is useful when stone probability is intermediate or a small distal stone remains uncertain.
Why is confirmation not required by the pathway asked about here?
The combined bilirubin and duct-dilation criterion already places this patient in the direct-ERCP high-risk category; individualized practice may differ, but the specified pathway is unambiguous.
Takeaway: A combined high-risk criterion can justify therapeutic evaluation even when ultrasound does not display the stone.
A. Observe without further biliary evaluation (Why this does not fit)
Observation can be reasonable when symptoms resolve and the overall biochemical and imaging assessment becomes reassuring. No. Conjugated bilirubin is rising and the distal duct was not evaluated adequately, so falling ALT alone cannot close the investigation.
Reasoning steps for option A
When can observation after suspected stone passage be appropriate?
Observation can be reasonable when symptoms resolve and the overall biochemical and imaging assessment becomes reassuring.
Is the complete trajectory reassuring here?
No. Conjugated bilirubin is rising and the distal duct was not evaluated adequately, so falling ALT alone cannot close the investigation.
B. Perform hepatobiliary scintigraphy of the gallbladder (Why this does not fit)
It can assess gallbladder filling and cystic duct patency. The distal common duct was obscured and direct bilirubin is rising; gallbladder filling would not adequately exclude a retained duct stone.
Reasoning steps for option B
What can scintigraphy contribute to suspected cholecystitis?
It can assess gallbladder filling and cystic duct patency.
Which unresolved location is more relevant here?
The distal common duct was obscured and direct bilirubin is rising; gallbladder filling would not adequately exclude a retained duct stone.
C. Obtain endoscopic ultrasound of the distal duct (Best answer)
Yes. Acute stone obstruction can occur with substantial aminotransferase increases before marked dilation is apparent. It can evaluate the obscured distal duct for a small retained stone while the evolving conjugated bilirubin pattern remains concerning.
Reasoning steps for option C
Can a narrow duct coexist with an acute common duct stone?
Yes. Acute stone obstruction can occur with substantial aminotransferase increases before marked dilation is apparent.
What can EUS add to the limited examination?
It can evaluate the obscured distal duct for a small retained stone while the evolving conjugated bilirubin pattern remains concerning.
D. Perform liver biopsy before duct imaging (Why this does not fit)
Toxic, ischemic, viral, or autoimmune injury can produce substantial aminotransferase increases and may need evaluation. The pain pattern, gallstones, and rising direct bilirubin leave a treatable duct cause unresolved; targeted duct imaging is less invasive and more relevant first.
Reasoning steps for option D
What does a hepatocellular laboratory pattern raise concern for?
Toxic, ischemic, viral, or autoimmune injury can produce substantial aminotransferase increases and may need evaluation.
Why is biopsy not the preferred immediate discriminator?
The pain pattern, gallstones, and rising direct bilirubin leave a treatable duct cause unresolved; targeted duct imaging is less invasive and more relevant first.
Takeaway: An early aminotransferase spike and a narrow duct do not independently exclude choledocholithiasis.
The gallbladder drains through the cystic duct. No. Both liver drainage systems are obstructed at their junction, not at the gallbladder branch.
Reasoning steps for option A
Which structure depends directly on the cystic duct?
The gallbladder drains through the cystic duct.
Would that isolated site explain bilateral intrahepatic dilation?
No. Both liver drainage systems are obstructed at their junction, not at the gallbladder branch.
B. Right-left hepatic duct confluence (Best answer)
The right and left ducts meet at the hepatic confluence before entering the common hepatic duct. Both dilated intrahepatic systems end at that junction, with a nondistended duct downstream.
Reasoning steps for option B
Where do the two hepatic systems share an exit?
The right and left ducts meet at the hepatic confluence before entering the common hepatic duct.
How does that match the observed transition?
Both dilated intrahepatic systems end at that junction, with a nondistended duct downstream.
C. Ampulla of Vater (Why this does not fit)
The common bile duct and its communicating hepatic and gallbladder pathways lie upstream. The observed transition is at the hepatic junction, while the distal duct is not distended and has no filling defect.
Reasoning steps for option C
What lies upstream of an ampullary blockage?
The common bile duct and its communicating hepatic and gallbladder pathways lie upstream.
Which distribution argues against this distal site?
The observed transition is at the hepatic junction, while the distal duct is not distended and has no filling defect.
D. Intrapancreatic common bile duct (Why this does not fit)
The extrahepatic duct above the pancreas would lie upstream along with the hepatic branches. The distal common duct remains downstream of the demonstrated transition at the hepatic confluence.
Reasoning steps for option D
What should be upstream of an intrapancreatic duct block?
The extrahepatic duct above the pancreas would lie upstream along with the hepatic branches.
What contradicts that localization in this examination?
The distal common duct remains downstream of the demonstrated transition at the hepatic confluence.
Takeaway: Use the transition point, not jaundice alone, to localize the obstruction.
A. Progressive cholestasis from loss of intrahepatic ducts (Why this does not fit)
Loss of functioning intrahepatic ducts can cause persistent cholestasis. No. Imaging identifies an isolated cystic duct stone and a patent main biliary pathway, not diffuse intrahepatic duct disease.
Reasoning steps for option A
What can diffuse small-duct destruction produce?
Loss of functioning intrahepatic ducts can cause persistent cholestasis.
Is such duct loss shown in this episode?
No. Imaging identifies an isolated cystic duct stone and a patent main biliary pathway, not diffuse intrahepatic duct disease.
B. Marked bilirubinuria from blocked hepatic drainage (Why this does not fit)
Conjugated bilirubin can enter urine when its concentration in blood increases from impaired excretion. No. The main hepatic and common ducts remain patent, so substantial obstructive bilirubinuria is not predicted from this isolated lesion.
Reasoning steps for option B
When does conjugated bilirubin appear in urine?
Conjugated bilirubin can enter urine when its concentration in blood increases from impaired excretion.
Does the demonstrated stone block hepatic outflow?
No. The main hepatic and common ducts remain patent, so substantial obstructive bilirubinuria is not predicted from this isolated lesion.
C. Predominantly indirect bilirubin from biliary hemolysis (Why this does not fit)
Accelerated red-cell breakdown increases unconjugated bilirubin production. No. The described lesion is a local drainage problem, with no evidence of a hemolytic process.
Reasoning steps for option C
What causes an indirect bilirubin increase in hemolysis?
Does a cystic duct stone establish red-cell destruction?
No. The described lesion is a local drainage problem, with no evidence of a hemolytic process.
D. Little bilirubin change from this isolated block (Best answer)
The common hepatic duct and common bile duct provide the liver-to-intestine route independently of gallbladder emptying. It can inflame and distend the gallbladder without itself causing marked cholestatic hyperbilirubinemia; unexpected jaundice warrants another explanation.
Reasoning steps for option D
Which route remains open from liver to intestine?
The common hepatic duct and common bile duct provide the liver-to-intestine route independently of gallbladder emptying.
What does cystic duct obstruction therefore predict?
It can inflame and distend the gallbladder without itself causing marked cholestatic hyperbilirubinemia; unexpected jaundice warrants another explanation.
Takeaway: Marked jaundice in apparent isolated cholecystitis should prompt evaluation for another obstructive or hepatic process.
A. Intraluminal migration of a gallbladder stone (Why this does not fit)
A retained or migrated common duct stone can cause intermittent or persistent obstruction. Imaging shows a short fixed narrowing at the operative field rather than an intraductal filling defect.
Reasoning steps for option A
What can a migrated stone cause after biliary symptoms?
A retained or migrated common duct stone can cause intermittent or persistent obstruction.
Which described feature instead favors a stricture?
Imaging shows a short fixed narrowing at the operative field rather than an intraductal filling defect.
B. Multifocal inflammatory scarring of large ducts (Why this does not fit)
Multifocal stricturing with intervening duct changes supports a large-duct sclerosing cholangiopathy. The abnormality is a single short postoperative narrowing and the remaining ducts are smooth, making a local injury more plausible.
Reasoning steps for option B
What distribution often supports primary sclerosing cholangitis?
Multifocal stricturing with intervening duct changes supports a large-duct sclerosing cholangiopathy.
How does this duct map differ?
The abnormality is a single short postoperative narrowing and the remaining ducts are smooth, making a local injury more plausible.
C. Fibrotic repair after local biliary injury (Best answer)
Local injury, including ischemic damage, can heal with fibrosis that contracts the duct lumen. The timing and location favor postoperative scarring, but imaging without a mass does not by itself exclude malignancy; the stricture still needs appropriate assessment.
Reasoning steps for option C
How can an operative injury produce delayed narrowing?
Local injury, including ischemic damage, can heal with fibrosis that contracts the duct lumen.
Why is that the leading explanation rather than a final diagnosis?
The timing and location favor postoperative scarring, but imaging without a mass does not by itself exclude malignancy; the stricture still needs appropriate assessment.
D. Autoimmune destruction of small intrahepatic ducts (Why this does not fit)
Primary biliary cholangitis targets small intrahepatic ducts and can cause chronic cholestasis. A focal common hepatic duct narrowing at a recent operative site is a more direct structural explanation than diffuse small-duct injury.
Reasoning steps for option D
Which ducts are primarily affected in primary biliary cholangitis?
Primary biliary cholangitis targets small intrahepatic ducts and can cause chronic cholestasis.
Why does it fit this distribution less well?
A focal common hepatic duct narrowing at a recent operative site is a more direct structural explanation than diffuse small-duct injury.
Takeaway: A postoperative location makes a benign scar plausible without making malignancy impossible.
A. Fully covered metal stent for 6 to 12 months (Best answer)
It conditionally suggests a temporary fully covered self-expandable metal stent for 6 to 12 months. The cause is benign chronic pancreatitis, anatomy is distal, and follow-up permits planned extraction or reassessment rather than indefinite implantation.
Reasoning steps for option A
What stent strategy does the 2026 guideline suggest for chronic pancreatitis-associated strictures?
It conditionally suggests a temporary fully covered self-expandable metal stent for 6 to 12 months.
Why do this patient and interval fit that suggestion?
The cause is benign chronic pancreatitis, anatomy is distal, and follow-up permits planned extraction or reassessment rather than indefinite implantation.
B. Uncovered metal stent with indefinite symptom-based follow-up (Why this does not fit)
They can provide a durable lumen when long-term palliative drainage is intended. Tissue ingrowth can make an uncovered implant difficult to extract, while the benign-stricture strategy requires planned temporary treatment.
Reasoning steps for option B
Why are uncovered metal stents used in some malignant obstructions?
They can provide a durable lumen when long-term palliative drainage is intended.
Why is that strategy unsuitable for this confirmed benign cause?
Tissue ingrowth can make an uncovered implant difficult to extract, while the benign-stricture strategy requires planned temporary treatment.
C. Balloon dilation alone followed by routine yearly imaging (Why this does not fit)
Balloon dilation can help open selected benign strictures and is used in cause-specific strategies. For a chronic pancreatitis-associated stricture, the cited 2026 recommendation favors a temporary fully covered metal stent rather than this balloon-only annual follow-up plan.
Reasoning steps for option C
When might balloon dilation be part of treatment?
Balloon dilation can help open selected benign strictures and is used in cause-specific strategies.
Why does it not best match the requested recommendation?
For a chronic pancreatitis-associated stricture, the cited 2026 recommendation favors a temporary fully covered metal stent rather than this balloon-only annual follow-up plan.
D. Single plastic stent with no scheduled exchange visit (Why this does not fit)
Plastic stents can provide temporary drainage and form part of selected benign-stricture treatment protocols. A single indefinitely retained plastic stent does not match the cause-specific recommendation and lacks the follow-up needed to address occlusion and reassess the narrowing.
Reasoning steps for option D
What role can plastic stents have in biliary treatment?
Plastic stents can provide temporary drainage and form part of selected benign-stricture treatment protocols.
What is inadequate about this proposed plan?
A single indefinitely retained plastic stent does not match the cause-specific recommendation and lacks the follow-up needed to address occlusion and reassess the narrowing.
Takeaway: Benign-stricture treatment is cause-specific and includes a defined stent follow-up plan.
A. Absent urine bilirubin with reduced stool pigment (Why this does not fit)
Less bilirubin delivered to the intestine reduces stool pigment. Marked conjugated hyperbilirubinemia with preserved renal function supports bilirubinuria rather than the unconjugated pattern implied by its absence.
Reasoning steps for option A
How can obstruction affect stool color?
Less bilirubin delivered to the intestine reduces stool pigment.
Why is absent urine bilirubin the inconsistent half?
Marked conjugated hyperbilirubinemia with preserved renal function supports bilirubinuria rather than the unconjugated pattern implied by its absence.
B. Present urine bilirubin with reduced stool pigment (Best answer)
Conjugated bilirubin can be filtered into urine when its blood concentration increases. Minimal bile reaches the intestine, so stool pigment decreases; the two findings follow from the same impaired excretion pathway.
Reasoning steps for option B
Why can urine darken in obstructive conjugated hyperbilirubinemia?
Conjugated bilirubin can be filtered into urine when its blood concentration increases.
What happens to intestinal pigment delivery here?
Minimal bile reaches the intestine, so stool pigment decreases; the two findings follow from the same impaired excretion pathway.
C. Absent urine bilirubin with increased stool pigment (Why this does not fit)
Unconjugated bilirubin is albumin-bound and is not filtered into urine; hemolysis can increase pigment delivered to the intestine. Her bilirubin is predominantly direct, and the lesion limits rather than increases bile delivery to the intestine.
Reasoning steps for option C
Which bilirubin fraction is absent from urine in isolated hemolysis?
Unconjugated bilirubin is albumin-bound and is not filtered into urine; hemolysis can increase pigment delivered to the intestine.
Why does that pair not fit this patient?
Her bilirubin is predominantly direct, and the lesion limits rather than increases bile delivery to the intestine.
D. Present urine bilirubin with increased stool pigment (Why this does not fit)
Yes. Conjugated bilirubin is water soluble and can enter urine. The obstructed outlet reduces intestinal delivery, so increased stool pigment is not the expected companion finding.
Reasoning steps for option D
Can direct hyperbilirubinemia produce bilirubinuria?
Yes. Conjugated bilirubin is water soluble and can enter urine.
Which half of the pair conflicts with the obstruction?
The obstructed outlet reduces intestinal delivery, so increased stool pigment is not the expected companion finding.
Takeaway: Interpret the fractions and the drainage route together, rather than treating dark urine as evidence of hemolysis.
A. Magnetic resonance cholangiopancreatography (Why this does not fit)
MRCP can map a duct lesion when symptoms, liver chemistries, or prior imaging raise substantive concern. A mildly wide duct after remote cholecystectomy does not establish the cause of isolated ALP, especially with a healing fracture and normal GGT.
Reasoning steps for option A
What can MRCP clarify in suspected obstruction?
MRCP can map a duct lesion when symptoms, liver chemistries, or prior imaging raise substantive concern.
Why is fractionation the more focused test now?
A mildly wide duct after remote cholecystectomy does not establish the cause of isolated ALP, especially with a healing fracture and normal GGT.
B. ERCP with duct sampling (Why this does not fit)
ERCP can sample a duct lesion and provide drainage. There is no established hepatobiliary source for the isolated ALP increase and no symptomatic or biochemical evidence of obstruction.
Reasoning steps for option B
What could ERCP evaluate if a clinically significant stricture were suspected?
ERCP can sample a duct lesion and provide drainage.
What is missing before undertaking that risk here?
There is no established hepatobiliary source for the isolated ALP increase and no symptomatic or biochemical evidence of obstruction.
C. Antimitochondrial antibody measurement (Why this does not fit)
It helps evaluate primary biliary cholangitis in an appropriate persistent hepatic cholestatic pattern. This patient has a plausible bone source and normal accompanying hepatic tests; the first uncertainty is whether the ALP is hepatic at all.
Reasoning steps for option C
When is antimitochondrial antibody testing useful?
It helps evaluate primary biliary cholangitis in an appropriate persistent hepatic cholestatic pattern.
Why is enzyme-source confirmation more direct first?
This patient has a plausible bone source and normal accompanying hepatic tests; the first uncertainty is whether the ALP is hepatic at all.
D. Alkaline phosphatase isoenzyme fractionation (Best answer)
Bone formation during healing can increase the bone fraction of ALP. It can identify the enzyme source when normal GGT and bilirubin argue against automatically attributing the result to a biliary obstruction.
Reasoning steps for option D
Why can a fracture affect total ALP?
Bone formation during healing can increase the bone fraction of ALP.
How does fractionation answer the unresolved question?
It can identify the enzyme source when normal GGT and bilirubin argue against automatically attributing the result to a biliary obstruction.
Takeaway: Confirm the source of isolated ALP; incidental duct caliber should not force an invasive biliary diagnosis.
A. Give antibiotics and await complete renal recovery before drainage (Why this does not fit)
They treat bacterial infection and should be given promptly. Persistent obstruction sustains the source; acute kidney dysfunction is evidence of severity that strengthens, rather than postpones, source-control planning.
Reasoning steps for option A
What do antibiotics contribute in biliary sepsis?
They treat bacterial infection and should be given promptly.
Why should renal recovery not be a prerequisite for drainage?
Persistent obstruction sustains the source; acute kidney dysfunction is evidence of severity that strengthens, rather than postpones, source-control planning.
B. Resuscitate, give intravenous antibiotics, and arrange urgent biliary drainage (Best answer)
Hypotension, confusion, and acute kidney dysfunction accompany an obstructed and infected biliary system. Begin circulatory and respiratory support and antibiotics while organizing drainage as soon as feasible after initial stabilization, without waiting for full organ recovery.
Reasoning steps for option B
Which findings establish a severe presentation?
Hypotension, confusion, and acute kidney dysfunction accompany an obstructed and infected biliary system.
How should stabilization and drainage be coordinated?
Begin circulatory and respiratory support and antibiotics while organizing drainage as soon as feasible after initial stabilization, without waiting for full organ recovery.
C. Obtain elective MRCP and defer intervention pending the duct map (Why this does not fit)
MRCP can clarify uncertain anatomy or stones in a stable patient. A duct stone is already demonstrated and the patient has shock and organ dysfunction, so an elective mapping delay does not address the urgent problem.
Reasoning steps for option C
When is MRCP a useful first confirmatory step?
MRCP can clarify uncertain anatomy or stones in a stable patient.
Why would that sequence be hazardous here?
A duct stone is already demonstrated and the patient has shock and organ dysfunction, so an elective mapping delay does not address the urgent problem.
D. Treat presumed nonbiliary sepsis because abdominal pain is absent (Why this does not fit)
Not every patient with cholangitis has fever, jaundice, and reported right upper quadrant pain together. Rigors, direct hyperbilirubinemia, a duct stone, and upstream dilation strongly support biliary infection despite absent pain.
Reasoning steps for option D
Why can the classic symptom triad be misleading?
Not every patient with cholangitis has fever, jaundice, and reported right upper quadrant pain together.
Which evidence still identifies a biliary source?
Rigors, direct hyperbilirubinemia, a duct stone, and upstream dilation strongly support biliary infection despite absent pain.
Takeaway: The absence of one classic symptom does not outweigh evidence of an obstructed system with sepsis and organ dysfunction.
A. Delay drainage until hypotension develops (Why this does not fit)
It would indicate clinical deterioration and possible severe organ dysfunction. This patient already has a moderate-severity profile and persistent obstruction; waiting for shock would defer indicated source control.
Reasoning steps for option A
What would new hypotension signify?
It would indicate clinical deterioration and possible severe organ dysfunction.
Why is that not the threshold to await?
This patient already has a moderate-severity profile and persistent obstruction; waiting for shock would defer indicated source control.
B. Repeat imaging after a prolonged antibiotic-only trial (Why this does not fit)
Further imaging can help when the cause or location of obstruction remains uncertain. The stone is already documented, and infection persists; additional mapping should not replace early decompression of a known source.
Reasoning steps for option B
What can additional imaging clarify?
Further imaging can help when the cause or location of obstruction remains uncertain.
Why is a prolonged imaging-first delay unnecessary here?
The stone is already documented, and infection persists; additional mapping should not replace early decompression of a known source.
C. Arrange early drainage during this admission (Best answer)
No. Multiple moderate-severity features can be present before organ dysfunction develops. Advanced age, high fever, leukocytosis, a retained stone, and persistent symptoms favor early biliary decompression while antibiotics continue.
Reasoning steps for option C
Does normal blood pressure make all cholangitis mild?
No. Multiple moderate-severity features can be present before organ dysfunction develops.
Which features support early drainage in this patient?
Advanced age, high fever, leukocytosis, a retained stone, and persistent symptoms favor early biliary decompression while antibiotics continue.
D. Schedule outpatient drainage after antibiotics finish (Why this does not fit)
A stable patient without ongoing infection may sometimes complete a planned outpatient evaluation or treatment pathway. She has persistent fever and jaundice with multiple severity features and a retained stone, requiring inpatient treatment and early drainage.
Reasoning steps for option D
When might elective outpatient duct management be considered?
A stable patient without ongoing infection may sometimes complete a planned outpatient evaluation or treatment pathway.
Why does that not fit the present course?
She has persistent fever and jaundice with multiple severity features and a retained stone, requiring inpatient treatment and early drainage.
Takeaway: Early drainage is not reserved for patients who have already developed shock.
A. Elective MRCP for both patients before treatment decisions (Why this does not fit)
A stable patient with unresolved diagnostic uncertainty can often undergo MRCP before intervention. B already has a documented stone and severe physiologic deterioration; resuscitation, antibiotics, and source control should not await elective mapping.
Reasoning steps for option A
When is a noninvasive map an appropriate priority?
A stable patient with unresolved diagnostic uncertainty can often undergo MRCP before intervention.
Why should B not follow the same elective sequence?
B already has a documented stone and severe physiologic deterioration; resuscitation, antibiotics, and source control should not await elective mapping.
B. Urgent decompression for both patients based on duct width (Why this does not fit)
Dilation can support impaired outflow when considered with symptoms, laboratory results, and anatomy. Patient A has stable postoperative caliber and normal chemistries, whereas B has an acutely infected obstructed system with organ dysfunction.
Reasoning steps for option B
What does a wide duct contribute to an obstruction assessment?
Dilation can support impaired outflow when considered with symptoms, laboratory results, and anatomy.
Why should width not produce the same emergency plan here?
Patient A has stable postoperative caliber and normal chemistries, whereas B has an acutely infected obstructed system with organ dysfunction.
C. Antibiotics for B alone; drainage reserved for greater dilation (Why this does not fit)
Antibiotics are essential to treat the infectious component. The current obstruction and organ dysfunction already justify urgent drainage planning; waiting for more dilation would not address the severity of the illness.
Reasoning steps for option C
What role do antibiotics play in cholangitis?
Antibiotics are essential to treat the infectious component.
Why is a larger duct not the missing indication?
The current obstruction and organ dysfunction already justify urgent drainage planning; waiting for more dilation would not address the severity of the illness.
D. Selective evaluation for A; resuscitation and urgent drainage for B (Best answer)
Prior cholecystectomy and long-term stability can contextualize mild dilation, while systemic illness establishes a separate urgency assessment. A has no current evidence of clinically significant obstruction; B has a stone, rigors, hypotension, and confusion requiring immediate treatment and source control.
Reasoning steps for option D
Why can the same measurement carry different meanings?
Prior cholecystectomy and long-term stability can contextualize mild dilation, while systemic illness establishes a separate urgency assessment.
Which features determine the difference in these plans?
A has no current evidence of clinically significant obstruction; B has a stone, rigors, hypotension, and confusion requiring immediate treatment and source control.
Takeaway: A duct measurement is an anatomic observation, not a severity score.
A. Finish antibiotics before reassessing the obstructed duct (Why this does not fit)
Antibiotics can reduce bacterial burden and systemic inflammation. No. Rising bilirubin and a persistent obstructing stone demonstrate that the mechanical source remains and should not await completion of the antibiotic course.
Reasoning steps for option A
Why can fever fall after antibiotics?
Antibiotics can reduce bacterial burden and systemic inflammation.
Does that response establish adequate bile flow?
No. Rising bilirubin and a persistent obstructing stone demonstrate that the mechanical source remains and should not await completion of the antibiotic course.
B. Stop biliary treatment because the fever has resolved (Why this does not fit)
Clinical improvement together with evidence of restored drainage would support a resolving outflow problem. The stone still obstructs the duct and bilirubin is rising, so improvement in temperature alone cannot establish source resolution.
Reasoning steps for option B
What would support resolution of a biliary obstruction?
Clinical improvement together with evidence of restored drainage would support a resolving outflow problem.
Which supplied findings contradict that conclusion?
The stone still obstructs the duct and bilirubin is rising, so improvement in temperature alone cannot establish source resolution.
C. Reserve drainage for a subsequently positive blood culture (Why this does not fit)
They can identify organisms and guide antibiotic narrowing when obtained without delaying care. A culture may be negative after antibiotics and is not required to recognize the documented obstructed biliary source with persistent cholestasis.
Reasoning steps for option C
What can blood cultures contribute?
They can identify organisms and guide antibiotic narrowing when obtained without delaying care.
Why should they not decide whether this duct needs treatment?
A culture may be negative after antibiotics and is not required to recognize the documented obstructed biliary source with persistent cholestasis.
D. Continue antibiotics and arrange early therapeutic ERCP (Best answer)
ERCP can decompress the duct and treat the obstructing stone. The rising bilirubin and persistent stone show continued impaired outflow despite a partial systemic response to medical treatment.
Reasoning steps for option D
What component does ERCP address that antibiotics do not?
ERCP can decompress the duct and treat the obstructing stone.
Why is drainage still needed after initial improvement?
The rising bilirubin and persistent stone show continued impaired outflow despite a partial systemic response to medical treatment.
Takeaway: A lower temperature is not proof that an obstructed biliary system has been decompressed.
A. Establish drainage and defer difficult stone clearance (Best answer)
An unstable patient may not tolerate prolonged comprehensive stone treatment during the initial ERCP. A stent can restore drainage promptly through access already obtained; difficult clearance can follow after stabilization.
Reasoning steps for option A
When can decompression alone be the safer initial strategy?
An unstable patient may not tolerate prolonged comprehensive stone treatment during the initial ERCP.
What is immediately achievable in this case?
A stent can restore drainage promptly through access already obtained; difficult clearance can follow after stabilization.
B. End ERCP and obtain percutaneous drainage instead (Why this does not fit)
It is valuable when endoscopic drainage fails, is unavailable, or is unsuitable. Endoscopic access above the obstruction is already secure and prompt stent drainage is feasible, so switching would add delay without addressing an access failure.
Reasoning steps for option B
When is percutaneous drainage useful?
It is valuable when endoscopic drainage fails, is unavailable, or is unsuitable.
What makes switching routes unnecessary here?
Endoscopic access above the obstruction is already secure and prompt stent drainage is feasible, so switching would add delay without addressing an access failure.
C. Perform cholecystectomy before treating the common duct (Why this does not fit)
It can reduce recurrent gallstone events when appropriate after the acute episode. The current problem is an infected obstructed common duct in an unstable patient; immediate duct drainage is available and should not await gallbladder surgery.
Reasoning steps for option C
What future problem can cholecystectomy address?
It can reduce recurrent gallstone events when appropriate after the acute episode.
Why is it not the immediate procedural goal?
The current problem is an infected obstructed common duct in an unstable patient; immediate duct drainage is available and should not await gallbladder surgery.
D. Complete lithotripsy before placing a drainage stent (Why this does not fit)
Comprehensive treatment is useful when the patient can tolerate the required procedure. Vasopressor dependence and a predicted prolonged lithotripsy session favor prompt decompression rather than delaying it until full clearance.
Reasoning steps for option D
When is combined drainage and stone clearance reasonable?
Comprehensive treatment is useful when the patient can tolerate the required procedure.
Why is the proposed order poorly suited to this patient?
Vasopressor dependence and a predicted prolonged lithotripsy session favor prompt decompression rather than delaying it until full clearance.
Takeaway: Urgent source control does not require completing every technically difficult definitive treatment in the same session.
A. Percutaneous transhepatic biliary drainage (Why this does not fit)
It can drain an obstructed system when endoscopic routes are unavailable, unsuccessful, or unsuitable. An expert EUS service and a suitable transmural route are available; current ESGE guidance favors that route after failed ERCP in malignant obstruction.
Reasoning steps for option A
When can percutaneous drainage provide effective rescue?
It can drain an obstructed system when endoscopic routes are unavailable, unsuccessful, or unsuitable.
Why is it not the preferred next option under these supplied conditions?
An expert EUS service and a suitable transmural route are available; current ESGE guidance favors that route after failed ERCP in malignant obstruction.
B. Open surgical biliary bypass as the first rescue (Why this does not fit)
Surgical palliation may be appropriate in selected patients within a multidisciplinary treatment plan. A less invasive, feasible expert endoscopic drainage route is available after failed ERCP in unresectable disease.
Reasoning steps for option B
When can a surgical bypass be considered?
Surgical palliation may be appropriate in selected patients within a multidisciplinary treatment plan.
Why is it not the favored immediate rescue in this case?
A less invasive, feasible expert endoscopic drainage route is available after failed ERCP in unresectable disease.
C. Repeat standard ERCP without a changed access strategy (Why this does not fit)
A repeat attempt can succeed when a remediable technical problem or more suitable expertise changes the prospect of access. Tumor prevents papillary access, while an alternative expert transmural route is already demonstrated to be feasible.
Reasoning steps for option C
What sometimes justifies a repeat ERCP attempt?
A repeat attempt can succeed when a remediable technical problem or more suitable expertise changes the prospect of access.
What makes an unchanged attempt less appropriate here?
Tumor prevents papillary access, while an alternative expert transmural route is already demonstrated to be feasible.
D. EUS-guided transmural biliary drainage (Best answer)
ESGE favors expert EUS-guided transmural drainage over percutaneous drainage after failed ERCP for malignant obstruction when feasible. The obstruction is malignant and distal, ERCP has failed, and the experienced service has confirmed a suitable route without the stated major barriers.
Reasoning steps for option D
What is the relevant current rescue recommendation?
ESGE favors expert EUS-guided transmural drainage over percutaneous drainage after failed ERCP for malignant obstruction when feasible.
Which patient-specific conditions make that recommendation applicable?
The obstruction is malignant and distal, ERCP has failed, and the experienced service has confirmed a suitable route without the stated major barriers.
Takeaway: Rescue drainage depends on the cause, anatomy, available expertise, and feasibility, not a fixed rule that failed ERCP always requires a percutaneous catheter.
A. Continue antibiotics until the transfer can be scheduled (Why this does not fit)
No. They treat infection but do not correct the anastomotic outflow obstruction. The patient has shock with a documented source and an immediately feasible drainage route; delay would prolong inadequate source control.
Reasoning steps for option A
Can antibiotics alone always compensate for an obstructed infected system?
No. They treat infection but do not correct the anastomotic outflow obstruction.
Why is a prolonged wait unsafe in this presentation?
The patient has shock with a documented source and an immediately feasible drainage route; delay would prolong inadequate source control.
B. Arrange immediate percutaneous transhepatic drainage (Best answer)
It provides biliary decompression when endoscopic access is unsuccessful or unavailable and the anatomy permits safe drainage. The patient has ongoing severe infection and can receive source control now, whereas expert endoscopic rescue would be substantially delayed.
Reasoning steps for option B
When is a percutaneous route particularly valuable?
It provides biliary decompression when endoscopic access is unsuccessful or unavailable and the anatomy permits safe drainage.
Why does it best fit the current urgency?
The patient has ongoing severe infection and can receive source control now, whereas expert endoscopic rescue would be substantially delayed.
C. Wait for bilirubin to fall before selecting a drainage route (Why this does not fit)
A subsequent decline can support improved bile excretion. The outflow remains obstructed and shock is present; waiting for biochemical recovery before providing drainage reverses the needed sequence.
Reasoning steps for option C
What can bilirubin trends indicate after successful drainage?
A subsequent decline can support improved bile excretion.
Why is that trend not a prerequisite for intervention?
The outflow remains obstructed and shock is present; waiting for biochemical recovery before providing drainage reverses the needed sequence.
D. Repeat conventional ERCP before considering another route (Why this does not fit)
A reconstructed gastrointestinal route may prevent a conventional endoscope from reaching the biliary anastomosis. The access barrier is already established, while an effective percutaneous route is available without a transfer delay.
Reasoning steps for option D
What limitation can altered anatomy create?
A reconstructed gastrointestinal route may prevent a conventional endoscope from reaching the biliary anastomosis.
Why is another unchanged attempt not the best next step?
The access barrier is already established, while an effective percutaneous route is available without a transfer delay.
Takeaway: An expert-route preference must not become an avoidable delay in source control when a suitable alternative is available.
A. Delay surgery for percutaneous drainage and biochemical normalization (Why this does not fit)
Percutaneous drainage is useful when drainage is indicated and an endoscopic route is unavailable or unsuitable. There is no established need for preoperative drainage or endoscopic-access failure, and delaying planned surgery merely to normalize bilirubin is not required by the stated pathway.
Reasoning steps for option A
When is a percutaneous catheter useful in an obstructed system?
Percutaneous drainage is useful when drainage is indicated and an endoscopic route is unavailable or unsuitable.
Why is that not the preferred preoperative sequence here?
There is no established need for preoperative drainage or endoscopic-access failure, and delaying planned surgery merely to normalize bilirubin is not required by the stated pathway.
B. Proceed through the surgical plan without routine preoperative drainage (Best answer)
Current ESGE guidance allows avoidance in selected stable patients proceeding to upfront surgery within 1 to 2 weeks. Surgery is in seven days, with no cholangitis, intense pruritus, or neoadjuvant interval that would favor drainage first.
Reasoning steps for option B
When can routine preoperative drainage be avoided?
Current ESGE guidance allows avoidance in selected stable patients proceeding to upfront surgery within 1 to 2 weeks.
Which supplied features support that pathway?
Surgery is in seven days, with no cholangitis, intense pruritus, or neoadjuvant interval that would favor drainage first.
C. Place an endoscopic stent solely to normalize bilirubin before surgery (Why this does not fit)
Cholangitis, severe symptoms, a prolonged delay, or jaundice before neoadjuvant treatment can justify it. No. This stable patient has imminent surgery and none of the stated additional indications; routine stenting adds another procedure without the supplied justification.
Reasoning steps for option C
What circumstances can favor preoperative drainage?
Cholangitis, severe symptoms, a prolonged delay, or jaundice before neoadjuvant treatment can justify it.
Is a bilirubin value alone sufficient in this planned interval?
No. This stable patient has imminent surgery and none of the stated additional indications; routine stenting adds another procedure without the supplied justification.
D. Perform a surgical biliary bypass before reassessing tumor resection (Why this does not fit)
Bypass may provide palliation in selected unresectable disease or specific operative circumstances. The tumor is considered resectable with definitive surgery scheduled, so an additional bypass-first pathway does not address an established indication.
Reasoning steps for option D
When can a biliary bypass be part of cancer care?
Bypass may provide palliation in selected unresectable disease or specific operative circumstances.
Why does this proposal not fit the current treatment intent?
The tumor is considered resectable with definitive surgery scheduled, so an additional bypass-first pathway does not address an established indication.
Takeaway: Stable malignant jaundice does not automatically require a preoperative stent when definitive surgery is imminent.
A. Coordinate endoscopic stent drainage before neoadjuvant treatment (Best answer)
A jaundiced patient facing a prolonged treatment interval may need bile flow restored before systemic therapy. The cause is confirmed malignancy, bilirubin is substantially increased, and the team has identified jaundice as a barrier to the planned regimen.
Reasoning steps for option A
Why can neoadjuvant treatment change the drainage decision?
A jaundiced patient facing a prolonged treatment interval may need bile flow restored before systemic therapy.
What features support that approach here?
The cause is confirmed malignancy, bilirubin is substantially increased, and the team has identified jaundice as a barrier to the planned regimen.
B. Repeat diagnostic cytology before considering any drainage (Why this does not fit)
It is important when the etiology or required histologic diagnosis remains unresolved. No. Malignancy is biopsy-confirmed; the current task is managing obstructive jaundice so that the agreed treatment can proceed.
Reasoning steps for option B
When is additional tissue acquisition important?
It is important when the etiology or required histologic diagnosis remains unresolved.
Is that the limiting uncertainty in this patient?
No. Malignancy is biopsy-confirmed; the current task is managing obstructive jaundice so that the agreed treatment can proceed.
C. Give prophylactic antibiotics throughout the neoadjuvant interval (Why this does not fit)
They treat bacterial infection rather than the physical narrowing of the duct. The patient has obstructive jaundice without current infection; antibiotics do not restore bile flow or replace a coordinated drainage plan.
Reasoning steps for option C
What do antibiotics address when cholangitis is present?
They treat bacterial infection rather than the physical narrowing of the duct.
Why would prolonged antibiotics not solve this treatment barrier?
The patient has obstructive jaundice without current infection; antibiotics do not restore bile flow or replace a coordinated drainage plan.
D. Wait for definitive surgery before treating the jaundice (Why this does not fit)
Selected stable patients proceeding to imminent upfront surgery may not need routine preoperative drainage. Her surgery is months away and jaundice interferes with neoadjuvant therapy, so waiting would obstruct the intended treatment sequence.
Reasoning steps for option D
When can preoperative drainage be omitted?
Selected stable patients proceeding to imminent upfront surgery may not need routine preoperative drainage.
Why does this patient fall outside that circumstance?
Her surgery is months away and jaundice interferes with neoadjuvant therapy, so waiting would obstruct the intended treatment sequence.
Takeaway: Drainage decisions depend on the planned treatment interval as well as the presence or absence of infection.
A. Combine EUS-guided and ERCP-based tissue acquisition (Best answer)
For jaundice with a distal extrahepatic stricture and no pancreatic mass, complementary EUS-guided and ERCP-based sampling is preferred. Only initial brushing has been nondiagnostic, so the patient still needs the complementary lesion-directed assessment, with further targeted methods if uncertainty persists.
Reasoning steps for option A
Which location-specific strategy does ESGE recommend?
For jaundice with a distal extrahepatic stricture and no pancreatic mass, complementary EUS-guided and ERCP-based sampling is preferred.
Why is that the appropriate next diagnostic framework?
Only initial brushing has been nondiagnostic, so the patient still needs the complementary lesion-directed assessment, with further targeted methods if uncertainty persists.
B. Label the stricture benign and stop tissue evaluation (Why this does not fit)
It establishes that the submitted sample did not provide a diagnostic result, not that malignancy is absent. Jaundice and an unexplained distal stricture persist, and the planned complementary tissue evaluation has not been completed.
Reasoning steps for option B
What does a nondiagnostic cytology result establish?
It establishes that the submitted sample did not provide a diagnostic result, not that malignancy is absent.
What makes stopping inappropriate here?
Jaundice and an unexplained distal stricture persist, and the planned complementary tissue evaluation has not been completed.
C. Use a repeat CA 19-9 level as the sole diagnostic arbiter (Why this does not fit)
It can contribute contextual information, but benign cholestasis and malignancy can both affect the result. A marker alone cannot establish the cause of this persistent stricture or resolve the limitations of the nondiagnostic brush sample.
Reasoning steps for option C
What can a tumor marker add to stricture assessment?
It can contribute contextual information, but benign cholestasis and malignancy can both affect the result.
Why can it not replace tissue evaluation here?
A marker alone cannot establish the cause of this persistent stricture or resolve the limitations of the nondiagnostic brush sample.
D. Obtain a random liver biopsy instead of lesion-directed samples (Why this does not fit)
It may help characterize intrahepatic disease when noninvasive evaluation leaves that question unresolved. The unresolved lesion is a focal distal extrahepatic stricture; random parenchymal tissue is not the best way to determine its etiology.
Reasoning steps for option D
When can liver biopsy be helpful in cholestasis?
It may help characterize intrahepatic disease when noninvasive evaluation leaves that question unresolved.
Why is lesion-directed sampling more appropriate here?
The unresolved lesion is a focal distal extrahepatic stricture; random parenchymal tissue is not the best way to determine its etiology.
Takeaway: A negative or nondiagnostic brush sample must be interpreted in light of the unresolved clinical and imaging problem.
A. Perform urgent ERCP and defer gallbladder surgery indefinitely (Why this does not fit)
Cholangitis or persistent obstruction would supply a therapeutic duct indication. There is no retained duct stone or ongoing cholestasis, and deferring gallbladder care indefinitely leaves the source of recurrent events untreated.
Reasoning steps for option A
What would make urgent ERCP appropriate?
Cholangitis or persistent obstruction would supply a therapeutic duct indication.
Why does this two-part plan not fit the findings?
There is no retained duct stone or ongoing cholestasis, and deferring gallbladder care indefinitely leaves the source of recurrent events untreated.
B. Treat with antibiotics and omit further gallbladder management (Why this does not fit)
They are central when a biliary infection such as cholangitis is present. No infection is described, and antibiotics do not address the retained gallbladder stones responsible for recurrent biliary events.
Reasoning steps for option B
When are antibiotics central to biliary treatment?
They are central when a biliary infection such as cholangitis is present.
Why does this strategy fail to address the actual future risk?
No infection is described, and antibiotics do not address the retained gallbladder stones responsible for recurrent biliary events.
C. Place a prophylactic duct stent and schedule delayed reassessment (Why this does not fit)
It provides drainage when outflow is obstructed or temporary decompression is otherwise indicated. MRCP and laboratory improvement show no current drainage problem, so a prophylactic stent adds procedural and follow-up burdens without the supplied indication.
Reasoning steps for option C
What is a duct stent intended to accomplish?
It provides drainage when outflow is obstructed or temporary decompression is otherwise indicated.
What is missing in this resolving episode?
MRCP and laboratory improvement show no current drainage problem, so a prophylactic stent adds procedural and follow-up burdens without the supplied indication.
D. Avoid urgent ERCP and arrange same-admission cholecystectomy (Best answer)
It is not routinely indicated without cholangitis or ongoing biliary obstruction. Gallbladder stones remain, so an appropriate same-admission cholecystectomy plan for mild pancreatitis addresses recurrent biliary events.
Reasoning steps for option D
When is urgent ERCP unnecessary in gallstone pancreatitis?
It is not routinely indicated without cholangitis or ongoing biliary obstruction.
What still requires a preventive plan here?
Gallbladder stones remain, so an appropriate same-admission cholecystectomy plan for mild pancreatitis addresses recurrent biliary events.
Takeaway: Pancreatitis does not by itself mandate urgent ERCP; resolving mild gallstone pancreatitis still needs recurrence prevention.
It can produce ductular reaction and progressive portal-based fibrosis that advances to bridging septa and nodular remodeling. The chronic liver changes follow an established postoperative outflow obstruction rather than an unexplained primary cholangiopathy.
Reasoning steps for option A
What does persistent mechanical cholestasis do to portal structures?
It can produce ductular reaction and progressive portal-based fibrosis that advances to bridging septa and nodular remodeling.
Why is the term secondary appropriate here?
The chronic liver changes follow an established postoperative outflow obstruction rather than an unexplained primary cholangiopathy.
B. Drug-induced ductopenic liver disease (Why this does not fit)
Loss of small ducts can produce prolonged cholestatic injury and fibrosis. No relevant drug exposure or dominant duct-loss pattern is given, while a longstanding obstructing stricture is documented.
Reasoning steps for option B
What can drug-related duct loss cause?
Loss of small ducts can produce prolonged cholestatic injury and fibrosis.
Why is it less fitting than the mechanical explanation?
No relevant drug exposure or dominant duct-loss pattern is given, while a longstanding obstructing stricture is documented.
C. Primary sclerosing cholangitis (Why this does not fit)
Multifocal inflammatory stricturing can produce persistent cholestasis and advanced fibrosis. A single longstanding postoperative stricture explains the obstruction, and MRCP lacks the described multifocal irregularity.
Reasoning steps for option C
What biliary pattern often supports primary sclerosing cholangitis?
Multifocal inflammatory stricturing can produce persistent cholestasis and advanced fibrosis.
How do the history and map differ here?
A single longstanding postoperative stricture explains the obstruction, and MRCP lacks the described multifocal irregularity.
D. Primary biliary cholangitis (Why this does not fit)
Small intrahepatic duct injury can cause chronic cholestasis and eventually cirrhosis. A longstanding focal postoperative obstruction is documented, with a compatible portal-based response; the stated history does not favor a primary autoimmune small-duct process.
Reasoning steps for option D
What can primary biliary cholangitis produce over time?
Small intrahepatic duct injury can cause chronic cholestasis and eventually cirrhosis.
What provides a more direct explanation in this patient?
A longstanding focal postoperative obstruction is documented, with a compatible portal-based response; the stated history does not favor a primary autoimmune small-duct process.
Takeaway: Cirrhosis can be the downstream result of a chronic mechanical biliary lesion; it is not evidence that infection had to precede fibrosis.
A. The persistent varices prove that drainage has failed (Why this does not fit)
Varices reflect portal hypertension and can remain when fibrotic architecture persists. No. Imaging and falling bilirubin support better drainage; portal manifestations can persist on a different recovery timescale.
Reasoning steps for option A
What does variceal persistence reflect?
Varices reflect portal hypertension and can remain when fibrotic architecture persists.
Do they override direct evidence of improved duct patency?
No. Imaging and falling bilirubin support better drainage; portal manifestations can persist on a different recovery timescale.
B. The bilirubin decline establishes complete reversal of cirrhosis (Why this does not fit)
It supports improved excretion and relief of the cholestatic component. Bridging fibrosis and portal hypertension do not disappear simply because excretion improves, and the patient still has structural disease manifestations.
Reasoning steps for option B
What does falling bilirubin support after decompression?
It supports improved excretion and relief of the cholestatic component.
Why does it not prove architectural normalization?
Bridging fibrosis and portal hypertension do not disappear simply because excretion improves, and the patient still has structural disease manifestations.
C. Bile flow has improved while chronic structural disease persists (Best answer)
Yes. Bile excretion can improve before portal-based scarring and its hemodynamic consequences substantially change. Continue assessment of chronic liver disease and portal hypertension; possible fibrosis regression after durable relief is variable and is not equivalent to an immediate cure.
Reasoning steps for option C
Can different components of liver disease recover at different rates?
Yes. Bile excretion can improve before portal-based scarring and its hemodynamic consequences substantially change.
What does that mean for follow-up here?
Continue assessment of chronic liver disease and portal hypertension; possible fibrosis regression after durable relief is variable and is not equivalent to an immediate cure.
D. The remaining findings establish a new unrelated cholangiopathy (Why this does not fit)
Another diagnosis is worth investigating when the course or findings are not explained by the known disease. No. Residual portal hypertension after longstanding secondary cirrhosis already accounts for their persistence despite restored flow.
Reasoning steps for option D
When should another liver disease be considered?
Another diagnosis is worth investigating when the course or findings are not explained by the known disease.
Is a new primary cholangiopathy required to explain these findings?
No. Residual portal hypertension after longstanding secondary cirrhosis already accounts for their persistence despite restored flow.
Takeaway: Biochemical improvement, duct patency, and reversal of chronic liver architecture are related but nonidentical outcomes.
A. Occult distal stone; immediate ERCP for empiric duct clearance (Why this does not fit)
Recurrent biliary pain, a duct filling defect, or an appropriate obstructive laboratory and imaging profile can support it. The chronic serologic pattern supports small-duct autoimmune disease, while imaging and history provide no demonstrated mechanical target for urgent clearance.
Reasoning steps for option A
When would a distal stone be a strong possibility?
Recurrent biliary pain, a duct filling defect, or an appropriate obstructive laboratory and imaging profile can support it.
Why is empiric clearance not supported by the complete findings here?
The chronic serologic pattern supports small-duct autoimmune disease, while imaging and history provide no demonstrated mechanical target for urgent clearance.
B. Postoperative common duct scar; endoscopic dilation and stenting (Why this does not fit)
Prior biliary injury with a focal narrowing and upstream dilation would support that diagnosis. There is no surgical history, focal stricture, or upstream dilation; the serologic findings instead support an intrahepatic process.
Reasoning steps for option B
What history and imaging would favor a postoperative scar?
Prior biliary injury with a focal narrowing and upstream dilation would support that diagnosis.
Which required elements are absent?
There is no surgical history, focal stricture, or upstream dilation; the serologic findings instead support an intrahepatic process.
C. Small intrahepatic duct injury; hepatology-directed evaluation (Best answer)
Yes. MRCP displays the larger duct system and does not exclude a microscopic small-duct cholangiopathy. Persistent cholestatic liver chemistries and strongly positive antimitochondrial antibodies favor primary biliary cholangitis rather than a drainable extrahepatic obstruction.
Reasoning steps for option C
Can small-duct disease coexist with a normal MRCP?
Yes. MRCP displays the larger duct system and does not exclude a microscopic small-duct cholangiopathy.
Which results direct the evaluation in this patient?
Persistent cholestatic liver chemistries and strongly positive antimitochondrial antibodies favor primary biliary cholangitis rather than a drainable extrahepatic obstruction.
D. Large-duct sclerosing disease; drainage of a dominant stricture (Why this does not fit)
A clinically significant dominant or high-grade narrowing on duct evaluation can require a specific therapeutic plan. MRCP lacks multifocal large-duct abnormalities or a target stricture, while the antibody and chemistry pattern favors a different small-duct disorder.
Reasoning steps for option D
What would support a drainable large-duct sclerosing lesion?
A clinically significant dominant or high-grade narrowing on duct evaluation can require a specific therapeutic plan.
Why is that not the supplied problem?
MRCP lacks multifocal large-duct abnormalities or a target stricture, while the antibody and chemistry pattern favors a different small-duct disorder.
Takeaway: Normal large-duct imaging does not exclude cholestatic small-duct disease, and cholestasis alone does not establish a therapeutic ERCP target.
A. Treat as progressive cirrhosis without further stent intervention (Why this does not fit)
Yes. Prolonged injury can cause portal fibrosis and structural liver disease. The abrupt rigors, new organ dysfunction, and poorly draining stent identify an acute obstructed infectious source requiring immediate attention.
Reasoning steps for option A
Can chronic obstruction cause cirrhosis?
Yes. Prolonged injury can cause portal fibrosis and structural liver disease.
Why does that not explain away the urgent findings?
The abrupt rigors, new organ dysfunction, and poorly draining stent identify an acute obstructed infectious source requiring immediate attention.
B. Urgently restore drainage and arrange a new stent follow-up plan (Best answer)
Stent occlusion or dysfunction can recreate obstruction and permit cholangitis. Urgent assessment and restoration of drainage, usually including stent exchange or extraction as appropriate, addresses the source; a responsible service and scheduled follow-up address recurrence.
Reasoning steps for option B
What risk accompanies an overdue temporary stent?
Stent occlusion or dysfunction can recreate obstruction and permit cholangitis.
What is required beyond antibiotics in this episode?
Urgent assessment and restoration of drainage, usually including stent exchange or extraction as appropriate, addresses the source; a responsible service and scheduled follow-up address recurrence.
C. Wait for elective stricture reassessment after creatinine normalizes (Why this does not fit)
Stable patients need planned reassessment of stricture response and temporary-stent management. Confusion, worsening kidney function, rigors, and poor drainage indicate an acute severe infectious problem that should not await renal normalization.
Reasoning steps for option C
When is elective reassessment appropriate in stent care?
Stable patients need planned reassessment of stricture response and temporary-stent management.
Why is this not an elective episode?
Confusion, worsening kidney function, rigors, and poor drainage indicate an acute severe infectious problem that should not await renal normalization.
D. Continue the same stent and extend antibiotics for several weeks (Why this does not fit)
No. Antibiotics can improve infection while mechanical drainage remains impaired. Imaging and clinical deterioration indicate failed drainage, so extending antibiotics without source control leaves the obstructed system untreated.
Reasoning steps for option D
Can an antibiotic response establish adequate stent patency?
No. Antibiotics can improve infection while mechanical drainage remains impaired.
What makes retaining this plan inadequate?
Imaging and clinical deterioration indicate failed drainage, so extending antibiotics without source control leaves the obstructed system untreated.
Takeaway: A temporary stent is a treatment with an endpoint and follow-up obligation, not permanent proof of a patent biliary tree.
A. Fully covered metal stent extending above the confluence (Why this does not fit)
It can be considered in selected strictures, particularly those sufficiently distal to the main hepatic confluence. The stricture is only 6 mm below the junction; a covered segment above it could obstruct branch drainage, so this is not the suitable distal anatomy described in the guidance.
Reasoning steps for option A
When can a fully covered metal stent be an option after cholecystectomy?
It can be considered in selected strictures, particularly those sufficiently distal to the main hepatic confluence.
What creates a problem in this proposed placement?
The stricture is only 6 mm below the junction; a covered segment above it could obstruct branch drainage, so this is not the suitable distal anatomy described in the guidance.
B. Multiple plastic stents with planned serial exchanges (Best answer)
It suggests a temporary multiple-plastic-stent strategy, with covered metal stents reserved for selected circumstances. The lesion is close to the hepatic confluence and follow-up is reliable, favoring a planned branch-conscious plastic-stent strategy rather than a covered implant across the junction.
Reasoning steps for option B
What does current guidance suggest for postcholecystectomy strictures?
It suggests a temporary multiple-plastic-stent strategy, with covered metal stents reserved for selected circumstances.
Why does the anatomy in this case favor that approach?
The lesion is close to the hepatic confluence and follow-up is reliable, favoring a planned branch-conscious plastic-stent strategy rather than a covered implant across the junction.
C. Balloon dilation alone followed by routine yearly imaging (Why this does not fit)
Yes. It can help open the narrowing as part of an endoscopic treatment strategy. For a postcholecystectomy stricture selected for endoscopic therapy, the cited guidance favors temporary multiple stents rather than relying on dilation alone with only annual follow-up.
Reasoning steps for option C
Can balloon dilation contribute to benign-stricture treatment?
Yes. It can help open the narrowing as part of an endoscopic treatment strategy.
Why is this not the best match to the specified cause and plan?
For a postcholecystectomy stricture selected for endoscopic therapy, the cited guidance favors temporary multiple stents rather than relying on dilation alone with only annual follow-up.
D. Uncovered metal stent with indefinite symptom-based follow-up (Why this does not fit)
Tissue ingrowth makes it difficult to extract and can create a long-term management problem. The diagnosis is benign and both branch drainage and planned reassessment matter; an indefinite uncovered implant does not match that temporary treatment strategy.
Reasoning steps for option D
Why can an uncovered implant be problematic in benign disease?
Tissue ingrowth makes it difficult to extract and can create a long-term management problem.
Why does this proposal fail the current treatment goals?
The diagnosis is benign and both branch drainage and planned reassessment matter; an indefinite uncovered implant does not match that temporary treatment strategy.
Takeaway: Benign etiology, distance from the confluence, and follow-up feasibility all influence stent selection.