Compare bismuth, sucralfate and misoprostol through ulcer protection, H. pylori therapy, drug-binding schedules and patient-specific safety decisions.
A medicine can protect an ulcer without eradicating its cause, and a medicine that acts mainly in the gut can still harm another organ. Learn to separate surface protection, infection treatment and prostaglandin replacement, then use the medication record to predict what happens next.
Where does protection happen?
Picture an injured mucosal surface with acid above it. There are at least two ways to reduce further injury: change what reaches the surface, or change the signals controlling secretion and defense. These approaches can help the same patient for different reasons; they are not interchangeable prescriptions.
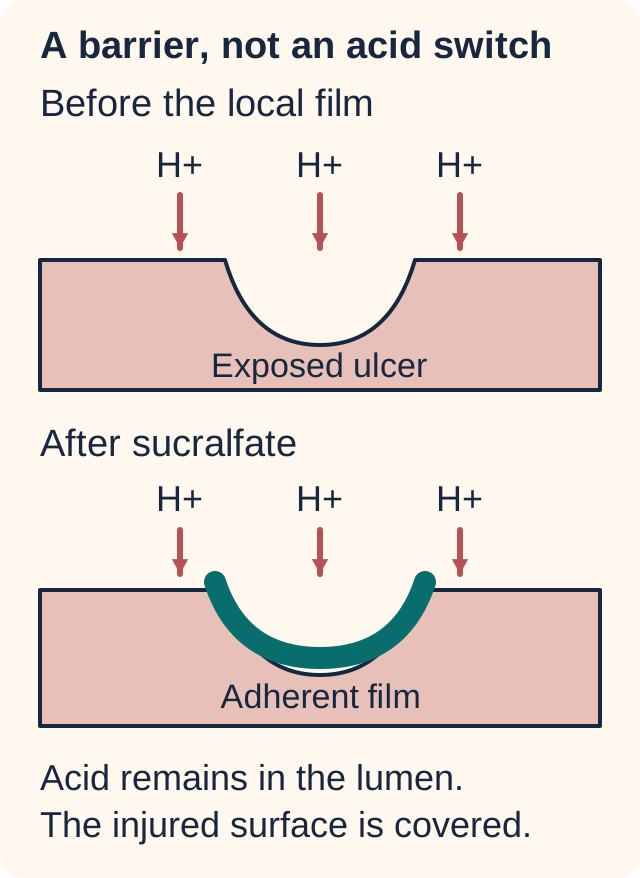
Sucralfate is a local protectant. Its sulfated sucrose-aluminum complex forms an adherent association with proteins at the ulcer. The resulting barrier limits acid penetration; pepsin inhibition and bile-salt adsorption also contribute to the protective description. It has some acid-neutralizing capacity, but strong suppression of acid production is not its defining action. [2]
Compare acid availability with acid access to tissue. The film changes the interface; it does not represent complete acid neutralization. Open full-size diagram.
Trace the acid arrows. Cover the lower drawing and predict whether an adherent film must make acid disappear from the lumen. Then compare the two surfaces.
The acid can remain while access to injured tissue is restricted. A lower acid output would suggest a different or additional effect, such as that of an acid-suppressive medicine. The film is not proof that an infection has been eliminated.
Bismuth has local protective and antimicrobial roles. Bismuth subsalicylate also supplies a salicylate component that can be absorbed. The comparatively small absorbed bismuth fraction and the systemic salicylate exposure must not be treated as the same thing. Bismuth-containing combinations are useful against H. pylori; laboratory antimicrobial activity does not make a bismuth product a universal treatment for every enteric pathogen. [1][7][8]
Misoprostol is a prostaglandin E1 analog. It supplies a prostaglandin-like signal rather than forming an adherent coating. Its gastric effects include reduced acid secretion and increased mucus and bicarbonate production at relevant doses. Effects outside the stomach explain why its safety questions differ from those of sucralfate. [3]
Try a new setting: an experiment shows unchanged acid production but a new ulcer-surface film. Local barrier protection fits better than a proton-pump explanation. Now change the observation to decreased acid plus increased defensive secretion: a prostaglandin-like effect becomes the better fit.
Bismuth: relief, healing and eradication are different outcomes
A patient reports less pain after a bismuth remedy. Before calling this a successful infection treatment, ask what was actually measured. Symptom improvement, endoscopic ulcer healing and elimination of H. pylori are separate outcomes. Bismuth alone is not a reliable eradication regimen. Its local antimicrobial effects belong within a complete, evidence-based combination. [1][10]
Build the whole regimen
For an appropriate treatment-naive adult when susceptibility is unknown, optimized bismuth quadruple therapy is a recommended 14-day option. It combines a proton-pump inhibitor twice daily, bismuth four times daily, tetracycline 500 mg four times daily, and metronidazole 500 mg three or four times daily. Bismuth formulation and dose must be checked together: the ACG table lists subcitrate 120 to 300 mg or subsalicylate 300 to 524 mg per dose. These are not automatically interchangeable products or quantities. [1][10]
Check previous antibiotic exposure, earlier eradication attempts, allergy history, contraindications and the feasibility of completing every component. Clarithromycin- or levofloxacin-containing treatment should not be selected empirically without demonstrated susceptibility. A penicillin allergy also changes the available alternatives. Do not simply omit one component, replace tetracycline with doxycycline by default, or substitute sucralfate for bismuth. [1][10]
Use two medication-free intervals
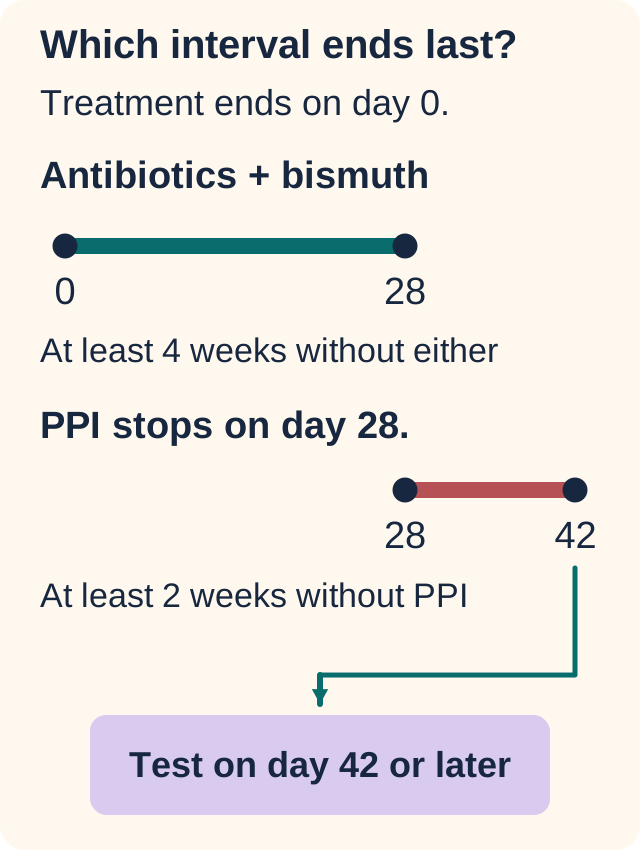
Arrange confirmation of eradication with a urea breath test, fecal antigen test or an appropriate biopsy-based test. ACG guidance requires testing at least four weeks after treatment, with antibiotics and bismuth withheld for four weeks and a PPI withheld for two weeks. The ACG summary also specifies a two-week interval without a potassium-competitive acid blocker. Check all prescribed and nonprescription exposures. [1][10]
Trace the treatment stop and PPI stop separately. The later qualifying date determines readiness, assuming no new interfering exposure and correct laboratory preparation. Open full-size diagram.
Choose the later date: antibiotics and bismuth stop on day 0, but the PPI stops on day 28. Say the first date that satisfies both intervals before following the diagram.
The first interval ends on day 28; the second ends on day 42. A negative test on day 35 does not reliably establish cure. For another patient, bismuth taken again through day 20 shifts the four-week bismuth-free endpoint to day 48.
Do not use symptoms or persistent antibodies to certify eradication. H2 blockers or antacids can sometimes bridge symptoms during the acid-suppressor washout, but the performing laboratory may impose additional preparation. For example, the cited Mayo breath-test instructions restrict H2 blockers. Coordinate the test plan rather than independently stopping necessary medicines. [1][11]
A short diarrhea course has a different purpose
For selected adults with mild, nonbloody travelers' diarrhea, bismuth subsalicylate can provide short-term symptom relief alongside fluid replacement. Hydration remains central. Fever, blood, severe pain, inability to maintain fluids or worsening illness changes the assessment. This symptom plan is not an H. pylori eradication course and does not justify continuing prophylaxis indefinitely. Age, pregnancy, kidney function and salicylate-related hazards must be checked first. [4]
Sucralfate: a helpful binding property with an inconvenient consequence
If a medicine can adhere to material inside the gut, could it also interfere with another oral medicine? Sucralfate can reduce the availability of selected coadministered drugs before they reach the circulation. The important distinction is reduced absorption, not automatically faster renal clearance or enzyme induction. [2]
The labeled oral suspension regimen for short-term active duodenal ulcer treatment is 1 g four times daily on an empty stomach. Treatment commonly continues for four to eight weeks unless healing has been documented. Do not let early pain improvement turn an intended course into either premature cessation or indefinite use. Sucralfate is not a replacement for treating an underlying infection. [2]
Think of the familiar acid-dependent coating description as chemistry, not permission to stop every acid suppressant. Review separate treatment indications. A patient with severe erosive esophagitis may still need a PPI. The explicit sucralfate administration instruction is to keep an antacid outside the half-hour window before and after a dose. Changing antacid brands does not solve a timing problem. [2]
Watch dose order change the available drug
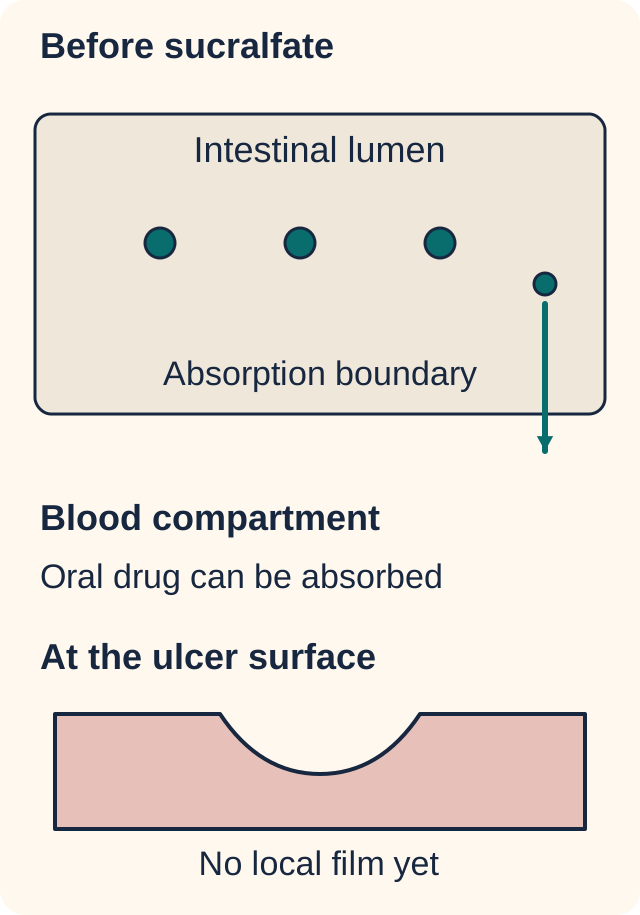
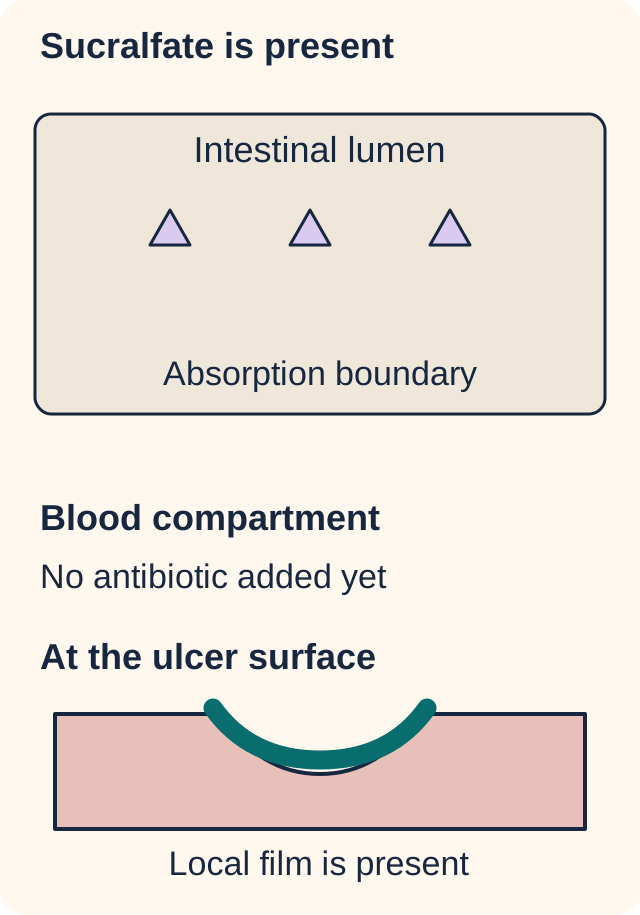
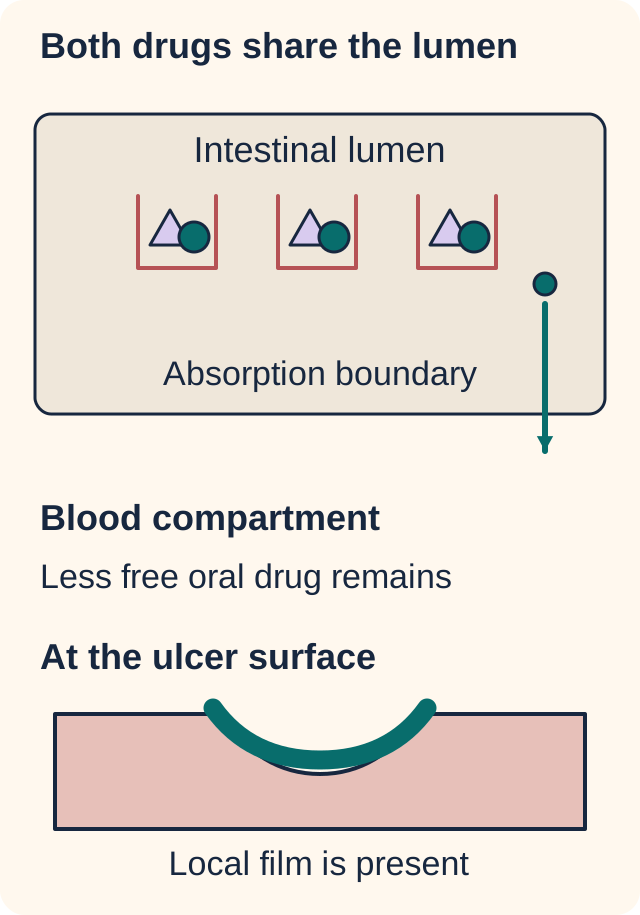
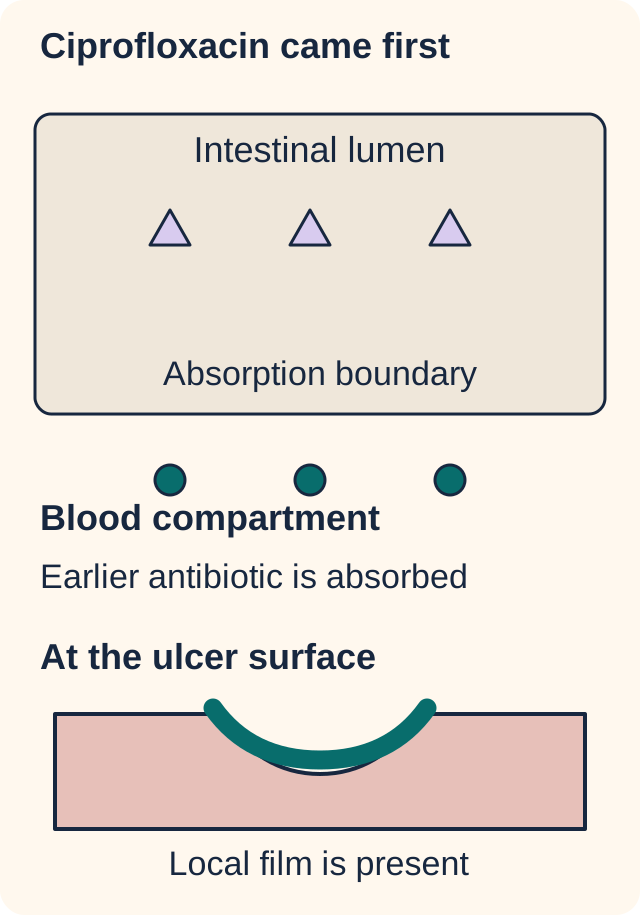
The circles below represent an oral antibiotic; triangles represent sucralfate. Their counts are a qualitative teaching model, not a measured fraction absorbed. Predict whether protecting the ulcer must also reduce antibiotic exposure, then compare concurrent dosing with adequately separated dosing.
Before sucralfate, free oral drug can cross the intestinal absorption boundary and the ulcer surface has no sucralfate film. Open full-size diagram.What changes when sucralfate enters the lumen?
The local film forms at the ulcer. The binder is also present where an oral medicine may encounter it.
Sucralfate particles are present in the lumen and an adherent film covers the ulcer. No antibiotic has yet been added to the illustrated interval. Open full-size diagram.What if ciprofloxacin is given at the same time?
Complexes can form before absorption. The ulcer can remain protected while the antibiotic has less free drug available to enter the blood.
When ciprofloxacin and sucralfate share the lumen, complexes leave less free antibiotic available for absorption, while the ulcer remains covered. Open full-size diagram.What if ciprofloxacin is given early enough?
Separating the doses allows antibiotic absorption before the binder arrives. Subsequent sucralfate can still provide its local protective effect. Check all neighboring doses.
When ciprofloxacin is taken sufficiently before sucralfate, more of the antibiotic can be absorbed before the binder is present, and subsequent sucralfate still forms a local film. Open full-size diagram.
Each panel opens independently, so you can compare the states in any order. Close the three panels to return to the starting state. Each control works with a tap, Enter or Space. There is no timed step.
The complete comparison: without the binder, an oral drug can be available for absorption. With simultaneous sucralfate, selected drugs can be bound within the lumen. Adequate separation changes that encounter; it does not require sacrificing the local ulcer film. An oral-only fall in exposure, with unchanged intravenous clearance, therefore points toward a pre-absorption interaction. [2][6]
There is no universal two-hour schedule
Different medicines, different administration instructions
Medicine
Relationship to sucralfate
MedicineCiprofloxacin
Relationship to sucralfateGive ciprofloxacin at least 2 hours before or 6 hours after sucralfate. [6]
MedicineLevothyroxine
Relationship to sucralfateSeparate from absorption-interfering medicines by at least 4 hours; monitor thyroid status. [5]
MedicineAntacids
Relationship to sucralfateKeep antacids outside the 30 minutes before and after sucralfate. [2]
Binding interactions also involve medicines such as tetracyclines, digoxin and phenytoin. The sucralfate label reports that giving selected studied drugs two hours before sucralfate prevented observed interactions. That finding does not establish two hours in either direction for every medicine. Use the specific formulation's instructions and clinical monitoring. [2]
Transfer the timing: ciprofloxacin at 06:00 can precede sucralfate at 08:00, assuming the rest of the schedule is suitable. Reverse the order: after sucralfate at 08:00, the ciprofloxacin interval extends to 14:00. Add levothyroxine at 05:00, and a 09:00 sucralfate dose satisfies its longer four-hour requirement. Check the next sucralfate dose as well as the preceding one.
If another medicine's dose was increased to compensate for poor absorption, ending sucralfate can increase exposure at that higher dose. Reassess concentrations or clinical effects when a binder starts, stops or changes timing. The same prescribed dose does not guarantee the same systemic exposure.[2]
Misoprostol: replace a signal, then account for its other targets
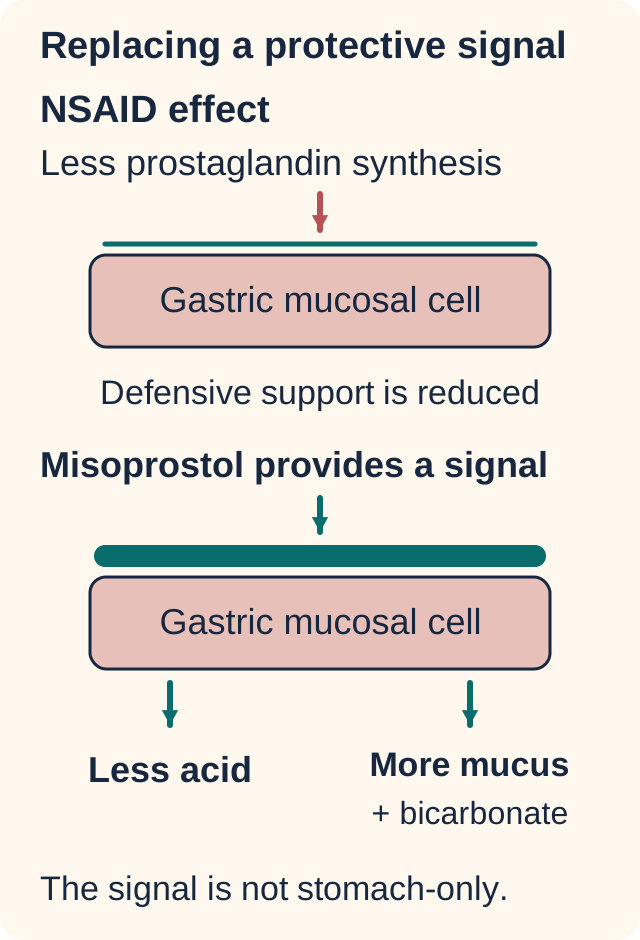
Why can an NSAID injure the stomach even when acid is not excessive? Inhibiting prostaglandin synthesis weakens a protective system. Misoprostol provides a prostaglandin E1-like signal rather than treating the surface as a place to deposit a coating. [3]
Compare the thin and thicker defensive layer, then follow both outputs. This model does not assign how much ulcer prevention comes from each effect or depict a measured perfusion benefit. Open full-size diagram.
Predict both outputs. Follow the signal to the cell, then trace acid secretion separately from mucus and bicarbonate. Does the protective effect require acid to increase?
No. Misoprostol reduces acid secretion and can increase defensive secretions. These effects occur together at relevant doses. The ulcer-prevention result alone cannot establish how much benefit comes from each one. The diagram is not a measurement of improved human mucosal blood flow. [3]
The US label supports reducing NSAID-associated gastric ulcer risk in patients at high risk while NSAID treatment is necessary. Reconsider the NSAID and alternatives first. This indication does not establish the same benefit for NSAID-associated duodenal ulcers, and trial prevention of gastric ulcers did not establish better relief of gastrointestinal pain or discomfort. A preventive purpose and a symptom-relief purpose require different evidence. [3]
The usual labeled adult dose is 200 micrograms four times daily with food, with the last dose at bedtime. A 100-microgram dose can be used when the usual dose is not tolerated; do not assume identical protection at every dose. Diarrhea and abdominal cramping are important practical limits. Taking doses with food and avoiding magnesium-containing antacids can reduce diarrhea. Persistent or severe symptoms, especially dehydration, require reassessment rather than automatic continuation. [3]
The pregnancy question is specific to the indication
Do not use misoprostol for NSAID-ulcer prevention during pregnancy. Uterine activity can cause pregnancy loss, premature birth and other pregnancy harm; the label also warns about birth defects and uterine rupture. Misoprostol's separate reproductive-health uses have different goals and protocols. Their existence does not make gastrointestinal prophylaxis during pregnancy acceptable. [3]
For a patient of reproductive potential in whom this high-risk NSAID indication is appropriate, the label requires a negative serum pregnancy test within two weeks before starting, ability to comply with effective contraception, and oral and written counseling about the risks. It specifies starting on the second or third day of the next normal menstrual period. An old negative test, cycle timing alone or counseling alone is not the complete safeguard. [3]
Apply the distinction: a patient discovers a pregnancy while taking misoprostol solely for ulcer prevention. Stop that prophylactic use and promptly contact the treating clinician for counseling and a revised medication plan. Reducing the dose does not solve the contraindication. Exposure also does not establish that harm has inevitably occurred. New severe pain, heavy bleeding or collapse requires urgent care. [3][9]
For a different patient, early nonbloody diarrhea after misoprostol plus a magnesium antacid suggests a medication-related contribution. First assess severity and hydration, then review the magnesium product, food timing and tolerability. The pregnancy decision and the diarrhea decision are not variations of the same dose-adjustment rule.
Let the patient's findings change the priority
Could the same dark stool call for reassurance in one patient and emergency care in another? Compare the whole presentation rather than ranking these drugs by a single list of adverse effects.
Dark tongue, formed dark stool, stable pulse and hemoglobin: a bismuth pigment effect is plausible. Explain it and review warning symptoms.
Sticky black stool, faintness, tachycardia, low blood pressure and a falling hemoglobin: treat this as suspected significant gastrointestinal bleeding. A familiar medication effect does not explain circulatory compromise. [4][9]
Change one observation: keep the bismuth history but add a substantial hemoglobin decline. Would the pigment explanation still account for the entire case? It would not. The new evidence requires urgent bleeding assessment, not waiting for the stool color to normalize.
Bismuth: review the salt and the cumulative exposure
Aspirin allergy, anticoagulant use, renal insufficiency and concurrent salicylates can make bismuth subsalicylate unsuitable. CDC guidance also cautions about gout, methotrexate and probenecid. It is not recommended in pregnancy; children and adolescents with viral illnesses have a salicylate-associated Reye syndrome concern. Bismuth subcitrate does not contain salicylate, but that does not eliminate other bismuth or combination-product precautions. [4][10]
Tinnitus after repeated subsalicylate or combined aspirin exposure warrants prompt assessment for toxicity. Separating those doses cannot erase the total salicylate exposure. Prolonged excess bismuth can also produce a rare encephalopathy with cognitive change, ataxia and myoclonus. Ask specifically about nonprescription products that a patient may not consider medicines. The cited case report illustrates this hazard; it does not measure its population frequency. [4][8]
Sucralfate: local action does not mean zero absorption
Constipation is its most frequent adverse effect. Small amounts of aluminum can be absorbed, and impaired renal clearance can permit accumulation, especially with prolonged treatment or additional aluminum antacids. Potential consequences include encephalopathy and bone disease. Protein-bound aluminum is not reliably cleared by routine dialysis, so a dialysis schedule is not sufficient reassurance. [2]
Sucralfate-associated bezoars have been reported, particularly with impaired gastric emptying or enteral feeding. New vomiting or feeding intolerance in that context warrants assessment for retained material rather than assuming uncomplicated ulcer symptoms. The oral suspension must never be administered intravenously. [2]
Transfer to a new kidney case: misoprostol does not introduce sucralfate's aluminum burden. Its label does not require routine dose adjustment solely for renal impairment, although intolerance can justify reduction. That distinction does not make an NSAID harmless to a patient with kidney disease; its necessity requires a separate review. [3]
Practice with the findings that change the answer
For each original educational case, identify the treatment goal, locate the drug's action and use the patient's medication history or measurements before choosing. Compare the explanation for the closest alternative with the explanation for your selection.
Case 1
Show answer and explanations for case 1
A. PPI, bismuth, clarithromycin, and metronidazole (Why this does not fit)
These agents avoid amoxicillin and appear to provide a multi-drug approach. Prior macrolide exposure and unknown clarithromycin susceptibility argue against this substitution. Four components do not make every combination an appropriate empiric regimen.
Reasoning steps for option A
For "PPI, bismuth, clarithromycin, and metronidazole", what case feature makes this choice seem initially reasonable?
These agents avoid amoxicillin and appear to provide a multi-drug approach.
Which supplied finding most directly argues against "PPI, bismuth, clarithromycin, and metronidazole" in this case?
Prior macrolide exposure and unknown clarithromycin susceptibility argue against this substitution.
What clinical discriminator should be carried forward when evaluating "PPI, bismuth, clarithromycin, and metronidazole"?
Four components do not make every combination an appropriate empiric regimen.
B. PPI, bismuth, levofloxacin, and metronidazole (Why this does not fit)
A fluoroquinolone-containing alternative might be considered in selected treatment circumstances. The case supplies no demonstrated levofloxacin susceptibility to justify this empiric substitution. Do not replace one resistance-sensitive antibiotic with another without the necessary evidence.
Reasoning steps for option B
For "PPI, bismuth, levofloxacin, and metronidazole", what case feature makes this choice seem initially reasonable?
A fluoroquinolone-containing alternative might be considered in selected treatment circumstances.
Which supplied finding most directly argues against "PPI, bismuth, levofloxacin, and metronidazole" in this case?
The case supplies no demonstrated levofloxacin susceptibility to justify this empiric substitution.
What clinical discriminator should be carried forward when evaluating "PPI, bismuth, levofloxacin, and metronidazole"?
Do not replace one resistance-sensitive antibiotic with another without the necessary evidence.
C. PPI, bismuth, tetracycline, and metronidazole (Best answer)
This provides acid suppression and the complete optimized bismuth quadruple regimen. It avoids amoxicillin and does not depend on unconfirmed clarithromycin susceptibility. Use all components for the prescribed 14-day course and arrange confirmation of eradication.
Reasoning steps for option C
Which common antibiotic is excluded?
The immediate penicillin allergy excludes an amoxicillin-containing initial regimen here.
What does the exposure history imply?
Prior clarithromycin and unknown susceptibility argue against empiric clarithromycin treatment.
Which remaining complete regimen fits?
Optimized bismuth quadruple therapy contains PPI, bismuth, tetracycline and metronidazole.
D. PPI, bismuth, tetracycline, and amoxicillin (Why this does not fit)
Amoxicillin is used in several H. pylori regimens. This patient has an immediate penicillin allergy, and this is not the indicated optimized tetracycline-metronidazole combination. Check both patient suitability and the actual components of the selected regimen.
Reasoning steps for option D
For "PPI, bismuth, tetracycline, and amoxicillin", what case feature makes this choice seem initially reasonable?
Amoxicillin is used in several H. pylori regimens.
Which supplied finding most directly argues against "PPI, bismuth, tetracycline, and amoxicillin" in this case?
This patient has an immediate penicillin allergy, and this is not the indicated optimized tetracycline-metronidazole combination.
What clinical discriminator should be carried forward when evaluating "PPI, bismuth, tetracycline, and amoxicillin"?
Check both patient suitability and the actual components of the selected regimen.
Takeaway: Check both allergy and resistance risk before choosing a complete eradication regimen.
A. Repeat the breath test on or after day 42 (Best answer)
Day 35 is more than four weeks after antibiotics and bismuth. Only seven days have elapsed since omeprazole stopped, so acid suppression can still undermine a negative result. Confirm eradication after both the antibiotic/bismuth interval and a full two-week PPI interval.
Reasoning steps for option A
Has the antimicrobial interval elapsed?
Yes. Day 35 is at least four weeks after day 0.
Has the PPI interval elapsed?
No. Only one week has passed since day 28.
When are both intervals satisfied?
Day 42 is two weeks after PPI cessation and six weeks after treatment completion.
B. Accept the result and end eradication follow-up (Why this does not fit)
A breath test is an appropriate active-infection test. The required PPI washout was not completed before this sample. The correct test can still be unreliable at the wrong time.
Reasoning steps for option B
For "Accept the result and end eradication follow-up", what case feature makes this choice seem initially reasonable?
A breath test is an appropriate active-infection test.
Which supplied finding most directly argues against "Accept the result and end eradication follow-up" in this case?
The required PPI washout was not completed before this sample.
What clinical discriminator should be carried forward when evaluating "Accept the result and end eradication follow-up"?
The correct test can still be unreliable at the wrong time.
C. Replace the breath test with serum antibody testing (Why this does not fit)
Serology is not suppressed in the same way by a recent PPI. Antibodies can persist after eradication and cannot resolve this cure question. Use an active-infection test under valid testing conditions.
Reasoning steps for option C
For "Replace the breath test with serum antibody testing", what case feature makes this choice seem initially reasonable?
Serology is not suppressed in the same way by a recent PPI.
Which supplied finding most directly argues against "Replace the breath test with serum antibody testing" in this case?
Antibodies can persist after eradication and cannot resolve this cure question.
What clinical discriminator should be carried forward when evaluating "Replace the breath test with serum antibody testing"?
Use an active-infection test under valid testing conditions.
D. Restart the same antibiotics before repeating testing (Why this does not fit)
Persistent infection sometimes requires another treatment course. An inadequately prepared negative test does not establish treatment failure. Correct the testing conditions before labeling a stable patient as a treatment failure.
Reasoning steps for option D
For "Restart the same antibiotics before repeating testing", what case feature makes this choice seem initially reasonable?
Persistent infection sometimes requires another treatment course.
Which supplied finding most directly argues against "Restart the same antibiotics before repeating testing" in this case?
An inadequately prepared negative test does not establish treatment failure.
What clinical discriminator should be carried forward when evaluating "Restart the same antibiotics before repeating testing"?
Correct the testing conditions before labeling a stable patient as a treatment failure.
Takeaway: A negative test obtained during inadequate washout does not reliably establish eradication.
Four weeks have elapsed since the eradication antibiotics ended. The additional bismuth ended only eight days before this date. Use the most recent interfering exposure, not just the original prescription end date.
Reasoning steps for option A
For "Day 28", what case feature makes this choice seem initially reasonable?
Four weeks have elapsed since the eradication antibiotics ended.
Which supplied finding most directly argues against "Day 28" in this case?
The additional bismuth ended only eight days before this date.
What clinical discriminator should be carried forward when evaluating "Day 28"?
Use the most recent interfering exposure, not just the original prescription end date.
B. Day 34 (Why this does not fit)
This provides two weeks after the last bismuth dose. The stated bismuth washout is four weeks, not the two-week PPI interval. Different medication categories have different testing intervals.
Reasoning steps for option B
For "Day 34", what case feature makes this choice seem initially reasonable?
This provides two weeks after the last bismuth dose.
Which supplied finding most directly argues against "Day 34" in this case?
The stated bismuth washout is four weeks, not the two-week PPI interval.
What clinical discriminator should be carried forward when evaluating "Day 34"?
Different medication categories have different testing intervals.
C. Day 38 (Why this does not fit)
This date allows four weeks from PPI cessation. It still provides only eighteen days since the last bismuth exposure. A longer PPI interval cannot compensate for an incomplete bismuth interval.
Reasoning steps for option C
For "Day 38", what case feature makes this choice seem initially reasonable?
This date allows four weeks from PPI cessation.
Which supplied finding most directly argues against "Day 38" in this case?
It still provides only eighteen days since the last bismuth exposure.
What clinical discriminator should be carried forward when evaluating "Day 38"?
A longer PPI interval cannot compensate for an incomplete bismuth interval.
D. Day 48 (Best answer)
The latest bismuth exposure was day 20. Twenty-eight days later is day 48, and the two-week PPI interval has also elapsed. The latest qualifying date across all interfering medicines determines test readiness.
Reasoning steps for option D
Which exposure now determines the bismuth interval?
The self-administered dose on day 20, not the prescribed course ending on day 0.
What date ends that four-week interval?
Day 20 plus 28 days is day 48.
Is the PPI interval also complete?
Yes. Its two-week interval ended on day 24.
Takeaway: Include nonprescription bismuth when preparing for an H. pylori cure test.
A. The positive antigen reflects antibodies left after cure (Why this does not fit)
Immune responses can persist after an infection has cleared. A stool antigen assay detects organism-derived antigen, not circulating antibodies. Distinguish an active-infection assay from serology.
Reasoning steps for option A
For "The positive antigen reflects antibodies left after cure", what case feature makes this choice seem initially reasonable?
Immune responses can persist after an infection has cleared.
Which supplied finding most directly argues against "The positive antigen reflects antibodies left after cure" in this case?
A stool antigen assay detects organism-derived antigen, not circulating antibodies.
What clinical discriminator should be carried forward when evaluating "The positive antigen reflects antibodies left after cure"?
Distinguish an active-infection assay from serology.
B. Ulcer healing occurred without reliable eradication (Best answer)
Local protection and suppression of bacterial activity can improve an ulcer. A properly timed positive active-infection test supports persistent H. pylori despite symptom improvement. Improvement in the tissue injury does not establish eradication of its cause.
Reasoning steps for option B
What outcome has improved?
Symptoms and the size of the mucosal injury.
What does the properly prepared antigen result indicate?
H. pylori remains detectable.
Can the first outcome prove the second is resolved?
No. Tissue healing and bacterial eradication are distinct endpoints.
C. A residual PPI effect produced a false-positive result (Why this does not fit)
Acid suppression can interfere with H. pylori testing. Its principal concern is a false-negative test, and an adequate washout is supplied. Do not reverse the direction of a known testing bias.
Reasoning steps for option C
For "A residual PPI effect produced a false-positive result", what case feature makes this choice seem initially reasonable?
Acid suppression can interfere with H. pylori testing.
Which supplied finding most directly argues against "A residual PPI effect produced a false-positive result" in this case?
Its principal concern is a false-negative test, and an adequate washout is supplied.
What clinical discriminator should be carried forward when evaluating "A residual PPI effect produced a false-positive result"?
Do not reverse the direction of a known testing bias.
D. The bismuth course created immediate reinfection (Why this does not fit)
Reinfection is possible after established eradication. This patient never received a reliable eradication regimen or had documented cure. Persistent infection is not the same as reinfection after confirmed clearance.
Reasoning steps for option D
For "The bismuth course created immediate reinfection", what case feature makes this choice seem initially reasonable?
Reinfection is possible after established eradication.
Which supplied finding most directly argues against "The bismuth course created immediate reinfection" in this case?
This patient never received a reliable eradication regimen or had documented cure.
What clinical discriminator should be carried forward when evaluating "The bismuth course created immediate reinfection"?
Persistent infection is not the same as reinfection after confirmed clearance.
Takeaway: Treat the infection and confirm cure rather than equating a quieter ulcer with eradication.
A. Explain pigment changes and review bleeding precautions (Best answer)
Bismuth commonly darkens the tongue and stools. The simultaneous tongue discoloration and stable assessment support a medication effect rather than demonstrated bleeding. Expected discoloration does not require abandoning treatment, but new bleeding symptoms still require assessment.
Reasoning steps for option A
Which shared exposure can explain both color changes?
Bismuth can cause benign tongue and stool pigmentation.
What evidence would increase concern for hemorrhage?
Instability, a hemoglobin decline, tarry stools or new systemic symptoms would change the assessment.
What follows from the supplied stable assessment?
Explain the expected effect, preserve prescribed therapy and give clear precautions.
B. Stop the entire regimen and arrange emergency endoscopy (Why this does not fit)
Black stools can occur with gastrointestinal bleeding. No new instability, hemoglobin decline or concerning symptoms accompany these formed stools. Assess the whole presentation rather than treating stool color alone as proof of hemorrhage.
Reasoning steps for option B
For "Stop the entire regimen and arrange emergency endoscopy", what case feature makes this choice seem initially reasonable?
Black stools can occur with gastrointestinal bleeding.
Which supplied finding most directly argues against "Stop the entire regimen and arrange emergency endoscopy" in this case?
No new instability, hemoglobin decline or concerning symptoms accompany these formed stools.
What clinical discriminator should be carried forward when evaluating "Stop the entire regimen and arrange emergency endoscopy"?
Assess the whole presentation rather than treating stool color alone as proof of hemorrhage.
C. Continue treatment and disregard later dark stools (Why this does not fit)
Benign pigmentation can persist while bismuth is taken. The current benign explanation cannot exclude a future bleed if symptoms or vital signs change. A medication-related color change is not permanent protection against bleeding.
Reasoning steps for option C
For "Continue treatment and disregard later dark stools", what case feature makes this choice seem initially reasonable?
Benign pigmentation can persist while bismuth is taken.
Which supplied finding most directly argues against "Continue treatment and disregard later dark stools" in this case?
The current benign explanation cannot exclude a future bleed if symptoms or vital signs change.
What clinical discriminator should be carried forward when evaluating "Continue treatment and disregard later dark stools"?
A medication-related color change is not permanent protection against bleeding.
D. Pause bismuth and continue the other three medicines (Why this does not fit)
Pausing a suspected culprit can be useful when a harmful reaction occurs. The stable assessment supports expected pigmentation, and deleting one component weakens the intended eradication regimen. Do not dismantle a complete regimen for an expected color change without a clinical reason.
Reasoning steps for option D
For "Pause bismuth and continue the other three medicines", what case feature makes this choice seem initially reasonable?
Pausing a suspected culprit can be useful when a harmful reaction occurs.
Which supplied finding most directly argues against "Pause bismuth and continue the other three medicines" in this case?
The stable assessment supports expected pigmentation, and deleting one component weakens the intended eradication regimen.
What clinical discriminator should be carried forward when evaluating "Pause bismuth and continue the other three medicines"?
Do not dismantle a complete regimen for an expected color change without a clinical reason.
Takeaway: Dark stool during bismuth use needs context, not automatic reassurance or automatic diagnosis of bleeding.
A. Stop bismuth and reassess stool color the next day (Why this does not fit)
Stopping the pigment-producing medicine can help interpret subsequent stool appearance. Hypotension, tachycardia and a large hemoglobin decline already indicate an urgent problem. Do not await pigment clearance when circulation is compromised.
Reasoning steps for option A
For "Stop bismuth and reassess stool color the next day", what case feature makes this choice seem initially reasonable?
Stopping the pigment-producing medicine can help interpret subsequent stool appearance.
Which supplied finding most directly argues against "Stop bismuth and reassess stool color the next day" in this case?
Hypotension, tachycardia and a large hemoglobin decline already indicate an urgent problem.
What clinical discriminator should be carried forward when evaluating "Stop bismuth and reassess stool color the next day"?
Do not await pigment clearance when circulation is compromised.
B. Obtain a stool antigen test before changing treatment (Why this does not fit)
H. pylori is relevant to the causes of peptic ulcer disease. An infection test does not address this immediate circulatory threat and recent bismuth can affect testing. Etiologic testing follows stabilization of an acute bleeding presentation.
Reasoning steps for option B
For "Obtain a stool antigen test before changing treatment", what case feature makes this choice seem initially reasonable?
H. pylori is relevant to the causes of peptic ulcer disease.
Which supplied finding most directly argues against "Obtain a stool antigen test before changing treatment" in this case?
An infection test does not address this immediate circulatory threat and recent bismuth can affect testing.
What clinical discriminator should be carried forward when evaluating "Obtain a stool antigen test before changing treatment"?
Etiologic testing follows stabilization of an acute bleeding presentation.
C. Begin emergency bleeding evaluation and stabilization (Best answer)
NSAID exposure adds ulcer risk to the new tarry stools. The circulatory findings and hemoglobin decline cannot be explained by harmless bismuth pigmentation. Treat suspected significant gastrointestinal bleeding without delay for a color-based explanation.
Reasoning steps for option C
Does bismuth pigmentation explain the circulatory findings?
No. A benign pigment effect does not cause shock or a substantial hemoglobin decline.
What working problem accounts for the combined findings?
Clinically significant gastrointestinal bleeding.
What takes priority?
Emergency assessment and stabilization rather than waiting for a medication washout.
D. Increase the local protectant and continue naproxen (Why this does not fit)
Protectants may reduce exposure of injured mucosa to luminal irritants. They do not stabilize shock or control an established major hemorrhage. A prophylactic or symptomatic drug is not emergency hemostatic care.
Reasoning steps for option D
For "Increase the local protectant and continue naproxen", what case feature makes this choice seem initially reasonable?
Protectants may reduce exposure of injured mucosa to luminal irritants.
Which supplied finding most directly argues against "Increase the local protectant and continue naproxen" in this case?
They do not stabilize shock or control an established major hemorrhage.
What clinical discriminator should be carried forward when evaluating "Increase the local protectant and continue naproxen"?
A prophylactic or symptomatic drug is not emergency hemostatic care.
Takeaway: A familiar adverse effect must not conceal a new emergency.
A. Use it at bedtime and keep the warfarin schedule (Why this does not fit)
Separating oral doses is useful for some gastrointestinal binding interactions. It does not eliminate the systemic salicylate-related bleeding concern with this product. A timing solution must match the actual interaction mechanism.
Reasoning steps for option A
For "Use it at bedtime and keep the warfarin schedule", what case feature makes this choice seem initially reasonable?
Separating oral doses is useful for some gastrointestinal binding interactions.
Which supplied finding most directly argues against "Use it at bedtime and keep the warfarin schedule" in this case?
It does not eliminate the systemic salicylate-related bleeding concern with this product.
What clinical discriminator should be carried forward when evaluating "Use it at bedtime and keep the warfarin schedule"?
A timing solution must match the actual interaction mechanism.
B. Use bismuth and omit warfarin while diarrhea lasts (Why this does not fit)
Holding anticoagulation can sometimes be necessary in active bleeding under supervision. No active bleed is supplied, and unsupervised interruption creates avoidable thromboembolic risk. Do not alter essential anticoagulation to enable an optional symptom remedy.
Reasoning steps for option B
For "Use bismuth and omit warfarin while diarrhea lasts", what case feature makes this choice seem initially reasonable?
Holding anticoagulation can sometimes be necessary in active bleeding under supervision.
Which supplied finding most directly argues against "Use bismuth and omit warfarin while diarrhea lasts" in this case?
No active bleed is supplied, and unsupervised interruption creates avoidable thromboembolic risk.
What clinical discriminator should be carried forward when evaluating "Use bismuth and omit warfarin while diarrhea lasts"?
Do not alter essential anticoagulation to enable an optional symptom remedy.
C. Use a reduced bismuth dose and arrange a later INR (Why this does not fit)
Laboratory monitoring is important when anticoagulant interactions are suspected. A reduced nonprescription dose and a later INR do not establish that this salicylate-containing remedy is suitable. Review the optional product before exposure rather than assuming dose reduction neutralizes bleeding risk.
Reasoning steps for option C
For "Use a reduced bismuth dose and arrange a later INR", what case feature makes this choice seem initially reasonable?
Laboratory monitoring is important when anticoagulant interactions are suspected.
Which supplied finding most directly argues against "Use a reduced bismuth dose and arrange a later INR" in this case?
A reduced nonprescription dose and a later INR do not establish that this salicylate-containing remedy is suitable.
What clinical discriminator should be carried forward when evaluating "Use a reduced bismuth dose and arrange a later INR"?
Review the optional product before exposure rather than assuming dose reduction neutralizes bleeding risk.
D. Avoid self-treatment with it and review alternatives (Best answer)
Bismuth subsalicylate contains a salicylate component. Anticoagulant use changes its suitability even when the diarrhea itself is mild. Maintain hydration and obtain a compatible symptom plan without independently stopping warfarin.
Reasoning steps for option D
Which component matters beyond the gut lumen?
The salicylate component of bismuth subsalicylate.
Does bedtime separation eliminate that exposure?
No. Spacing does not prevent the systemic bleeding-risk interaction.
Which part of the plan should change?
The optional diarrhea remedy, not unsupervised interruption of anticoagulation.
Takeaway: Not every gastrointestinal drug interaction can be solved by separating doses.
A. Oral rehydration plus a weight-adjusted dose of bismuth subsalicylate (Why this does not fit)
Oral replacement fits a patient who can drink and has no signs of circulatory compromise. Adjusting the dose does not resolve the salicylate-associated Reye syndrome concern during an adolescent viral illness. Determine whether a product is suitable before calculating its dose.
Reasoning steps for option A
For "Oral rehydration plus a weight-adjusted dose of bismuth subsalicylate", what case feature makes this choice seem initially reasonable?
Oral replacement fits a patient who can drink and has no signs of circulatory compromise.
Which supplied finding most directly argues against "Oral rehydration plus a weight-adjusted dose of bismuth subsalicylate" in this case?
Adjusting the dose does not resolve the salicylate-associated Reye syndrome concern during an adolescent viral illness.
What clinical discriminator should be carried forward when evaluating "Oral rehydration plus a weight-adjusted dose of bismuth subsalicylate"?
Determine whether a product is suitable before calculating its dose.
B. Oral rehydration without the proposed bismuth subsalicylate product (Best answer)
The assessment supports replacing losses by mouth rather than requiring intravenous access. The separate age-and-viral-illness assessment excludes the proposed salicylate product. Continue oral replacement and arrange reassessment for poor intake, worsening dehydration or other concerning symptoms.
Reasoning steps for option B
Which findings determine the initial fluid route?
Preserved perfusion and successful oral intake support oral rehydration.
Does that determine whether the symptom medicine is appropriate?
No. Its salicylate component creates a separate Reye syndrome concern during an adolescent viral illness.
Which plan satisfies both decisions?
Use oral rehydration without the proposed bismuth subsalicylate, with reassessment if the illness worsens.
C. Intravenous rehydration plus a weight-adjusted dose of bismuth subsalicylate (Why this does not fit)
Intravenous replacement is useful when oral replacement fails or circulation is compromised. Neither problem is supplied here, and a weight-based dose would not remove the viral-illness salicylate hazard. Fluid route and drug suitability each require their own clinical assessment.
Reasoning steps for option C
For "Intravenous rehydration plus a weight-adjusted dose of bismuth subsalicylate", what case feature makes this choice seem initially reasonable?
Intravenous replacement is useful when oral replacement fails or circulation is compromised.
Which supplied finding most directly argues against "Intravenous rehydration plus a weight-adjusted dose of bismuth subsalicylate" in this case?
Neither problem is supplied here, and a weight-based dose would not remove the viral-illness salicylate hazard.
What clinical discriminator should be carried forward when evaluating "Intravenous rehydration plus a weight-adjusted dose of bismuth subsalicylate"?
Fluid route and drug suitability each require their own clinical assessment.
D. Intravenous rehydration without the proposed bismuth subsalicylate product (Why this does not fit)
Avoiding bismuth subsalicylate addresses the adolescent viral-illness concern. The patient is alert, well perfused and able to drink, so the supplied findings do not require intravenous replacement. A contraindicated symptom remedy does not by itself change the route needed for rehydration.
Reasoning steps for option D
For "Intravenous rehydration without the proposed bismuth subsalicylate product", what case feature makes this choice seem initially reasonable?
Avoiding bismuth subsalicylate addresses the adolescent viral-illness concern.
Which supplied finding most directly argues against "Intravenous rehydration without the proposed bismuth subsalicylate product" in this case?
The patient is alert, well perfused and able to drink, so the supplied findings do not require intravenous replacement.
What clinical discriminator should be carried forward when evaluating "Intravenous rehydration without the proposed bismuth subsalicylate product"?
A contraindicated symptom remedy does not by itself change the route needed for rehydration.
Takeaway: Choose the fluid route from the patient assessment and judge the salicylate product separately.
A. Add an antibiotic initially; obtain clinical assessment after the change (Why this does not fit)
The later fever, blood and functional deterioration warrant clinical assessment. The initial mild illness did not justify routine antibiotic treatment. Apply severity criteria at each assessment rather than using later deterioration to justify earlier overtreatment.
Reasoning steps for option A
For "Add an antibiotic initially; obtain clinical assessment after the change", what case feature makes this choice seem initially reasonable?
The later fever, blood and functional deterioration warrant clinical assessment.
Which supplied finding most directly argues against "Add an antibiotic initially; obtain clinical assessment after the change" in this case?
The initial mild illness did not justify routine antibiotic treatment.
What clinical discriminator should be carried forward when evaluating "Add an antibiotic initially; obtain clinical assessment after the change"?
Apply severity criteria at each assessment rather than using later deterioration to justify earlier overtreatment.
B. Add an antibiotic initially; continue symptom treatment after the change (Why this does not fit)
Some travel-associated bacterial illnesses require antibiotics. This plan treats the initially mild illness too aggressively while failing to reassess later fever and bloody stools. Travel history does not replace severity assessment or reassessment when the presentation changes.
Reasoning steps for option B
For "Add an antibiotic initially; continue symptom treatment after the change", what case feature makes this choice seem initially reasonable?
Some travel-associated bacterial illnesses require antibiotics.
Which supplied finding most directly argues against "Add an antibiotic initially; continue symptom treatment after the change" in this case?
This plan treats the initially mild illness too aggressively while failing to reassess later fever and bloody stools.
What clinical discriminator should be carried forward when evaluating "Add an antibiotic initially; continue symptom treatment after the change"?
Travel history does not replace severity assessment or reassessment when the presentation changes.
C. Add short-course bismuth initially; obtain clinical assessment after the change (Best answer)
The initial mild illness and reassuring safety screen permit short symptomatic treatment alongside hydration. Later fever, visible blood and loss of usual function make continuation of a simple self-treatment plan inadequate. Obtain prompt clinical assessment for the changed illness and appropriate infection-directed management while replacing fluid losses.
Reasoning steps for option C
What does the initial functional assessment support?
A mild illness supports fluids and a short symptomatic course rather than routine antibiotics.
What changes the interpretation the next day?
Fever, visible blood and inability to participate in activities indicate a more serious presentation.
How should the plan change?
Continue replacement of fluid losses and obtain prompt clinical assessment rather than relying on bismuth alone.
D. Add short-course bismuth initially; continue symptom treatment after the change (Why this does not fit)
Short-course bismuth is an appropriate initial option for the mild presentation. The later fever and bloody stools require reassessment rather than continued symptom treatment as the complete plan. A medicine that fits the first assessment may not be sufficient after the illness changes.
Reasoning steps for option D
For "Add short-course bismuth initially; continue symptom treatment after the change", what case feature makes this choice seem initially reasonable?
Short-course bismuth is an appropriate initial option for the mild presentation.
Which supplied finding most directly argues against "Add short-course bismuth initially; continue symptom treatment after the change" in this case?
The later fever and bloody stools require reassessment rather than continued symptom treatment as the complete plan.
What clinical discriminator should be carried forward when evaluating "Add short-course bismuth initially; continue symptom treatment after the change"?
A medicine that fits the first assessment may not be sufficient after the illness changes.
Takeaway: Base a diarrhea plan on current severity; new fever, blood or functional deterioration changes what is sufficient.
A. Stop both nonprescription products and obtain prompt toxicity assessment (Best answer)
Both products contribute systemic salicylate despite their different treatment purposes. Tinnitus and nausea after repeated use require assessment, and a four-hour gap does not remove the cumulative exposure. Stop additional nonprescription salicylates and seek prompt clinical or poison-center advice rather than awaiting symptom resolution.
Reasoning steps for option A
Which component is shared despite the different purposes?
Aspirin and bismuth subsalicylate both contribute salicylate exposure.
Does the four-hour interval remove that exposure?
No. This is cumulative systemic exposure rather than a luminal binding interaction.
What do tinnitus and uncertain doses require?
Stop further nonprescription salicylates and obtain prompt toxicity assessment.
B. Stop the stomach product and defer assessment until tinnitus resolves (Why this does not fit)
Removing bismuth subsalicylate reduces one source of salicylate. Aspirin still supplies the same toxic component, and waiting is not appropriate when symptoms and uncertain doses raise concern. Review all products containing a shared active component and respond to toxicity symptoms promptly.
Reasoning steps for option B
For "Stop the stomach product and defer assessment until tinnitus resolves", what case feature makes this choice seem initially reasonable?
Removing bismuth subsalicylate reduces one source of salicylate.
Which supplied finding most directly argues against "Stop the stomach product and defer assessment until tinnitus resolves" in this case?
Aspirin still supplies the same toxic component, and waiting is not appropriate when symptoms and uncertain doses raise concern.
What clinical discriminator should be carried forward when evaluating "Stop the stomach product and defer assessment until tinnitus resolves"?
Review all products containing a shared active component and respond to toxicity symptoms promptly.
C. Separate the two products further and arrange routine medication review (Why this does not fit)
Longer intervals can correct some interactions caused by binding in the gut. The documented separation has not prevented symptoms because the concern is additive systemic exposure rather than luminal binding. Select an interaction correction that fits the mechanism rather than applying a universal timing rule.
Reasoning steps for option C
For "Separate the two products further and arrange routine medication review", what case feature makes this choice seem initially reasonable?
Longer intervals can correct some interactions caused by binding in the gut.
Which supplied finding most directly argues against "Separate the two products further and arrange routine medication review" in this case?
The documented separation has not prevented symptoms because the concern is additive systemic exposure rather than luminal binding.
What clinical discriminator should be carried forward when evaluating "Separate the two products further and arrange routine medication review"?
Select an interaction correction that fits the mechanism rather than applying a universal timing rule.
D. Reduce the aspirin dose and retain the current stomach product (Why this does not fit)
Reducing an excessive dose can reduce further exposure. This partial adjustment leaves an additional salicylate source and does not assess the new toxicity symptoms. Improvement in the original complaint does not establish safety of the combined medication exposure.
Reasoning steps for option D
For "Reduce the aspirin dose and retain the current stomach product", what case feature makes this choice seem initially reasonable?
Reducing an excessive dose can reduce further exposure.
Which supplied finding most directly argues against "Reduce the aspirin dose and retain the current stomach product" in this case?
This partial adjustment leaves an additional salicylate source and does not assess the new toxicity symptoms.
What clinical discriminator should be carried forward when evaluating "Reduce the aspirin dose and retain the current stomach product"?
Improvement in the original complaint does not establish safety of the combined medication exposure.
Takeaway: Dose spacing does not remove cumulative salicylate exposure from multiple products.
A. Replace subsalicylate with subcitrate during the neurologic assessment (Why this does not fit)
Changing formulations removes the salicylate component and can matter for a salicylate-specific hazard. The subacute neurologic syndrome after prolonged excess use raises concern for bismuth itself, which remains in subcitrate. A formulation change helps only when it removes the component responsible for the suspected harm.
Reasoning steps for option A
For "Replace subsalicylate with subcitrate during the neurologic assessment", what case feature makes this choice seem initially reasonable?
Changing formulations removes the salicylate component and can matter for a salicylate-specific hazard.
Which supplied finding most directly argues against "Replace subsalicylate with subcitrate during the neurologic assessment" in this case?
The subacute neurologic syndrome after prolonged excess use raises concern for bismuth itself, which remains in subcitrate.
What clinical discriminator should be carried forward when evaluating "Replace subsalicylate with subcitrate during the neurologic assessment"?
A formulation change helps only when it removes the component responsible for the suspected harm.
B. Suspend bismuth-containing products during the neurologic assessment (Best answer)
Chronic excess bismuth exposure can cause an encephalopathy with gait and myoclonic findings. Normal salicylate results do not assess the metal component, and subcitrate would continue that exposure. Stop bismuth products and investigate the body burden and other neurologic causes without assuming a confirmed diagnosis.
Reasoning steps for option B
What does the negative salicylate assessment leave untested?
The bismuth component and its potential accumulation are not excluded by a salicylate result.
How does the time course and organ pattern affect that concern?
Prolonged excess exposure with cognitive, gait and myoclonic findings supports investigating bismuth-associated encephalopathy.
Would changing to subcitrate remove the suspected exposure?
No. Subcitrate still supplies bismuth, so suspend bismuth products while investigating toxicity and other neurologic causes.
C. Reduce subsalicylate to labeled doses during the neurologic assessment (Why this does not fit)
Correcting excessive dosing can prevent additional avoidable exposure. A lower ongoing dose is not an adequate response to possible accumulated bismuth neurotoxicity. Suspected toxicity after prolonged use requires withdrawal and evaluation rather than simply resetting the daily dose.
Reasoning steps for option C
For "Reduce subsalicylate to labeled doses during the neurologic assessment", what case feature makes this choice seem initially reasonable?
Correcting excessive dosing can prevent additional avoidable exposure.
Which supplied finding most directly argues against "Reduce subsalicylate to labeled doses during the neurologic assessment" in this case?
A lower ongoing dose is not an adequate response to possible accumulated bismuth neurotoxicity.
What clinical discriminator should be carried forward when evaluating "Reduce subsalicylate to labeled doses during the neurologic assessment"?
Suspected toxicity after prolonged use requires withdrawal and evaluation rather than simply resetting the daily dose.
D. Separate subsalicylate doses further during the neurologic assessment (Why this does not fit)
Timing changes can reduce some interactions involving simultaneous gastrointestinal exposures. This pattern concerns accumulated bismuth rather than a competing oral medicine being bound in the lumen. Distinguish the total absorbed burden from the interval between administrations.
Reasoning steps for option D
For "Separate subsalicylate doses further during the neurologic assessment", what case feature makes this choice seem initially reasonable?
Timing changes can reduce some interactions involving simultaneous gastrointestinal exposures.
Which supplied finding most directly argues against "Separate subsalicylate doses further during the neurologic assessment" in this case?
This pattern concerns accumulated bismuth rather than a competing oral medicine being bound in the lumen.
What clinical discriminator should be carried forward when evaluating "Separate subsalicylate doses further during the neurologic assessment"?
Distinguish the total absorbed burden from the interval between administrations.
Takeaway: A salicylate-free formulation still contains bismuth; match a substitution to the component causing concern.
A. Suppression of parietal-cell proton-pump activity (Why this does not fit)
Proton-pump inhibition can protect an ulcer by reducing acid delivery. The experiment instead shows persistent acid production and a localized surface film. A barrier effect can protect tissue without shutting down secretion.
Reasoning steps for option A
For "Suppression of parietal-cell proton-pump activity", what case feature makes this choice seem initially reasonable?
Proton-pump inhibition can protect an ulcer by reducing acid delivery.
Which supplied finding most directly argues against "Suppression of parietal-cell proton-pump activity" in this case?
The experiment instead shows persistent acid production and a localized surface film.
What clinical discriminator should be carried forward when evaluating "Suppression of parietal-cell proton-pump activity"?
A barrier effect can protect tissue without shutting down secretion.
B. Replacement of a depleted prostaglandin signal (Why this does not fit)
Prostaglandin analogs can improve gastric defense and reduce secretion. The visible adherent drug-protein layer is characteristic of local sucralfate action. Distinguish a surface complex from receptor-mediated prostaglandin activity.
Reasoning steps for option B
For "Replacement of a depleted prostaglandin signal", what case feature makes this choice seem initially reasonable?
Prostaglandin analogs can improve gastric defense and reduce secretion.
Which supplied finding most directly argues against "Replacement of a depleted prostaglandin signal" in this case?
The visible adherent drug-protein layer is characteristic of local sucralfate action.
What clinical discriminator should be carried forward when evaluating "Replacement of a depleted prostaglandin signal"?
Distinguish a surface complex from receptor-mediated prostaglandin activity.
C. Neutralization of acid in the lumen (Why this does not fit)
An antacid can protect tissue by reducing acidity without directly inhibiting acid secretion. The unchanged bulk pH and localized adherent film favor a surface barrier as the explanation for the reduced tracer penetration. Use acid production, luminal pH and surface localization together to distinguish these actions.
Reasoning steps for option C
For "Neutralization of acid in the lumen", what case feature makes this choice seem initially reasonable?
An antacid can protect tissue by reducing acidity without directly inhibiting acid secretion.
Which supplied finding most directly argues against "Neutralization of acid in the lumen" in this case?
The unchanged bulk pH and localized adherent film favor a surface barrier as the explanation for the reduced tracer penetration.
What clinical discriminator should be carried forward when evaluating "Neutralization of acid in the lumen"?
Use acid production, luminal pH and surface localization together to distinguish these actions.
D. Surface barrier limiting luminal ulcer injury (Best answer)
Sucralfate forms an adherent complex with proteins at the injured site. The film restricts acid penetration while acid production can continue. Local physical protection and systemic secretion control are different therapeutic actions.
Reasoning steps for option D
Which acid-related measurements stay stable?
Acid production and the bulk luminal pH remain largely unchanged.
Where is the protective change located?
At the ulcer surface, where a drug-protein layer has formed.
What causal explanation fits both observations?
A local barrier limits further luminal injury without requiring strong acid suppression.
Takeaway: Protection at an ulcer surface is not the same as shutting off acid production.
A. Increased renal filtration of circulating digoxin (Why this does not fit)
Renal function is important for digoxin elimination. Unchanged intravenous clearance and renal measurements do not support faster elimination. An oral-only exposure change points toward events before systemic absorption.
Reasoning steps for option A
For "Increased renal filtration of circulating digoxin", what case feature makes this choice seem initially reasonable?
Renal function is important for digoxin elimination.
Which supplied finding most directly argues against "Increased renal filtration of circulating digoxin" in this case?
Unchanged intravenous clearance and renal measurements do not support faster elimination.
What clinical discriminator should be carried forward when evaluating "Increased renal filtration of circulating digoxin"?
An oral-only exposure change points toward events before systemic absorption.
B. Induction of systemic drug-metabolizing enzymes (Why this does not fit)
Enzyme induction can lower concentrations of susceptible medicines. The route-dependent change and stable intravenous disposition support a presystemic gastrointestinal interaction instead. Use oral versus intravenous findings to locate an interaction.
Reasoning steps for option B
For "Induction of systemic drug-metabolizing enzymes", what case feature makes this choice seem initially reasonable?
Enzyme induction can lower concentrations of susceptible medicines.
Which supplied finding most directly argues against "Induction of systemic drug-metabolizing enzymes" in this case?
The route-dependent change and stable intravenous disposition support a presystemic gastrointestinal interaction instead.
What clinical discriminator should be carried forward when evaluating "Induction of systemic drug-metabolizing enzymes"?
Use oral versus intravenous findings to locate an interaction.
C. Luminal binding before intestinal absorption (Best answer)
Sucralfate can bind selected concomitant medicines in the gastrointestinal tract. Reduced oral exposure with unchanged intravenous clearance localizes the problem before the drug reaches circulation. Separate critical oral medicines using their specific instructions and monitor the clinical response.
Reasoning steps for option C
Which route shows reduced exposure?
The oral route, not the intravenous route.
What does unchanged intravenous clearance argue against?
A new systemic elimination process as the principal explanation.
Where can sucralfate reduce availability?
In the gastrointestinal lumen, before the oral drug is absorbed.
D. Displacement from plasma proteins after absorption (Why this does not fit)
Changes in protein binding can alter free drug measurements and distribution. A selective fall in oral exposure with unchanged intravenous disposition is not explained by the proposed systemic change. Distinguish luminal availability from post-absorption handling.
Reasoning steps for option D
For "Displacement from plasma proteins after absorption", what case feature makes this choice seem initially reasonable?
Changes in protein binding can alter free drug measurements and distribution.
Which supplied finding most directly argues against "Displacement from plasma proteins after absorption" in this case?
A selective fall in oral exposure with unchanged intravenous disposition is not explained by the proposed systemic change.
What clinical discriminator should be carried forward when evaluating "Displacement from plasma proteins after absorption"?
Distinguish luminal availability from post-absorption handling.
Takeaway: Route-dependent pharmacokinetic data can identify a local absorption interaction.
This creates a two-hour gap after the first sucralfate dose. Two hours is the interval when ciprofloxacin comes first, not when sucralfate comes first. Keep the direction of the interval attached to the named drug.
Reasoning steps for option A
For "10:00", what case feature makes this choice seem initially reasonable?
This creates a two-hour gap after the first sucralfate dose.
Which supplied finding most directly argues against "10:00" in this case?
Two hours is the interval when ciprofloxacin comes first, not when sucralfate comes first.
What clinical discriminator should be carried forward when evaluating "10:00"?
Keep the direction of the interval attached to the named drug.
B. 14:00 (Best answer)
Six hours have elapsed since the 08:00 sucralfate dose. The next sucralfate is still four hours away, so both supplied conditions are satisfied. Check both neighboring doses rather than just one interval.
Reasoning steps for option B
When does the interval after the morning sucralfate end?
At 14:00, six hours after 08:00.
What is the latest permitted time before the evening sucralfate?
16:00, two hours before 18:00.
Which offered time is earliest within that interval?
14:00.
C. 16:00 (Why this does not fit)
This is two hours before the next sucralfate dose and eight hours after the last. It is acceptable but not the earliest qualifying time offered. When asked for the earliest time, satisfy all conditions without adding an unnecessary delay.
Reasoning steps for option C
For "16:00", what case feature makes this choice seem initially reasonable?
This is two hours before the next sucralfate dose and eight hours after the last.
Which supplied finding most directly argues against "16:00" in this case?
It is acceptable but not the earliest qualifying time offered.
What clinical discriminator should be carried forward when evaluating "16:00"?
When asked for the earliest time, satisfy all conditions without adding an unnecessary delay.
D. 17:00 (Why this does not fit)
This is more than six hours after the preceding sucralfate. Only one hour remains before the next sucralfate, so the second condition fails. A correct gap from the earlier dose does not excuse overlap with the next one.
Reasoning steps for option D
For "17:00", what case feature makes this choice seem initially reasonable?
This is more than six hours after the preceding sucralfate.
Which supplied finding most directly argues against "17:00" in this case?
Only one hour remains before the next sucralfate, so the second condition fails.
What clinical discriminator should be carried forward when evaluating "17:00"?
A correct gap from the earlier dose does not excuse overlap with the next one.
Takeaway: Dose-spacing instructions can be directional and must account for the next dose as well as the previous one.
This is four hours after levothyroxine and three hours after ciprofloxacin. Both minimum intervals have elapsed at this time. When several oral medicines interact, use the most restrictive applicable interval.
Reasoning steps for option A
What time satisfies levothyroxine separation?
09:00, four hours after the 05:00 dose.
What time satisfies ciprofloxacin separation?
08:00, two hours after the 06:00 dose.
Which lower bound determines the combined schedule?
09:00, because both conditions must be true.
B. 07:00 (Why this does not fit)
One hour has elapsed since ciprofloxacin. Neither the two-hour ciprofloxacin interval nor the four-hour levothyroxine interval is complete. A single shared medication time may violate more than one absorption requirement.
Reasoning steps for option B
For "07:00", what case feature makes this choice seem initially reasonable?
One hour has elapsed since ciprofloxacin.
Which supplied finding most directly argues against "07:00" in this case?
Neither the two-hour ciprofloxacin interval nor the four-hour levothyroxine interval is complete.
What clinical discriminator should be carried forward when evaluating "07:00"?
A single shared medication time may violate more than one absorption requirement.
C. 08:00 (Why this does not fit)
Two hours have elapsed since ciprofloxacin. Only three hours have elapsed since levothyroxine. The familiar two-hour rule cannot replace a second drug’s longer interval.
Reasoning steps for option C
For "08:00", what case feature makes this choice seem initially reasonable?
Two hours have elapsed since ciprofloxacin.
Which supplied finding most directly argues against "08:00" in this case?
Only three hours have elapsed since levothyroxine.
What clinical discriminator should be carried forward when evaluating "08:00"?
The familiar two-hour rule cannot replace a second drug’s longer interval.
D. 11:00 (Why this does not fit)
Both intervals would be satisfied by this later time. 09:00 already satisfies them, so this is not the earliest qualifying option. Find the latest minimum interval rather than adding all intervals together.
Reasoning steps for option D
For "11:00", what case feature makes this choice seem initially reasonable?
Both intervals would be satisfied by this later time.
Which supplied finding most directly argues against "11:00" in this case?
09:00 already satisfies them, so this is not the earliest qualifying option.
What clinical discriminator should be carried forward when evaluating "11:00"?
Find the latest minimum interval rather than adding all intervals together.
Takeaway: Build the schedule from each interacting drug’s own instructions.
A. Increase levothyroxine and keep both medicines together (Why this does not fit)
An increased thyroid dose can be appropriate when replacement requirements rise. The timing and newly added binding medicine suggest reduced absorption that should first be addressed. Avoid committing to a higher dose while leaving a reversible administration problem unchanged.
Reasoning steps for option A
For "Increase levothyroxine and keep both medicines together", what case feature makes this choice seem initially reasonable?
An increased thyroid dose can be appropriate when replacement requirements rise.
Which supplied finding most directly argues against "Increase levothyroxine and keep both medicines together" in this case?
The timing and newly added binding medicine suggest reduced absorption that should first be addressed.
What clinical discriminator should be carried forward when evaluating "Increase levothyroxine and keep both medicines together"?
Avoid committing to a higher dose while leaving a reversible administration problem unchanged.
B. Reduce levothyroxine and repeat thyroid tests later (Why this does not fit)
Dose reduction is appropriate when thyroid replacement is excessive. High TSH with low free T4 indicates inadequate replacement in primary hypothyroidism, not excess. Interpret both the direction of laboratory change and the clinical context.
Reasoning steps for option B
For "Reduce levothyroxine and repeat thyroid tests later", what case feature makes this choice seem initially reasonable?
Dose reduction is appropriate when thyroid replacement is excessive.
Which supplied finding most directly argues against "Reduce levothyroxine and repeat thyroid tests later" in this case?
High TSH with low free T4 indicates inadequate replacement in primary hypothyroidism, not excess.
What clinical discriminator should be carried forward when evaluating "Reduce levothyroxine and repeat thyroid tests later"?
Interpret both the direction of laboratory change and the clinical context.
C. Continue the schedule and disregard the TSH result (Why this does not fit)
TSH can be unreliable in central hypothyroidism and some acute illnesses. This patient has primary hypothyroidism with concordant low free T4 and symptoms. Do not dismiss a relevant monitoring marker when the physiology is internally consistent.
Reasoning steps for option C
For "Continue the schedule and disregard the TSH result", what case feature makes this choice seem initially reasonable?
TSH can be unreliable in central hypothyroidism and some acute illnesses.
Which supplied finding most directly argues against "Continue the schedule and disregard the TSH result" in this case?
This patient has primary hypothyroidism with concordant low free T4 and symptoms.
What clinical discriminator should be carried forward when evaluating "Continue the schedule and disregard the TSH result"?
Do not dismiss a relevant monitoring marker when the physiology is internally consistent.
D. Separate dosing by at least four hours; reassess (Best answer)
Sucralfate can reduce levothyroxine absorption when coadministered. The new dosing arrangement and concordant thyroid results support correcting the interaction and arranging follow-up testing. After changing absorption conditions, reassess before and during any subsequent dose adjustment.
Reasoning steps for option D
What do the thyroid results show in primary hypothyroidism?
A. Further loss of oral digoxin exposure (Why this does not fit)
Ongoing luminal binding can reduce digoxin availability. The binding medicine has now been discontinued, so that effect should no longer be assumed to persist. Reassess interacting medicines when an adjunct is stopped as well as when it is started.
Reasoning steps for option A
For "Further loss of oral digoxin exposure", what case feature makes this choice seem initially reasonable?
Ongoing luminal binding can reduce digoxin availability.
Which supplied finding most directly argues against "Further loss of oral digoxin exposure" in this case?
The binding medicine has now been discontinued, so that effect should no longer be assumed to persist.
What clinical discriminator should be carried forward when evaluating "Further loss of oral digoxin exposure"?
Reassess interacting medicines when an adjunct is stopped as well as when it is started.
B. Progressive reduction of renal digoxin clearance (Why this does not fit)
Renal deterioration can increase digoxin exposure. No change in renal function is supplied; the new event is withdrawal of a gastrointestinal binder. Do not attribute a changing concentration to clearance without supporting evidence.
Reasoning steps for option B
For "Progressive reduction of renal digoxin clearance", what case feature makes this choice seem initially reasonable?
Renal deterioration can increase digoxin exposure.
Which supplied finding most directly argues against "Progressive reduction of renal digoxin clearance" in this case?
No change in renal function is supplied; the new event is withdrawal of a gastrointestinal binder.
What clinical discriminator should be carried forward when evaluating "Progressive reduction of renal digoxin clearance"?
Do not attribute a changing concentration to clearance without supporting evidence.
C. Increased digoxin exposure at the higher dose (Best answer)
Discontinuing a binder can increase the amount of the oral drug available for absorption. The dose had been increased while the interaction was present and now continues without that interaction. Arrange clinical and concentration reassessment rather than automatically retaining a compensation dose.
Reasoning steps for option C
Why had the dose been increased?
Measured exposure fell while sucralfate was being taken at the same time.
What changed when the ulcer course ended?
The luminal binding exposure stopped.
What can happen at the retained higher digoxin dose?
Systemic exposure can rise, requiring reassessment for excess effect.
D. Unchanged exposure because prescribed dose is unchanged (Why this does not fit)
A stable dose can maintain stable exposure when absorption and clearance are stable. Absorption conditions changed when sucralfate ended. The same dose does not guarantee the same exposure after an interaction is altered.
Reasoning steps for option D
For "Unchanged exposure because prescribed dose is unchanged", what case feature makes this choice seem initially reasonable?
A stable dose can maintain stable exposure when absorption and clearance are stable.
Which supplied finding most directly argues against "Unchanged exposure because prescribed dose is unchanged" in this case?
Absorption conditions changed when sucralfate ended.
What clinical discriminator should be carried forward when evaluating "Unchanged exposure because prescribed dose is unchanged"?
The same dose does not guarantee the same exposure after an interaction is altered.
Takeaway: Stopping a binding medicine can make an earlier compensation dose excessive.
A. Assess aluminum accumulation and reconsider both products (Best answer)
Small amounts of aluminum can be absorbed from sucralfate and aluminum antacids. Impaired excretion and protein binding make routine dialysis an inadequate reassurance against accumulation. Long exposure and additional aluminum sources matter even for a primarily local medicine.
Reasoning steps for option A
Is absorption exactly zero?
No. Small quantities of aluminum can enter the body.
What prevents the usual clearance of that quantity?
Severe renal impairment limits urinary elimination.
Why is regular dialysis not a sufficient reassurance?
Protein-bound aluminum does not readily cross dialysis membranes.
What should the medication review target?
Both aluminum-containing products and the accumulated exposure, alongside investigation of other causes.
B. Increase the antacid dose to bind dietary phosphate (Why this does not fit)
Aluminum compounds can bind phosphate in the gastrointestinal tract. Additional aluminum adds to the suspected body burden and does not explain away the new symptoms. A useful local effect does not negate systemic accumulation risk.
Reasoning steps for option B
For "Increase the antacid dose to bind dietary phosphate", what case feature makes this choice seem initially reasonable?
Aluminum compounds can bind phosphate in the gastrointestinal tract.
Which supplied finding most directly argues against "Increase the antacid dose to bind dietary phosphate" in this case?
Additional aluminum adds to the suspected body burden and does not explain away the new symptoms.
What clinical discriminator should be carried forward when evaluating "Increase the antacid dose to bind dietary phosphate"?
A useful local effect does not negate systemic accumulation risk.
C. Shorten the interval between sucralfate and dialysis (Why this does not fit)
Dialysis timing helps manage medicines that are efficiently dialyzable. Protein-bound aluminum is not reliably cleared simply by scheduling the oral dose near dialysis. Determine dialyzability rather than assuming all absorbed substances are easily filtered.
Reasoning steps for option C
For "Shorten the interval between sucralfate and dialysis", what case feature makes this choice seem initially reasonable?
Dialysis timing helps manage medicines that are efficiently dialyzable.
Which supplied finding most directly argues against "Shorten the interval between sucralfate and dialysis" in this case?
Protein-bound aluminum is not reliably cleared simply by scheduling the oral dose near dialysis.
What clinical discriminator should be carried forward when evaluating "Shorten the interval between sucralfate and dialysis"?
Determine dialyzability rather than assuming all absorbed substances are easily filtered.
D. Intensify dialysis first and retain both stomach medicines (Why this does not fit)
Inadequate dialysis can contribute to encephalopathy in kidney failure. Adequacy measurements are unchanged, and routine dialysis does not reliably resolve the protein-bound aluminum burden. Do not retain an avoidable exposure solely because renal replacement is already occurring.
Reasoning steps for option D
For "Intensify dialysis first and retain both stomach medicines", what case feature makes this choice seem initially reasonable?
Inadequate dialysis can contribute to encephalopathy in kidney failure.
Which supplied finding most directly argues against "Intensify dialysis first and retain both stomach medicines" in this case?
Adequacy measurements are unchanged, and routine dialysis does not reliably resolve the protein-bound aluminum burden.
What clinical discriminator should be carried forward when evaluating "Intensify dialysis first and retain both stomach medicines"?
Do not retain an avoidable exposure solely because renal replacement is already occurring.
Takeaway: Local action does not eliminate accumulation risk in renal failure.
A. Inflammatory narrowing of the gastric outlet (Why this does not fit)
Ulcer-associated inflammation can sometimes obstruct gastric emptying. Endoscopy shows a patent outlet without obstructing edema and instead identifies compacted intraluminal material. Use the observed location of the obstruction rather than inferring a stenosis from vomiting alone.
Reasoning steps for option A
For "Inflammatory narrowing of the gastric outlet", what case feature makes this choice seem initially reasonable?
Ulcer-associated inflammation can sometimes obstruct gastric emptying.
Which supplied finding most directly argues against "Inflammatory narrowing of the gastric outlet" in this case?
Endoscopy shows a patent outlet without obstructing edema and instead identifies compacted intraluminal material.
What clinical discriminator should be carried forward when evaluating "Inflammatory narrowing of the gastric outlet"?
Use the observed location of the obstruction rather than inferring a stenosis from vomiting alone.
B. Aggregation in a stomach with delayed emptying (Best answer)
Sucralfate-associated bezoars have been reported, especially with impaired gastric emptying or enteral feeding. The patient has both risk contexts and a retained compacted mass. Review the need and delivery of sucralfate and investigate feeding intolerance rather than assuming uncomplicated ulcer pain.
Reasoning steps for option B
Where is the abnormal material located?
Inside the gastric lumen, rather than within the pyloric wall.
What background condition promotes retention?
Delayed gastric emptying.
How does the medicine history contribute?
Sucralfate-associated bezoars are reported particularly with stasis or enteral feeding.
C. A symptomatic ulcer without a retention complication (Why this does not fit)
Active ulcers can cause pain, nausea and food intolerance. Uncomplicated ulcer symptoms do not account for the endoscopically visible compacted material. Explain the structural finding as well as the symptoms.
Reasoning steps for option C
For "A symptomatic ulcer without a retention complication", what case feature makes this choice seem initially reasonable?
Active ulcers can cause pain, nausea and food intolerance.
Which supplied finding most directly argues against "A symptomatic ulcer without a retention complication" in this case?
Uncomplicated ulcer symptoms do not account for the endoscopically visible compacted material.
What clinical discriminator should be carried forward when evaluating "A symptomatic ulcer without a retention complication"?
Explain the structural finding as well as the symptoms.
D. Delayed emptying with only liquid feed retention (Why this does not fit)
Gastroparesis itself can delay emptying of enteral nutrition. The compacted material points to a retained concretion rather than liquid stasis alone. Distinguish the background motility problem from the additional retained-material complication.
Reasoning steps for option D
For "Delayed emptying with only liquid feed retention", what case feature makes this choice seem initially reasonable?
Gastroparesis itself can delay emptying of enteral nutrition.
Which supplied finding most directly argues against "Delayed emptying with only liquid feed retention" in this case?
The compacted material points to a retained concretion rather than liquid stasis alone.
What clinical discriminator should be carried forward when evaluating "Delayed emptying with only liquid feed retention"?
Distinguish the background motility problem from the additional retained-material complication.
Takeaway: New feeding intolerance in a high-risk patient warrants assessment for retained material.
A. Stop the PPI and retain the antacid schedule (Why this does not fit)
Acidity is relevant to sucralfate’s local film formation. That chemistry is not a reason to abandon indicated esophagitis treatment while leaving the directly conflicting antacid timing unchanged. Treat the patient’s indications rather than using acid dependence as an absolute prohibition.
Reasoning steps for option A
For "Stop the PPI and retain the antacid schedule", what case feature makes this choice seem initially reasonable?
Acidity is relevant to sucralfate’s local film formation.
Which supplied finding most directly argues against "Stop the PPI and retain the antacid schedule" in this case?
That chemistry is not a reason to abandon indicated esophagitis treatment while leaving the directly conflicting antacid timing unchanged.
What clinical discriminator should be carried forward when evaluating "Stop the PPI and retain the antacid schedule"?
Treat the patient’s indications rather than using acid dependence as an absolute prohibition.
B. Double sucralfate and retain all administration times (Why this does not fit)
A greater local dose might appear to compensate for an administration problem. Dose escalation does not correct inappropriate antacid timing and adds unnecessary exposure. Correct administration and reassess the indication before increasing a dose.
Reasoning steps for option B
For "Double sucralfate and retain all administration times", what case feature makes this choice seem initially reasonable?
A greater local dose might appear to compensate for an administration problem.
Which supplied finding most directly argues against "Double sucralfate and retain all administration times" in this case?
Dose escalation does not correct inappropriate antacid timing and adds unnecessary exposure.
What clinical discriminator should be carried forward when evaluating "Double sucralfate and retain all administration times"?
Correct administration and reassess the indication before increasing a dose.
C. Keep both doses together but use a different antacid (Why this does not fit)
Antacid formulations vary in their ingredients and adverse effects. Changing the product does not remove the sucralfate label’s antacid-separation instruction. Check the interaction instruction rather than relying on a brand substitution.
Reasoning steps for option C
For "Keep both doses together but use a different antacid", what case feature makes this choice seem initially reasonable?
Antacid formulations vary in their ingredients and adverse effects.
Which supplied finding most directly argues against "Keep both doses together but use a different antacid" in this case?
Changing the product does not remove the sucralfate label’s antacid-separation instruction.
What clinical discriminator should be carried forward when evaluating "Keep both doses together but use a different antacid"?
Check the interaction instruction rather than relying on a brand substitution.
D. Separate the antacid and review the combined regimen (Best answer)
The sucralfate label keeps antacids outside the half-hour window before and after dosing. The PPI has a separate documented indication that should not be stopped automatically. Reconcile necessity and timing with the clinician while preserving needed acid-suppressive care.
Reasoning steps for option D
Which administration conflict is explicit?
Antacid is being taken within the restricted half-hour sucralfate window.
Does the chemistry erase the PPI’s clinical indication?
No. Severe erosive esophagitis still requires an appropriate treatment plan.
What is the defensible correction?
Address antacid timing and clinician review of the overall regimen rather than stopping the PPI automatically.
Takeaway: Acid-dependent film formation is not a universal prohibition against clinically indicated acid suppression.
A. Prostaglandin-receptor stimulation with reduced acid secretion (Best answer)
NSAIDs reduce the synthesis of protective prostaglandins in gastric mucosa. A prostaglandin analog can bypass that synthesis deficit, restore defensive secretion and inhibit acid secretion without forming a film. A downstream receptor agonist can compensate for a missing endogenous signal while the synthesis block persists.
Reasoning steps for option A
Where has naproxen interrupted the protective process?
NSAID action reduces endogenous prostaglandin synthesis and defensive secretion.
What does recovery despite persistent synthesis suppression imply?
The adjunct can supply the missing effect downstream rather than reactivate the blocked synthetic step.
Which action also predicts the additional acid response?
Prostaglandin-receptor stimulation by misoprostol fits the rescue and predicts reduced acid secretion at an effective dose.
B. Cyclooxygenase reactivation with increased acid secretion (Why this does not fit)
Restoring the enzyme upstream could restore endogenous prostaglandin production. The experiment explicitly shows that endogenous mediator synthesis remains suppressed, so enzyme reactivation does not explain the rescue. Use the measured upstream response to distinguish restoration of synthesis from a downstream replacement effect.
Reasoning steps for option B
For "Cyclooxygenase reactivation with increased acid secretion", what case feature makes this choice seem initially reasonable?
Restoring the enzyme upstream could restore endogenous prostaglandin production.
Which supplied finding most directly argues against "Cyclooxygenase reactivation with increased acid secretion" in this case?
The experiment explicitly shows that endogenous mediator synthesis remains suppressed, so enzyme reactivation does not explain the rescue.
What clinical discriminator should be carried forward when evaluating "Cyclooxygenase reactivation with increased acid secretion"?
Use the measured upstream response to distinguish restoration of synthesis from a downstream replacement effect.
C. Ulcer-protein binding with unchanged acid secretion (Why this does not fit)
Sucralfate can provide local protection while acid production continues. A drug-protein film is absent, and restored mucus and bicarbonate secretion indicate a different protective process. Separate an adherent barrier from a pharmacologic change in epithelial secretion.
Reasoning steps for option C
For "Ulcer-protein binding with unchanged acid secretion", what case feature makes this choice seem initially reasonable?
Sucralfate can provide local protection while acid production continues.
Which supplied finding most directly argues against "Ulcer-protein binding with unchanged acid secretion" in this case?
A drug-protein film is absent, and restored mucus and bicarbonate secretion indicate a different protective process.
What clinical discriminator should be carried forward when evaluating "Ulcer-protein binding with unchanged acid secretion"?
Separate an adherent barrier from a pharmacologic change in epithelial secretion.
D. Luminal acid neutralization with unchanged defensive signaling (Why this does not fit)
Neutralizing acid can reduce injury without directly inhibiting acid production. It does not account for recovery of defensive secretion while the endogenous mediator deficit persists. Protection from acid and replacement of a missing signaling effect are distinct mechanisms.
Reasoning steps for option D
For "Luminal acid neutralization with unchanged defensive signaling", what case feature makes this choice seem initially reasonable?
Neutralizing acid can reduce injury without directly inhibiting acid production.
Which supplied finding most directly argues against "Luminal acid neutralization with unchanged defensive signaling" in this case?
It does not account for recovery of defensive secretion while the endogenous mediator deficit persists.
What clinical discriminator should be carried forward when evaluating "Luminal acid neutralization with unchanged defensive signaling"?
Protection from acid and replacement of a missing signaling effect are distinct mechanisms.
Takeaway: A replacement signal can restore secretion downstream of a synthesis block without forming a local film.
A. Continue the lower dose and reassess after the first trimester (Why this does not fit)
Lower doses can improve gastrointestinal tolerability. A lower dose does not resolve the pregnancy contraindication for NSAID-ulcer prevention. Dose adjustment for diarrhea and pregnancy safety are different decisions.
Reasoning steps for option A
For "Continue the lower dose and reassess after the first trimester", what case feature makes this choice seem initially reasonable?
Lower doses can improve gastrointestinal tolerability.
Which supplied finding most directly argues against "Continue the lower dose and reassess after the first trimester" in this case?
A lower dose does not resolve the pregnancy contraindication for NSAID-ulcer prevention.
What clinical discriminator should be carried forward when evaluating "Continue the lower dose and reassess after the first trimester"?
Dose adjustment for diarrhea and pregnancy safety are different decisions.
B. Continue treatment because obstetric clinicians also use it (Why this does not fit)
Misoprostol does have separate reproductive-health applications. Those uses do not justify exposure for gastrointestinal prophylaxis during a pregnancy the patient wishes to continue. Indication-specific use and monitoring cannot be transferred to a different treatment goal.
Reasoning steps for option B
For "Continue treatment because obstetric clinicians also use it", what case feature makes this choice seem initially reasonable?
Misoprostol does have separate reproductive-health applications.
Which supplied finding most directly argues against "Continue treatment because obstetric clinicians also use it" in this case?
Those uses do not justify exposure for gastrointestinal prophylaxis during a pregnancy the patient wishes to continue.
What clinical discriminator should be carried forward when evaluating "Continue treatment because obstetric clinicians also use it"?
Indication-specific use and monitoring cannot be transferred to a different treatment goal.
C. Stop this prophylactic use and contact the treating clinician now (Best answer)
Misoprostol can produce uterine contractions and pregnancy harm. The current purpose is ulcer prophylaxis, for which pregnancy is contraindicated. Arrange prompt individualized counseling and review the NSAID and gastroprotection plan; exposure does not establish an inevitable outcome.
Reasoning steps for option C
Why is misoprostol being used here?
For prevention of NSAID-associated ulcers, not for an obstetric indication.
What newly changes its suitability?
Confirmed pregnancy, given its uterotonic and pregnancy-harm potential.
Does dose reduction solve the problem?
No. The GI prophylaxis indication remains contraindicated.
What follows?
Discontinue that use and obtain prompt counseling and a revised medication plan.
D. Continue until the scheduled scan because there is no bleeding (Why this does not fit)
Obstetric imaging can contribute to follow-up after an exposure. Absence of bleeding does not make continued misoprostol use appropriate for gastrointestinal prophylaxis in pregnancy. End the contraindicated prophylactic exposure and arrange counseling without waiting for symptoms.
Reasoning steps for option D
For "Continue until the scheduled scan because there is no bleeding", what case feature makes this choice seem initially reasonable?
Obstetric imaging can contribute to follow-up after an exposure.
Which supplied finding most directly argues against "Continue until the scheduled scan because there is no bleeding" in this case?
Absence of bleeding does not make continued misoprostol use appropriate for gastrointestinal prophylaxis in pregnancy.
What clinical discriminator should be carried forward when evaluating "Continue until the scheduled scan because there is no bleeding"?
End the contraindicated prophylactic exposure and arrange counseling without waiting for symptoms.
Takeaway: Pregnancy contraindicates misoprostol for ulcer prevention; counseling must not imply that harm is certain.
A. Keep doses before meals; replace the magnesium antacid (Why this does not fit)
Replacing the magnesium-containing product addresses one contributor to diarrhea. The doses are still being taken before food rather than with meals as instructed for tolerability. Correct each relevant administration problem rather than stopping after identifying one contributor.
Reasoning steps for option A
For "Keep doses before meals; replace the magnesium antacid", what case feature makes this choice seem initially reasonable?
Replacing the magnesium-containing product addresses one contributor to diarrhea.
Which supplied finding most directly argues against "Keep doses before meals; replace the magnesium antacid" in this case?
The doses are still being taken before food rather than with meals as instructed for tolerability.
What clinical discriminator should be carried forward when evaluating "Keep doses before meals; replace the magnesium antacid"?
Correct each relevant administration problem rather than stopping after identifying one contributor.
B. Give doses with meals; replace the magnesium antacid (Best answer)
Diarrhea can develop early during misoprostol treatment and can be worsened by magnesium-containing antacids. The new timing and antacid change address both modifiable contributors in this otherwise stable assessment. Keep the last dose at bedtime and reassess persistent intolerance, including the labeled lower-dose option when appropriate.
Reasoning steps for option B
Does the symptom onset fit the new drug?
Early diarrhea and cramping are compatible with misoprostol intolerance.
Which two administration factors can worsen tolerability?
Taking doses without food and using a magnesium-containing antacid are both relevant.
Which initial plan addresses both?
Give the doses with meals, keep the last dose at bedtime and replace the magnesium antacid.
What follows persistent or severe symptoms?
Arrange clinical reassessment; dose reduction may be appropriate, while severe diarrhea or dehydration requires prompt assessment.
C. Halve each fasting dose; retain the magnesium antacid (Why this does not fit)
The label permits a lower dose when the usual dose is not tolerated. This plan leaves both fasting administration and a potentially aggravating magnesium product uncorrected. Review reversible contributors as well as dose when deciding how to manage intolerance.
Reasoning steps for option C
For "Halve each fasting dose; retain the magnesium antacid", what case feature makes this choice seem initially reasonable?
The label permits a lower dose when the usual dose is not tolerated.
Which supplied finding most directly argues against "Halve each fasting dose; retain the magnesium antacid" in this case?
This plan leaves both fasting administration and a potentially aggravating magnesium product uncorrected.
What clinical discriminator should be carried forward when evaluating "Halve each fasting dose; retain the magnesium antacid"?
Review reversible contributors as well as dose when deciding how to manage intolerance.
D. Give doses with meals; retain the magnesium antacid (Why this does not fit)
Taking misoprostol with food can improve tolerability. Continuing the magnesium-containing antacid leaves another supplied contributor to diarrhea in place. A successful timing correction does not resolve a separate adverse effect from another product.
Reasoning steps for option D
For "Give doses with meals; retain the magnesium antacid", what case feature makes this choice seem initially reasonable?
Taking misoprostol with food can improve tolerability.
Which supplied finding most directly argues against "Give doses with meals; retain the magnesium antacid" in this case?
Continuing the magnesium-containing antacid leaves another supplied contributor to diarrhea in place.
What clinical discriminator should be carried forward when evaluating "Give doses with meals; retain the magnesium antacid"?
A successful timing correction does not resolve a separate adverse effect from another product.
Takeaway: Address both food timing and the antacid ingredient; reassess ongoing intolerance rather than simply adding another medicine.
A. Replace it with sucralfate because aluminum cannot be absorbed (Why this does not fit)
Sucralfate acts mainly in the gastrointestinal lumen. Small amounts of aluminum can be absorbed and accumulate with impaired renal clearance. Primarily local action is not proof of zero systemic exposure.
Reasoning steps for option A
For "Replace it with sucralfate because aluminum cannot be absorbed", what case feature makes this choice seem initially reasonable?
Sucralfate acts mainly in the gastrointestinal lumen.
Which supplied finding most directly argues against "Replace it with sucralfate because aluminum cannot be absorbed" in this case?
Small amounts of aluminum can be absorbed and accumulate with impaired renal clearance.
What clinical discriminator should be carried forward when evaluating "Replace it with sucralfate because aluminum cannot be absorbed"?
Primarily local action is not proof of zero systemic exposure.
B. Halve misoprostol automatically and keep the same rationale (Why this does not fit)
Renal impairment can alter exposure to misoprostol’s active metabolite. The label does not require a routine dose reduction solely for renal impairment when the dose is tolerated. Use the drug’s specific guidance rather than a universal renal-dose assumption.
Reasoning steps for option B
For "Halve misoprostol automatically and keep the same rationale", what case feature makes this choice seem initially reasonable?
Renal impairment can alter exposure to misoprostol’s active metabolite.
Which supplied finding most directly argues against "Halve misoprostol automatically and keep the same rationale" in this case?
The label does not require a routine dose reduction solely for renal impairment when the dose is tolerated.
What clinical discriminator should be carried forward when evaluating "Halve misoprostol automatically and keep the same rationale"?
Use the drug’s specific guidance rather than a universal renal-dose assumption.
C. Increase misoprostol because renal disease reduces its exposure (Why this does not fit)
A dose increase is sometimes needed when exposure falls. Renal impairment does not provide that rationale for misoprostol; exposure can increase. Determine the direction of pharmacokinetic change before adjusting a dose.
Reasoning steps for option C
For "Increase misoprostol because renal disease reduces its exposure", what case feature makes this choice seem initially reasonable?
A dose increase is sometimes needed when exposure falls.
Which supplied finding most directly argues against "Increase misoprostol because renal disease reduces its exposure" in this case?
Renal impairment does not provide that rationale for misoprostol; exposure can increase.
What clinical discriminator should be carried forward when evaluating "Increase misoprostol because renal disease reduces its exposure"?
Determine the direction of pharmacokinetic change before adjusting a dose.
D. Use tolerance-based review rather than an aluminum-based switch (Best answer)
Misoprostol has no sucralfate-like aluminum burden. Routine renal dose adjustment is not required by its label, although intolerance can justify reduction. Keep the separate NSAID renal-risk assessment in place while using drug-specific gastroprotection guidance.
Reasoning steps for option D
Which of the two drugs introduces an aluminum burden?
Sucralfate, not misoprostol.
What does the misoprostol label require solely for renal impairment?
No routine schedule adjustment, with reduction considered if the usual dose is not tolerated.
What should not be lost in this comparison?
The independent assessment of whether continued NSAID exposure is appropriate in renal disease.
Takeaway: Renal disease does not create the same hazard or dosing rule for every gastroprotective drug.
A. Compare treated patients with people who never use NSAIDs (Why this does not fit)
People without NSAID exposure may have a different ulcer risk. That comparison changes the injurious exposure as well as the protective treatment. A mechanistic comparison should not replace the relevant baseline risk with a different population.
Reasoning steps for option A
For "Compare treated patients with people who never use NSAIDs", what case feature makes this choice seem initially reasonable?
People without NSAID exposure may have a different ulcer risk.
Which supplied finding most directly argues against "Compare treated patients with people who never use NSAIDs" in this case?
That comparison changes the injurious exposure as well as the protective treatment.
What clinical discriminator should be carried forward when evaluating "Compare treated patients with people who never use NSAIDs"?
A mechanistic comparison should not replace the relevant baseline risk with a different population.
B. Compare high-dose treatment with no treatment while measuring acid alone (Why this does not fit)
A treatment-versus-control comparison can establish a clinical effect. If both acid and defensive secretion differ, measuring only acid does not isolate the defensive contribution. Unmeasured concurrent effects can still prevent a single-mechanism conclusion.
Reasoning steps for option B
For "Compare high-dose treatment with no treatment while measuring acid alone", what case feature makes this choice seem initially reasonable?
A treatment-versus-control comparison can establish a clinical effect.
Which supplied finding most directly argues against "Compare high-dose treatment with no treatment while measuring acid alone" in this case?
If both acid and defensive secretion differ, measuring only acid does not isolate the defensive contribution.
What clinical discriminator should be carried forward when evaluating "Compare high-dose treatment with no treatment while measuring acid alone"?
Unmeasured concurrent effects can still prevent a single-mechanism conclusion.
C. Compare groups with similar acid control but different defensive effects (Best answer)
Matching acid control reduces one competing explanation for ulcer prevention. A difference in ulcer outcomes could then inform the contribution of the remaining defensive effects, subject to the study design. When two effects change together, an outcome cannot identify their separate contributions by itself.
Reasoning steps for option C
How many relevant effects changed with treatment?
At least two: acid secretion and defensive mucus/bicarbonate production.
Can an improved ulcer outcome by itself allocate their contributions?
No. The effects vary together at the relevant doses.
What comparison would address a competing explanation?
A design with comparable acid control but different defensive effects.
D. Compare only the patients whose symptoms improve after treatment (Why this does not fit)
Symptomatic responders are clinically interesting. Selecting patients after observing response creates a biased subgroup and symptoms are not a direct measure of ulcer prevention. Avoid using a response-defined subgroup to establish an untested causal mechanism.
Reasoning steps for option D
For "Compare only the patients whose symptoms improve after treatment", what case feature makes this choice seem initially reasonable?
Symptomatic responders are clinically interesting.
Which supplied finding most directly argues against "Compare only the patients whose symptoms improve after treatment" in this case?
Selecting patients after observing response creates a biased subgroup and symptoms are not a direct measure of ulcer prevention.
What clinical discriminator should be carried forward when evaluating "Compare only the patients whose symptoms improve after treatment"?
Avoid using a response-defined subgroup to establish an untested causal mechanism.
Takeaway: Observed protection does not establish which simultaneous drug effect caused all of the benefit.
A. About 2 percentage points; better pain relief was not demonstrated (Why this does not fit)
The treated event rate is approximately 2 percent, and the pain statement matches the reported endpoint. Two percent is the residual treated risk, not the difference between the placebo and treated risks. Calculate the absolute reduction by subtracting event proportions rather than reporting the treated proportion.
Reasoning steps for option A
For "About 2 percentage points; better pain relief was not demonstrated", what case feature makes this choice seem initially reasonable?
The treated event rate is approximately 2 percent, and the pain statement matches the reported endpoint.
Which supplied finding most directly argues against "About 2 percentage points; better pain relief was not demonstrated" in this case?
Two percent is the residual treated risk, not the difference between the placebo and treated risks.
What clinical discriminator should be carried forward when evaluating "About 2 percentage points; better pain relief was not demonstrated"?
Calculate the absolute reduction by subtracting event proportions rather than reporting the treated proportion.
B. About 20 percentage points; better pain relief was not demonstrated (Best answer)
The placebo risk is about 21.7 percent and the treated risk is about 2.2 percent. Their difference is approximately 19.6 percentage points, while the separate pain endpoint did not show an established benefit. Counsel about gastric-ulcer prevention without promising gastrointestinal analgesia or assuming the same evidence for duodenal ulcers.
Reasoning steps for option B
What are the two gastric-ulcer risks?
The treated risk is about 2.2 percent and the placebo risk is about 21.7 percent.
What is the absolute reduction?
Subtract the treated risk from the placebo risk: about 19.6 percentage points, rounded to 20.
What can be promised about gastrointestinal pain?
The separate pain assessment did not demonstrate better relief, so the ulcer result is not a promise of analgesia.
C. About 20 percentage points; better pain relief was demonstrated (Why this does not fit)
Subtracting the event proportions gives an absolute reduction close to 20 percentage points. That structural outcome does not establish a symptom benefit, and the supplied pain result does not support the claim. A correct quantitative effect for one outcome does not transfer that effect to another outcome.
Reasoning steps for option C
For "About 20 percentage points; better pain relief was demonstrated", what case feature makes this choice seem initially reasonable?
Subtracting the event proportions gives an absolute reduction close to 20 percentage points.
Which supplied finding most directly argues against "About 20 percentage points; better pain relief was demonstrated" in this case?
That structural outcome does not establish a symptom benefit, and the supplied pain result does not support the claim.
What clinical discriminator should be carried forward when evaluating "About 20 percentage points; better pain relief was demonstrated"?
A correct quantitative effect for one outcome does not transfer that effect to another outcome.
D. About 2 percentage points; better pain relief was demonstrated (Why this does not fit)
The treated group had a gastric-ulcer risk close to 2 percent. This mistakes the treated risk for the absolute reduction and also contradicts the supplied pain assessment. Compute the treatment contrast and interpret each endpoint independently.
Reasoning steps for option D
For "About 2 percentage points; better pain relief was demonstrated", what case feature makes this choice seem initially reasonable?
The treated group had a gastric-ulcer risk close to 2 percent.
Which supplied finding most directly argues against "About 2 percentage points; better pain relief was demonstrated" in this case?
This mistakes the treated risk for the absolute reduction and also contradicts the supplied pain assessment.
What clinical discriminator should be carried forward when evaluating "About 2 percentage points; better pain relief was demonstrated"?
Compute the treatment contrast and interpret each endpoint independently.
Takeaway: Absolute risk reduction compares two proportions; gastric-ulcer prevention and pain relief remain different outcomes.
A. Use the old test, provide counseling, and begin today (Why this does not fit)
A prior negative test offers information about an earlier point in time. Three weeks exceeds the label’s two-week pre-treatment test interval, and the specified cycle timing is not met. A negative pregnancy result is not a permanent clearance for starting therapy.
Reasoning steps for option A
For "Use the old test, provide counseling, and begin today", what case feature makes this choice seem initially reasonable?
A prior negative test offers information about an earlier point in time.
Which supplied finding most directly argues against "Use the old test, provide counseling, and begin today" in this case?
Three weeks exceeds the label’s two-week pre-treatment test interval, and the specified cycle timing is not met.
What clinical discriminator should be carried forward when evaluating "Use the old test, provide counseling, and begin today"?
A negative pregnancy result is not a permanent clearance for starting therapy.
B. Repeat the test and begin today without further counseling (Why this does not fit)
An updated pregnancy test is one required safeguard. It does not replace effective contraception, oral and written warnings or the specified timing within a normal period. A single correct precaution does not satisfy the complete initiation plan.
Reasoning steps for option B
For "Repeat the test and begin today without further counseling", what case feature makes this choice seem initially reasonable?
An updated pregnancy test is one required safeguard.
Which supplied finding most directly argues against "Repeat the test and begin today without further counseling" in this case?
It does not replace effective contraception, oral and written warnings or the specified timing within a normal period.
What clinical discriminator should be carried forward when evaluating "Repeat the test and begin today without further counseling"?
A single correct precaution does not satisfy the complete initiation plan.
C. Wait for the period and rely on the old test without counseling (Why this does not fit)
Menstrual timing is part of the labeled initiation plan. The old test and absent counseling remain unresolved. Cycle timing and testing are complementary safeguards rather than substitutes.
Reasoning steps for option C
For "Wait for the period and rely on the old test without counseling", what case feature makes this choice seem initially reasonable?
Menstrual timing is part of the labeled initiation plan.
Which supplied finding most directly argues against "Wait for the period and rely on the old test without counseling" in this case?
The old test and absent counseling remain unresolved.
What clinical discriminator should be carried forward when evaluating "Wait for the period and rely on the old test without counseling"?
Cycle timing and testing are complementary safeguards rather than substitutes.
D. Update testing and counseling, then use the specified cycle timing (Best answer)
The label requires a negative serum test within two weeks before treatment together with contraceptive capability and oral and written warnings. Starting on the second or third day of the next normal period addresses the remaining timing requirement. Confirm all safeguards and the clinical indication rather than treating one precaution as sufficient.
Reasoning steps for option D
Is the available pregnancy test recent enough for the labeled plan?
No. It was obtained three weeks earlier rather than within two weeks.
What non-test precautions are also required?
Effective contraception capability and oral and written hazard counseling.
What initiation timing does this GI label specify?
The second or third day of the next normal menstrual period.
Takeaway: Pregnancy screening, counseling, contraception and initiation timing address different parts of the risk.
A. Use subcitrate and retain the other regimen components (Best answer)
Bismuth subcitrate does not contain the salicylate moiety of bismuth subsalicylate. It can provide the bismuth component while avoiding the identified aspirin-related formulation concern. Confirm the correct product and dose; different bismuth salts are not automatically interchangeable milligram for milligram.
Reasoning steps for option A
Which part of the current bismuth formulation creates concern?
Its salicylate component.
Does avoiding that component require eliminating all bismuth salts?
Not necessarily; an appropriate subcitrate formulation lacks salicylate.
What else must remain correct?
The full regimen and the specific product’s dose, under prescriber review.
B. Keep subsalicylate but separate it from the antibiotics (Why this does not fit)
Spacing is useful for selected absorption interactions. It does not prevent exposure to the salicylate component that matters in this history. Dose separation does not solve an allergy-related formulation problem.
Reasoning steps for option B
For "Keep subsalicylate but separate it from the antibiotics", what case feature makes this choice seem initially reasonable?
Spacing is useful for selected absorption interactions.
Which supplied finding most directly argues against "Keep subsalicylate but separate it from the antibiotics" in this case?
It does not prevent exposure to the salicylate component that matters in this history.
What clinical discriminator should be carried forward when evaluating "Keep subsalicylate but separate it from the antibiotics"?
Dose separation does not solve an allergy-related formulation problem.
C. Omit bismuth and retain the three remaining components (Why this does not fit)
Avoiding the offending product addresses one safety concern. Simply deleting a component changes the optimized regimen rather than selecting a complete validated alternative. Replace the formulation appropriately or choose another complete evidence-based regimen.
Reasoning steps for option C
For "Omit bismuth and retain the three remaining components", what case feature makes this choice seem initially reasonable?
Avoiding the offending product addresses one safety concern.
Which supplied finding most directly argues against "Omit bismuth and retain the three remaining components" in this case?
Simply deleting a component changes the optimized regimen rather than selecting a complete validated alternative.
What clinical discriminator should be carried forward when evaluating "Omit bismuth and retain the three remaining components"?
Replace the formulation appropriately or choose another complete evidence-based regimen.
D. Replace bismuth with sucralfate and retain the antibiotics (Why this does not fit)
Sucralfate offers local mucosal protection. It is not an interchangeable antimicrobial component of optimized bismuth quadruple therapy. Similar protective effects do not make two drugs equivalent within an eradication regimen.
Reasoning steps for option D
For "Replace bismuth with sucralfate and retain the antibiotics", what case feature makes this choice seem initially reasonable?
Sucralfate offers local mucosal protection.
Which supplied finding most directly argues against "Replace bismuth with sucralfate and retain the antibiotics" in this case?
It is not an interchangeable antimicrobial component of optimized bismuth quadruple therapy.
What clinical discriminator should be carried forward when evaluating "Replace bismuth with sucralfate and retain the antibiotics"?
Similar protective effects do not make two drugs equivalent within an eradication regimen.
Takeaway: Select the salt deliberately and preserve a complete treatment regimen.