Connect meal-related pain and colonic low-flow injury to vascular anatomy, safe testing, severity assessment, revascularization and surgical escalation.
Does this patient need restored arterial inflow, careful assessment of injured colon, or urgent evaluation of bowel viability? Follow the timing, vascular territory and depth of injury to choose safely. The lesson builds those decisions before asking you to apply them to new cases.
First identify what changed: demand, supply or injury
Why does one patient avoid meals while another suddenly passes blood? A 71-year-old with peripheral arterial disease has pain after lunch for three months and now eats half portions. Another patient develops cramps and urgency after perioperative hypotension, then passes maroon stool that evening. Both may have inadequate intestinal perfusion, but their timing asks different questions.
Chronic mesenteric ischemia usually reflects insufficient arterial reserve during digestion. Pain often begins within about 10 to 30 minutes after a meal and lasts one to two hours. Eating less reduces the trigger but can cause substantial weight loss. Diarrhea and nausea can occur. The complete combination of postprandial pain, weight loss and an abdominal bruit is not required; a patient can remain overweight despite important recent weight loss. Atherosclerosis is the usual substrate, supported by smoking, diabetes or disease in other arterial beds. [1][3]
Compare timing before naming a vascular syndrome
Pattern
What needs explaining?
Priority
PatternRecurrent pain after meals over weeks or months
What needs explaining?Demand exceeds available arterial reserve
PriorityPrompt arterial evaluation
PatternAcute cramps, urgency, then rectal blood
What needs explaining?Colonic mucosal injury, often after reduced perfusion
PriorityAssess distribution and severity
PatternNew sustained severe pain, with or without blood
What needs explaining?Possible acute mesenteric ischemia or deeper injury
PriorityEmergency evaluation, not routine follow-up
Try the distinction: identify which patient's symptoms depend on eating, then identify the patient with a sudden perfusion disturbance. The first pattern suggests chronic mesenteric ischemia; the second suggests colonic ischemia. Neither pattern alone proves the diagnosis.
Typical ischemic colitis begins with acute crampy abdominal pain and an urge to defecate; hematochezia or bloody diarrhea often follows within 24 hours. A low-flow episode may be brief or undocumented. Diverticular bleeding is more often painless, while infection and inflammatory bowel disease can also cause painful bloody diarrhea. Chronic pancreatitis and peptic disease also enter the differential for recurrent meal-related pain. Medication, infectious exposure, radiation and prior bowel history help distinguish competing causes. CT distribution and, when safe, endoscopy provide additional evidence. [2]
Transfer: when the first patient's pain becomes continuous overnight, do not keep the old chronic label as a safety guarantee. Acute thrombosis can develop on a chronically narrowed artery. Severe pain may precede guarding because injury begins at the mucosa before reaching the outer bowel surface. [4]
A meal tests the reserve of a collateral network
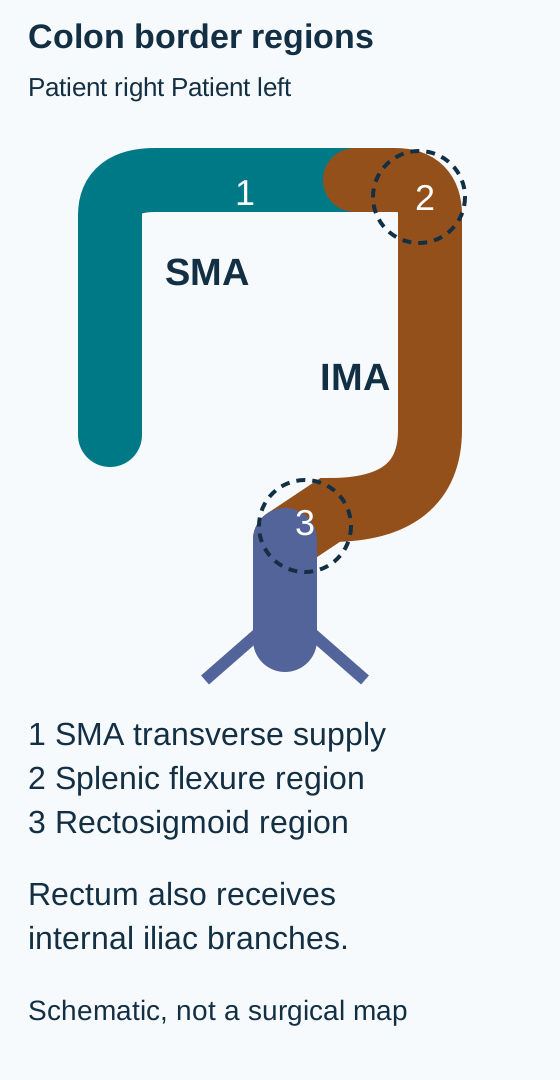
Does a narrowed vessel necessarily mean symptomatic ischemia? No. The celiac artery supplies foregut structures; the superior mesenteric artery, or SMA, supplies most small bowel and the right and proximal transverse colon. The inferior mesenteric artery, or IMA, supplies the distal transverse and left colon, sigmoid and superior rectal territory. Pancreaticoduodenal connections link celiac and SMA flow, while the marginal artery links colonic branches. These alternate routes can preserve resting perfusion. [3]
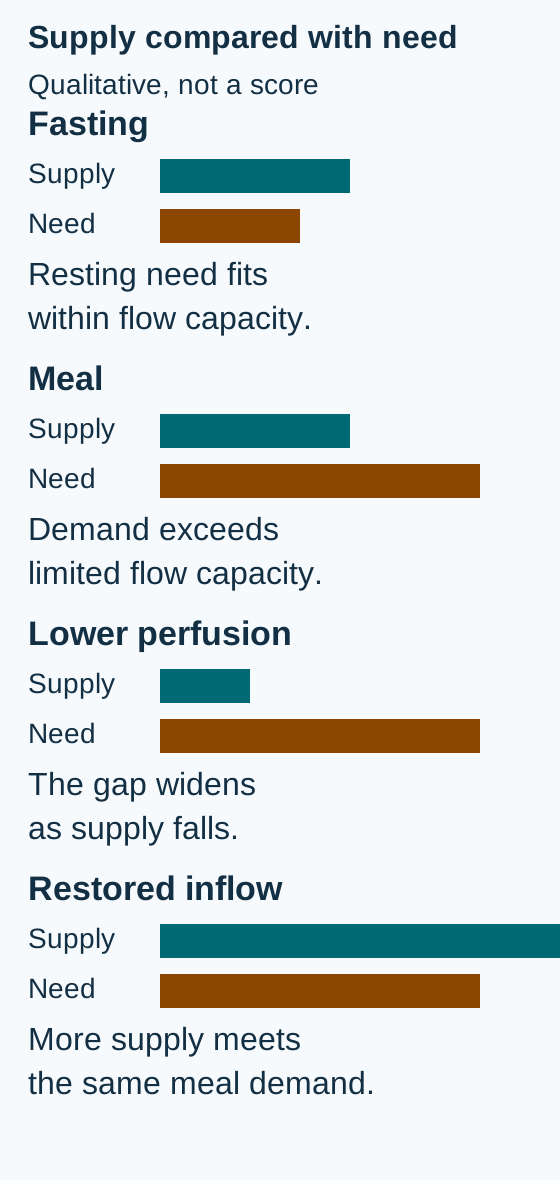
With a fixed inflow limitation, blood delivery may meet fasting needs but fail to rise sufficiently during digestion. The useful relationship is available supply compared with current demand, not a vessel count alone. Symptoms and significant mesenteric arterial disease must fit together. Multivessel disease makes the vascular explanation more likely, but carefully evaluated single-vessel SMA or celiac disease can also be symptomatic. An incidental stenosis in someone eating normally without symptoms does not establish chronic mesenteric ischemia. [1][3]
Compare the length of need with supply, not the color alone. Bar lengths illustrate relationships, not measured flow or a clinical threshold. [1][3]
Change one part of the relationship
Start with the fasting figure. Predict whether each change enlarges or reduces the supply deficit, then compare the labeled supply and demand bars in the figures. Open a response to check your explanation; closing it hides only that response. Every comparison figure remains visible. These are qualitative drawings, not measured perfusion or a patient risk calculator.
Starting state: resting demand fits within available supply.Add a meal without changing inflow
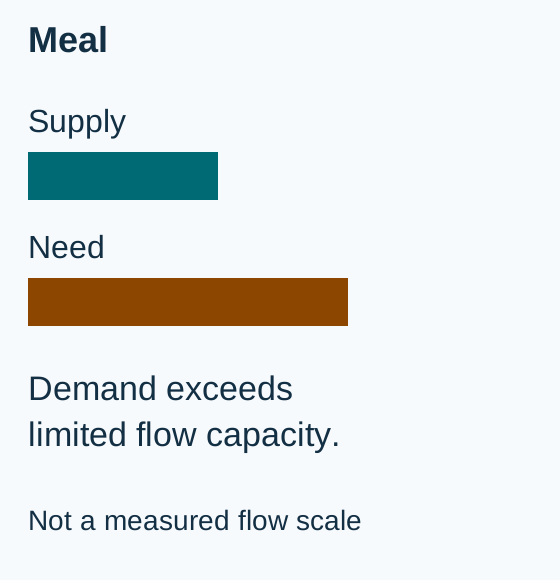
Demand increases while limited supply stays the same. The new deficit explains meal-triggered pain.
Compare with fasting: meal demand increases while limited supply stays the same. Bar lengths illustrate relationships, not measured flow or a clinical threshold. [1][3]Lower perfusion during the same meal
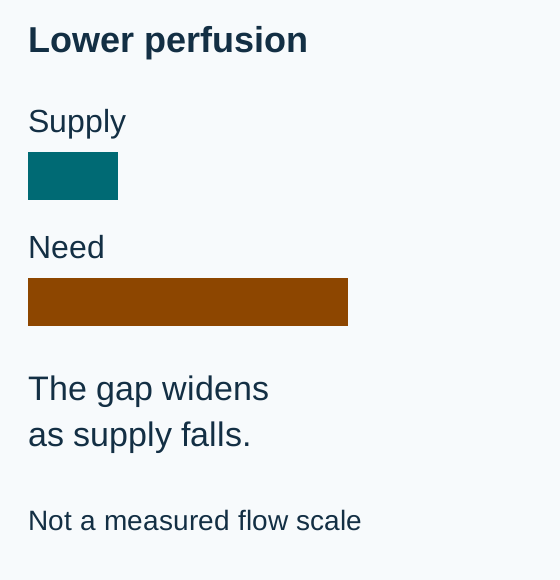
A fall in perfusion worsens the deficit even without a new visible arterial clot.
Compare with the meal state: supply falls while digestive demand is unchanged. Bar lengths illustrate relationships, not measured flow or a clinical threshold. [3][4]Restore inflow during the same meal
More arterial supply can meet the same digestive demand. This addresses the cause rather than perpetuating food avoidance.
Compare with the meal state: restored supply meets the same digestive demand. Bar lengths illustrate relationships, not measured flow or a clinical threshold. [1][3]
The complete four-state comparison above remains readable whether or not any exercise is opened. Reduced meal size may lessen pain, but it does not repair an artery. Conversely, a fall in systemic perfusion can threaten bowel despite patent major vessels. Transfer: explain why a patient on dialysis may develop ischemic pain after hypotension even when imaging shows no new large-vessel occlusion. [3][4]
Locate vulnerable colon without assuming one artery is blocked
Why can low perfusion injure one segment while sparing the rectum? Border regions have less dependable collateral reserve. The splenic flexure lies near the SMA and IMA interface, often called Griffith's point. The rectosigmoid region includes the junction between the last sigmoid supply and superior rectal supply, often called Sudeck's point. These are vulnerable regions, not universal sharply fixed lines. The rectum also receives middle and inferior rectal contributions from the internal iliac circulation and is usually relatively spared. [2][3]
Trace each supply territory. The splenic flexure is vulnerable near the SMA and IMA interface; the rectosigmoid has a last-sigmoid to superior-rectal junction. Pelvic vessels help protect the rectum. [2][3]
Trace before reading onward: follow the right-colon supply to the SMA, then follow the descending colon toward the IMA. A poorly perfused left-sided segment with rectal sparing fits colonic ischemia, but the pattern is supportive rather than diagnostic by itself. Inflammatory and infectious disease still require consideration.
Most colonic ischemia is not caused by an embolus visibly blocking a major artery. Reduced flow, vasoconstriction and vulnerable smaller vessels can injure the mucosa. Isolated right-colon ischemia is particularly concerning: it has a worse prognosis and can be an early manifestation of a broader SMA problem. A patient with right-sided pain and little bleeding therefore needs more urgent assessment, not reassurance from the absence of blood. [2][4]
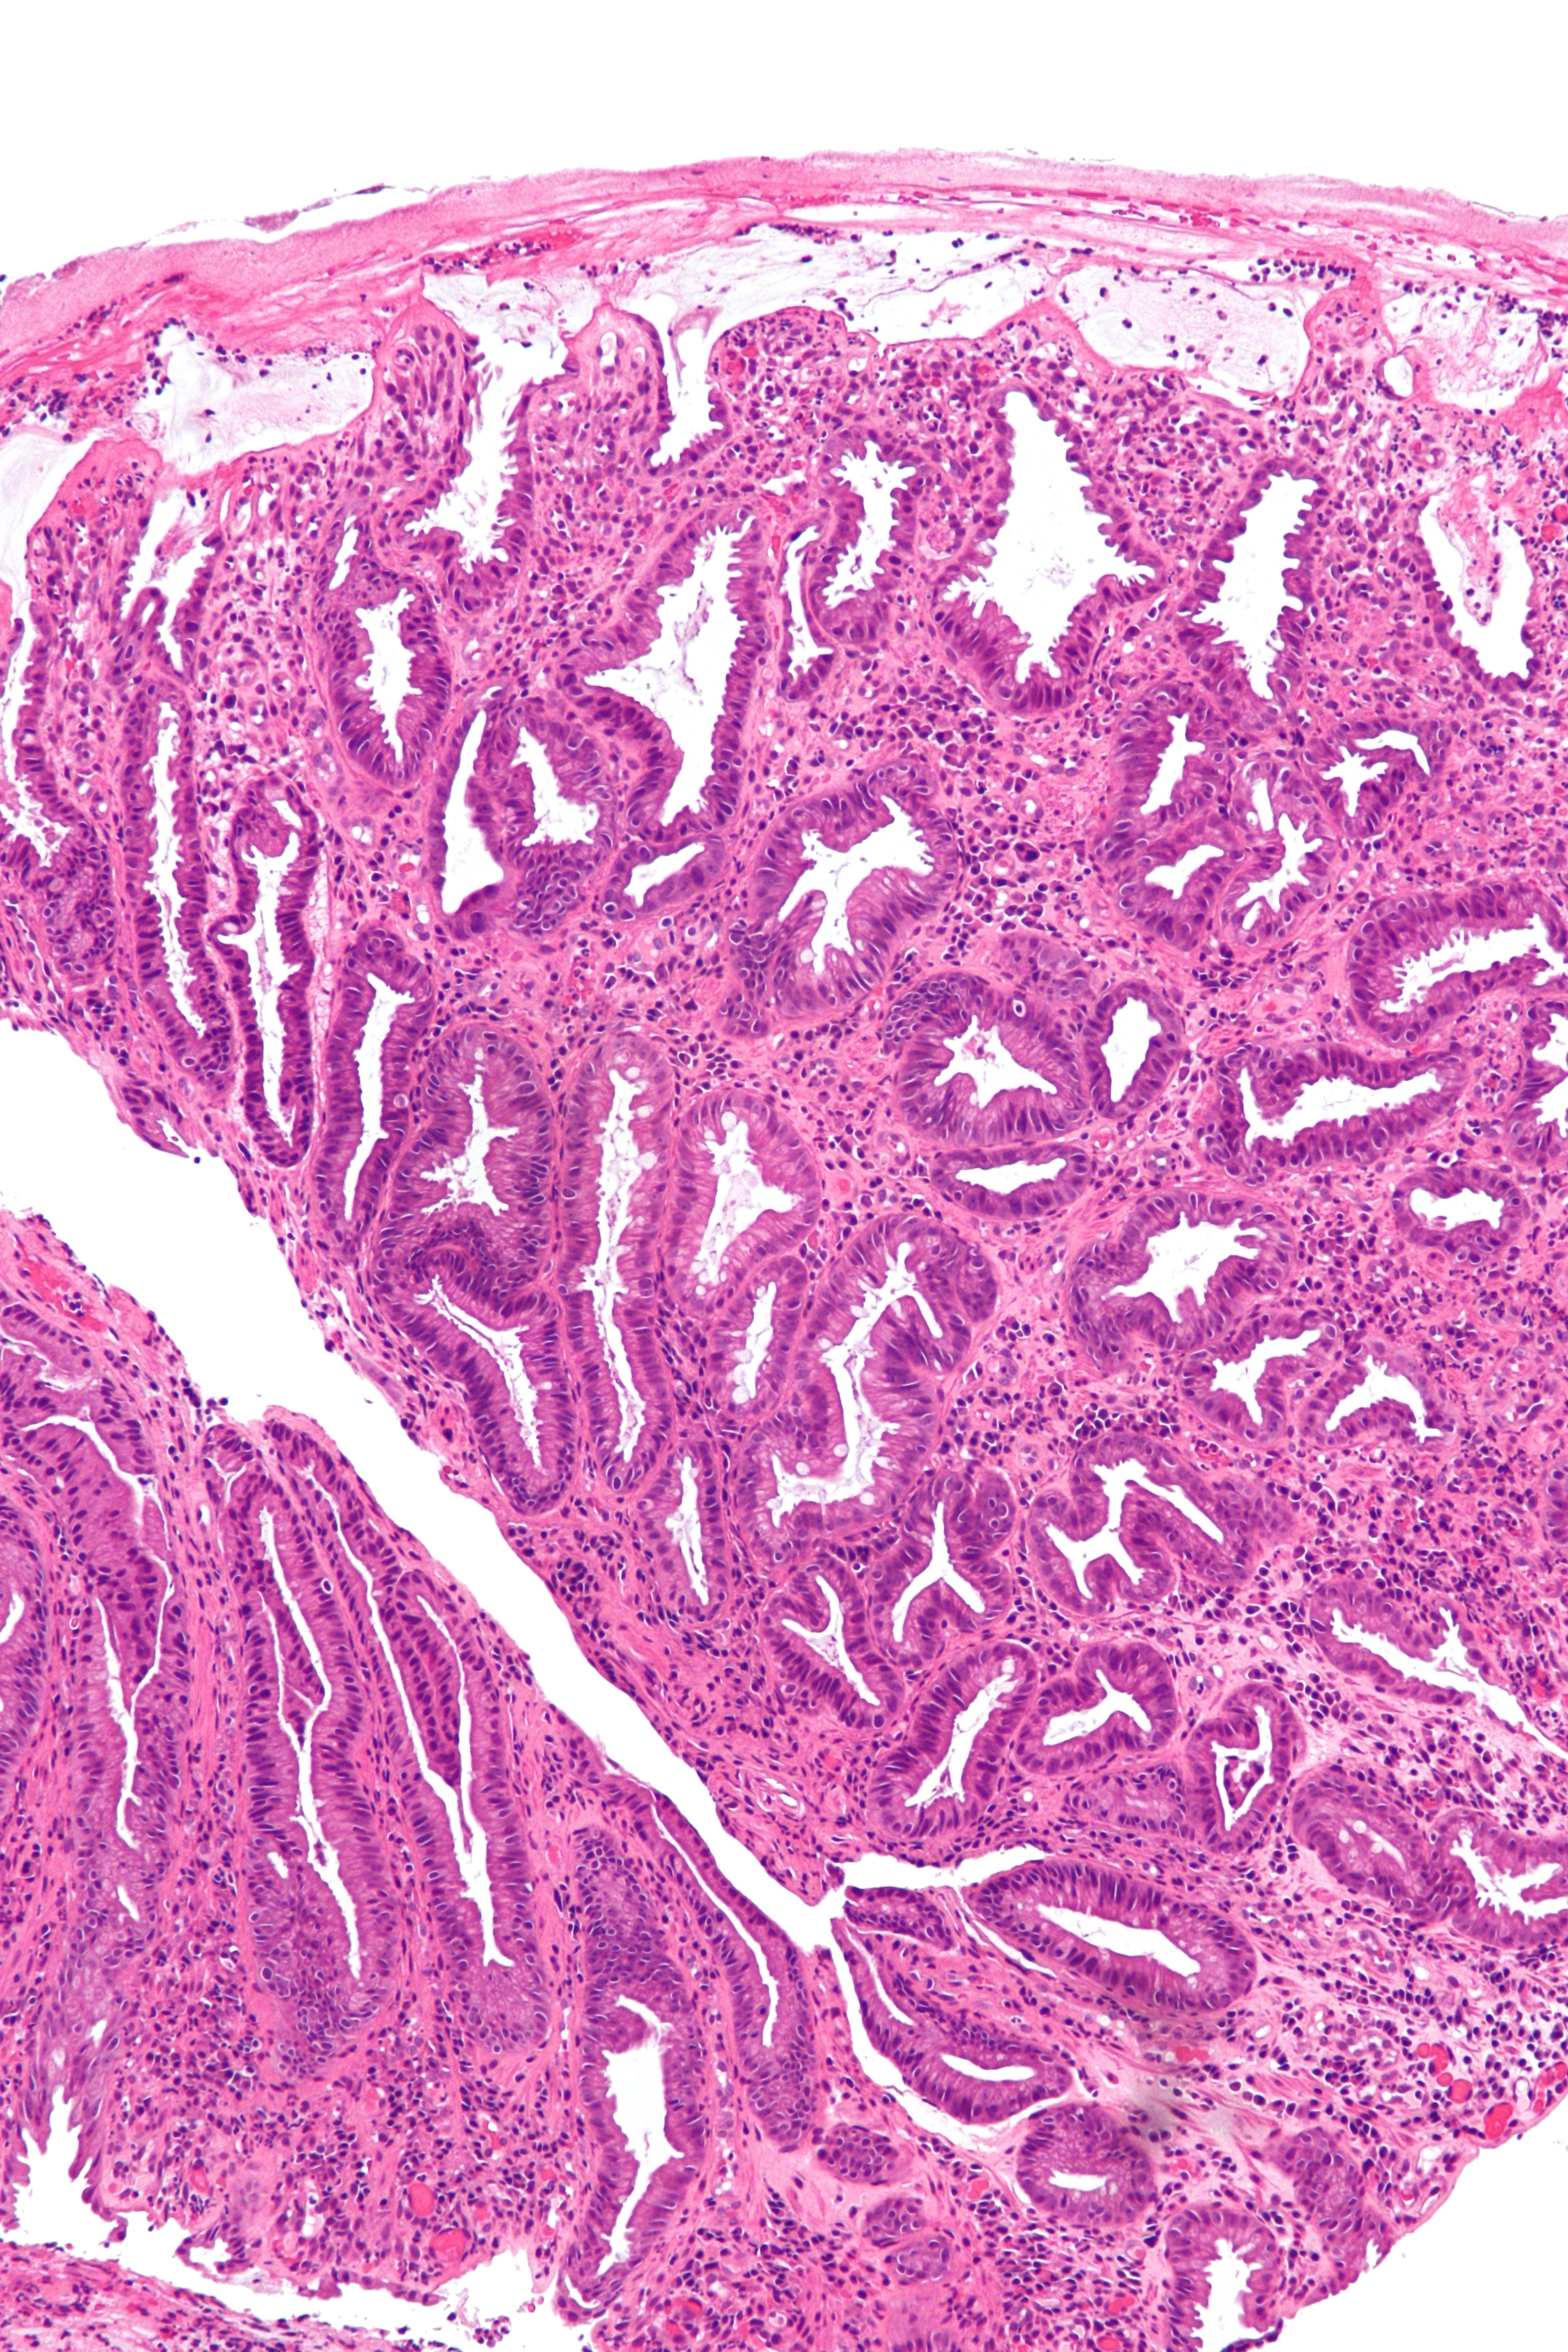
Historical clinical example of ischemic colonic injury. Compare surface and crypt architecture rather than expecting a vessel clot in this field. The image alone does not determine the vascular cause or full-wall viability. Image: Nephron, 2012; original source, CC BY-SA 3.0. [5].
Image task: locate the luminal surface, then compare the injured superficial tissue with the deeper crypt profiles. The clinically useful consequence is that mucosa can be injured before the entire wall is infarcted. Histology must be interpreted with timing, distribution, imaging and examination; a small biopsy cannot certify the rest of the bowel as viable. [2][4]
Transfer: a patient after aortic surgery has bloody diarrhea with rectal sparing. Consider compromised colonic perfusion after changes to IMA or collateral supply, rather than assuming pelvic supply makes the whole colon safe. Review the operation and hemodynamics while evaluating other causes. [2]
Ask the right question before choosing the test
Do you need an arterial map, mucosal confirmation, or an assessment for infarction? In a stable patient with suspected chronic mesenteric ischemia, CTA defines arterial stenoses, collateral anatomy and alternative abdominal disease. Contrast-enhanced MR angiography is an alternative when CTA is unsuitable, with renal function and the contrast agent assessed individually. Experienced duplex ultrasound can screen proximal arteries, but gas, body habitus and operator limitations can make it nondiagnostic. A report that the SMA was not visualized is not a normal SMA. [1][3]
For suspected colonic ischemia, contrast-enhanced CT evaluates distribution and complications. Wall thickening, submucosal edema and thumbprinting support an injured colon but are nonspecific. Multiphasic CTA is indicated when isolated right-colon ischemia is suspected or acute mesenteric ischemia cannot be excluded. An ordinary portal-venous-phase CT does not necessarily answer that arterial question. [2]
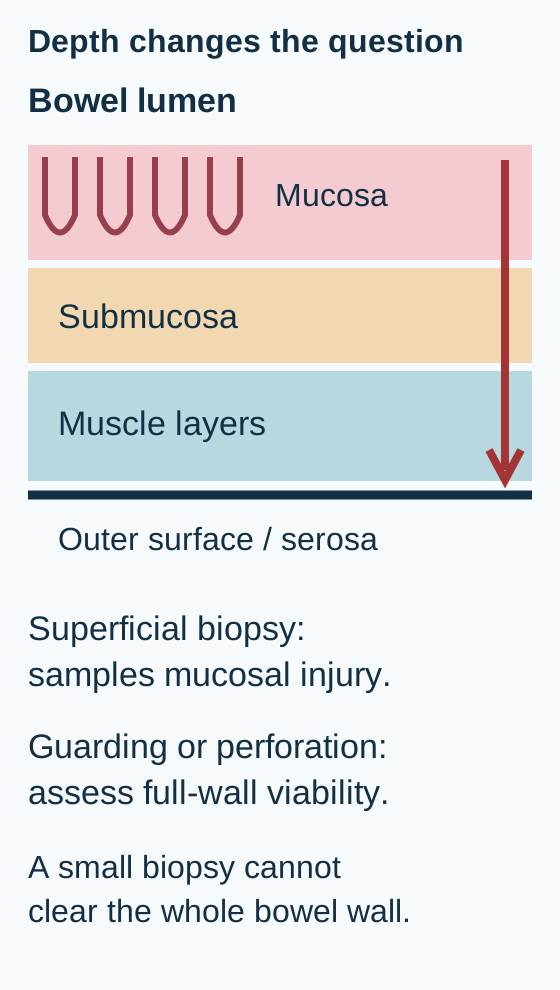
Connect the sampled layer to the question it can answer. Endoscopy can support mucosal ischemia; peritoneal deterioration requires assessment beyond the mucosa. [2][4]
When there is no peritonitis or evidence of irreversible ischemic injury, early colonoscopy, usually within 48 hours, can support the diagnosis. Use minimal insufflation; in severe disease being assessed endoscopically, CT guides a limited examination and the scope should not be advanced through the injured segment to complete the colon. Obtain biopsies unless gangrene is present. A routine full examination with forceful distension is not the goal. [2]
Choose the question: after a stable patient has CT-demonstrated left-sided colitis without ominous features, mucosal confirmation may help. Change the same patient to one with guarding and worsening acidosis, and the question becomes bowel viability. Colonoscopy must not delay surgical assessment in that second situation.
No blood test safely excludes early acute mesenteric ischemia. A normal lactate can coexist with threatened bowel; a high lactate can also result from dehydration or other shock states. In a clinically concerning acute presentation, perform CTA without delay, including when acute kidney injury is present. The danger of missing ischemic bowel can exceed the contrast risk. Do not wait for oral contrast, a repeat lactate or a chronic outpatient MR pathway. Resuscitation and specialist contact proceed in parallel. [4]
Gas in the bowel wall is called pneumatosis. Portal or mesenteric venous gas adds concern. In a deteriorating patient with absent bowel enhancement, acidosis or peritoneal signs, these findings strongly support advanced injury. Pneumatosis alone has other causes and is not an automatic instruction to resect all affected bowel. Nevertheless, in suspected colonic ischemia it is a high-risk finding requiring urgent assessment, not routine colonoscopy. [2][4]
Transfer: a critically ill patient has worsening abdominal findings despite patent large arteries on CTA. Nonocclusive mesenteric ischemia remains possible because impaired perfusion need not produce a proximal arterial filling defect. Reassess perfusion, bowel findings and the need for urgent specialist intervention. [4]
Grade severity using the patient, not the volume of blood
Which patient is more concerning: one passing blood with stable perfusion, or one with little blood but persistent hypotension? Bleeding reflects mucosal injury and does not measure the remaining viable bowel. Right-sided disease, systemic deterioration and peritoneal findings can indicate severe illness with little hematochezia. Serial vital signs, abdominal examination, urine output and laboratory trends matter. [2]
The ACG framework separates mild, moderate and severe colonic ischemia. It is a guideline framework, not a validated weighted probability calculator. Do not assign invented points to symptoms or convert a total into a percentage risk. [2]
ACG severity categories used with clinical judgment
Category
Features
Care direction
CategoryMild
FeaturesTypical segmental disease, not isolated right colon, without the listed poor-outcome factors
Care directionSupportive care and observation
CategoryModerate
FeaturesOne to three listed factors, without a severe feature
Care directionCorrect perfusion, consider antibiotics, obtain surgical consultation
CategorySevere
FeaturesMore than three factors, or any severe feature
Care directionUrgent surgical assessment and intensive monitoring or critical care as needed
Listed factors are male sex; systolic pressure below 90 mmHg; pulse above 100/min; pain without rectal bleeding; BUN above 20 mg/dL; hemoglobin below 12 g/dL; LDH above 350 U/L; sodium below 136 mmol/L; white-cell count above 15,000/microliter; and mucosal ulceration. Do not assume an unmeasured factor is absent. Severe features override the count: peritoneal signs, pneumatosis or portal venous gas, endoscopic gangrene, pancolonic disease, or isolated right-colon involvement. [2]
Apply the boundary: a woman with left-sided colitis has BUN 26, sodium 133, rectal bleeding, pulse 88 and no other listed factor or severe feature. The two factors support moderate disease. Now change only the distribution to isolated right colon. The severe classification follows from the territory even though the factor count stays two.
These categories guide escalation, not an automatic operation for every person in the severe category. A patient with peritonitis, gangrene, perforation or progressive systemic deterioration may need urgent exploration and resection of nonviable bowel. A patient with a high-risk distribution but no established necrosis still needs urgent surgical and vascular evaluation, including the appropriate imaging, rather than a predetermined colectomy. [2][4]
Transfer: falling blood pressure and urine output after an initially reassuring CT should change the plan. A previous mild designation is not a durable property of the patient. Reassess the trajectory and search for deeper or more extensive ischemia. [2][4]
Treat the threatened tissue and the reason flow failed
Why is bowel rest reasonable for one patient but inadequate as the definitive plan for another? In uncomplicated mild colonic ischemia, reduce immediate bowel demand, provide intravenous fluids as needed, correct the precipitating low-flow state and reassess frequently. Review vasoconstrictive, constipating and other potentially contributory drugs. Do not start therapeutic anticoagulation merely because the word ischemia appears; an embolic, thrombotic or separate anticoagulation indication must be evaluated. [2]
For moderate or severe colonic ischemia, consider broad-spectrum antibiotics and involve surgery early. The antimicrobial recommendation rests on very low-quality evidence; it does not establish a mortality benefit for every mild episode. Regimen, duration and adjustments depend on severity, organ function, local practice and clinical response. Suspected gangrene, perforation, peritonitis or persistent deterioration requires urgent source-control assessment rather than waiting for antibiotics to rescue nonviable bowel. [2][4]
Perfused enough to recover: supportive care reduces stress while perfusion recovers.
Possible nonviable bowel: urgently assess for exploration and removal of dead tissue while resuscitating.
Match treatment to cause: compare a recovering transient hypotension-related colitis episode with months of food avoidance and significant SMA disease. Supportive observation can fit the first; starvation or repeated bowel rest cannot be the definitive solution for the second.
Symptomatic atherosclerotic chronic mesenteric ischemia usually requires revascularization. The SMA is the principal target. Endovascular treatment is generally the initial approach when anatomy is suitable; open reconstruction is selected for circumstances such as unsuitable anatomy, failed endovascular treatment or patients in whom durability considerations favor it. Decisions belong with a vascular team and account for procedural risk, anatomy and preferences, not age alone. Add cardiovascular secondary prevention, including smoking cessation, lipid management and appropriate antiplatelet treatment. [1][3]
Malnutrition deserves attention, but attempts to force oral intake, start feeding solely to gain weight, or postpone revascularization for nutritional improvement can worsen demand-related ischemia. Restore circulation promptly and coordinate nutrition around that plan. The European recommendation explicitly acknowledges limited supporting evidence; it is not permission to neglect nutrition after perfusion is addressed. [3]
After revascularization, arrange clinical and vascular surveillance. Recurrent meal-related symptoms require evaluation for restenosis and other causes. After colonic ischemia, persistent pain, recurrent sepsis or later obstructive symptoms require follow-up; ischemic healing can leave a symptomatic stricture. Young patients or those with recurrent unexplained colonic ischemia may need evaluation for thrombophilia or other unusual causes rather than automatic attribution to age-related atherosclerosis. [1][2]
Final transfer: state the unresolved problem in one sentence: inadequate chronic inflow, potentially reversible colonic injury, or threatened bowel viability. Then identify the evidence that could change that assessment. This keeps a diagnosis from becoming a reason to stop reassessing.
Apply the decisions to new patients
Case 1
Show answer and explanations for case 1
A. Portal venous pressure rises because of impaired hepatic drainage (Why this does not fit)
Impaired hepatic drainage would raise venous pressure and cause portal congestion, an outflow problem rather than reduced arterial inflow. CTA shows ostial arterial stenoses, not hepatic outflow obstruction. Pain provoked by larger meals therefore fits limited digestive perfusion reserve better than portal hypertension.
Reasoning steps for option A
Where would impaired hepatic drainage raise pressure in this patient?
Impaired hepatic drainage would raise venous pressure and cause portal congestion, an outflow problem rather than reduced arterial inflow.
Do the SMA and celiac lesions explain meal-size dependence through portal congestion?
CTA shows ostial arterial stenoses, not hepatic outflow obstruction. Pain provoked by larger meals therefore fits limited digestive perfusion reserve better than portal hypertension.
B. A transient embolus blocks the SMA after each meal (Why this does not fit)
An embolus produces a new arterial obstruction. It does not normally appear and disappear according to whether the patient eats a snack or a full meal. The same meal-size challenge repeatedly provokes pain in a circulation with two fixed ostial stenoses. Increased demand on limited reserve explains that pattern without requiring a new embolus after each meal.
Reasoning steps for option B
Would an SMA embolus produce a new interruption of supply or a repeatable response to meal size?
An embolus produces a new arterial obstruction. It does not normally appear and disappear according to whether the patient eats a snack or a full meal.
How do reproducible postprandial episodes distinguish fixed stenosis from repeated embolization?
The same meal-size challenge repeatedly provokes pain in a circulation with two fixed ostial stenoses. Increased demand on limited reserve explains that pattern without requiring a new embolus after each meal.
C. Digestive demand exceeds the available increase in arterial supply (Best answer)
A larger meal increases digestive demand and the blood flow needed to support it, explaining why normal meals stress the circulation more than small snacks. Collateral vessels may maintain resting flow while the two stenoses restrict the additional arterial supply available during digestion. Normal-meal demand then exceeds that reserve.
Reasoning steps for option C
How does replacing a snack with a normal meal change intestinal demand?
A larger meal increases digestive demand and the blood flow needed to support it, explaining why normal meals stress the circulation more than small snacks.
Why does collateral filling not guarantee painless meals with severe SMA and celiac stenoses?
Collateral vessels may maintain resting flow while the two stenoses restrict the additional arterial supply available during digestion. Normal-meal demand then exceeds that reserve.
D. Colonic mucosal inflammation increases despite preserved perfusion reserve (Why this does not fit)
An inflammatory bowel disorder can cause discomfort associated with eating, so meal-associated pain alone does not identify an arterial cause. The severe SMA and celiac stenoses provide a demonstrated inflow limitation, and symptom intensity follows meal size. Together they favor a supply-demand deficit over inflammation with intact reserve.
Reasoning steps for option D
Which part of this presentation could also occur with colonic inflammation?
An inflammatory bowel disorder can cause discomfort associated with eating, so meal-associated pain alone does not identify an arterial cause.
What contradicts the assumption of preserved perfusion reserve in the inflammation option?
The severe SMA and celiac stenoses provide a demonstrated inflow limitation, and symptom intensity follows meal size. Together they favor a supply-demand deficit over inflammation with intact reserve.
Takeaway: Compare digestive demand with available arterial reserve.
A. Correlate the SMA lesion with symptoms despite the other patent vessels (Best answer)
Four months of postprandial pain, smaller portions and an 8-kg weight loss form a compatible demand-related syndrome; the evaluated gastrointestinal alternatives do not explain it. Those vessels may provide compensation, but significant single-vessel SMA disease can still be symptomatic. Clinical correlation remains necessary rather than automatically excluding ischemia or proceeding directly to intervention.
Reasoning steps for option A
Which findings make the isolated 85% SMA stenosis clinically relevant?
Four months of postprandial pain, smaller portions and an 8-kg weight loss form a compatible demand-related syndrome; the evaluated gastrointestinal alternatives do not explain it.
What does patency of the celiac artery and IMA change about the need for correlation?
Those vessels may provide compensation, but significant single-vessel SMA disease can still be symptomatic. Clinical correlation remains necessary rather than automatically excluding ischemia or proceeding directly to intervention.
B. Exclude a vascular cause because the celiac artery and IMA remain patent (Why this does not fit)
The celiac artery and IMA can contribute collateral flow around an SMA stenosis, potentially maintaining intestinal perfusion. No. Patent alternative vessels do not prove that collateral reserve meets digestive demand. The compatible symptoms and severe SMA lesion still require assessment as a vascular explanation.
Reasoning steps for option B
What compensatory role could the two patent mesenteric arteries provide?
The celiac artery and IMA can contribute collateral flow around an SMA stenosis, potentially maintaining intestinal perfusion.
Does that potential compensation exclude ischemia in a patient losing weight from meal pain?
No. Patent alternative vessels do not prove that collateral reserve meets digestive demand. The compatible symptoms and severe SMA lesion still require assessment as a vascular explanation.
C. Diagnose acute bowel infarction from the measured degree of SMA narrowing (Why this does not fit)
It measures arterial narrowing, not the depth or reversibility of injury in the bowel wall. Significant stenosis is not itself proof of infarction. The history describes four months of meal-triggered symptoms without a supplied abrupt deterioration, peritoneal findings or imaging evidence of dead bowel. Those data support evaluation of chronic ischemia rather than a diagnosis of acute infarction.
Reasoning steps for option C
What does the reported 85% stenosis measure, and what does it not measure?
It measures arterial narrowing, not the depth or reversibility of injury in the bowel wall. Significant stenosis is not itself proof of infarction.
Which supplied features argue against labeling this chronic presentation acute infarction?
The history describes four months of meal-triggered symptoms without a supplied abrupt deterioration, peritoneal findings or imaging evidence of dead bowel. Those data support evaluation of chronic ischemia rather than a diagnosis of acute infarction.
D. Classify the SMA lesion as incidental because collateral vessels remain open (Why this does not fit)
An incidental stenosis would lack a compatible symptomatic syndrome. This patient has meal-related pain, food avoidance and weight loss despite evaluation of alternative causes. An open collateral route does not measure its capacity to meet postprandial demand. The artery and symptom pattern must be correlated before the stenosis is labeled incidental.
Reasoning steps for option D
How would an incidental mesenteric stenosis differ clinically from this SMA finding?
An incidental stenosis would lack a compatible symptomatic syndrome. This patient has meal-related pain, food avoidance and weight loss despite evaluation of alternative causes.
Why is visible collateral patency insufficient to dismiss the SMA lesion?
An open collateral route does not measure its capacity to meet postprandial demand. The artery and symptom pattern must be correlated before the stenosis is labeled incidental.
Takeaway: A single significant SMA lesion can be symptomatic; establish the clinical fit.
A. Arrange celiac stenting before symptoms have an opportunity to develop (Why this does not fit)
Compatible ischemic symptoms or a relevant high-risk abdominal operation can change the significance of mesenteric arterial disease and its treatment assessment. They do not establish symptomatic ischemia or an operative circumstance warranting intervention. A 75% isolated celiac stenosis alone does not justify applying a symptomatic revascularization strategy.
Reasoning steps for option A
What clinical or operative circumstance would make a mesenteric stenosis more than an incidental finding?
Compatible ischemic symptoms or a relevant high-risk abdominal operation can change the significance of mesenteric arterial disease and its treatment assessment.
Do her normal meals, stable weight and absence of a planned operation justify prophylactic celiac stenting?
They do not establish symptomatic ischemia or an operative circumstance warranting intervention. A 75% isolated celiac stenosis alone does not justify applying a symptomatic revascularization strategy.
B. Start therapeutic anticoagulation to dissolve the ostial narrowing (Why this does not fit)
Anticoagulation addresses appropriate thromboembolic indications; it does not dissolve the atherosclerotic plaque responsible for a stable ostial stenosis. No acute thrombus or ischemic syndrome is supplied. The relevant response is assessment of atherosclerotic risk, not anticoagulation intended to dissolve the narrowing.
Reasoning steps for option B
Would therapeutic anticoagulation repair plaque-related celiac narrowing?
Anticoagulation addresses appropriate thromboembolic indications; it does not dissolve the atherosclerotic plaque responsible for a stable ostial stenosis.
What evidence of acute thromboembolism is supplied by this incidental renal-cyst scan?
No acute thrombus or ischemic syndrome is supplied. The relevant response is assessment of atherosclerotic risk, not anticoagulation intended to dissolve the narrowing.
C. Restrict meal size indefinitely to prevent intestinal infarction (Why this does not fit)
Smaller meals can reduce digestive demand and temporarily lessen postprandial pain when arterial reserve is insufficient. There is no meal-triggered pain to relieve, and her weight is stable. Restriction adds nutritional risk without repairing the incidental stenosis or establishing protection against infarction.
Reasoning steps for option C
What symptom might smaller meals relieve in genuine demand-related mesenteric ischemia?
Smaller meals can reduce digestive demand and temporarily lessen postprandial pain when arterial reserve is insufficient.
Why does indefinite restriction not fit this woman with painless normal portions?
There is no meal-triggered pain to relieve, and her weight is stable. Restriction adds nutritional risk without repairing the incidental stenosis or establishing protection against infarction.
D. Address cardiovascular risk and arrange individualized vascular follow-up (Best answer)
It can signal systemic cardiovascular risk that deserves attention, although the intestinal lesion is currently asymptomatic. They argue against revascularization based only on the celiac stenosis percentage. Address cardiovascular risk and tailor vascular follow-up to her circumstances rather than imposing an unnecessary procedure or food restriction.
Reasoning steps for option D
What does incidental celiac atherosclerosis reveal even without an intestinal symptom syndrome?
It can signal systemic cardiovascular risk that deserves attention, although the intestinal lesion is currently asymptomatic.
How do normal intake and patent SMA and IMA shape the vascular plan?
They argue against revascularization based only on the celiac stenosis percentage. Address cardiovascular risk and tailor vascular follow-up to her circumstances rather than imposing an unnecessary procedure or food restriction.
Takeaway: Treat the patient and vascular risk, not the stenosis percentage in isolation.
A. Repeat an unenhanced abdominal CT to assess the arterial lumen (Why this does not fit)
It can show calcification and some alternative abdominal abnormalities, but it does not reliably define the mesenteric arterial lumen. The unresolved question is whether a significant SMA stenosis limits inflow. Seeing calcification without diagnostic luminal imaging would not answer that question.
Reasoning steps for option A
What arterial information could unenhanced CT provide after the nondiagnostic duplex?
It can show calcification and some alternative abdominal abnormalities, but it does not reliably define the mesenteric arterial lumen.
Why would another unenhanced scan leave the food-avoidance workup incomplete?
The unresolved question is whether a significant SMA stenosis limits inflow. Seeing calcification without diagnostic luminal imaging would not answer that question.
B. Contrast-enhanced MR angiography of the mesenteric vessels (Best answer)
She is stable, has normal renal function and no MR contraindication; prior anaphylaxis to iodinated contrast makes CTA unsuitable in this chronic evaluation. CE-MRA can define mesenteric arterial stenosis and resolve the unassessed SMA lumen. It supplies an arterial study rather than treating technical nonvisualization as a negative result.
Reasoning steps for option B
Which combination makes contrast-enhanced MR angiography feasible for this patient?
She is stable, has normal renal function and no MR contraindication; prior anaphylaxis to iodinated contrast makes CTA unsuitable in this chronic evaluation.
What can CE-MRA establish that the gas-obscured duplex could not?
CE-MRA can define mesenteric arterial stenosis and resolve the unassessed SMA lumen. It supplies an arterial study rather than treating technical nonvisualization as a negative result.
C. Accept the duplex report as excluding significant SMA disease (Why this does not fit)
It tells you that the examination did not assess that artery adequately. It does not demonstrate either a normal lumen or absence of significant disease. The compatible symptoms remain unexplained because bowel gas prevented SMA assessment. A negative interpretation requires adequate visualization, so this report cannot close the vascular workup.
Reasoning steps for option C
What does an SMA that was not visualized on duplex tell you about stenosis?
It tells you that the examination did not assess that artery adequately. It does not demonstrate either a normal lumen or absence of significant disease.
Why should the continuing meal pain and food avoidance prompt another arterial study?
The compatible symptoms remain unexplained because bowel gas prevented SMA assessment. A negative interpretation requires adequate visualization, so this report cannot close the vascular workup.
D. Use early colonoscopy to quantify the SMA stenosis (Why this does not fit)
Colonoscopy inspects colonic mucosa and can support selected diagnoses of colonic injury. It does not measure narrowing of the mesenteric arteries. No. Meal pain and progressive food avoidance still require a diagnostic arterial map. Colonoscopy cannot quantify the SMA stenosis that the ultrasound failed to assess.
Reasoning steps for option D
Which structure does colonoscopy inspect rather than the SMA lumen?
Colonoscopy inspects colonic mucosa and can support selected diagnoses of colonic injury. It does not measure narrowing of the mesenteric arteries.
Would mucosal inspection resolve the arterial uncertainty created by this failed duplex?
No. Meal pain and progressive food avoidance still require a diagnostic arterial map. Colonoscopy cannot quantify the SMA stenosis that the ultrasound failed to assess.
Takeaway: A nondiagnostic vascular study leaves the arterial question open.
A. Obtain urgent multiphasic CTA while contacting the surgical and vascular teams (Best answer)
The change from intermittent postprandial pain to sustained severe pain raises concern for acute-on-chronic mesenteric ischemia. Mild tenderness without guarding does not exclude early threatened bowel. Neither a normal early lactate nor acute kidney injury justifies delaying CTA when acute mesenteric ischemia is suspected. Obtain urgent multiphasic CTA with resuscitation and surgical and vascular contact in parallel.
Reasoning steps for option A
What does six hours of continuous severe pain change about the prior meal-related syndrome?
The change from intermittent postprandial pain to sustained severe pain raises concern for acute-on-chronic mesenteric ischemia. Mild tenderness without guarding does not exclude early threatened bowel.
Should lactate 1.6 or the creatinine rise postpone CTA in this acute presentation?
Neither a normal early lactate nor acute kidney injury justifies delaying CTA when acute mesenteric ischemia is suspected. Obtain urgent multiphasic CTA with resuscitation and surgical and vascular contact in parallel.
B. Repeat lactate after fluids and image only if it becomes abnormal (Why this does not fit)
No. Threatened bowel can be present before lactate rises, so the normal value cannot override six hours of new severe continuous pain. That strategy can delay arterial and bowel assessment while ischemia progresses. Serial lactate may assist perfusion monitoring during fluids, but urgent CTA should proceed on the clinical concern.
Reasoning steps for option B
Can lactate 1.6 mmol/L exclude early ischemia after this abrupt change in pain?
No. Threatened bowel can be present before lactate rises, so the normal value cannot override six hours of new severe continuous pain.
What is lost by making an abnormal repeat lactate the condition for imaging?
That strategy can delay arterial and bowel assessment while ischemia progresses. Serial lactate may assist perfusion monitoring during fluids, but urgent CTA should proceed on the clinical concern.
C. Arrange outpatient MR angiography after kidney function returns to baseline (Why this does not fit)
MR angiography can evaluate stable chronic arterial disease, such as an unchanged pattern of meal-triggered symptoms when immediate bowel threat is not suspected. The new severe continuous pain is an acute warning, not a stable chronic complaint. Waiting for renal recovery before outpatient imaging leaves possible acute ischemia unassessed.
Reasoning steps for option C
For what symptom course would an outpatient mesenteric MR pathway be reasonable?
MR angiography can evaluate stable chronic arterial disease, such as an unchanged pattern of meal-triggered symptoms when immediate bowel threat is not suspected.
Why does waiting for creatinine to return from 2.1 to 1.0 misclassify the current urgency?
The new severe continuous pain is an acute warning, not a stable chronic complaint. Waiting for renal recovery before outpatient imaging leaves possible acute ischemia unassessed.
D. Perform colonoscopy before deciding whether arterial imaging is needed (Why this does not fit)
Colonoscopy examines colonic mucosa, whereas this acute-on-chronic presentation requires prompt evaluation of mesenteric vessels and bowel by CTA. Early mesenteric ischemia may cause severe pain before guarding develops. Mucosal inspection cannot exclude that vascular threat and should not delay time-critical arterial imaging.
Reasoning steps for option D
Would colonoscopy define the arterial cause of six hours of new severe pain?
Colonoscopy examines colonic mucosa, whereas this acute-on-chronic presentation requires prompt evaluation of mesenteric vessels and bowel by CTA.
Why should the mild examination not justify a colonoscopy-first sequence?
Early mesenteric ischemia may cause severe pain before guarding develops. Mucosal inspection cannot exclude that vascular threat and should not delay time-critical arterial imaging.
Takeaway: A new acute pattern overrides reassurance from a normal lactate or previously chronic symptoms.
A. An invasive enteric infection produces acute inflammatory mucosal injury (Why this does not fit)
Enteric infection can cause cramping, bloody diarrhea and wall thickening, so maroon stool and edema alone are not specific for ischemia. Hypotension precedes cramps and urgency, followed five hours later by blood. The segmental left-sided injury and recovery of pressure with fluids support a low-flow trigger more directly than an infectious cause.
Reasoning steps for option A
Which symptoms make infection a competing explanation for this postoperative colitis?
Enteric infection can cause cramping, bloody diarrhea and wall thickening, so maroon stool and edema alone are not specific for ischemia.
What sequence favors hypoperfusion over infection in the descending-colon segment?
Hypotension precedes cramps and urgency, followed five hours later by blood. The segmental left-sided injury and recovery of pressure with fluids support a low-flow trigger more directly than an infectious cause.
B. An immune-mediated colitis produces a new chronic inflammatory disorder (Why this does not fit)
It could produce those overlapping symptoms, but the symptom combination alone does not establish a chronic immune-mediated disorder. The abrupt onset after hypotension, segmental descending-colon edema and improvement in systemic perfusion favor transient ischemic injury. They do not supply a basis for diagnosing a new chronic inflammatory condition.
Reasoning steps for option B
Could new inflammatory bowel disease account for painful bloody diarrhea?
It could produce those overlapping symptoms, but the symptom combination alone does not establish a chronic immune-mediated disorder.
How does the postoperative hemodynamic history weigh against that chronic inflammatory explanation?
The abrupt onset after hypotension, segmental descending-colon edema and improvement in systemic perfusion favor transient ischemic injury. They do not supply a basis for diagnosing a new chronic inflammatory condition.
C. Transient hypoperfusion injures a susceptible colonic mucosal segment (Best answer)
Reduced systemic perfusion can lower mucosal blood delivery in a susceptible colonic segment without producing a major arterial occlusion. Cramps and urgency follow hypotension, then bleeding appears within hours in association with descending-colon edema. Preserved enhancement, no pneumatosis and recovered systemic perfusion support a transient low-flow explanation rather than requiring a persistent large-vessel clot.
Reasoning steps for option C
How could the brief pressure drop injure colon while the major arteries remain open?
Reduced systemic perfusion can lower mucosal blood delivery in a susceptible colonic segment without producing a major arterial occlusion.
Which timing and CT findings connect that mechanism to the maroon stool?
Cramps and urgency follow hypotension, then bleeding appears within hours in association with descending-colon edema. Preserved enhancement, no pneumatosis and recovered systemic perfusion support a transient low-flow explanation rather than requiring a persistent large-vessel clot.
D. A ruptured diverticular arteriole produces an isolated bleeding event (Why this does not fit)
It would explain lower gastrointestinal bleeding, a common presentation in older adults, but isolated diverticular hemorrhage is more often painless. Cramps and urgency precede the blood, and CT shows an edematous colonic segment after hypotension. That combination favors mucosal injury from low perfusion rather than a bleeding-only event.
Reasoning steps for option D
What would a ruptured diverticular arteriole explain about the maroon stool?
It would explain lower gastrointestinal bleeding, a common presentation in older adults, but isolated diverticular hemorrhage is more often painless.
Which findings require an explanation beyond an isolated bleeding vessel?
Cramps and urgency precede the blood, and CT shows an edematous colonic segment after hypotension. That combination favors mucosal injury from low perfusion rather than a bleeding-only event.
Takeaway: Low-flow colonic injury can coexist with open major mesenteric arteries.
A. Catheter mesenteric angiography as the routine confirmatory test (Why this does not fit)
Catheter angiography can help selected mesenteric arterial or nonocclusive emergencies when a vascular question remains, rather than serving as routine confirmation of every colitis episode. No arterial emergency is established by the supplied distribution or stable examination. The remaining uncertainty is the cause of colonic mucosal injury, for which safe endoscopic assessment is more directly informative.
Reasoning steps for option A
What unresolved problem would justify catheter angiography instead of mucosal assessment?
Catheter angiography can help selected mesenteric arterial or nonocclusive emergencies when a vascular question remains, rather than serving as routine confirmation of every colitis episode.
Does stable left-sided colitis with negative pathogen testing establish that angiographic indication?
No arterial emergency is established by the supplied distribution or stable examination. The remaining uncertainty is the cause of colonic mucosal injury, for which safe endoscopic assessment is more directly informative.
B. Early colonoscopy with minimal insufflation and mucosal biopsy (Best answer)
She is stable without guarding, and CT shows no free air or pneumatosis. There is no supplied evidence of peritonitis or irreversible injury that would make routine colonoscopy inappropriate. Early colonoscopy with minimal insufflation and appropriate mucosal biopsy can support ischemic injury and clarify the remaining colitis differential. CT distribution and negative pathogen testing alone have not established the cause.
Reasoning steps for option B
Which examination and CT findings permit early mucosal assessment in this patient?
She is stable without guarding, and CT shows no free air or pneumatosis. There is no supplied evidence of peritonitis or irreversible injury that would make routine colonoscopy inappropriate.
What evidence can cautious colonoscopy add after left-sided colitis and negative stool tests?
Early colonoscopy with minimal insufflation and appropriate mucosal biopsy can support ischemic injury and clarify the remaining colitis differential. CT distribution and negative pathogen testing alone have not established the cause.
C. Capsule endoscopy to replace colonic biopsy sampling (Why this does not fit)
A capsule does not obtain a colonic mucosal biopsy. The demonstrated lesion is in the colon, not an unexplained small-bowel disorder for which capsule evaluation might be selected. After nonspecific CT findings and negative stool tests, direct colonic inspection and biopsy can add diagnostic evidence. Replacing that assessment with a capsule leaves the sampling question unanswered.
Reasoning steps for option C
What evidence would capsule endoscopy fail to supply for this colonic abnormality?
A capsule does not obtain a colonic mucosal biopsy. The demonstrated lesion is in the colon, not an unexplained small-bowel disorder for which capsule evaluation might be selected.
Why does the unresolved etiology favor a tissue-capable examination?
After nonspecific CT findings and negative stool tests, direct colonic inspection and biopsy can add diagnostic evidence. Replacing that assessment with a capsule leaves the sampling question unanswered.
D. Unenhanced CT repeated after the bleeding resolves (Why this does not fit)
It has localized left-sided colitis and shown no free air, pneumatosis or right-colon involvement; the patient remains clinically stable. Another scan without a defined new clinical question would add limited etiologic specificity and postpone useful mucosal assessment. The unresolved issue is not simply whether colitis remains visible.
Reasoning steps for option D
What has the existing contrast CT already established before the proposed repeat scan?
It has localized left-sided colitis and shown no free air, pneumatosis or right-colon involvement; the patient remains clinically stable.
Would waiting for bleeding to stop and repeating unenhanced CT identify the cause?
Another scan without a defined new clinical question would add limited etiologic specificity and postpone useful mucosal assessment. The unresolved issue is not simply whether colitis remains visible.
Takeaway: Safe early mucosal assessment can clarify CT-demonstrated colitis.
A. Advance to the cecum using additional insufflation to map the disease (Why this does not fit)
It would attempt a complete endoscopic map even though CT has already defined the involved left-sided segment and the distal injury has been encountered. The acutely injured mucosa raises procedural risk. A full survey is not worth advancing through that segment when a limited examination can provide the needed confirmation.
Reasoning steps for option A
What additional information would reaching the cecum seek after CT already mapped sigmoid-to-flexure disease?
It would attempt a complete endoscopic map even though CT has already defined the involved left-sided segment and the distal injury has been encountered.
How do friability and ulceration change the value of extra insufflation and traversal?
The acutely injured mucosa raises procedural risk. A full survey is not worth advancing through that segment when a limited examination can provide the needed confirmation.
B. Replace the examination with capsule endoscopy to inspect the proximal colon (Why this does not fit)
A capsule cannot obtain the mucosal tissue needed to clarify the observed injury; accessible distal mucosa can be sampled during the limited examination when appropriate. CT already maps the disease to the splenic flexure. Replacing the focused examination with a capsule adds no supplied management-relevant reason to abandon distal tissue assessment.
Reasoning steps for option B
What diagnostic capability is missing from a capsule when ulcerated distal sigmoid is already accessible?
A capsule cannot obtain the mucosal tissue needed to clarify the observed injury; accessible distal mucosa can be sampled during the limited examination when appropriate.
Does proximal inspection by capsule solve an unresolved extent question in this case?
CT already maps the disease to the splenic flexure. Replacing the focused examination with a capsule adds no supplied management-relevant reason to abandon distal tissue assessment.
C. Perform immediate catheter angiography before sampling the colonic mucosa (Why this does not fit)
A suspected treatable mesenteric vascular process would create a reason for angiography. The case instead supplies stable, CT-localized left-sided colitis without a new arterial concern. The examination has reached the distal abnormal segment, where appropriate biopsy can clarify mucosal injury. An invasive arterial test does not answer that immediate tissue question.
Reasoning steps for option C
Which concern would need to emerge before catheter angiography displaced the current limited examination?
A suspected treatable mesenteric vascular process would create a reason for angiography. The case instead supplies stable, CT-localized left-sided colitis without a new arterial concern.
Why is the encountered distal sigmoid mucosa the relevant diagnostic target now?
The examination has reached the distal abnormal segment, where appropriate biopsy can clarify mucosal injury. An invasive arterial test does not answer that immediate tissue question.
D. Obtain distal mucosal biopsies without traversing the injured segment (Best answer)
It is the distal extent of the known injured segment. Further advancement is not needed merely to rediscover the proximal extent already shown on CT. Appropriate distal mucosal biopsies can be obtained when gangrene is absent, while keeping the examination limited. Avoid traversing the injured segment and minimize insufflation rather than pursuing a complete survey.
Reasoning steps for option D
What does the first friable sigmoid segment represent relative to the CT-defined disease?
It is the distal extent of the known injured segment. Further advancement is not needed merely to rediscover the proximal extent already shown on CT.
How does the absence of visible gangrene affect sampling at that endpoint?
Appropriate distal mucosal biopsies can be obtained when gangrene is absent, while keeping the examination limited. Avoid traversing the injured segment and minimize insufflation rather than pursuing a complete survey.
Takeaway: In acutely injured colon, stop at the distal disease rather than pursuing a complete survey.
A. Limited colonoscopy before obtaining any further arterial imaging (Why this does not fit)
When safe, endoscopy can support a diagnosis of colonic mucosal ischemia, but it cannot define the inadequately assessed SMA origin. Severe right-sided pain and isolated right-colon injury raise concern for an SMA-related process or broader acute mesenteric ischemia. Colonoscopy should not delay the arterial study that the venous-phase CT failed to provide.
Reasoning steps for option A
What could limited colonoscopy establish about the cecal and ascending-colon edema?
When safe, endoscopy can support a diagnosis of colonic mucosal ischemia, but it cannot define the inadequately assessed SMA origin.
Why does this right-sided presentation require arterial imaging before mucosal confirmation?
Severe right-sided pain and isolated right-colon injury raise concern for an SMA-related process or broader acute mesenteric ischemia. Colonoscopy should not delay the arterial study that the venous-phase CT failed to provide.
B. Repeat the lactate after six hours before choosing another study (Why this does not fit)
A near-normal lactate does not exclude acute mesenteric ischemia or resolve the unassessed SMA anatomy, even when blood pressure is currently maintained. Repeating lactate may track deterioration but cannot show the SMA lumen. High-risk distribution already justifies prompt vascular imaging without waiting for biochemical worsening.
Reasoning steps for option B
What does lactate 1.9 mmol/L fail to exclude in this patient with right-colon injury?
A near-normal lactate does not exclude acute mesenteric ischemia or resolve the unassessed SMA anatomy, even when blood pressure is currently maintained.
Why is a six-hour laboratory wait a poor substitute for the missing arterial phase?
Repeating lactate may track deterioration but cannot show the SMA lumen. High-risk distribution already justifies prompt vascular imaging without waiting for biochemical worsening.
C. Multiphasic CTA to assess mesenteric arteries and bowel enhancement (Best answer)
The right colon lies in SMA territory, and the supplied portal-venous-phase CT does not adequately assess the SMA origin. CTA evaluates mesenteric arterial anatomy and possible broader acute ischemia. The right-sided distribution warrants this assessment without requiring prominent bleeding or an elevated lactate.
Reasoning steps for option C
Which artery connects isolated cecal and ascending-colon injury to the unanswered vascular question?
The right colon lies in SMA territory, and the supplied portal-venous-phase CT does not adequately assess the SMA origin.
How does multiphasic CTA improve on that incomplete study despite scant blood and lactate 1.9?
CTA evaluates mesenteric arterial anatomy and possible broader acute ischemia. The right-sided distribution warrants this assessment without requiring prominent bleeding or an elevated lactate.
D. Elective fasting duplex ultrasound after the acute pain subsides (Why this does not fit)
Duplex can screen selected stable chronic mesenteric disease, where arterial evaluation is not being delayed during an acute bowel threat. This is acute severe pain with isolated right-colon injury and an unassessed SMA origin. A delayed chronic screening pathway would leave a time-sensitive arterial question unresolved.
Reasoning steps for option D
What clinical setting is appropriate for elective fasting mesenteric duplex screening?
Duplex can screen selected stable chronic mesenteric disease, where arterial evaluation is not being delayed during an acute bowel threat.
Why does waiting until the right-sided pain subsides not fit this CT pattern?
This is acute severe pain with isolated right-colon injury and an unassessed SMA origin. A delayed chronic screening pathway would leave a time-sensitive arterial question unresolved.
Takeaway: Isolated right-colon ischemia requires evaluation for a broader mesenteric vascular threat.
A. Endoscopic biopsy to prove the tissue diagnosis before surgical planning (Why this does not fit)
They indicate peritoneal deterioration and possible advanced bowel injury, making routine colonoscopy inappropriate rather than a prerequisite to surgical planning. No. Poor enhancement, pneumatosis, portal gas and persistent hypotension demand assessment of potentially nonviable bowel. Obtaining superficial histology first would delay that decision.
Reasoning steps for option A
How do involuntary guarding and shock change the safety of endoscopic biopsy?
They indicate peritoneal deterioration and possible advanced bowel injury, making routine colonoscopy inappropriate rather than a prerequisite to surgical planning.
Would a mucosal sample resolve viability more effectively than urgent operative assessment here?
No. Poor enhancement, pneumatosis, portal gas and persistent hypotension demand assessment of potentially nonviable bowel. Obtaining superficial histology first would delay that decision.
B. Urgent operative assessment for exploration and removal of nonviable bowel (Best answer)
Diffuse involuntary guarding, confusion and hypotension despite resuscitation accompany poorly enhancing bowel. Together they support advanced ischemic injury with possible nonviable tissue. Urgent exploration assesses bowel viability and allows removal of nonviable bowel for source control. Antibiotics and resuscitation do not eliminate the need to address dead tissue when peritonitis and shock persist.
Reasoning steps for option B
Which combination makes the intramural and portal gas more ominous than an isolated CT finding?
Diffuse involuntary guarding, confusion and hypotension despite resuscitation accompany poorly enhancing bowel. Together they support advanced ischemic injury with possible nonviable tissue.
What does operative assessment address that the current antibiotics cannot?
Urgent exploration assesses bowel viability and allows removal of nonviable bowel for source control. Antibiotics and resuscitation do not eliminate the need to address dead tissue when peritonitis and shock persist.
C. A further antibiotic trial before arranging procedural assessment (Why this does not fit)
Broad-spectrum antibiotics can accompany care for moderate or severe disease, but they do not restore viability to infarcted bowel. The deterioration raises concern for nonviable tissue requiring source control. Waiting to judge another antimicrobial trial would postpone the urgent operative assessment indicated by the examination and CT.
Reasoning steps for option C
What useful role do antibiotics have during treatment of severe colonic ischemia?
Broad-spectrum antibiotics can accompany care for moderate or severe disease, but they do not restore viability to infarcted bowel.
Why is another antibiotic trial insufficient after persistent hypotension and new guarding?
The deterioration raises concern for nonviable tissue requiring source control. Waiting to judge another antimicrobial trial would postpone the urgent operative assessment indicated by the examination and CT.
D. Mesenteric stenting followed by observation without direct viability assessment (Why this does not fit)
Stenting can improve arterial inflow in suitable occlusive disease. Restoring supply addresses the vessel but does not establish that all bowel remains viable. Involuntary guarding and progressive shock require direct assessment of bowel viability and any need for removal of dead tissue. Revascularization alone cannot substitute for that assessment.
Reasoning steps for option D
What problem could mesenteric stenting treat if an appropriate occlusive lesion were identified?
Stenting can improve arterial inflow in suitable occlusive disease. Restoring supply addresses the vessel but does not establish that all bowel remains viable.
Why is observation after stenting inadequate in this patient with peritonitis?
Involuntary guarding and progressive shock require direct assessment of bowel viability and any need for removal of dead tissue. Revascularization alone cannot substitute for that assessment.
Takeaway: Peritonitis with deteriorating perfusion makes bowel viability and source control urgent.
A. Mild disease: supportive observation without an escalation assessment (Why this does not fit)
BUN 28 mg/dL exceeds the ACG threshold of 20, and sodium 132 mmol/L is below 136. These are two specified poor-outcome factors. They support moderate disease, not mild disease. Stable pressure and pulse do not erase the laboratory factors or justify observation without the additional assessment appropriate to moderate illness.
Reasoning steps for option A
Which supplied laboratory results conflict with a mild classification despite pressure 118/72?
BUN 28 mg/dL exceeds the ACG threshold of 20, and sodium 132 mmol/L is below 136. These are two specified poor-outcome factors.
What do two qualifying factors mean when the left-sided disease has no severe feature?
They support moderate disease, not mild disease. Stable pressure and pulse do not erase the laboratory factors or justify observation without the additional assessment appropriate to moderate illness.
B. Severe disease: immediate bowel resection for the laboratory abnormalities (Why this does not fit)
No. They supply two factors; the ACG severe category requires more than three factors or an overriding severe feature, none of which is supplied. Laboratory risk factors do not diagnose irreversible bowel death. These results neither support the proposed severe classification nor independently establish an indication for immediate resection.
Reasoning steps for option B
Do BUN 28 and sodium 132 reach the numerical boundary for severe disease?
No. They supply two factors; the ACG severe category requires more than three factors or an overriding severe feature, none of which is supplied.
Even with a severe category, would those two laboratory values establish tissue requiring resection?
Laboratory risk factors do not diagnose irreversible bowel death. These results neither support the proposed severe classification nor independently establish an indication for immediate resection.
C. Moderate disease: nutritional support alone until the laboratory values normalize (Why this does not fit)
The moderate classification is appropriate because elevated BUN and low sodium supply two factors without a severe feature. The profile warrants perfusion-directed correction, antibiotic consideration and surgical consultation. Nutrition may support recovery but does not replace those assessments while the abnormalities persist.
Reasoning steps for option C
Which part of this nutrition-only plan correctly interprets the two laboratory abnormalities?
The moderate classification is appropriate because elevated BUN and low sodium supply two factors without a severe feature.
Why is waiting for nutritional support to normalize the results not adequate moderate-disease care?
The profile warrants perfusion-directed correction, antibiotic consideration and surgical consultation. Nutrition may support recovery but does not replace those assessments while the abnormalities persist.
D. Moderate disease: correct perfusion, consider antibiotics, consult surgery (Best answer)
Two qualify: BUN 28 is above 20 mg/dL and sodium 132 is below 136 mmol/L. The supplied other values, rectal bleeding and absence of ulceration or severe features do not add another factor. Moderate disease calls for perfusion correction, consideration of antibiotics and surgical consultation. Her normal vital signs do not reduce the category to mild, and the two factors do not mandate resection.
Reasoning steps for option D
How many ACG factors remain after checking the listed pressure, pulse, blood counts and LDH?
Two qualify: BUN 28 is above 20 mg/dL and sodium 132 is below 136 mmol/L. The supplied other values, rectal bleeding and absence of ulceration or severe features do not add another factor.
Which care level follows from two factors without a severe-feature override?
Moderate disease calls for perfusion correction, consideration of antibiotics and surgical consultation. Her normal vital signs do not reduce the category to mild, and the two factors do not mandate resection.
Takeaway: Count the actual guideline factors and check separately for severe features.
A. Right-colon involvement warrants urgent assessment as severe disease (Best answer)
Isolated right-colon involvement is an overriding severe feature in the ACG framework, independent of the number of laboratory or vital-sign factors. It warrants urgent specialist assessment at a severe-disease level. Reassuring values do not cancel the right-sided risk, although the distribution alone does not prove irreversible infarction.
Reasoning steps for option A
What severity feature is established by ischemia confined to the ascending colon?
Isolated right-colon involvement is an overriding severe feature in the ACG framework, independent of the number of laboratory or vital-sign factors.
How should that anatomic feature affect care despite pressure 122/74 and reassuring supplied blood tests?
It warrants urgent specialist assessment at a severe-disease level. Reassuring values do not cancel the right-sided risk, although the distribution alone does not prove irreversible infarction.
B. Normal pressure and laboratory results justify observation as mild disease (Why this does not fit)
Pressure and pulse are stable, and the supplied BUN, sodium, hemoglobin and WBC do not cross their poor-outcome thresholds. Isolated ascending-colon ischemic injury meets the right-colon severe-feature criterion. The distribution overrides a low factor count and calls for urgent assessment rather than routine mild-disease observation.
Reasoning steps for option B
What aspect of the vital signs and supplied laboratory values could suggest lower risk?
Pressure and pulse are stable, and the supplied BUN, sodium, hemoglobin and WBC do not cross their poor-outcome thresholds.
Which CT finding prevents that reassuring profile from establishing mild disease?
Isolated ascending-colon ischemic injury meets the right-colon severe-feature criterion. The distribution overrides a low factor count and calls for urgent assessment rather than routine mild-disease observation.
C. Absent pneumatosis rules out clinically important intestinal ischemia (Why this does not fit)
Intramural gas can signal advanced injury, but important ischemia does not require it to be visible. CT already shows ischemic injury in a high-risk right-sided distribution. The absence of one ominous finding neither excludes ischemia nor removes the severe anatomic classification.
Reasoning steps for option C
What would pneumatosis add to the assessment of ischemic bowel?
Intramural gas can signal advanced injury, but important ischemia does not require it to be visible.
Why does its absence fail to clear this isolated ascending-colon injury?
CT already shows ischemic injury in a high-risk right-sided distribution. The absence of one ominous finding neither excludes ischemia nor removes the severe anatomic classification.
D. Right-colon involvement proves infarction and mandates immediate colectomy (Why this does not fit)
No. It identifies increased risk and the need for urgent assessment, not proof that the involved colon is already irreversibly infarcted. The supplied scan has no pneumatosis or free air, and no established necrosis is reported. Specialist assessment must determine the need for intervention rather than treating distribution alone as proof that resection is required.
Reasoning steps for option D
Does a severe classification from right-colon distribution directly measure bowel viability?
No. It identifies increased risk and the need for urgent assessment, not proof that the involved colon is already irreversibly infarcted.
What distinguishes the need for urgent review from a predetermined colectomy in this case?
The supplied scan has no pneumatosis or free air, and no established necrosis is reported. Specialist assessment must determine the need for intervention rather than treating distribution alone as proof that resection is required.
Takeaway: Right-colon involvement can set the severity category before laboratory deterioration.
A. Perform routine colonoscopy immediately to determine whether the gas is benign (Why this does not fit)
No. In suspected colonic ischemia, intramural gas is a high-risk finding that requires urgent assessment before considering routine mucosal examination. Mild tenderness and normal pressure do not erase the concern about injured bowel. Routine colonoscopy could add procedural risk while delaying the assessment of perfusion, viability and progression.
Reasoning steps for option A
Does preserved enhancement remove the endoscopic safety concern raised by colonic pneumatosis?
No. In suspected colonic ischemia, intramural gas is a high-risk finding that requires urgent assessment before considering routine mucosal examination.
Why is immediate colonoscopy not the way to decide whether this gas is benign?
Mild tenderness and normal pressure do not erase the concern about injured bowel. Routine colonoscopy could add procedural risk while delaying the assessment of perfusion, viability and progression.
B. Urgent surgical assessment with perfusion correction and serial review (Best answer)
Intramural gas in a patient with abdominal pain after dehydration raises concern for ischemic injury and warrants urgent surgical assessment, even without current shock. Preserved enhancement and no guarding, portal gas or free air do not establish irreversible necrosis. Correct perfusion and reassess the trajectory while determining whether intervention is needed, rather than automatically ordering resection.
Reasoning steps for option B
What makes this short segment of pneumatosis important despite normal pressure and pH?
Intramural gas in a patient with abdominal pain after dehydration raises concern for ischemic injury and warrants urgent surgical assessment, even without current shock.
How do enhancement and the absence of guarding affect what that assessment should determine?
Preserved enhancement and no guarding, portal gas or free air do not establish irreversible necrosis. Correct perfusion and reassess the trajectory while determining whether intervention is needed, rather than automatically ordering resection.
C. Schedule immediate colectomy solely because intramural gas is present (Why this does not fit)
The examination, bowel enhancement and physiological trajectory matter because pneumatosis can occur with infarction but also with noninfarction causes. They do not corroborate irreversible injury sufficiently to mandate removal from this scan alone. The gas requires urgent assessment, not a predetermined resection based solely on its presence.
Reasoning steps for option C
What would intramural gas need to be interpreted alongside before labeling this colon nonviable?
The examination, bowel enhancement and physiological trajectory matter because pneumatosis can occur with infarction but also with noninfarction causes.
Do normal pH, preserved enhancement and tenderness without guarding prove a need for colectomy?
They do not corroborate irreversible injury sufficiently to mandate removal from this scan alone. The gas requires urgent assessment, not a predetermined resection based solely on its presence.
D. Arrange routine outpatient follow-up because enhancement is preserved (Why this does not fit)
Preserved enhancement is more reassuring than absent enhancement because the bowel is still taking up contrast, but it does not settle the significance of intramural gas. Possible ischemic pneumatosis remains a high-risk finding requiring urgent evaluation and close reassessment. The reassuring features do not make a routine discharge pathway appropriate.
Reasoning steps for option D
What aspect of preserved bowel enhancement is reassuring in this dehydration-associated presentation?
Preserved enhancement is more reassuring than absent enhancement because the bowel is still taking up contrast, but it does not settle the significance of intramural gas.
Why is routine outpatient follow-up inadequate despite normal pressure and mild tenderness?
Possible ischemic pneumatosis remains a high-risk finding requiring urgent evaluation and close reassessment. The reassuring features do not make a routine discharge pathway appropriate.
Takeaway: Pneumatosis warrants urgent context-sensitive assessment, not automatic reassurance or automatic resection.
A. Reduced mesenteric perfusion with vasoconstriction despite open major vessels (Best answer)
Severe systemic low flow and mesenteric vasoconstriction can compromise tissue perfusion without blocking the proximal artery, producing nonocclusive mesenteric ischemia. Patchy poor small-bowel enhancement and worsening acidosis accompany the shock state. Patent arteries and veins exclude neither inadequate tissue delivery nor an evolving nonocclusive injury.
Reasoning steps for option A
How can septic shock and vasopressor exposure reduce bowel perfusion with an open SMA?
Severe systemic low flow and mesenteric vasoconstriction can compromise tissue perfusion without blocking the proximal artery, producing nonocclusive mesenteric ischemia.
Which bowel and physiological findings keep that mechanism concerning on this CTA?
Patchy poor small-bowel enhancement and worsening acidosis accompany the shock state. Patent arteries and veins exclude neither inadequate tissue delivery nor an evolving nonocclusive injury.
B. A benign functional ileus that is established by arterial patency (Why this does not fit)
Critical illness can impair motility and cause abdominal distension, so distension alone would not distinguish ileus from ischemic bowel injury. The bowel itself enhances poorly and acidosis is worsening. Those findings remain concerning for inadequate perfusion even without a proximal blockage and cannot be dismissed as a proven functional disorder.
Reasoning steps for option B
Which part of this critically ill patient's presentation could be explained by functional ileus?
Critical illness can impair motility and cause abdominal distension, so distension alone would not distinguish ileus from ischemic bowel injury.
Why do patent proximal vessels fail to establish benign ileus in the face of poor enhancement?
The bowel itself enhances poorly and acidosis is worsening. Those findings remain concerning for inadequate perfusion even without a proximal blockage and cannot be dismissed as a proven functional disorder.
C. An occlusive SMA embolus that is directly demonstrated by the study (Why this does not fit)
An embolic filling defect obstructing the SMA would support that mechanism, but the scan explicitly reports a patent proximal SMA without an embolic defect. The septic shock and vasopressor setting supports low-flow, vasoconstrictive nonocclusive ischemia. Naming a directly demonstrated embolus contradicts the supplied vascular findings.
Reasoning steps for option C
What CTA finding would directly support the proposed occlusive SMA embolus?
An embolic filling defect obstructing the SMA would support that mechanism, but the scan explicitly reports a patent proximal SMA without an embolic defect.
Which mechanism better accounts for poorly enhancing bowel without the proposed obstruction?
The septic shock and vasopressor setting supports low-flow, vasoconstrictive nonocclusive ischemia. Naming a directly demonstrated embolus contradicts the supplied vascular findings.
D. Mesenteric venous thrombosis causing impaired outflow on the scan (Why this does not fit)
Venous thrombosis would obstruct mesenteric drainage; the CTA instead reports patent mesenteric veins, so it does not demonstrate the proposed outflow lesion. Septic shock with vasopressor exposure can reduce mesenteric tissue flow despite open veins and arteries. That systemic and vasoconstrictive mechanism fits the poorly enhancing bowel without inventing a venous clot.
Reasoning steps for option D
What outflow abnormality would mesenteric venous thrombosis require on this study?
Venous thrombosis would obstruct mesenteric drainage; the CTA instead reports patent mesenteric veins, so it does not demonstrate the proposed outflow lesion.
What supplied perfusion disturbance remains after the venous explanation is unsupported?
Septic shock with vasopressor exposure can reduce mesenteric tissue flow despite open veins and arteries. That systemic and vasoconstrictive mechanism fits the poorly enhancing bowel without inventing a venous clot.
Takeaway: Nonocclusive ischemia can threaten bowel despite patent mesenteric arteries and veins.
A. The celiac trunk directly supplies the rectal mucosa through the splenic artery (Why this does not fit)
No. The celiac circulation supplies foregut structures; a splenic arterial branch is not the direct supplementary inflow that protects rectal mucosa. The injury involves descending and sigmoid colon, while the spared tissue is pelvic rectum. Supplemental rectal arterial inflow comes from pelvic branches, not a direct celiac-to-rectum route.
Reasoning steps for option A
Does the splenic artery provide the direct rectal supply proposed in this option?
No. The celiac circulation supplies foregut structures; a splenic arterial branch is not the direct supplementary inflow that protects rectal mucosa.
Which regional distinction rules out this foregut explanation for rectal sparing?
The injury involves descending and sigmoid colon, while the spared tissue is pelvic rectum. Supplemental rectal arterial inflow comes from pelvic branches, not a direct celiac-to-rectum route.
B. The ileocolic artery directly supplies the superior rectum through a terminal branch (Why this does not fit)
The ileocolic artery supplies ileal, cecal and proximal colonic territory. It does not send the proposed direct terminal branch to the superior rectum. Rectal preservation alongside descending and sigmoid injury requires a regional pelvic collateral explanation. Reassigning an ileocolic branch to the superior rectum does not match the arterial anatomy.
Reasoning steps for option B
Where does the ileocolic artery supply tissue relative to the spared rectum?
The ileocolic artery supplies ileal, cecal and proximal colonic territory. It does not send the proposed direct terminal branch to the superior rectum.
Why would assigning that right-sided artery to the rectum misread this injury pattern?
Rectal preservation alongside descending and sigmoid injury requires a regional pelvic collateral explanation. Reassigning an ileocolic branch to the superior rectum does not match the arterial anatomy.
C. Pelvic rectal branches supplement the superior rectal arterial supply (Best answer)
Rectal branches associated with the internal iliac circulation provide additional arterial inflow to the rectum beyond its superior rectal supply. Collateral supply is regional. Pelvic rectal branches can maintain rectal perfusion while a more proximal, predominantly IMA-supplied colonic segment is injured after hypotension.
Reasoning steps for option C
Which arterial routes can supplement superior rectal flow after reduced left-colon perfusion?
Rectal branches associated with the internal iliac circulation provide additional arterial inflow to the rectum beyond its superior rectal supply.
Why can those pelvic routes protect the rectum without protecting the descending and sigmoid colon equally?
Collateral supply is regional. Pelvic rectal branches can maintain rectal perfusion while a more proximal, predominantly IMA-supplied colonic segment is injured after hypotension.
D. Portal venous inflow reverses to replace the reduced rectal arterial supply (Why this does not fit)
No. Venous drainage affects congestion and pressure; it is not the normal substitute for oxygenated arterial inflow described by rectal collateral protection. The rectum has supplemental pelvic arterial routes that the injured descending and sigmoid segments do not share to the same degree. That regional arterial supply, not reversed portal flow, explains relative preservation.
Reasoning steps for option D
Would reversed portal venous drainage provide the usual protective arterial supply to the rectum?
No. Venous drainage affects congestion and pressure; it is not the normal substitute for oxygenated arterial inflow described by rectal collateral protection.
How does the proposed reversal differ from the vascular mechanism of rectal sparing here?
The rectum has supplemental pelvic arterial routes that the injured descending and sigmoid segments do not share to the same degree. That regional arterial supply, not reversed portal flow, explains relative preservation.
Takeaway: The rectum often remains perfused through supplemental internal iliac branches.
A. Ileocolic and right colic territories (Why this does not fit)
These branches supply right-sided colonic territory, including cecal and ascending regions, rather than the splenic flexure identified on CT. The injured segment lies at a different vascular interface. Selecting two right-colon territories does not explain the vulnerability of the distal transverse and splenic-flexure region.
Reasoning steps for option A
Which colonic region lies in the ileocolic and right colic territories?
These branches supply right-sided colonic territory, including cecal and ascending regions, rather than the splenic flexure identified on CT.
Why does the CT-centered flexure lesion reject this pair after the pressure drop?
The injured segment lies at a different vascular interface. Selecting two right-colon territories does not explain the vulnerability of the distal transverse and splenic-flexure region.
B. Last sigmoid and superior rectal territories (Why this does not fit)
Their junction is relevant to rectosigmoid vulnerability, a distal colonic border region rather than the splenic flexure. CT centers the injury at the splenic flexure. A low-flow trigger can affect different border regions, but the supplied location calls for the middle-colic and left-colic interface, not the rectosigmoid junction.
Reasoning steps for option B
At what junction would the last sigmoid and superior rectal territories be relevant?
Their junction is relevant to rectosigmoid vulnerability, a distal colonic border region rather than the splenic flexure.
Which localization prevents substituting that distal watershed for this patient's lesion?
CT centers the injury at the splenic flexure. A low-flow trigger can affect different border regions, but the supplied location calls for the middle-colic and left-colic interface, not the rectosigmoid junction.
C. Left gastric and short gastric territories (Why this does not fit)
They supply portions of the stomach, not a border region of the colon. The scan identifies colonic tissue at the flexure, not gastric injury. The relevant vascular border is between colonic branches of the SMA and IMA, regardless of the nearby splenic name.
Reasoning steps for option C
What organ do the left gastric and short gastric arteries supply?
They supply portions of the stomach, not a border region of the colon.
Why does proximity to the spleen not make those gastric territories explain splenic-flexure ischemia?
The scan identifies colonic tissue at the flexure, not gastric injury. The relevant vascular border is between colonic branches of the SMA and IMA, regardless of the nearby splenic name.
D. Middle colic and left colic territories (Best answer)
These branches of the SMA and IMA meet near the distal transverse colon and splenic flexure, matching the injured segment. Limited collateral reserve at the border can become inadequate during hypoperfusion without a new trunk occlusion. The pattern identifies a vulnerable watershed, not proof that either main artery is blocked.
Reasoning steps for option D
How do the middle colic and left colic territories meet the CT localization?
These branches of the SMA and IMA meet near the distal transverse colon and splenic flexure, matching the injured segment.
Why can a prolonged pressure drop injure that interface while both main trunks remain patent?
Limited collateral reserve at the border can become inadequate during hypoperfusion without a new trunk occlusion. The pattern identifies a vulnerable watershed, not proof that either main artery is blocked.
Takeaway: Splenic-flexure vulnerability relates to the SMA and IMA colonic interface.
A. Prioritize revascularization and coordinate nutrition around restored perfusion (Best answer)
The severe SMA and celiac stenoses limit inflow enough that even liquid intake provokes demand-related pain. The 12% weight loss reflects the clinical consequence of that feeding problem. Increasing intake before restoring flow can intensify the supply-demand deficit. Coordinate nutritional care with prompt restoration of perfusion rather than postponing treatment of the fixed arterial limitation.
Reasoning steps for option A
What does pain even with liquid meals imply about this patient's remaining arterial reserve?
The severe SMA and celiac stenoses limit inflow enough that even liquid intake provokes demand-related pain. The 12% weight loss reflects the clinical consequence of that feeding problem.
Why should feasible revascularization take priority over requiring weight gain first?
Increasing intake before restoring flow can intensify the supply-demand deficit. Coordinate nutritional care with prompt restoration of perfusion rather than postponing treatment of the fixed arterial limitation.
B. Delay revascularization until several weeks of forced enteral feeding restore weight (Why this does not fit)
Nutritional optimization can be useful before operations in many conditions, so the substantial weight loss creates a legitimate nutritional concern. Even liquid meals trigger pain through inadequate arterial reserve. Forcing more digestive demand while delaying a feasible repair can worsen ischemia instead of resolving the cause of malnutrition.
Reasoning steps for option B
Why might preoperative feeding seem attractive after a 12% loss of body weight?
Nutritional optimization can be useful before operations in many conditions, so the substantial weight loss creates a legitimate nutritional concern.
What makes several weeks of forced enteral feeding before vascular repair problematic here?
Even liquid meals trigger pain through inadequate arterial reserve. Forcing more digestive demand while delaying a feasible repair can worsen ischemia instead of resolving the cause of malnutrition.
C. Use prolonged parenteral nutrition as the definitive treatment of the stenoses (Why this does not fit)
It can deliver calories without enteral feeding in selected situations, but supplying calories does not restore flow through the severe SMA and celiac stenoses. The symptomatic arterial limitation remains untreated. Nutritional support cannot replace assessment and treatment of a correctable inflow problem merely by bypassing the feeding trigger.
Reasoning steps for option C
What could parenteral nutrition provide that painful enteral meals currently do not?
It can deliver calories without enteral feeding in selected situations, but supplying calories does not restore flow through the severe SMA and celiac stenoses.
Why is prolonged parenteral nutrition not definitive treatment when reconstruction is feasible?
The symptomatic arterial limitation remains untreated. Nutritional support cannot replace assessment and treatment of a correctable inflow problem merely by bypassing the feeding trigger.
D. Use small meals and defer intervention until gastrointestinal bleeding occurs (Why this does not fit)
Smaller meals can reduce digestive demand, although this patient now has pain even with liquid meals and has already lost substantial weight. No. Progressive food-related symptoms and malnutrition already establish clinically important chronic disease. Bleeding is not a prerequisite for restoring flow in symptomatic chronic mesenteric ischemia.
Reasoning steps for option D
How could smaller meals temporarily change this patient's postprandial pain?
Smaller meals can reduce digestive demand, although this patient now has pain even with liquid meals and has already lost substantial weight.
Does the absence of gastrointestinal bleeding justify deferring intervention?
No. Progressive food-related symptoms and malnutrition already establish clinically important chronic disease. Bleeding is not a prerequisite for restoring flow in symptomatic chronic mesenteric ischemia.
Takeaway: Restore flow promptly rather than making weight gain a prerequisite to treating demand ischemia.
A. Continue dietary restriction indefinitely because a catheter attempt failed (Why this does not fit)
Reducing intake may lessen demand-related pain temporarily, but it leaves the long symptomatic arterial occlusion in place. He has acceptable operative risk and suitable distal targets, so an alternative route to revascularization remains feasible. Failure of one technique does not remove the need to restore inflow.
Reasoning steps for option A
What would continued dietary restriction do to symptoms without changing the calcified SMA occlusion?
Reducing intake may lessen demand-related pain temporarily, but it leaves the long symptomatic arterial occlusion in place.
Why does failure of catheter crossing not justify indefinite restriction in this patient?
He has acceptable operative risk and suitable distal targets, so an alternative route to revascularization remains feasible. Failure of one technique does not remove the need to restore inflow.
B. Repeat catheter treatment without reassessing the previously uncrossable anatomy (Why this does not fit)
An experienced team could not cross the long, heavily calcified SMA occlusion. That specific anatomic limitation must be reassessed before another catheter attempt is chosen. A newly feasible anatomic approach or relevant additional expertise could change the assessment. Neither is supplied here, while suitable targets and acceptable risk support evaluating open reconstruction.
Reasoning steps for option B
What feature of the prior catheter attempt must inform a decision to repeat it?
An experienced team could not cross the long, heavily calcified SMA occlusion. That specific anatomic limitation must be reassessed before another catheter attempt is chosen.
What would make another endovascular approach different from simply repeating the failed strategy?
A newly feasible anatomic approach or relevant additional expertise could change the assessment. Neither is supplied here, while suitable targets and acceptable risk support evaluating open reconstruction.
C. Use long-term parenteral nutrition instead of further revascularization assessment (Why this does not fit)
It could support caloric intake in selected circumstances, but it would not correct the symptomatic arterial occlusion or restore intestinal inflow. Symptoms persist despite risk-factor treatment, and operative risk and distal reconstruction targets are favorable. A feasible corrective procedure remains to be assessed rather than abandoned for nutritional support alone.
Reasoning steps for option C
Would long-term parenteral nutrition reopen the uncrossable SMA lesion?
It could support caloric intake in selected circumstances, but it would not correct the symptomatic arterial occlusion or restore intestinal inflow.
Which supplied findings argue against replacing further vascular assessment with nutrition alone?
Symptoms persist despite risk-factor treatment, and operative risk and distal reconstruction targets are favorable. A feasible corrective procedure remains to be assessed rather than abandoned for nutritional support alone.
D. Open mesenteric arterial reconstruction after multidisciplinary evaluation (Best answer)
The experienced team could not cross the long calcified occlusion, establishing failure of the initial endovascular route while the patient remains symptomatic. Acceptable operative risk and suitable distal targets make open reconstruction a reasonable definitive alternative to assess. An endovascular-first strategy does not exclude open treatment after an unsuccessful catheter approach.
Reasoning steps for option D
Which procedural result makes open reconstruction relevant after the endovascular attempt?
The experienced team could not cross the long calcified occlusion, establishing failure of the initial endovascular route while the patient remains symptomatic.
What additional facts support multidisciplinary evaluation of an open mesenteric repair?
Acceptable operative risk and suitable distal targets make open reconstruction a reasonable definitive alternative to assess. An endovascular-first strategy does not exclude open treatment after an unsuccessful catheter approach.
Takeaway: Use anatomy, prior procedural results and operative risk to select the revascularization route.
A. Attribute the pain to functional dyspepsia because the artery contains a stent (Why this does not fit)
Functional dyspepsia can cause postprandial discomfort, but that symptom overlap does not establish a nonvascular cause in a patient with prior mesenteric disease. The patient initially improved after SMA stenting, then redeveloped the same meal pattern alongside higher in-stent velocities. A stent does not guarantee lasting patency, so the vascular recurrence needs assessment.
Reasoning steps for option A
Which part of the recurrent meal-related discomfort could overlap with functional dyspepsia?
Functional dyspepsia can cause postprandial discomfort, but that symptom overlap does not establish a nonvascular cause in a patient with prior mesenteric disease.
Why do the stent history and changed duplex argue against attributing the pain to dyspepsia now?
The patient initially improved after SMA stenting, then redeveloped the same meal pattern alongside higher in-stent velocities. A stent does not guarantee lasting patency, so the vascular recurrence needs assessment.
B. Evaluate for restenosis with vascular review and confirmatory imaging (Best answer)
Weight gain and normal meals followed revascularization, whereas renewed pain about 20 minutes after eating and smaller portions suggest recurrent limitation of postprandial supply. The increase from the postprocedure duplex baseline strengthens concern for restenosis and warrants vascular reassessment with confirmatory imaging. Visible collateral flow does not prove adequate reserve or exclude a symptomatic recurrent lesion.
Reasoning steps for option B
How do the initial response to stenting and the nine-month recurrence relate to arterial inflow?
Weight gain and normal meals followed revascularization, whereas renewed pain about 20 minutes after eating and smaller portions suggest recurrent limitation of postprandial supply.
What does the velocity rise add, and why do visible collaterals not end the workup?
The increase from the postprocedure duplex baseline strengthens concern for restenosis and warrants vascular reassessment with confirmatory imaging. Visible collateral flow does not prove adequate reserve or exclude a symptomatic recurrent lesion.
C. Schedule colectomy based solely on the increased duplex velocity (Why this does not fit)
It is a vascular surveillance finding that raises an arterial question; it does not demonstrate colonic infarction or identify nonviable bowel. The recurrent meal symptoms and changed study call for confirmation of possible arterial restenosis. No colonic tissue finding supplied in the case establishes a resection indication.
Reasoning steps for option C
What does a higher in-stent duplex velocity measure rather than establish about colonic tissue?
It is a vascular surveillance finding that raises an arterial question; it does not demonstrate colonic infarction or identify nonviable bowel.
Why would colectomy based only on this velocity change answer the wrong problem?
The recurrent meal symptoms and changed study call for confirmation of possible arterial restenosis. No colonic tissue finding supplied in the case establishes a resection indication.
D. Wait for rest pain before obtaining additional vascular studies (Why this does not fit)
Pain independent of digestive demand could signal more advanced perfusion impairment, but it is not required before recurrent chronic mesenteric symptoms merit investigation. Meal-related pain has returned with food avoidance and a marked rise in in-stent velocities. Those changes already justify additional vascular assessment rather than waiting for a later or more dangerous presentation.
Reasoning steps for option D
What would new rest pain suggest beyond the currently recurrent postprandial pattern?
Pain independent of digestive demand could signal more advanced perfusion impairment, but it is not required before recurrent chronic mesenteric symptoms merit investigation.
Why is waiting for rest pain unnecessary after this changed surveillance study?
Meal-related pain has returned with food avoidance and a marked rise in in-stent velocities. Those changes already justify additional vascular assessment rather than waiting for a later or more dangerous presentation.
Takeaway: Recurrent meal symptoms after stenting require reassessment even when collaterals remain visible.
A. Repeat routine colonoscopy to obtain a larger mucosal sample before escalation (Why this does not fit)
No. More mucosal tissue can clarify some surface diagnoses, but it does not assess all bowel-wall layers or determine the viability of the entire bowel. They signal clinical deterioration with possible deeper injury, making routine repeat colonoscopy unsafe and potentially delaying. Urgent viability assessment takes priority over another superficial sample.
Reasoning steps for option A
Would a larger mucosal biopsy convert the earlier limited sample into a full-wall viability test?
No. More mucosal tissue can clarify some surface diagnoses, but it does not assess all bowel-wall layers or determine the viability of the entire bowel.
How do new involuntary guarding and rising lactate change the safety of repeating colonoscopy?
They signal clinical deterioration with possible deeper injury, making routine repeat colonoscopy unsafe and potentially delaying. Urgent viability assessment takes priority over another superficial sample.
B. Continue the same plan because the earlier biopsy establishes current bowel viability (Why this does not fit)
It describes the sampled mucosa at the time of collection. It cannot establish the current condition of unsampled layers or rule out progression during the next twelve hours. Worsening pain, involuntary guarding and rising lactate require reassessment for threatened bowel viability. The earlier surface result cannot override a newly deteriorating clinical state.
Reasoning steps for option B
What time and tissue boundaries limit the reassurance from the early biopsy?
It describes the sampled mucosa at the time of collection. It cannot establish the current condition of unsampled layers or rule out progression during the next twelve hours.
Why does continuing the same plan disregard the new examination?
Worsening pain, involuntary guarding and rising lactate require reassessment for threatened bowel viability. The earlier surface result cannot override a newly deteriorating clinical state.
C. Urgently reassess bowel viability because the biopsy did not sample the full wall (Best answer)
The biopsy did not sample the full bowel wall. A negative finding in superficial tissue cannot clear the viability of layers that were never examined. New involuntary guarding, worsening pain and rising lactate indicate deterioration that may reflect deeper or progressing ischemia. Those changes require urgent bowel-viability assessment rather than reassurance from the old mucosal sample.
Reasoning steps for option C
Why does absence of full-thickness necrosis in a mucosal sample not exclude deeper injury?
The biopsy did not sample the full bowel wall. A negative finding in superficial tissue cannot clear the viability of layers that were never examined.
What makes reassessment urgent twelve hours after the initially stable examination?
New involuntary guarding, worsening pain and rising lactate indicate deterioration that may reflect deeper or progressing ischemia. Those changes require urgent bowel-viability assessment rather than reassurance from the old mucosal sample.
D. Exclude ischemia because mucosal injury should cause bleeding before guarding (Why this does not fit)
No. Bleeding is common with mucosal ischemia, but severe or deeper injury may produce little blood; a fixed bleeding-before-guarding sequence is not required. The biopsy already supports ischemic injury, and the new guarding and rising lactate raise concern for progression. An assumed bleeding sequence cannot negate either the tissue evidence or the deteriorating examination.
Reasoning steps for option D
Does ischemic bowel have to produce prominent bleeding before peritoneal findings appear?
No. Bleeding is common with mucosal ischemia, but severe or deeper injury may produce little blood; a fixed bleeding-before-guarding sequence is not required.
What evidence prevents the proposed bleeding rule from excluding ischemia here?
The biopsy already supports ischemic injury, and the new guarding and rising lactate raise concern for progression. An assumed bleeding sequence cannot negate either the tissue evidence or the deteriorating examination.
Takeaway: A superficial sample cannot exclude later or deeper ischemic injury.
A. The response establishes antibiotic effectiveness in all severity categories (Why this does not fit)
No. Several interventions occurred together, and reversible ischemic injury can improve during perfusion correction. This uncontrolled observation cannot identify which component caused recovery. An individual response does not prove a treatment effect, and moderate disease is not evidence of universal benefit in mild or severe disease. Both the causal attribution and the cross-severity generalization exceed the observation.
Reasoning steps for option A
Can improvement during fluids, bowel rest and antibiotics isolate the antibiotic effect?
No. Several interventions occurred together, and reversible ischemic injury can improve during perfusion correction. This uncontrolled observation cannot identify which component caused recovery.
Why does a recovering moderate case not establish effectiveness in every severity category?
An individual response does not prove a treatment effect, and moderate disease is not evidence of universal benefit in mild or severe disease. Both the causal attribution and the cross-severity generalization exceed the observation.
B. The response proves the original disease was infectious rather than ischemic (Why this does not fit)
Some infectious colitides improve with antibiotics, so the treatment response could overlap with infection. The patient also received fluids and bowel rest, which can accompany recovery from reversible ischemia. No. Recovery during combined care does not identify the original cause. Perfusion correction and healing of ischemic injury remain explanations without reclassifying the illness as proven infection.
Reasoning steps for option B
Why might improvement while receiving antibiotics suggest infection without proving it?
Some infectious colitides improve with antibiotics, so the treatment response could overlap with infection. The patient also received fluids and bowel rest, which can accompany recovery from reversible ischemia.
Does the two-day response overturn the diagnosis of moderate colonic ischemia?
No. Recovery during combined care does not identify the original cause. Perfusion correction and healing of ischemic injury remain explanations without reclassifying the illness as proven infection.
C. The low certainty of evidence establishes that antibiotics have no role in severe disease (Why this does not fit)
It limits confidence in the estimated benefit. It does not demonstrate that antibiotics are ineffective or establish that they have no role. The ACG guidance still supports antibiotic consideration in moderate or severe colonic ischemia despite very low-quality evidence. Uncertainty about benefit cannot be reversed into proof of futility in severe disease.
Reasoning steps for option C
What does very low-certainty evidence mean about the claim of antibiotic benefit?
It limits confidence in the estimated benefit. It does not demonstrate that antibiotics are ineffective or establish that they have no role.
How does that distinction apply to the proposed dismissal of antibiotics in severe disease?
The ACG guidance still supports antibiotic consideration in moderate or severe colonic ischemia despite very low-quality evidence. Uncertainty about benefit cannot be reversed into proof of futility in severe disease.
D. The combined-care response cannot establish a universal antibiotic mortality benefit (Best answer)
The claim assigns recovery under several simultaneous treatments to antibiotics alone and extrapolates from one moderate case to all mild cases. Neither inference is established by the observed improvement. The recommendation supports considering antibiotics in moderate or severe disease on very low-quality evidence. It does not establish a universal mortality benefit in mild ischemic colitis, and this combined-care response cannot supply that proof.
Reasoning steps for option D
Which two inferential leaps are present in the claim that antibiotics prevent death in every mild case?
The claim assigns recovery under several simultaneous treatments to antibiotics alone and extrapolates from one moderate case to all mild cases. Neither inference is established by the observed improvement.
What does the guideline recommendation support without proving that universal mortality claim?
The recommendation supports considering antibiotics in moderate or severe disease on very low-quality evidence. It does not establish a universal mortality benefit in mild ischemic colitis, and this combined-care response cannot supply that proof.
Takeaway: An individual combined-treatment response does not prove a universal mortality benefit.
A. Acute embolic occlusion of the proximal SMA (Why this does not fit)
An embolus can abruptly interrupt mesenteric arterial inflow and cause acute ischemia. That is different from progressive obstructive symptoms arising weeks after recovery. The short stenotic segment is at the previous injury site six weeks later, with upstream dilation and no new hypoenhancement or pneumatosis. That continuity favors a healing complication over a new acute proximal SMA event.
Reasoning steps for option A
What time course would a new proximal SMA embolus more naturally produce?
An embolus can abruptly interrupt mesenteric arterial inflow and cause acute ischemia. That is different from progressive obstructive symptoms arising weeks after recovery.
How do the same left-colon location and fixed narrowing weigh against a new SMA embolus?
The short stenotic segment is at the previous injury site six weeks later, with upstream dilation and no new hypoenhancement or pneumatosis. That continuity favors a healing complication over a new acute proximal SMA event.
B. Reversible smooth-muscle spasm without structural change (Why this does not fit)
The scan shows a fixed short narrowing with dilation upstream, indicating an objective structural obstruction rather than just intermittent functional contraction. Injury can heal with a narrowing at the damaged site. The progressive constipation and distension after that episode warrant evaluation of a structural sequela rather than dismissal as reversible spasm.
Reasoning steps for option B
What feature distinguishes the CT abnormality from transient smooth-muscle spasm?
The scan shows a fixed short narrowing with dilation upstream, indicating an objective structural obstruction rather than just intermittent functional contraction.
Why does prior ischemia at exactly that segment strengthen the structural interpretation?
Injury can heal with a narrowing at the damaged site. The progressive constipation and distension after that episode warrant evaluation of a structural sequela rather than dismissal as reversible spasm.
C. Fibrotic remodeling of the injured colonic segment (Best answer)
Fibrotic remodeling of the injured segment can produce an ischemic stricture, narrowing the lumen even after the original perfusion disturbance has resolved. The six-week interval, narrowing at the previously injured segment and upstream dilation fit a healing stricture. Further evaluation still needs to exclude alternative causes of the structural narrowing.
Reasoning steps for option C
What healing process can leave a fixed narrowed lumen weeks after colonic ischemia?
Fibrotic remodeling of the injured segment can produce an ischemic stricture, narrowing the lumen even after the original perfusion disturbance has resolved.
Which observations connect that remodeling to the current obstruction without proving it is the only possible cause?
The six-week interval, narrowing at the previously injured segment and upstream dilation fit a healing stricture. Further evaluation still needs to exclude alternative causes of the structural narrowing.
D. Immediate mucosal edema from the original transient hypotension (Why this does not fit)
Acute mucosal edema can narrow the lumen during the initial ischemic injury, when swelling is part of the immediate response. The delayed fixed narrowing at the prior injury site fits structural remodeling more closely than the original acute swelling. The time course distinguishes a healing complication from the transient insult itself.
Reasoning steps for option D
When would edema from the original hypotensive episode most directly narrow the bowel lumen?
Acute mucosal edema can narrow the lumen during the initial ischemic injury, when swelling is part of the immediate response.
Why is immediate edema a weaker explanation after six weeks of recovery and progressive obstruction?
The delayed fixed narrowing at the prior injury site fits structural remodeling more closely than the original acute swelling. The time course distinguishes a healing complication from the transient insult itself.
Takeaway: Persistent or delayed obstructive symptoms after colonic ischemia need evaluation for stricture and alternative pathology.
A. Targeted evaluation for thrombophilia and other unusual ischemic causes (Best answer)
The patient is 36, has two confirmed episodes within a year and has no major mesenteric atherosclerosis or clear hypotensive or drug trigger. The usual supplied explanations have not accounted for recurrence. Targeted evaluation for thrombophilia and other unusual ischemic causes is appropriate to consider. Confirmation of ischemic injury does not itself establish why a young patient has repeated episodes.
Reasoning steps for option A
Which features make this recurrent ischemic disorder atypical for an assumed atherosclerotic cause?
The patient is 36, has two confirmed episodes within a year and has no major mesenteric atherosclerosis or clear hypotensive or drug trigger. The usual supplied explanations have not accounted for recurrence.
What etiologic question remains after stabilization and exclusion of infection and inflammatory bowel disease?
Targeted evaluation for thrombophilia and other unusual ischemic causes is appropriate to consider. Confirmation of ischemic injury does not itself establish why a young patient has repeated episodes.
B. Repeat the same arterial imaging before considering a systemic cause (Why this does not fit)
A new vascular concern or technical limitation could justify another study. Neither is supplied, and the existing CTA has shown no major mesenteric atherosclerotic target. Young age and recurrent confirmed injury remain unexplained despite the arterial assessment. Testing should address that etiologic gap rather than postpone it until the same vascular study has been repeated.
Reasoning steps for option B
When would repeating arterial imaging add useful evidence beyond a prior adequate CTA?
A new vascular concern or technical limitation could justify another study. Neither is supplied, and the existing CTA has shown no major mesenteric atherosclerotic target.
Why should identical arterial imaging not be a prerequisite to considering a systemic cause now?
Young age and recurrent confirmed injury remain unexplained despite the arterial assessment. Testing should address that etiologic gap rather than postpone it until the same vascular study has been repeated.
C. Long-term anti-inflammatory treatment without revisiting the tissue diagnosis (Why this does not fit)
It would require an established inflammatory diagnosis that warrants that treatment. The supplied evaluations excluded inflammatory bowel disease and supported ischemic injury. Uncertainty about the cause of recurrence does not undo the tissue diagnosis or establish a previously excluded disorder. Etiologic evaluation should follow the confirmed recurrent ischemia rather than assume inflammation.
Reasoning steps for option C
What diagnostic support would long-term anti-inflammatory treatment for bowel disease require?
It would require an established inflammatory diagnosis that warrants that treatment. The supplied evaluations excluded inflammatory bowel disease and supported ischemic injury.
Why does an unexplained ischemic cause not justify substituting chronic inflammatory treatment?
Uncertainty about the cause of recurrence does not undo the tissue diagnosis or establish a previously excluded disorder. Etiologic evaluation should follow the confirmed recurrent ischemia rather than assume inflammation.
D. Deferral of further assessment until a proximal arterial occlusion appears (Why this does not fit)
No. A new major-vessel lesion would be important if it developed, but its absence does not explain or negate the recurrent confirmed colonic injury. Two unexplained episodes at age 36 after exclusion of infection and inflammatory bowel disease warrant consideration of unusual causes. A proximal occlusion is not a prerequisite for that investigation.
Reasoning steps for option D
Would waiting for a proximal arterial occlusion explain the two episodes that have already occurred?
No. A new major-vessel lesion would be important if it developed, but its absence does not explain or negate the recurrent confirmed colonic injury.
Which existing features justify reassessment before any large-vessel obstruction appears?
Two unexplained episodes at age 36 after exclusion of infection and inflammatory bowel disease warrant consideration of unusual causes. A proximal occlusion is not a prerequisite for that investigation.
Takeaway: Young or recurrent unexplained colonic ischemia merits an individualized search for unusual causes.
A. Moderate remains moderate because the distribution is still left-sided (Why this does not fit)
It avoids an isolated right-colon severe-feature designation, but it does not override the separate rule that more than three poor-outcome factors indicate severe disease. It adds a fourth factor to persistent tachycardia, elevated BUN and low sodium. The category therefore crosses from moderate to severe despite remaining left-sided.
Reasoning steps for option A
What protection does a left-sided distribution provide against the factor-count criterion for severe disease?
It avoids an isolated right-colon severe-feature designation, but it does not override the separate rule that more than three poor-outcome factors indicate severe disease.
How does WBC 17,000 change the count even though the involved territory is unchanged?
It adds a fourth factor to persistent tachycardia, elevated BUN and low sodium. The category therefore crosses from moderate to severe despite remaining left-sided.
B. Moderate becomes severe, requiring urgent escalation assessment (Best answer)
Pulse 108/min is above 100, BUN 25 mg/dL is above 20, and sodium 134 mmol/L is below 136. Those three factors support moderate disease without a severe feature. The WBC is now above 15,000, giving four persistent factors. More than three crosses the severe boundary and requires urgent escalation assessment, without by itself proving gangrene.
Reasoning steps for option B
Which ACG thresholds are crossed before the WBC rises?
Pulse 108/min is above 100, BUN 25 mg/dL is above 20, and sodium 134 mmol/L is below 136. Those three factors support moderate disease without a severe feature.
What does adding WBC 17,000/microliter require on reassessment?
The WBC is now above 15,000, giving four persistent factors. More than three crosses the severe boundary and requires urgent escalation assessment, without by itself proving gangrene.
C. Mild becomes moderate because only the new WBC result should be counted (Why this does not fit)
No. Tachycardia, BUN above 20 and sodium below 136 already supplied three qualifying factors, so the initial category was moderate. The stem states the other findings are unchanged, so all three original factors persist. The current count is four, not one, making the new category severe rather than moderate.
Reasoning steps for option C
Was the initial profile mild before leukocytosis developed?
No. Tachycardia, BUN above 20 and sodium below 136 already supplied three qualifying factors, so the initial category was moderate.
Why cannot the newest WBC result be counted while the initial abnormalities are ignored?
The stem states the other findings are unchanged, so all three original factors persist. The current count is four, not one, making the new category severe rather than moderate.
D. Severe becomes proven gangrenous disease, establishing a resection requirement (Why this does not fit)
It changes the classification from moderate to severe and signals the need for urgent assessment. It is a risk boundary, not a histologic or operative finding of gangrene. Leukocytosis plus the other factors does not prove irreversible tissue death or determine its location. Viability and the need for intervention require assessment beyond the factor count.
Reasoning steps for option D
What does the new fourth poor-outcome factor establish about severity?
It changes the classification from moderate to severe and signals the need for urgent assessment. It is a risk boundary, not a histologic or operative finding of gangrene.
Why does the WBC rise not identify bowel that must be resected?
Leukocytosis plus the other factors does not prove irreversible tissue death or determine its location. Viability and the need for intervention require assessment beyond the factor count.
Takeaway: A change from three to four ACG factors crosses a severity boundary without itself proving gangrene.
Restoring celiac flow can improve foregut inflow, and the artery may be an appropriate revascularization target in symptomatic disease. Guidelines generally prioritize the SMA for symptomatic chronic mesenteric ischemia. A relevant celiac lesion can be an additional treatment target without displacing that usual primary choice.
Reasoning steps for option A
Why is the diseased celiac artery a relevant vessel even though it is not the usual first target here?
Restoring celiac flow can improve foregut inflow, and the artery may be an appropriate revascularization target in symptomatic disease.
What prioritization applies when both the celiac artery and SMA are feasible but only one is restored first?
Guidelines generally prioritize the SMA for symptomatic chronic mesenteric ischemia. A relevant celiac lesion can be an additional treatment target without displacing that usual primary choice.
B. Inferior mesenteric artery (Why this does not fit)
The IMA supplies left-colon territory and contributes collateral flow, so it is part of the mesenteric network. The described syndrome calls for restoring the dominant intestinal inflow supplied by the SMA. Left-colon collateral contribution does not make the IMA the usual first target for these two severe ostial lesions.
Reasoning steps for option B
Which bowel territory and collateral function make the IMA relevant to intestinal circulation?
The IMA supplies left-colon territory and contributes collateral flow, so it is part of the mesenteric network.
Why does that role not make the IMA the usual primary target for this symptomatic celiac and SMA disease?
The described syndrome calls for restoring the dominant intestinal inflow supplied by the SMA. Left-colon collateral contribution does not make the IMA the usual first target for these two severe ostial lesions.
C. Superior mesenteric artery (Best answer)
The SMA supplies most small bowel and the right and proximal transverse colon, giving it a major role in intestinal perfusion during digestion. The SMA is the usual principal revascularization target in symptomatic chronic mesenteric ischemia. Its broad intestinal inflow role supports prioritizing it over the celiac artery in the stated plan.
Reasoning steps for option C
Which major intestinal territory explains the SMA's importance for meal-related demand?
The SMA supplies most small bowel and the right and proximal transverse colon, giving it a major role in intestinal perfusion during digestion.
How does that role guide the one-vessel-first plan when celiac and SMA treatment are both feasible?
The SMA is the usual principal revascularization target in symptomatic chronic mesenteric ischemia. Its broad intestinal inflow role supports prioritizing it over the celiac artery in the stated plan.
D. Internal iliac artery (Why this does not fit)
Pelvic branches contribute supplemental rectal arterial supply, helping explain relative rectal preservation during some colonic low-flow injuries. The symptomatic lesions are in the celiac artery and SMA, and the broader intestinal demand problem is not corrected by treating pelvic rectal inflow. The usual primary target remains the SMA, not an internal iliac artery.
Reasoning steps for option D
What intestinal protection can internal iliac branches provide?
Pelvic branches contribute supplemental rectal arterial supply, helping explain relative rectal preservation during some colonic low-flow injuries.
Why does rectal collateral supply not make the internal iliac artery the first target for this meal-pain syndrome?
The symptomatic lesions are in the celiac artery and SMA, and the broader intestinal demand problem is not corrected by treating pelvic rectal inflow. The usual primary target remains the SMA, not an internal iliac artery.
Takeaway: The SMA is the usual primary target in symptomatic chronic mesenteric revascularization.
A. Colitis on CT with an unresolved cause requiring further evaluation (Best answer)
It supports colitis but is not specific for ischemia. Ischemic, infectious and inflammatory injury can produce overlapping wall changes. It supplies a plausible competing cause that should remain under consideration. Clinical and microbiologic evidence, with endoscopic assessment when safe and appropriate, can clarify etiology rather than treating the CT pattern as proof of ischemia.
Reasoning steps for option A
What does segmental thickening with preserved enhancement establish about the bowel?
It supports colitis but is not specific for ischemia. Ischemic, infectious and inflammatory injury can produce overlapping wall changes.
How should the infectious exposure affect the remaining workup despite an ischemia-compatible symptom sequence?
It supplies a plausible competing cause that should remain under consideration. Clinical and microbiologic evidence, with endoscopic assessment when safe and appropriate, can clarify etiology rather than treating the CT pattern as proof of ischemia.
B. Ischemic colitis confirmed by the segmental pattern of wall thickening (Why this does not fit)
No. Both can produce segmental wall thickening, so the finding is compatible with ischemia without being specific for it. The recent infectious exposure offers a competing explanation for cramping and bloody diarrhea. That alternative remains to be assessed rather than excluded by nonspecific CT distribution.
Reasoning steps for option B
Can segmental thickening distinguish ischemic from infectious colitis by itself?
No. Both can produce segmental wall thickening, so the finding is compatible with ischemia without being specific for it.
Which supplied history makes premature assignment of an ischemic cause especially problematic?
The recent infectious exposure offers a competing explanation for cramping and bloody diarrhea. That alternative remains to be assessed rather than excluded by nonspecific CT distribution.
C. Colonic ischemia excluded by patency of the major mesenteric arteries (Why this does not fit)
The scan shows no major mesenteric arterial occlusion, but colonic hypoperfusion can cause mucosal ischemia without a visible large-vessel blockage. No. Those findings do not exclude a transient or smaller-vessel low-perfusion process. They cannot settle the ischemic versus infectious differential on their own.
Reasoning steps for option C
Which vascular mechanism is absent from the scan, and which ischemic mechanism can still occur?
The scan shows no major mesenteric arterial occlusion, but colonic hypoperfusion can cause mucosal ischemia without a visible large-vessel blockage.
Does stable pressure at assessment plus open arteries prove that perfusion-related injury did not occur?
No. Those findings do not exclude a transient or smaller-vessel low-perfusion process. They cannot settle the ischemic versus infectious differential on their own.
D. Infectious colitis confirmed by the preserved bowel-wall enhancement (Why this does not fit)
No. Infection can have preserved enhancement, but reversible ischemic injury can also retain enhancement. The exposure makes infection plausible, not established by the enhancement pattern. Etiologic correlation is still required because the imaging features overlap with noninfectious colitis.
Reasoning steps for option D
Does preserved enhancement identify infection uniquely in an edematous colonic segment?
No. Infection can have preserved enhancement, but reversible ischemic injury can also retain enhancement.
What remains unproven even when an infectious exposure accompanies that CT finding?
The exposure makes infection plausible, not established by the enhancement pattern. Etiologic correlation is still required because the imaging features overlap with noninfectious colitis.
Takeaway: Nonspecific colonic CT findings need etiologic correlation even when symptoms suggest ischemia.