Separate slowed bowel propulsion from a physical blockage, identify reversible contributors, and choose feeding, decompression or colon-specific treatment safely.
Is the road blocked, or has the conveyor stopped? Both problems can produce vomiting and a swollen abdomen. This lesson separates a physical obstruction from reduced propulsion, then asks which reversible factor is keeping the bowel from working. The activities let you change one finding at a time without racing a clock.
Four swollen abdomens, four different decisions
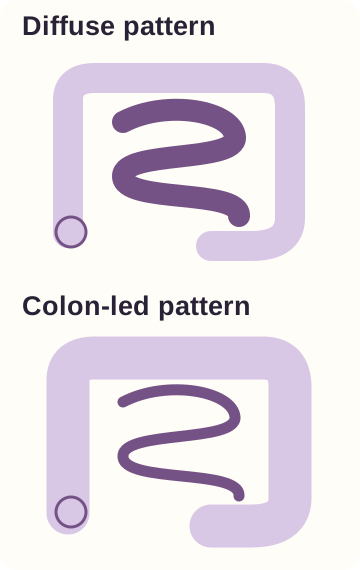
Ileus describes impaired coordinated intestinal propulsion without a focal mechanical barrier. After surgery, the small bowel and colon may both appear dilated. In contrast, a mechanical obstruction usually produces a more localized transition between dilated upstream bowel and relatively decompressed downstream bowel. The overlap can be confusing, especially early after an operation. CT can help resolve that uncertainty. [1][4][5]
Do not make every motility problem the same diagnosis
Acute colonic pseudo-obstruction, also called Ogilvie syndrome, predominantly affects the colon without a mechanical obstructing lesion. It often occurs during severe illness or after surgery or trauma. A very dilated cecum in a patient recovering from a hip fracture deserves a different assessment from diffuse postoperative small- and large-bowel dilation. [2]
Toxic megacolon adds severe colonic inflammation and systemic toxicity. A patient with bloody diarrhea, fever, tachycardia, tenderness, and a dilated inflamed colon does not belong on an uncomplicated ileus pathway. Neither a stimulant laxative nor routine neostigmine is a substitute for urgent management of the inflammatory emergency. [6]
Generalized ileus
Broadly impaired propulsion. Search for postoperative, medication, metabolic, or illness-related contributors. [1][5]
Mechanical obstruction
A barrier and transition change the diagnostic and surgical questions. [4]
Colonic pseudo-obstruction
Predominantly colonic dilation without a mechanical lesion. [2]
Toxic megacolon
Inflamed dilated colon with systemic toxicity requires an urgent disease-specific plan. [6]
Start with distribution and context. The word distention is a finding, not a complete diagnosis. [2][4]
Find the factors holding propulsion back
The bowel depends on coordinated neural and muscular activity. Surgery and the postoperative response can disrupt that coordination. Opioids act at intestinal mu-opioid receptors and slow transit. Anticholinergic drugs can further impair motility. When several contributors occur together, correcting only one may not restore useful bowel function. [1][2][3]
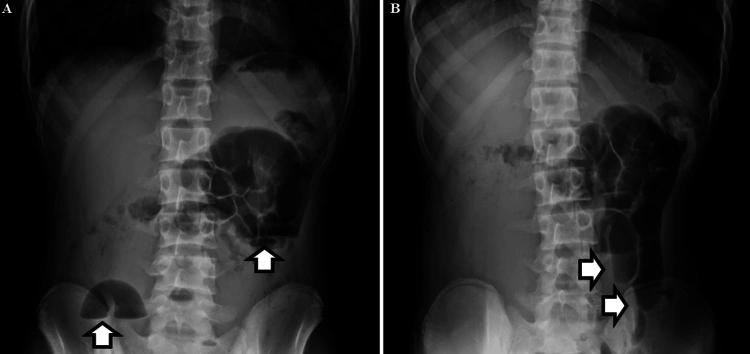
These radiographs come from a published ileus case. Gas and air-fluid levels can also occur without a focal mechanical barrier. Original source arrows are retained; none were added here.
Shiori Ouchida, Reiko Saito, Nao Ohama, Mami Kuwamura, Reiji Fukano, Alexander Muacevic, John R Adler. CC BY 4.0. Source and provenance
Review the medicine list and the illness
A patient who needs morphine after abdominal surgery and has potassium depletion has more than a postoperative date on the chart. The opioid and electrolyte disorder are treatable contributors. Review anticholinergic exposure, hydration, potassium, and magnesium, while investigating infection or another illness when the clinical course suggests it. Do not stop pain relief indiscriminately; use an effective opioid-sparing plan when feasible. [1][2]
Severe infection, organ dysfunction, injury, and immobility can accompany intestinal dysmotility. Those associations are particularly important in acute colonic pseudo-obstruction. Treat the underlying illness rather than assuming that a bowel-directed drug will solve sepsis, pneumonia, or metabolic derangement. At the same time, an ill patient can also develop mechanical obstruction, so the presence of a plausible motility trigger does not end the diagnostic assessment. [2][4][7]
Medication effect
Review opioids and anticholinergic drugs while preserving appropriate symptom control. [1][2]
Metabolic contribution
Correct relevant electrolyte and volume abnormalities and recheck the response. [2]
Underlying illness
Look for infection, injury, or organ dysfunction that sustains the motility problem. [7]
Think of several brakes, not one switch. Review medication, metabolic state, and the patient's illness together. [1][2]
Reassess when the course stops fitting
Postoperative does not automatically mean ileus. A new focal transition, collapsed distal bowel, a trapped loop, or worsening peritoneal signs should reopen the diagnosis. CT is useful when symptoms and plain films cannot distinguish ileus from mechanical obstruction. A previous reassuring assessment is not a permanent explanation for a changing abdomen. [4][8]
The term postoperative gastrointestinal dysfunction covers a spectrum, and definitions have varied across studies. A fixed rule that every bowel compartment must recover at exactly the same number of hours is not a reliable decision tool. Review oral tolerance, vomiting, distention, pain, stool or flatus, hydration, and the overall trajectory. Persistent or worsening dysfunction deserves reassessment instead of repeatedly resetting a waiting period. [5]
Bowel sounds are not a dependable permission slip for feeding or discharge. Similarly, gas in the rectum does not exclude every early or partial mechanical obstruction. The useful question is whether the complete pattern supports improving propulsion, a continuing barrier, or a complication that needs investigation. This is why serial clinical review matters even when an initial image seemed compatible with ileus. [1][4][8]
Improving pattern
Less vomiting and distention, better intake, and stable physiology support recovery in context. [1][5]
Changed pattern
New focal pain, guarding, a transition, poor enhancement, or systemic deterioration requires a new assessment. [4][8]
The label must fit today's findings. Do not use yesterday's ileus diagnosis to dismiss a new obstruction or infection. [4][8]

 Enlarge the whole image
 Enlarge the whole image
 Enlarge the whole image