
Choose an answer, then open any option to work its reasoning.
MSK · Neuromuscular Junction
MG vs LEMS vs Botulism: The Neuromuscular Junction Discriminator
Fatigable or facilitating? Myasthenia gravis tires with use, Lambert-Eaton gets stronger with it, and botulism descends without stopping. One junction, three defects, and a handful of bedside tests that separate them before the crisis: the ice pack, the handshake, the pupils, the antibody, the trace, and the antitoxin clock.
What this page makes you able to do
- Read a fatigable or facilitating weakness pattern and name the junction defect
- Run the bedside split: ice pack, handshake, pupils, and the Tensilon test
- Read the repetitive-stimulation trace: decrement (MG) versus increment (LEMS)
- Triage the crisis and the descending paralysis: ICU with IVIG or PLEX, atropine, and antitoxin on suspicion
- Dr. Fatima Ali, DOPsychiatry residentPrimary reviewer
Last reviewed
The pearl
Fatigable with use is postsynaptic (MG): ice lifts the ptosis, 3 Hz stimulation decrements, and anti-AChR names it. Facilitating with use is presynaptic (LEMS): the handshake strengthens, high-rate stimulation increments, and anti-VGCC points at small cell lung cancer. Descending, symmetric, bulbar-first paralysis with dilated pupils is botulism until proven otherwise, and the antitoxin never waits for the culture.
Prove it
Opening question
Answer before you read anything, then keep the fatigable-facilitating reflex and the pupil check in mind through every section.
A 34-year-old woman comes to the office because of 4 months of double vision that appears when she is tired and a right eyelid that droops by evening. She reports trouble swallowing pills and says her jaw tires when she chews meat. Examination shows right ptosis that worsens after 60 seconds of sustained upgaze and improves after a minute of rest; pupils are equal and reactive; reflexes are 2+. Laboratory studies, including serum creatine kinase, are within normal limits.Which of the following is the most likely diagnosis?
- Why this is rightWeakness that worsens with sustained use and recovers with rest, worse at the end of the day, with spared pupils, is the myasthenia gravis signature. The ptosis fatigues on upgaze, the jaw tires with chewing, and the pupils stay normal because MG spares the pupillary muscles. Rule: fatigable, fluctuating, pupil-sparing weakness is MG until proven otherwise.
- Why this failsLEMS is the mirror image: weakness improves with repetition, starts in the proximal legs, and brings autonomic dryness. This patient gets weaker with use, starts in the eyes, and has no dry mouth. Rule: LEMS facilitates; MG fatigues.
- Why this failsBotulism is acute, symmetric, and descending, bulbar first, with dilated unreactive pupils and an exposure story. Four months of evening fluctuation with reactive pupils is the wrong tempo and the wrong pupil. Rule: botulism descends and dilates; this story fluctuates and spares.
- Why this failsA third nerve palsy brings a dilated pupil with the eye down and out, no fatigability, and no fluctuation. Bilateral fluctuating symptoms with equal reactive pupils are not third nerve territory. Rule: pupil-sparing and fluctuating means not a third nerve palsy.
Work the reasoning
Postsynaptic receptor loss means the margin of safety is gone: with rest the muscle transmits, with use it fails, so symptoms cycle with the day. Fatigable ptosis that recovers with rest is the MG fingerprint.
MG spares the pupillary muscles; botulism and third nerve palsy do not. Equal reactive pupils with fatigable ptosis push the differential hard toward the junction, not the nerve or the toxin.
Anti-AChR antibodies are positive in about 85% of generalized MG, the ice pack test improves the ptosis, and electrodiagnostics (decrement at 3 Hz, single-fiber jitter) catch the rest. Every MG patient also gets a CT of the chest to screen for thymoma.
The answer is A: myasthenia gravis. Fatigable, fluctuating, pupil-sparing weakness is the MG signature, and the workup is anti-AChR antibodies, the ice test, electrodiagnostics, and a CT chest for thymoma.
THE FATIGABLE FACE
The Fatigable Face: Myasthenia Gravis
Antibodies against the postsynaptic acetylcholine receptor shrink the margin of safety, so every nerve impulse lands on fewer receptors and the muscle gives out as the day goes on. Learn the pattern, then prove it with the ice pack, the antibody, and the trace.
Myasthenia gravis is the postsynaptic disease: anti-acetylcholine receptor (AChR) IgG blocks and destroys receptors on the motor end plate, so the end plate potential barely crosses threshold. Repeated firing cannot keep the muscle above threshold, and that is why weakness worsens with repetitive use and improves with rest, classically worst by evening. The pattern announces itself: ptosis and diplopia first (the lid may alternate sides and fall on sustained upgaze), then bulbar trouble (dysarthria, dysphagia, nasal voice, jaw fatigue with chewing), then proximal limb weakness (arms fail while blow-drying hair, legs give out on stairs). Reflexes stay normal, and the pupils are always spared, your first cut against botulism and third nerve palsy.
The workup is four tests with one question. The ice pack test: ice on the closed ptotic lid for 2 minutes; cold slows acetylcholinesterase, so more acetylcholine survives to hit the remaining receptors and the ptosis lifts in most ocular MG. Antibodies: anti-AChR is positive in about 85% of generalized and 50% of ocular MG; anti-MuSK and anti-LRP4 cover many seronegative cases, and a negative antibody never excludes the disease. The Tensilon test: edrophonium, a short-acting acetylcholinesterase inhibitor, transiently improves MG weakness within seconds, worsens cholinergic crisis, and barely moves Lambert-Eaton. Electrodiagnostics: repetitive nerve stimulation at 3 Hz shows a decremental response, and single-fiber EMG shows increased jitter, the most sensitive test of all. Every generalized MG patient gets a CT of the chest: thymoma changes management, and anti-AChR-positive patients improve with thymectomy even without a tumor.
Treatment starts with pyridostigmine 30 to 60 mg every 4 to 6 hours, the long-acting oral acetylcholinesterase inhibitor. Inadequate response adds corticosteroids, then steroid-sparing agents (azathioprine or mycophenolate); crisis gets IVIG or plasmapheresis; thymoma gets thymectomy.
Flip between the two weakness directions until the reflex is instant.

THE ANTIBODY SPLIT
The Antibody Split: Who Carries Which Marker
Each disease in this trio is named by a different molecule, and the molecule tells you where the junction broke: postsynaptic receptor, presynaptic calcium channel, or SNARE machinery.
Boards hand you the antibody yield like a password. Myasthenia gravis: anti-AChR in about 85% of generalized and 50% of ocular disease; seronegative patients split into anti-MuSK (bulbar-predominant, often young women) and anti-LRP4. The thymus is the engine: thymoma in about 10 to 15%, classically in the bimodal MG peaks, young women and older men, and every generalized MG patient gets a chest CT with thymectomy when a tumor is found, because the tumor and the junction disease improve together.
Lambert-Eaton carries anti-voltage-gated calcium channel (VGCC, P/Q-type) antibodies, the presynaptic marker: calcium entry fails, so the first squeeze is weak and facilitation needs high-frequency firing to pool calcium. The marker is also the cancer clue: SCLC cells display the same channels, so the antibody that weakens the legs is the antibody that found the tumor.
Botulism carries no antibody at all. The disease is a toxin that cleaves SNARE proteins (SNAP-25, VAMP, syntaxin), so the vesicle cannot fuse and no acetylcholine is released. No autoantibody, no chronic fluctuation, no thymus: the diagnosis comes from the exposure and the descending pattern, and the treatment is antitoxin on suspicion.
Commit to the antibody from the presentation.
A 58-year-old man with a 40 pack-year smoking history has 5 months of proximal leg weakness that improves after he climbs a few stairs, plus a persistently dry mouth. Examination shows hyporeflexia. Which serum antibody finding is most likely to be positive?
A. Anti-VGCC antibodies. Facilitating proximal weakness, hyporeflexia, and autonomic dryness in a smoker is Lambert-Eaton: the presynaptic calcium channel is the target, and the same antibody story points at small cell lung cancer, so chest imaging follows. B. Anti-AChR. That is the postsynaptic marker of MG, whose weakness fatigues with use rather than improving. C. Anti-MuSK. A seronegative-MG marker with bulbar-predominant weakness, not a facilitating leg syndrome. D. Anti-SS-A. Sjogren syndrome explains dry mouth but not facilitation, hyporeflexia, or a smoking history. Rule: legs that strengthen with use plus a dry mouth in a smoker is anti-VGCC until proven otherwise, and the chest CT comes next.
THE NMJ MAP
The NMJ Map: Presynaptic, Cleft, Postsynaptic
One junction, three defects, three diseases. Place the lesion on the map and the diagnosis follows: the nerve terminal, the cleft, or the muscle-side receptor.
The neuromuscular junction is a three-part machine. On the presynaptic side, an action potential opens voltage-gated calcium channels, calcium floods in, and synaptic vesicles fuse with the membrane through SNARE proteins (VAMP on the vesicle; SNAP-25 and syntaxin on the membrane) to spill acetylcholine into the cleft. In the cleft, acetylcholinesterase chews the transmitter down, which is exactly the enzyme the treatment drugs inhibit. On the postsynaptic folds, acetylcholine binds receptors that open channels and raise the end plate potential toward threshold.
Now place the diseases. MG is postsynaptic: anti-AChR antibodies block and destroy the receptors, so the end plate potential shrinks and fails with repetition, while the cleft enzyme keeps chewing. LEMS is presynaptic but upstream: anti-VGCC antibodies cut calcium entry, so the first impulse releases too little acetylcholine, and only high-frequency firing lets calcium accumulate and facilitate. Botulism is presynaptic but at the fuse: the toxin cleaves the SNARE proteins, so even a calcium flood cannot fuse a vesicle; acetylcholine release stops entirely, which is why the paralysis is fixed and the pupils dilate (autonomic cholinergic transmission dies too). The map also explains the tests: acetylcholinesterase inhibitors rescue MG (more transmitter reaches surviving receptors), barely touch LEMS (the transmitter was never released), and do nothing for botulism (there is no transmitter to save).
Tap each zone of the junction and read which disease lives there.
Tap a region.
THE FACILITATING LEGS
Lambert-Eaton: The Facilitating Legs
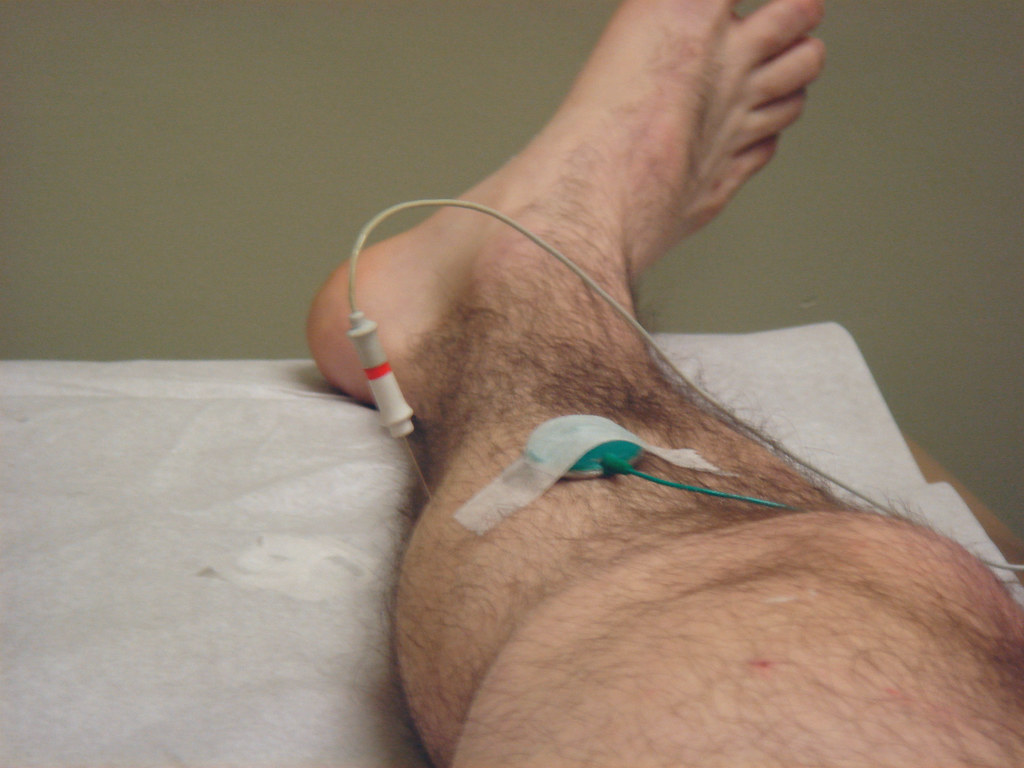
The mirror image of MG: anti-VGCC antibodies starve the presynaptic terminal of calcium, so the first squeeze is weak. Every squeeze pools a little more calcium, and by the fourth rep the muscle is stronger.
Lambert-Eaton myasthenic syndrome is the presynaptic disease, and its signature is the opposite of MG: weakness that improves with repetition. The legs go first, proximal more than distal, so the patient struggles to rise from a chair and then climbs the next flight better. The handshake strengthens by the third or fourth squeeze, and the reflexes are hypoactive or absent yet briefly return after exercise, because the reflex facilitates just like the muscle. Autonomic cholinergic transmission is presynaptic too, so the board package includes dry mouth, dry eyes, constipation, and erectile dysfunction; ptosis and diplopia can appear but stay less prominent than in MG, and the pupils may be sluggish, never the fixed dilated pupils of botulism.
The cancer link is the emergency inside the diagnosis: LEMS is paraneoplastic in about half of patients, driven by small cell lung cancer, whose cells display the same voltage-gated calcium channels the immune system is attacking. Every new LEMS patient gets chest imaging, and the neurologic syndrome can precede the cancer by months. Treatment is 3,4-diaminopyridine (amifampridine), typically started at 5 to 10 mg three times daily: it blocks potassium channels, prolongs the action potential, and lets more calcium enter with each impulse. Treat the underlying cancer, and use IVIG or plasmapheresis for refractory paraneoplastic disease.
Tick every facilitating feature and read where the picture lands.
Checked 0
THE DESCENDING FLOP
Botulism: The Descending Flop
Botulinum toxin is a protease that severs the SNARE machinery, so vesicles cannot fuse and acetylcholine release stops. The result is a symmetric, descending, flaccid paralysis that starts at the top, and the antitoxin never waits for the culture.
Botulism is poisoning of the fuse. The toxin cleaves SNAP-25, VAMP, and syntaxin, the SNARE proteins that dock synaptic vesicles to the membrane, so no acetylcholine is released anywhere: skeletal muscle flops and the autonomic system goes dry. The exam signature is symmetric descending paralysis, bulbar first: diplopia, ptosis, dysphagia, and dysarthria, then neck and arm weakness, then the diaphragm, with no fever and no sensory loss. Autonomic blockade shows up as dilated unreactive pupils, dry mouth, constipation, and urinary retention, the pupil finding that MG never makes.
Three forms, three vehicles. Infant botulism (3 weeks to 6 months): spores germinate in the immature gut and release toxin in vivo; constipation first, then weak cry, poor feeding, drooling, and progressive hypotonia, classically with honey on the pacifier. Treatment is supportive care plus human botulism immune globulin (BabyBIG), and honey stays banned under 12 months. Foodborne botulism: preformed toxin from improperly canned food, with nausea, vomiting, and cramps 12 to 36 hours after the meal before the neurologic syndrome descends. Wound botulism: Clostridium botulinum grows in devitalized tissue, classically at an injection site in a drug user, 4 to 14 days before the same descending weakness; treatment adds surgical debridement because the infected tissue keeps making toxin until it is gone.
The one clock that matters: botulinum antitoxin (heptavalent, types A through G) is given on clinical suspicion, never deferred for culture or toxin assay, because it only neutralizes circulating toxin and every hour lets more dock at the junction. Supportive care in the ICU with intubation when the diaphragm fails completes the treatment.
Put the botulism clock in order.

THE CRISIS SPLIT
The Crisis Split: Myasthenic vs Cholinergic
The MG patient who arrives unable to breathe is either under-treated or over-treated. Learn the bedside split, because the treatments are opposite and the wrong one is lethal.
Myasthenic crisis is the disease winning: infection, surgery, or a missed dose pushes weakness to respiratory failure, with progressive dyspnea, a weak cough, shallow breathing, and pooling secretions. Edrophonium improves myasthenic crisis. Treatment is the ICU with IVIG or plasmapheresis, serial vital capacity and negative inspiratory force monitoring, and intubation before fatigue wins; corticosteroids are added once the patient can tolerate them, and worsening on steroids in the first days is expected, so they are never the crisis monotherapy.
Cholinergic crisis is the drug winning: too much acetylcholinesterase inhibitor floods muscarinic receptors. The board package is DUMBBELLS: Diarrhea, Urination, Miosis, Bradycardia, Bronchospasm, Emesis, Lacrimation, Lethargy, Salivation, plus fasciculations from nicotinic excess. Edrophonium worsens cholinergic crisis, which is the classic way the two are separated at the bedside. Treatment is atropine 0.5 to 1 mg IV, repeat as needed, and holding the pyridostigmine: more drug is the lethal answer, and the drug restarts once the muscarinic storm clears.
Run the fork: which crisis is this, and which door does the patient walk through?
A patient with MG on pyridostigmine arrives in the emergency department. Which door fits which presentation?
THE WORSENING-DRUG LIST
The Worsening-Drug List
Half of crisis questions are pharmacology questions: a patient with MG gets one of these and suddenly cannot breathe. Know the list, know the ladder, and know what to reach for.
The drugs that worsen MG share one mechanism: they impair neuromuscular transmission, and in a junction with no margin of safety, that tips the patient into weakness or crisis. The board list is fixed: aminoglycosides, macrolides, fluoroquinolones, beta-blockers, calcium channel blockers, magnesium, botulinum toxin, D-penicillamine, procainamide, quinine, and quinidine. The high-yield traps: the aminoglycoside (gentamicin, tobramycin) given to a hospitalized MG patient for pyelonephritis or sepsis; magnesium as a tocolytic or in a preeclampsia protocol; fluoroquinolones and macrolides prescribed for a routine respiratory infection; botulinum toxin injected cosmetically; and beta-blockers or calcium channel blockers for a new cardiac diagnosis. When an MG patient worsens after one of these, the move is stopping the offending drug and monitoring respiration, not adding pyridostigmine.
Tap each letter and hold the drug behind it.
AMF BCM BD PQQ
AAminoglycosides: gentamicin, tobramycin, the classic hospital-trigger crisis drugs
MMacrolides: azithromycin, clarithromycin, erythromycin
FFluoroquinolones: ciprofloxacin, levofloxacin, moxifloxacin
BBeta-blockers: propranolol, metoprolol
CCalcium channel blockers: verapamil, diltiazem, nifedipine
MMagnesium: tocolysis, preeclampsia protocols, IVDU electrolyte replacement
BBotulinum toxin: cosmetic or therapeutic injections
DD-penicillamine: a drug that can itself cause myasthenia
PProcainamide: the antiarrhythmic that blocks the junction
QQuinine: antimalarial and leg-cramp relic
QQuinidine: the antiarrhythmic twin
Open each rung of the treatment ladder and hold the sequence.
Pyridostigmine 30 to 60 mg every 4 to 6 hours first; add corticosteroids for inadequate response, then steroid-sparing agents (azathioprine or mycophenolate). Crisis gets ICU care with IVIG or plasmapheresis. CT chest for thymoma in every generalized patient, and thymectomy for thymoma, or for anti-AChR-positive generalized MG even without a tumor.
3,4-diaminopyridine (amifampridine) 5 to 10 mg three times daily blocks potassium channels so calcium entry recovers; treat the underlying small cell lung cancer, which is the definitive move; IVIG or plasmapheresis for refractory paraneoplastic disease.
Heptavalent botulinum antitoxin (types A through G) on clinical suspicion, never deferred for culture or toxin assay; supportive care in the ICU with intubation when the diaphragm fails. Infant botulism gets human botulism immune globulin (BabyBIG); wound botulism adds surgical debridement.
Myasthenic crisis: IVIG or plasmapheresis in the ICU, with serial vital capacity and negative inspiratory force monitoring. Cholinergic crisis: atropine 0.5 to 1 mg IV repeated as needed, and hold the pyridostigmine. Edrophonium improves myasthenic crisis and worsens cholinergic crisis, which is how the fork is named at the bedside.
Prove it
Walkthrough: the NMJ trio, case by case
Original practice scenarios, one at a time. Choose an answer, then open any option to work its reasoning.
Clinical walkthrough
