The legs are getting weaker, the reflexes are fading, and the oxygen saturation is still normal. Which finding should guide care? In Guillain-Barre syndrome, breathing muscle strength can deteriorate before oxygen saturation changes. Diagnose the neuropathy and assess respiratory risk together.
Ascending weakness is a useful pattern, not a required itinerary. A normal early lumbar puncture does not close the diagnosis.
An immune attack on peripheral nerves
Recognize acute immune neuropathy, distinguish its variants and mimics, interpret early tests, and protect breathing while choosing evidence-based treatment.
Guillain-Barre syndrome, or GBS, is an acute immune-mediated polyradiculoneuropathy. “Poly” means multiple nerves; “radiculo” includes the nerve roots. The lesion is outside the brain and spinal cord. Weakness usually progresses over days, with reduced or absent deep tendon reflexes and relatively mild sensory loss. Tingling, back pain, or painful legs may precede obvious weakness. Children may stop walking because of pain before an adult recognizes paralysis. A recent gastrointestinal or respiratory illness supports the diagnosis, but an absent infection history does not exclude it. [2]
After some infections, the immune response recognizes structures shared by a pathogen and peripheral nerve membranes. Campylobacter jejuni lipooligosaccharides can resemble neural gangliosides. This is molecular mimicry. Experimental work supports a GM1 mimicry mechanism in axonal disease. [8] The immune injury can involve myelin, nodes of Ranvier, or axons; it is not simply bacteria invading nerves. Do not turn a proven mechanism in some subtypes into a claim that every patient's disease has the same antibody or target. Routine ganglioside panels add little in typical sensorimotor GBS. [1]
Where transmission fails
Nerve root and peripheral nerve Schwann-cell myelin surrounds the axon. Gaps between myelin segments are nodes of Ranvier.
AIDP Myelin dysfunction disrupts saltatory conduction. Signals slow, disperse, or fail across segments.
AMAN or AMSAN Nodal conduction failure and axonal injury can reduce motor responses. Reversible nodal failure need not mean permanent axon loss.
Muscle A muscle can be structurally intact yet weak because its nerve signal cannot reliably arrive.
Conceptual longitudinal comparison, not a scale drawing. The reflex arc also depends on these peripheral nerves. Its interruption helps explain areflexia. [3]
There is no established rule that the longest nerves must demyelinate first. Weakness may be proximal, distal, or both. Cranial and upper-limb variants are real. Likewise, recovery has no obligatory head-to-foot sequence. Keep the typical pattern as a starting hypothesis and let the examination refine it.
Case 7
Show answer and explanations for case 7
A. Unequal slowing of impulse arrival among conducting motor fibers (Best answer)
Make one prediction at a time. Earlier explanations stay available.
What does a broader compound response say about impulse arrival times?
The individual impulses are arriving less synchronously.
Does this option fit the findings: Unequal slowing of impulse arrival among conducting motor fibers?
Temporal dispersion reflects loss of synchrony as impulses traverse affected fibers at different speeds. The multinerve slowing and prolonged distal latencies support demyelinating physiology, although severe disease can also cause axon loss.
Which distinction should you carry into the next patient?
Use a combination of electrophysiologic features to classify demyelination.
Read the complete explanation
Temporal dispersion reflects loss of synchrony as impulses traverse affected fibers at different speeds. The multinerve slowing and prolonged distal latencies support demyelinating physiology, although severe disease can also cause axon loss.
B. Variable failure of acetylcholine release during repeated stimulation (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
What does a broader compound response say about impulse arrival times?
The individual impulses are arriving less synchronously.
Does this option fit the findings: Variable failure of acetylcholine release during repeated stimulation?
That suggests a presynaptic transmission disorder. The supplied abnormality is dispersion and slowing during nerve conduction, not a repetitive-stimulation pattern.
Which distinction should you carry into the next patient?
Use a combination of electrophysiologic features to classify demyelination.
Read the complete explanation
That suggests a presynaptic transmission disorder. The supplied abnormality is dispersion and slowing during nerve conduction, not a repetitive-stimulation pattern.
C. Reduced muscle-fiber action potentials from primary muscle injury (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
What does a broader compound response say about impulse arrival times?
The individual impulses are arriving less synchronously.
Does this option fit the findings: Reduced muscle-fiber action potentials from primary muscle injury?
Muscle injury can reduce responses, but does not best account for conduction slowing and prolonged distal motor latencies across several nerves.
Which distinction should you carry into the next patient?
Use a combination of electrophysiologic features to classify demyelination.
Read the complete explanation
Muscle injury can reduce responses, but does not best account for conduction slowing and prolonged distal motor latencies across several nerves.
D. Uniform loss of motor axons with unchanged conduction timing in survivors (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
What does a broader compound response say about impulse arrival times?
The individual impulses are arriving less synchronously.
Does this option fit the findings: Uniform loss of motor axons with unchanged conduction timing in survivors?
Motor axon loss can lower amplitude, but by itself does not best explain marked dispersion plus widespread slowing and prolonged distal latencies.
Which distinction should you carry into the next patient?
Use a combination of electrophysiologic features to classify demyelination.
Read the complete explanation
Motor axon loss can lower amplitude, but by itself does not best explain marked dispersion plus widespread slowing and prolonged distal latencies.
Takeaway: Use a combination of electrophysiologic features to classify demyelination.
Classic GBS produces bilateral, relatively symmetric weakness, often beginning in the legs. Facial weakness may be bilateral. A weak cough, nasal speech, difficulty swallowing, or inability to lift the head expands the problem beyond walking. Autonomic involvement can produce labile blood pressure, tachycardia or bradycardia, arrhythmias, ileus, and urinary retention. Severe dysautonomia is itself dangerous, even if limb strength has stopped changing. [2]
AIDP
Acute inflammatory demyelinating polyradiculoneuropathy is the common electrophysiologic subtype in Europe and North America. Slowed conduction, prolonged distal latencies or F-wave abnormalities, temporal dispersion, and conduction block support demyelination.
AMAN and AMSAN
Acute motor axonal neuropathy primarily affects motor fibers. Acute motor and sensory axonal neuropathy also affects sensory fibers. Anti-GM1 or anti-GD1a antibodies may occur, particularly after Campylobacter infection. Some AMAN patients retain reflexes. Early nodal conduction failure may be reversible and can resemble demyelinating block, so serial studies sometimes change the initial classification.
Miller Fisher syndrome
Ophthalmoplegia, ataxia, and areflexia define the classic triad, often with little limb weakness. Anti-GQ1b antibodies are strongly associated. This is not defined by a descending march of paralysis. Assess for overlap with generalized GBS when bulbar or respiratory weakness appears. [1][3]
Most patients reach their greatest weakness within two weeks, and the usual diagnostic framework requires progression to nadir within four weeks. A deficit maximal within minutes points toward a vascular event. Continued worsening after eight weeks, or three or more treatment-related fluctuations, should prompt reassessment for acute-onset chronic inflammatory demyelinating polyradiculoneuropathy, or CIDP. Slow recovery alone is not evidence of CIDP. [1]
Case 9
Show answer and explanations for case 9
A. Anti-GM1 (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
What makes an ocular symptom pattern different from myasthenia here?
The associated ataxia and absent reflexes point toward the ocular-ataxic peripheral syndrome.
Does this option fit the findings: Anti-GM1?
This is associated with some motor axonal GBS patterns. The ocular-ataxic-areflexic presentation more specifically points toward anti-GQ1b.
Which distinction should you carry into the next patient?
Choose the antibody from the phenotype, not from weakness alone.
Read the complete explanation
This is associated with some motor axonal GBS patterns. The ocular-ataxic-areflexic presentation more specifically points toward anti-GQ1b.
B. Anti-GQ1b (Best answer)
Make one prediction at a time. Earlier explanations stay available.
What makes an ocular symptom pattern different from myasthenia here?
The associated ataxia and absent reflexes point toward the ocular-ataxic peripheral syndrome.
Does this option fit the findings: Anti-GQ1b?
Ophthalmoplegia, ataxia and areflexia with relatively preserved limb strength suggest Miller Fisher syndrome. Anti-GQ1b is a useful supportive test; its absence would not by itself settle every clinical question.
Which distinction should you carry into the next patient?
Choose the antibody from the phenotype, not from weakness alone.
Read the complete explanation
Ophthalmoplegia, ataxia and areflexia with relatively preserved limb strength suggest Miller Fisher syndrome. Anti-GQ1b is a useful supportive test; its absence would not by itself settle every clinical question.
C. Anti-acetylcholine receptor (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
What makes an ocular symptom pattern different from myasthenia here?
The associated ataxia and absent reflexes point toward the ocular-ataxic peripheral syndrome.
Does this option fit the findings: Anti-acetylcholine receptor?
This supports autoimmune myasthenia in the right setting; myasthenia does not readily explain the severe ataxia and areflexia.
Which distinction should you carry into the next patient?
Choose the antibody from the phenotype, not from weakness alone.
Read the complete explanation
This supports autoimmune myasthenia in the right setting; myasthenia does not readily explain the severe ataxia and areflexia.
D. Anti-aquaporin-4 (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
What makes an ocular symptom pattern different from myasthenia here?
The associated ataxia and absent reflexes point toward the ocular-ataxic peripheral syndrome.
Does this option fit the findings: Anti-aquaporin-4?
This supports an appropriate central inflammatory syndrome, but the supplied examination and imaging favor the peripheral ocular-ataxic syndrome.
Which distinction should you carry into the next patient?
Choose the antibody from the phenotype, not from weakness alone.
Read the complete explanation
This supports an appropriate central inflammatory syndrome, but the supplied examination and imaging favor the peripheral ocular-ataxic syndrome.
Takeaway: Choose the antibody from the phenotype, not from weakness alone.
Obtain cerebrospinal fluid and electrodiagnostic studies when feasible, but do not postpone necessary treatment for a severely progressive clinical syndrome while waiting for results. Albuminocytologic dissociation means raised CSF protein without a proportionate rise in white cells. For example, protein 120 mg/dL with 3 leukocytes/µL supports the pattern. Protein may remain normal early. The finding is supportive rather than specific and can occur in other root or nerve disorders. [1]
A substantial CSF pleocytosis should widen the differential to infectious or malignant polyradiculopathy and other inflammatory disorders. Mild pleocytosis can occur in GBS, but it deserves explanation. More than 50 leukocytes/µL strongly argues for looking beyond typical GBS. A nerve conduction study can also be nondiagnostic in the first week, particularly in proximal disease or a variant. Repeating a study can be more informative than treating one normal result as exclusion. [3]
A sensory level changes the location
A clear truncal sensory level, early prominent sphincter dysfunction, or extensor plantar responses raises concern for a spinal cord lesion. Acute myelopathy can initially be flaccid and areflexic during spinal shock. Therefore, absent reflexes alone do not rule out cord compression or transverse myelitis. Obtain urgent spinal imaging when the distribution points there.
Fatigable eyes change the target
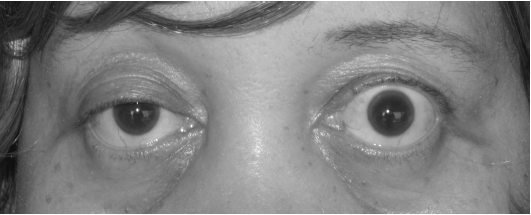
Ptosis means a drooping upper eyelid. This historical photograph is from a patient with myasthenia gravis, a GBS mimic. The photograph cannot demonstrate fatigability or establish a diagnosis. Compare it with the history, sensation and reflexes. Mohankumar Kurukumbi, Roger L. Image: Weir, Janaki Kalyanam, Mansoor Nasim and Annapurni Jayam-Trouth (2008). Source. CC BY 2.0. Select to enlarge the whole photograph.
Ptosis and diplopia that vary with use, preserved sensation, and generally normal reflexes suggest myasthenia gravis. Antibody testing and neuromuscular transmission studies are more relevant than a CSF protein measurement.
Exposure or electrolytes can change the treatment
Botulism often starts with cranial neuropathies and descends, with dry mouth or pupillary dysfunction. Pupils are not an absolute separator because abnormalities can occur in GBS and may be absent in botulism. Tick paralysis can resemble ascending GBS; inspect the scalp and skin after a compatible exposure. Prompt tick removal addresses the toxin source, while respiratory monitoring continues. [7] In infants, constipation, poor feeding, weak cry and reduced head control raise concern for botulism caused by intestinal colonization. Honey exposure is not required. Seek prompt infant botulism consultation and treatment when clinically indicated. [9] Hypokalemia can cause flaccid weakness with reduced reflexes, so obtain electrolytes rather than assuming areflexia proves immune disease. [3][5]
Check medication and toxin exposure, glucose, electrolytes, renal function, and other tests directed by the history. Imaging is primarily useful when the diagnosis is uncertain or a structural mimic needs exclusion. Nerve-root enhancement can support a polyradiculopathy, but it is neither necessary nor specific for GBS.
Case 4
Show answer and explanations for case 4
A. Rising CSF protein with few cells and multifocal motor conduction slowing (Best answer)
Make one prediction at a time. Earlier explanations stay available.
What does a normal protein result on day two establish?
It does not rule out an early inflammatory peripheral neuropathy.
Does this option fit the findings: Rising CSF protein with few cells and multifocal motor conduction slowing?
The early normal protein does not exclude GBS. Later protein elevation with few cells, together with supportive nerve studies, can fit an inflammatory peripheral polyradiculoneuropathy.
Which distinction should you carry into the next patient?
An early normal test can coexist with a convincing clinical syndrome.
Read the complete explanation
The early normal protein does not exclude GBS. Later protein elevation with few cells, together with supportive nerve studies, can fit an inflammatory peripheral polyradiculoneuropathy.
B. A reproducible transmission decrement with fatigable ptosis and intact sensation (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
What does a normal protein result on day two establish?
It does not rule out an early inflammatory peripheral neuropathy.
Does this option fit the findings: A reproducible transmission decrement with fatigable ptosis and intact sensation?
That pattern redirects attention to the neuromuscular junction rather than explaining the supplied sensory peripheral syndrome.
Which distinction should you carry into the next patient?
An early normal test can coexist with a convincing clinical syndrome.
Read the complete explanation
That pattern redirects attention to the neuromuscular junction rather than explaining the supplied sensory peripheral syndrome.
C. Rising CSF leukocytes with fever and a persistently low CSF glucose (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
What does a normal protein result on day two establish?
It does not rule out an early inflammatory peripheral neuropathy.
Does this option fit the findings: Rising CSF leukocytes with fever and a persistently low CSF glucose?
This inflammatory pattern raises concern for infection or another process rather than the usual GBS CSF pattern.
Which distinction should you carry into the next patient?
An early normal test can coexist with a convincing clinical syndrome.
Read the complete explanation
This inflammatory pattern raises concern for infection or another process rather than the usual GBS CSF pattern.
D. A new truncal sensory level with an intramedullary spinal cord lesion (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
What does a normal protein result on day two establish?
It does not rule out an early inflammatory peripheral neuropathy.
Does this option fit the findings: A new truncal sensory level with an intramedullary spinal cord lesion?
Those findings would redirect localization to the cord, despite the initially reduced reflexes.
Which distinction should you carry into the next patient?
An early normal test can coexist with a convincing clinical syndrome.
Read the complete explanation
Those findings would redirect localization to the cord, despite the initially reduced reflexes.
Takeaway: An early normal test can coexist with a convincing clinical syndrome.
A normal saturation measures oxygenation at that moment. It does not measure the reserve of a weakening diaphragm or the ability to protect the airway.
Follow forced vital capacity, the respiratory examination, cough strength, swallowing, neck flexion, and the rate of change. Inspiratory and expiratory pressures can add information. Facial weakness may prevent a reliable mouth seal, so interpret unexpectedly low or inconsistent measurements in context. Do not dismiss a weak cough or pooling secretions because the spirometry number is above a threshold.
The 2023 EAN/PNS guidance advises considering elective ventilation at FVC at or below 20 mL/kg. A fall exceeding 30% in 24 hours warrants immediate ICU transfer consideration. These are escalation signals, not automatic intubation commands independent of the examination. Bulbar dysfunction, inability to clear secretions, and evolving distress can require airway protection earlier. A negative inspiratory force becoming less negative reflects weaker inspiration. [1]
Monitor cardiac rhythm and blood pressure during active disease. Abrupt bradycardia and hypotension may be dysautonomic, but assess concurrent infection, pulmonary embolism, bleeding, or myocardial disease when the clinical context supports them. Avoid assuming that every new problem is GBS. If blood pressure treatment is required, cautious titration is important because autonomic tone may change abruptly. Continued vigilance is necessary during recovery and after leaving intensive care. [3]
Case 3
Show answer and explanations for case 3
A. FVC has fallen about 13%, with secretion retention as the main abnormality (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
Which number is the denominator when calculating the fall from 31 to 18?
Use the starting value, 31; the fall is 13/31, about 42%.
Does this option fit the findings: FVC has fallen about 13%, with secretion retention as the main abnormality?
Thirteen is the absolute change in mL/kg, not the percentage decrease. This understates the rapid loss of measured reserve.
Which distinction should you carry into the next patient?
Bulbar failure and falling FVC justify escalation before hypoxemia.
Read the complete explanation
Thirteen is the absolute change in mL/kg, not the percentage decrease. This understates the rapid loss of measured reserve.
B. FVC has fallen about 42%, with established hypercapnia explaining the weak cough (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
Which number is the denominator when calculating the fall from 31 to 18?
Use the starting value, 31; the fall is 13/31, about 42%.
Does this option fit the findings: FVC has fallen about 42%, with established hypercapnia explaining the weak cough?
The percentage is correct, but no carbon dioxide value is supplied. Weak cough and bulbar dysfunction can prompt escalation before hypercapnia is documented.
Which distinction should you carry into the next patient?
Bulbar failure and falling FVC justify escalation before hypoxemia.
Read the complete explanation
The percentage is correct, but no carbon dioxide value is supplied. Weak cough and bulbar dysfunction can prompt escalation before hypercapnia is documented.
C. FVC has fallen about 72%, with hypoxemia as the main abnormality (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
Which number is the denominator when calculating the fall from 31 to 18?
Use the starting value, 31; the fall is 13/31, about 42%.
Does this option fit the findings: FVC has fallen about 72%, with hypoxemia as the main abnormality?
Dividing 13 by the final value 18 gives about 72%, but percentage decline uses the initial value. Saturation of 97% does not demonstrate hypoxemia.
Which distinction should you carry into the next patient?
Bulbar failure and falling FVC justify escalation before hypoxemia.
Read the complete explanation
Dividing 13 by the final value 18 gives about 72%, but percentage decline uses the initial value. Saturation of 97% does not demonstrate hypoxemia.
D. FVC has fallen about 42%, with impaired airway protection despite preserved oxygenation (Best answer)
Make one prediction at a time. Earlier explanations stay available.
Which number is the denominator when calculating the fall from 31 to 18?
Use the starting value, 31; the fall is 13/31, about 42%.
Does this option fit the findings: FVC has fallen about 42%, with impaired airway protection despite preserved oxygenation?
The fall is (31-18)/31, approximately 42%. The rapid decline together with weak cough and pooled secretions signals loss of ventilatory reserve and airway protection; saturation does not remove that risk.
Which distinction should you carry into the next patient?
Bulbar failure and falling FVC justify escalation before hypoxemia.
Read the complete explanation
The fall is (31-18)/31, approximately 42%. The rapid decline together with weak cough and pooled secretions signals loss of ventilatory reserve and airway protection; saturation does not remove that risk.
Takeaway: Bulbar failure and falling FVC justify escalation before hypoxemia.
IV immunoglobulin and plasma exchange are established disease-modifying treatments. IVIG is commonly given as 0.4 g/kg daily for five days. The strongest IVIG evidence is for patients unable to walk independently treated within two weeks of weakness onset; plasma exchange has evidence within four weeks. Specialist treatment may also be appropriate for an ambulatory patient with substantial progression, bulbar weakness, respiratory involvement, or dysautonomia. Choice depends on availability, vascular access, hemodynamic stability, and renal or thrombotic risk. [1]
Corticosteroids are not an effective treatment for acute GBS. This separates GBS from CIDP, where corticosteroids may help. Routine sequential plasma exchange and IVIG offers no established added benefit. Do not prescribe a second IVIG course solely because the predicted outcome is poor or improvement has not yet occurred. The SID-GBS randomized trial found no benefit for that strategy and more serious adverse events. A true deterioration after initial improvement or stabilization is a different clinical question and requires reassessment for a treatment-related fluctuation or an alternative diagnosis. [4]
Immune treatment does not replace supportive care. Assess swallowing before oral intake when bulbar weakness is present. Plan nutrition, venous thromboembolism prevention for immobility when appropriate, pressure-area care, corneal protection with poor eyelid closure, bladder and bowel care, pain management, and rehabilitation. Neuropathic pain can persist even as strength improves. Activity should be graded to function and fatigue rather than forcing exhaustion. [3]
IVIG can be associated with thrombosis, kidney injury, hemolysis, aseptic meningitis, and a misleading low sodium measurement from hyperproteinemia. Distinguish true hypotonic hyponatremia from pseudohyponatremia using measured osmolality and, when needed, a direct-ion-selective sodium measurement. A low laboratory sodium number alone does not justify fluid restriction or hypertonic saline. [6]
Recovery often takes months and can continue beyond the first year. Persistent fatigue, pain, or weakness deserves follow-up rather than a promise of complete recovery by a fixed date. The practical decision tool is simple. Bilateral progressive weakness prompts localization; reduced reflexes support peripheral nerve involvement; respiratory and swallowing trends decide the care setting; IVIG or plasma exchange addresses the acute immune process. Reconsider the diagnosis whenever the time course or examination stops fitting.
Case 11
Show answer and explanations for case 11
A. Begin oral corticosteroids, then reassess the walking response before selecting another therapy (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
Why do the timing and walking ability matter together?
The early disabling course supports a decision about acute immune treatment.
Does this option fit the findings: Begin oral corticosteroids, then reassess the walking response before selecting another therapy?
Corticosteroids are effective in some other immune neuropathies, but have not demonstrated benefit as treatment for acute GBS.
Which distinction should you carry into the next patient?
Use IVIG or plasma exchange for functionally significant acute GBS.
Read the complete explanation
Corticosteroids are effective in some other immune neuropathies, but have not demonstrated benefit as treatment for acute GBS.
B. Begin plasma exchange followed immediately by IVIG to combine their routine benefits (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
Why do the timing and walking ability matter together?
The early disabling course supports a decision about acute immune treatment.
Does this option fit the findings: Begin plasma exchange followed immediately by IVIG to combine their routine benefits?
Both treatments work individually, but routine sequential treatment has not shown a superior benefit and is not the standard plan.
Which distinction should you carry into the next patient?
Use IVIG or plasma exchange for functionally significant acute GBS.
Read the complete explanation
Both treatments work individually, but routine sequential treatment has not shown a superior benefit and is not the standard plan.
C. Begin a standard IVIG course or plasma exchange, choosing between them for this patient (Best answer)
Make one prediction at a time. Earlier explanations stay available.
Why do the timing and walking ability matter together?
The early disabling course supports a decision about acute immune treatment.
Does this option fit the findings: Begin a standard IVIG course or plasma exchange, choosing between them for this patient?
Loss of unaided walking within the early treatment window supports disease-modifying treatment. IVIG and plasma exchange are effective options; choice depends on individual circumstances and availability.
Which distinction should you carry into the next patient?
Use IVIG or plasma exchange for functionally significant acute GBS.
Read the complete explanation
Loss of unaided walking within the early treatment window supports disease-modifying treatment. IVIG and plasma exchange are effective options; choice depends on individual circumstances and availability.
D. Begin IVIG now with a second full course scheduled for persistent walking disability next week (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
Why do the timing and walking ability matter together?
The early disabling course supports a decision about acute immune treatment.
Does this option fit the findings: Begin IVIG now with a second full course scheduled for persistent walking disability next week?
A first course can be appropriate, but persistent disability or poor prognosis does not justify automatically scheduling a second course.
Which distinction should you carry into the next patient?
Use IVIG or plasma exchange for functionally significant acute GBS.
Read the complete explanation
A first course can be appropriate, but persistent disability or poor prognosis does not justify automatically scheduling a second course.
Takeaway: Use IVIG or plasma exchange for functionally significant acute GBS.
Apply the nerve, breathing, and treatment decisions
Case 1
Show answer and explanations for case 1
A. A decrement during repetitive stimulation with preserved sensory responses (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
Where does the combined weakness, sensory change and reflex loss localize?
The combined pattern points to peripheral nerves and roots.
Does this option fit the findings: A decrement during repetitive stimulation with preserved sensory responses?
A decrement can support impaired neuromuscular transmission, but that localization does not explain distal sensory loss well.
Which distinction should you carry into the next patient?
Localize progressive bilateral areflexic weakness to peripheral nerves and roots.
Read the complete explanation
A decrement can support impaired neuromuscular transmission, but that localization does not explain distal sensory loss well.
B. A focal thoracic cord lesion with a matching sensory level (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
Where does the combined weakness, sensory change and reflex loss localize?
The combined pattern points to peripheral nerves and roots.
Does this option fit the findings: A focal thoracic cord lesion with a matching sensory level?
Cord disease remains an important mimic, but the supplied examination lacks a level and instead shows a diffuse peripheral pattern.
Which distinction should you carry into the next patient?
Localize progressive bilateral areflexic weakness to peripheral nerves and roots.
Read the complete explanation
Cord disease remains an important mimic, but the supplied examination lacks a level and instead shows a diffuse peripheral pattern.
C. Small, brief motor units with early recruitment during needle examination (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
Where does the combined weakness, sensory change and reflex loss localize?
The combined pattern points to peripheral nerves and roots.
Does this option fit the findings: Small, brief motor units with early recruitment during needle examination?
That pattern supports myopathy; normal creatine kinase does not exclude myopathy, but sensory loss and areflexia favor nerves and roots here.
Which distinction should you carry into the next patient?
Localize progressive bilateral areflexic weakness to peripheral nerves and roots.
Read the complete explanation
That pattern supports myopathy; normal creatine kinase does not exclude myopathy, but sensory loss and areflexia favor nerves and roots here.
D. Abnormal late motor responses across several peripheral nerves (Best answer)
Make one prediction at a time. Earlier explanations stay available.
Where does the combined weakness, sensory change and reflex loss localize?
The combined pattern points to peripheral nerves and roots.
Does this option fit the findings: Abnormal late motor responses across several peripheral nerves?
The bilateral areflexic sensorimotor pattern localizes to peripheral nerves and roots. Abnormal late responses across multiple nerves would support that localization, although no single finding proves GBS.
Which distinction should you carry into the next patient?
Localize progressive bilateral areflexic weakness to peripheral nerves and roots.
Read the complete explanation
The bilateral areflexic sensorimotor pattern localizes to peripheral nerves and roots. Abnormal late responses across multiple nerves would support that localization, although no single finding proves GBS.
Takeaway: Localize progressive bilateral areflexic weakness to peripheral nerves and roots.
A. An arterial blood gas paired with repeat pulse oximetry (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
What does a weakening cough suggest even when saturation is normal?
The respiratory muscles or airway-protection system may be weakening.
Does this option fit the findings: An arterial blood gas paired with repeat pulse oximetry?
These assess gas exchange and can reveal later respiratory failure, but may remain reassuring while muscle reserve and secretion clearance deteriorate.
Which distinction should you carry into the next patient?
Assess respiratory reserve, not oxygenation alone.
Read the complete explanation
These assess gas exchange and can reveal later respiratory failure, but may remain reassuring while muscle reserve and secretion clearance deteriorate.
B. Peak expiratory flow paired with bronchodilator testing (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
What does a weakening cough suggest even when saturation is normal?
The respiratory muscles or airway-protection system may be weakening.
Does this option fit the findings: Peak expiratory flow paired with bronchodilator testing?
This combination evaluates an airflow-obstruction hypothesis. No wheeze or obstruction history is supplied, and inspiratory reserve and bulbar function remain the concern.
Which distinction should you carry into the next patient?
Assess respiratory reserve, not oxygenation alone.
Read the complete explanation
This combination evaluates an airflow-obstruction hypothesis. No wheeze or obstruction history is supplied, and inspiratory reserve and bulbar function remain the concern.
C. Serial forced vital capacity paired with cough and swallowing assessment (Best answer)
Make one prediction at a time. Earlier explanations stay available.
What does a weakening cough suggest even when saturation is normal?
The respiratory muscles or airway-protection system may be weakening.
Does this option fit the findings: Serial forced vital capacity paired with cough and swallowing assessment?
A weaker cough and reduced ability to sustain speech raise concern for respiratory muscle reserve and airway protection. Serial FVC and the bulbar examination address these deficits before oxygenation necessarily changes.
Which distinction should you carry into the next patient?
Assess respiratory reserve, not oxygenation alone.
Read the complete explanation
A weaker cough and reduced ability to sustain speech raise concern for respiratory muscle reserve and airway protection. Serial FVC and the bulbar examination address these deficits before oxygenation necessarily changes.
D. Chest radiography paired with lung ultrasonography (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
What does a weakening cough suggest even when saturation is normal?
The respiratory muscles or airway-protection system may be weakening.
Does this option fit the findings: Chest radiography paired with lung ultrasonography?
These can identify lung or pleural disease; the evolving weak cough suggests a neuromuscular deficit that imaging does not quantify.
Which distinction should you carry into the next patient?
Assess respiratory reserve, not oxygenation alone.
Read the complete explanation
These can identify lung or pleural disease; the evolving weak cough suggests a neuromuscular deficit that imaging does not quantify.
Takeaway: Assess respiratory reserve, not oxygenation alone.
A. Lymphocyte-rich inflammation of the leptomeninges (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
How should you read high protein alongside only four CSF cells?
The protein is high while the cell count remains low: albuminocytologic dissociation.
Does this option fit the findings: Lymphocyte-rich inflammation of the leptomeninges?
Viral or other lymphocytic meningeal inflammation can raise protein, but usually also raises cells; the low cell count favors dissociation here.
Which distinction should you carry into the next patient?
Protein and cell count describe different aspects of inflammation.
Read the complete explanation
Viral or other lymphocytic meningeal inflammation can raise protein, but usually also raises cells; the low cell count favors dissociation here.
B. Neutrophil-rich inflammation of the leptomeninges (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
How should you read high protein alongside only four CSF cells?
The protein is high while the cell count remains low: albuminocytologic dissociation.
Does this option fit the findings: Neutrophil-rich inflammation of the leptomeninges?
Bacterial meningeal inflammation can raise protein, but the low leukocyte count and afebrile peripheral presentation do not support this explanation.
Which distinction should you carry into the next patient?
Protein and cell count describe different aspects of inflammation.
Read the complete explanation
Bacterial meningeal inflammation can raise protein, but the low leukocyte count and afebrile peripheral presentation do not support this explanation.
C. Protein accumulation below an obstructing spinal lesion (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
How should you read high protein alongside only four CSF cells?
The protein is high while the cell count remains low: albuminocytologic dissociation.
Does this option fit the findings: Protein accumulation below an obstructing spinal lesion?
A spinal block can produce high CSF protein, making it a real alternative; the supplied imaging specifically excludes an obstructing lesion.
Which distinction should you carry into the next patient?
Protein and cell count describe different aspects of inflammation.
Read the complete explanation
A spinal block can produce high CSF protein, making it a real alternative; the supplied imaging specifically excludes an obstructing lesion.
D. Increased protein entry associated with inflamed peripheral nerve roots (Best answer)
Make one prediction at a time. Earlier explanations stay available.
How should you read high protein alongside only four CSF cells?
The protein is high while the cell count remains low: albuminocytologic dissociation.
Does this option fit the findings: Increased protein entry associated with inflamed peripheral nerve roots?
High protein with few cells is albuminocytologic dissociation. In this peripheral syndrome without a spinal block, root inflammation and altered barrier permeability provide the best explanation.
Which distinction should you carry into the next patient?
Protein and cell count describe different aspects of inflammation.
Read the complete explanation
High protein with few cells is albuminocytologic dissociation. In this peripheral syndrome without a spinal block, root inflammation and altered barrier permeability provide the best explanation.
Takeaway: Protein and cell count describe different aspects of inflammation.
A. Repeat nerve studies to prioritize demyelinating-versus-axonal GBS classification (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
Does a peripheral localization tell you the cause of the disease?
No. Marked CSF pleocytosis and fever still require an etiologic investigation.
Does this option fit the findings: Repeat nerve studies to prioritize demyelinating-versus-axonal GBS classification?
Subtyping can be useful, but it does not explain or resolve the marked pleocytosis and persistent fever that challenge routine GBS attribution.
Which distinction should you carry into the next patient?
Substantial pleocytosis is a reason to widen the differential.
Read the complete explanation
Subtyping can be useful, but it does not explain or resolve the marked pleocytosis and persistent fever that challenge routine GBS attribution.
B. Repeat lumbar puncture after an interval to look for a typical high-protein pattern (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
Does a peripheral localization tell you the cause of the disease?
No. Marked CSF pleocytosis and fever still require an etiologic investigation.
Does this option fit the findings: Repeat lumbar puncture after an interval to look for a typical high-protein pattern?
Repeating CSF may contribute later, but high protein is already present. Waiting for a more typical pattern does not address the current marked pleocytosis and fever.
Which distinction should you carry into the next patient?
Substantial pleocytosis is a reason to widen the differential.
Read the complete explanation
Repeating CSF may contribute later, but high protein is already present. Waiting for a more typical pattern does not address the current marked pleocytosis and fever.
C. Investigate infectious and other inflammatory causes of polyradiculopathy (Best answer)
Make one prediction at a time. Earlier explanations stay available.
Does a peripheral localization tell you the cause of the disease?
No. Marked CSF pleocytosis and fever still require an etiologic investigation.
Does this option fit the findings: Investigate infectious and other inflammatory causes of polyradiculopathy?
A peripheral localization does not establish an autoimmune GBS cause. Marked pleocytosis and persistent fever warrant a broader etiologic investigation despite the high protein and areflexic weakness.
Which distinction should you carry into the next patient?
Substantial pleocytosis is a reason to widen the differential.
Read the complete explanation
A peripheral localization does not establish an autoimmune GBS cause. Marked pleocytosis and persistent fever warrant a broader etiologic investigation despite the high protein and areflexic weakness.
D. Assess chronic inflammatory neuropathy because the CSF protein is markedly elevated (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
Does a peripheral localization tell you the cause of the disease?
No. Marked CSF pleocytosis and fever still require an etiologic investigation.
Does this option fit the findings: Assess chronic inflammatory neuropathy because the CSF protein is markedly elevated?
High protein can occur in acute or chronic neuropathies. It does not establish a chronic course or account for this substantial cell count and febrile illness.
Which distinction should you carry into the next patient?
Substantial pleocytosis is a reason to widen the differential.
Read the complete explanation
High protein can occur in acute or chronic neuropathies. It does not establish a chronic course or account for this substantial cell count and febrile illness.
Takeaway: Substantial pleocytosis is a reason to widen the differential.
A. An acute motor-only axonal pattern; offer IVIG or plasma exchange (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
What changes when sensory responses become reduced as well as motor responses?
The measured pattern now includes both sensory and motor axon involvement.
Does this option fit the findings: An acute motor-only axonal pattern; offer IVIG or plasma exchange?
The treatment plan fits the early disabling GBS course, but the classification omits the newly abnormal sensory responses.
Which distinction should you carry into the next patient?
AMAN primarily affects motor fibers; AMSAN also affects sensory fibers.
Read the complete explanation
The treatment plan fits the early disabling GBS course, but the classification omits the newly abnormal sensory responses.
B. An acute motor-sensory axonal pattern; offer IVIG or plasma exchange (Best answer)
Make one prediction at a time. Earlier explanations stay available.
What changes when sensory responses become reduced as well as motor responses?
The measured pattern now includes both sensory and motor axon involvement.
Does this option fit the findings: An acute motor-sensory axonal pattern; offer IVIG or plasma exchange?
The new sensory axon findings shift the pattern from motor-only toward AMSAN. Early loss of unaided walking supports IVIG or plasma exchange; an axonal classification is not a reason to withhold effective GBS treatment.
Which distinction should you carry into the next patient?
AMAN primarily affects motor fibers; AMSAN also affects sensory fibers.
Read the complete explanation
The new sensory axon findings shift the pattern from motor-only toward AMSAN. Early loss of unaided walking supports IVIG or plasma exchange; an axonal classification is not a reason to withhold effective GBS treatment.
C. An acute motor-sensory axonal pattern; use supportive care without acute immunotherapy (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
What changes when sensory responses become reduced as well as motor responses?
The measured pattern now includes both sensory and motor axon involvement.
Does this option fit the findings: An acute motor-sensory axonal pattern; use supportive care without acute immunotherapy?
The classification incorporates both motor and sensory findings, but it does not address the evidence for immunotherapy in this early disabling course.
Which distinction should you carry into the next patient?
AMAN primarily affects motor fibers; AMSAN also affects sensory fibers.
Read the complete explanation
The classification incorporates both motor and sensory findings, but it does not address the evidence for immunotherapy in this early disabling course.
D. An acute motor-only axonal pattern; use supportive care without acute immunotherapy (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
What changes when sensory responses become reduced as well as motor responses?
The measured pattern now includes both sensory and motor axon involvement.
Does this option fit the findings: An acute motor-only axonal pattern; use supportive care without acute immunotherapy?
This misses the sensory involvement and also treats the axonal label as a reason to omit indicated acute immunotherapy. Supportive care is necessary alongside disease treatment.
Which distinction should you carry into the next patient?
AMAN primarily affects motor fibers; AMSAN also affects sensory fibers.
Read the complete explanation
This misses the sensory involvement and also treats the axonal label as a reason to omit indicated acute immunotherapy. Supportive care is necessary alongside disease treatment.
Takeaway: AMAN primarily affects motor fibers; AMSAN also affects sensory fibers.
A. Reversible dysfunction at motor nerve nodes (Best answer)
Make one prediction at a time. Earlier explanations stay available.
What does rapid reversal of conduction failure argue against?
It argues against explaining the entire change by structural axon degeneration and regrowth.
Does this option fit the findings: Reversible dysfunction at motor nerve nodes?
Some motor GBS variants preserve reflexes. Rapid reversal of conduction failure without evolving demyelinating features supports nodal dysfunction and cautions against equating every low motor response with irreversible axon degeneration.
Which distinction should you carry into the next patient?
A typical sign is not an absolute requirement across all variants.
Read the complete explanation
Some motor GBS variants preserve reflexes. Rapid reversal of conduction failure without evolving demyelinating features supports nodal dysfunction and cautions against equating every low motor response with irreversible axon degeneration.
B. Segmental demyelination followed by evolving temporal dispersion (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
What does rapid reversal of conduction failure argue against?
It argues against explaining the entire change by structural axon degeneration and regrowth.
Does this option fit the findings: Segmental demyelination followed by evolving temporal dispersion?
Demyelination can cause conduction failure, but the serial recovery without evolving demyelinating features favors the supplied nodal mechanism.
Which distinction should you carry into the next patient?
A typical sign is not an absolute requirement across all variants.
Read the complete explanation
Demyelination can cause conduction failure, but the serial recovery without evolving demyelinating features favors the supplied nodal mechanism.
C. Postsynaptic receptor loss with fluctuating transmission failure (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
What does rapid reversal of conduction failure argue against?
It argues against explaining the entire change by structural axon degeneration and regrowth.
Does this option fit the findings: Postsynaptic receptor loss with fluctuating transmission failure?
A junction disorder can fluctuate, but the documented peripheral motor nerve conduction failure and postinfectious course support a nodal neuropathy here.
Which distinction should you carry into the next patient?
A typical sign is not an absolute requirement across all variants.
Read the complete explanation
A junction disorder can fluctuate, but the documented peripheral motor nerve conduction failure and postinfectious course support a nodal neuropathy here.
D. Motor axon degeneration with reinnervation by surviving axons (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
What does rapid reversal of conduction failure argue against?
It argues against explaining the entire change by structural axon degeneration and regrowth.
Does this option fit the findings: Motor axon degeneration with reinnervation by surviving axons?
Collateral reinnervation can contribute to recovery after axon loss, but does not best explain rapid reversal of the measured conduction failure without evolving demyelinating features.
Which distinction should you carry into the next patient?
A typical sign is not an absolute requirement across all variants.
Read the complete explanation
Collateral reinnervation can contribute to recovery after axon loss, but does not best explain rapid reversal of the measured conduction failure without evolving demyelinating features.
Takeaway: A typical sign is not an absolute requirement across all variants.
A. Avoid them as disease treatment for both because the initial presentation determines the treatment evidence (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
Which patient has a course that needs a new diagnostic framework?
Patient B has new late deterioration; patient A is following an acute improving course.
Does this option fit the findings: Avoid them as disease treatment for both because the initial presentation determines the treatment evidence?
The original acute label does not settle B's subsequent diagnosis. New progression beyond eight weeks makes reassessment important and may change effective treatment options.
Which distinction should you carry into the next patient?
An immune mechanism does not automatically imply steroid benefit.
Read the complete explanation
The original acute label does not settle B's subsequent diagnosis. New progression beyond eight weeks makes reassessment important and may change effective treatment options.
B. They lack demonstrated benefit for A; they may be relevant if B is reclassified as acute-onset CIDP (Best answer)
Make one prediction at a time. Earlier explanations stay available.
Which patient has a course that needs a new diagnostic framework?
Patient B has new late deterioration; patient A is following an acute improving course.
Does this option fit the findings: They lack demonstrated benefit for A; they may be relevant if B is reclassified as acute-onset CIDP?
A fits an acute GBS course, for which corticosteroids have not demonstrated benefit. B has new late progression suggesting a chronic inflammatory neuropathy; reassessment matters because corticosteroids can have a role in CIDP.
Which distinction should you carry into the next patient?
An immune mechanism does not automatically imply steroid benefit.
Read the complete explanation
A fits an acute GBS course, for which corticosteroids have not demonstrated benefit. B has new late progression suggesting a chronic inflammatory neuropathy; reassessment matters because corticosteroids can have a role in CIDP.
C. Use them as initial immune treatment for A; reserve them for residual pain after recovery in B (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
Which patient has a course that needs a new diagnostic framework?
Patient B has new late deterioration; patient A is following an acute improving course.
Does this option fit the findings: Use them as initial immune treatment for A; reserve them for residual pain after recovery in B?
This reverses the evidence distinction. Corticosteroids do not have demonstrated benefit for acute GBS, while B needs reassessment for a disorder in which steroids may be disease treatment.
Which distinction should you carry into the next patient?
An immune mechanism does not automatically imply steroid benefit.
Read the complete explanation
This reverses the evidence distinction. Corticosteroids do not have demonstrated benefit for acute GBS, while B needs reassessment for a disorder in which steroids may be disease treatment.
D. They can improve disease recovery for both because both disorders show immune-mediated demyelination (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
Which patient has a course that needs a new diagnostic framework?
Patient B has new late deterioration; patient A is following an acute improving course.
Does this option fit the findings: They can improve disease recovery for both because both disorders show immune-mediated demyelination?
Shared immune mechanisms do not establish shared treatment benefit. The clinical time course changes the diagnostic framework and the relevant corticosteroid evidence.
Which distinction should you carry into the next patient?
An immune mechanism does not automatically imply steroid benefit.
Read the complete explanation
Shared immune mechanisms do not establish shared treatment benefit. The clinical time course changes the diagnostic framework and the relevant corticosteroid evidence.
Takeaway: An immune mechanism does not automatically imply steroid benefit.
A. Continue supportive care and reassessment; the poor score does not establish second-course benefit (Best answer)
Make one prediction at a time. Earlier explanations stay available.
Has this patient demonstrated a new deterioration?
No. The supplied course is an unchanged early plateau, not a documented new decline.
Does this option fit the findings: Continue supportive care and reassessment; the poor score does not establish second-course benefit?
A poor prognosis is not evidence that another IVIG course helps. SID-GBS found no demonstrated benefit for this indication and more serious adverse events; a stable plateau is not a treatment-related fluctuation.
Which distinction should you carry into the next patient?
Poor predicted recovery and treatment-related fluctuation are different questions.
Read the complete explanation
A poor prognosis is not evidence that another IVIG course helps. SID-GBS found no demonstrated benefit for this indication and more serious adverse events; a stable plateau is not a treatment-related fluctuation.
B. Repeat IVIG based on the continuing severe functional disability (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
Has this patient demonstrated a new deterioration?
No. The supplied course is an unchanged early plateau, not a documented new decline.
Does this option fit the findings: Repeat IVIG based on the continuing severe functional disability?
A fluctuation requires a meaningful change in trajectory, typically deterioration after improvement or stabilization. This short unchanged course and poor score do not establish that indication.
Which distinction should you carry into the next patient?
Poor predicted recovery and treatment-related fluctuation are different questions.
Read the complete explanation
A fluctuation requires a meaningful change in trajectory, typically deterioration after improvement or stabilization. This short unchanged course and poor score do not establish that indication.
C. Reclassify the persistent weakness as acute-onset CIDP and start a maintenance immune regimen (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
Has this patient demonstrated a new deterioration?
No. The supplied course is an unchanged early plateau, not a documented new decline.
Does this option fit the findings: Reclassify the persistent weakness as acute-onset CIDP and start a maintenance immune regimen?
A short unchanged course is different from new progression beyond eight weeks or repeated fluctuations. Poor prognosis does not itself establish a chronic inflammatory course.
Which distinction should you carry into the next patient?
Poor predicted recovery and treatment-related fluctuation are different questions.
Read the complete explanation
A short unchanged course is different from new progression beyond eight weeks or repeated fluctuations. Poor prognosis does not itself establish a chronic inflammatory course.
D. Add plasma exchange to address the severe residual weakness (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
Has this patient demonstrated a new deterioration?
No. The supplied course is an unchanged early plateau, not a documented new decline.
Does this option fit the findings: Add plasma exchange to address the severe residual weakness?
Recovery may be delayed despite appropriate therapy; persistent disability alone does not demonstrate benefit from routine sequential treatment.
Which distinction should you carry into the next patient?
Poor predicted recovery and treatment-related fluctuation are different questions.
Read the complete explanation
Recovery may be delayed despite appropriate therapy; persistent disability alone does not demonstrate benefit from routine sequential treatment.
Takeaway: Poor predicted recovery and treatment-related fluctuation are different questions.
A. A recurrent acute neuropathy representing a separate disease episode (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
Is this residual weakness or renewed loss of function?
It is renewed loss after documented improvement.
Does this option fit the findings: A recurrent acute neuropathy representing a separate disease episode?
A recurrent episode is a real consideration over a longitudinal history. This brief early improvement-then-decline is more consistent with fluctuation within the same episode.
Which distinction should you carry into the next patient?
Document whether the patient never improved or truly worsened again.
Read the complete explanation
A recurrent episode is a real consideration over a longitudinal history. This brief early improvement-then-decline is more consistent with fluctuation within the same episode.
B. An acute-onset chronic inflammatory neuropathy entering a relapsing course (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
Is this residual weakness or renewed loss of function?
It is renewed loss after documented improvement.
Does this option fit the findings: An acute-onset chronic inflammatory neuropathy entering a relapsing course?
That possibility becomes more concerning with later progression or repeated fluctuations. One deterioration at three weeks more directly fits an early treatment-related fluctuation and does not establish CIDP.
Which distinction should you carry into the next patient?
Document whether the patient never improved or truly worsened again.
Read the complete explanation
That possibility becomes more concerning with later progression or repeated fluctuations. One deterioration at three weeks more directly fits an early treatment-related fluctuation and does not establish CIDP.
C. A possible treatment-related fluctuation within the early GBS course (Best answer)
Make one prediction at a time. Earlier explanations stay available.
Is this residual weakness or renewed loss of function?
It is renewed loss after documented improvement.
Does this option fit the findings: A possible treatment-related fluctuation within the early GBS course?
Objective improvement followed by renewed deterioration within the early course raises concern for a treatment-related fluctuation. Specialist reassessment should confirm the trajectory, assess alternatives and guide treatment.
Which distinction should you carry into the next patient?
Document whether the patient never improved or truly worsened again.
Read the complete explanation
Objective improvement followed by renewed deterioration within the early course raises concern for a treatment-related fluctuation. Specialist reassessment should confirm the trajectory, assess alternatives and guide treatment.
D. Persistent disability during a slow but uninterrupted recovery (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
Is this residual weakness or renewed loss of function?
It is renewed loss after documented improvement.
Does this option fit the findings: Persistent disability during a slow but uninterrupted recovery?
The documented regain and subsequent loss of walking ability distinguish new deterioration from persistent residual weakness.
Which distinction should you carry into the next patient?
Document whether the patient never improved or truly worsened again.
Read the complete explanation
The documented regain and subsequent loss of walking ability distinguish new deterioration from persistent residual weakness.
Takeaway: Document whether the patient never improved or truly worsened again.
A. Residual disability after monophasic GBS; plan rehabilitation without maintenance immune treatment (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
Does the week-11 finding describe a stable residual deficit?
No. Strength and walking ability have newly declined after improvement.
Does this option fit the findings: Residual disability after monophasic GBS; plan rehabilitation without maintenance immune treatment?
Residual disability can require prolonged rehabilitation, but it does not explain the supplied new objective decline after improvement as well as an active relapsing process.
Which distinction should you carry into the next patient?
Tempo can change both diagnosis and immune treatment.
Read the complete explanation
Residual disability can require prolonged rehabilitation, but it does not explain the supplied new objective decline after improvement as well as an active relapsing process.
B. Residual disability after monophasic GBS; plan a maintenance immune-treatment strategy (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
Does the week-11 finding describe a stable residual deficit?
No. Strength and walking ability have newly declined after improvement.
Does this option fit the findings: Residual disability after monophasic GBS; plan a maintenance immune-treatment strategy?
This pairs a static residual-injury explanation with ongoing immune treatment without establishing ongoing disease activity. The new late decline instead requires diagnostic reassessment.
Which distinction should you carry into the next patient?
Tempo can change both diagnosis and immune treatment.
Read the complete explanation
This pairs a static residual-injury explanation with ongoing immune treatment without establishing ongoing disease activity. The new late decline instead requires diagnostic reassessment.
C. Possible acute-onset CIDP; plan rehabilitation without reassessing immune treatment (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
Does the week-11 finding describe a stable residual deficit?
No. Strength and walking ability have newly declined after improvement.
Does this option fit the findings: Possible acute-onset CIDP; plan rehabilitation without reassessing immune treatment?
The diagnostic concern fits, but the clinical consequence is incomplete: new late deterioration warrants specialist reassessment of immune treatment as well as rehabilitation.
Which distinction should you carry into the next patient?
Tempo can change both diagnosis and immune treatment.
Read the complete explanation
The diagnostic concern fits, but the clinical consequence is incomplete: new late deterioration warrants specialist reassessment of immune treatment as well as rehabilitation.
D. Possible acute-onset CIDP; reassess with a specialist for a maintenance immune-treatment strategy (Best answer)
Make one prediction at a time. Earlier explanations stay available.
Does the week-11 finding describe a stable residual deficit?
No. Strength and walking ability have newly declined after improvement.
Does this option fit the findings: Possible acute-onset CIDP; reassess with a specialist for a maintenance immune-treatment strategy?
New objective deterioration beyond eight weeks, after real improvement, prompts reassessment for acute-onset CIDP. This matters because ongoing immune-treatment planning may differ from rehabilitation for fixed residual disability.
Which distinction should you carry into the next patient?
Tempo can change both diagnosis and immune treatment.
Read the complete explanation
New objective deterioration beyond eight weeks, after real improvement, prompts reassessment for acute-onset CIDP. This matters because ongoing immune-treatment planning may differ from rehabilitation for fixed residual disability.
Takeaway: Tempo can change both diagnosis and immune treatment.
A. New pleuritic chest pain with sustained hypoxemia (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
What links the cardiovascular and gastrointestinal changes?
Both can result from autonomic nerve dysfunction.
Does this option fit the findings: New pleuritic chest pain with sustained hypoxemia?
This would raise concern for a pulmonary complication such as embolism rather than simply extending the described autonomic pattern.
Which distinction should you carry into the next patient?
Stable limb strength does not eliminate autonomic danger.
Read the complete explanation
This would raise concern for a pulmonary complication such as embolism rather than simply extending the described autonomic pattern.
B. New urinary retention without a sensory level (Best answer)
Make one prediction at a time. Earlier explanations stay available.
What links the cardiovascular and gastrointestinal changes?
Both can result from autonomic nerve dysfunction.
Does this option fit the findings: New urinary retention without a sensory level?
The linked cardiovascular and gastrointestinal changes suggest autonomic nerve dysfunction. Bladder dysfunction can accompany the same process, while a sensory level or other new localization would require reassessment.
Which distinction should you carry into the next patient?
Stable limb strength does not eliminate autonomic danger.
Read the complete explanation
The linked cardiovascular and gastrointestinal changes suggest autonomic nerve dysfunction. Bladder dysfunction can accompany the same process, while a sensory level or other new localization would require reassessment.
C. New fever with persistent vasodilatory hypotension (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
What links the cardiovascular and gastrointestinal changes?
Both can result from autonomic nerve dysfunction.
Does this option fit the findings: New fever with persistent vasodilatory hypotension?
This would raise concern for infection and distributive shock; the supplied alternating bradycardia and pressure lability without fever suggest a different unifying mechanism.
Which distinction should you carry into the next patient?
Stable limb strength does not eliminate autonomic danger.
Read the complete explanation
This would raise concern for infection and distributive shock; the supplied alternating bradycardia and pressure lability without fever suggest a different unifying mechanism.
D. New focal ST elevation with regional ventricular dysfunction (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
What links the cardiovascular and gastrointestinal changes?
Both can result from autonomic nerve dysfunction.
Does this option fit the findings: New focal ST elevation with regional ventricular dysfunction?
These would demand cardiac evaluation and would not be adequately explained by assigning every new change to the existing autonomic syndrome.
Which distinction should you carry into the next patient?
Stable limb strength does not eliminate autonomic danger.
Read the complete explanation
These would demand cardiac evaluation and would not be adequately explained by assigning every new change to the existing autonomic syndrome.
Takeaway: Stable limb strength does not eliminate autonomic danger.
A. Multinerve conduction studies to classify a peripheral neuropathy (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
Which finding changes localization despite reduced reflexes?
The sharp sensory level raises concern for the spinal cord.
Does this option fit the findings: Multinerve conduction studies to classify a peripheral neuropathy?
These assess peripheral nerves, but the level and urinary retention prioritize assessment of the cord rather than peripheral subtype classification.
Which distinction should you carry into the next patient?
A sensory level outweighs an isolated reflex shortcut.
Read the complete explanation
These assess peripheral nerves, but the level and urinary retention prioritize assessment of the cord rather than peripheral subtype classification.
B. Repetitive stimulation to assess neuromuscular transmission (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
Which finding changes localization despite reduced reflexes?
The sharp sensory level raises concern for the spinal cord.
Does this option fit the findings: Repetitive stimulation to assess neuromuscular transmission?
A junction disorder can cause weakness but does not explain a sharply demarcated sensory level and sphincter dysfunction.
Which distinction should you carry into the next patient?
A sensory level outweighs an isolated reflex shortcut.
Read the complete explanation
A junction disorder can cause weakness but does not explain a sharply demarcated sensory level and sphincter dysfunction.
C. Urgent spinal MRI to assess an acute cord process (Best answer)
Make one prediction at a time. Earlier explanations stay available.
Which finding changes localization despite reduced reflexes?
The sharp sensory level raises concern for the spinal cord.
Does this option fit the findings: Urgent spinal MRI to assess an acute cord process?
An acute cord lesion may initially be areflexic during spinal shock. The sharp sensory level and sphincter involvement outweigh reflex loss as isolated evidence for a peripheral neuropathy.
Which distinction should you carry into the next patient?
A sensory level outweighs an isolated reflex shortcut.
Read the complete explanation
An acute cord lesion may initially be areflexic during spinal shock. The sharp sensory level and sphincter involvement outweigh reflex loss as isolated evidence for a peripheral neuropathy.
D. Lumbar puncture to assess for albuminocytologic dissociation (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
Which finding changes localization despite reduced reflexes?
The sharp sensory level raises concern for the spinal cord.
Does this option fit the findings: Lumbar puncture to assess for albuminocytologic dissociation?
CSF can support GBS in the right setting, but does not replace urgent imaging for a potentially treatable cord lesion suggested by the level and bladder findings.
Which distinction should you carry into the next patient?
A sensory level outweighs an isolated reflex shortcut.
Read the complete explanation
CSF can support GBS in the right setting, but does not replace urgent imaging for a potentially treatable cord lesion suggested by the level and bladder findings.
Takeaway: A sensory level outweighs an isolated reflex shortcut.
A. CSF analysis and multinerve studies for an inflammatory polyradiculopathy (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
What does fatigability add to the localization?
Fatigable ocular-bulbar weakness with preserved sensation supports impaired neuromuscular transmission.
Does this option fit the findings: CSF analysis and multinerve studies for an inflammatory polyradiculopathy?
These are useful for a peripheral nerve/root syndrome, but the supplied fatigability and preserved sensation/reflexes favor a junction disorder.
Which distinction should you carry into the next patient?
Fatigable ocular-bulbar weakness suggests the junction.
Read the complete explanation
These are useful for a peripheral nerve/root syndrome, but the supplied fatigability and preserved sensation/reflexes favor a junction disorder.
B. Brainstem MRI and evoked potentials for a central inflammatory lesion (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
What does fatigability add to the localization?
Fatigable ocular-bulbar weakness with preserved sensation supports impaired neuromuscular transmission.
Does this option fit the findings: Brainstem MRI and evoked potentials for a central inflammatory lesion?
Central disease can cause diplopia, but a six-week fatigable ocular-bulbar pattern without central examination findings more directly supports junction testing.
Which distinction should you carry into the next patient?
Fatigable ocular-bulbar weakness suggests the junction.
Read the complete explanation
Central disease can cause diplopia, but a six-week fatigable ocular-bulbar pattern without central examination findings more directly supports junction testing.
C. Creatine kinase testing and muscle imaging for an inflammatory myopathy (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
What does fatigability add to the localization?
Fatigable ocular-bulbar weakness with preserved sensation supports impaired neuromuscular transmission.
Does this option fit the findings: Creatine kinase testing and muscle imaging for an inflammatory myopathy?
Myopathy can cause weakness and swallowing difficulty; the fluctuating ocular findings and fatigable ptosis are more characteristic of transmission failure.
Which distinction should you carry into the next patient?
Fatigable ocular-bulbar weakness suggests the junction.
Read the complete explanation
Myopathy can cause weakness and swallowing difficulty; the fluctuating ocular findings and fatigable ptosis are more characteristic of transmission failure.
D. AChR antibody testing and neuromuscular transmission studies (Best answer)
Make one prediction at a time. Earlier explanations stay available.
What does fatigability add to the localization?
Fatigable ocular-bulbar weakness with preserved sensation supports impaired neuromuscular transmission.
Does this option fit the findings: AChR antibody testing and neuromuscular transmission studies?
Fatigable ocular-bulbar weakness with preserved sensation and reflexes suggests impaired neuromuscular transmission. Antibody and transmission studies address that localization.
Which distinction should you carry into the next patient?
Fatigable ocular-bulbar weakness suggests the junction.
Read the complete explanation
Fatigable ocular-bulbar weakness with preserved sensation and reflexes suggests impaired neuromuscular transmission. Antibody and transmission studies address that localization.
Takeaway: Fatigable ocular-bulbar weakness suggests the junction.
A. Postsynaptic acetylcholine receptors at skeletal neuromuscular junctions (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
Why do dry mouth and sluggish pupils matter with the weakness?
They connect the motor syndrome to autonomic cholinergic dysfunction.
Does this option fit the findings: Postsynaptic acetylcholine receptors at skeletal neuromuscular junctions?
Autoimmune myasthenia can cause ocular-bulbar weakness, but does not typically explain the pupillary and dry-mouth autonomic findings in this exposure-linked presentation.
Which distinction should you carry into the next patient?
Exposure, tempo and distribution should agree before choosing a diagnosis.
Read the complete explanation
Autoimmune myasthenia can cause ocular-bulbar weakness, but does not typically explain the pupillary and dry-mouth autonomic findings in this exposure-linked presentation.
B. Descending motor pathways within a focal brainstem lesion (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
Why do dry mouth and sluggish pupils matter with the weakness?
They connect the motor syndrome to autonomic cholinergic dysfunction.
Does this option fit the findings: Descending motor pathways within a focal brainstem lesion?
A brainstem lesion can produce cranial and limb signs, but this linked exposure-related peripheral cholinergic pattern without sensory or focal central findings favors botulism.
Which distinction should you carry into the next patient?
Exposure, tempo and distribution should agree before choosing a diagnosis.
Read the complete explanation
A brainstem lesion can produce cranial and limb signs, but this linked exposure-related peripheral cholinergic pattern without sensory or focal central findings favors botulism.
C. Presynaptic acetylcholine release at peripheral cholinergic terminals (Best answer)
Make one prediction at a time. Earlier explanations stay available.
Why do dry mouth and sluggish pupils matter with the weakness?
They connect the motor syndrome to autonomic cholinergic dysfunction.
Does this option fit the findings: Presynaptic acetylcholine release at peripheral cholinergic terminals?
The acute cranial-first weakness, autonomic findings and food exposure raise urgent concern for botulism. Its toxin impairs acetylcholine release at somatic and autonomic cholinergic terminals.
Which distinction should you carry into the next patient?
Exposure, tempo and distribution should agree before choosing a diagnosis.
Read the complete explanation
The acute cranial-first weakness, autonomic findings and food exposure raise urgent concern for botulism. Its toxin impairs acetylcholine release at somatic and autonomic cholinergic terminals.
D. Myelin surrounding proximal motor and sensory nerve roots (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
Why do dry mouth and sluggish pupils matter with the weakness?
They connect the motor syndrome to autonomic cholinergic dysfunction.
Does this option fit the findings: Myelin surrounding proximal motor and sensory nerve roots?
GBS can include cranial and autonomic dysfunction, so these are not absolute exclusions; the food exposure and acute cranial-first pattern make toxin-mediated transmission failure the stronger explanation.
Which distinction should you carry into the next patient?
Exposure, tempo and distribution should agree before choosing a diagnosis.
Read the complete explanation
GBS can include cranial and autonomic dysfunction, so these are not absolute exclusions; the food exposure and acute cranial-first pattern make toxin-mediated transmission failure the stronger explanation.
Takeaway: Exposure, tempo and distribution should agree before choosing a diagnosis.
A. New demyelinating conduction abnormalities despite ongoing deterioration (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
Does normal early CSF prove that the tick caused the weakness?
No. Early GBS can also have normal CSF; the subsequent course supplies additional evidence.
Does this option fit the findings: New demyelinating conduction abnormalities despite ongoing deterioration?
That pattern would increase concern for an inflammatory demyelinating neuropathy rather than confirm toxin reversal.
Which distinction should you carry into the next patient?
Examine the scalp and skin when an exposure could explain areflexic weakness.
Read the complete explanation
That pattern would increase concern for an inflammatory demyelinating neuropathy rather than confirm toxin reversal.
B. New ophthalmoplegia with ataxia and persistent areflexia (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
Does normal early CSF prove that the tick caused the weakness?
No. Early GBS can also have normal CSF; the subsequent course supplies additional evidence.
Does this option fit the findings: New ophthalmoplegia with ataxia and persistent areflexia?
That evolving pattern would prompt assessment for an ocular-ataxic peripheral syndrome rather than specifically establish a tick-toxin response.
Which distinction should you carry into the next patient?
Examine the scalp and skin when an exposure could explain areflexic weakness.
Read the complete explanation
That evolving pattern would prompt assessment for an ocular-ataxic peripheral syndrome rather than specifically establish a tick-toxin response.
C. Weakness reaching a plateau followed by gradual improvement over several months (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
Does normal early CSF prove that the tick caused the weakness?
No. Early GBS can also have normal CSF; the subsequent course supplies additional evidence.
Does this option fit the findings: Weakness reaching a plateau followed by gradual improvement over several months?
This can fit recovery from an inflammatory neuropathy and is less specifically supportive of prompt reversal after removing a tick.
Which distinction should you carry into the next patient?
Examine the scalp and skin when an exposure could explain areflexic weakness.
Read the complete explanation
This can fit recovery from an inflammatory neuropathy and is less specifically supportive of prompt reversal after removing a tick.
D. Clear improvement of strength over the following day or two (Best answer)
Make one prediction at a time. Earlier explanations stay available.
Does normal early CSF prove that the tick caused the weakness?
No. Early GBS can also have normal CSF; the subsequent course supplies additional evidence.
Does this option fit the findings: Clear improvement of strength over the following day or two?
In a compatible tick-paralysis presentation, improvement after removal supports the toxin hypothesis. Respiratory monitoring remains necessary; recovery is not guaranteed to be immediate and course varies by tick species.
Which distinction should you carry into the next patient?
Examine the scalp and skin when an exposure could explain areflexic weakness.
Read the complete explanation
In a compatible tick-paralysis presentation, improvement after removal supports the toxin hypothesis. Respiratory monitoring remains necessary; recovery is not guaranteed to be immediate and course varies by tick species.
Takeaway: Examine the scalp and skin when an exposure could explain areflexic weakness.
A. Assess respiratory function and obtain multinerve conduction studies for an additional peripheral neuropathy (Best answer)
Make one prediction at a time. Earlier explanations stay available.
What does progression after potassium and ECG normalization suggest?
The potassium disturbance does not fully explain the evolving sensorimotor syndrome.
Does this option fit the findings: Assess respiratory function and obtain multinerve conduction studies for an additional peripheral neuropathy?
The potassium-related ECG abnormality resolves while a sensorimotor areflexic syndrome progresses, suggesting an additional peripheral process. Normal early CSF protein does not exclude GBS; nerve studies and ongoing respiratory assessment are appropriate.
Which distinction should you carry into the next patient?
Correct dangerous electrolyte abnormalities promptly, then reassess weakness that persists or evolves despite correction.
Read the complete explanation
The potassium-related ECG abnormality resolves while a sensorimotor areflexic syndrome progresses, suggesting an additional peripheral process. Normal early CSF protein does not exclude GBS; nerve studies and ongoing respiratory assessment are appropriate.
B. Obtain spinal imaging to evaluate a focal compressive cord lesion (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
What does progression after potassium and ECG normalization suggest?
The potassium disturbance does not fully explain the evolving sensorimotor syndrome.
Does this option fit the findings: Obtain spinal imaging to evaluate a focal compressive cord lesion?
Cord disease is an important weakness mimic, but the absence of a level and the evolving distal sensory and reflex pattern favor a diffuse peripheral process in this case.
Which distinction should you carry into the next patient?
Correct dangerous electrolyte abnormalities promptly, then reassess weakness that persists or evolves despite correction.
Read the complete explanation
Cord disease is an important weakness mimic, but the absence of a level and the evolving distal sensory and reflex pattern favor a diffuse peripheral process in this case.
C. Obtain muscle MRI and consider biopsy for a primary inflammatory myopathy (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
What does progression after potassium and ECG normalization suggest?
The potassium disturbance does not fully explain the evolving sensorimotor syndrome.
Does this option fit the findings: Obtain muscle MRI and consider biopsy for a primary inflammatory myopathy?
Myopathy can cause weakness, but new distal sensory symptoms and areflexia point toward nerves; normal creatine kinase further weakens this competing explanation.
Which distinction should you carry into the next patient?
Correct dangerous electrolyte abnormalities promptly, then reassess weakness that persists or evolves despite correction.
Read the complete explanation
Myopathy can cause weakness, but new distal sensory symptoms and areflexia point toward nerves; normal creatine kinase further weakens this competing explanation.
D. Obtain AChR antibodies and repetitive stimulation for a neuromuscular-junction disorder (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
What does progression after potassium and ECG normalization suggest?
The potassium disturbance does not fully explain the evolving sensorimotor syndrome.
Does this option fit the findings: Obtain AChR antibodies and repetitive stimulation for a neuromuscular-junction disorder?
A junction disorder can persist after electrolyte correction, but it would not explain the new distal paresthesias well. The sensorimotor pattern favors peripheral nerve assessment.
Which distinction should you carry into the next patient?
Correct dangerous electrolyte abnormalities promptly, then reassess weakness that persists or evolves despite correction.
Read the complete explanation
A junction disorder can persist after electrolyte correction, but it would not explain the new distal paresthesias well. The sensorimotor pattern favors peripheral nerve assessment.
Takeaway: Correct dangerous electrolyte abnormalities promptly, then reassess weakness that persists or evolves despite correction.
A. Corneal exposure injury and isolated respiratory muscle fatigue (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
Which protective function is lost when the lids cannot close?
The corneal surface is left exposed.
Does this option fit the findings: Corneal exposure injury and isolated respiratory muscle fatigue?
The eye mechanism fits. Respiratory muscle weakness can coexist, but the wet voice and cough specifically triggered by drinking indicate impaired swallowing safety rather than isolated ventilatory weakness.
Which distinction should you carry into the next patient?
Supportive care must follow the specific muscles that are weak.
Read the complete explanation
The eye mechanism fits. Respiratory muscle weakness can coexist, but the wet voice and cough specifically triggered by drinking indicate impaired swallowing safety rather than isolated ventilatory weakness.
B. Exposure injury to the cornea and aspiration into the airway (Best answer)
Make one prediction at a time. Earlier explanations stay available.
Which protective function is lost when the lids cannot close?
The corneal surface is left exposed.
Does this option fit the findings: Exposure injury to the cornea and aspiration into the airway?
Incomplete closure leaves the corneal surface exposed. Coughing with liquids suggests impaired swallowing safety; normal saturation does not exclude aspiration risk.
Which distinction should you carry into the next patient?
Supportive care must follow the specific muscles that are weak.
Read the complete explanation
Incomplete closure leaves the corneal surface exposed. Coughing with liquids suggests impaired swallowing safety; normal saturation does not exclude aspiration risk.
C. Reduced corneal sensation and aspiration into the airway (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
Which protective function is lost when the lids cannot close?
The corneal surface is left exposed.
Does this option fit the findings: Reduced corneal sensation and aspiration into the airway?
Aspiration risk fits the wet voice and coughing with liquids. However, the supplied failure of eyelid closure specifically identifies exposure; reduced corneal sensation is not demonstrated by these findings.
Which distinction should you carry into the next patient?
Supportive care must follow the specific muscles that are weak.
Read the complete explanation
Aspiration risk fits the wet voice and coughing with liquids. However, the supplied failure of eyelid closure specifically identifies exposure; reduced corneal sensation is not demonstrated by these findings.
D. Reduced tear production and isolated respiratory muscle fatigue (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
Which protective function is lost when the lids cannot close?
The corneal surface is left exposed.
Does this option fit the findings: Reduced tear production and isolated respiratory muscle fatigue?
Autonomic and respiratory dysfunction can occur in GBS. Here, observed closure failure and liquid-triggered cough more directly implicate exposure and airway protection; reduced tear production has not been shown.
Which distinction should you carry into the next patient?
Supportive care must follow the specific muscles that are weak.
Read the complete explanation
Autonomic and respiratory dysfunction can occur in GBS. Here, observed closure failure and liquid-triggered cough more directly implicate exposure and airway protection; reduced tear production has not been shown.
Takeaway: Supportive care must follow the specific muscles that are weak.
A. Start therapeutic anticoagulation while arranging routine screening ultrasonography (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
Has the stem established an existing clot?
No. It establishes an immobility-related risk that calls for prevention.
Does this option fit the findings: Start therapeutic anticoagulation while arranging routine screening ultrasonography?
Therapeutic dosing addresses a suspected or established clot. No supplied signs justify treating a clot as present merely because he is immobile.
Which distinction should you carry into the next patient?
Immunotherapy does not prevent the complications of immobility.
Read the complete explanation
Therapeutic dosing addresses a suspected or established clot. No supplied signs justify treating a clot as present merely because he is immobile.
B. Use an antiplatelet strategy directed at arterial thrombosis risk (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
Has the stem established an existing clot?
No. It establishes an immobility-related risk that calls for prevention.
Does this option fit the findings: Use an antiplatelet strategy directed at arterial thrombosis risk?
The main immobility-related mechanism is venous stasis, so an arterial-focused strategy does not substitute for appropriate venous prophylaxis.
Which distinction should you carry into the next patient?
Immunotherapy does not prevent the complications of immobility.
Read the complete explanation
The main immobility-related mechanism is venous stasis, so an arterial-focused strategy does not substitute for appropriate venous prophylaxis.
C. Use venous thromboembolism prophylaxis appropriate to his bleeding risk and mobility (Best answer)
Make one prediction at a time. Earlier explanations stay available.
Has the stem established an existing clot?
No. It establishes an immobility-related risk that calls for prevention.
Does this option fit the findings: Use venous thromboembolism prophylaxis appropriate to his bleeding risk and mobility?
Immobility increases venous thromboembolic risk, while the supplied history does not establish an existing clot. Prevention is therefore indicated according to individualized risk rather than empiric therapeutic anticoagulation.
Which distinction should you carry into the next patient?
Immunotherapy does not prevent the complications of immobility.
Read the complete explanation
Immobility increases venous thromboembolic risk, while the supplied history does not establish an existing clot. Prevention is therefore indicated according to individualized risk rather than empiric therapeutic anticoagulation.
D. Use serial leg examinations and initiate prophylaxis if asymmetric swelling appears (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
Has the stem established an existing clot?
No. It establishes an immobility-related risk that calls for prevention.
Does this option fit the findings: Use serial leg examinations and initiate prophylaxis if asymmetric swelling appears?
Surveillance is useful, but waiting for a possible clot sign misses prevention while a predictable immobility risk is already present.
Which distinction should you carry into the next patient?
Immunotherapy does not prevent the complications of immobility.
Read the complete explanation
Surveillance is useful, but waiting for a possible clot sign misses prevention while a predictable immobility risk is already present.
Takeaway: Immunotherapy does not prevent the complications of immobility.
A. Increased plasma protein has produced pseudohyponatremia on the indirect assay (Best answer)
Make one prediction at a time. Earlier explanations stay available.
Do the direct sodium and measured osmolality support true hypotonic hyponatremia?
No. Both are within their supplied reference ranges.
Does this option fit the findings: Increased plasma protein has produced pseudohyponatremia on the indirect assay?
The normal measured osmolality and direct sodium argue against true hypotonic hyponatremia. Increased plasma protein after IVIG can affect the indirect measurement and produce pseudohyponatremia.
Which distinction should you carry into the next patient?
Confirm tonicity and measurement method before treating a sodium number.
Read the complete explanation
The normal measured osmolality and direct sodium argue against true hypotonic hyponatremia. Increased plasma protein after IVIG can affect the indirect measurement and produce pseudohyponatremia.
B. Osmotically active glucose has shifted water out of cells and lowered sodium (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
Do the direct sodium and measured osmolality support true hypotonic hyponatremia?
No. Both are within their supplied reference ranges.
Does this option fit the findings: Osmotically active glucose has shifted water out of cells and lowered sodium?
Translocational hyponatremia from glucose requires the relevant glucose abnormality; the supplied normal glucose and assay discordance instead favor an indirect-assay artifact.
Which distinction should you carry into the next patient?
Confirm tonicity and measurement method before treating a sodium number.
Read the complete explanation
Translocational hyponatremia from glucose requires the relevant glucose abnormality; the supplied normal glucose and assay discordance instead favor an indirect-assay artifact.
C. SIADH has produced hypotonic hyponatremia detectable primarily by the indirect assay (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
Do the direct sodium and measured osmolality support true hypotonic hyponatremia?
No. Both are within their supplied reference ranges.
Does this option fit the findings: SIADH has produced hypotonic hyponatremia detectable primarily by the indirect assay?
SIADH can complicate GBS, making it a real competitor, but normal measured osmolality and normal direct sodium do not support true hypotonic hyponatremia here.
Which distinction should you carry into the next patient?
Confirm tonicity and measurement method before treating a sodium number.
Read the complete explanation
SIADH can complicate GBS, making it a real competitor, but normal measured osmolality and normal direct sodium do not support true hypotonic hyponatremia here.
D. Renal salt loss has lowered extracellular sodium despite a normal direct measurement (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
Do the direct sodium and measured osmolality support true hypotonic hyponatremia?
No. Both are within their supplied reference ranges.
Does this option fit the findings: Renal salt loss has lowered extracellular sodium despite a normal direct measurement?
Salt loss causing true hypotonic hyponatremia would not be explained by a normal direct sodium with this normal measured osmolality.
Which distinction should you carry into the next patient?
Confirm tonicity and measurement method before treating a sodium number.
Read the complete explanation
Salt loss causing true hypotonic hyponatremia would not be explained by a normal direct sodium with this normal measured osmolality.
Takeaway: Confirm tonicity and measurement method before treating a sodium number.
A. Treat the symptoms beyond eight weeks as CIDP and start maintenance immunotherapy (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
Does post-exercise fatigue establish an objective motor relapse?
No. The repeated rested examinations and walking function are improving.
Does this option fit the findings: Treat the symptoms beyond eight weeks as CIDP and start maintenance immunotherapy?
The duration threshold concerns new progression, not any symptom lasting longer than eight weeks. Her objective trajectory is improving.
Which distinction should you carry into the next patient?
Follow recovery by function and trajectory, not a promised deadline.
Read the complete explanation
The duration threshold concerns new progression, not any symptom lasting longer than eight weeks. Her objective trajectory is improving.
B. Adjust graded rehabilitation and treat neuropathic pain while tracking objective strength (Best answer)
Make one prediction at a time. Earlier explanations stay available.
Does post-exercise fatigue establish an objective motor relapse?
No. The repeated rested examinations and walking function are improving.
Does this option fit the findings: Adjust graded rehabilitation and treat neuropathic pain while tracking objective strength?
Exertional fatigue and pain can persist despite neurologic recovery. The improving rested examinations and function argue against treating the symptom report as an objective relapse; individualized rehabilitation, pain treatment and follow-up address the demonstrated problems.
Which distinction should you carry into the next patient?
Follow recovery by function and trajectory, not a promised deadline.
Read the complete explanation
Exertional fatigue and pain can persist despite neurologic recovery. The improving rested examinations and function argue against treating the symptom report as an objective relapse; individualized rehabilitation, pain treatment and follow-up address the demonstrated problems.
C. Treat the post-exercise weakness as a late fluctuation and give another IVIG course (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
Does post-exercise fatigue establish an objective motor relapse?
No. The repeated rested examinations and walking function are improving.
Does this option fit the findings: Treat the post-exercise weakness as a late fluctuation and give another IVIG course?
A report of fatigue after exertion is not equivalent to documented renewed motor deterioration. The improving rested strength and walking ability do not support this treatment rationale.
Which distinction should you carry into the next patient?
Follow recovery by function and trajectory, not a promised deadline.
Read the complete explanation
A report of fatigue after exertion is not equivalent to documented renewed motor deterioration. The improving rested strength and walking ability do not support this treatment rationale.
D. Suspend active rehabilitation until pain and fatigue have fully resolved (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
Does post-exercise fatigue establish an objective motor relapse?
No. The repeated rested examinations and walking function are improving.
Does this option fit the findings: Suspend active rehabilitation until pain and fatigue have fully resolved?
Symptoms warrant adjusting activity and treatment, but persistent recovery symptoms do not require abandoning individualized graded rehabilitation until the patient is symptom-free.
Which distinction should you carry into the next patient?
Follow recovery by function and trajectory, not a promised deadline.
Read the complete explanation
Symptoms warrant adjusting activity and treatment, but persistent recovery symptoms do not require abandoning individualized graded rehabilitation until the patient is symptom-free.
Takeaway: Follow recovery by function and trajectory, not a promised deadline.
A. Postinfectious immune injury to peripheral nerve roots and axons (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
Does the absence of reported honey exposure exclude this infant syndrome?
No. Honey exposure is not required for infant botulism.
Does this option fit the findings: Postinfectious immune injury to peripheral nerve roots and axons?
GBS can cause hypotonia and areflexia, but the age and constipation-first cranial weakness pattern prioritize infant botulism here.
Which distinction should you carry into the next patient?
Infant botulism remains possible without honey exposure; recognize the cranial, feeding and autonomic pattern promptly.
Read the complete explanation
GBS can cause hypotonia and areflexia, but the age and constipation-first cranial weakness pattern prioritize infant botulism here.
B. Progressive loss of anterior horn cells from an inherited motor neuron disorder (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
Does the absence of reported honey exposure exclude this infant syndrome?
No. Honey exposure is not required for infant botulism.
Does this option fit the findings: Progressive loss of anterior horn cells from an inherited motor neuron disorder?
Spinal muscular atrophy can cause hypotonia and areflexia, but the abrupt acquired cranial/autonomic sequence after normal development argues for a different mechanism.
Which distinction should you carry into the next patient?
Infant botulism remains possible without honey exposure; recognize the cranial, feeding and autonomic pattern promptly.
Read the complete explanation
Spinal muscular atrophy can cause hypotonia and areflexia, but the abrupt acquired cranial/autonomic sequence after normal development argues for a different mechanism.
C. Transplacental antibodies reducing postsynaptic acetylcholine receptors (Why this does not fit)
Make one prediction at a time. Earlier explanations stay available.
Does the absence of reported honey exposure exclude this infant syndrome?
No. Honey exposure is not required for infant botulism.
Does this option fit the findings: Transplacental antibodies reducing postsynaptic acetylcholine receptors?
Transient neonatal myasthenia can cause poor feeding and weakness, but usually presents near birth; the acquired syndrome at four months with constipation is more consistent with infant botulism.
Which distinction should you carry into the next patient?
Infant botulism remains possible without honey exposure; recognize the cranial, feeding and autonomic pattern promptly.
Read the complete explanation
Transient neonatal myasthenia can cause poor feeding and weakness, but usually presents near birth; the acquired syndrome at four months with constipation is more consistent with infant botulism.
D. Intestinal colonization with toxin production that impairs acetylcholine release (Best answer)
Make one prediction at a time. Earlier explanations stay available.
Does the absence of reported honey exposure exclude this infant syndrome?
No. Honey exposure is not required for infant botulism.
Does this option fit the findings: Intestinal colonization with toxin production that impairs acetylcholine release?
The acquired constipation and cranial weakness followed by hypotonia suggest infant botulism. Intestinal toxin production impairs presynaptic acetylcholine release; a reported honey exposure is not required.
Which distinction should you carry into the next patient?
Infant botulism remains possible without honey exposure; recognize the cranial, feeding and autonomic pattern promptly.
Read the complete explanation
The acquired constipation and cranial weakness followed by hypotonia suggest infant botulism. Intestinal toxin production impairs presynaptic acetylcholine release; a reported honey exposure is not required.
Takeaway: Infant botulism remains possible without honey exposure; recognize the cranial, feeding and autonomic pattern promptly.