Aphasias: Test the Pattern, Localize the Network, Plan the Care
Classify aphasia by bedside domains, localize the distributed network, act on sudden onset, and extend care through rehabilitation, referral, and dosing safeguards.
Aphasia is a pattern across language domains, not a synonym for hard-to-understand speech. Step/Level 1 builds the domain physiology and network localization; Step/Level 2 adds acute diagnosis and first-line decisions; Step/Level 3 adds reassessment, rehabilitation, safety, and progressive disease; Beyond translates these findings into emergency, referral, dosing, and communication plans.
Prove the language pattern before naming it
Aphasia is an acquired disorder of language. It can affect spoken expression, comprehension, naming, repetition, reading, and writing. Dysarthria impairs execution of speech, while apraxia of speech impairs planning of learned speech actions. These disorders may coexist, so a clinician must demonstrate which language abilities are preserved instead of inferring them from pronunciation alone. [1][15]
Begin with access to the task. Check alertness, hearing, vision, preferred language, premorbid literacy, attention, and the motor ability required to point or write. A weak right hand can prevent writing despite intact formulation. Limited proficiency in the examiner's language can mimic comprehension or naming failure. Use trained language support and sample the languages that mattered before illness. [1][10]
Figure 1. Test message processing and speech production as related but separable systems.
Language
Connected output, comprehension, repetition, naming, reading, and writing
Speech production
Speech mechanics. Articulation, consistency, strength, sequencing, prosody, and voice
Use a stable six-domain examination. Ask for a scene description, then test word and sentence comprehension, novel sentence repetition, object and action naming, reading aloud plus written comprehension, and spontaneous writing. Increase task difficulty only after simpler access is confirmed. A familiar greeting or memorized prayer is automatic language, not proof that generative language is intact.
Then compare spoken output with another modality. A patient who follows a novel three-step command and writes a complete sentence but has consistently slurred consonants has a motor execution problem. A patient with intact comprehension and writing but variable sound distortions, articulatory groping, and abnormal prosody has a speech-planning problem. The causal rule is profile before location: first document impaired and preserved functions, then ask which network arrangement best explains both.
Try it here · Checkpoint 1 of 3
Make your prediction before reading the choices. A first attempt is just a starting point.
Case 2
Show answer and explanations for case 2
A. Flaccid dysarthria from lower motor neuron weakness (Why this does not fit)
Flaccid dysarthria requires weakness and typically produces a more consistent pattern of imprecise speech. Oral strength is preserved, and the variable distortions with groping point elsewhere.
Reasoning steps for option A
For aph-02 option A, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Flaccid dysarthria requires weakness and typically produces a more consistent pattern of imprecise speech.
For aph-02 option A, which case-specific contrast decides whether the choice fits?
The decisive comparison for Flaccid dysarthria from lower motor neuron weakness is the remaining discriminator: Oral strength is preserved, and the variable distortions with groping point elsewhere.
B. Apraxia of speech from impaired speech planning (Best answer)
The patient preserves language in comprehension and writing, so the core deficit is not aphasia. Groping, inconsistent distortions, and prosodic disruption support impaired planning of learned speech actions.
Reasoning steps for option B
For aph-02 option B, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: The patient preserves language in comprehension and writing, so the core deficit is not aphasia.
For aph-02 option B, which case-specific contrast decides whether the choice fits?
The decisive comparison for Apraxia of speech from impaired speech planning is the remaining discriminator: Groping, inconsistent distortions, and prosodic disruption support impaired planning of learned speech actions.
C. Wernicke aphasia from posterior language injury (Why this does not fit)
Wernicke aphasia produces fluent output with impaired comprehension and often poor monitoring of content. This patient understands complex questions and writes accurate, grammatical responses.
Reasoning steps for option C
For aph-02 option C, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Wernicke aphasia produces fluent output with impaired comprehension and often poor monitoring of content.
For aph-02 option C, which case-specific contrast decides whether the choice fits?
The decisive comparison for Wernicke aphasia from posterior language injury is the remaining discriminator: This patient understands complex questions and writes accurate, grammatical responses.
D. Anomic aphasia from isolated word retrieval failure (Why this does not fit)
Anomic aphasia causes retrieval pauses or circumlocution while articulation remains structurally accurate. The dominant findings here are distorted, inconsistent speech sounds and groping.
Reasoning steps for option D
For aph-02 option D, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Anomic aphasia causes retrieval pauses or circumlocution while articulation remains structurally accurate.
For aph-02 option D, which case-specific contrast decides whether the choice fits?
The decisive comparison for Anomic aphasia from isolated word retrieval failure is the remaining discriminator: The dominant findings here are distorted, inconsistent speech sounds and groping.
Takeaway: Inconsistent distorted speech with preserved language supports apraxia of speech rather than aphasia.
Classical aphasia labels are useful summaries, not substitutes for testing. Start with three comparisons: Is connected output fluent? Is spoken comprehension relatively preserved? Is repetition relatively preserved? A profile may be incomplete, mixed, or different later in recovery, so the bedside findings remain primary. [1][8][15]
Figure 2. After fluency and comprehension are known, repetition often separates the closest profiles.
Profile
Output
Comprehension
Repetition
ProfileBroca
OutputNonfluent, often agrammatic
ComprehensionRelatively preserved
RepetitionImpaired
ProfileTranscortical motor
OutputNonfluent or poorly initiated
ComprehensionRelatively preserved
RepetitionRelatively preserved
ProfileWernicke
OutputFluent, often paraphasic
ComprehensionImpaired
RepetitionImpaired
ProfileTranscortical sensory
OutputFluent
ComprehensionImpaired
RepetitionRelatively preserved
ProfileConduction
OutputRelatively fluent
ComprehensionRelatively preserved
RepetitionDisproportionately impaired
ProfileGlobal
OutputSeverely limited
ComprehensionSeverely impaired
RepetitionSeverely impaired
ProfileMixed transcortical
OutputSeverely limited
ComprehensionImpaired
RepetitionRelatively preserved
ProfileAnomic
OutputFluent with retrieval pauses
ComprehensionRelatively preserved
RepetitionRelatively preserved
For a nonfluent patient with relatively good comprehension, preserved repetition favors a transcortical motor profile, while impaired repetition favors a Broca profile. For a fluent patient with poor comprehension, preserved repetition favors a transcortical sensory profile, while impaired repetition favors a Wernicke profile. Severe deficits in output and comprehension separate global from mixed transcortical aphasia by the same repetition comparison.
A conduction profile combines comparatively fluent output and comprehension with repetition that is worse than the rest of the examination. Long or phonologically complex material exposes the deficit better than a short familiar word. Anomia can occur in nearly every aphasia; use an anomic label when word retrieval is the predominant residual weakness and the other tested domains are comparatively stronger.
Do not treat the table as a rigid classifier. Broca aphasia can impair comprehension of complex syntax, and a person with global aphasia may preserve greetings or overlearned expressions. Echoing a sentence does not prove understanding. Copying written words does not prove access to meaning. The useful action is to identify the single discordant domain and test it with an unfamiliar task.
Translate the profile into a network hypothesis
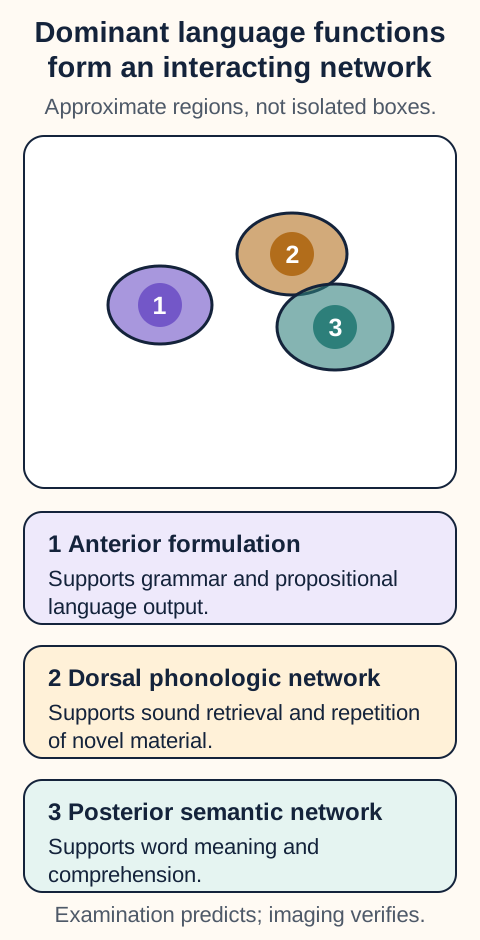
Distributed network. Language is distributed across dominant frontal, temporal, parietal, and subcortical systems. Inferior frontal regions contribute to structured output; posterior temporal and broader semantic systems support meaning; temporoparietal cortex and dorsal connections support phonologic processing and repetition. Lesion size, white matter involvement, perfusion, and individual organization determine the actual examination. [4][8][9]
Figure 3. Use the examination to choose an anterior, dorsal, posterior, or surrounding-network hypothesis.
Anterior
Anterior. Production, grammar, initiation
Dorsal
Dorsal. Sound coding and repetition
Posterior
Posterior. Meaning and comprehension
Surrounding regions
Surrounding regions. Isolation can preserve repetition
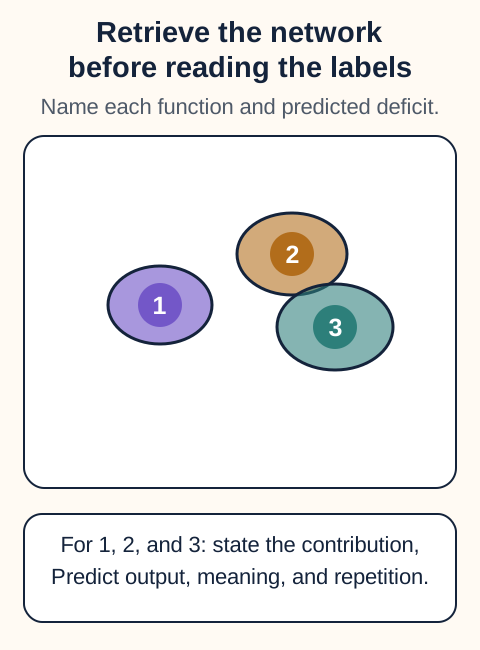
Figure 4. Retrieve the function and predicted deficit for regions 1 through 3 before reading the key.
Retrieval prompt Name the main contribution of each numbered region, then predict output, meaning, and repetition.
A dominant superior-division middle cerebral artery (MCA) infarct often affects anterior language regions and may add right face or arm weakness. An inferior-division MCA infarct can produce a fluent comprehension disorder without dense weakness. A large dominant MCA infarct can disrupt several systems and produce a global pattern. These are common arrangements, not one-to-one rules.
Watershed injury supplies a powerful prediction. Frontal or medial frontal hypoperfusion may reduce self-generated speech while sparing repetition, producing a transcortical motor pattern. Posterior border-zone injury may spare repetition despite poor comprehension. Extensive surrounding injury may leave the central perisylvian system relatively available but disconnected from association cortex, producing mixed transcortical aphasia.
Do not restrict aphasia to cortical MCA lesions. Dominant thalamic injury can disrupt connected language systems, and dominant anterior cerebral or posterior cerebral artery injury can affect language in characteristic contexts. Most people, including most left-handed people, have predominantly left-sided language, but handedness changes probability rather than proving dominance. Crossed aphasia classically describes aphasia after a right-hemisphere lesion in a right-handed person. [5][9]
Name the error and test the written-language dissociation
Describe errors before assigning a syndrome. A semantic paraphasia substitutes a related word, a phonemic paraphasia alters target sounds, a neologism is a nonword, circumlocution describes the target, perseveration repeats a prior response, and echolalia repeats another speaker. Each observation narrows the profile, but none establishes a location by itself. [1]
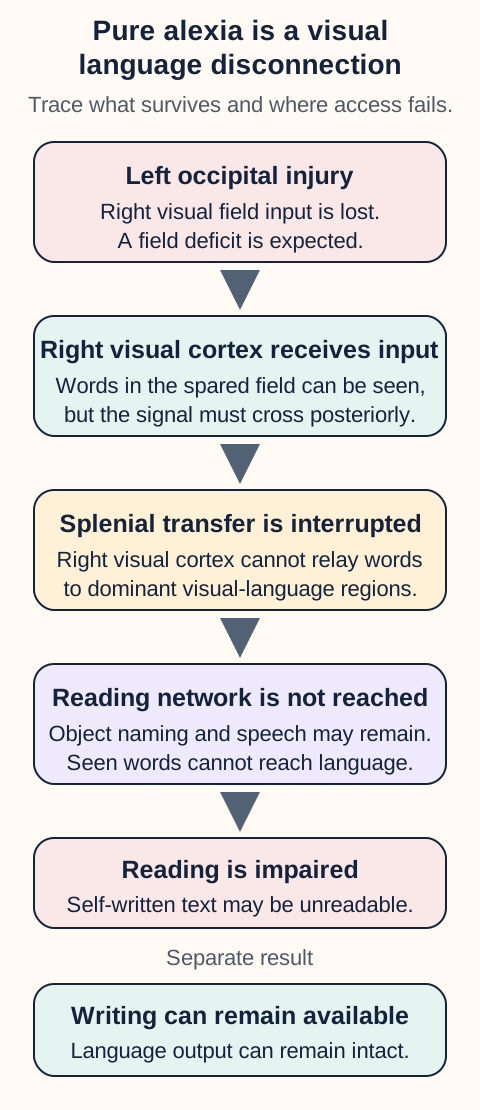
Reading aloud, understanding written material, spelling, and generating a written message are separable. In pure alexia, visual word recognition is severely impaired while writing is relatively preserved. A patient may write a coherent sentence and then be unable to read it. Visual fields must be tested because the classic pattern often includes a right homonymous field deficit. [6]
Figure 5. The classic reading disconnection preserves writing while visual word information cannot reach the dominant reading system.
Left occipital injury limits direct visual input to the dominant hemisphere.
The right visual cortex still receives part of the visual scene.
Posterior callosal injury blocks transfer to dominant reading regions.
Writing may remain available despite severe reading failure.
The classic arrangement combines left occipital and posterior callosal injury, often in dominant posterior cerebral artery territory. Ventral occipitotemporal injury can also impair word recognition, so no single lesion is mandatory. A field deficit alone may slow reading but does not create the full reading-writing dissociation.
Alexia with agraphia differs because both reading and writing are impaired. Dominant inferior parietal or angular-region dysfunction may accompany the Gerstmann cluster: agraphia, acalculia, finger agnosia, and left-right disorientation. The cluster supports a localization, but every component need not be present. [7]
Treat sudden aphasia as a time-sensitive neurologic emergency
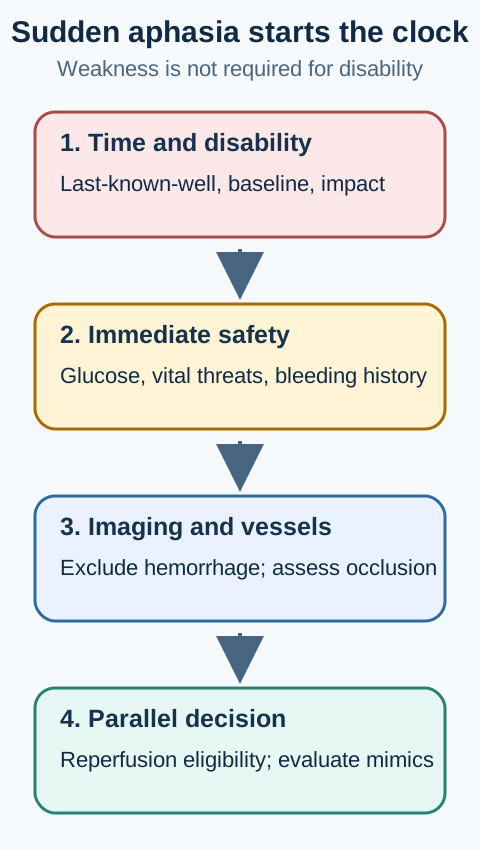
New sudden aphasia can be disabling even when limb strength is normal. Establish last-known-well time, check glucose, obtain urgent brain imaging, and activate the acute stroke pathway. Noncontrast computed tomography can exclude hemorrhage for many initial decisions, but a normal early scan does not exclude ischemia. Do not postpone an otherwise appropriate reperfusion decision solely to obtain routine magnetic resonance imaging. [3]
Figure 6. Sudden language loss triggers parallel timing, safety, vessel, and mimic assessment.
Confirm abrupt onset and last-known-well time.
Check glucose and immediate physiologic threats.
Image for hemorrhage and assess relevant vessels.
Decide reperfusion eligibility while evaluating plausible mimics.
Use parallel reasoning rather than serial delay. Seizure, severe glucose disturbance, migraine, toxic-metabolic illness, infection, and structural lesions can mimic aphasia. A witnessed convulsion or fluctuating deficit may increase seizure concern, but one reassuring feature does not cancel stroke evaluation. The key question is whether the proposed mimic explains the full domain pattern and time course.
After stabilization, repeat the domain examination. Perfusion, fatigue, medication effects, delirium, and early recovery can change performance. Document what the patient can currently understand and express rather than carrying forward a static label. A profile that begins globally impaired may later resemble Broca or anomic aphasia as domains recover unevenly. [1][10]
A brief stroke scale can identify language impairment but cannot replace a structured language examination. Record the patient's best response channel before procedures and handoffs so urgent consent, symptom reporting, and safety instructions remain possible. When imaging and examination disagree, reassess access barriers and consider seizure, hypoperfusion, or a lesion outside the expected cortical territory rather than forcing a classical location.
Try it here · Checkpoint 2 of 3
Make your prediction before reading the choices. A first attempt is just a starting point.
Case 24
Show answer and explanations for case 24
A. Observe because isolated aphasia is not disabling without weakness (Why this does not fit)
Aphasia can be profoundly disabling even when motor strength is preserved. Waiting would discard time-sensitive treatment opportunity based on an incorrect severity shortcut.
Reasoning steps for option A
For aph-24 option A, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Aphasia can be profoundly disabling even when motor strength is preserved.
For aph-24 option A, which case-specific contrast decides whether the choice fits?
The decisive comparison for Observe because isolated aphasia is not disabling without weakness is the remaining discriminator: Waiting would discard time-sensitive treatment opportunity based on an incorrect severity shortcut.
B. Obtain routine electroencephalography before any reperfusion decision (Why this does not fit)
Seizure is a possible mimic, but no seizure features are supplied and urgent treatment should not be delayed by routine testing when ischemic stroke is likely. Diagnostic testing should match the actual uncertainty and hemorrhage risk.
Reasoning steps for option B
For aph-24 option B, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Seizure is a possible mimic, but no seizure features are supplied and urgent treatment should not be delayed by routine testing when ischemic stroke is likely.
For aph-24 option B, which case-specific contrast decides whether the choice fits?
The decisive comparison for Obtain routine electroencephalography before any reperfusion decision is the remaining discriminator: Diagnostic testing should match the actual uncertainty and hemorrhage risk.
C. Wait for magnetic resonance imaging to prove an infarct (Why this does not fit)
Noncontrast computed tomography is sufficient initial imaging for many thrombolysis decisions when hemorrhage is excluded. Waiting for magnetic resonance imaging can create harmful delay.
Reasoning steps for option C
For aph-24 option C, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Noncontrast computed tomography is sufficient initial imaging for many thrombolysis decisions when hemorrhage is excluded.
For aph-24 option C, which case-specific contrast decides whether the choice fits?
The decisive comparison for Wait for magnetic resonance imaging to prove an infarct is the remaining discriminator: Waiting for magnetic resonance imaging can create harmful delay.
D. Proceed with immediate reperfusion eligibility assessment and treatment if criteria remain met (Best answer)
The patient has a recent disabling deficit, hemorrhage has been excluded, and no contraindication is identified. Current guidance supports prompt treatment rather than delaying for additional routine imaging.
Reasoning steps for option D
For aph-24 option D, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: The patient has a recent disabling deficit, hemorrhage has been excluded, and no contraindication is identified.
For aph-24 option D, which case-specific contrast decides whether the choice fits?
The decisive comparison for Proceed with immediate reperfusion eligibility assessment and treatment if criteria remain met is the remaining discriminator: Current guidance supports prompt treatment rather than delaying for additional routine imaging.
Takeaway: Sudden disabling aphasia requires the same urgent reperfusion assessment as other disabling stroke deficits.
Use trajectory before classifying progressive aphasia
Primary progressive aphasia begins insidiously, with language serving as the leading source of functional difficulty early in a neurodegenerative illness. Abrupt onset suggests another process. Before choosing a variant, establish the trajectory, confirm that language is the dominant early problem, and test the same domains used in acquired aphasia. [2]
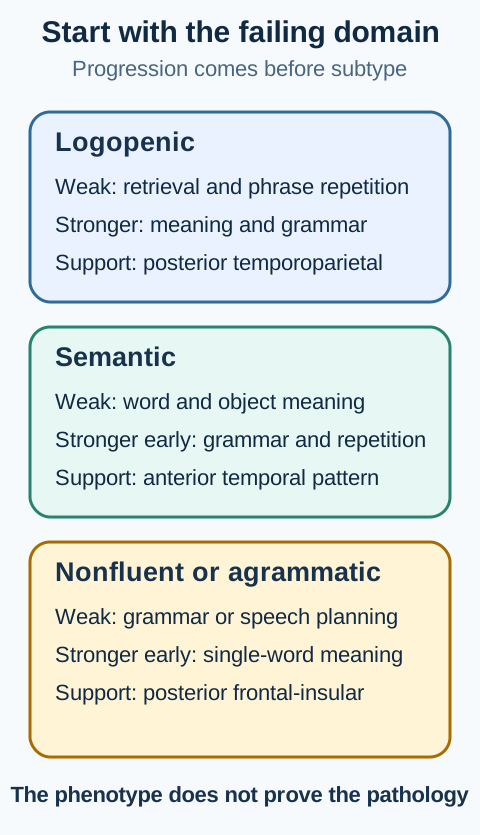
Figure 7. The three major progressive profiles separate by meaning, grammar and speech planning, and phrase repetition.
Logopenic
Logopenic. Word retrieval and phrase repetition fail; word meaning is stronger early.
Semantic
Semantic. Word and object meaning erode; grammar and repetition are stronger early.
Nonfluent or agrammatic
Nonfluent or agrammatic. Grammar or speech planning fails; single-word meaning is stronger early.
The logopenic variant features pauses for word retrieval and impaired phrase or sentence repetition, with relatively preserved single-word meaning and no prominent early agrammatism. The semantic variant produces loss of word meaning and object knowledge despite fluent grammatical speech and comparatively stronger repetition. The nonfluent or agrammatic variant requires agrammatism or effortful apraxic speech, often with relatively preserved single-word comprehension early. [2]
Imaging can support the phenotype: posterior temporal-inferior parietal involvement for logopenic disease, anterior temporal involvement for semantic disease, and posterior frontal-insular involvement for nonfluent or agrammatic disease. The clinical variant does not prove one protein pathology. Use biomarkers, genetics, or pathology when a specific biological cause would change counseling or treatment.
Refer early for speech-language assessment rather than waiting for severe loss. Treatment may include impairment-based practice, compensatory strategies, communication-partner training, personalized vocabulary or scripts, and augmentative communication introduced while learning capacity is stronger. Nearly every person with primary progressive aphasia can potentially benefit from individualized communication intervention, although the evidence base is smaller than for post-stroke aphasia. [12]
No medication is prescribed simply because the syndrome is called primary progressive aphasia. Treat a supported underlying disease and associated symptoms according to their own evidence, while keeping communication therapy central. Revisit driving, work, financial vulnerability, advance planning, and caregiver training as function changes. The clinical phenotype guides communication care even when biological certainty remains incomplete.
Build rehabilitation around function, not one test score
Post-stroke assessment should integrate language, motor speech, hearing, cognition, mood, and the communication demands of daily life. Start rehabilitation during acute care and maintain coordinated handoffs across inpatient, home, and outpatient settings. Combine restorative practice with compensatory supports instead of treating them as competing approaches. [10]
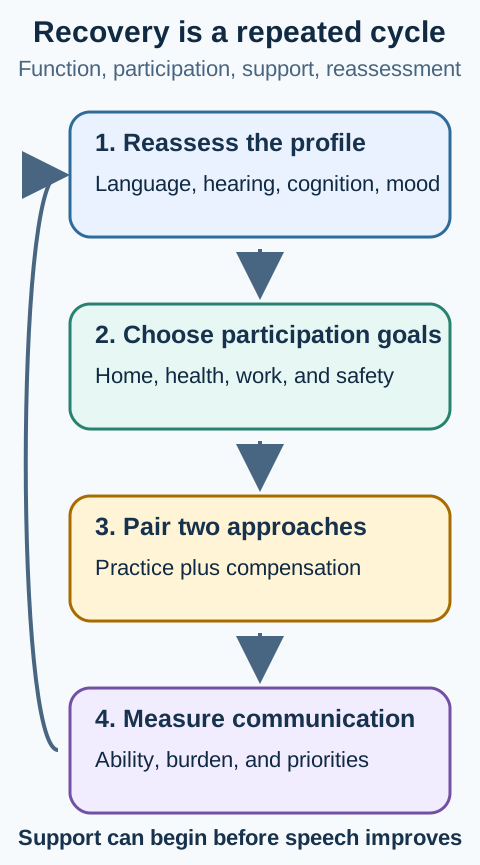
Figure 8. Reassessment links impairment practice to participation goals and communication supports.
Measure the current domain profile and access barriers.
Choose a meaningful participation goal with the patient.
Pair targeted practice with compensatory communication.
Reassess function, burden, and changing priorities.
Speech-language therapy improves functional communication, reading, writing, and expressive language compared with no therapy. Higher intensity or dose may help some patients, but higher-intensity programs also have greater dropout in trials. Choose tolerable intensity based on fatigue, severity, access, goals, and response rather than assuming that more hours are always better. [11]
Train communication partners to allow response time, verify meaning, reduce competing noise, write key choices, use pictures or gesture, and confirm decisions without speaking over the patient. Augmentative and alternative communication can supplement speech from the beginning; it is not evidence that recovery has ended. Telehealth, group treatment, and computerized practice may expand access when matched to the person's severity and context. [10]
Before interpreting a treatment plateau, recheck hearing, vision, sleep, mood, pain, medication burden, and cognitive load. A new hearing aid, larger print, shorter instructions, or a quieter setting may reveal ability that was hidden by access failure. This is why communication effectiveness, not spoken output alone, is the longitudinal outcome.
Three outcome levels. Track outcomes at three levels: the impaired function, the activity, and real participation. Naming accuracy matters, but so do ordering a meal, discussing symptoms, returning to work, and maintaining relationships. Periodic reassessment after discharge can identify decline, a new barrier, or a need for renewed therapy. [10][15]
Write the therapy dose in usable terms: minutes per session, sessions per week, home-practice burden, and the target behavior. Monitor fatigue, frustration, generalization, and attendance rather than counting scheduled hours alone. A patient who performs well in a quiet clinic but cannot communicate during a noisy medication review needs a different functional test, not simply a harder naming list.
Try it here · Checkpoint 3 of 3
Make your prediction before reading the choices. A first attempt is just a starting point.
Case 27
Show answer and explanations for case 27
A. Continue to record global aphasia because the initial label is permanent (Why this does not fit)
Aphasia profiles can change as different domains recover. Keeping the original label would understate the current improvement in comprehension.
Reasoning steps for option A
For aph-27 option A, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Aphasia profiles can change as different domains recover.
For aph-27 option A, which case-specific contrast decides whether the choice fits?
The decisive comparison for Continue to record global aphasia because the initial label is permanent is the remaining discriminator: Keeping the original label would understate the current improvement in comprehension.
B. Record an anomic profile because recovery has begun (Why this does not fit)
Anomic aphasia requires fluent output with retrieval difficulty as the predominant deficit. Speech remains short and agrammatic, and repetition remains impaired.
Reasoning steps for option B
For aph-27 option B, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Anomic aphasia requires fluent output with retrieval difficulty as the predominant deficit.
For aph-27 option B, which case-specific contrast decides whether the choice fits?
The decisive comparison for Record an anomic profile because recovery has begun is the remaining discriminator: Speech remains short and agrammatic, and repetition remains impaired.
C. Describe the current Broca-like profile and list the tested abilities (Best answer)
The current examination shows nonfluent agrammatic output, improved comprehension, and impaired repetition. Updating the descriptive profile communicates present function more accurately than preserving the initial global label.
Reasoning steps for option C
For aph-27 option C, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: The current examination shows nonfluent agrammatic output, improved comprehension, and impaired repetition.
For aph-27 option C, which case-specific contrast decides whether the choice fits?
The decisive comparison for Describe the current Broca-like profile and list the tested abilities is the remaining discriminator: Updating the descriptive profile communicates present function more accurately than preserving the initial global label.
D. Remove the aphasia diagnosis because comprehension improved (Why this does not fit)
Improved comprehension does not eliminate persistent language-formulation and repetition deficits. The patient still has aphasia, although its pattern has evolved.
Reasoning steps for option D
For aph-27 option D, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Improved comprehension does not eliminate persistent language-formulation and repetition deficits.
For aph-27 option D, which case-specific contrast decides whether the choice fits?
The decisive comparison for Remove the aphasia diagnosis because comprehension improved is the remaining discriminator: The patient still has aphasia, although its pattern has evolved.
Takeaway: Repeat the domain examination and update the profile as recovery changes the pattern.
Protect autonomy and monitor the complications that hide behind language loss
Aphasia does not equal incapacity. Capacity is decision-specific and depends on understanding, appreciation, reasoning, and communicating a choice. Support the communication channel before judging the decision. Use plain language, one idea at a time, written or pictorial choices when helpful, and a teach-back method adapted to the patient's strongest modality. [1]
Screen for depression, anxiety, social isolation, hearing loss, cognitive impairment, and caregiver strain. These problems can reduce participation and may be mistaken for language decline. Ask about driving, medication management, emergency communication, finances, work, and vulnerability to exploitation. The result should be a safety plan, not automatic removal of independence. [10][15]
Longitudinal documentation should state the current profile, communication supports that work, meaningful goals, who owns follow-up, and what change should trigger reassessment. A sudden new deficit returns to the emergency pathway. Gradual deterioration prompts evaluation for progressive disease or another neurologic process. A plateau after stroke does not end care if participation remains limited or a new life demand exposes an untreated barrier.
For a difficult decision, first optimize hearing, vision, language, and response time. Ask the patient to explain the situation in the strongest available modality, then assess appreciation of personal consequences, comparison of options, and a stable choice. A communication partner may assist access but should not substitute the partner's preference. Document both the support provided and the reasoning the patient demonstrated.
Rehabilitation does not replace cause-specific prevention. Coordinate vascular risk management after stroke, seizure treatment when indicated, and neurodegenerative counseling for progressive disease. The communication plan must travel with the patient across settings so that handoff failure does not become a preventable clinical error. [3][10]
Beyond the boards: convert the profile into an operational plan
In real acute care, four tracks proceed together: define onset and disability, exclude hemorrhage and major physiologic mimics, identify a treatable vascular lesion, and prepare communication support. Isolated aphasia may still be disabling. Reperfusion selection depends on the current guideline, imaging, timing, bleeding risk, and local protocol, not the presence or absence of weakness. [3]
For adults with eligible acute ischemic stroke, the current U.S. Activase label uses alteplase 0.9 mg/kg intravenously, maximum 90 mg, with 10% as a 1-minute bolus and the remainder over 60 minutes. The current TNKase label uses a weight-tiered single intravenous bolus over 5 seconds: 15 mg below 60 kg, 17.5 mg at 60 to under 70 kg, 20 mg at 70 to under 80 kg, 22.5 mg at 80 to under 90 kg, and 25 mg at 90 kg or more.
These are stroke-team regimens, not aphasia-specific treatment. Verify every dose against current labeling, the active guideline, the patient's weight, contraindications, and institutional protocol. [13][14]
Current guideline-based practice may consider selected thrombolysis beyond the three-hour product-label language, including patients treated within 4.5 hours, while the cited U.S. labels state initiation within three hours. This is a deliberate guideline-label distinction. Do not resolve it from memory. Use the active stroke protocol and document the basis for eligibility. Large-vessel occlusion assessment and thrombectomy selection also proceed on their own imaging and time criteria. [3][13][14]
Escalate referral according to the problem: abrupt language loss to emergency stroke care; persistent acquired aphasia to speech-language pathology and coordinated rehabilitation; progressive language loss to cognitive or behavioral neurology plus speech-language pathology; uncertain hearing access to audiology; and high-burden mood or safety concerns to the appropriate mental health and social supports. Referral timing matters because communication strategies are easier to learn before crisis or severe progression. [10][12]
Counsel with concrete expectations. Syndrome labels may change, recovery differs by domain, and no single therapy intensity suits everyone. Explain what the person can still do, demonstrate the support that improves communication today, name the next reassessment point, and give family members one observable reason to seek urgent care. The final plan should preserve patient participation while making emergencies, medications, and follow-up understandable.
A practical handoff can fit in five lines: current comprehension, current expression, reliable yes-no method, effective aids, and the change that requires escalation. Add the preferred language, hearing or visual needs, and the responsible follow-up clinician. This communication passport reduces repeated invalid testing and helps the next team include the patient from the first encounter.
Apply domains, location, time course, and care planning
The cases below require at least two findings. Predict the best discriminator before reading the options, then compare the keyed answer with every preserved and impaired domain in the stem.
Case 1
Show answer and explanations for case 1
A. Dysarthria affecting motor execution of speech (Best answer)
Language formulation and comprehension are preserved across spoken and written tasks. Consistent slurring and imprecise articulation instead localize the problem to motor execution of speech.
Reasoning steps for option A
For aph-01 option A, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Language formulation and comprehension are preserved across spoken and written tasks.
For aph-01 option A, which case-specific contrast decides whether the choice fits?
The decisive comparison for Dysarthria affecting motor execution of speech is the remaining discriminator: Consistent slurring and imprecise articulation instead localize the problem to motor execution of speech.
B. Broca aphasia affecting grammatical language output (Why this does not fit)
Broca aphasia would impair formulation of connected language, often producing short or agrammatic phrases. This patient can name objects and generate a complete written sentence despite poor articulation.
Reasoning steps for option B
For aph-01 option B, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Broca aphasia would impair formulation of connected language, often producing short or agrammatic phrases.
For aph-01 option B, which case-specific contrast decides whether the choice fits?
The decisive comparison for Broca aphasia affecting grammatical language output is the remaining discriminator: This patient can name objects and generate a complete written sentence despite poor articulation.
C. Apraxia of speech affecting learned speech planning (Why this does not fit)
Apraxia of speech often produces effortful initiation, distorted sound substitutions, and inconsistency across attempts. The repeated errors here are stable and slurred, which better fits impaired motor execution.
Reasoning steps for option C
For aph-01 option C, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Apraxia of speech often produces effortful initiation, distorted sound substitutions, and inconsistency across attempts.
For aph-01 option C, which case-specific contrast decides whether the choice fits?
The decisive comparison for Apraxia of speech affecting learned speech planning is the remaining discriminator: The repeated errors here are stable and slurred, which better fits impaired motor execution.
D. Global aphasia affecting several language domains (Why this does not fit)
Global aphasia severely impairs expression, comprehension, and repetition. This patient follows a complex command and demonstrates intact naming and written language.
Reasoning steps for option D
For aph-01 option D, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Global aphasia severely impairs expression, comprehension, and repetition.
For aph-01 option D, which case-specific contrast decides whether the choice fits?
The decisive comparison for Global aphasia affecting several language domains is the remaining discriminator: This patient follows a complex command and demonstrates intact naming and written language.
Takeaway: Demonstrate language separately from articulation before labeling difficult speech aphasia.
Broca aphasia can be nonfluent with relatively preserved comprehension, but repetition is usually impaired. Accurate repetition of a long unfamiliar sentence is the key discordant finding.
Reasoning steps for option A
For aph-03 option A, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Broca aphasia can be nonfluent with relatively preserved comprehension, but repetition is usually impaired.
For aph-03 option A, which case-specific contrast decides whether the choice fits?
The decisive comparison for Broca aphasia is the remaining discriminator: Accurate repetition of a long unfamiliar sentence is the key discordant finding.
B. Anomic aphasia (Why this does not fit)
Anomic aphasia is usually fluent, with word retrieval pauses as the predominant deficit. Markedly reduced spontaneous output does not fit that residual pattern.
Reasoning steps for option B
For aph-03 option B, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Anomic aphasia is usually fluent, with word retrieval pauses as the predominant deficit.
For aph-03 option B, which case-specific contrast decides whether the choice fits?
The decisive comparison for Anomic aphasia is the remaining discriminator: Markedly reduced spontaneous output does not fit that residual pattern.
C. Transcortical motor aphasia (Best answer)
Poor initiation or nonfluent output with comparatively preserved comprehension and repetition defines a transcortical motor profile. The frontal border-zone lesion supplies a compatible vascular arrangement.
Reasoning steps for option C
For aph-03 option C, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Poor initiation or nonfluent output with comparatively preserved comprehension and repetition defines a transcortical motor profile.
For aph-03 option C, which case-specific contrast decides whether the choice fits?
The decisive comparison for Transcortical motor aphasia is the remaining discriminator: The frontal border-zone lesion supplies a compatible vascular arrangement.
D. Conduction aphasia with disproportionate repetition failure (Why this does not fit)
Conduction aphasia is relatively fluent and is distinguished by disproportionate repetition failure. This patient shows the opposite repetition pattern.
Reasoning steps for option D
For aph-03 option D, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Conduction aphasia is relatively fluent and is distinguished by disproportionate repetition failure.
For aph-03 option D, which case-specific contrast decides whether the choice fits?
The decisive comparison for Conduction aphasia with disproportionate repetition failure is the remaining discriminator: This patient shows the opposite repetition pattern.
Takeaway: Preserved repetition separates transcortical motor aphasia from a neighboring Broca profile.
A. Wernicke aphasia with impaired sentence repetition (Why this does not fit)
Wernicke aphasia explains fluent output and impaired comprehension, but repetition is generally impaired. Accurate sentence repetition and echolalia identify a different profile.
Reasoning steps for option A
For aph-04 option A, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Wernicke aphasia explains fluent output and impaired comprehension, but repetition is generally impaired.
For aph-04 option A, which case-specific contrast decides whether the choice fits?
The decisive comparison for Wernicke aphasia with impaired sentence repetition is the remaining discriminator: Accurate sentence repetition and echolalia identify a different profile.
B. Conduction aphasia (Why this does not fit)
Conduction aphasia preserves comprehension better than this and produces disproportionate repetition failure. Both defining comparisons run opposite to the findings.
Reasoning steps for option B
For aph-04 option B, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Conduction aphasia preserves comprehension better than this and produces disproportionate repetition failure.
For aph-04 option B, which case-specific contrast decides whether the choice fits?
The decisive comparison for Conduction aphasia is the remaining discriminator: Both defining comparisons run opposite to the findings.
C. Anomic aphasia (Why this does not fit)
Anomic aphasia preserves comprehension and repetition, with retrieval difficulty as the main deficit. Severe word-object and command comprehension failure excludes that pattern.
Reasoning steps for option C
For aph-04 option C, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Anomic aphasia preserves comprehension and repetition, with retrieval difficulty as the main deficit.
For aph-04 option C, which case-specific contrast decides whether the choice fits?
The decisive comparison for Anomic aphasia is the remaining discriminator: Severe word-object and command comprehension failure excludes that pattern.
D. Transcortical sensory aphasia (Best answer)
Fluent low-content output and impaired comprehension resemble a posterior language disorder, while preserved repetition identifies the transcortical sensory pattern. Echolalia can make that preservation conspicuous.
Reasoning steps for option D
For aph-04 option D, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Fluent low-content output and impaired comprehension resemble a posterior language disorder, while preserved repetition identifies the transcortical sensory pattern.
For aph-04 option D, which case-specific contrast decides whether the choice fits?
The decisive comparison for Transcortical sensory aphasia is the remaining discriminator: Echolalia can make that preservation conspicuous.
Takeaway: Preserved repetition distinguishes transcortical sensory aphasia from Wernicke aphasia.
Conversational fluency and comprehension are comparatively preserved, while repetition is disproportionately impaired. Phonemic errors and successive approximations toward a target further support a conduction profile.
Reasoning steps for option A
For aph-05 option A, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Conversational fluency and comprehension are comparatively preserved, while repetition is disproportionately impaired.
For aph-05 option A, which case-specific contrast decides whether the choice fits?
The decisive comparison for Conduction aphasia is the remaining discriminator: Phonemic errors and successive approximations toward a target further support a conduction profile.
B. Wernicke aphasia (Why this does not fit)
Wernicke aphasia can be fluent and paraphasic, but spoken comprehension is usually substantially impaired. This patient follows complex commands reliably.
Reasoning steps for option B
For aph-05 option B, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Wernicke aphasia can be fluent and paraphasic, but spoken comprehension is usually substantially impaired.
For aph-05 option B, which case-specific contrast decides whether the choice fits?
The decisive comparison for Wernicke aphasia is the remaining discriminator: This patient follows complex commands reliably.
C. Transcortical sensory aphasia (Why this does not fit)
Transcortical sensory aphasia combines poor comprehension with relatively preserved repetition. Both domains in this case show the reverse relationship.
Reasoning steps for option C
For aph-05 option C, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Transcortical sensory aphasia combines poor comprehension with relatively preserved repetition.
For aph-05 option C, which case-specific contrast decides whether the choice fits?
The decisive comparison for Transcortical sensory aphasia is the remaining discriminator: Both domains in this case show the reverse relationship.
D. Apraxia of speech (Why this does not fit)
Apraxia of speech can disrupt sound production, but it does not by itself explain a selective collapse of linguistic repetition with fluent conversation and intact comprehension. The examination describes a language-network dissociation.
Reasoning steps for option D
For aph-05 option D, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Apraxia of speech can disrupt sound production, but it does not by itself explain a selective collapse of linguistic repetition with fluent conversation and intact comprehension.
For aph-05 option D, which case-specific contrast decides whether the choice fits?
The decisive comparison for Apraxia of speech is the remaining discriminator: The examination describes a language-network dissociation.
Takeaway: Disproportionate repetition failure with stronger comprehension and fluency supports conduction aphasia.
A. Global aphasia with severely impaired repetition (Why this does not fit)
Global aphasia can severely impair output and comprehension, but repetition is also severely impaired. Exact repetition is the feature that argues against the global profile.
Reasoning steps for option A
For aph-06 option A, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Global aphasia can severely impair output and comprehension, but repetition is also severely impaired.
For aph-06 option A, which case-specific contrast decides whether the choice fits?
The decisive comparison for Global aphasia with severely impaired repetition is the remaining discriminator: Exact repetition is the feature that argues against the global profile.
B. Mixed transcortical aphasia (Best answer)
Severely limited self-generated output and poor comprehension coexist with unexpectedly preserved repetition. Echolalia after a watershed event is a classic expression of network isolation.
Reasoning steps for option B
For aph-06 option B, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Severely limited self-generated output and poor comprehension coexist with unexpectedly preserved repetition.
For aph-06 option B, which case-specific contrast decides whether the choice fits?
The decisive comparison for Mixed transcortical aphasia is the remaining discriminator: Echolalia after a watershed event is a classic expression of network isolation.
C. Broca aphasia (Why this does not fit)
Broca aphasia causes nonfluent output with better comprehension than shown here and usually impaired repetition. The patient has severe comprehension failure with accurate repetition.
Reasoning steps for option C
For aph-06 option C, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Broca aphasia causes nonfluent output with better comprehension than shown here and usually impaired repetition.
For aph-06 option C, which case-specific contrast decides whether the choice fits?
The decisive comparison for Broca aphasia is the remaining discriminator: The patient has severe comprehension failure with accurate repetition.
D. Anomic aphasia (Why this does not fit)
Anomic aphasia is fluent and preserves comprehension, with naming as the predominant weakness. It cannot account for severe deficits in spontaneous output and understanding.
Reasoning steps for option D
For aph-06 option D, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Anomic aphasia is fluent and preserves comprehension, with naming as the predominant weakness.
For aph-06 option D, which case-specific contrast decides whether the choice fits?
The decisive comparison for Anomic aphasia is the remaining discriminator: It cannot account for severe deficits in spontaneous output and understanding.
Takeaway: Preserved repetition separates mixed transcortical aphasia from global aphasia.
Conduction aphasia requires disproportionate repetition impairment, which is absent. Circumlocution alone does not establish that syndrome.
Reasoning steps for option A
For aph-07 option A, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Conduction aphasia requires disproportionate repetition impairment, which is absent.
For aph-07 option A, which case-specific contrast decides whether the choice fits?
The decisive comparison for Conduction aphasia is the remaining discriminator: Circumlocution alone does not establish that syndrome.
B. Transcortical motor aphasia (Why this does not fit)
Transcortical motor aphasia produces reduced initiation or nonfluent output. This patient speaks fluently in complete sentences.
Reasoning steps for option B
For aph-07 option B, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Transcortical motor aphasia produces reduced initiation or nonfluent output.
For aph-07 option B, which case-specific contrast decides whether the choice fits?
The decisive comparison for Transcortical motor aphasia is the remaining discriminator: This patient speaks fluently in complete sentences.
C. Anomic aphasia (Best answer)
Fluent grammatical speech, preserved comprehension, and preserved repetition leave word retrieval as the predominant deficit. Circumlocution is a common strategy when the target word is inaccessible.
Reasoning steps for option C
For aph-07 option C, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Fluent grammatical speech, preserved comprehension, and preserved repetition leave word retrieval as the predominant deficit.
For aph-07 option C, which case-specific contrast decides whether the choice fits?
The decisive comparison for Anomic aphasia is the remaining discriminator: Circumlocution is a common strategy when the target word is inaccessible.
D. Wernicke aphasia (Why this does not fit)
Wernicke aphasia includes impaired comprehension and often inaccurate content monitoring. This patient understands conversation and selects the correct target when it is supplied.
Reasoning steps for option D
For aph-07 option D, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Wernicke aphasia includes impaired comprehension and often inaccurate content monitoring.
For aph-07 option D, which case-specific contrast decides whether the choice fits?
The decisive comparison for Wernicke aphasia is the remaining discriminator: This patient understands conversation and selects the correct target when it is supplied.
Takeaway: Update the syndrome label as recovery leaves a predominantly anomic profile.
Global aphasia causes severe impairment across output, comprehension, and repetition. This patient understands simple commands and shows a selective syntax-sensitive comprehension deficit rather than broad comprehension failure.
Reasoning steps for option A
For aph-08 option A, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Global aphasia causes severe impairment across output, comprehension, and repetition.
For aph-08 option A, which case-specific contrast decides whether the choice fits?
The decisive comparison for Global aphasia is the remaining discriminator: This patient understands simple commands and shows a selective syntax-sensitive comprehension deficit rather than broad comprehension failure.
B. Wernicke aphasia (Why this does not fit)
Wernicke aphasia usually produces fluent output with a broader comprehension disorder. The nonfluent agrammatic speech and inferior frontal lesion point to an anterior profile.
Reasoning steps for option B
For aph-08 option B, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Wernicke aphasia usually produces fluent output with a broader comprehension disorder.
For aph-08 option B, which case-specific contrast decides whether the choice fits?
The decisive comparison for Wernicke aphasia is the remaining discriminator: The nonfluent agrammatic speech and inferior frontal lesion point to an anterior profile.
C. Isolated auditory processing disorder (Why this does not fit)
An isolated auditory disorder would impair access to spoken material more consistently. The contrast between simple commands and grammatically demanding sentences indicates a language-syntax problem.
Reasoning steps for option C
For aph-08 option C, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: An isolated auditory disorder would impair access to spoken material more consistently.
For aph-08 option C, which case-specific contrast decides whether the choice fits?
The decisive comparison for Isolated auditory processing disorder is the remaining discriminator: The contrast between simple commands and grammatically demanding sentences indicates a language-syntax problem.
D. Broca aphasia (Best answer)
Broca aphasia often preserves simple comprehension better than language output while complex grammatical relations can still fail. Nonfluent agrammatic speech with impaired repetition supports this diagnosis.
Reasoning steps for option D
For aph-08 option D, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Broca aphasia often preserves simple comprehension better than language output while complex grammatical relations can still fail.
For aph-08 option D, which case-specific contrast decides whether the choice fits?
The decisive comparison for Broca aphasia is the remaining discriminator: Nonfluent agrammatic speech with impaired repetition supports this diagnosis.
Takeaway: Broca aphasia can preserve simple comprehension while complex grammatical relations remain difficult.
A. Dominant posterior temporal language cortex supplied by the inferior middle cerebral artery division (Best answer)
Fluent low-content output with impaired comprehension and repetition supports a posterior perisylvian language lesion. Inferior-division involvement can occur without dense motor weakness.
Reasoning steps for option A
For aph-09 option A, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Fluent low-content output with impaired comprehension and repetition supports a posterior perisylvian language lesion.
For aph-09 option A, which case-specific contrast decides whether the choice fits?
The decisive comparison for Dominant posterior temporal language cortex supplied by the inferior middle cerebral artery division is the remaining discriminator: Inferior-division involvement can occur without dense motor weakness.
B. Dominant inferior frontal language cortex supplied by the superior middle cerebral artery division (Why this does not fit)
An inferior frontal lesion is more likely to produce nonfluent, effortful, or agrammatic output. The fluent comprehension disorder points posteriorly.
Reasoning steps for option B
For aph-09 option B, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: An inferior frontal lesion is more likely to produce nonfluent, effortful, or agrammatic output.
For aph-09 option B, which case-specific contrast decides whether the choice fits?
The decisive comparison for Dominant inferior frontal language cortex supplied by the superior middle cerebral artery division is the remaining discriminator: The fluent comprehension disorder points posteriorly.
C. Nondominant parietal association cortex causing hemispatial neglect (Why this does not fit)
Neglect can impair attention to one side of space but does not explain fluent neologistic speech with impaired spoken comprehension and repetition. The language profile localizes to the dominant hemisphere.
Reasoning steps for option C
For aph-09 option C, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Neglect can impair attention to one side of space but does not explain fluent neologistic speech with impaired spoken comprehension and repetition.
For aph-09 option C, which case-specific contrast decides whether the choice fits?
The decisive comparison for Nondominant parietal association cortex causing hemispatial neglect is the remaining discriminator: The language profile localizes to the dominant hemisphere.
D. Bilateral corticobulbar pathways causing pseudobulbar dysarthria (Why this does not fit)
Bilateral corticobulbar injury can alter articulation and emotional expression. It does not account for fluent language that lacks meaning or for failure of comprehension.
Reasoning steps for option D
For aph-09 option D, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Bilateral corticobulbar injury can alter articulation and emotional expression.
For aph-09 option D, which case-specific contrast decides whether the choice fits?
The decisive comparison for Bilateral corticobulbar pathways causing pseudobulbar dysarthria is the remaining discriminator: It does not account for fluent language that lacks meaning or for failure of comprehension.
Takeaway: Posterior dominant language injury can produce severe aphasia without dense hemiparesis.
A. Inferior division of the dominant middle cerebral artery (Why this does not fit)
Inferior-division injury is more strongly associated with posterior temporal language dysfunction and often lacks dense face-arm weakness. The speech profile and motor pattern point anteriorly.
Reasoning steps for option A
For aph-10 option A, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Inferior-division injury is more strongly associated with posterior temporal language dysfunction and often lacks dense face-arm weakness.
For aph-10 option A, which case-specific contrast decides whether the choice fits?
The decisive comparison for Inferior division of the dominant middle cerebral artery is the remaining discriminator: The speech profile and motor pattern point anteriorly.
B. Superior division of the dominant middle cerebral artery (Best answer)
The nonfluent agrammatic profile localizes to dominant inferior frontal language regions. Right face and arm weakness with relative leg sparing is compatible with adjacent lateral frontal motor cortex injury in the superior division.
Reasoning steps for option B
For aph-10 option B, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: The nonfluent agrammatic profile localizes to dominant inferior frontal language regions.
For aph-10 option B, which case-specific contrast decides whether the choice fits?
The decisive comparison for Superior division of the dominant middle cerebral artery is the remaining discriminator: Right face and arm weakness with relative leg sparing is compatible with adjacent lateral frontal motor cortex injury in the superior division.
C. Dominant posterior cerebral artery (Why this does not fit)
Dominant posterior cerebral artery injury can affect reading, memory, or posterior language pathways. It does not best fit the combined inferior frontal language pattern and lateral face-arm motor deficit.
Reasoning steps for option C
For aph-10 option C, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Dominant posterior cerebral artery injury can affect reading, memory, or posterior language pathways.
For aph-10 option C, which case-specific contrast decides whether the choice fits?
The decisive comparison for Dominant posterior cerebral artery is the remaining discriminator: It does not best fit the combined inferior frontal language pattern and lateral face-arm motor deficit.
D. Dominant anterior cerebral artery (Why this does not fit)
Anterior cerebral artery injury more often affects medial frontal structures and the contralateral leg. The prominent face-arm weakness and inferior frontal language findings fit a lateral middle cerebral artery distribution.
Reasoning steps for option D
For aph-10 option D, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Anterior cerebral artery injury more often affects medial frontal structures and the contralateral leg.
For aph-10 option D, which case-specific contrast decides whether the choice fits?
The decisive comparison for Dominant anterior cerebral artery is the remaining discriminator: The prominent face-arm weakness and inferior frontal language findings fit a lateral middle cerebral artery distribution.
Takeaway: Combine the language profile with the motor distribution when forming a vascular hypothesis.
A. Posterior temporal language cortex (Why this does not fit)
Posterior temporal injury usually impairs comprehension and can produce fluent low-content speech. Comprehension and repetition are both strong here.
Reasoning steps for option A
For aph-11 option A, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Posterior temporal injury usually impairs comprehension and can produce fluent low-content speech.
For aph-11 option A, which case-specific contrast decides whether the choice fits?
The decisive comparison for Posterior temporal language cortex is the remaining discriminator: Comprehension and repetition are both strong here.
B. Dorsal temporoparietal repetition network (Why this does not fit)
Damage to the dorsal repetition network would be expected to impair repetition disproportionately. Accurate long-sentence repetition argues against that localization.
Reasoning steps for option B
For aph-11 option B, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Damage to the dorsal repetition network would be expected to impair repetition disproportionately.
For aph-11 option B, which case-specific contrast decides whether the choice fits?
The decisive comparison for Dorsal temporoparietal repetition network is the remaining discriminator: Accurate long-sentence repetition argues against that localization.
C. Dominant frontal border-zone or medial frontal language network (Best answer)
Hypoperfusion can affect frontal border-zone or medial frontal regions that support initiation. Sparse self-generated speech with preserved comprehension and repetition fits a transcortical motor profile.
Reasoning steps for option C
For aph-11 option C, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Hypoperfusion can affect frontal border-zone or medial frontal regions that support initiation.
For aph-11 option C, which case-specific contrast decides whether the choice fits?
The decisive comparison for Dominant frontal border-zone or medial frontal language network is the remaining discriminator: Sparse self-generated speech with preserved comprehension and repetition fits a transcortical motor profile.
D. Left occipital cortex and posterior callosal fibers (Why this does not fit)
That combination is associated with a reading disconnection, often with preserved writing. It does not explain selective loss of speech initiation with intact repetition.
Reasoning steps for option D
For aph-11 option D, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: That combination is associated with a reading disconnection, often with preserved writing.
For aph-11 option D, which case-specific contrast decides whether the choice fits?
The decisive comparison for Left occipital cortex and posterior callosal fibers is the remaining discriminator: It does not explain selective loss of speech initiation with intact repetition.
Takeaway: After hypotension, sparse output with preserved repetition suggests a frontal border-zone profile.
A. Dominant inferior frontal injury (Why this does not fit)
Inferior frontal injury usually produces nonfluent or agrammatic output. This patient is fluent and has marked comprehension failure.
Reasoning steps for option A
For aph-12 option A, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Inferior frontal injury usually produces nonfluent or agrammatic output.
For aph-12 option A, which case-specific contrast decides whether the choice fits?
The decisive comparison for Dominant inferior frontal injury is the remaining discriminator: This patient is fluent and has marked comprehension failure.
B. Dominant dorsal temporoparietal injury (Why this does not fit)
Dorsal temporoparietal injury is associated with disproportionate repetition impairment. Repetition is preserved in this case.
Reasoning steps for option B
For aph-12 option B, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Dorsal temporoparietal injury is associated with disproportionate repetition impairment.
For aph-12 option B, which case-specific contrast decides whether the choice fits?
The decisive comparison for Dominant dorsal temporoparietal injury is the remaining discriminator: Repetition is preserved in this case.
C. Large dominant perisylvian infarction (Why this does not fit)
A large perisylvian infarct can produce global aphasia with severe impairment of repetition. Preserved sentence repetition argues for relative sparing of the central perisylvian network.
Reasoning steps for option C
For aph-12 option C, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: A large perisylvian infarct can produce global aphasia with severe impairment of repetition.
For aph-12 option C, which case-specific contrast decides whether the choice fits?
The decisive comparison for Large dominant perisylvian infarction is the remaining discriminator: Preserved sentence repetition argues for relative sparing of the central perisylvian network.
D. Dominant posterior border-zone injury (Best answer)
Posterior border-zone injury can impair comprehension while leaving repetition comparatively preserved. The hypotensive setting and fluent transcortical sensory profile support this arrangement.
Reasoning steps for option D
For aph-12 option D, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Posterior border-zone injury can impair comprehension while leaving repetition comparatively preserved.
For aph-12 option D, which case-specific contrast decides whether the choice fits?
The decisive comparison for Dominant posterior border-zone injury is the remaining discriminator: The hypotensive setting and fluent transcortical sensory profile support this arrangement.
Takeaway: Posterior border-zone injury can mimic Wernicke aphasia while preserving repetition.
A. The core perisylvian language network is relatively spared but isolated from surrounding association cortex (Best answer)
Preserved repetition suggests that central perisylvian language pathways remain relatively available. Extensive surrounding watershed injury can isolate that network, producing a mixed transcortical profile.
Reasoning steps for option A
For aph-13 option A, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Preserved repetition suggests that central perisylvian language pathways remain relatively available.
For aph-13 option A, which case-specific contrast decides whether the choice fits?
The decisive comparison for The core perisylvian language network is relatively spared but isolated from surrounding association cortex is the remaining discriminator: Extensive surrounding watershed injury can isolate that network, producing a mixed transcortical profile.
B. The entire dominant perisylvian network is destroyed (Why this does not fit)
Destruction of the entire perisylvian network would severely impair repetition as part of a global profile. Accurate sentence repetition is inconsistent with complete destruction.
Reasoning steps for option B
For aph-13 option B, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Destruction of the entire perisylvian network would severely impair repetition as part of a global profile.
For aph-13 option B, which case-specific contrast decides whether the choice fits?
The decisive comparison for The entire dominant perisylvian network is destroyed is the remaining discriminator: Accurate sentence repetition is inconsistent with complete destruction.
C. A pure motor speech disorder prevents all self-generated language (Why this does not fit)
A motor speech disorder would also affect repeated speech unless a highly specific dissociation were demonstrated. Here repetition is clear while comprehension and naming are severely impaired, indicating language dysfunction.
Reasoning steps for option C
For aph-13 option C, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: A motor speech disorder would also affect repeated speech unless a highly specific dissociation were demonstrated.
For aph-13 option C, which case-specific contrast decides whether the choice fits?
The decisive comparison for A pure motor speech disorder prevents all self-generated language is the remaining discriminator: Here repetition is clear while comprehension and naming are severely impaired, indicating language dysfunction.
D. A posterior visual pathway lesion prevents understanding spoken commands (Why this does not fit)
A posterior visual lesion can impair reading or visual fields but does not explain failure of spoken comprehension and naming. The preserved repetition with severe language deficits points to network isolation.
Reasoning steps for option D
For aph-13 option D, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: A posterior visual lesion can impair reading or visual fields but does not explain failure of spoken comprehension and naming.
For aph-13 option D, which case-specific contrast decides whether the choice fits?
The decisive comparison for A posterior visual pathway lesion prevents understanding spoken commands is the remaining discriminator: The preserved repetition with severe language deficits points to network isolation.
Takeaway: Mixed transcortical aphasia reflects severe surrounding injury with relative preservation of repetition pathways.
A. The aphasia must be psychogenic because cortex is intact (Why this does not fit)
Aphasia can arise from subcortical injury through disruption of connected language networks. Absence of a cortical infarct does not make the deficit psychogenic.
Reasoning steps for option A
For aph-14 option A, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Aphasia can arise from subcortical injury through disruption of connected language networks.
For aph-14 option A, which case-specific contrast decides whether the choice fits?
The decisive comparison for The aphasia must be psychogenic because cortex is intact is the remaining discriminator: Absence of a cortical infarct does not make the deficit psychogenic.
B. Dominant thalamic injury can produce aphasia through network disruption (Best answer)
The thalamus participates in distributed cortical-subcortical systems. A dominant thalamic lesion can alter language through network dysfunction even when classical cortical regions appear structurally intact.
Reasoning steps for option B
For aph-14 option B, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: The thalamus participates in distributed cortical-subcortical systems.
For aph-14 option B, which case-specific contrast decides whether the choice fits?
The decisive comparison for Dominant thalamic injury can produce aphasia through network disruption is the remaining discriminator: A dominant thalamic lesion can alter language through network dysfunction even when classical cortical regions appear structurally intact.
C. The lesion proves a fixed Wernicke profile with predictable abilities (Why this does not fit)
A fluent comprehension disorder can resemble a posterior cortical profile, but the observed domains should be documented directly. A lesion site does not guarantee every feature of a named syndrome.
Reasoning steps for option C
For aph-14 option C, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: A fluent comprehension disorder can resemble a posterior cortical profile, but the observed domains should be documented directly.
For aph-14 option C, which case-specific contrast decides whether the choice fits?
The decisive comparison for The lesion proves a fixed Wernicke profile with predictable abilities is the remaining discriminator: A lesion site does not guarantee every feature of a named syndrome.
D. Only middle cerebral artery lesions can cause acquired aphasia (Why this does not fit)
Language dysfunction can follow dominant thalamic, anterior cerebral, posterior cerebral, or other subcortical lesions. Restricting aphasia to one arterial territory is too narrow.
Reasoning steps for option D
For aph-14 option D, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Language dysfunction can follow dominant thalamic, anterior cerebral, posterior cerebral, or other subcortical lesions.
For aph-14 option D, which case-specific contrast decides whether the choice fits?
The decisive comparison for Only middle cerebral artery lesions can cause acquired aphasia is the remaining discriminator: Restricting aphasia to one arterial territory is too narrow.
Takeaway: Language localization is network based; subcortical lesions can produce genuine aphasia.
A. Global aphasia caused by a typical left-dominant network (Why this does not fit)
The domain profile may be global in severity, but the causative lesion is in the right hemisphere. A typical left-dominant description does not account for the observed lateralization.
Reasoning steps for option A
For aph-15 option A, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: The domain profile may be global in severity, but the causative lesion is in the right hemisphere.
For aph-15 option A, which case-specific contrast decides whether the choice fits?
The decisive comparison for Global aphasia caused by a typical left-dominant network is the remaining discriminator: A typical left-dominant description does not account for the observed lateralization.
B. Bilateral language representation established solely by the patient's right-handedness (Why this does not fit)
Right-handedness increases the probability of left dominance but does not establish bilateral representation. The deficit after a unilateral right lesion supports atypical right-sided language organization.
Reasoning steps for option B
For aph-15 option B, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Right-handedness increases the probability of left dominance but does not establish bilateral representation.
For aph-15 option B, which case-specific contrast decides whether the choice fits?
The decisive comparison for Bilateral language representation established solely by the patient's right-handedness is the remaining discriminator: The deficit after a unilateral right lesion supports atypical right-sided language organization.
C. Crossed aphasia after a right-hemisphere lesion in a right-handed person (Best answer)
Crossed aphasia classically refers to aphasia from a right-hemisphere lesion in a right-handed person. The broad acquired language impairment and adequate sensory access support that label.
Reasoning steps for option C
For aph-15 option C, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Crossed aphasia classically refers to aphasia from a right-hemisphere lesion in a right-handed person.
For aph-15 option C, which case-specific contrast decides whether the choice fits?
The decisive comparison for Crossed aphasia after a right-hemisphere lesion in a right-handed person is the remaining discriminator: The broad acquired language impairment and adequate sensory access support that label.
D. Nondominant neglect misclassified as a language disorder (Why this does not fit)
Neglect can impair exploration and response, but it does not explain deficits across spoken comprehension, repetition, reading, and writing when attention and sensory access are adequate. The pattern demonstrates acquired language dysfunction.
Reasoning steps for option D
For aph-15 option D, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Neglect can impair exploration and response, but it does not explain deficits across spoken comprehension, repetition, reading, and writing when attention and sensory access are adequate.
For aph-15 option D, which case-specific contrast decides whether the choice fits?
The decisive comparison for Nondominant neglect misclassified as a language disorder is the remaining discriminator: The pattern demonstrates acquired language dysfunction.
Takeaway: Handedness changes the probability of language dominance but does not determine it.
A. Phonemic paraphasia followed by echolalia (Why this does not fit)
A phonemic paraphasia changes the sound structure of a target, while echolalia repeats another person's utterance. Neither label matches the related-word substitution plus descriptive workaround.
Reasoning steps for option A
For aph-16 option A, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: A phonemic paraphasia changes the sound structure of a target, while echolalia repeats another person's utterance.
For aph-16 option A, which case-specific contrast decides whether the choice fits?
The decisive comparison for Phonemic paraphasia followed by echolalia is the remaining discriminator: Neither label matches the related-word substitution plus descriptive workaround.
B. Neologism and perseveration (Why this does not fit)
A neologism is a novel nonword, and perseveration repeats a prior response inappropriately. 'Fork' is a real related word, and the second response is a description rather than repetition.
Reasoning steps for option B
For aph-16 option B, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: A neologism is a novel nonword, and perseveration repeats a prior response inappropriately.
For aph-16 option B, which case-specific contrast decides whether the choice fits?
The decisive comparison for Neologism and perseveration is the remaining discriminator: 'Fork' is a real related word, and the second response is a description rather than repetition.
C. Semantic paraphasia and neologism (Why this does not fit)
Calling a spoon a fork is a semantic paraphasia, but the description of a watch is not a nonword. The second behavior is a meaningful description used when the target name is unavailable.
Reasoning steps for option C
For aph-16 option C, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Calling a spoon a fork is a semantic paraphasia, but the description of a watch is not a nonword.
For aph-16 option C, which case-specific contrast decides whether the choice fits?
The decisive comparison for Semantic paraphasia and neologism is the remaining discriminator: The second behavior is a meaningful description used when the target name is unavailable.
D. Semantic paraphasia and circumlocution (Best answer)
The first response substitutes a meaning-related real word, which is a semantic paraphasia. The second conveys the target through description, which is circumlocution.
Reasoning steps for option D
For aph-16 option D, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: The first response substitutes a meaning-related real word, which is a semantic paraphasia.
For aph-16 option D, which case-specific contrast decides whether the choice fits?
The decisive comparison for Semantic paraphasia and circumlocution is the remaining discriminator: The second conveys the target through description, which is circumlocution.
Takeaway: Describe the error itself before using it to support a broader language profile.
A. Left occipital cortex plus posterior callosal fibers (Best answer)
Left occipital injury limits direct visual input to the dominant hemisphere, while posterior callosal injury interrupts transfer from the right visual cortex. Written language generation can remain available despite severe reading failure.
Reasoning steps for option A
For aph-17 option A, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Left occipital injury limits direct visual input to the dominant hemisphere, while posterior callosal injury interrupts transfer from the right visual cortex.
For aph-17 option A, which case-specific contrast decides whether the choice fits?
The decisive comparison for Left occipital cortex plus posterior callosal fibers is the remaining discriminator: Written language generation can remain available despite severe reading failure.
B. Dominant inferior frontal cortex plus premotor speech regions (Why this does not fit)
Inferior frontal and premotor injury would be expected to impair spoken formulation or speech planning. Those functions are preserved, and the dominant deficit is visual word recognition.
Reasoning steps for option B
For aph-17 option B, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Inferior frontal and premotor injury would be expected to impair spoken formulation or speech planning.
For aph-17 option B, which case-specific contrast decides whether the choice fits?
The decisive comparison for Dominant inferior frontal cortex plus premotor speech regions is the remaining discriminator: Those functions are preserved, and the dominant deficit is visual word recognition.
C. Dominant angular region plus adjacent inferior parietal cortex (Why this does not fit)
Angular-region dysfunction can impair both reading and writing. Preserved writing despite inability to read favors a disconnection pattern rather than alexia with agraphia.
Reasoning steps for option C
For aph-17 option C, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Angular-region dysfunction can impair both reading and writing.
For aph-17 option C, which case-specific contrast decides whether the choice fits?
The decisive comparison for Dominant angular region plus adjacent inferior parietal cortex is the remaining discriminator: Preserved writing despite inability to read favors a disconnection pattern rather than alexia with agraphia.
D. Bilateral auditory cortex plus posterior temporal language regions (Why this does not fit)
Bilateral auditory injury would impair access to spoken language, and posterior temporal injury could impair comprehension. Dictation, spoken comprehension, and repetition are preserved here.
Reasoning steps for option D
For aph-17 option D, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Bilateral auditory injury would impair access to spoken language, and posterior temporal injury could impair comprehension.
For aph-17 option D, which case-specific contrast decides whether the choice fits?
The decisive comparison for Bilateral auditory cortex plus posterior temporal language regions is the remaining discriminator: Dictation, spoken comprehension, and repetition are preserved here.
Takeaway: Pure alexia can result from left occipital injury combined with interrupted visual transfer to the dominant reading network.
A. The field deficit is sufficient to diagnose pure alexia (Why this does not fit)
A visual field deficit can slow reading and require compensatory scanning. Pure alexia requires a disproportionate visual word-recognition disorder, not merely missing visual space.
Reasoning steps for option A
For aph-18 option A, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: A visual field deficit can slow reading and require compensatory scanning.
For aph-18 option A, which case-specific contrast decides whether the choice fits?
The decisive comparison for The field deficit is sufficient to diagnose pure alexia is the remaining discriminator: Pure alexia requires a disproportionate visual word-recognition disorder, not merely missing visual space.
B. Field loss without the full pure-alexia dissociation (Best answer)
Reading remains accurate with a scanning strategy, and writing is normal. The field deficit alone does not demonstrate disruption of visual access to the dominant reading network.
Reasoning steps for option B
For aph-18 option B, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Reading remains accurate with a scanning strategy, and writing is normal.
For aph-18 option B, which case-specific contrast decides whether the choice fits?
The decisive comparison for Field loss without the full pure-alexia dissociation is the remaining discriminator: The field deficit alone does not demonstrate disruption of visual access to the dominant reading network.
C. The patient has alexia with agraphia from angular-region injury (Why this does not fit)
Alexia with agraphia impairs both reading and writing. Both are substantially preserved in this case.
Reasoning steps for option C
For aph-18 option C, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Alexia with agraphia impairs both reading and writing.
For aph-18 option C, which case-specific contrast decides whether the choice fits?
The decisive comparison for The patient has alexia with agraphia from angular-region injury is the remaining discriminator: Both are substantially preserved in this case.
D. The patient has Wernicke aphasia limited to written language (Why this does not fit)
Wernicke aphasia includes impaired spoken comprehension and fluent language disturbance. Spoken language is normal, and the reading difficulty is explained by the visual field deficit.
Reasoning steps for option D
For aph-18 option D, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Wernicke aphasia includes impaired spoken comprehension and fluent language disturbance.
For aph-18 option D, which case-specific contrast decides whether the choice fits?
The decisive comparison for The patient has Wernicke aphasia limited to written language is the remaining discriminator: Spoken language is normal, and the reading difficulty is explained by the visual field deficit.
Takeaway: A visual field deficit can hinder reading without producing pure alexia.
A. Dominant posterior temporal cortex (Why this does not fit)
Posterior temporal injury can impair spoken comprehension, which is comparatively preserved. The combined reading, writing, calculation, finger, and laterality deficits point elsewhere.
Reasoning steps for option A
For aph-19 option A, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Posterior temporal injury can impair spoken comprehension, which is comparatively preserved.
For aph-19 option A, which case-specific contrast decides whether the choice fits?
The decisive comparison for Dominant posterior temporal cortex is the remaining discriminator: The combined reading, writing, calculation, finger, and laterality deficits point elsewhere.
B. Left occipital cortex and posterior callosal fibers (Why this does not fit)
That disconnection can impair reading while preserving writing. Writing is impaired here, and the additional calculation and body-schema findings are not explained.
Reasoning steps for option B
For aph-19 option B, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: That disconnection can impair reading while preserving writing.
For aph-19 option B, which case-specific contrast decides whether the choice fits?
The decisive comparison for Left occipital cortex and posterior callosal fibers is the remaining discriminator: Writing is impaired here, and the additional calculation and body-schema findings are not explained.
C. Dominant angular and inferior parietal region (Best answer)
Alexia with agraphia plus acalculia, finger agnosia, and left-right disorientation forms the classic Gerstmann cluster. This constellation supports dominant inferior parietal localization.
Reasoning steps for option C
For aph-19 option C, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Alexia with agraphia plus acalculia, finger agnosia, and left-right disorientation forms the classic Gerstmann cluster.
For aph-19 option C, which case-specific contrast decides whether the choice fits?
The decisive comparison for Dominant angular and inferior parietal region is the remaining discriminator: This constellation supports dominant inferior parietal localization.
D. Dominant inferior frontal language cortex (Why this does not fit)
Inferior frontal injury would more strongly affect fluent formulation, grammar, and repetition. It does not best integrate the written-language and parietal association deficits.
Reasoning steps for option D
For aph-19 option D, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Inferior frontal injury would more strongly affect fluent formulation, grammar, and repetition.
For aph-19 option D, which case-specific contrast decides whether the choice fits?
The decisive comparison for Dominant inferior frontal language cortex is the remaining discriminator: It does not best integrate the written-language and parietal association deficits.
Takeaway: Alexia with agraphia and the Gerstmann cluster support dominant inferior parietal localization.
A. Semantic variant primary progressive aphasia (Why this does not fit)
The semantic variant causes loss of single-word meaning and object knowledge, often with fluent grammatical speech. Those semantic abilities remain strong in this patient.
Reasoning steps for option A
For aph-20 option A, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: The semantic variant causes loss of single-word meaning and object knowledge, often with fluent grammatical speech.
For aph-20 option A, which case-specific contrast decides whether the choice fits?
The decisive comparison for Semantic variant primary progressive aphasia is the remaining discriminator: Those semantic abilities remain strong in this patient.
B. Nonfluent or agrammatic primary progressive aphasia (Why this does not fit)
The nonfluent or agrammatic variant requires agrammatism or effortful apraxic speech as a core feature. Speech is articulated and grammatical here.
Reasoning steps for option B
For aph-20 option B, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: The nonfluent or agrammatic variant requires agrammatism or effortful apraxic speech as a core feature.
For aph-20 option B, which case-specific contrast decides whether the choice fits?
The decisive comparison for Nonfluent or agrammatic primary progressive aphasia is the remaining discriminator: Speech is articulated and grammatical here.
C. Transcortical motor aphasia from an acute border-zone infarct (Why this does not fit)
Transcortical motor aphasia has reduced initiation with preserved repetition and follows an acquired lesion. The course is progressive, and sentence repetition is impaired.
Reasoning steps for option C
For aph-20 option C, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Transcortical motor aphasia has reduced initiation with preserved repetition and follows an acquired lesion.
For aph-20 option C, which case-specific contrast decides whether the choice fits?
The decisive comparison for Transcortical motor aphasia from an acute border-zone infarct is the remaining discriminator: The course is progressive, and sentence repetition is impaired.
D. Logopenic variant primary progressive aphasia (Best answer)
Progressive word-retrieval pauses and impaired phrase or sentence repetition, with preserved single-word meaning and no frank agrammatism, define the logopenic profile. The posterior temporal-inferior parietal atrophy supports it.
Reasoning steps for option D
For aph-20 option D, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Progressive word-retrieval pauses and impaired phrase or sentence repetition, with preserved single-word meaning and no frank agrammatism, define the logopenic profile.
For aph-20 option D, which case-specific contrast decides whether the choice fits?
The decisive comparison for Logopenic variant primary progressive aphasia is the remaining discriminator: The posterior temporal-inferior parietal atrophy supports it.
Takeaway: Logopenic primary progressive aphasia combines retrieval pauses with impaired sentence repetition and preserved early word meaning.
A. Semantic variant primary progressive aphasia (Best answer)
Progressive loss of single-word meaning and object knowledge is central to the semantic variant. Fluent grammar, relatively preserved repetition, and anterior temporal atrophy reinforce the profile.
Reasoning steps for option A
For aph-21 option A, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Progressive loss of single-word meaning and object knowledge is central to the semantic variant.
For aph-21 option A, which case-specific contrast decides whether the choice fits?
The decisive comparison for Semantic variant primary progressive aphasia is the remaining discriminator: Fluent grammar, relatively preserved repetition, and anterior temporal atrophy reinforce the profile.
B. Logopenic variant primary progressive aphasia (Why this does not fit)
The logopenic variant preserves single-word meaning early and prominently impairs phrase or sentence repetition. This patient shows the opposite semantic-repetition relationship.
Reasoning steps for option B
For aph-21 option B, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: The logopenic variant preserves single-word meaning early and prominently impairs phrase or sentence repetition.
For aph-21 option B, which case-specific contrast decides whether the choice fits?
The decisive comparison for Logopenic variant primary progressive aphasia is the remaining discriminator: This patient shows the opposite semantic-repetition relationship.
C. Conduction aphasia from a focal dorsal network lesion (Why this does not fit)
Conduction aphasia is an acquired profile with disproportionate repetition impairment and relatively preserved comprehension. The gradual semantic loss and preserved repetition do not fit.
Reasoning steps for option C
For aph-21 option C, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Conduction aphasia is an acquired profile with disproportionate repetition impairment and relatively preserved comprehension.
For aph-21 option C, which case-specific contrast decides whether the choice fits?
The decisive comparison for Conduction aphasia from a focal dorsal network lesion is the remaining discriminator: The gradual semantic loss and preserved repetition do not fit.
D. Nonfluent or agrammatic primary progressive aphasia (Why this does not fit)
The nonfluent or agrammatic variant features agrammatism or effortful apraxic speech. Output remains fluent and grammatical here.
Reasoning steps for option D
For aph-21 option D, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: The nonfluent or agrammatic variant features agrammatism or effortful apraxic speech.
For aph-21 option D, which case-specific contrast decides whether the choice fits?
The decisive comparison for Nonfluent or agrammatic primary progressive aphasia is the remaining discriminator: Output remains fluent and grammatical here.
Takeaway: Progressive loss of word meaning and object knowledge with fluent speech supports the semantic variant.
A. Logopenic variant primary progressive aphasia with impaired repetition (Why this does not fit)
Logopenic disease produces retrieval pauses and impaired sentence repetition without prominent agrammatism or apraxic speech early. The grammatical and motor-speech findings here are more anterior.
Reasoning steps for option A
For aph-22 option A, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Logopenic disease produces retrieval pauses and impaired sentence repetition without prominent agrammatism or apraxic speech early.
For aph-22 option A, which case-specific contrast decides whether the choice fits?
The decisive comparison for Logopenic variant primary progressive aphasia with impaired repetition is the remaining discriminator: The grammatical and motor-speech findings here are more anterior.
B. Nonfluent or agrammatic primary progressive aphasia (Best answer)
Agrammatism or effortful apraxic speech is central to this variant. Preserved single-word comprehension and posterior frontal-insular atrophy support the same classification.
Reasoning steps for option B
For aph-22 option B, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Agrammatism or effortful apraxic speech is central to this variant.
For aph-22 option B, which case-specific contrast decides whether the choice fits?
The decisive comparison for Nonfluent or agrammatic primary progressive aphasia is the remaining discriminator: Preserved single-word comprehension and posterior frontal-insular atrophy support the same classification.
C. Semantic variant primary progressive aphasia (Why this does not fit)
The semantic variant primarily impairs word meaning and object knowledge while speech often remains fluent and grammatical. Those defining semantic deficits are absent.
Reasoning steps for option C
For aph-22 option C, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: The semantic variant primarily impairs word meaning and object knowledge while speech often remains fluent and grammatical.
For aph-22 option C, which case-specific contrast decides whether the choice fits?
The decisive comparison for Semantic variant primary progressive aphasia is the remaining discriminator: Those defining semantic deficits are absent.
D. Wernicke aphasia after an acute posterior lesion (Why this does not fit)
Wernicke aphasia is abrupt and fluent, with impaired comprehension. This case is progressive, nonfluent, and relatively preserves single-word meaning.
Reasoning steps for option D
For aph-22 option D, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Wernicke aphasia is abrupt and fluent, with impaired comprehension.
For aph-22 option D, which case-specific contrast decides whether the choice fits?
The decisive comparison for Wernicke aphasia after an acute posterior lesion is the remaining discriminator: This case is progressive, nonfluent, and relatively preserves single-word meaning.
Takeaway: Effortful agrammatic language or apraxic speech with frontal-insular atrophy supports the nonfluent variant.
A. Explain that the phenotype alone proves Alzheimer pathology (Why this does not fit)
Logopenic presentations are often associated with Alzheimer pathology, but a clinical phenotype does not establish the biological cause in an individual. Additional etiologic evidence is required.
Reasoning steps for option A
For aph-23 option A, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Logopenic presentations are often associated with Alzheimer pathology, but a clinical phenotype does not establish the biological cause in an individual.
For aph-23 option A, which case-specific contrast decides whether the choice fits?
The decisive comparison for Explain that the phenotype alone proves Alzheimer pathology is the remaining discriminator: Additional etiologic evidence is required.
B. Explain that the phenotype alone proves frontotemporal lobar degeneration (Why this does not fit)
Several biological processes can produce progressive language syndromes. The logopenic profile does not uniquely establish frontotemporal lobar degeneration.
Reasoning steps for option B
For aph-23 option B, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Several biological processes can produce progressive language syndromes.
For aph-23 option B, which case-specific contrast decides whether the choice fits?
The decisive comparison for Explain that the phenotype alone proves frontotemporal lobar degeneration is the remaining discriminator: The logopenic profile does not uniquely establish frontotemporal lobar degeneration.
C. Explain that the syndrome is classified clinically while etiology requires separate evidence (Best answer)
The language and imaging findings support a logopenic syndrome. Biomarkers, genetics, or pathology are needed when a specific biological cause must be established.
Reasoning steps for option C
For aph-23 option C, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: The language and imaging findings support a logopenic syndrome.
For aph-23 option C, which case-specific contrast decides whether the choice fits?
The decisive comparison for Explain that the syndrome is classified clinically while etiology requires separate evidence is the remaining discriminator: Biomarkers, genetics, or pathology are needed when a specific biological cause must be established.
D. Defer every syndrome classification until tissue pathology is available (Why this does not fit)
Primary progressive aphasia variants can be classified clinically and can receive imaging support before pathology is known. Tissue confirmation is a separate level of etiologic certainty.
Reasoning steps for option D
For aph-23 option D, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Primary progressive aphasia variants can be classified clinically and can receive imaging support before pathology is known.
For aph-23 option D, which case-specific contrast decides whether the choice fits?
The decisive comparison for Defer every syndrome classification until tissue pathology is available is the remaining discriminator: Tissue confirmation is a separate level of etiologic certainty.
Takeaway: A progressive language phenotype supports syndrome classification but does not by itself prove pathology.
A. Assess decision-specific capacity using supported communication (Best answer)
Aphasia limits expression but does not establish incapacity. The patient demonstrates understanding and a stable choice when communication barriers are reduced, so direct supported assessment is appropriate.
Reasoning steps for option A
For aph-25 option A, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Aphasia limits expression but does not establish incapacity.
For aph-25 option A, which case-specific contrast decides whether the choice fits?
The decisive comparison for Assess decision-specific capacity using supported communication is the remaining discriminator: The patient demonstrates understanding and a stable choice when communication barriers are reduced, so direct supported assessment is appropriate.
B. Accept the relative's answer because fluent speech is required for consent (Why this does not fit)
Consent requires decision-specific understanding and voluntary choice, not fluent speech. The patient is already demonstrating comprehension through accessible responses.
Reasoning steps for option B
For aph-25 option B, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Consent requires decision-specific understanding and voluntary choice, not fluent speech.
For aph-25 option B, which case-specific contrast decides whether the choice fits?
The decisive comparison for Accept the relative's answer because fluent speech is required for consent is the remaining discriminator: The patient is already demonstrating comprehension through accessible responses.
C. Assume incapacity until spoken naming and repetition normalize (Why this does not fit)
Naming and repetition are language functions, not universal measures of decision-making capacity. Delaying participation until recovery would wrongly equate aphasia with global cognitive failure.
Reasoning steps for option C
For aph-25 option C, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Naming and repetition are language functions, not universal measures of decision-making capacity.
For aph-25 option C, which case-specific contrast decides whether the choice fits?
The decisive comparison for Assume incapacity until spoken naming and repetition normalize is the remaining discriminator: Delaying participation until recovery would wrongly equate aphasia with global cognitive failure.
D. Cancel all decisions because picture-supported responses are invalid (Why this does not fit)
Accessible communication methods can reveal understanding and preferences. Their use should be documented and checked for consistency rather than dismissed.
Reasoning steps for option D
For aph-25 option D, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Accessible communication methods can reveal understanding and preferences.
For aph-25 option D, which case-specific contrast decides whether the choice fits?
The decisive comparison for Cancel all decisions because picture-supported responses are invalid is the remaining discriminator: Their use should be documented and checked for consistency rather than dismissed.
Takeaway: Aphasia requires communication support, not automatic removal of the patient from decisions.
A. Diagnose a postictal state and omit brain imaging (Why this does not fit)
Improvement after a seizure supports a postictal explanation, but seizure can accompany acute structural injury. Omission of imaging would leave a time-sensitive vascular or other lesion unassessed.
Reasoning steps for option A
For aph-26 option A, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Improvement after a seizure supports a postictal explanation, but seizure can accompany acute structural injury.
For aph-26 option A, which case-specific contrast decides whether the choice fits?
The decisive comparison for Diagnose a postictal state and omit brain imaging is the remaining discriminator: Omission of imaging would leave a time-sensitive vascular or other lesion unassessed.
B. Treat the event as an urgent neurologic presentation while evaluating seizure and stroke in parallel (Best answer)
The witnessed seizure and improving deficit make a postictal state plausible, but they do not exclude acute ischemia or hemorrhage. Urgent imaging and time-course assessment should proceed while seizure-related causes are evaluated.
Reasoning steps for option B
For aph-26 option B, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: The witnessed seizure and improving deficit make a postictal state plausible, but they do not exclude acute ischemia or hemorrhage.
For aph-26 option B, which case-specific contrast decides whether the choice fits?
The decisive comparison for Treat the event as an urgent neurologic presentation while evaluating seizure and stroke in parallel is the remaining discriminator: Urgent imaging and time-course assessment should proceed while seizure-related causes are evaluated.
C. Exclude ischemia because the language deficit is improving (Why this does not fit)
Transient or improving deficits can still reflect cerebral ischemia. Improvement changes the differential but does not safely remove stroke from consideration.
Reasoning steps for option C
For aph-26 option C, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Transient or improving deficits can still reflect cerebral ischemia.
For aph-26 option C, which case-specific contrast decides whether the choice fits?
The decisive comparison for Exclude ischemia because the language deficit is improving is the remaining discriminator: Improvement changes the differential but does not safely remove stroke from consideration.
D. Wait for complete language recovery before establishing the onset history (Why this does not fit)
Onset and last-known-well information are time-sensitive and should be gathered immediately from witnesses and records. Waiting can erase eligibility information without resolving the cause.
Reasoning steps for option D
For aph-26 option D, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Onset and last-known-well information are time-sensitive and should be gathered immediately from witnesses and records.
For aph-26 option D, which case-specific contrast decides whether the choice fits?
The decisive comparison for Wait for complete language recovery before establishing the onset history is the remaining discriminator: Waiting can erase eligibility information without resolving the cause.
Takeaway: Seizure can mimic or accompany stroke, so urgent evaluation should address both possibilities.
A. Diagnose Wernicke aphasia from the English comprehension errors (Why this does not fit)
Poor performance in a less proficient language can mimic acquired comprehension failure. The reported Spanish conversation makes an English-only syndrome label unreliable.
Reasoning steps for option A
For aph-28 option A, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Poor performance in a less proficient language can mimic acquired comprehension failure.
For aph-28 option A, which case-specific contrast decides whether the choice fits?
The decisive comparison for Diagnose Wernicke aphasia from the English comprehension errors is the remaining discriminator: The reported Spanish conversation makes an English-only syndrome label unreliable.
B. Diagnose anomic aphasia because naming is impaired in English (Why this does not fit)
Naming in one nonpreferred language does not establish a selective acquired retrieval disorder. Premorbid proficiency and performance across the patient's languages must be considered.
Reasoning steps for option B
For aph-28 option B, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Naming in one nonpreferred language does not establish a selective acquired retrieval disorder.
For aph-28 option B, which case-specific contrast decides whether the choice fits?
The decisive comparison for Diagnose anomic aphasia because naming is impaired in English is the remaining discriminator: Premorbid proficiency and performance across the patient's languages must be considered.
C. Repeat the same English tasks more loudly (Why this does not fit)
Increased volume addresses hearing access, not language proficiency. The conflict between English testing and reported Spanish function requires a linguistically appropriate assessment.
Reasoning steps for option C
For aph-28 option C, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: Increased volume addresses hearing access, not language proficiency.
For aph-28 option C, which case-specific contrast decides whether the choice fits?
The decisive comparison for Repeat the same English tasks more loudly is the remaining discriminator: The conflict between English testing and reported Spanish function requires a linguistically appropriate assessment.
D. Assess the languages used before illness with trained language support and document accommodations (Best answer)
A valid assessment should sample the patient's relevant languages and distinguish premorbid proficiency from new impairment. Trained interpretation or bilingual speech-language evaluation can clarify the true pattern.
Reasoning steps for option D
For aph-28 option D, which domain-level observation must be checked first?
Map the option back to the observed abilities before naming a syndrome: A valid assessment should sample the patient's relevant languages and distinguish premorbid proficiency from new impairment.
For aph-28 option D, which case-specific contrast decides whether the choice fits?
The decisive comparison for Assess the languages used before illness with trained language support and document accommodations is the remaining discriminator: Trained interpretation or bilingual speech-language evaluation can clarify the true pattern.
Takeaway: Multilingual assessment must distinguish acquired language loss from limited proficiency in the examiner's language.