Explore how glucocorticoids disrupt bone remodeling, calcium balance, and strength, then apply risk-based fracture prevention through original cases.
If an osteoclast makes a pit, what matters more next: how deep it is, or how completely it is refilled? Steroids can disturb both. Start with one remodeling cycle, then connect it to fracture prevention.
Optional marks stay in this browser when storage is available. Nothing is sent by these lesson tools.
The pit is only half the story
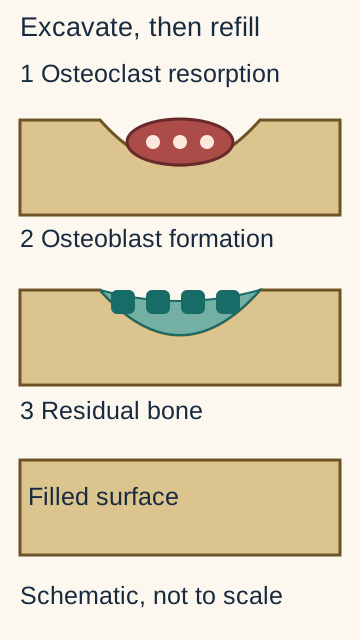
A vertebra can weaken even when its calcium supply is adequate. Picture one patch of bone being renewed. An osteoclast excavates old matrix. Osteoblast precursors are recruited, mature, and fill the cavity with new matrix that subsequently mineralizes. Osteocytes are former osteoblasts embedded inside that matrix. They help sense loading and coordinate maintenance. A completed cycle needs enough replacement bone, not merely a stopped osteoclast.
Glucocorticoids impair formation through reduced osteoblast production and survival. Early exposure can also favor resorption, but that is not a uniform cellular response. The 1998 Weinstein study found reduced formation and cell survival in mice, with supporting human observations. The 2002 mouse/culture study showed prolonged osteoclast survival. Kim and colleagues in 2006 found longer survival with impaired resorptive function in their experimental setting. More surviving osteoclasts does not necessarily mean more excavation.[3][4][14]
A resorption marker reflects matrix breakdown; a formation marker reflects new matrix production. Neither directly measures the depth of one pit or the volume of one refill. Incomplete replacement is compatible with formation falling relative to removal, but markers alone do not prove a net volume deficit or select a drug. Separate cell number, cell function, turnover markers, and structural change.
Use the surface model to compare possible outcomes. The deeper early-exposure pit illustrates one possible imbalance, not a measured human phase or an inevitable steroid response. Within each pictured cycle, filling makes the pit shallower and preserves or thickens the remaining connection. The final sustained view then changes scale to a separate cumulative example after repeated deficits. Assess BMD, fracture risk and treatment duration separately.
A common shortcut is to call all steroid bone disease excessive osteoclast activity. That misses the persistent formation deficit. Keep the entire cycle in view. A shallow pit can still produce net loss if it is poorly refilled. Then ask how a therapy changes one part of that cycle without assuming it repairs every damaged connection.
A remodeling site first loses matrix, then receives replacement. Green indicates newly deposited matrix, which subsequently mineralizes. This schematic has no measured time or volume scale.
No third-party artwork. Physiological references [3][4].
Case 2
Show answer and explanations for case 2
A. Replacement remains inadequate; resorption is demonstrated to be below baseline (Why this does not fit)
Read the explanation or work through it
Continued thinning supports inadequate replacement relative to removal. The resorption comparison uses week 6 rather than a pretreatment value. Lower resorption than an early-treatment measured value does not establish below-baseline turnover.
Predict one fact before revealing it.
What supports a continuing replacement problem?
Continued thinning supports inadequate replacement relative to removal.
Which reference point was actually measured?
The resorption comparison uses week 6 rather than a pretreatment value.
Why is the below-baseline claim too strong?
Lower resorption than an early-treatment measured value does not establish below-baseline turnover.
A decline between two measurements establishes direction between them, not a peak or an unmeasured baseline.[3][4]
Read all reasoning steps
What supports a continuing replacement problem?
Continued thinning supports inadequate replacement relative to removal.
Which reference point was actually measured?
The resorption comparison uses week 6 rather than a pretreatment value.
Why is the below-baseline claim too strong?
Lower resorption than an early-treatment measured value does not establish below-baseline turnover.
B. Replacement now matches removal; residual thinning reflects earlier damage (Why this does not fit)
Read the explanation or work through it
A thin trabecula at one time point could reflect past exposure. Further thinning between months 12 and 24 demonstrates interval deterioration. The interval loss is inconsistent with attributing the entire structural deficit to earlier damage.
Predict one fact before revealing it.
When could old damage explain a thin trabecula?
A thin trabecula at one time point could reflect past exposure.
What distinguishes this dataset from one old scan?
Further thinning between months 12 and 24 demonstrates interval deterioration.
Why does the past-damage explanation fail here?
The interval loss is inconsistent with attributing the entire structural deficit to earlier damage.
A decline between two measurements establishes direction between them, not a peak or an unmeasured baseline.[3][4]
Read all reasoning steps
When could old damage explain a thin trabecula?
A thin trabecula at one time point could reflect past exposure.
What distinguishes this dataset from one old scan?
Further thinning between months 12 and 24 demonstrates interval deterioration.
Why does the past-damage explanation fail here?
The interval loss is inconsistent with attributing the entire structural deficit to earlier damage.
C. Replacement exceeds removal; lower resorption is restoring the framework (Why this does not fit)
Read the explanation or work through it
Lower resorption can reduce the amount of bone that needs replacement. The measured trabeculae nevertheless become thinner during the later interval. The structural direction does not support net restoration during that interval.
Lower resorption can reduce the amount of bone that needs replacement.
What structural direction was observed?
The measured trabeculae nevertheless become thinner during the later interval.
Why is restoration not the supported conclusion?
The structural direction does not support net restoration during that interval.
D. Replacement is impaired; progressively increasing resorption explains the later loss (Why this does not fit)
Read the explanation or work through it
Reduced cell availability and thinner walls support impaired replacement. The later resorption measure is lower than the early-treatment measure. Increasing resorption is unnecessary to explain loss when replacement remains insufficient.
Predict one fact before revealing it.
What evidence supports the first half of this interpretation?
Reduced cell availability and thinner walls support impaired replacement.
What contradicts a continuously increasing resorption trajectory?
The later resorption measure is lower than the early-treatment measure.
How can loss continue despite the lower resorption measurement?
Increasing resorption is unnecessary to explain loss when replacement remains insufficient.
A decline between two measurements establishes direction between them, not a peak or an unmeasured baseline.[3][4]
Read all reasoning steps
What evidence supports the first half of this interpretation?
Reduced cell availability and thinner walls support impaired replacement.
What contradicts a continuously increasing resorption trajectory?
The later resorption measure is lower than the early-treatment measure.
How can loss continue despite the lower resorption measurement?
Increasing resorption is unnecessary to explain loss when replacement remains insufficient.
E. Replacement remains inadequate; resorption is lower than early treatment but not proven below baseline (Best answer)
Read the explanation or work through it
Fewer osteoblasts with thinner completed walls supports impaired replacement capacity. Further thinning between months 12 and 24 supports an ongoing structural deficit rather than only old damage. The missing baseline resorption value prevents a claim that current resorption is below pretreatment levels.
Predict one fact before revealing it.
What do the cellular and wall findings establish?
Fewer osteoblasts with thinner completed walls supports impaired replacement capacity.
What does interval trabecular thinning add?
Further thinning between months 12 and 24 supports an ongoing structural deficit rather than only old damage.
Which resorption comparison is unavailable?
The missing baseline resorption value prevents a claim that current resorption is below pretreatment levels.
A decline between two measurements establishes direction between them, not a peak or an unmeasured baseline.[3][4]
Read all reasoning steps
What do the cellular and wall findings establish?
Fewer osteoblasts with thinner completed walls supports impaired replacement capacity.
What does interval trabecular thinning add?
Further thinning between months 12 and 24 supports an ongoing structural deficit rather than only old damage.
Which resorption comparison is unavailable?
The missing baseline resorption value prevents a claim that current resorption is below pretreatment levels.
Takeaway: Continued thinning supports ongoing negative balance; a fall from an early measured value does not establish turnover below normal.
RANKL binds RANK on osteoclast-lineage cells. OPG, or osteoprotegerin, intercepts RANKL as a decoy. More free RANKL can support osteoclast development. Glucocorticoids can shift this signaling balance, but the net result also depends on recruitment, survival, and the cell's resorptive machinery. A controlled ligand comparison does not prove that steroids changed nothing else in a patient. [4][10]
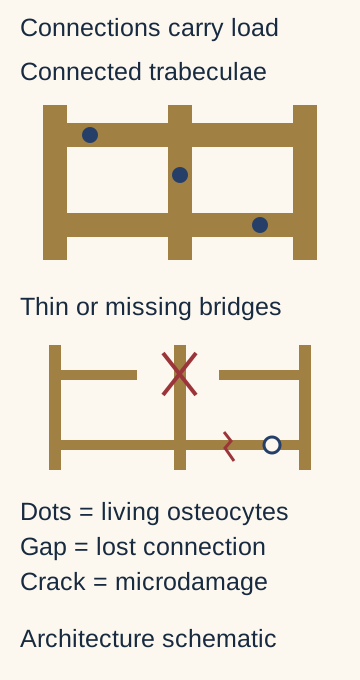
Bone strength depends on connected architecture and maintenance by living cells. The lower network illustrates disconnection, microdamage, and an injured osteocyte shown as a hollow circle. The disconnected links and hollow osteocyte show how damage can weaken the network.
No third-party artwork. Physiological references [3][13].
Wnt signaling supports osteoblast differentiation. DKK1 is an extracellular Wnt antagonist. In Ohnaka and colleagues' 2005 primary human osteoblast cultures, dexamethasone reduced Wnt-driven transcription. A downstream GSK-3 beta inhibitor still activated transcription, while DKK1 neutralization restored only part of the Wnt response. A bypass can help locate a defect; partial rescue identifies a contribution without proving that one pathway explains everything. These are culture findings, not a clinical DKK1 test or treatment recommendation. [5]
Glucocorticoids also shorten osteoblast and osteocyte survival. A living osteocyte network helps coordinate the response to mechanical strain and damage. Losing cells can impair maintenance before a DXA number fully expresses the problem. Experimental and human observations support cell injury, while the exact contribution varies with exposure and the underlying illness. [3]
Trabecular bone consists of interconnected plates and rods. It has a large remodeling surface relative to its volume. Incomplete refilling narrows those connections; perforation can disconnect them. The vertebral body is particularly vulnerable because it relies heavily on this internal framework. Cortical bone and hip fractures also matter, so vertebral susceptibility does not mean the rest of the skeleton is protected.
Compare the two schematic networks. A thinner connection carries load through less material. A missing connection changes how load reaches adjacent struts. Neither drawing is a biopsy or a measured microarchitecture scan. Bone quantity, connectivity, and living-cell maintenance are related but different properties. That is why a density measurement alone cannot settle fracture risk. [13]
Case 3
Show answer and explanations for case 3
A. Suppression upstream of the bypass, with DKK1 accounting for the entire effect (Why this does not fit)
Read the explanation or work through it
The bypass response supports an upstream site of suppression. DKK1 neutralization restores only part of the lost response. The partial rescue does not establish DKK1 as the exclusive explanation.
Predict one fact before revealing it.
Which localization fits the bypass?
The bypass response supports an upstream site of suppression.
How complete is the antibody rescue?
DKK1 neutralization restores only part of the lost response.
Why does exclusivity exceed these findings?
The partial rescue does not establish DKK1 as the exclusive explanation.
The partial rescue does not establish DKK1 as the exclusive explanation.[5]
Read all reasoning steps
Which localization fits the bypass?
The bypass response supports an upstream site of suppression.
How complete is the antibody rescue?
DKK1 neutralization restores only part of the lost response.
Why does exclusivity exceed these findings?
The partial rescue does not establish DKK1 as the exclusive explanation.
B. Suppression upstream of the bypass, with DKK1 accounting for part of the effect (Best answer)
Read the explanation or work through it
Preserved downstream activation argues against failure of the tested downstream transcriptional machinery. Partial rescue by DKK1 neutralization supports a DKK1 contribution to suppression. The incomplete rescue leaves other inhibitory contributions unresolved.
Predict one fact before revealing it.
What does the preserved downstream response rule against?
Preserved downstream activation argues against failure of the tested downstream transcriptional machinery.
What does antibody rescue establish about DKK1?
Partial rescue by DKK1 neutralization supports a DKK1 contribution to suppression.
What does incomplete rescue leave uncertain?
The incomplete rescue leaves other inhibitory contributions unresolved.
The incomplete rescue leaves other inhibitory contributions unresolved.[5]
Read all reasoning steps
What does the preserved downstream response rule against?
Preserved downstream activation argues against failure of the tested downstream transcriptional machinery.
What does antibody rescue establish about DKK1?
Partial rescue by DKK1 neutralization supports a DKK1 contribution to suppression.
What does incomplete rescue leave uncertain?
The incomplete rescue leaves other inhibitory contributions unresolved.
C. Suppression downstream of the bypass, with DKK1 accounting for part of the effect (Why this does not fit)
Read the explanation or work through it
Partial antibody rescue supports a DKK1 contribution. The downstream activator retains its transcriptional effect during dexamethasone exposure. A disabled pathway downstream of that activator would not explain the preserved bypass response.
Predict one fact before revealing it.
Which attribution fits the antibody experiment?
Partial antibody rescue supports a DKK1 contribution.
What happens when the upstream signal is bypassed?
The downstream activator retains its transcriptional effect during dexamethasone exposure.
Why does the proposed downstream block fail?
A disabled pathway downstream of that activator would not explain the preserved bypass response.
A disabled pathway downstream of that activator would not explain the preserved bypass response.[5]
Read all reasoning steps
Which attribution fits the antibody experiment?
Partial antibody rescue supports a DKK1 contribution.
What happens when the upstream signal is bypassed?
The downstream activator retains its transcriptional effect during dexamethasone exposure.
Why does the proposed downstream block fail?
A disabled pathway downstream of that activator would not explain the preserved bypass response.
D. Suppression downstream of the bypass, with DKK1 accounting for the entire effect (Why this does not fit)
Read the explanation or work through it
DKK1 inhibits Wnt signaling outside the cell. The preserved bypass response argues against the proposed downstream block. The incomplete antibody rescue also fails to establish exclusive DKK1 mediation.
Predict one fact before revealing it.
Where does DKK1 act?
DKK1 inhibits Wnt signaling outside the cell.
Which finding challenges the downstream localization?
The preserved bypass response argues against the proposed downstream block.
Which finding challenges exclusive attribution?
The incomplete antibody rescue also fails to establish exclusive DKK1 mediation.
The incomplete antibody rescue also fails to establish exclusive DKK1 mediation.[5]
Read all reasoning steps
Where does DKK1 act?
DKK1 inhibits Wnt signaling outside the cell.
Which finding challenges the downstream localization?
The preserved bypass response argues against the proposed downstream block.
Which finding challenges exclusive attribution?
The incomplete antibody rescue also fails to establish exclusive DKK1 mediation.
E. Suppression upstream of the bypass, without a demonstrated DKK1 contribution (Why this does not fit)
Read the explanation or work through it
The preserved bypass response supports upstream suppression. Neutralizing DKK1 restores a portion of Wnt-dependent transcription. The rescue provides evidence for DKK1 involvement even though the rescue is incomplete.
Predict one fact before revealing it.
Which part of the interpretation fits the bypass?
The preserved bypass response supports upstream suppression.
What changes after DKK1 neutralization?
Neutralizing DKK1 restores a portion of Wnt-dependent transcription.
Why is no demonstrated contribution too skeptical?
The rescue provides evidence for DKK1 involvement even though the rescue is incomplete.
The rescue provides evidence for DKK1 involvement even though the rescue is incomplete.[5]
Read all reasoning steps
Which part of the interpretation fits the bypass?
The preserved bypass response supports upstream suppression.
What changes after DKK1 neutralization?
Neutralizing DKK1 restores a portion of Wnt-dependent transcription.
Why is no demonstrated contribution too skeptical?
The rescue provides evidence for DKK1 involvement even though the rescue is incomplete.
Takeaway: A downstream bypass localizes the defect; partial neutralization rescue identifies a contribution without proving exclusivity.
Normal serum calcium is not a structural inspection
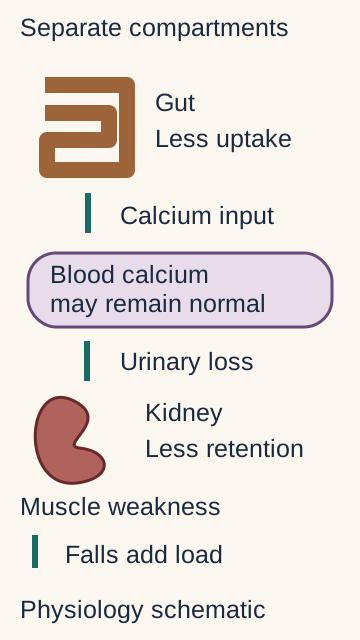
Calcium in blood is a regulated compartment. It is not a running total of calcium retained in the skeleton. Glucocorticoids can reduce intestinal calcium absorption and increase urinary calcium loss. A person can therefore have unfavorable calcium balance while a serum calcium result remains within the laboratory range. Follow the gut, blood, kidney, and bone as separate compartments. [6][13]
A normal blood calcium value is compatible with unfavorable calcium balance. Muscle weakness adds a separate route to fracture through falls. Arrow size is not a measured flux.
No third-party artwork. Physiological references [6][13].
Secondary hyperparathyroidism may contribute in some settings, but sustained PTH excess and hypocalcemia are not required. Hahn and colleagues studied 12 healthy adults given prednisone 20 mg/day for 14 days in 1981. Calcium absorption fell without a fall in circulating calcitriol or a rise in fasting PTH. That small short-term experiment rejects an obligatory conversion-block explanation; it does not describe every chronic patient. [6]
There is also a route to fracture that does not begin in bone. Proximal muscle weakness can make standing, stepping, and recovering balance harder. More falls increase the chance that a vulnerable bone experiences a damaging load. Resistance and balance exercise, safe activity, and fall-risk assessment address a different part of the problem than a bone-directed drug. [1][13] In an older adult, chair-rise weakness and sedative-associated drowsiness point to different intervention targets. Assess the actual strength, balance, medication, sensory, and cardiovascular findings rather than assigning every fall to steroids. The 2022 World Falls Guidelines support individualized interventions following this assessment. [19]
Glucocorticoids can suppress gonadal function. Low sex-hormone exposure may add another skeletal stressor. Ask about relevant menstrual or sexual symptoms rather than treating every low BMD result as purely nutritional. Chronic inflammation, reduced mobility, low body weight, smoking, and other illnesses may also contribute.
Sarcoidosis needs its own calcium context. In a 1990 experiment using cultured alveolar macrophages from patients with sarcoidosis, these cells produced active vitamin D outside the kidney and dexamethasone inhibited that production. This disease-specific effect is not a universal renal conversion block. Individualize calcium and vitamin D support to intake, laboratory findings, kidney function, and disease. Normal serum calcium does not establish favorable skeletal balance.[22]
Before the follow-up case, separate measurement from delivery. A DXA facility's least significant change is the precision threshold used to judge a serial BMD difference. Alendronate is an oral antiresorptive whose absorption is reduced by food and coffee. A record of swallowed tablets does not establish how much drug was absorbed. Compare the measured change, then examine how treatment was actually taken. [16][8]
Case 6
Show answer and explanations for case 6
A. No measurable interval loss; address impaired oral delivery and arrange reassessment before declaring pharmacologic failure (Why this does not fit)
Read the explanation or work through it
The 5.25% decline exceeds the 3.0% least significant change and establishes measurable interval loss. Taking alendronate with food and coffee can reduce oral drug absorption. The administration-focused follow-up is appropriate, but the claim of no measurable loss understates the serial finding.
Predict one fact before revealing it.
Does the BMD decline remain within this facility precision threshold?
The 5.25% decline exceeds the 3.0% least significant change and establishes measurable interval loss.
Which administration finding still needs correction?
Taking alendronate with food and coffee can reduce oral drug absorption.
Which part of this paired conclusion needs revision?
The administration-focused follow-up is appropriate, but the claim of no measurable loss understates the serial finding.
Establish whether a serial change exceeds measurement uncertainty, then check actual drug delivery before interpreting treatment response.[1][8][16]
Read all reasoning steps
Does the BMD decline remain within this facility precision threshold?
The 5.25% decline exceeds the 3.0% least significant change and establishes measurable interval loss.
Which administration finding still needs correction?
Taking alendronate with food and coffee can reduce oral drug absorption.
Which part of this paired conclusion needs revision?
The administration-focused follow-up is appropriate, but the claim of no measurable loss understates the serial finding.
B. Measurable interval loss; discuss a class change for loss despite adequately delivered oral treatment (Why this does not fit)
Read the explanation or work through it
The precision-qualified DXA comparison supports interval deterioration. Breakfast and coffee at the time of alendronate dosing prevent assuming adequate absorption. A class-change discussion for loss despite adequate delivery presupposes an exposure condition that this history does not establish.
Predict one fact before revealing it.
Does the DXA comparison support interval deterioration?
The precision-qualified DXA comparison supports interval deterioration.
Does the dosing history establish adequate oral delivery?
Breakfast and coffee at the time of alendronate dosing prevent assuming adequate absorption.
Why is a failure-based class-change discussion premature on this rationale?
A class-change discussion for loss despite adequate delivery presupposes an exposure condition that this history does not establish.
Establish whether a serial change exceeds measurement uncertainty, then check actual drug delivery before interpreting treatment response.[1][8][16]
Read all reasoning steps
Does the DXA comparison support interval deterioration?
The precision-qualified DXA comparison supports interval deterioration.
Does the dosing history establish adequate oral delivery?
Breakfast and coffee at the time of alendronate dosing prevent assuming adequate absorption.
Why is a failure-based class-change discussion premature on this rationale?
A class-change discussion for loss despite adequate delivery presupposes an exposure condition that this history does not establish.
C. Measurable interval loss; address impaired oral delivery and arrange reassessment before declaring pharmacologic failure (Best answer)
Read the explanation or work through it
The hip BMD decline is 5.25%, exceeding the facility least significant change of 3.0%. Food and coffee impair alendronate absorption despite a history of no missed doses. The next review should correct administration or discuss a feasible nonoral plan, with subsequent response reassessment before declaring failure despite adequate exposure.
Predict one fact before revealing it.
What percentage change follows from the two hip BMD values?
The hip BMD decline is 5.25%, exceeding the facility least significant change of 3.0%.
What does taking alendronate with breakfast and coffee imply about drug delivery?
Food and coffee impair alendronate absorption despite a history of no missed doses.
What follow-up addresses the exposure problem before a failure judgment?
The next review should correct administration or discuss a feasible nonoral plan, with subsequent response reassessment before declaring failure despite adequate exposure.
Establish whether a serial change exceeds measurement uncertainty, then check actual drug delivery before interpreting treatment response.[1][8][16]
Read all reasoning steps
What percentage change follows from the two hip BMD values?
The hip BMD decline is 5.25%, exceeding the facility least significant change of 3.0%.
What does taking alendronate with breakfast and coffee imply about drug delivery?
Food and coffee impair alendronate absorption despite a history of no missed doses.
What follow-up addresses the exposure problem before a failure judgment?
The next review should correct administration or discuss a feasible nonoral plan, with subsequent response reassessment before declaring failure despite adequate exposure.
D. No measurable interval loss; continue the adequately delivered regimen with scheduled surveillance (Why this does not fit)
Read the explanation or work through it
The comparison establishes measurable loss rather than a change within measurement uncertainty. Food and coffee with each alendronate dose create a documented absorption problem. Surveillance without addressing administration would leave a correctable exposure problem during demonstrated loss.
Predict one fact before revealing it.
What does comparing 5.25% with the 3.0% least significant change establish?
The comparison establishes measurable loss rather than a change within measurement uncertainty.
What challenges the claim that the oral regimen was adequately delivered?
Food and coffee with each alendronate dose create a documented absorption problem.
Why is unchanged treatment with surveillance insufficient here?
Surveillance without addressing administration would leave a correctable exposure problem during demonstrated loss.
Establish whether a serial change exceeds measurement uncertainty, then check actual drug delivery before interpreting treatment response.[1][8][16]
Read all reasoning steps
What does comparing 5.25% with the 3.0% least significant change establish?
The comparison establishes measurable loss rather than a change within measurement uncertainty.
What challenges the claim that the oral regimen was adequately delivered?
Food and coffee with each alendronate dose create a documented absorption problem.
Why is unchanged treatment with surveillance insufficient here?
Surveillance without addressing administration would leave a correctable exposure problem during demonstrated loss.
E. Change cannot be quantified without cross-calibration; establish a new baseline and continue the adequately delivered regimen (Why this does not fit)
Read the explanation or work through it
Cross-calibration is relevant when comparing different DXA instruments. Both scans used the same calibrated system with a stated facility least significant change. Continuing the regimen as adequately delivered ignores the food-associated alendronate absorption problem.
Predict one fact before revealing it.
When would cross-calibration be needed for this type of comparison?
Cross-calibration is relevant when comparing different DXA instruments.
What feature makes the supplied serial comparison usable?
Both scans used the same calibrated system with a stated facility least significant change.
Why is the proposed continuation plan also incomplete?
Continuing the regimen as adequately delivered ignores the food-associated alendronate absorption problem.
Establish whether a serial change exceeds measurement uncertainty, then check actual drug delivery before interpreting treatment response.[1][8][16]
Read all reasoning steps
When would cross-calibration be needed for this type of comparison?
Cross-calibration is relevant when comparing different DXA instruments.
What feature makes the supplied serial comparison usable?
Both scans used the same calibrated system with a stated facility least significant change.
Why is the proposed continuation plan also incomplete?
Continuing the regimen as adequately delivered ignores the food-associated alendronate absorption problem.
Takeaway: Establish whether a serial change exceeds measurement uncertainty, then check actual drug delivery before interpreting treatment response.
Risk can rise soon after systemic glucocorticoids begin. Dose, duration, repeated courses, and the underlying illness matter. Van Staa and colleagues' 2000 observational study of oral corticosteroid users found dose-related fracture associations and declining risk after cessation. Confounding limits causal conclusions. Prior exposure can leave structural damage even after exposure stops; a single low DXA result does not demonstrate continuing loss. [7]
The 2022 ACR GIOP guideline, published in 2023, strongly recommends prompt initial fracture-risk assessment in adults starting or continuing prednisone-equivalent doses of at least 2.5 mg/day for more than three months. Review dose, duration and pattern, fractures, height loss, falls, frailty, weight change, smoking, alcohol, hypogonadism, and secondary causes. Use DXA with vertebral fracture assessment or spine radiographs when available. Incorporate an adequate recent DXA rather than automatically repeating it. A painless vertebral fracture can still matter. [1][2]
DXA reports areal mineral density. T-scores compare with a young-adult reference; Z-scores compare with an age-matched reference. ISCD prefers Z-scores in premenopausal women and men younger than 50. A Z-score of -2.0 or lower is below the expected range for age. In postmenopausal women and men at least 50, a valid T-score of -2.5 or lower can establish densitometric osteoporosis. Density classification and clinical fracture risk are different questions. [16]
Glucocorticoid-related fractures can occur at less reduced BMD than fractures in primary postmenopausal osteoporosis. A documented low-trauma vertebral fracture matters even when the T-score is not in the osteoporosis range. Do not confuse osteoporosis with osteomalacia, which is defective mineralization. DXA alone cannot diagnose that mineralization defect. [13]
Use FRAX only from age 40 in this guideline framework. FRAX estimates 10-year probabilities of hip fracture and major osteoporotic fracture, covering clinical spine, hip, forearm, and proximal humerus. For prednisone above 7.5 mg/day, the ACR correction multiplies the major-fracture probability by 1.15 and the hip probability by 1.2. The corrected number still underrepresents some dose patterns, frailty, falls, and recent or multiple fractures. Do not invent an age or a falls percentage. [1][2]
Use the highest applicable ACR risk category for adults at least 40. These are guideline decision categories, not universal diagnostic cutoffs. Treatment choices depend on individual risks, preferences, feasibility, and label precautions. The following reference paraphrases the ACR summary revised July 9, 2023. [2]
Very high risk. Prior osteoporotic fracture, T-score at or below -3.5, adjusted major-fracture probability at least 30% or hip probability at least 4.5%, prednisone at least 30 mg/day for more than 30 days, or cumulative exposure at least 5 g/year.
High risk. Without a very-high criterion, T-score at or below -2.5 but above -3.5, adjusted major probability at least 20% but below 30%, or hip probability at least 3% but below 4.5%.
Moderate risk. Without a higher criterion, adjusted major probability at least 10% but below 20%, hip probability above 1% but below 3%, or T-score between -1 and -2.4 as reported in the ACR summary.
Low risk. No higher criterion, adjusted major probability below 10%, hip probability below 1%, and BMD T-score above -1.0. Use the source table and clinical judgment for boundary values rather than rounding a patient into reassurance.
For adults younger than 40, FRAX is not validated. The ACR moderate-risk criterion includes continuing prednisone at least 7.5 mg/day for at least six months with a Z-score below -3 or significant BMD loss beyond the facility least significant change. Prior fractures or high-dose exposure require the separate younger-adult assessment. A Z-score below the expected age range is not identical to meeting the ACR moderate-risk threshold. Pharmacotherapy recommendations for these younger adults are conditional. [1][2]
Reassess fractures, falls, exposure, adherence, adverse effects, and secondary causes over time. ACR recommends BMD with vertebral assessment or spine radiography every 1 to 2 years during continuing exposure, including follow-up during treatment and after stopping osteoporosis therapy. New pain, height loss, or fracture warrants earlier clinical review. Compare serial BMD with the facility least significant change on a comparable system. A small change below that threshold is not proven progression. [1][2][16]
Case 11
Show answer and explanations for case 11
A. Discuss bone-directed therapy for moderate risk and proceed with zoledronic acid while correcting calcium afterward (Why this does not fit)
Read the explanation or work through it
Moderate risk supports a pharmacotherapy discussion. Adequate renal function does not remove the separate hypocalcemia contraindication. The infusion should wait for correction rather than precede correction of the calcium abnormality.
Predict one fact before revealing it.
What supports the treatment discussion?
Moderate risk supports a pharmacotherapy discussion.
Does the renal result settle every safety requirement?
Adequate renal function does not remove the separate hypocalcemia contraindication.
Why is the proposed order unsafe?
The infusion should wait for correction rather than precede correction of the calcium abnormality.
The infusion should wait for correction rather than precede correction of the calcium abnormality.[1][2][17][10]
Read all reasoning steps
What supports the treatment discussion?
Moderate risk supports a pharmacotherapy discussion.
Does the renal result settle every safety requirement?
Adequate renal function does not remove the separate hypocalcemia contraindication.
Why is the proposed order unsafe?
The infusion should wait for correction rather than precede correction of the calcium abnormality.
B. Correct hypocalcemia and defer medication discussion because T-score is above -2.5 (Why this does not fit)
Read the explanation or work through it
Hypocalcemia requires evaluation and correction. The adjusted fracture probabilities already satisfy moderate-risk criteria. A T-score above -2.5 does not justify omitting bone-directed therapy discussion at this assessed risk.
Predict one fact before revealing it.
Which part of this plan is appropriate?
Hypocalcemia requires evaluation and correction.
What independent evidence supports pharmacotherapy?
The adjusted fracture probabilities already satisfy moderate-risk criteria.
Why is the density cutoff an incomplete treatment rule?
A T-score above -2.5 does not justify omitting bone-directed therapy discussion at this assessed risk.
A T-score above -2.5 does not justify omitting bone-directed therapy discussion at this assessed risk.[1][2][17][10]
Read all reasoning steps
Which part of this plan is appropriate?
Hypocalcemia requires evaluation and correction.
What independent evidence supports pharmacotherapy?
The adjusted fracture probabilities already satisfy moderate-risk criteria.
Why is the density cutoff an incomplete treatment rule?
A T-score above -2.5 does not justify omitting bone-directed therapy discussion at this assessed risk.
C. Correct hypocalcemia and use teriparatide as the guideline-preferred treatment for this risk category (Why this does not fit)
Read the explanation or work through it
Teriparatide is among options that may be considered at moderate risk. The ACR guideline does not prefer teriparatide over the other listed agents for all moderate-risk adults. The plan should reflect suitability and patient preference rather than an invented universal anabolic preference.
Predict one fact before revealing it.
Can teriparatide be considered at moderate risk?
Teriparatide is among options that may be considered at moderate risk.
Does the guideline rank it first for this category?
The ACR guideline does not prefer teriparatide over the other listed agents for all moderate-risk adults.
What should determine selection among suitable options?
The plan should reflect suitability and patient preference rather than an invented universal anabolic preference.
The plan should reflect suitability and patient preference rather than an invented universal anabolic preference.[1][2][17][10]
Read all reasoning steps
Can teriparatide be considered at moderate risk?
Teriparatide is among options that may be considered at moderate risk.
Does the guideline rank it first for this category?
The ACR guideline does not prefer teriparatide over the other listed agents for all moderate-risk adults.
What should determine selection among suitable options?
The plan should reflect suitability and patient preference rather than an invented universal anabolic preference.
D. Replace the infusion with denosumab now to bypass the calcium concern (Why this does not fit)
Read the explanation or work through it
Denosumab is an alternative bone-directed medication in selected patients. Denosumab also requires correction of pre-existing hypocalcemia. Changing the antiresorptive agent does not resolve the immediate mineral abnormality.
Predict one fact before revealing it.
Why is denosumab a plausible alternative class?
Denosumab is an alternative bone-directed medication in selected patients.
Does denosumab remove the calcium requirement?
Denosumab also requires correction of pre-existing hypocalcemia.
Why is immediate substitution insufficient?
Changing the antiresorptive agent does not resolve the immediate mineral abnormality.
Changing the antiresorptive agent does not resolve the immediate mineral abnormality.[1][2][17][10]
Read all reasoning steps
Why is denosumab a plausible alternative class?
Denosumab is an alternative bone-directed medication in selected patients.
Does denosumab remove the calcium requirement?
Denosumab also requires correction of pre-existing hypocalcemia.
Why is immediate substitution insufficient?
Changing the antiresorptive agent does not resolve the immediate mineral abnormality.
E. Discuss bone-directed therapy for moderate risk, but correct hypocalcemia before the proposed zoledronic acid infusion (Best answer)
Read the explanation or work through it
The supplied risk findings meet the ACR moderate-risk category without evidence of a higher category. Zoledronic acid is contraindicated in uncorrected hypocalcemia. The medication plan should continue while the calcium abnormality is evaluated and corrected before infusion.
Predict one fact before revealing it.
Which risk category follows from the complete findings?
The supplied risk findings meet the ACR moderate-risk category without evidence of a higher category.
What immediate safety barrier affects the proposed infusion?
Zoledronic acid is contraindicated in uncorrected hypocalcemia.
How should the two findings change the plan?
The medication plan should continue while the calcium abnormality is evaluated and corrected before infusion.
The medication plan should continue while the calcium abnormality is evaluated and corrected before infusion.[1][2][17][10]
Read all reasoning steps
Which risk category follows from the complete findings?
The supplied risk findings meet the ACR moderate-risk category without evidence of a higher category.
What immediate safety barrier affects the proposed infusion?
Zoledronic acid is contraindicated in uncorrected hypocalcemia.
How should the two findings change the plan?
The medication plan should continue while the calcium abnormality is evaluated and corrected before infusion.
Takeaway: Treatment eligibility does not eliminate the need to correct a drug-specific safety problem before administration.
Protect the existing surface or support new formation
Calcium, vitamin D, weight-bearing activity, resistance exercise, smoking cessation, and fall prevention support skeletal health. They do not adequately replace bone-directed treatment at moderate, high, or very high fracture risk. Optimize intake rather than giving the same supplement amounts to everyone regardless of diet or disease. The ACR recommendations compare medication benefits and harms within risk categories. [1]
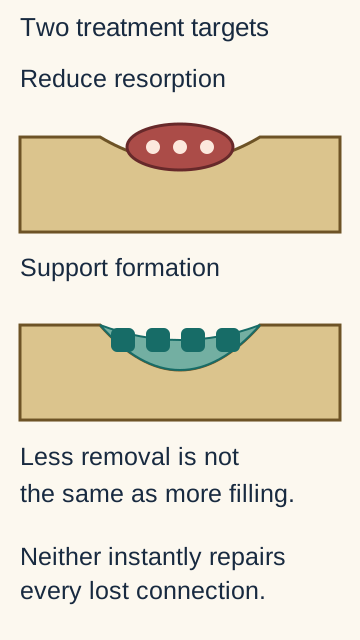
Antiresorptives reduce removal. Alendronate binds bone mineral and impairs osteoclast-mediated resorption. Denosumab binds RANKL, reducing osteoclast formation, function, and survival. They approach the same side of the remodeling balance through different targets. They do not directly recreate a lost trabecular connection in a single cycle. [8][10]
Anabolic treatment supports formation. Intermittent teriparatide activates the PTH receptor and stimulates new bone formation. This intermittent pharmacologic exposure is not equivalent to sustained endogenous PTH excess. It offers a way to address the formation side, but low turnover alone is not a rule that antiresorptives cannot help. Routine biopsy is not required to allocate ordinary GIOP treatment. [9]
Antiresorptives limit removal; anabolics support formation. This conceptual comparison is not a head-to-head efficacy estimate, a prescribing recommendation, or instant structural restoration.
No third-party artwork. Physiological references [1][8][9][10].
For adults at least 40 receiving long-term glucocorticoids, ACR strongly recommends pharmacotherapy at moderate, high, or very high fracture risk. At moderate risk, the listed bisphosphonate, denosumab, and PTH/PTHrP options have no preferred order. At very high risk, ACR conditionally favors PTH/PTHrP therapy over antiresorptives. Oral bisphosphonates have a strong recommendation over no treatment at high and very high risk. Conditional preferences do not make every other feasible agent wrong. Initial selection should be shared and individualized. [1][2] At high risk, ACR conditionally favors denosumab or PTH/PTHrP over bisphosphonates. A suitable bisphosphonate remains an option after shared discussion of preferences and constraints. [1]
Drug choice includes safety. Oral alendronate is contraindicated with esophageal emptying disorders such as stricture and with inability to remain upright as directed. Correct hypocalcemia before therapy. Its label does not recommend use when creatinine clearance is below 35 mL/min. Rare osteonecrosis of the jaw and atypical femoral fractures require appropriate assessment without erasing expected benefit in high-risk disease. [8] Intravenous zoledronic acid avoids esophageal exposure but is contraindicated with hypocalcemia, creatinine clearance below 35 mL/min, or acute renal impairment. Check mineral status, renal function, hydration, and the product's administration requirements before infusion. Creatinine clearance and indexed eGFR are different estimates, not interchangeable numbers. [17] For oral alendronate, taking every prescribed tablet does not guarantee adequate delivery. Food and coffee reduce absorption. Review actual dosing conditions before interpreting a poor BMD response. [8]
Denosumab is not a risk-free substitute in advanced kidney disease. Severe hypocalcemia is a boxed warning, especially with CKD-mineral and bone disorder. Teriparatide has precautions for hypercalcemic disorders, stones, and increased baseline osteosarcoma risk such as prior skeletal radiation. Its current label allows consideration beyond two lifetime years only when high fracture risk persists or returns. [9][10] The June 2026 denosumab label identifies advanced CKD using eGFR below 30 mL/min/1.73 m2. Assess possible CKD-mineral and bone disorder with suitable expertise; reduced kidney function alone does not prove its subtype. The August 2026 FORTEO label corroborates the skeletal-radiation avoidance precaution and duration language. [18]
Pregnancy plans require drug-specific discussion. Denosumab is contraindicated during pregnancy. Alendronate labeling directs discontinuation when pregnancy is recognized; teriparatide labeling advises considering discontinuation. These distinctions call for prospective planning rather than assuming that one bone drug is interchangeable with another. [8][9][10]
The labels and guideline answer different questions. A guideline can discuss an agent within a risk category while its product indication, precautions, and the individual patient still constrain use. Romosozumab targets sclerostin, unlike RANKL-targeting denosumab; that target comparison is not a routine GIOP prescribing recommendation. [1][20]
Case 14
Show answer and explanations for case 14
A. Initial teriparatide is conditionally favored; oral alendronate remains suitable if taken with extra water (Why this does not fit)
Read the explanation or work through it
The fracture history supports the conditional initial anabolic preference. An esophageal stricture with delayed emptying is an oral alendronate contraindication. Extra water does not remove the documented emptying disorder.
Predict one fact before revealing it.
Which part follows the risk-based recommendation?
The fracture history supports the conditional initial anabolic preference.
What is the drug-specific problem?
An esophageal stricture with delayed emptying is an oral alendronate contraindication.
Why does the proposed administration adjustment fail?
Extra water does not remove the documented emptying disorder.
Extra water does not remove the documented emptying disorder.[1][2][8][9][18]
Read all reasoning steps
Which part follows the risk-based recommendation?
The fracture history supports the conditional initial anabolic preference.
What is the drug-specific problem?
An esophageal stricture with delayed emptying is an oral alendronate contraindication.
Why does the proposed administration adjustment fail?
Extra water does not remove the documented emptying disorder.
B. Initial teriparatide should await antiresorptive failure; oral alendronate is unsuitable because of the stricture (Why this does not fit)
Read the explanation or work through it
The stricture makes oral alendronate unsuitable. The ACR very-high-risk recommendation permits initial anabolic treatment. The guideline does not require prior antiresorptive failure for this initial discussion.
Predict one fact before revealing it.
Which part correctly applies the esophageal precaution?
The stricture makes oral alendronate unsuitable.
What does the guideline allow at very high risk?
The ACR very-high-risk recommendation permits initial anabolic treatment.
Why is mandatory prior failure an added restriction?
The guideline does not require prior antiresorptive failure for this initial discussion.
The guideline does not require prior antiresorptive failure for this initial discussion.[1][2][8][9][18]
Read all reasoning steps
Which part correctly applies the esophageal precaution?
The stricture makes oral alendronate unsuitable.
What does the guideline allow at very high risk?
The ACR very-high-risk recommendation permits initial anabolic treatment.
Why is mandatory prior failure an added restriction?
The guideline does not require prior antiresorptive failure for this initial discussion.
C. Initial teriparatide should await antiresorptive failure; oral alendronate remains suitable with extra water (Why this does not fit)
Read the explanation or work through it
The ACR guideline does not impose a universal antiresorptive-first sequence at very high risk. The documented stricture is also a contraindication to oral alendronate. Neither postponing the anabolic discussion nor using extra water resolves the supplied clinical constraints.
Predict one fact before revealing it.
Does the guideline require this treatment sequence?
The ACR guideline does not impose a universal antiresorptive-first sequence at very high risk.
What independently limits the oral option?
The documented stricture is also a contraindication to oral alendronate.
Why does the combined comparison fail?
Neither postponing the anabolic discussion nor using extra water resolves the supplied clinical constraints.
Neither postponing the anabolic discussion nor using extra water resolves the supplied clinical constraints.[1][2][8][9][18]
Read all reasoning steps
Does the guideline require this treatment sequence?
The ACR guideline does not impose a universal antiresorptive-first sequence at very high risk.
What independently limits the oral option?
The documented stricture is also a contraindication to oral alendronate.
Why does the combined comparison fail?
Neither postponing the anabolic discussion nor using extra water resolves the supplied clinical constraints.
D. Initial teriparatide is conditionally favored for her fracture-risk category; oral alendronate is unsuitable because of the stricture (Best answer)
Read the explanation or work through it
The prior osteoporotic vertebral fractures place this adult in the ACR very-high-risk category. The ACR guideline conditionally favors PTH/PTHrP therapy over antiresorptives at very high risk. The esophageal emptying disorder independently contraindicates oral alendronate.
Predict one fact before revealing it.
Which risk category follows from the fracture history?
The prior osteoporotic vertebral fractures place this adult in the ACR very-high-risk category.
What initial class preference does ACR state for that category?
The ACR guideline conditionally favors PTH/PTHrP therapy over antiresorptives at very high risk.
Which separate finding limits oral alendronate?
The esophageal emptying disorder independently contraindicates oral alendronate.
The esophageal emptying disorder independently contraindicates oral alendronate.[1][2][8][9][18]
Read all reasoning steps
Which risk category follows from the fracture history?
The prior osteoporotic vertebral fractures place this adult in the ACR very-high-risk category.
What initial class preference does ACR state for that category?
The ACR guideline conditionally favors PTH/PTHrP therapy over antiresorptives at very high risk.
Which separate finding limits oral alendronate?
The esophageal emptying disorder independently contraindicates oral alendronate.
E. Initial teriparatide is conditionally favored; every bisphosphonate route is unsuitable because of the stricture (Why this does not fit)
Read the explanation or work through it
The fracture history supports considering initial teriparatide. An esophageal emptying disorder specifically limits oral alendronate administration. The stricture does not itself prohibit intravenous bisphosphonate therapy if otherwise suitable.
Predict one fact before revealing it.
Which part fits the risk category?
The fracture history supports considering initial teriparatide.
Which route is affected by the stricture?
An esophageal emptying disorder specifically limits oral alendronate administration.
Why is the exclusion of every route too broad?
The stricture does not itself prohibit intravenous bisphosphonate therapy if otherwise suitable.
The stricture does not itself prohibit intravenous bisphosphonate therapy if otherwise suitable.[1][2][8][9][18]
Read all reasoning steps
Which part fits the risk category?
The fracture history supports considering initial teriparatide.
Which route is affected by the stricture?
An esophageal emptying disorder specifically limits oral alendronate administration.
Why is the exclusion of every route too broad?
The stricture does not itself prohibit intravenous bisphosphonate therapy if otherwise suitable.
Takeaway: A conditional initial anabolic preference and an oral-drug contraindication are separate decisions.
Plan the next phase before stopping the current one
Reducing glucocorticoid exposure can reduce harm when disease control permits. That means coordinating the lowest effective exposure and steroid-sparing care. It does not mean abruptly stopping long-term prednisone. Adrenal suppression and recurrence of the underlying disease require a supervised tapering plan. [12]
Denosumab cessation needs a successor plan because its effect is not retained as a bisphosphonate-like skeletal depot. The ACR summary discusses starting bisphosphonate protection around 6 to 7 months after the last injection; vertebral fractures have occurred as early as 7 to 9 months. Precise timing, agent, and duration remain individualized and under study. Oral or IV suitability matters. Direct transition to PTH/PTHrP alone can cause transient bone loss and is not the routine recommended sequence. After an anabolic course, antiresorptive treatment is generally needed to retain gains. [1][2][10]
A lower prednisone dose or a better DXA does not automatically end treatment. When glucocorticoids stop, ACR recommends continuing osteoporosis therapy if meaningful fracture risk remains. Its discontinuation pathway considers no new fragility fracture and current T-score at least -2.5, alongside current risk and drug history. Bisphosphonates or raloxifene may be stopped without mandatory sequential treatment when cessation is appropriate. Denosumab, PTH/PTHrP agents, and romosozumab still need sequential protection. Continue supportive care and monitoring. [1][2]
New focal groin pain needs a separate evaluation. Osteonecrosis concerns bone viability; insufficiency fracture concerns failure under ordinary load. Both may occur without a very low DXA result. A crescent sign indicates subchondral fracture and may precede appreciable collapse. The 2026 ARCO guideline separates fracture from loss of the rounded femoral-head contour. An antiresorptive plan for generalized fragility does not settle this focal problem. [11][15]
MRI morphology can assist that differential. A smooth, concave band around a segment favors osteonecrosis; an irregular band convex to the surface more often favors primary subchondral insufficiency fracture. Ikemura and colleagues' 2010 MRI/histology study involved older patients with collapsed femoral heads selected for surgery. The pattern is an aid, not a universal diagnostic rule or validation in every earlier stage. Our case uses a written educational description, not a clinical photograph or image-interpretation certification. Orthopedic assessment integrates symptoms, lesion extent, fracture, and collapse. Steroid reduction alone is not treatment of an established lesion, and lack of fever cannot exclude infection. [21][15]
The earlier medication comparison is useful only as a starting pattern. Cushingoid fat redistribution, skin fragility, and hyperglycemia fit systemic glucocorticoid exposure. Other anti-inflammatory drugs have different adverse-effect profiles; they cannot be excluded by one reassuring symptom. New pain still needs clinical assessment. Do not assume osteoporosis medication prevents steroid-related osteonecrosis.
Before labeling a bone drug ineffective, review adherence, oral absorption and administration, new secondary causes, and measurement precision. ACR conditionally recommends changing medication class when a fracture occurs after at least 12 months of treatment or significant BMD loss occurs after 1 to 2 years. A poor oral administration history may instead support a feasible nonoral plan after assessment. [1]
Bring the lesson back to one decision. First identify exposure and fracture risk. Then consider formation, resorption, mineral support, and falls as distinct contributors. Finally choose a feasible treatment and transition plan. Protecting bone is a continuing risk-based process, not a single supplement prescription.[1]
Case 17
Show answer and explanations for case 17
A. Arrange oral alendronate transition now with upright-position counseling (Why this does not fit)
Read the explanation or work through it
A bisphosphonate transition addresses the denosumab discontinuation hazard. The esophageal stricture remains a contraindication to oral alendronate. Upright counseling does not repair the stricture, so a nonoral transition should be assessed.
Predict one fact before revealing it.
What is appropriate about a bisphosphonate transition?
A bisphosphonate transition addresses the denosumab discontinuation hazard.
What patient-specific issue excludes this route?
The esophageal stricture remains a contraindication to oral alendronate.
Why does counseling alone not resolve it?
Upright counseling does not repair the stricture, so a nonoral transition should be assessed.
Upright counseling does not repair the stricture, so a nonoral transition should be assessed.[1][2][8][10][17]
Read all reasoning steps
What is appropriate about a bisphosphonate transition?
A bisphosphonate transition addresses the denosumab discontinuation hazard.
What patient-specific issue excludes this route?
The esophageal stricture remains a contraindication to oral alendronate.
Why does counseling alone not resolve it?
Upright counseling does not repair the stricture, so a nonoral transition should be assessed.
B. Arrange intravenous bisphosphonate only after a DXA decline documents loss (Why this does not fit)
Read the explanation or work through it
An intravenous route avoids the esophageal administration problem. Denosumab cessation can cause vertebral fractures before a delayed DXA-based response is arranged. Sequential protection should be planned by the treatment interval rather than waiting for documented loss.
Predict one fact before revealing it.
Which route constraint is respected?
An intravenous route avoids the esophageal administration problem.
What risk makes waiting problematic?
Denosumab cessation can cause vertebral fractures before a delayed DXA-based response is arranged.
What should guide transition planning instead?
Sequential protection should be planned by the treatment interval rather than waiting for documented loss.
Sequential protection should be planned by the treatment interval rather than waiting for documented loss.[1][2][8][10][17]
Read all reasoning steps
Which route constraint is respected?
An intravenous route avoids the esophageal administration problem.
What risk makes waiting problematic?
Denosumab cessation can cause vertebral fractures before a delayed DXA-based response is arranged.
What should guide transition planning instead?
Sequential protection should be planned by the treatment interval rather than waiting for documented loss.
C. Arrange intravenous bisphosphonate transition around this interval with renal and mineral checks (Best answer)
Read the explanation or work through it
Six months since the last injection is approaching the ACR-discussed bisphosphonate transition interval. The esophageal stricture favors a nonoral route for sequential bisphosphonate protection. Stable clearance above the zoledronic acid cutoff supports considering that route after the usual safety checks.
Predict one fact before revealing it.
Why does the date of the last injection matter now?
Six months since the last injection is approaching the ACR-discussed bisphosphonate transition interval.
How does the esophageal finding affect the successor route?
The esophageal stricture favors a nonoral route for sequential bisphosphonate protection.
Which renal finding supports consideration of IV treatment?
Stable clearance above the zoledronic acid cutoff supports considering that route after the usual safety checks.
Stable clearance above the zoledronic acid cutoff supports considering that route after the usual safety checks.[1][2][8][10][17]
Read all reasoning steps
Why does the date of the last injection matter now?
Six months since the last injection is approaching the ACR-discussed bisphosphonate transition interval.
How does the esophageal finding affect the successor route?
The esophageal stricture favors a nonoral route for sequential bisphosphonate protection.
Which renal finding supports consideration of IV treatment?
Stable clearance above the zoledronic acid cutoff supports considering that route after the usual safety checks.
D. Switch directly to teriparatide alone now as the preferred rebound-prevention strategy (Why this does not fit)
Read the explanation or work through it
Teriparatide can be useful in selected patients who need anabolic treatment. Transition from denosumab to PTH/PTHrP alone can produce transient bone loss. The ACR guideline does not recommend that sequence as the routine solution to denosumab withdrawal.
Predict one fact before revealing it.
Why might an anabolic drug be considered generally?
Teriparatide can be useful in selected patients who need anabolic treatment.
What happens with this particular treatment order?
Transition from denosumab to PTH/PTHrP alone can produce transient bone loss.
Why is this sequence not the preferred solution here?
The ACR guideline does not recommend that sequence as the routine solution to denosumab withdrawal.
The ACR guideline does not recommend that sequence as the routine solution to denosumab withdrawal.[1][2][8][10][17]
Read all reasoning steps
Why might an anabolic drug be considered generally?
Teriparatide can be useful in selected patients who need anabolic treatment.
What happens with this particular treatment order?
Transition from denosumab to PTH/PTHrP alone can produce transient bone loss.
Why is this sequence not the preferred solution here?
The ACR guideline does not recommend that sequence as the routine solution to denosumab withdrawal.
E. Begin an unprotected holiday because four years of denosumab leaves a persistent skeletal depot (Why this does not fit)
Read the explanation or work through it
Bisphosphonates can remain associated with bone mineral after administration stops. Denosumab does not provide a comparable retained skeletal depot. A bisphosphonate-style unprotected holiday therefore fails to address denosumab rebound risk.
Predict one fact before revealing it.
Which drug class can provide residual skeletal persistence?
Bisphosphonates can remain associated with bone mineral after administration stops.
Does denosumab have comparable persistence?
Denosumab does not provide a comparable retained skeletal depot.
Why is the proposed holiday inappropriate?
A bisphosphonate-style unprotected holiday therefore fails to address denosumab rebound risk.
A bisphosphonate-style unprotected holiday therefore fails to address denosumab rebound risk.[1][2][8][10][17]
Read all reasoning steps
Which drug class can provide residual skeletal persistence?
Bisphosphonates can remain associated with bone mineral after administration stops.
Does denosumab have comparable persistence?
Denosumab does not provide a comparable retained skeletal depot.
Why is the proposed holiday inappropriate?
A bisphosphonate-style unprotected holiday therefore fails to address denosumab rebound risk.
Takeaway: Denosumab cessation requires timely sequential protection, and the successor must fit the patient's route and renal constraints.
All 18 original educational cases remain available in this document. Six are placed beside related teaching. These questions have not been psychometrically calibrated to a licensing examination.
Case 1
Show answer and explanations for case 1
A. Longer survival with higher resorptive activity per viable cell (Why this does not fit)
Read the explanation or work through it
The survival result supports a larger surviving osteoclast pool. Measured viable-cell-time accounts for differences in viable-cell exposure throughout the dentin assay. The lower normalized resorbed area argues against increased average activity per viable cell.
Predict one fact before revealing it.
What part of this interpretation fits the first assay?
The survival result supports a larger surviving osteoclast pool.
What difference does measured viable-cell-time normalization control?
Measured viable-cell-time accounts for differences in viable-cell exposure throughout the dentin assay.
Which direction of activity does the second assay support?
The lower normalized resorbed area argues against increased average activity per viable cell.
Compare survival separately from resorption normalized to viable-cell exposure over the entire assay.[4][14]
Read all reasoning steps
What part of this interpretation fits the first assay?
The survival result supports a larger surviving osteoclast pool.
What difference does measured viable-cell-time normalization control?
Measured viable-cell-time accounts for differences in viable-cell exposure throughout the dentin assay.
Which direction of activity does the second assay support?
The lower normalized resorbed area argues against increased average activity per viable cell.
B. Shorter survival with lower resorptive activity per viable cell (Why this does not fit)
Read the explanation or work through it
The dentin result supports reduced activity per viable cell. The survival assay began with equal cell counts in both groups. The larger surviving steroid-exposed population argues against shortened survival.
Predict one fact before revealing it.
What part of this interpretation fits the dentin assay?
The dentin result supports reduced activity per viable cell.
What baseline comparison matters for survival?
The survival assay began with equal cell counts in both groups.
Why does the survival conclusion fail?
The larger surviving steroid-exposed population argues against shortened survival.
Compare survival separately from resorption normalized to viable-cell exposure over the entire assay.[4][14]
Read all reasoning steps
What part of this interpretation fits the dentin assay?
The dentin result supports reduced activity per viable cell.
What baseline comparison matters for survival?
The survival assay began with equal cell counts in both groups.
Why does the survival conclusion fail?
The larger surviving steroid-exposed population argues against shortened survival.
C. Longer survival with lower resorptive activity per viable cell (Best answer)
Read the explanation or work through it
More surviving cells after equal starting counts supports prolonged osteoclast survival. Lower resorbed area per measured viable-cell-time supports reduced average resorptive activity per viable cell. The combined findings do not establish total skeletal resorption in a patient.
Predict one fact before revealing it.
What does the survival assay establish?
More surviving cells after equal starting counts supports prolonged osteoclast survival.
What does the viable-cell-time-normalized dentin result compare?
Lower resorbed area per measured viable-cell-time supports reduced average resorptive activity per viable cell.
How far can these culture findings be extended?
The combined findings do not establish total skeletal resorption in a patient.
Compare survival separately from resorption normalized to viable-cell exposure over the entire assay.[4][14]
Read all reasoning steps
What does the survival assay establish?
More surviving cells after equal starting counts supports prolonged osteoclast survival.
What does the viable-cell-time-normalized dentin result compare?
Lower resorbed area per measured viable-cell-time supports reduced average resorptive activity per viable cell.
How far can these culture findings be extended?
The combined findings do not establish total skeletal resorption in a patient.
D. Shorter survival with higher resorptive activity per viable cell (Why this does not fit)
Read the explanation or work through it
Cell survival cannot be inferred from pit area alone. The separate survival assay supports prolonged survival with dexamethasone. The viable-cell-time-normalized dentin assay supports lower average activity per viable cell.
Predict one fact before revealing it.
Can the dentin result alone establish survival?
Cell survival cannot be inferred from pit area alone.
Which survival direction is actually supported?
The separate survival assay supports prolonged survival with dexamethasone.
Which functional direction is actually supported?
The viable-cell-time-normalized dentin assay supports lower average activity per viable cell.
Compare survival separately from resorption normalized to viable-cell exposure over the entire assay.[4][14]
Read all reasoning steps
Can the dentin result alone establish survival?
Cell survival cannot be inferred from pit area alone.
Which survival direction is actually supported?
The separate survival assay supports prolonged survival with dexamethasone.
Which functional direction is actually supported?
The viable-cell-time-normalized dentin assay supports lower average activity per viable cell.
E. Unchanged survival with lower resorptive activity per viable cell (Why this does not fit)
Read the explanation or work through it
Lower average resorptive activity fits the viable-cell-time-normalized dentin assay. The independent survival comparison contains more viable steroid-exposed cells at day 3. The survival difference cannot be dismissed merely because each surviving cell resorbs less.
Predict one fact before revealing it.
Which finding fits this interpretation?
Lower average resorptive activity fits the viable-cell-time-normalized dentin assay.
What does the first assay add?
The independent survival comparison contains more viable steroid-exposed cells at day 3.
Why is unchanged survival not supported?
The survival difference cannot be dismissed merely because each surviving cell resorbs less.
Compare survival separately from resorption normalized to viable-cell exposure over the entire assay.[4][14]
Read all reasoning steps
Which finding fits this interpretation?
Lower average resorptive activity fits the viable-cell-time-normalized dentin assay.
What does the first assay add?
The independent survival comparison contains more viable steroid-exposed cells at day 3.
Why is unchanged survival not supported?
The survival difference cannot be dismissed merely because each surviving cell resorbs less.
Takeaway: Cell survival and resorption per viable cell are different measurements.
A. Scarce OPG increases available ligand; precursor responsiveness is increased (Why this does not fit)
Read the explanation or work through it
The scarce-OPG mixture supports increased ligand availability. A heightened response to matched free RANKL would support increased precursor responsiveness. The overlapping curves provide no such evidence of increased responsiveness.
Predict one fact before revealing it.
Which part fits the decoy comparison?
The scarce-OPG mixture supports increased ligand availability.
What would demonstrate heightened responsiveness?
A heightened response to matched free RANKL would support increased precursor responsiveness.
Why does the second part fail?
The overlapping curves provide no such evidence of increased responsiveness.
The overlapping curves provide no such evidence of increased responsiveness.[4][10]
Read all reasoning steps
Which part fits the decoy comparison?
The scarce-OPG mixture supports increased ligand availability.
What would demonstrate heightened responsiveness?
A heightened response to matched free RANKL would support increased precursor responsiveness.
Why does the second part fail?
The overlapping curves provide no such evidence of increased responsiveness.
B. Scarce OPG decreases available ligand; precursor responsiveness is increased (Why this does not fit)
Read the explanation or work through it
OPG binds RANKL as a decoy rather than supplying ligand to RANK. Reducing the decoy therefore increases rather than decreases ligand availability. The matched free-ligand curves also fail to show increased precursor responsiveness.
Predict one fact before revealing it.
What does OPG do to RANKL?
OPG binds RANKL as a decoy rather than supplying ligand to RANK.
What direction follows from reducing OPG?
Reducing the decoy therefore increases rather than decreases ligand availability.
What does the independent precursor experiment rule against?
The matched free-ligand curves also fail to show increased precursor responsiveness.
The matched free-ligand curves also fail to show increased precursor responsiveness.[4][10]
Read all reasoning steps
What does OPG do to RANKL?
OPG binds RANKL as a decoy rather than supplying ligand to RANK.
What direction follows from reducing OPG?
Reducing the decoy therefore increases rather than decreases ligand availability.
What does the independent precursor experiment rule against?
The matched free-ligand curves also fail to show increased precursor responsiveness.
C. Scarce OPG increases available ligand; precursor responsiveness is decreased (Why this does not fit)
Read the explanation or work through it
Less OPG interception can explain more osteoclast maturation. Decreased precursor responsiveness would require a lower response to matched free ligand. The overlapping curves do not support that reduced-response claim.
Predict one fact before revealing it.
What explains the decoy experiment?
Less OPG interception can explain more osteoclast maturation.
What finding would support decreased responsiveness?
Decreased precursor responsiveness would require a lower response to matched free ligand.
Why is that conclusion unsupported here?
The overlapping curves do not support that reduced-response claim.
The overlapping curves do not support that reduced-response claim.[4][10]
Read all reasoning steps
What explains the decoy experiment?
Less OPG interception can explain more osteoclast maturation.
What finding would support decreased responsiveness?
Decreased precursor responsiveness would require a lower response to matched free ligand.
Why is that conclusion unsupported here?
The overlapping curves do not support that reduced-response claim.
D. Scarce OPG increases available ligand; altered precursor responsiveness is not demonstrated (Best answer)
Read the explanation or work through it
Less OPG leaves more of the fixed RANKL supply available for RANK binding. Overlapping responses to matched free RANKL do not demonstrate altered precursor responsiveness. The experiments distinguish a ligand-availability effect from a receptor-response change.
Predict one fact before revealing it.
How does less decoy change the free ligand supply?
Less OPG leaves more of the fixed RANKL supply available for RANK binding.
What do the overlapping free-ligand curves show?
Overlapping responses to matched free RANKL do not demonstrate altered precursor responsiveness.
Which two levels must remain separate?
The experiments distinguish a ligand-availability effect from a receptor-response change.
The experiments distinguish a ligand-availability effect from a receptor-response change.[4][10]
Read all reasoning steps
How does less decoy change the free ligand supply?
Less OPG leaves more of the fixed RANKL supply available for RANK binding.
What do the overlapping free-ligand curves show?
Overlapping responses to matched free RANKL do not demonstrate altered precursor responsiveness.
Which two levels must remain separate?
The experiments distinguish a ligand-availability effect from a receptor-response change.
E. Scarce OPG decreases available ligand; altered precursor responsiveness is not demonstrated (Why this does not fit)
Read the explanation or work through it
The overlapping curves do not demonstrate a precursor-response difference. OPG normally removes RANKL from the supply available to RANK. Reducing OPG therefore changes available ligand in the opposite direction from this option.
Predict one fact before revealing it.
Which half fits the free-ligand experiment?
The overlapping curves do not demonstrate a precursor-response difference.
How does the decoy normally affect available ligand?
OPG normally removes RANKL from the supply available to RANK.
Why is the proposed ligand direction reversed?
Reducing OPG therefore changes available ligand in the opposite direction from this option.
Reducing OPG therefore changes available ligand in the opposite direction from this option.[4][10]
Read all reasoning steps
Which half fits the free-ligand experiment?
The overlapping curves do not demonstrate a precursor-response difference.
How does the decoy normally affect available ligand?
OPG normally removes RANKL from the supply available to RANK.
Why is the proposed ligand direction reversed?
Reducing OPG therefore changes available ligand in the opposite direction from this option.
Takeaway: Ligand availability can change without a demonstrated change in precursor responsiveness.
A. The fracture warrants bone-directed treatment assessment; the measured DXA change does not establish interval loss (Best answer)
Read the explanation or work through it
The low-trauma vertebral fracture establishes clinically important skeletal fragility despite the T-score. The 1.2% change is smaller than the facility least significant change of 3.0%. Treatment assessment is justified by the fracture rather than by a statistically established DXA decline.
Predict one fact before revealing it.
What does the low-trauma fracture establish beyond density classification?
The low-trauma vertebral fracture establishes clinically important skeletal fragility despite the T-score.
Does the DXA change exceed measurement uncertainty?
The 1.2% change is smaller than the facility least significant change of 3.0%.
Which finding should drive treatment assessment?
Treatment assessment is justified by the fracture rather than by a statistically established DXA decline.
Treatment assessment is justified by the fracture rather than by a statistically established DXA decline.[1][2][3][13][16]
Read all reasoning steps
What does the low-trauma fracture establish beyond density classification?
The low-trauma vertebral fracture establishes clinically important skeletal fragility despite the T-score.
Does the DXA change exceed measurement uncertainty?
The 1.2% change is smaller than the facility least significant change of 3.0%.
Which finding should drive treatment assessment?
Treatment assessment is justified by the fracture rather than by a statistically established DXA decline.
B. The fracture warrants bone-directed treatment assessment; DXA confirms progressive loss during this year (Why this does not fit)
Read the explanation or work through it
The vertebral fracture makes treatment assessment appropriate. The observed BMD change does not exceed the facility precision threshold. The DXA comparison cannot establish progressive loss during this interval.
Predict one fact before revealing it.
Which finding supports treatment assessment?
The vertebral fracture makes treatment assessment appropriate.
How does the observed change compare with least significant change?
The observed BMD change does not exceed the facility precision threshold.
Why is confirmed progression too strong?
The DXA comparison cannot establish progressive loss during this interval.
The DXA comparison cannot establish progressive loss during this interval.[1][2][3][13][16]
Read all reasoning steps
Which finding supports treatment assessment?
The vertebral fracture makes treatment assessment appropriate.
How does the observed change compare with least significant change?
The observed BMD change does not exceed the facility precision threshold.
Why is confirmed progression too strong?
The DXA comparison cannot establish progressive loss during this interval.
C. Supportive care without medication assessment is sufficient; the measured DXA change does not establish loss (Why this does not fit)
Read the explanation or work through it
The small DXA change does not establish interval deterioration. A low-trauma vertebral fracture carries risk information beyond the density category. Stable measured density does not justify omitting medication assessment after this fracture.
Predict one fact before revealing it.
What is reasonable about the DXA interpretation?
The small DXA change does not establish interval deterioration.
What independent risk information does the fracture supply?
A low-trauma vertebral fracture carries risk information beyond the density category.
Why does the treatment conclusion fail?
Stable measured density does not justify omitting medication assessment after this fracture.
Stable measured density does not justify omitting medication assessment after this fracture.[1][2][3][13][16]
Read all reasoning steps
What is reasonable about the DXA interpretation?
The small DXA change does not establish interval deterioration.
What independent risk information does the fracture supply?
A low-trauma vertebral fracture carries risk information beyond the density category.
Why does the treatment conclusion fail?
Stable measured density does not justify omitting medication assessment after this fracture.
D. Supportive care without medication assessment is sufficient; DXA confirms progressive loss during this year (Why this does not fit)
Read the explanation or work through it
A T-score above -2.5 can distract from clinical fracture history. The vertebral fracture still warrants medication assessment. The subthreshold DXA change also fails to establish interval loss.
Predict one fact before revealing it.
Why might the density category be misleading?
A T-score above -2.5 can distract from clinical fracture history.
Which finding changes the treatment discussion?
The vertebral fracture still warrants medication assessment.
What is wrong with the serial DXA claim?
The subthreshold DXA change also fails to establish interval loss.
The subthreshold DXA change also fails to establish interval loss.[1][2][3][13][16]
Read all reasoning steps
Why might the density category be misleading?
A T-score above -2.5 can distract from clinical fracture history.
Which finding changes the treatment discussion?
The vertebral fracture still warrants medication assessment.
What is wrong with the serial DXA claim?
The subthreshold DXA change also fails to establish interval loss.
E. The fracture warrants treatment assessment; DXA establishes that osteocyte loss caused the fracture (Why this does not fit)
Read the explanation or work through it
Experimental glucocorticoid studies support osteocyte injury as a possible contributor to fragility. DXA measures areal mineral density rather than living osteocyte number. This patient has established fragility without patient-specific proof of an osteocyte mechanism.
Predict one fact before revealing it.
Why is osteocyte injury biologically plausible?
Experimental glucocorticoid studies support osteocyte injury as a possible contributor to fragility.
What does DXA actually measure?
DXA measures areal mineral density rather than living osteocyte number.
What causal distinction must the explanation preserve?
This patient has established fragility without patient-specific proof of an osteocyte mechanism.
This patient has established fragility without patient-specific proof of an osteocyte mechanism.[1][2][3][13][16]
Read all reasoning steps
Why is osteocyte injury biologically plausible?
Experimental glucocorticoid studies support osteocyte injury as a possible contributor to fragility.
What does DXA actually measure?
DXA measures areal mineral density rather than living osteocyte number.
What causal distinction must the explanation preserve?
This patient has established fragility without patient-specific proof of an osteocyte mechanism.
Takeaway: A fragility fracture can establish major clinical risk without proving an interval DXA decline.
A. Individualized strength and balance rehabilitation plus treatment for orthostatic hypotension (Why this does not fit)
Read the explanation or work through it
Proximal weakness supports individualized rehabilitation. The supplied assessment does not demonstrate orthostatic hypotension. The temporal sedative association makes medication review the better supported second target.
The supplied assessment does not demonstrate orthostatic hypotension.
What independent finding supplies a better second target?
The temporal sedative association makes medication review the better supported second target.
B. Individualized strength and balance rehabilitation plus review of the sedative (Best answer)
Read the explanation or work through it
Difficulty rising with proximal weakness supports a functional strength and balance intervention. New drowsiness after a sedative was introduced supports review of a medication-related fall contributor. A combined plan addresses both observed contributors without assuming either is the sole cause.
Predict one fact before revealing it.
Which finding supports a functional intervention?
Difficulty rising with proximal weakness supports a functional strength and balance intervention.
Which separate finding supports medication review?
New drowsiness after a sedative was introduced supports review of a medication-related fall contributor.
Why select the combined plan?
A combined plan addresses both observed contributors without assuming either is the sole cause.
A combined plan addresses both observed contributors without assuming either is the sole cause.[1][12][13][19]
Read all reasoning steps
Which finding supports a functional intervention?
Difficulty rising with proximal weakness supports a functional strength and balance intervention.
Which separate finding supports medication review?
New drowsiness after a sedative was introduced supports review of a medication-related fall contributor.
Why select the combined plan?
A combined plan addresses both observed contributors without assuming either is the sole cause.
C. Sensory compensation training plus review of the sedative (Why this does not fit)
Read the explanation or work through it
Sedative-associated drowsiness supports medication review. The examination preserves sensation while demonstrating proximal weakness. Strength and balance rehabilitation fits the measured functional deficit better than a sensory-only program.
The examination preserves sensation while demonstrating proximal weakness.
Why is the rehabilitation target mismatched?
Strength and balance rehabilitation fits the measured functional deficit better than a sensory-only program.
D. Vestibular rehabilitation plus treatment for orthostatic hypotension (Why this does not fit)
Read the explanation or work through it
Turning-associated falls can prompt consideration of vestibular dysfunction. The stem demonstrates proximal weakness rather than a vestibular deficit. The supplied blood-pressure assessment also fails to support an orthostatic treatment target.
Predict one fact before revealing it.
Why might a vestibular explanation be considered?
Turning-associated falls can prompt consideration of vestibular dysfunction.
Which functional deficit is actually demonstrated?
The stem demonstrates proximal weakness rather than a vestibular deficit.
What evidence is missing for the second intervention?
The supplied blood-pressure assessment also fails to support an orthostatic treatment target.
The supplied blood-pressure assessment also fails to support an orthostatic treatment target.[1][12][13][19]
Read all reasoning steps
Why might a vestibular explanation be considered?
Turning-associated falls can prompt consideration of vestibular dysfunction.
Which functional deficit is actually demonstrated?
The stem demonstrates proximal weakness rather than a vestibular deficit.
What evidence is missing for the second intervention?
The supplied blood-pressure assessment also fails to support an orthostatic treatment target.
E. Sensory compensation training plus vestibular rehabilitation (Why this does not fit)
Read the explanation or work through it
Sensory and vestibular disorders can contribute to falls in older adults. Preserved sensation with chair-rise difficulty favors a strength-related limitation in this case. The proposed pair also leaves the new sedative-associated drowsiness unaddressed.
Predict one fact before revealing it.
Why are these interventions plausible in another patient?
Sensory and vestibular disorders can contribute to falls in older adults.
Which finding distinguishes the functional problem here?
Preserved sensation with chair-rise difficulty favors a strength-related limitation in this case.
Which independent contributor would remain untreated?
The proposed pair also leaves the new sedative-associated drowsiness unaddressed.
The proposed pair also leaves the new sedative-associated drowsiness unaddressed.[1][12][13][19]
Read all reasoning steps
Why are these interventions plausible in another patient?
Sensory and vestibular disorders can contribute to falls in older adults.
Which finding distinguishes the functional problem here?
Preserved sensation with chair-rise difficulty favors a strength-related limitation in this case.
Which independent contributor would remain untreated?
The proposed pair also leaves the new sedative-associated drowsiness unaddressed.
Takeaway: Falls prevention should match demonstrated functional and medication-related contributors.
A. Use the unadjusted FRAX estimate, retain the recent DXA BMD, and obtain new vertebral imaging now (Why this does not fit)
Read the explanation or work through it
Obtaining new vertebral imaging now addresses the interval height loss after previously normal imaging. The glucocorticoid checkbox does not fully represent this daily dose. The unadjusted estimate omits the recommended correction for prednisone above 7.5 mg/day.
Predict one fact before revealing it.
What is appropriate about this plan?
Obtaining new vertebral imaging now addresses the interval height loss after previously normal imaging.
What limitation remains in the calculator input?
The glucocorticoid checkbox does not fully represent this daily dose.
Why is the estimate incomplete?
The unadjusted estimate omits the recommended correction for prednisone above 7.5 mg/day.
Retain adequate recent density measurements while obtaining new structural imaging for a new vertebral concern.[1][2][7]
Read all reasoning steps
What is appropriate about this plan?
Obtaining new vertebral imaging now addresses the interval height loss after previously normal imaging.
What limitation remains in the calculator input?
The glucocorticoid checkbox does not fully represent this daily dose.
Why is the estimate incomplete?
The unadjusted estimate omits the recommended correction for prednisone above 7.5 mg/day.
B. Apply the dose adjustment and defer vertebral assessment until back pain develops (Why this does not fit)
Read the explanation or work through it
Dose correction addresses underrepresentation of higher daily prednisone exposure. Vertebral fractures can occur without back pain. The measured height loss makes deferral until pain an inadequate assessment strategy.
Predict one fact before revealing it.
Which part addresses exposure?
Dose correction addresses underrepresentation of higher daily prednisone exposure.
Why is absence of pain insufficient reassurance?
Vertebral fractures can occur without back pain.
What current finding argues against deferral?
The measured height loss makes deferral until pain an inadequate assessment strategy.
Retain adequate recent density measurements while obtaining new structural imaging for a new vertebral concern.[1][2][7]
Read all reasoning steps
Which part addresses exposure?
Dose correction addresses underrepresentation of higher daily prednisone exposure.
Why is absence of pain insufficient reassurance?
Vertebral fractures can occur without back pain.
What current finding argues against deferral?
The measured height loss makes deferral until pain an inadequate assessment strategy.
C. Use the unadjusted estimate and defer vertebral assessment until the next scheduled DXA (Why this does not fit)
Read the explanation or work through it
The baseline DXA provides useful density information. The higher prednisone dose is incompletely represented by the unadjusted estimate. The new height loss makes the previous normal vertebral assessment insufficient reassurance about current structure.
Predict one fact before revealing it.
What useful information is already available?
The baseline DXA provides useful density information.
Which exposure omission remains?
The higher prednisone dose is incompletely represented by the unadjusted estimate.
Which structural concern remains unresolved?
The new height loss makes the previous normal vertebral assessment insufficient reassurance about current structure.
Retain adequate recent density measurements while obtaining new structural imaging for a new vertebral concern.[1][2][7]
Read all reasoning steps
What useful information is already available?
The baseline DXA provides useful density information.
Which exposure omission remains?
The higher prednisone dose is incompletely represented by the unadjusted estimate.
Which structural concern remains unresolved?
The new height loss makes the previous normal vertebral assessment insufficient reassurance about current structure.
D. Apply the dose adjustment and repeat DXA alone now to resolve the height loss (Why this does not fit)
Read the explanation or work through it
Dose correction is appropriate for the prescribed prednisone exposure. Areal density measurements do not directly establish whether a vertebral body has fractured. Repeating an adequate recent DXA without vertebral assessment does not resolve the height loss.
Predict one fact before revealing it.
Which part of this plan is appropriate?
Dose correction is appropriate for the prescribed prednisone exposure.
What question can DXA alone not answer?
Areal density measurements do not directly establish whether a vertebral body has fractured.
Why is repeating density alone an insufficient next test?
Repeating an adequate recent DXA without vertebral assessment does not resolve the height loss.
Retain adequate recent density measurements while obtaining new structural imaging for a new vertebral concern.[1][2][7]
Read all reasoning steps
Which part of this plan is appropriate?
Dose correction is appropriate for the prescribed prednisone exposure.
What question can DXA alone not answer?
Areal density measurements do not directly establish whether a vertebral body has fractured.
Why is repeating density alone an insufficient next test?
Repeating an adequate recent DXA without vertebral assessment does not resolve the height loss.
E. Apply the glucocorticoid dose adjustment, use the existing recent DXA BMD, and order new VFA or lateral spine radiographs now (Best answer)
Read the explanation or work through it
The prednisone dose exceeds 7.5 mg/day and calls for the guideline FRAX dose adjustment. New measured height loss raises concern for an interval vertebral fracture despite the previously normal vertebral study and absent pain. The existing recent DXA supplies BMD while newly ordered VFA or lateral spine radiographs evaluate current vertebral structure.
Predict one fact before revealing it.
Which exposure feature changes interpretation of FRAX?
The prednisone dose exceeds 7.5 mg/day and calls for the guideline FRAX dose adjustment.
Which finding calls for vertebral evaluation?
New measured height loss raises concern for an interval vertebral fracture despite the previously normal vertebral study and absent pain.
How should the recent adequate density study be used?
The existing recent DXA supplies BMD while newly ordered VFA or lateral spine radiographs evaluate current vertebral structure.
Retain adequate recent density measurements while obtaining new structural imaging for a new vertebral concern.[1][2][7]
Read all reasoning steps
Which exposure feature changes interpretation of FRAX?
The prednisone dose exceeds 7.5 mg/day and calls for the guideline FRAX dose adjustment.
Which finding calls for vertebral evaluation?
New measured height loss raises concern for an interval vertebral fracture despite the previously normal vertebral study and absent pain.
How should the recent adequate density study be used?
The existing recent DXA supplies BMD while newly ordered VFA or lateral spine radiographs evaluate current vertebral structure.
Takeaway: Dose correction and vertebral assessment answer different omissions in an apparently reassuring evaluation.
A. Use the Z-score context and provide supportive care without a medication discussion because Z-score is above -3 (Why this does not fit)
Read the explanation or work through it
A Z-score above -3 does not meet that particular younger-adult density criterion. The ACR criterion also recognizes significant BMD loss during the specified continuing exposure. The precision-qualified loss makes omission of a medication discussion inappropriate on this rationale.
Predict one fact before revealing it.
Which single density criterion is not met?
A Z-score above -3 does not meet that particular younger-adult density criterion.
What alternative criterion matters?
The ACR criterion also recognizes significant BMD loss during the specified continuing exposure.
Why is the proposed reassurance incomplete?
The precision-qualified loss makes omission of a medication discussion inappropriate on this rationale.
The precision-qualified loss makes omission of a medication discussion inappropriate on this rationale.[1][2][16]
Read all reasoning steps
Which single density criterion is not met?
A Z-score above -3 does not meet that particular younger-adult density criterion.
What alternative criterion matters?
The ACR criterion also recognizes significant BMD loss during the specified continuing exposure.
Why is the proposed reassurance incomplete?
The precision-qualified loss makes omission of a medication discussion inappropriate on this rationale.
B. Apply the older-adult T-score category and prescribe on that density category alone (Why this does not fit)
Read the explanation or work through it
The T-score is familiar from older-adult osteoporosis classification. Z-score interpretation is preferred in men younger than 50. This patient needs an age-appropriate risk discussion incorporating significant loss rather than a density-only label.
Predict one fact before revealing it.
Why might the T-score attract attention?
The T-score is familiar from older-adult osteoporosis classification.
Which age-related convention applies?
Z-score interpretation is preferred in men younger than 50.
What assessment is lost by using the density label alone?
This patient needs an age-appropriate risk discussion incorporating significant loss rather than a density-only label.
This patient needs an age-appropriate risk discussion incorporating significant loss rather than a density-only label.[1][2][16]
Read all reasoning steps
Why might the T-score attract attention?
The T-score is familiar from older-adult osteoporosis classification.
Which age-related convention applies?
Z-score interpretation is preferred in men younger than 50.
What assessment is lost by using the density label alone?
This patient needs an age-appropriate risk discussion incorporating significant loss rather than a density-only label.
C. Enter age 40 in FRAX and use its output to decide whether the BMD loss matters (Why this does not fit)
Read the explanation or work through it
FRAX does not supply a validated estimate for this 34-year-old. Substituting age 40 changes the patient rather than validating the calculation. The significant BMD loss already has clinical meaning within the younger-adult ACR framework.
Predict one fact before revealing it.
What is the calculator limitation?
FRAX does not supply a validated estimate for this 34-year-old.
Why does substituting age fail to repair it?
Substituting age 40 changes the patient rather than validating the calculation.
What evidence can guide assessment instead?
The significant BMD loss already has clinical meaning within the younger-adult ACR framework.
The significant BMD loss already has clinical meaning within the younger-adult ACR framework.[1][2][16]
Read all reasoning steps
What is the calculator limitation?
FRAX does not supply a validated estimate for this 34-year-old.
Why does substituting age fail to repair it?
Substituting age 40 changes the patient rather than validating the calculation.
What evidence can guide assessment instead?
The significant BMD loss already has clinical meaning within the younger-adult ACR framework.
D. Use the Z-score context and significant loss during continuing exposure to discuss pharmacotherapy without FRAX (Best answer)
Read the explanation or work through it
For a man younger than 50, the Z-score is the preferred density comparison. Significant loss during at least 7.5 mg/day for at least six months meets the ACR younger-adult moderate-risk criterion. The prevention discussion can proceed without FRAX because FRAX is not validated below age 40.
Predict one fact before revealing it.
Which density comparison is preferred for this patient?
For a man younger than 50, the Z-score is the preferred density comparison.
How does significant loss combine with the exposure duration and dose?
Significant loss during at least 7.5 mg/day for at least six months meets the ACR younger-adult moderate-risk criterion.
How can treatment assessment proceed without a valid FRAX calculation?
The prevention discussion can proceed without FRAX because FRAX is not validated below age 40.
The prevention discussion can proceed without FRAX because FRAX is not validated below age 40.[1][2][16]
Read all reasoning steps
Which density comparison is preferred for this patient?
For a man younger than 50, the Z-score is the preferred density comparison.
How does significant loss combine with the exposure duration and dose?
Significant loss during at least 7.5 mg/day for at least six months meets the ACR younger-adult moderate-risk criterion.
How can treatment assessment proceed without a valid FRAX calculation?
The prevention discussion can proceed without FRAX because FRAX is not validated below age 40.
E. Use the Z-score context and treat the decline as measurement variation until Z-score falls below -3 (Why this does not fit)
Read the explanation or work through it
Serial DXA interpretation depends on the facility least significant change. The 6% decline exceeds the reported 3% precision threshold. Waiting for a Z-score below -3 would disregard already demonstrated significant loss.
Predict one fact before revealing it.
What determines whether the decline is measurable?
Serial DXA interpretation depends on the facility least significant change.
Does this decline exceed that boundary?
The 6% decline exceeds the reported 3% precision threshold.
Why is waiting for a different density threshold inappropriate?
Waiting for a Z-score below -3 would disregard already demonstrated significant loss.
Waiting for a Z-score below -3 would disregard already demonstrated significant loss.[1][2][16]
Read all reasoning steps
What determines whether the decline is measurable?
Serial DXA interpretation depends on the facility least significant change.
Does this decline exceed that boundary?
The 6% decline exceeds the reported 3% precision threshold.
Why is waiting for a different density threshold inappropriate?
Waiting for a Z-score below -3 would disregard already demonstrated significant loss.
Takeaway: Younger adults need age-appropriate interpretation and attention to significant ongoing loss, without an invented FRAX age.
A. High risk; discuss IV zoledronic acid after usual preinfusion checks, avoiding oral alendronate (Best answer)
Read the explanation or work through it
The corrected probabilities of 20.7% and 3.12% place this adult in the ACR high-risk category. The esophageal emptying abnormality contraindicates oral alendronate. IV zoledronic acid remains a feasible discussion after usual checks, given the stated renal and mineral findings and her informed preference.
Predict one fact before revealing it.
Which risk category follows from the corrected FRAX values?
The corrected probabilities of 20.7% and 3.12% place this adult in the ACR high-risk category.
What does persistent tablet hold-up imply for oral alendronate?
The esophageal emptying abnormality contraindicates oral alendronate.
Which bisphosphonate route remains feasible to discuss?
IV zoledronic acid remains a feasible discussion after usual checks, given the stated renal and mineral findings and her informed preference.
Calculate the exposure-adjusted risk category before choosing a treatment route that meets the individual drug precautions.[1][2][8][17]
Read all reasoning steps
Which risk category follows from the corrected FRAX values?
The corrected probabilities of 20.7% and 3.12% place this adult in the ACR high-risk category.
What does persistent tablet hold-up imply for oral alendronate?
The esophageal emptying abnormality contraindicates oral alendronate.
Which bisphosphonate route remains feasible to discuss?
IV zoledronic acid remains a feasible discussion after usual checks, given the stated renal and mineral findings and her informed preference.
B. High risk; discuss oral alendronate after usual administration counseling (Why this does not fit)
Read the explanation or work through it
Multiplying the major and hip probabilities by 1.15 and 1.2 yields high-risk values of 20.7% and 3.12%. Routine administration counseling does not remove the documented esophageal emptying disorder. The oral alendronate route should be replaced by discussion of a suitable nonoral option.
Predict one fact before revealing it.
Does dose correction support the high-risk classification?
Multiplying the major and hip probabilities by 1.15 and 1.2 yields high-risk values of 20.7% and 3.12%.
Can routine administration counseling resolve persistent tablet hold-up?
Routine administration counseling does not remove the documented esophageal emptying disorder.
Which part of this plan must change?
The oral alendronate route should be replaced by discussion of a suitable nonoral option.
Calculate the exposure-adjusted risk category before choosing a treatment route that meets the individual drug precautions.[1][2][8][17]
Read all reasoning steps
Does dose correction support the high-risk classification?
Multiplying the major and hip probabilities by 1.15 and 1.2 yields high-risk values of 20.7% and 3.12%.
Can routine administration counseling resolve persistent tablet hold-up?
Routine administration counseling does not remove the documented esophageal emptying disorder.
Which part of this plan must change?
The oral alendronate route should be replaced by discussion of a suitable nonoral option.
C. Moderate risk; discuss IV zoledronic acid after usual preinfusion checks, avoiding oral alendronate (Why this does not fit)
Read the explanation or work through it
The unadjusted values of 18% and 2.6% lie within the ACR moderate-risk ranges. Prednisone above 7.5 mg/day calls for correction that raises these probabilities into the high-risk category. The nonoral bisphosphonate discussion fits the esophageal finding and the acceptable renal and mineral profile.
Predict one fact before revealing it.
Why would the unadjusted probabilities suggest moderate risk?
The unadjusted values of 18% and 2.6% lie within the ACR moderate-risk ranges.
What does the prednisone dose do to that classification?
Prednisone above 7.5 mg/day calls for correction that raises these probabilities into the high-risk category.
Does the route decision itself fit the supplied constraints?
The nonoral bisphosphonate discussion fits the esophageal finding and the acceptable renal and mineral profile.
Calculate the exposure-adjusted risk category before choosing a treatment route that meets the individual drug precautions.[1][2][8][17]
Read all reasoning steps
Why would the unadjusted probabilities suggest moderate risk?
The unadjusted values of 18% and 2.6% lie within the ACR moderate-risk ranges.
What does the prednisone dose do to that classification?
Prednisone above 7.5 mg/day calls for correction that raises these probabilities into the high-risk category.
Does the route decision itself fit the supplied constraints?
The nonoral bisphosphonate discussion fits the esophageal finding and the acceptable renal and mineral profile.
D. Moderate risk; discuss oral alendronate after usual administration counseling (Why this does not fit)
Read the explanation or work through it
The moderate-risk calculation omits the upward correction for the supplied prednisone dose. Persistent tablet hold-up demonstrates an esophageal emptying problem that contraindicates oral alendronate. The plan requires revision of both the risk category and the proposed oral route.
Predict one fact before revealing it.
What is missing from the moderate-risk calculation?
The moderate-risk calculation omits the upward correction for the supplied prednisone dose.
What finding independently limits oral alendronate?
Persistent tablet hold-up demonstrates an esophageal emptying problem that contraindicates oral alendronate.
Why does the combined plan fail?
The plan requires revision of both the risk category and the proposed oral route.
Calculate the exposure-adjusted risk category before choosing a treatment route that meets the individual drug precautions.[1][2][8][17]
Read all reasoning steps
What is missing from the moderate-risk calculation?
The moderate-risk calculation omits the upward correction for the supplied prednisone dose.
What finding independently limits oral alendronate?
Persistent tablet hold-up demonstrates an esophageal emptying problem that contraindicates oral alendronate.
Why does the combined plan fail?
The plan requires revision of both the risk category and the proposed oral route.
E. Very high risk; defer all bisphosphonate options because the renal value excludes both oral and IV therapy (Why this does not fit)
Read the explanation or work through it
The corrected values remain below the ACR very-high-risk probability boundaries, with no other stated very-high-risk criterion. A stable clearance of 58 mL/min is above the zoledronic acid renal contraindication boundary of 35 mL/min. The documented emptying disorder excludes oral alendronate without excluding a suitable IV bisphosphonate.
Predict one fact before revealing it.
Do these corrected values reach the very-high-risk boundaries?
The corrected values remain below the ACR very-high-risk probability boundaries, with no other stated very-high-risk criterion.
Does a stable creatinine clearance of 58 mL/min exclude zoledronic acid?
A stable clearance of 58 mL/min is above the zoledronic acid renal contraindication boundary of 35 mL/min.
What drug restriction is actually demonstrated?
The documented emptying disorder excludes oral alendronate without excluding a suitable IV bisphosphonate.
Calculate the exposure-adjusted risk category before choosing a treatment route that meets the individual drug precautions.[1][2][8][17]
Read all reasoning steps
Do these corrected values reach the very-high-risk boundaries?
The corrected values remain below the ACR very-high-risk probability boundaries, with no other stated very-high-risk criterion.
Does a stable creatinine clearance of 58 mL/min exclude zoledronic acid?
A stable clearance of 58 mL/min is above the zoledronic acid renal contraindication boundary of 35 mL/min.
What drug restriction is actually demonstrated?
The documented emptying disorder excludes oral alendronate without excluding a suitable IV bisphosphonate.
Takeaway: Calculate the exposure-adjusted risk category before choosing a treatment route that meets the individual drug precautions.
A. Optimize calcium; start alendronate; reassess in 1-2 years (Why this does not fit)
Read the explanation or work through it
Calcium optimization addresses the documented intake deficit. The completed fracture-risk assessment remains low. The ACR guideline recommends against adding osteoporosis medication solely for glucocorticoid exposure at this low assessed risk.
Predict one fact before revealing it.
Which part addresses the actual dietary problem?
Calcium optimization addresses the documented intake deficit.
What is the current fracture-risk category?
The completed fracture-risk assessment remains low.
Why is automatic alendronate unsupported?
The ACR guideline recommends against adding osteoporosis medication solely for glucocorticoid exposure at this low assessed risk.
The ACR guideline recommends against adding osteoporosis medication solely for glucocorticoid exposure at this low assessed risk.[1][2]
Read all reasoning steps
Which part addresses the actual dietary problem?
Calcium optimization addresses the documented intake deficit.
What is the current fracture-risk category?
The completed fracture-risk assessment remains low.
Why is automatic alendronate unsupported?
The ACR guideline recommends against adding osteoporosis medication solely for glucocorticoid exposure at this low assessed risk.
B. Optimize calcium; no osteoporosis drug; stop scheduled skeletal reassessment (Why this does not fit)
Read the explanation or work through it
The current low-risk assessment supports supportive care without an osteoporosis drug. Prednisone exposure is continuing for at least another year. Ongoing exposure makes permanent discharge from scheduled risk reassessment inappropriate.
Predict one fact before revealing it.
Which treatment decision fits current risk?
The current low-risk assessment supports supportive care without an osteoporosis drug.
What future exposure remains?
Prednisone exposure is continuing for at least another year.
Why does follow-up remain necessary?
Ongoing exposure makes permanent discharge from scheduled risk reassessment inappropriate.
Ongoing exposure makes permanent discharge from scheduled risk reassessment inappropriate.[1][2]
Read all reasoning steps
Which treatment decision fits current risk?
The current low-risk assessment supports supportive care without an osteoporosis drug.
What future exposure remains?
Prednisone exposure is continuing for at least another year.
Why does follow-up remain necessary?
Ongoing exposure makes permanent discharge from scheduled risk reassessment inappropriate.
C. Optimize calcium; no osteoporosis drug; reassess in 1-2 years (Best answer)
Read the explanation or work through it
The complete assessment meets the ACR low-risk criteria for an adult at least 40 years old. The dietary deficit calls for individualized calcium optimization rather than automatic identical supplementation. Continuing glucocorticoid exposure warrants planned reassessment despite the currently low risk.
Predict one fact before revealing it.
Which category follows from the combined risk measurements?
The complete assessment meets the ACR low-risk criteria for an adult at least 40 years old.
What specific supportive-care deficit needs correction?
The dietary deficit calls for individualized calcium optimization rather than automatic identical supplementation.
Why retain scheduled follow-up?
Continuing glucocorticoid exposure warrants planned reassessment despite the currently low risk.
Continuing glucocorticoid exposure warrants planned reassessment despite the currently low risk.[1][2]
Read all reasoning steps
Which category follows from the combined risk measurements?
The complete assessment meets the ACR low-risk criteria for an adult at least 40 years old.
What specific supportive-care deficit needs correction?
The dietary deficit calls for individualized calcium optimization rather than automatic identical supplementation.
Why retain scheduled follow-up?
Continuing glucocorticoid exposure warrants planned reassessment despite the currently low risk.
D. Optimize calcium; start teriparatide; reassess in 1-2 years (Why this does not fit)
Read the explanation or work through it
Glucocorticoids can impair formation even before a fracture occurs. A cellular mechanism alone does not establish medication-level clinical fracture risk. The supplied low-risk assessment does not justify initial teriparatide.
Predict one fact before revealing it.
Why might an anabolic mechanism sound attractive?
Glucocorticoids can impair formation even before a fracture occurs.
What additional link is needed before prescribing?
A cellular mechanism alone does not establish medication-level clinical fracture risk.
Why is that link missing in this case?
The supplied low-risk assessment does not justify initial teriparatide.
The supplied low-risk assessment does not justify initial teriparatide.[1][2]
Read all reasoning steps
Why might an anabolic mechanism sound attractive?
Glucocorticoids can impair formation even before a fracture occurs.
What additional link is needed before prescribing?
A cellular mechanism alone does not establish medication-level clinical fracture risk.
Why is that link missing in this case?
The supplied low-risk assessment does not justify initial teriparatide.
E. Maintain calcium intake; no osteoporosis drug; reassess only after fracture (Why this does not fit)
Read the explanation or work through it
Low current fracture risk supports avoiding unnecessary bone-directed medication. The dietary assessment still identifies inadequate calcium intake. Waiting for a fracture also omits planned reassessment during continuing exposure.
Predict one fact before revealing it.
What part of the plan fits low risk?
Low current fracture risk supports avoiding unnecessary bone-directed medication.
Which support deficit remains unaddressed?
The dietary assessment still identifies inadequate calcium intake.
Why is a fracture-only trigger inadequate?
Waiting for a fracture also omits planned reassessment during continuing exposure.
Waiting for a fracture also omits planned reassessment during continuing exposure.[1][2]
Read all reasoning steps
What part of the plan fits low risk?
Low current fracture risk supports avoiding unnecessary bone-directed medication.
Which support deficit remains unaddressed?
The dietary assessment still identifies inadequate calcium intake.
Why is a fracture-only trigger inadequate?
Waiting for a fracture also omits planned reassessment during continuing exposure.
Takeaway: Derive low risk from the full assessment, correct the identified support deficit, and retain follow-up during ongoing exposure.
A. Arrange prompt renal bone-disease and mineral assessment with appropriate expertise before selecting a feasible bone-directed regimen (Best answer)
Read the explanation or work through it
The low-trauma vertebral fracture warrants active prevention planning. The alendronate label does not recommend use below 35 mL/min creatinine clearance. Possible CKD-mineral and bone disorder requires assessment before an automatic alternative is selected.
Predict one fact before revealing it.
Why must prevention planning remain active?
The low-trauma vertebral fracture warrants active prevention planning.
How does the measured creatinine clearance affect alendronate?
The alendronate label does not recommend use below 35 mL/min creatinine clearance.
What unresolved renal issue changes alternative selection?
Possible CKD-mineral and bone disorder requires assessment before an automatic alternative is selected.
Possible CKD-mineral and bone disorder requires assessment before an automatic alternative is selected.[1][2][8][10][17]
Read all reasoning steps
Why must prevention planning remain active?
The low-trauma vertebral fracture warrants active prevention planning.
How does the measured creatinine clearance affect alendronate?
The alendronate label does not recommend use below 35 mL/min creatinine clearance.
What unresolved renal issue changes alternative selection?
Possible CKD-mineral and bone disorder requires assessment before an automatic alternative is selected.
B. Start standard oral alendronate now and use the next DXA to decide whether renal evaluation is necessary (Why this does not fit)
Read the explanation or work through it
Alendronate has evidence supporting fracture prevention in glucocorticoid-treated adults. The creatinine clearance is below the label's recommended-use boundary. A later DXA response does not substitute for the renal assessment needed before treatment selection.
Predict one fact before revealing it.
Why is alendronate normally considered?
Alendronate has evidence supporting fracture prevention in glucocorticoid-treated adults.
Which patient-specific fact limits routine initiation?
The creatinine clearance is below the label's recommended-use boundary.
Why does waiting for DXA not solve that problem?
A later DXA response does not substitute for the renal assessment needed before treatment selection.
A later DXA response does not substitute for the renal assessment needed before treatment selection.[1][2][8][10][17]
Read all reasoning steps
Why is alendronate normally considered?
Alendronate has evidence supporting fracture prevention in glucocorticoid-treated adults.
Which patient-specific fact limits routine initiation?
The creatinine clearance is below the label's recommended-use boundary.
Why does waiting for DXA not solve that problem?
A later DXA response does not substitute for the renal assessment needed before treatment selection.
C. Use intravenous zoledronic acid now because avoiding the gastrointestinal route resolves the limitation (Why this does not fit)
Read the explanation or work through it
Intravenous administration avoids esophageal exposure. Zoledronic acid is contraindicated when creatinine clearance is below 35 mL/min. Changing the route does not eliminate this patient's renal limitation.
Zoledronic acid is contraindicated when creatinine clearance is below 35 mL/min.
Why is route substitution insufficient?
Changing the route does not eliminate this patient's renal limitation.
D. Begin denosumab now because the absence of renal dose adjustment resolves the main safety concern (Why this does not fit)
Read the explanation or work through it
Denosumab does not require renal dose adjustment. Advanced CKD nevertheless increases the risk of severe denosumab-associated hypocalcemia. The unresolved CKD-mineral and bone disorder assessment remains necessary before such substitution.
Predict one fact before revealing it.
Why can denosumab initially seem attractive in renal impairment?
Denosumab does not require renal dose adjustment.
What serious risk survives that pharmacokinetic advantage?
Advanced CKD nevertheless increases the risk of severe denosumab-associated hypocalcemia.
What must be assessed before proceeding?
The unresolved CKD-mineral and bone disorder assessment remains necessary before such substitution.
The unresolved CKD-mineral and bone disorder assessment remains necessary before such substitution.[1][2][8][10][17]
Read all reasoning steps
Why can denosumab initially seem attractive in renal impairment?
Denosumab does not require renal dose adjustment.
What serious risk survives that pharmacokinetic advantage?
Advanced CKD nevertheless increases the risk of severe denosumab-associated hypocalcemia.
What must be assessed before proceeding?
The unresolved CKD-mineral and bone disorder assessment remains necessary before such substitution.
E. Provide nutritional support and postpone medication assessment until a further fracture demonstrates treatment need (Why this does not fit)
Read the explanation or work through it
Kidney disease makes bone-drug selection more complex. The existing low-trauma vertebral fracture already establishes substantial clinical concern. Renal complexity calls for tailored assessment rather than waiting for another fracture.
Predict one fact before revealing it.
Why might a clinician hesitate about drug selection?
Kidney disease makes bone-drug selection more complex.
What evidence of fragility is already present?
The existing low-trauma vertebral fracture already establishes substantial clinical concern.
What should replace postponement?
Renal complexity calls for tailored assessment rather than waiting for another fracture.
Renal complexity calls for tailored assessment rather than waiting for another fracture.[1][2][8][10][17]
Read all reasoning steps
Why might a clinician hesitate about drug selection?
Kidney disease makes bone-drug selection more complex.
What evidence of fragility is already present?
The existing low-trauma vertebral fracture already establishes substantial clinical concern.
What should replace postponement?
Renal complexity calls for tailored assessment rather than waiting for another fracture.
Takeaway: Renal impairment changes treatment selection without making a fragility fracture unimportant.
A. Solution carryover is supported; average resorption per viable-cell-hour is half the control value (Why this does not fit)
Read the explanation or work through it
The final wash fluid tests for transferable inhibitory activity remaining in solution. The final wash produces no inhibition, favoring retained mineral-associated activity over active solution carryover. The normalized rates of 1 versus 2 square micrometers per viable-cell-hour correctly indicate a halved agent rate.
Predict one fact before revealing it.
Which control tests whether active solution carryover explains inhibition?
The final wash fluid tests for transferable inhibitory activity remaining in solution.
Does the final wash support that carryover explanation?
The final wash produces no inhibition, favoring retained mineral-associated activity over active solution carryover.
Which quantitative part of the option remains correct?
The normalized rates of 1 versus 2 square micrometers per viable-cell-hour correctly indicate a halved agent rate.
Use a carryover control to localize a retained effect, and normalize cumulative output to viable-cell exposure before comparing cellular activity.[4][8][10]
Read all reasoning steps
Which control tests whether active solution carryover explains inhibition?
The final wash fluid tests for transferable inhibitory activity remaining in solution.
Does the final wash support that carryover explanation?
The final wash produces no inhibition, favoring retained mineral-associated activity over active solution carryover.
Which quantitative part of the option remains correct?
The normalized rates of 1 versus 2 square micrometers per viable-cell-hour correctly indicate a halved agent rate.
B. Mineral-associated inhibition is supported; average resorption per viable-cell-hour is half the control value (Best answer)
Read the explanation or work through it
The inactive final wash supports a retained mineral-associated effect rather than active-agent carryover in the surrounding solution. Control and agent rates are 2 and 1 square micrometers per viable-cell-hour, respectively. The normalized agent rate is half the control rate, consistent with lower average activity per viable cell in this assay.
Predict one fact before revealing it.
What does the inactive final wash add to persistent inhibition on pretreated dentin?
The inactive final wash supports a retained mineral-associated effect rather than active-agent carryover in the surrounding solution.
What normalized rates follow from the measured areas and viable-cell-hours?
Control and agent rates are 2 and 1 square micrometers per viable-cell-hour, respectively.
How does the agent rate compare with the control rate?
The normalized agent rate is half the control rate, consistent with lower average activity per viable cell in this assay.
Use a carryover control to localize a retained effect, and normalize cumulative output to viable-cell exposure before comparing cellular activity.[4][8][10]
Read all reasoning steps
What does the inactive final wash add to persistent inhibition on pretreated dentin?
The inactive final wash supports a retained mineral-associated effect rather than active-agent carryover in the surrounding solution.
What normalized rates follow from the measured areas and viable-cell-hours?
Control and agent rates are 2 and 1 square micrometers per viable-cell-hour, respectively.
How does the agent rate compare with the control rate?
The normalized agent rate is half the control rate, consistent with lower average activity per viable cell in this assay.
C. Mineral-associated inhibition is supported; average resorption per viable-cell-hour is unchanged (Why this does not fit)
Read the explanation or work through it
Inhibition retained on dentin despite an inactive final wash supports mineral-associated activity. Normalization yields 1 square micrometer per viable-cell-hour with agent versus 2 with vehicle. The normalized agent rate remains lower, so the smaller area cannot be attributed solely to less viable-cell exposure.
Predict one fact before revealing it.
What location of inhibitory activity fits the wash comparison?
Inhibition retained on dentin despite an inactive final wash supports mineral-associated activity.
Do the differing viable-cell-hours fully account for the area difference?
Normalization yields 1 square micrometer per viable-cell-hour with agent versus 2 with vehicle.
Why is unchanged activity unsupported?
The normalized agent rate remains lower, so the smaller area cannot be attributed solely to less viable-cell exposure.
Use a carryover control to localize a retained effect, and normalize cumulative output to viable-cell exposure before comparing cellular activity.[4][8][10]
Read all reasoning steps
What location of inhibitory activity fits the wash comparison?
Inhibition retained on dentin despite an inactive final wash supports mineral-associated activity.
Do the differing viable-cell-hours fully account for the area difference?
Normalization yields 1 square micrometer per viable-cell-hour with agent versus 2 with vehicle.
Why is unchanged activity unsupported?
The normalized agent rate remains lower, so the smaller area cannot be attributed solely to less viable-cell exposure.
D. Solution carryover is supported; average resorption per viable-cell-hour is unchanged (Why this does not fit)
Read the explanation or work through it
The final wash has no transferable inhibitory effect in the matched control assay. The agent culture resorbs half as much area per viable-cell-hour as the vehicle culture. The proposed solution location and unchanged normalized activity both conflict with their respective assay results.
Predict one fact before revealing it.
What argues against an inhibitory solution carried through the wash?
The final wash has no transferable inhibitory effect in the matched control assay.
What does normalization show about average cellular activity?
The agent culture resorbs half as much area per viable-cell-hour as the vehicle culture.
Why does this paired interpretation fail?
The proposed solution location and unchanged normalized activity both conflict with their respective assay results.
Use a carryover control to localize a retained effect, and normalize cumulative output to viable-cell exposure before comparing cellular activity.[4][8][10]
Read all reasoning steps
What argues against an inhibitory solution carried through the wash?
The final wash has no transferable inhibitory effect in the matched control assay.
What does normalization show about average cellular activity?
The agent culture resorbs half as much area per viable-cell-hour as the vehicle culture.
Why does this paired interpretation fail?
The proposed solution location and unchanged normalized activity both conflict with their respective assay results.
E. The wash comparison cannot localize activity; average resorption per viable-cell-hour is doubled (Why this does not fit)
Read the explanation or work through it
The inactive final wash distinguishes retained mineral-associated inhibition from active solution carryover in the tested system. The agent rate of 1 square micrometer per viable-cell-hour is the numerator over the control rate of 2. The agent-to-control ratio is 0.5 rather than 2, so the doubling claim reverses the comparison.
Predict one fact before revealing it.
Does the final-wash control add information about retained activity?
The inactive final wash distinguishes retained mineral-associated inhibition from active solution carryover in the tested system.
Which rate belongs in the numerator of the agent-to-control ratio?
The agent rate of 1 square micrometer per viable-cell-hour is the numerator over the control rate of 2.
What follows from that ratio?
The agent-to-control ratio is 0.5 rather than 2, so the doubling claim reverses the comparison.
Use a carryover control to localize a retained effect, and normalize cumulative output to viable-cell exposure before comparing cellular activity.[4][8][10]
Read all reasoning steps
Does the final-wash control add information about retained activity?
The inactive final wash distinguishes retained mineral-associated inhibition from active solution carryover in the tested system.
Which rate belongs in the numerator of the agent-to-control ratio?
The agent rate of 1 square micrometer per viable-cell-hour is the numerator over the control rate of 2.
What follows from that ratio?
The agent-to-control ratio is 0.5 rather than 2, so the doubling claim reverses the comparison.
Takeaway: Use a carryover control to localize a retained effect, and normalize cumulative output to viable-cell exposure before comparing cellular activity.
A. Consider teriparatide; avoid oral alendronate (Why this does not fit)
Read the explanation or work through it
Avoiding oral alendronate respects the documented esophageal emptying abnormality. The dosimetry confirms prior external-beam irradiation involving bone. Ability to self-inject does not remove the skeletal-radiation avoidance precaution.
Predict one fact before revealing it.
Which part correctly applies the swallow study?
Avoiding oral alendronate respects the documented esophageal emptying abnormality.
What independent history weighs against teriparatide?
The dosimetry confirms prior external-beam irradiation involving bone.
Why does injection feasibility not settle teriparatide selection?
Ability to self-inject does not remove the skeletal-radiation avoidance precaution.
Assess each candidate against its own precautions; independent restrictions can exclude two routes without excluding all bone-directed treatment.[1][8][9][18]
Read all reasoning steps
Which part correctly applies the swallow study?
Avoiding oral alendronate respects the documented esophageal emptying abnormality.
What independent history weighs against teriparatide?
The dosimetry confirms prior external-beam irradiation involving bone.
Why does injection feasibility not settle teriparatide selection?
Ability to self-inject does not remove the skeletal-radiation avoidance precaution.
B. Avoid teriparatide; consider oral alendronate (Why this does not fit)
Read the explanation or work through it
Teriparatide is subject to the avoidance precaution for prior skeletal irradiation. Preserved upright ability does not resolve the separate esophageal emptying disorder. Persistent tablet retention contraindicates oral alendronate despite the acceptable renal and calcium findings.
Predict one fact before revealing it.
Which candidate is limited by the radiation history?
Teriparatide is subject to the avoidance precaution for prior skeletal irradiation.
Does preserved ability to remain upright establish oral alendronate suitability?
Preserved upright ability does not resolve the separate esophageal emptying disorder.
Why must the oral treatment proposal change?
Persistent tablet retention contraindicates oral alendronate despite the acceptable renal and calcium findings.
Assess each candidate against its own precautions; independent restrictions can exclude two routes without excluding all bone-directed treatment.[1][8][9][18]
Read all reasoning steps
Which candidate is limited by the radiation history?
Teriparatide is subject to the avoidance precaution for prior skeletal irradiation.
Does preserved ability to remain upright establish oral alendronate suitability?
Preserved upright ability does not resolve the separate esophageal emptying disorder.
Why must the oral treatment proposal change?
Persistent tablet retention contraindicates oral alendronate despite the acceptable renal and calcium findings.
C. Consider teriparatide; consider oral alendronate (Why this does not fit)
Read the explanation or work through it
The documented skeletal irradiation weighs against teriparatide under its label precaution. The delayed esophageal emptying contraindicates oral alendronate. Normal mineral status and acceptable clearance do not cancel either of the independently documented restrictions.
Predict one fact before revealing it.
What does the radiation field require in teriparatide selection?
The documented skeletal irradiation weighs against teriparatide under its label precaution.
What does the swallow study require in oral alendronate selection?
The delayed esophageal emptying contraindicates oral alendronate.
Why do reassuring renal and calcium values not make both drugs suitable?
Normal mineral status and acceptable clearance do not cancel either of the independently documented restrictions.
Assess each candidate against its own precautions; independent restrictions can exclude two routes without excluding all bone-directed treatment.[1][8][9][18]
Read all reasoning steps
What does the radiation field require in teriparatide selection?
The documented skeletal irradiation weighs against teriparatide under its label precaution.
What does the swallow study require in oral alendronate selection?
The delayed esophageal emptying contraindicates oral alendronate.
Why do reassuring renal and calcium values not make both drugs suitable?
Normal mineral status and acceptable clearance do not cancel either of the independently documented restrictions.
D. Defer teriparatide for hypocalcemia; defer oral alendronate for renal impairment (Why this does not fit)
Read the explanation or work through it
Serum calcium is normal, so hypocalcemia is not the demonstrated treatment issue. Creatinine clearance of 62 mL/min is above the alendronate label boundary of 35 mL/min. Skeletal irradiation and delayed esophageal emptying are the documented drug-selection constraints.
Predict one fact before revealing it.
Is hypocalcemia the supplied reason to defer teriparatide?
Serum calcium is normal, so hypocalcemia is not the demonstrated treatment issue.
Does the stated clearance fall below the alendronate recommended-use boundary?
Creatinine clearance of 62 mL/min is above the alendronate label boundary of 35 mL/min.
Which histories actually constrain these candidates?
Skeletal irradiation and delayed esophageal emptying are the documented drug-selection constraints.
Assess each candidate against its own precautions; independent restrictions can exclude two routes without excluding all bone-directed treatment.[1][8][9][18]
Read all reasoning steps
Is hypocalcemia the supplied reason to defer teriparatide?
Serum calcium is normal, so hypocalcemia is not the demonstrated treatment issue.
Does the stated clearance fall below the alendronate recommended-use boundary?
Creatinine clearance of 62 mL/min is above the alendronate label boundary of 35 mL/min.
Which histories actually constrain these candidates?
Skeletal irradiation and delayed esophageal emptying are the documented drug-selection constraints.
E. Avoid teriparatide; avoid oral alendronate (Best answer)
Read the explanation or work through it
External-beam exposure involving the iliac bones meets the teriparatide skeletal-radiation avoidance precaution. The documented delay in esophageal emptying contraindicates oral alendronate. The fracture-prevention discussion should assess other suitable regimens rather than conclude that all bone-directed therapy is excluded.
Predict one fact before revealing it.
How does the recorded radiation field affect teriparatide suitability?
External-beam exposure involving the iliac bones meets the teriparatide skeletal-radiation avoidance precaution.
What does persistent tablet retention imply for oral alendronate?
The documented delay in esophageal emptying contraindicates oral alendronate.
What should follow exclusion of these two candidates?
The fracture-prevention discussion should assess other suitable regimens rather than conclude that all bone-directed therapy is excluded.
Assess each candidate against its own precautions; independent restrictions can exclude two routes without excluding all bone-directed treatment.[1][8][9][18]
Read all reasoning steps
How does the recorded radiation field affect teriparatide suitability?
External-beam exposure involving the iliac bones meets the teriparatide skeletal-radiation avoidance precaution.
What does persistent tablet retention imply for oral alendronate?
The documented delay in esophageal emptying contraindicates oral alendronate.
What should follow exclusion of these two candidates?
The fracture-prevention discussion should assess other suitable regimens rather than conclude that all bone-directed therapy is excluded.
Takeaway: Assess each candidate against its own precautions; independent restrictions can exclude two routes without excluding all bone-directed treatment.
A. Osteonecrosis is favored; subchondral fracture is present without demonstrated collapse (Best answer)
Read the explanation or work through it
The described smooth concave band favors osteonecrosis over the competing insufficiency-fracture pattern. The CT fracture line establishes subchondral fracture without measurable contour depression. The fracture finding does not by itself establish collapse of the femoral head.
Predict one fact before revealing it.
Which lesion is favored by the stated MRI morphology?
The described smooth concave band favors osteonecrosis over the competing insufficiency-fracture pattern.
What structural stage does the CT establish?
The CT fracture line establishes subchondral fracture without measurable contour depression.
Why must fracture and collapse remain distinct?
The fracture finding does not by itself establish collapse of the femoral head.
The fracture finding does not by itself establish collapse of the femoral head.[11][15][21]
Read all reasoning steps
Which lesion is favored by the stated MRI morphology?
The described smooth concave band favors osteonecrosis over the competing insufficiency-fracture pattern.
What structural stage does the CT establish?
The CT fracture line establishes subchondral fracture without measurable contour depression.
Why must fracture and collapse remain distinct?
The fracture finding does not by itself establish collapse of the femoral head.
B. Osteonecrosis is favored; a subchondral fracture establishes that collapse has already occurred (Why this does not fit)
Read the explanation or work through it
The described MRI morphology favors osteonecrosis. A subchondral fracture can precede appreciable loss of femoral-head contour. The preserved CT contour therefore does not support a claim of established collapse.
Predict one fact before revealing it.
Which part fits the MRI description?
The described MRI morphology favors osteonecrosis.
Can fracture precede collapse?
A subchondral fracture can precede appreciable loss of femoral-head contour.
Which finding limits the stage claim?
The preserved CT contour therefore does not support a claim of established collapse.
The preserved CT contour therefore does not support a claim of established collapse.[11][15][21]
Read all reasoning steps
Which part fits the MRI description?
The described MRI morphology favors osteonecrosis.
Can fracture precede collapse?
A subchondral fracture can precede appreciable loss of femoral-head contour.
Which finding limits the stage claim?
The preserved CT contour therefore does not support a claim of established collapse.
C. Primary subchondral insufficiency fracture is favored; collapse has not been demonstrated (Why this does not fit)
Read the explanation or work through it
Primary insufficiency fracture can cause focal hip pain without a very low T-score. The smooth concave band favors a necrotic segment over the irregular insufficiency pattern in this comparison. The preserved contour addresses collapse but does not reverse the lesion-pattern interpretation.
Predict one fact before revealing it.
Why is insufficiency fracture a plausible differential?
Primary insufficiency fracture can cause focal hip pain without a very low T-score.
Which morphology favors the competing lesion?
The smooth concave band favors a necrotic segment over the irregular insufficiency pattern in this comparison.
Why does the contour finding not settle etiology?
The preserved contour addresses collapse but does not reverse the lesion-pattern interpretation.
The preserved contour addresses collapse but does not reverse the lesion-pattern interpretation.[11][15][21]
Read all reasoning steps
Why is insufficiency fracture a plausible differential?
Primary insufficiency fracture can cause focal hip pain without a very low T-score.
Which morphology favors the competing lesion?
The smooth concave band favors a necrotic segment over the irregular insufficiency pattern in this comparison.
Why does the contour finding not settle etiology?
The preserved contour addresses collapse but does not reverse the lesion-pattern interpretation.
D. Primary subchondral insufficiency fracture is favored; collapse is already established (Why this does not fit)
Read the explanation or work through it
Insufficiency fracture and osteonecrosis can both involve subchondral bone. The supplied morphology favors osteonecrosis in this comparison. The lack of contour depression also prevents calling collapse established.
Predict one fact before revealing it.
What makes the two lesions clinically confusable?
Insufficiency fracture and osteonecrosis can both involve subchondral bone.
Which lesion does the morphology favor?
The supplied morphology favors osteonecrosis in this comparison.
Which stage claim is additionally unsupported?
The lack of contour depression also prevents calling collapse established.
The lack of contour depression also prevents calling collapse established.[11][15][21]
Read all reasoning steps
What makes the two lesions clinically confusable?
Insufficiency fracture and osteonecrosis can both involve subchondral bone.
Which lesion does the morphology favor?
The supplied morphology favors osteonecrosis in this comparison.
Which stage claim is additionally unsupported?
The lack of contour depression also prevents calling collapse established.
E. Generalized low bone density explains the focal lesion; collapse is not demonstrated (Why this does not fit)
Read the explanation or work through it
DXA identifies reduced areal bone mineral density. A density category does not account for the described focal segment of altered viability. The focal lesion needs its own orthopedic assessment even though collapse is not demonstrated.
Predict one fact before revealing it.
What information does DXA contribute?
DXA identifies reduced areal bone mineral density.
What finding lies beyond a density classification?
A density category does not account for the described focal segment of altered viability.
What assessment remains necessary?
The focal lesion needs its own orthopedic assessment even though collapse is not demonstrated.
The focal lesion needs its own orthopedic assessment even though collapse is not demonstrated.[11][15][21]
Read all reasoning steps
What information does DXA contribute?
DXA identifies reduced areal bone mineral density.
What finding lies beyond a density classification?
A density category does not account for the described focal segment of altered viability.
What assessment remains necessary?
The focal lesion needs its own orthopedic assessment even though collapse is not demonstrated.
Takeaway: The pattern of the focal lesion and the presence of collapse are separate imaging questions; neither is settled by DXA.